Annual epidemiological spotlight on HIV in the South East: 2024 data
Updated 20 October 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/hiv-south-east-annual-data-spotlight/annual-epidemiological-spotlight-on-hiv-in-the-south-east-2024-data
Summary
Changes to the HIV spotlight report
During 2024 and 2025, UKHSA engaged in a stakeholders’ review on language use for HIV. Consequently, a number of changes have been made to the language used in this report. These include reference to gender identity, sexual orientation and probable route of exposure:
- for gay, bisexual and all men who have sex with men, the abbreviation is gay and bisexual men (instead of GBMSM or sex between men)
- for heterosexual men or men who acquired HIV through sex with women, we abbreviate as heterosexual men (instead of men exposed through sex with women)
- for heterosexual and bisexual women or women who acquired HIV through sex with men, we use heterosexual women (instead of women exposed through sex with men)
In previous STI Spotlights reports, counts of new HIV diagnoses included people diagnosed with HIV before continuing care in England (referred to as “previously diagnosed abroad”). These cases do not reflect HIV acquired in England and most of these individuals are rapidly linked to care shortly after arrival, making the majority extremely unlikely to pass on HIV in England (1). For this report, reflecting changes in national HIV statistics, reference to new HIV diagnoses now only includes diagnoses first made in England.
HIV in the South East
HIV remains an important public health challenge in the South East. In 2024, 13,152 people were living with diagnosed HIV in the South East. There were 376 new HIV diagnoses (first made in England) in South East residents in 2024, representing 14% of all new diagnoses in England. In the South East, there were 382 new HIV diagnoses in those diagnosed with HIV before continuing care in England in 2024, 30% lower than in 2023. 60% of new HIV diagnoses were in heterosexual men and women and 34% were in gay and bisexual men. 38% of new HIV diagnoses were in the White ethnic group and 37% in the Black African ethnic group. Between 2022 and 2024, 47% of diagnoses were defined as late. HIV testing numbers increased by 6% from 2023 to 2024, and by 36% from 2020 to 2024. This report aims to provide key intelligence about HIV in the South East. For a broader context see UKHSA’s national HIV report.
New diagnoses
In 2024, 376 South East residents were newly diagnosed with HIV, accounting for 14% of new diagnoses in England. This represents a rise of 6% from 2023.
The new diagnosis rate for South East residents (4 per 100,000) was below that of England in 2024 (5 per 100,000).
In 2024, 34% of all new diagnoses in South East residents were in gay and bisexual men (compared to 34% in 2023 and 61% in 2015). The number of gay and bisexual men resident in the South East newly diagnosed with HIV (128, adjusted for missing information) was 52% lower than in 2015. Of the gay and bisexual men newly diagnosed with HIV 65% were White and 47% were UK-born.
Heterosexual contact was the largest route of exposure for new diagnoses in South East residents in 2024 (60%). Infections in African-born persons accounted for 64% of all heterosexually acquired cases in 2024 (n=123), compared to 45% (n=65) in 2015. Infections in UK born persons accounted for 20% of all heterosexually acquired cases in 2024.
Injecting drug use accounted for 1% of new diagnoses in South East residents.
Black Africans represented 37% of all newly diagnosed South East residents in 2024 (compared to 39% in 2023 and 15% in 2015). A small proportion of new diagnoses in 2024 were in Black Caribbeans (3%).
The number of new diagnoses was highest in the 35 to 44 year age group in males and the 25 to 34 year age group in females in 2024.
Late diagnoses
Reducing late HIV diagnoses is one of the indicators in the Public Health Outcomes Framework and HIV Action Plan Monitoring and Evaluation Framework. People who are diagnosed late have a tenfold risk of dying within one year of diagnosis compared to those diagnosed promptly and late diagnoses result in increased healthcare costs.
It is of particular concern that a large proportion of South East residents with HIV are diagnosed late (47% from 2022 to 2024, compared to 43% in England), defined by a CD4 count of less than 350 cells/mm at diagnosis.
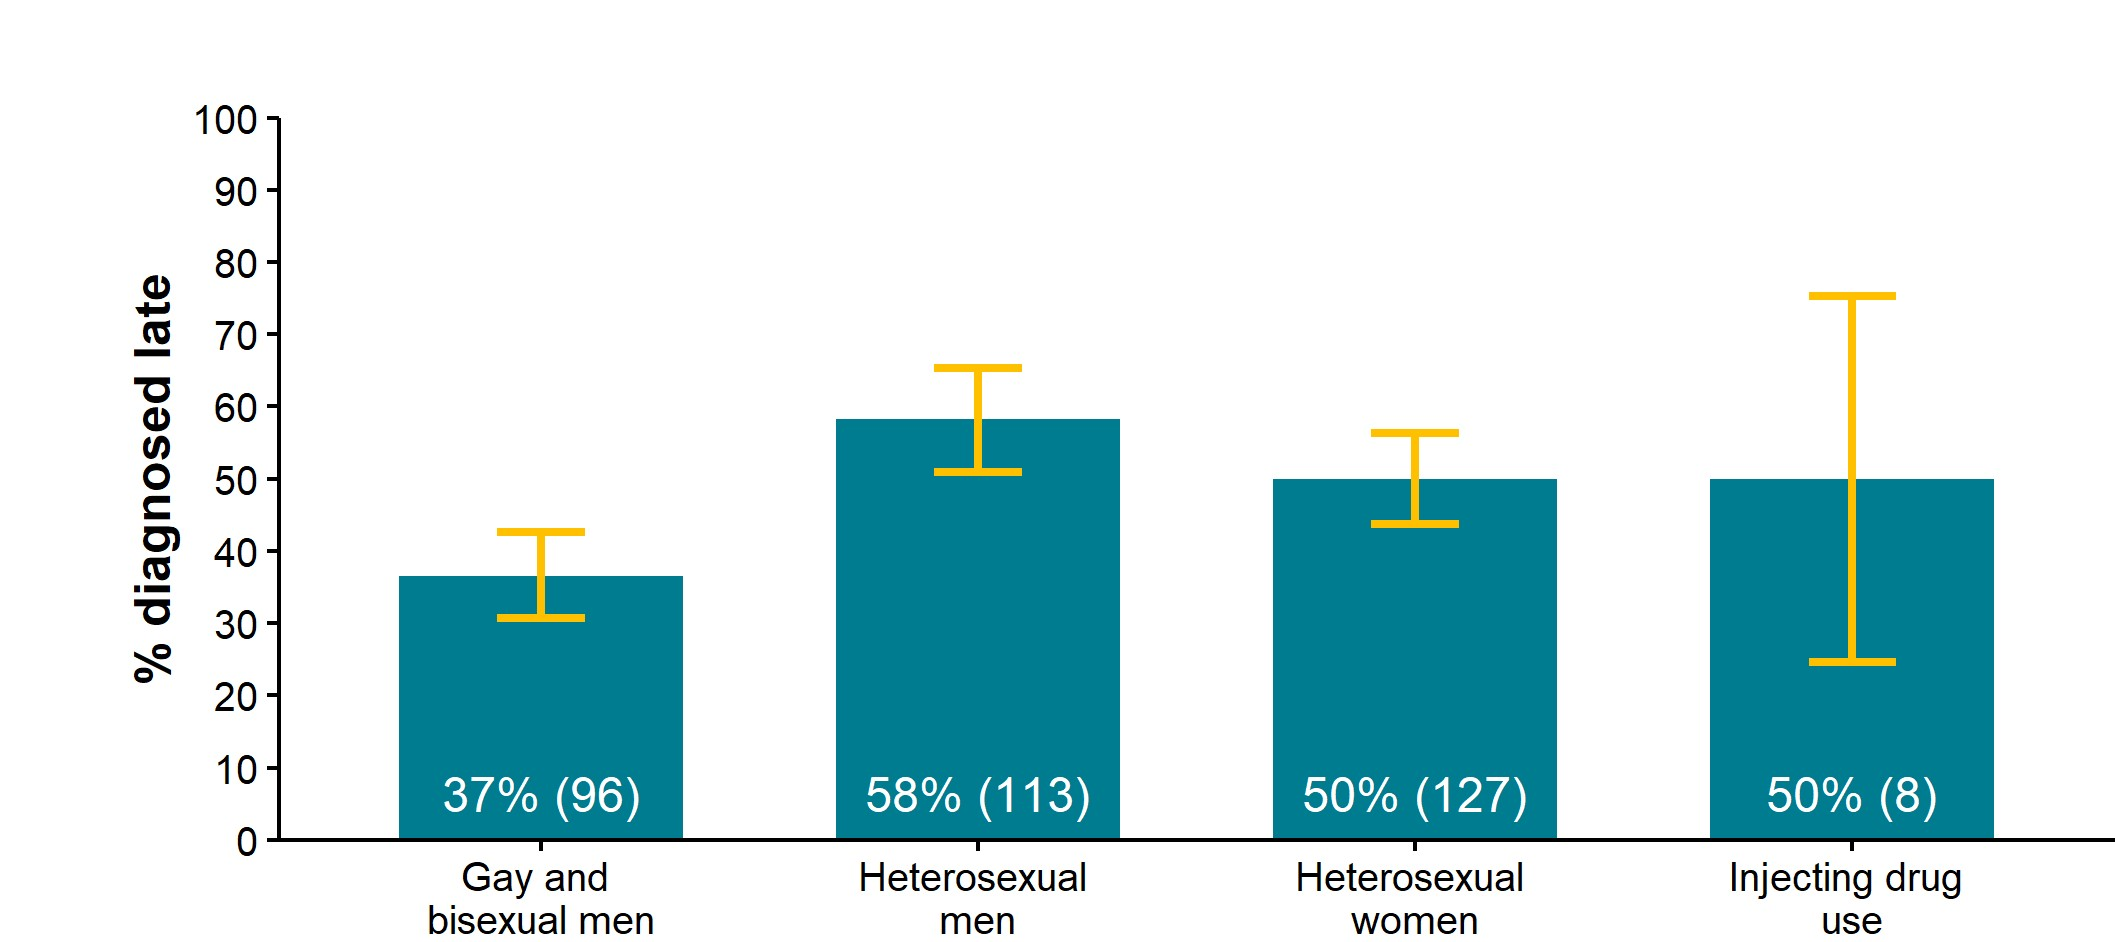
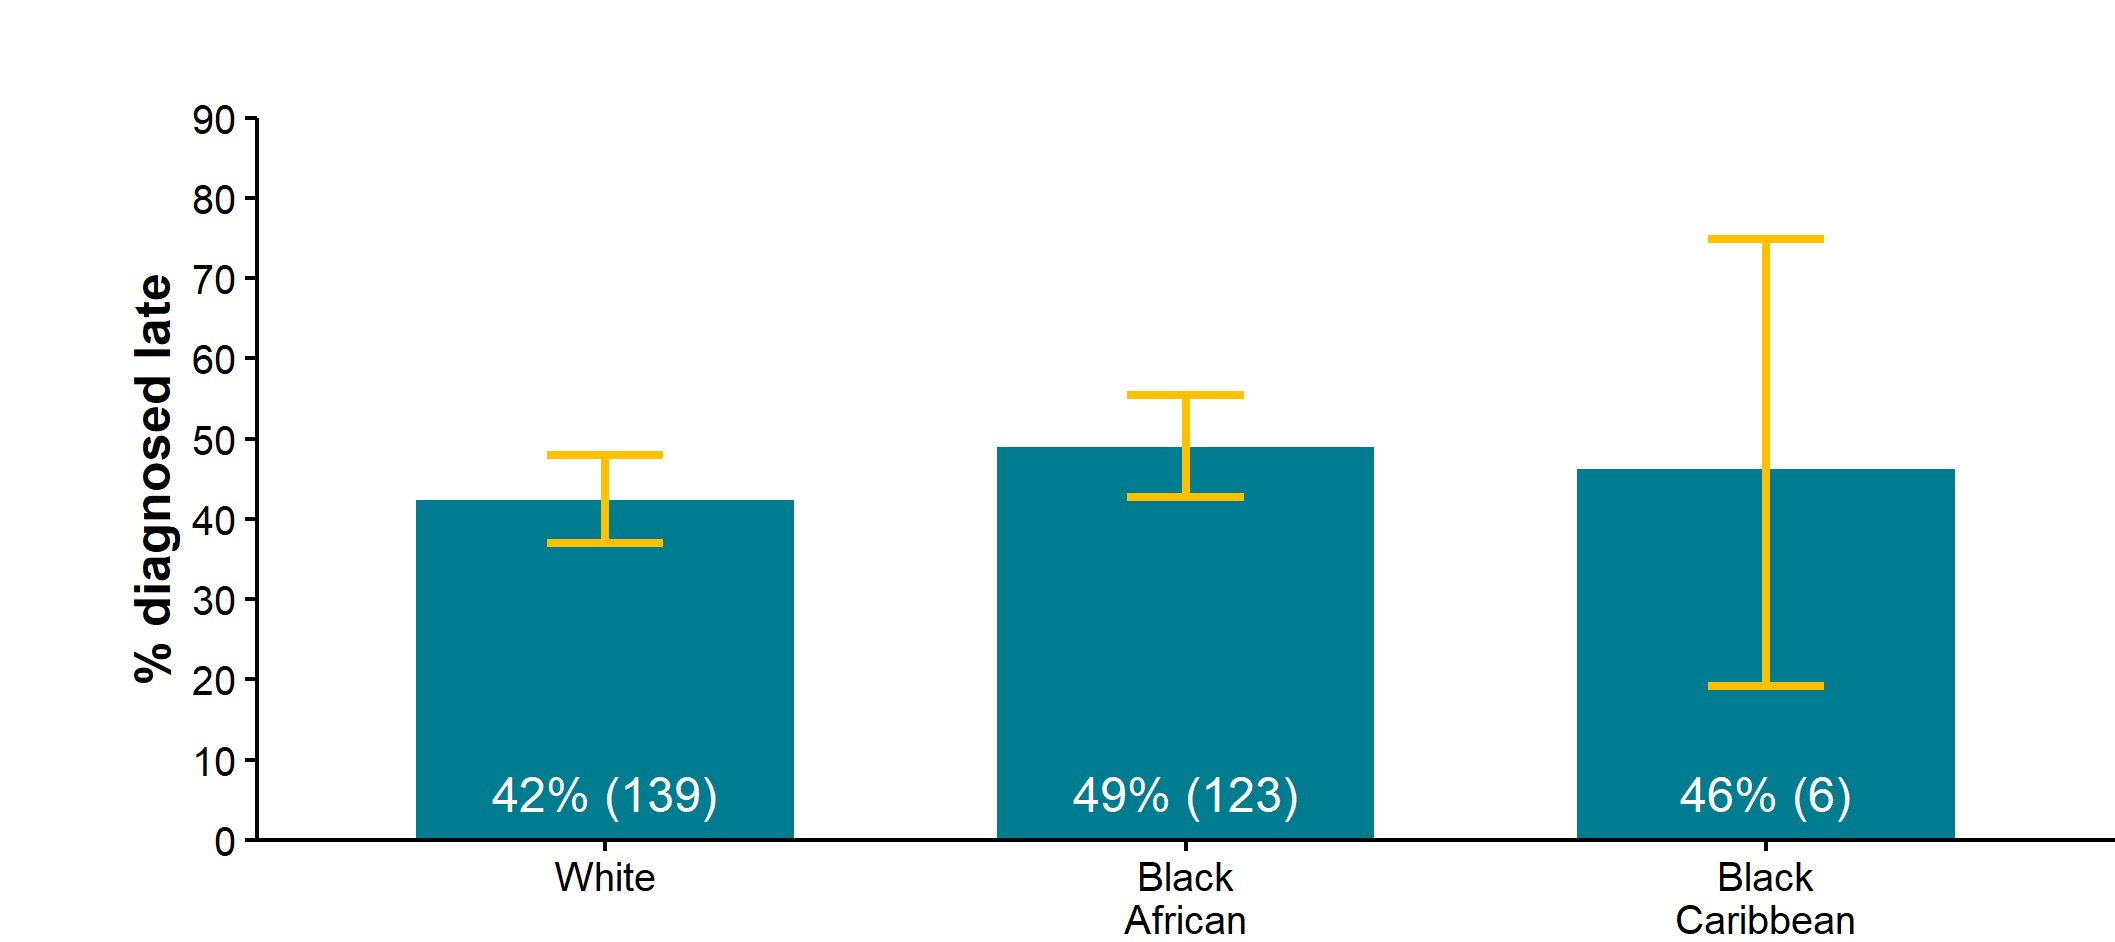
In the South East, heterosexuals were more likely to be diagnosed late (58% of males, 50% of females) than gay and bisexual men (37%). By ethnic group, Black Africans were more likely to be diagnosed late than the White population (49% and 42% respectively).
People living with diagnosed HIV
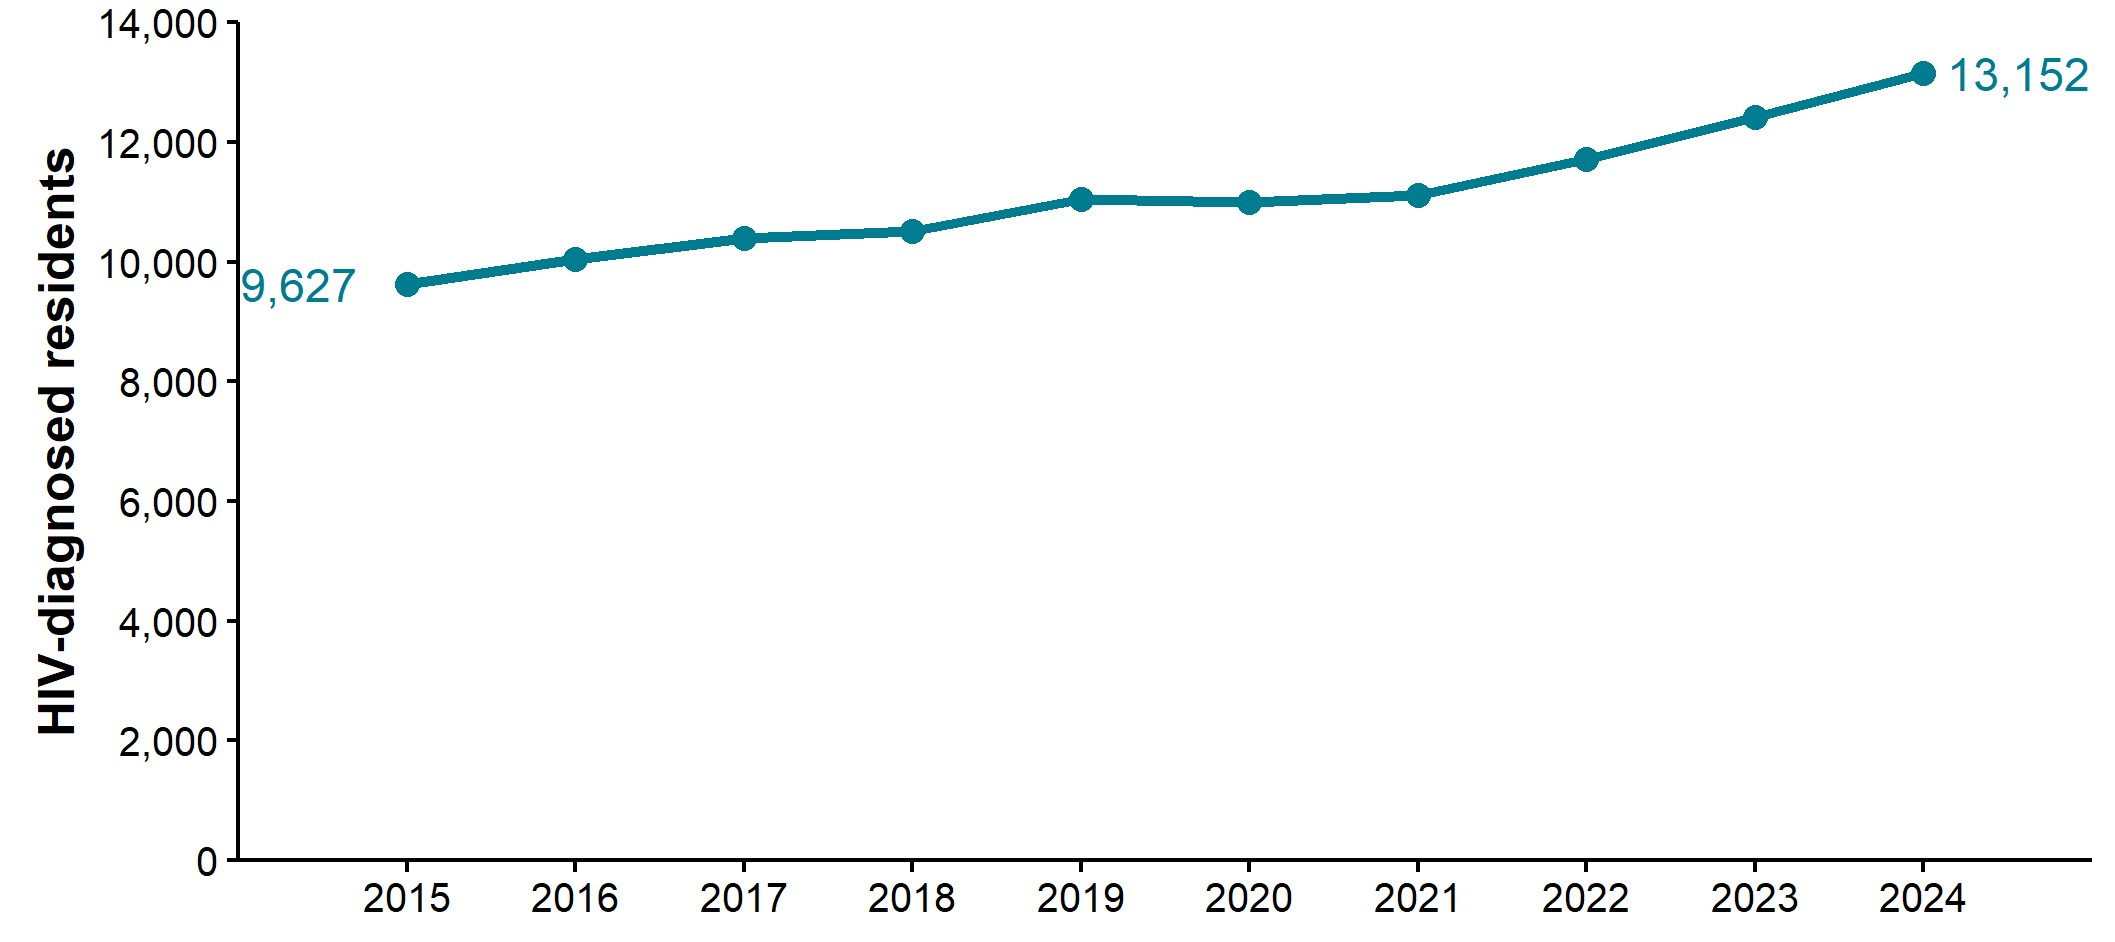
The 13,152 people living with diagnosed HIV in the South East in 2024 was 6% higher than in 2023 and 37% higher than in 2015. This increase is partly due to the effectiveness of HIV treatment, which has reduced the number of deaths from HIV.
The diagnosed prevalence rate of HIV in the South East in 2024 was 2 per 1,000 residents aged 15 to 59 years. This was equal to that observed in England as a whole. Eight local authorities in the South East had a diagnosed HIV prevalence in excess of 2 per 1,000 population aged 15-59 in 2024, which is the threshold for expanded HIV testing. They were Brighton and Hove (6.5), East Sussex (2.0), Medway (2.2), Portsmouth (2.7), Reading (3.1), Slough (3), Southampton (3) and West Sussex (2.0).
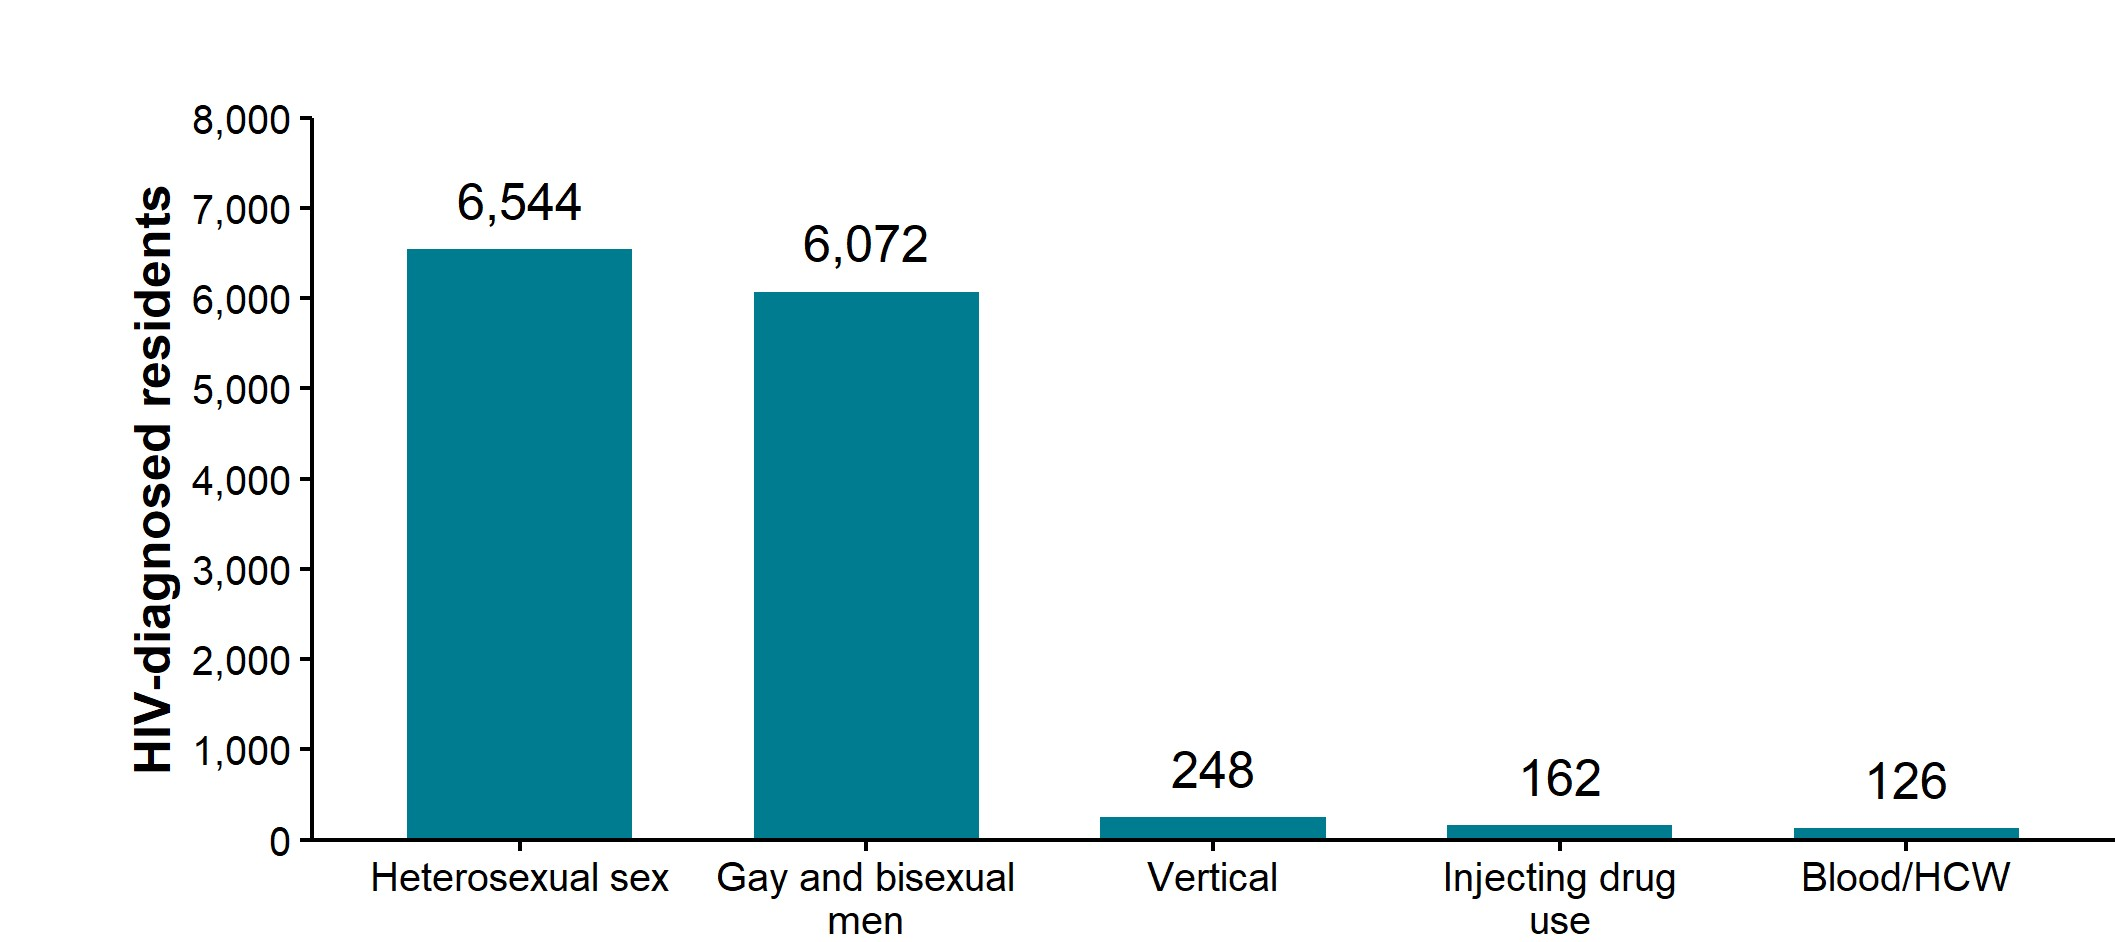
The 2 most common probable exposure routes for South East residents living with diagnosed HIV in 2024 were heterosexual sex (50%) and sex between men (46%).
In 2024, 36% of those living with diagnosed HIV in the South East were aged between 35 and 49 years, and 54% were aged 50 years and over (up from 35% in 2015). Males represented 66% of South East residents living with diagnosed HIV in 2024 and females represented 34%.
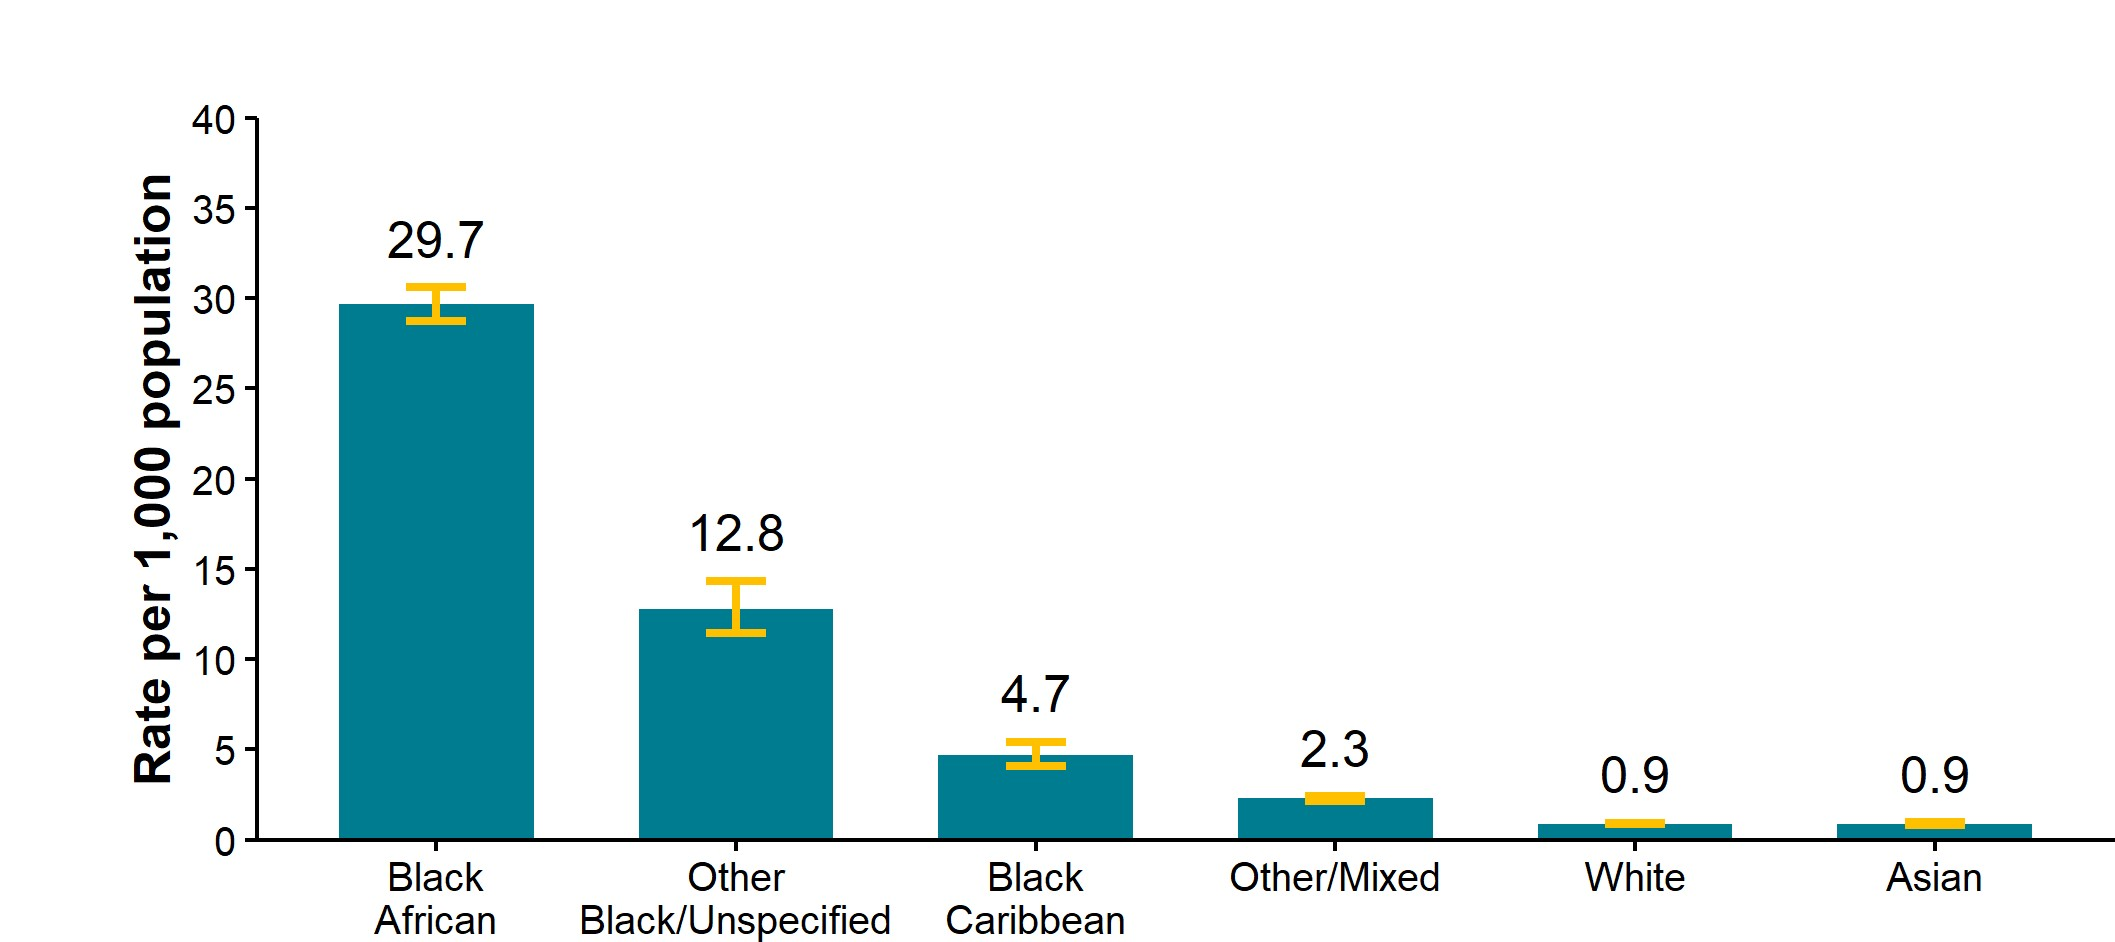
In 2024, 56% of South East residents living with diagnosed HIV were White and 30% were Black Africans. However, due to the relative sizes of the White and Black African populations the rate per 1,000 population aged 15 to 59 years was much higher in Black Africans (30 per 1,000) than in the White population (1 per 1,000).
HIV testing
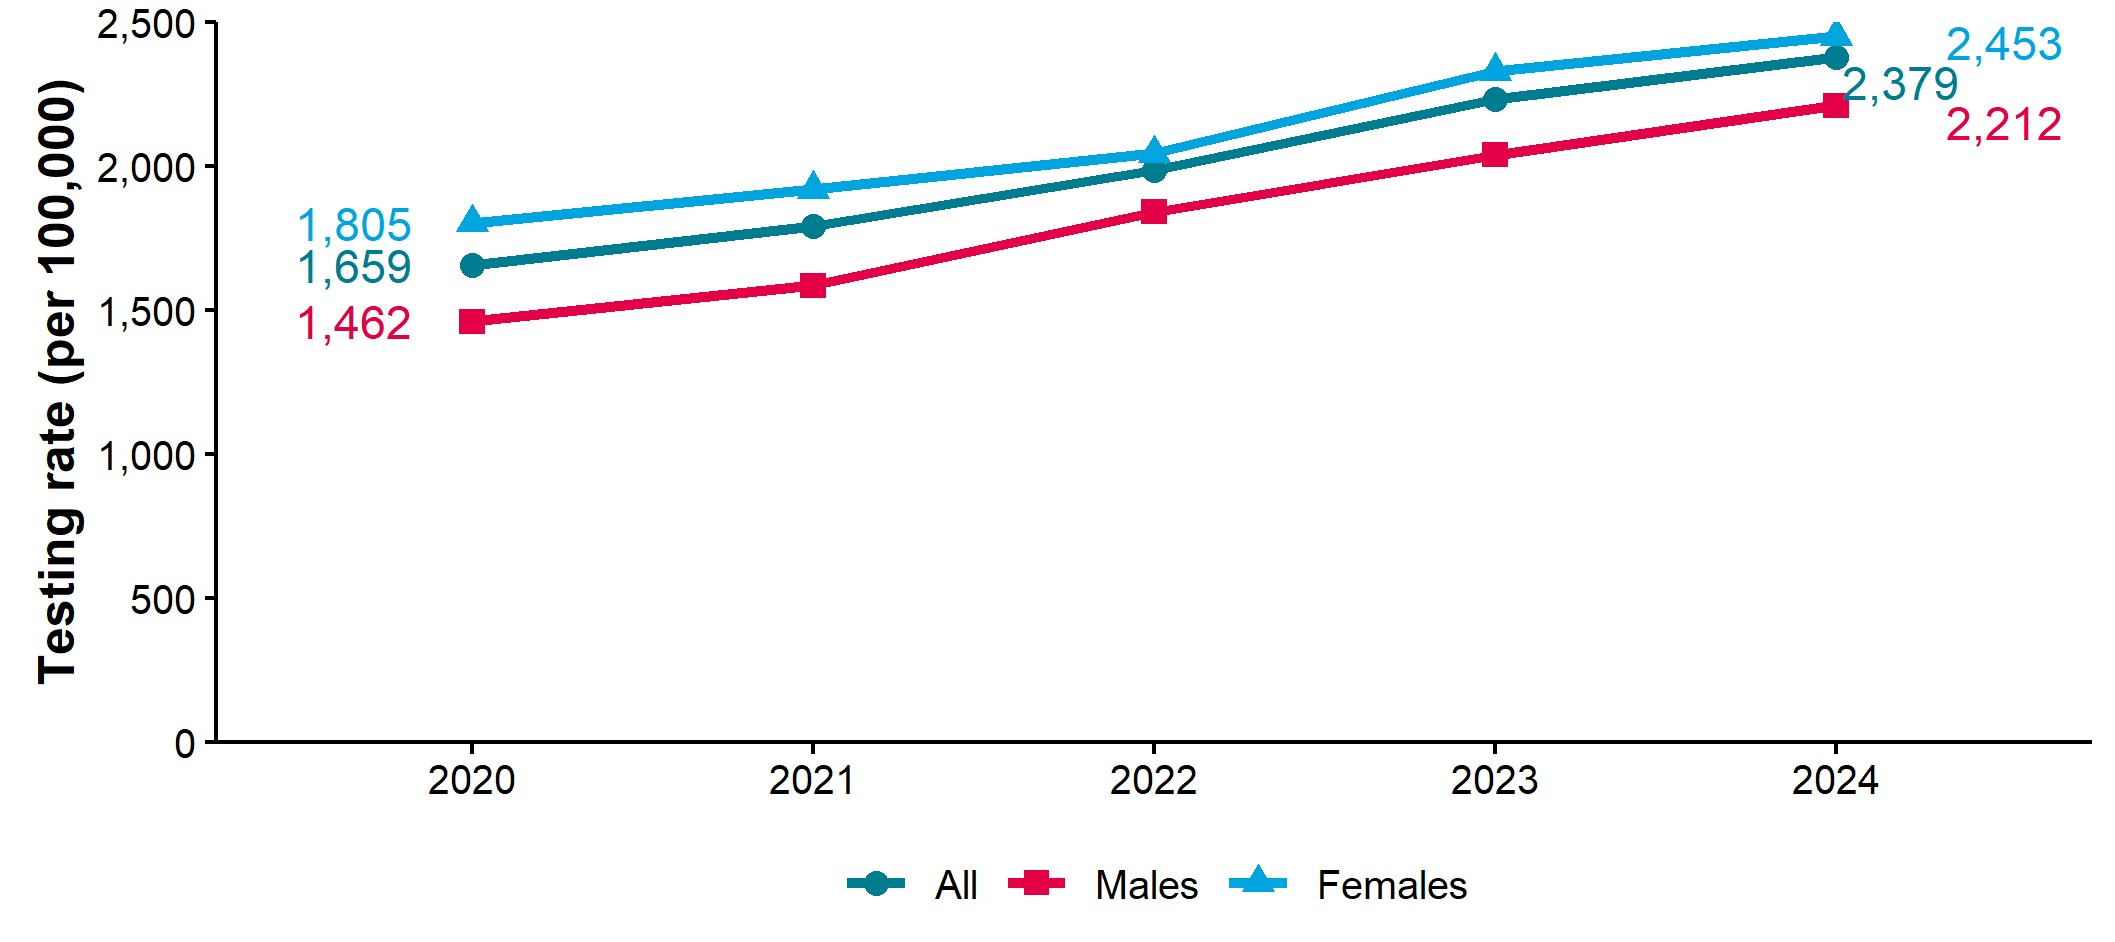
A total of 106,169 people were tested in specialist sexual health services (SHSs) in the South East in 2024, an increase of 72% since 2020 and an increase of 14% since 2023. The HIV testing rate (per 100,000 population) at all SHSs in the South East was 2,379, which compares to 2,843 across England. HIV testing rates in all SHSs (specialist and non-specialist sexual health services) in the South East is lower in men (2,212) than women (2,453).
PrEP
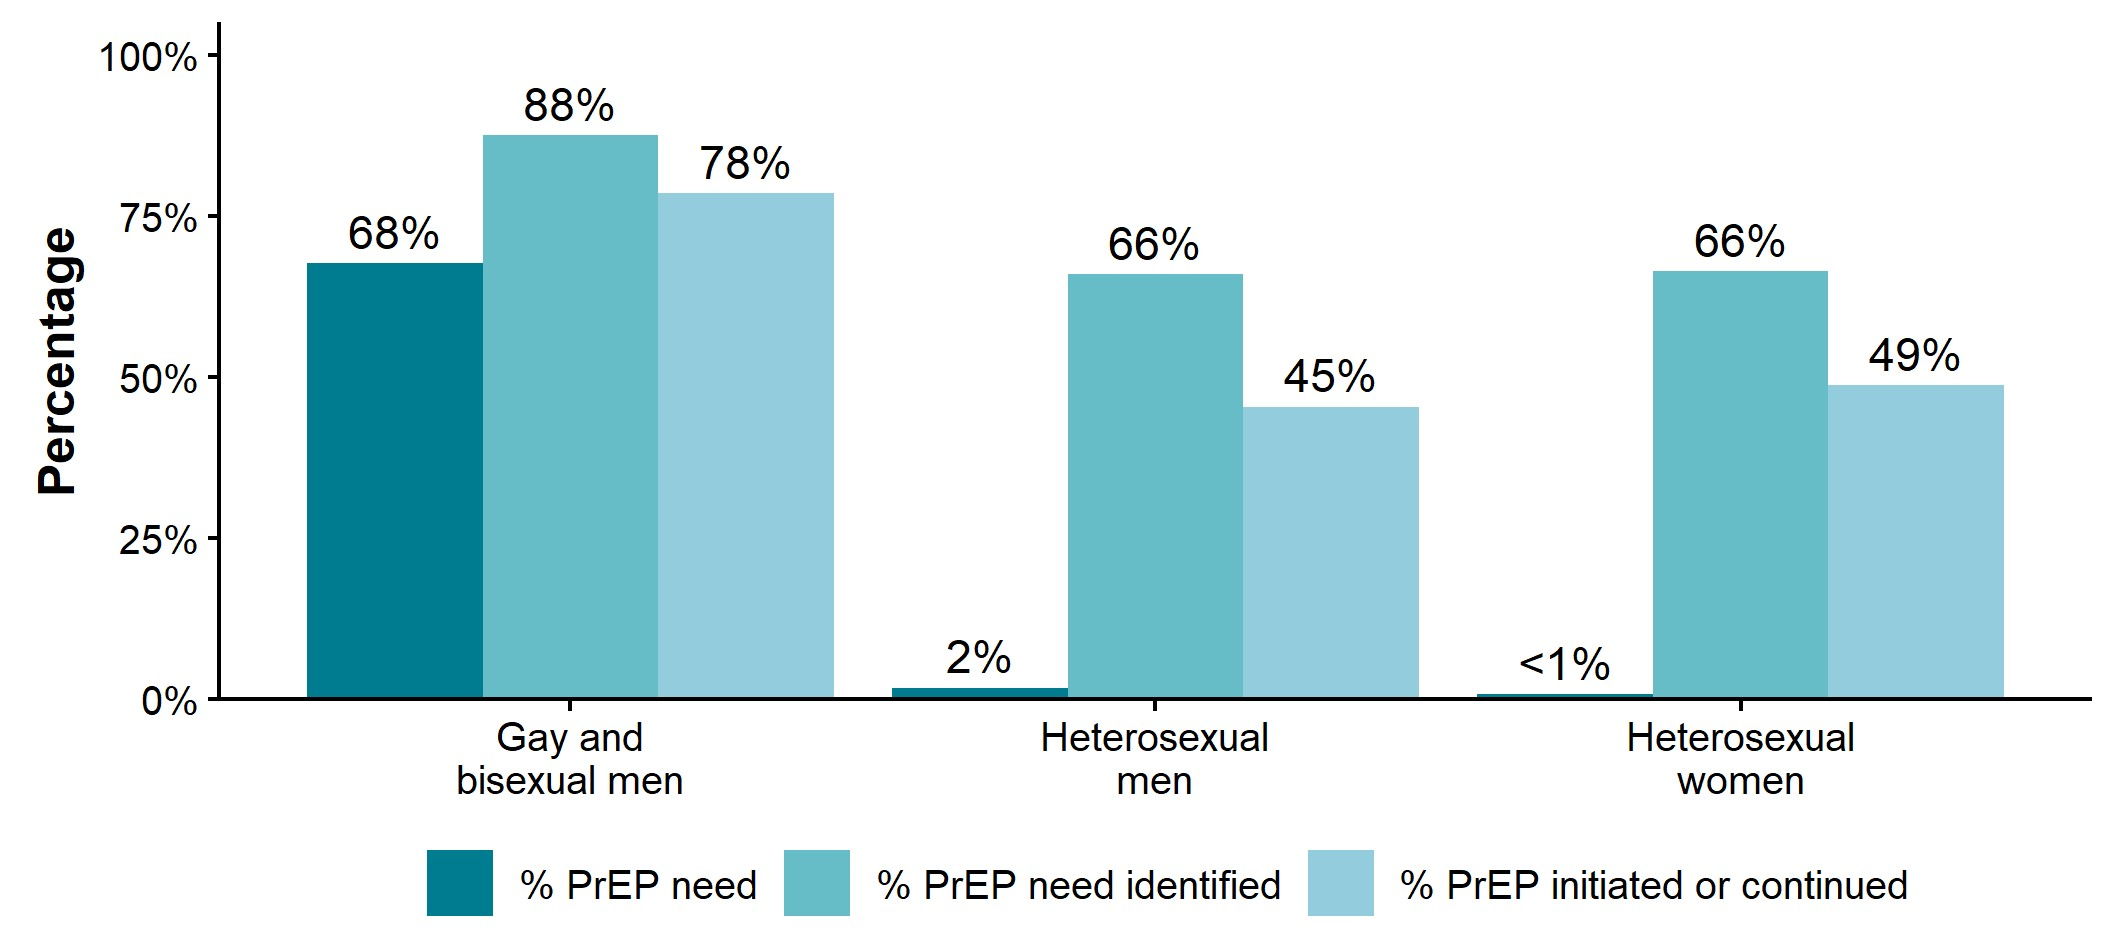
In 2024, 9% of HIV-negative South East residents accessing SHSs in England were defined as having a pre-exposure prophylaxis (PrEP) need, among whom 75% initiated or continued PrEP. Of those with PrEP need, 86% had this need identified at a clinical consultation. Among gay and bisexual men, the group with greatest need, these proportions were: 68% need, 78% initiated/continued and 88% identified at consultation. Consistent use of PrEP is an effective intervention to prevent HIV acquisition. Despite PrEP being routinely available through specialist SHS, awareness, accessibility and uptake of primary prevention initiatives is variable for different population groups. Addressing this disparity is key to HIV prevention. PrEP need is defined and measured differently in different key population groups (see the Appendix section of the HIV pre-exposure prophylaxis (PrEP): monitoring and evaluation).
HIV in England
The HIV Action Plan for England, 2025 to 2030 was published on 1 December 2025. It sets UNAIDS 2025 ambitions to reduce HIV transmission (measured by new HIV diagnoses) and AIDS-related deaths by 90% between 2010 and 2030. New diagnoses among White gay and bisexual men are on track to reach the ambition, however further work is needed over the next 5 years for other population groups such as ethnic minority gay and bisexual men, Black African and Other ethnic minority heterosexual populations. This is why HIV Official Statistics this year highlight progress along the HIV pathway for 5 population groups.
The number of people first diagnosed with HIV in England decreased by 2% in 2024 (2,838 in 2023 to 2,773)(2). Gay and bisexual men accounted for almost 30% of new HIV diagnoses (810 of 2,773), with heterosexual men 23% (634) and heterosexual women 27% (749). Within and between these population groups, there remains evidence of considerable inequalities (2). Further provision of services that are culturally competent and accessible to diverse populations is needed.
The number of new HIV diagnoses in England decreased by 6% (859 to 810) in 2024 for gay and bisexual men (2). However, this reduction was not seen consistently among all ethnic groups. While a reduction of 6% was observed among White gay and bisexual men (488 to 461), new HIV diagnoses increased among Black (15%, 80 to 92) and Asian (6%, 101 to 107) gay and bisexual men. Nearly half (48%, 386 of 810) of the gay and bisexual men newly diagnosed in England in 2024 were born abroad.
For heterosexuals, the number of new HIV diagnoses were similar in 2024 compared to 2023 (1,371 to 1,383), although numbers increased for heterosexual men (by 3%, 615 to 634) and decreased marginally for heterosexual women (by 1%, 755 to 749)(2). As with gay and bisexual men, for heterosexuals, there was considerable variation between ethnic groups. Notably, new HIV diagnoses among Black African heterosexual men increased by 15% (231 to 265) but decreased by 5% among Black African heterosexual women (441 to 418). Of the heterosexual men newly diagnosed in 2024, 27% (170 of 634) were known to be born in the UK and 68% (431 of 634) abroad. Among women, 15% (116 of 749) were known to be born in the UK and 77% (580 of 749) abroad.
Overall, the number of people tested for HIV in sexual health services in England was 3% higher in 2024 than 2023 but has not fully recovered to pre-pandemic (2019) levels for all groups. Whereas testing increased markedly within specialist SHSs (9%), non-specialist online testing declined by 4% in 2024. The proportion of people tested through online consultations at all SHSs (compared to face-to-face) fell by 3%, continuing a year-on-year reduction in this proportion since a peak in 2021. There was a 7% decrease in the HIV testing rate in all SHSs in people aged 15 to 24 years. This compares to a continued increase in the HIV testing rate in all other age groups.
Testing increases were observed across gender and sexual orientation groups (gay and bisexual men, 2% increase; heterosexual men, 5%; heterosexual woman, 2%). Consistently increased testing for gay and bisexual men, coupled with an overall decline in HIV test positivity (0.3% in 2020 to 0.2% in 2024) suggests that there may be a reduction in transmission in this community. HIV test positivity in heterosexual men and women has remained similar in 2023 and 2024 (0.05% to 0.06%, and 0.08% to 0.08%, respectively). The programme of emergency departments (ED) opt-out testing for bloodborne viruses continues to be a successful approach for HIV diagnoses, contributing to 8% of all new HIV diagnoses in 2024.
The number of people diagnosed with HIV before continuing care in England fell markedly in 2024 (3,363 to 2,525) with a corresponding 15% drop in all HIV diagnoses (6,201 to 5,298). The reduction in the number of people diagnosed before continuing care in England was most pronounced in heterosexual women (33%), compared to reductions in heterosexual men (11%) and gay and bisexual men (21%). The decline in the number of people diagnosed before continuing care in England in 2024 varied by ethnic group. The largest proportionate reductions in numbers (compared to 2023) were seen in people of Black Other (30%; 79 to 55), Black African (28%; 2,196 to 1,587), Asian (25%; 228 to 172), Other or Mixed (25%; 288 to 216) and White (22%; 326 to 253) ethnicities.
The number of people receiving HIV pre-exposure prophylaxis via SHSs has been increasing on an annual basis since 2020, increasing by 7.7% between 2023 and 2024 (111,123 in 2024 versus 103,138 in 2023). However, inequalities in access remain. While the overall number of gay and bisexual men with unmet HIV PrEP need was highest, there is proportionally greater unidentified and unmet PrEP need among heterosexual men and women.
Despite a 2% decrease in the number of adults being diagnosed late between 2023 and 2024 (950 to 928), 42% (928 of 2,196) of the new HIV diagnoses were made at a late stage in England in 2024. Reductions in the number of late HIV diagnoses fell most among gay and bisexual men (11%) compared with heterosexual women (4%) and heterosexual men (1%). The percentage of new diagnoses that were late for all 3 groups remained similar to 2023 (45% to 46%, 53% to 52%, 31% to 30% for heterosexual women, heterosexual men, and gay and bisexual men, respectively). In 2024, half of adult Black African heterosexuals newly diagnosed with HIV were diagnosed late (285 of 572; 50%). People diagnosed late with HIV in England in 2023 were 10 times more likely to die within a year of their diagnosis, compared to those diagnosed promptly.
Provisional estimates are that 95% of all adults living with HIV in England are diagnosed, with 99% of diagnosed adults receiving treatment, and 98% of adults on treatment having suppressed viral loads.
HIV prevention messages
Combined prevention methods prevent HIV; these include HIV testing and treatment, PrEP and condom use. Using condoms consistently and correctly protects against HIV and other STIs such as chlamydia, gonorrhoea and syphilis.
HIV testing is central to HIV prevention since it provides access to PrEP and health advice for those who don’t have HIV, while an HIV result leads to essential HIV care and treatment, keeping a person healthy and preventing onward transmission. Anyone having sex without a condom with new or casual partners needs an STI screen, including an HIV test, on at least an annual basis. Gay and bisexual men should have tests for HIV and STIs annually, or every 3 months if having sex without condoms with new or casual partners.
HIV PrEP is available for free from specialist SHSs and can be used to reduce an individual’s risk of acquiring HIV. Consistent use of PrEP can be an efficacious and effective intervention to prevent HIV acquisition. Despite PrEP being routinely available through specialist SHSs, awareness, accessibility and uptake of this primary prevention initiative remain low in many population groups (3).
HIV post-exposure prophylaxis (PEP) can be used to reduce the risk of acquiring HIV following exposure. PEP is available for free from specialist SHSs and most emergency departments and is effective if taken within 72 hours.
HIV and AIDS symptoms may not appear for many years, and people who don’t know they have HIV may unintentionally pass HIV to others. Prevention messages should reinforce that anyone can acquire HIV regardless of age, gender, ethnicity, sexuality or religion, and it is important to challenge assumptions and stigma about who can acquire HIV.
People who know they are living with HIV, are on treatment and have an undetectable viral load, are unable to pass on the virus to others during sex, even without PrEP or condoms. This is known as Undetectable = Untransmittable or U=U (4).
Stigma, anxiety and depression experienced by people living with HIV may stop them seeking healthcare, engaging in treatment and remaining in care (5). Reducing stigma in healthcare services and society encourages people to get the healthcare they need.
Specialist SHS are free and confidential. They offer testing and treatment for HIV and STIs, condoms, vaccination, HIV PrEP and PEP regardless of immigration status. Both clinic-based services and online testing for HIV and STIs are widely available. Information and advice about sexual health, including how to access services, is available at NHS.UK and from the national sexual health helpline on 0300 123 7123.
Local and regional prevention strategies
HIV prevention strategies at a local and regional level should consider inclusion of all actions published recently in the HIV Action Plan for England (HIVAP). Below are some examples of how this could be done, focusing on each of the 5 HIVAP priorities:
Prevent
- Drive forward HIV service improvements and innovation with a focus on reducing inequalities in HIV testing, access to HIV PrEP and PEP
- Collate evidence and best practice of HIV PrEP provision pilot studies
- Ensure localities are aware that there is central funding for formula milk (and related sterilised equipment) for the infants of women living with HIV
Test
- Implement and monitor British HIV Association (BHIVA), British Association for Sexual Health and HIV (BASHH) and British Infection Association (BIA) Adult HIV testing guidelines 2020, including opt-out in SHSs and reduce inequalities in HIV testing
- Continue ED opt-out testing in very high and high prevalence HIV areas
- Work with GP practices to promote HIV testing into routine primary care pathways
- Scale up partner notification activities
- Understand the drivers of late diagnosis in order to better focus interventions
Treat
- Share learnings from UKHSA audits with local networks and encourage provision of peer support and psychological support within HIV treatment services
- Ensure commissioning arrangements are in place with local providers for HIV peer support provision
- Ensure local SHSs and HIV services engage with and learn from retention in care reviews to strengthen pathways
Thrive
- Ensure services provide a holistic approach to HIV care for women, signposting to other services, such as partner violence services and menopause clinics, when needed
- Improve the quality of life for people living with HIV, including promotion of U=U, particularly for older adults and people with complex health and care needs, by commissioning integrated, person-centred support services that address physical, mental and social wellbeing
Collaborate
- Share culturally competent education and awareness of new technologies as they become available to enhance national messaging
- Apply and promote the HIV Low Prevalence Toolkit to guide local planning, commissioning and evaluation and strengthen outreach, primary care partnerships and service visibility to ensure equitable access to prevention, treatment and care in low prevalence areas
Charts, tables and maps
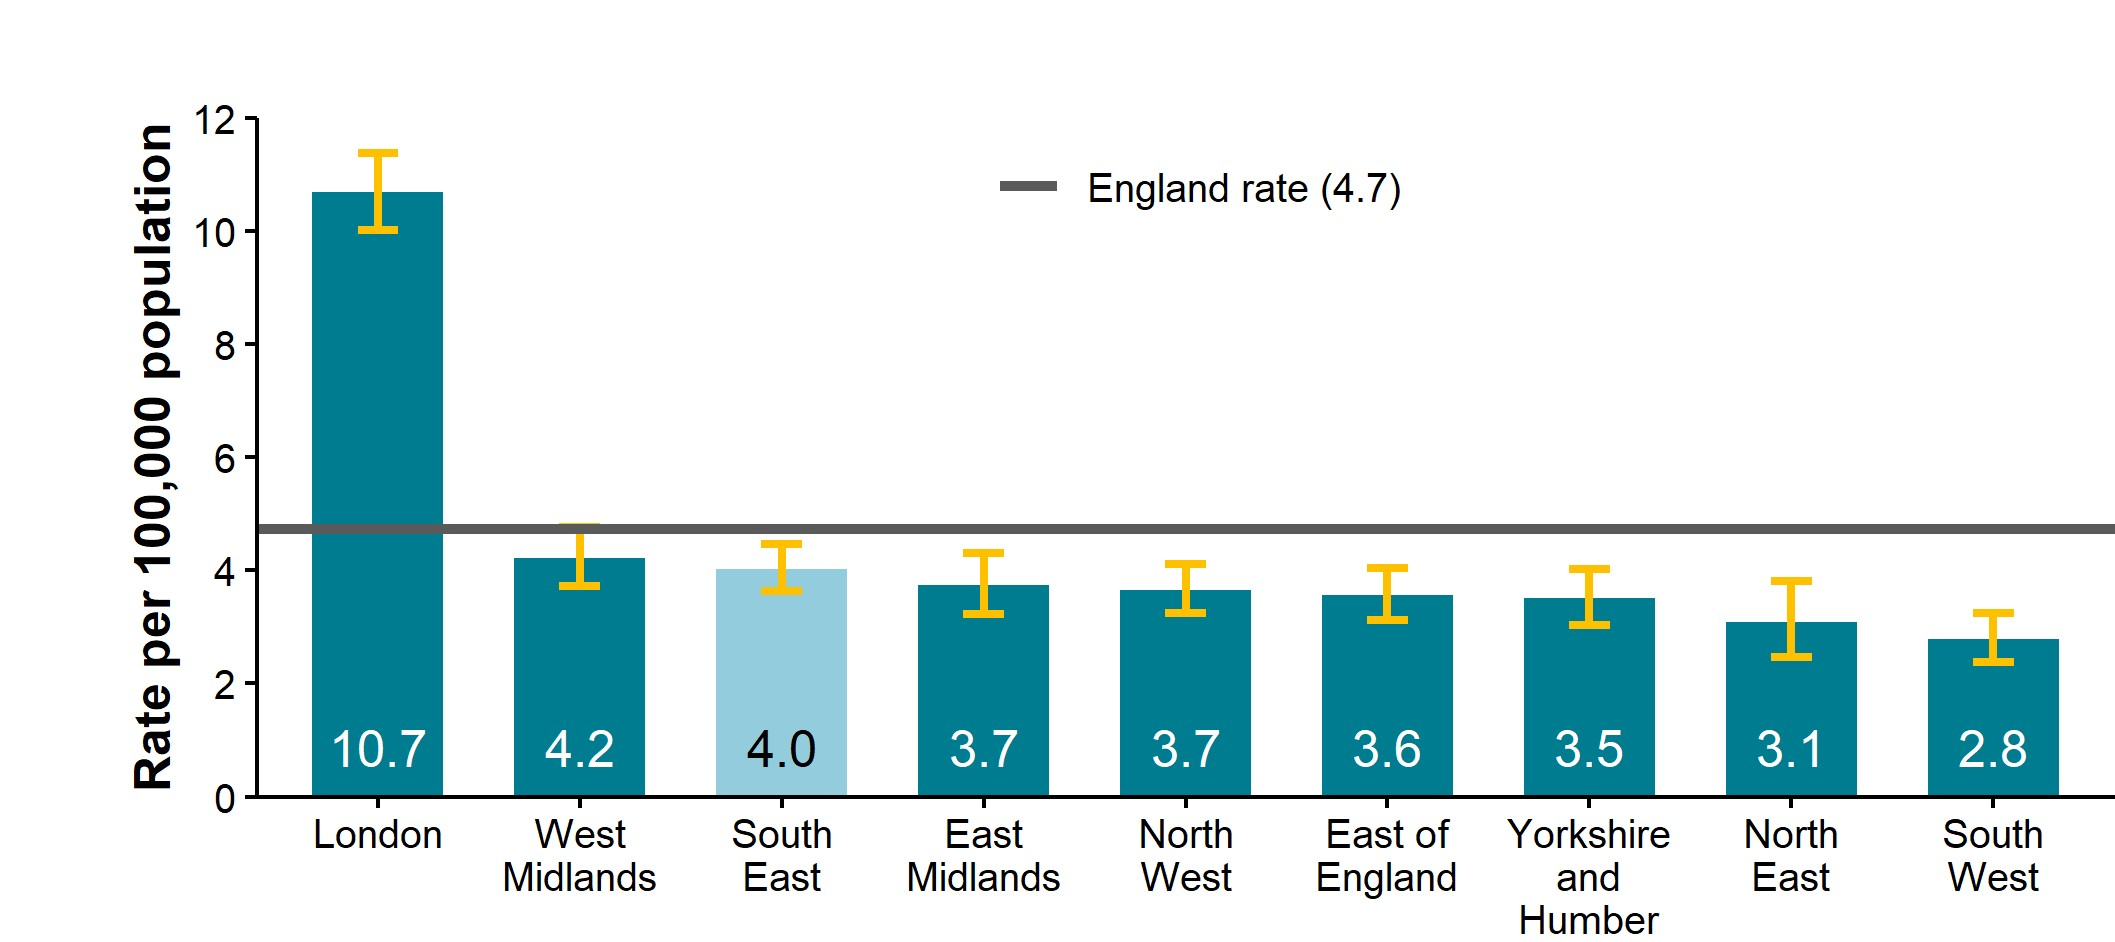
Figure 1. Rate of new HIV diagnoses per 100,000 population (all ages) by UKHSA region of residence, 2024
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Figure 1 is a column chart showing the rate of new HIV diagnoses per 100,000 population by region of residence for the year 2024. The overall England rate (4.7) is represented as a solid horizontal line.
The chart shows that the rate of new HIV diagnoses in the South East (4.0) was the third highest of the 9 regions, and below the average for England as a whole.
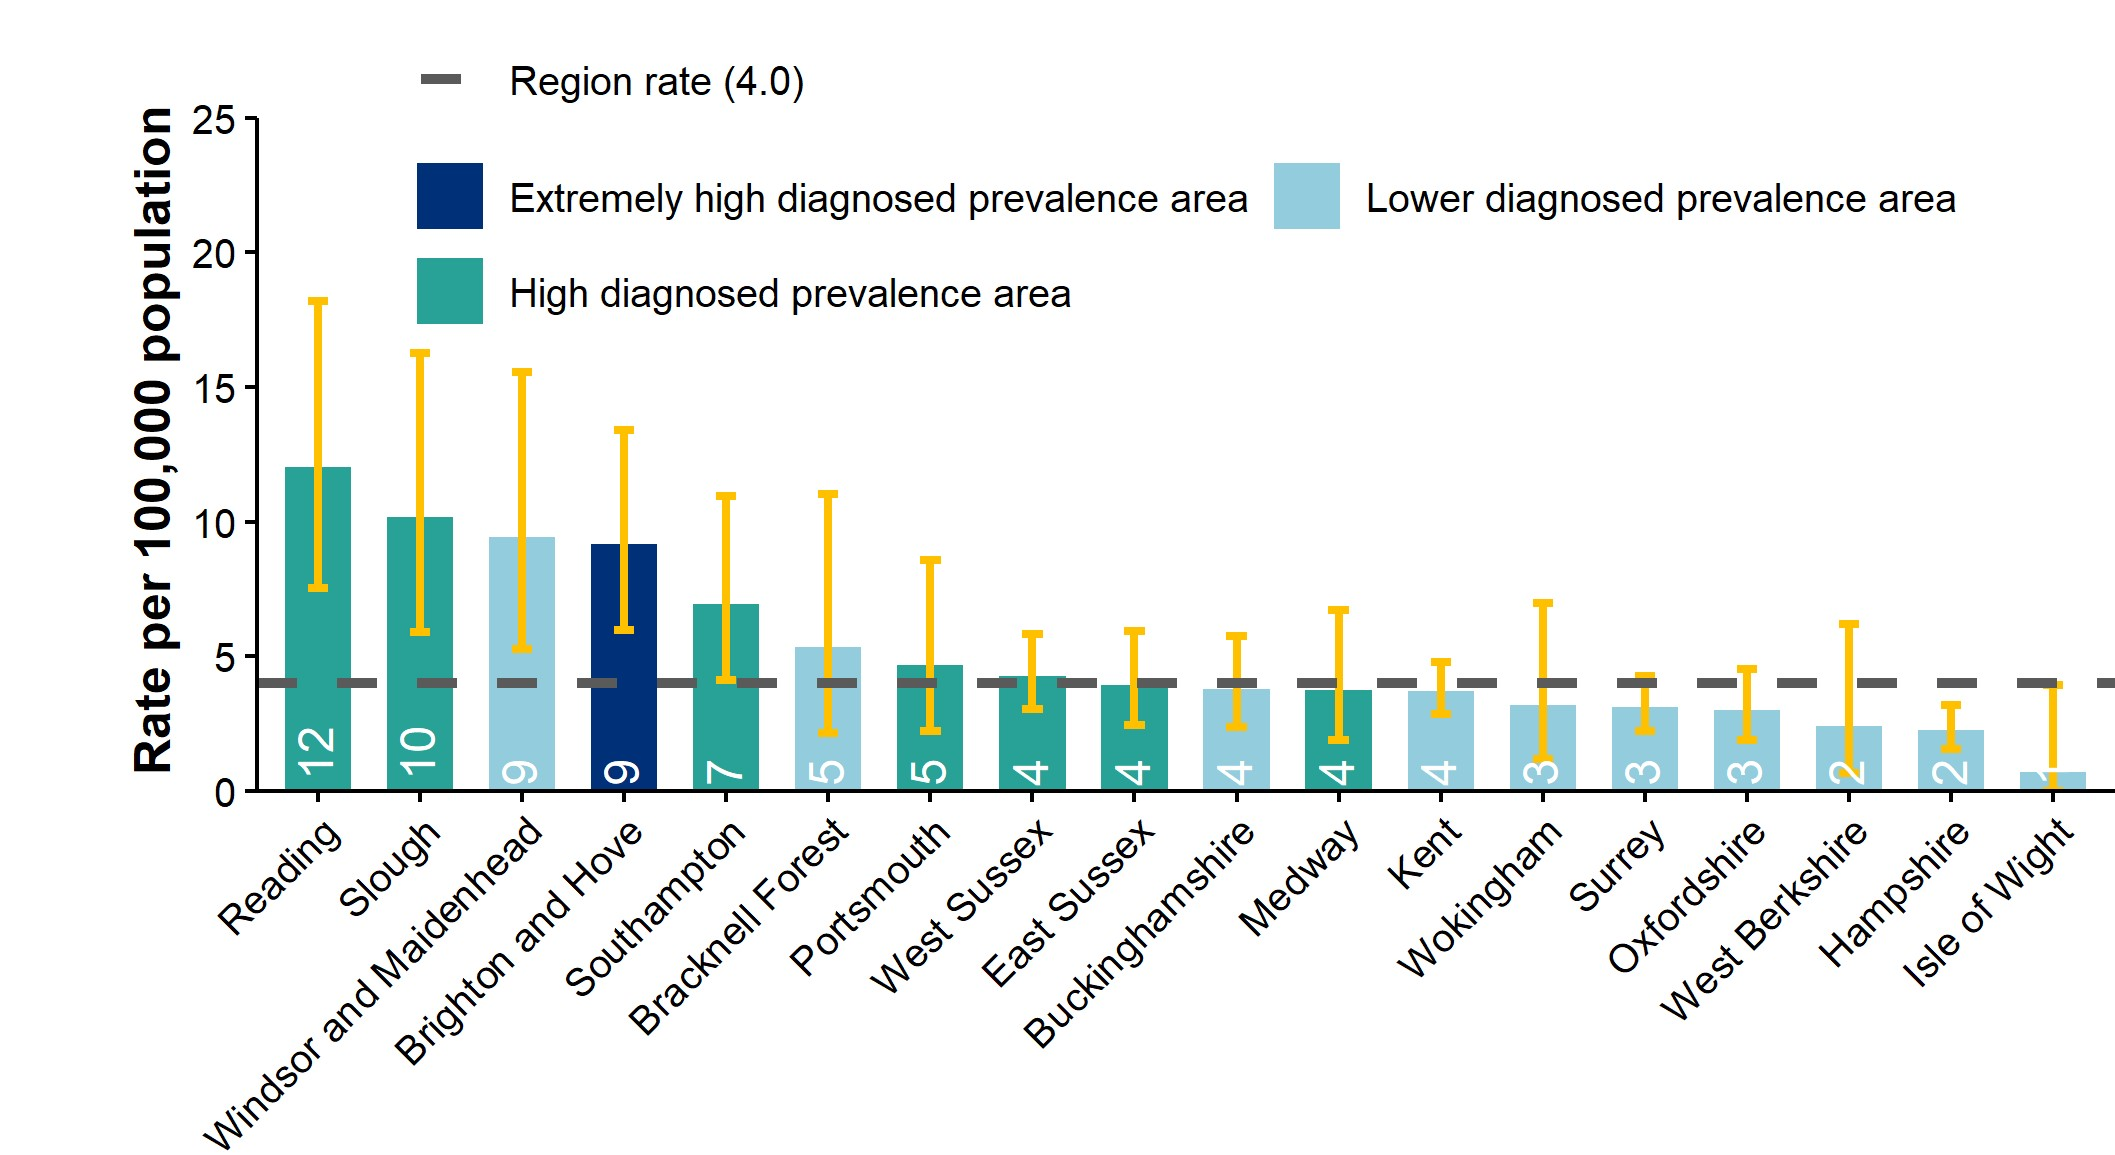
Figure 2. Rate of new HIV diagnoses per 100,000 population (all ages) by upper tier local authority of residence, South East residents, 2024
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. HIV diagnosed prevalence (rate per 1,000 aged 15 to 59 years as per NICE testing guidelines). Lower diagnosed prevalence less than 2, high diagnosed prevalence 2 to 5, Extremely high diagnosed prevalence more than 5.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Colour coding of bars does not relate to new diagnosis but to the data in the diagnosed prevalence section (see Figures 16 to 32, below).
Figure 2 is a column chart showing rates of new HIV diagnoses per 100,000 population by South East local authority of residence for the year 2024. Local authorities are shown in descending order in relation to their rate of new HIV diagnoses. The overall rate for the South East (4.0) is represented as a dashed horizontal line. The colour of the columns indicates whether the local authority is an extremely high diagnosed prevalence area (dark blue), high diagnosed prevalence area (green), or lower diagnosed prevalence area (light blue).
Reading (12), Slough (10), Windsor and Maidenhead (9), and Brighton and Hove (9) were the 4 local authorities with the highest rates of new HIV diagnoses in the South East, and with rates more than double the rate of the South East as a whole. Brighton and Hove was the only local authority in the South East classified as an extremely high diagnosed prevalence area. Reading, Slough, Southampton, Portsmouth, West Sussex, East Sussex, and Medway were all classified as high diagnosed prevalence areas.
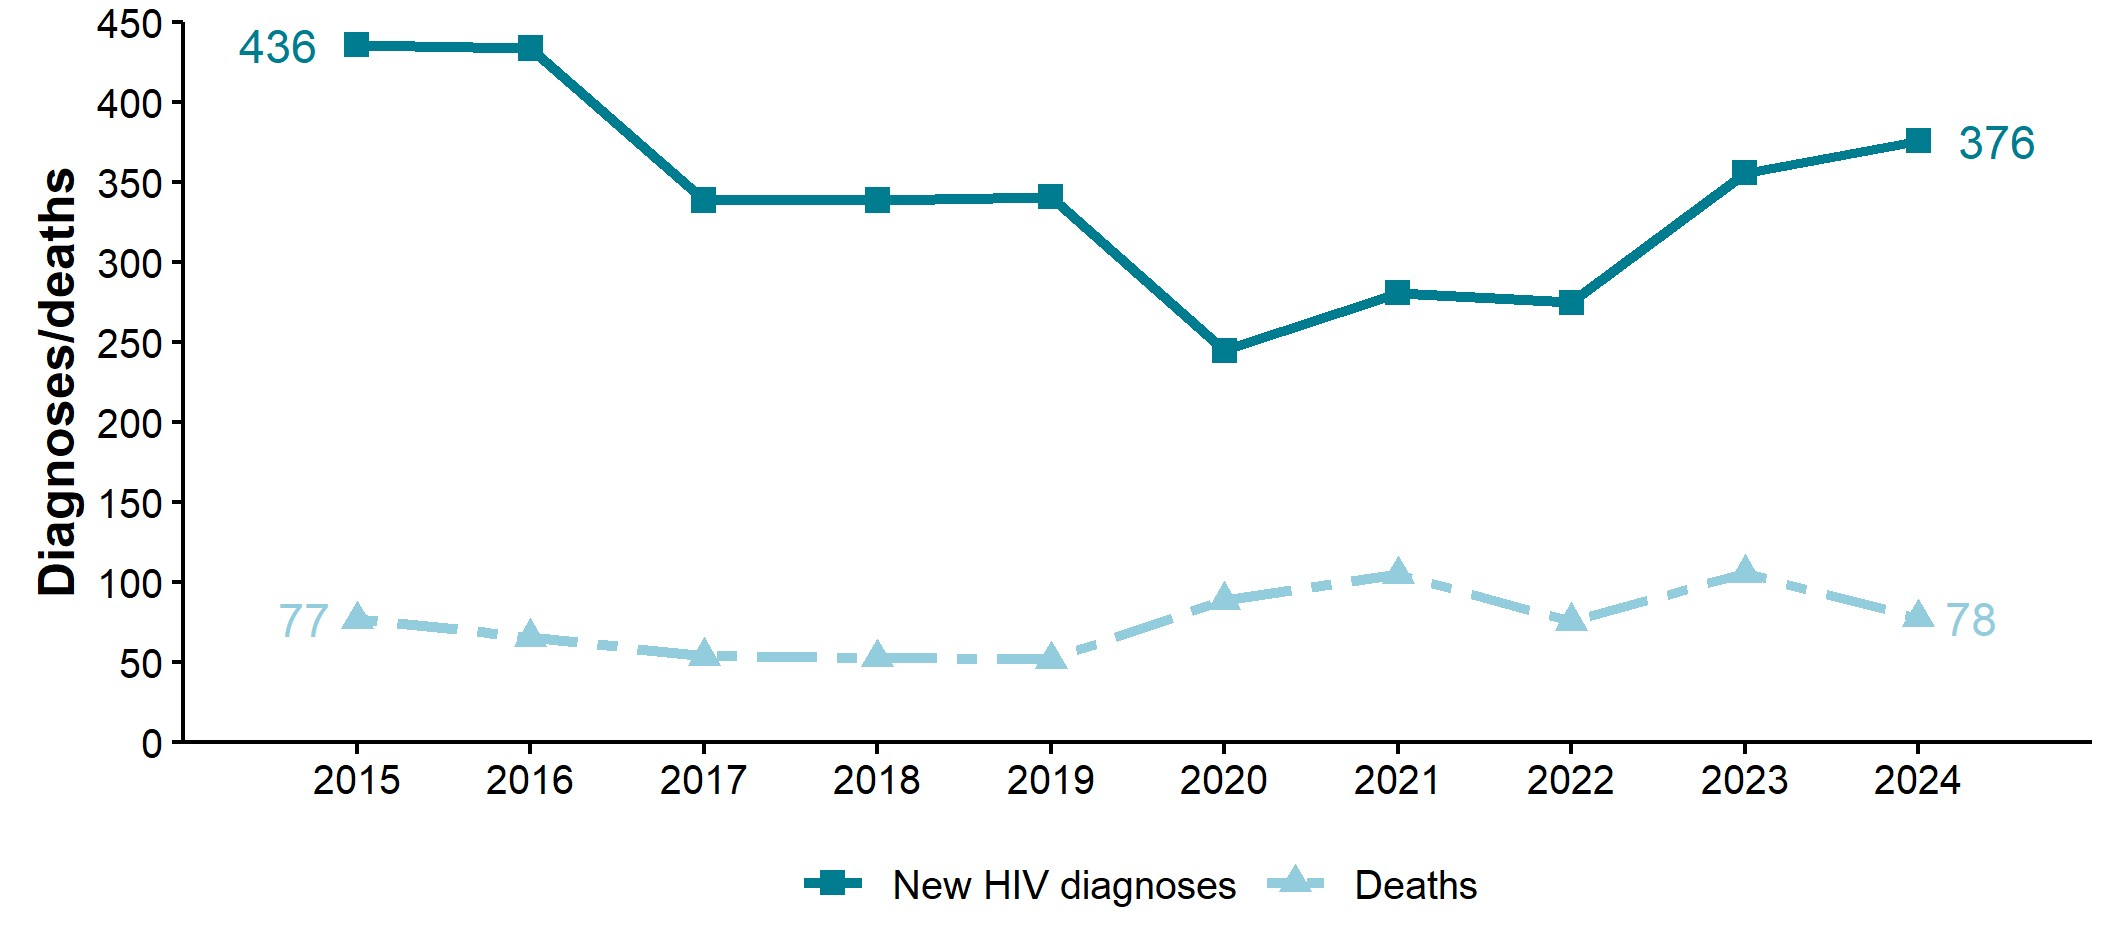
Figure 3. New HIV diagnoses and deaths, the South East, 2015 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. Numbers may rise as we receive more reports and more information. This will impact on interpretation of trends in more recent years. New HIV diagnoses are shown by UK region of residence at diagnosis. Deaths are shown by UK region of death which in some instances may not be the same as UK region of residence at diagnosis. Region of death may not be known for all deaths, particularly for those in the most recent years. Numbers for these years should be interpreted as minimum numbers (deaths reported and allocated to a region of death to date) and not as a trend.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 3 is a line chart showing the trend in number of new HIV diagnoses and deaths in HIV-diagnosed South East residents between the years 2015 and 2024.
The chart shows that there were 376 new HIV diagnoses and 78 deaths in South East residents diagnosed with HIV in 2024, compared to 436 new HIV diagnoses and 77 deaths in 2015. The number of new HIV diagnoses was 6% higher and the number of deaths was 26% lower in 2024 than in 2023 (356 diagnoses and 106 deaths). The number of deaths increased after 2019, coinciding with improved ascertainment of deaths following the introduction of the National HIV Mortality Review. Moreover, additional deaths due to COVID-19 were reported during the pandemic in people living with HIV. Deaths tend to be subject to a greater reporting delay than diagnoses, and it is important to be aware of this when interpreting the number of deaths currently reported for the most recent year.
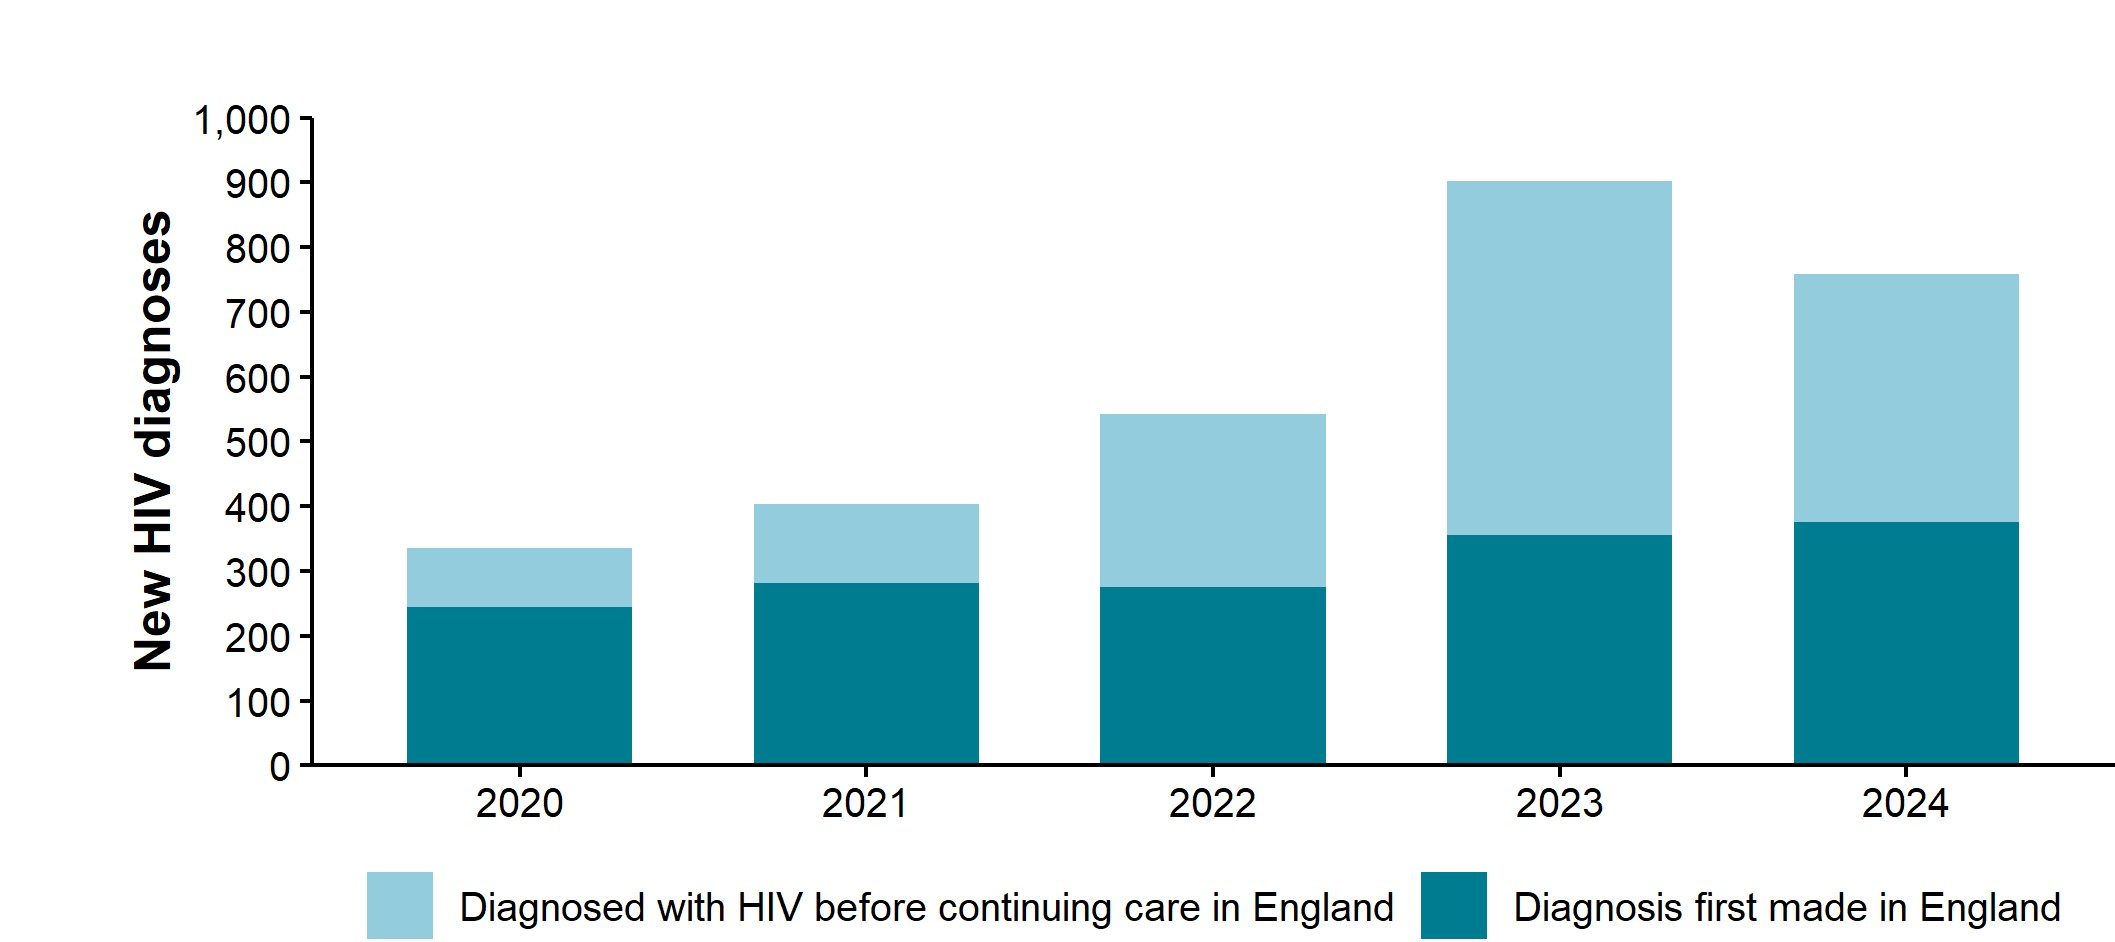
Figure 4. New HIV diagnoses by whether a person had been diagnosed with HIV before continuing care in England, the South East, 2020 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 4 is a column chart showing the trend in new HIV diagnoses in South East residents between 2020 and 2024 by whether patients had a diagnosis first made in England (teal) or whether they were diagnosed with HIV before continuing care in England (light blue). Identifying patients who have been previously diagnosed abroad has become an issue of increasing importance as access to testing and treatment has improved worldwide. Including those previously diagnosed abroad in all analyses can lead to distortions in our understanding of which groups remain exposed to the greatest risk of transmission in England.
The chart shows that the proportion of South East residents diagnosed with HIV before continuing care in England has increased over the 5-year period from 27% in 2020 (90 of 335 HIV diagnoses) to 50% in 2024 (382 of 758 HIV diagnoses). The proportion of diagnoses classified as diagnosed with HIV before continuing care in England was 61% in 2023 (546 of 902 HIV diagnoses), the highest proportion in the 5-year period.
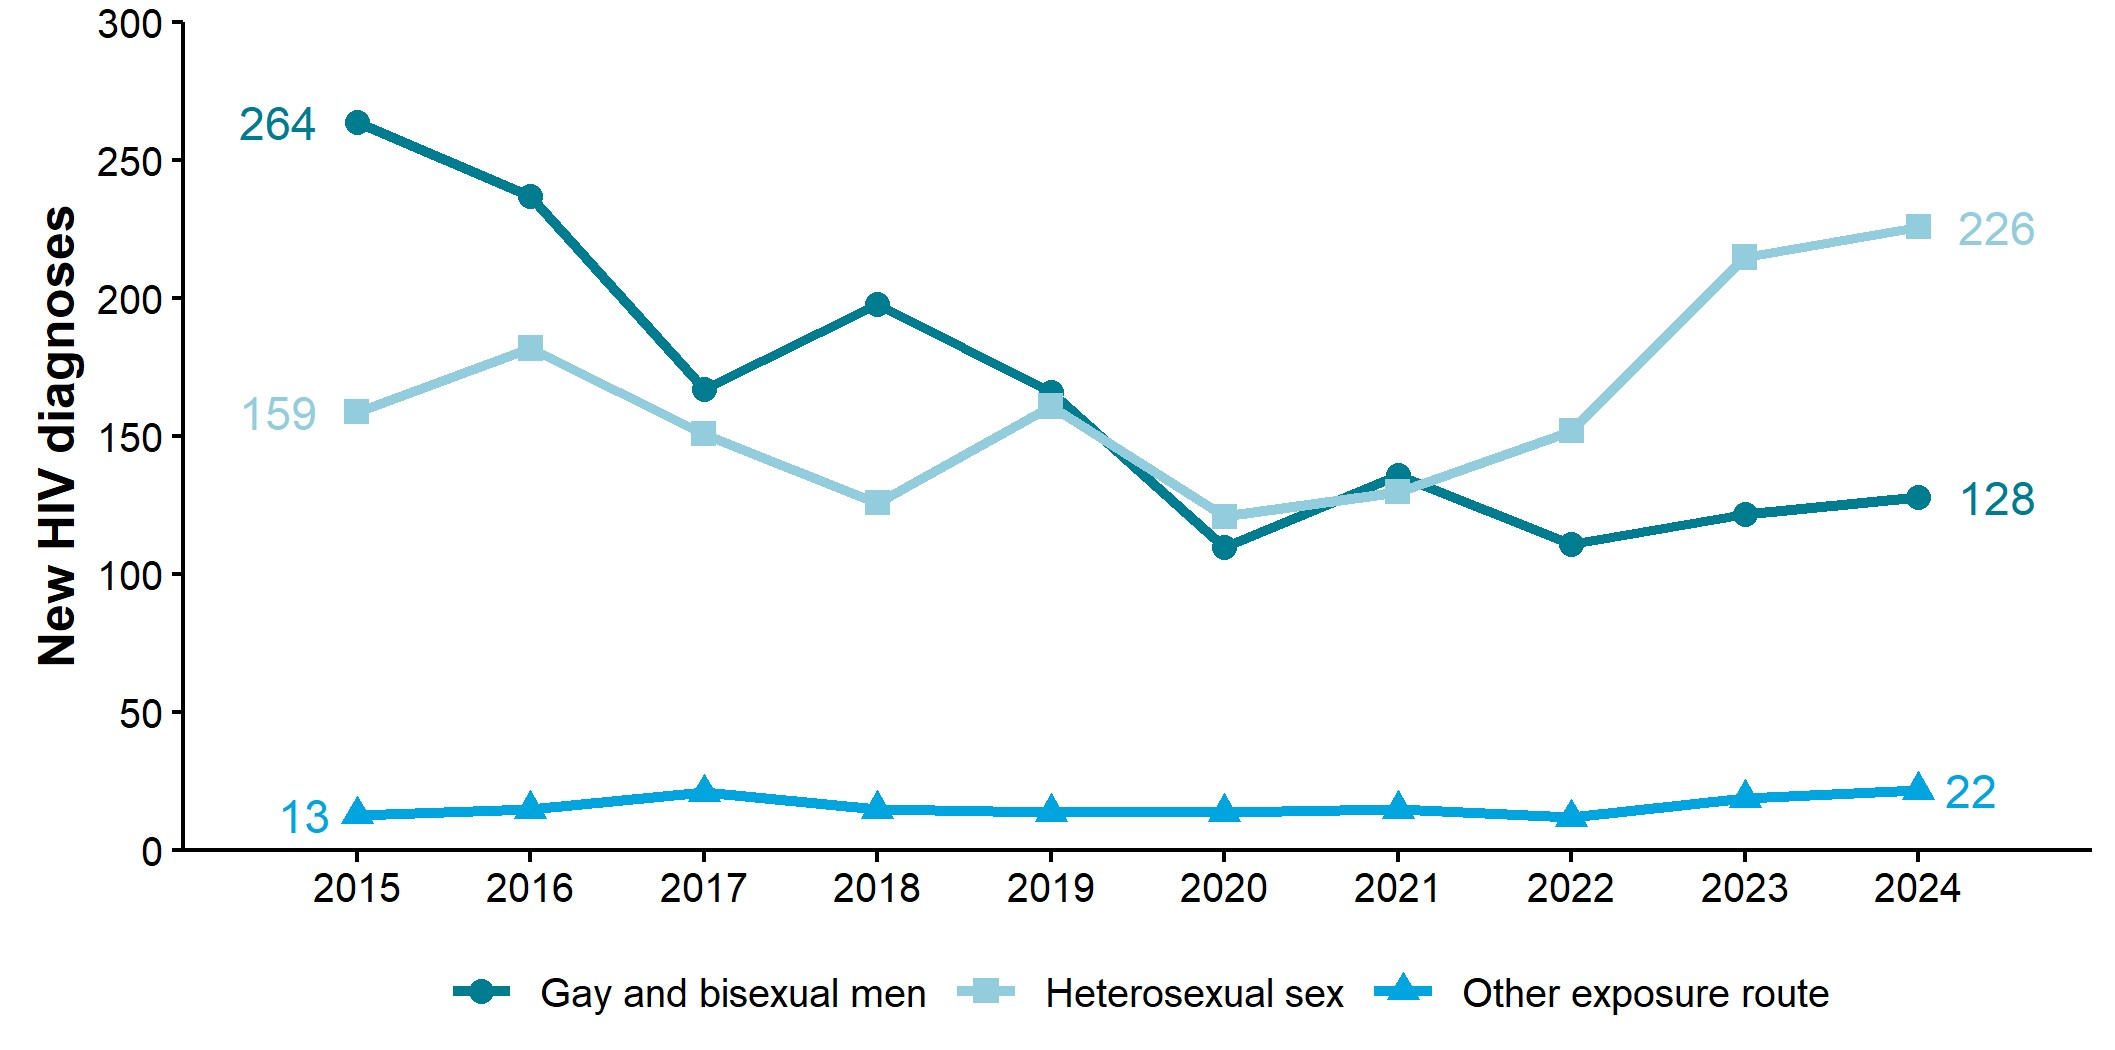
Figure 5. New HIV diagnoses by probable route of exposure (adjusted for missing route information), South East residents, 2015 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 5 is a line chart showing the trend in new HIV diagnoses in South East residents by probable route of exposure from 2015 to 2024. Numbers have been adjusted for missing route information, and diagnoses where this information is unknown have been proportionately allocated to the 3 exposure groups.
The chart shows that the number of new HIV diagnoses in those with heterosexual sex as their probable route of exposure has increased by 42% over the 10-year period, from 159 in 2015 to 226 in 2024.
The number of new HIV diagnoses in those with ‘Other exposure route’ as their probable route of infection has also increased by 69% over the 10-year period, from 13 in 2015 to 22 in 2024.
The number of new HIV diagnoses in gay and bisexual men has decreased by 52% over the 10-year period, from 264 in 2015 to 128 in 2024.
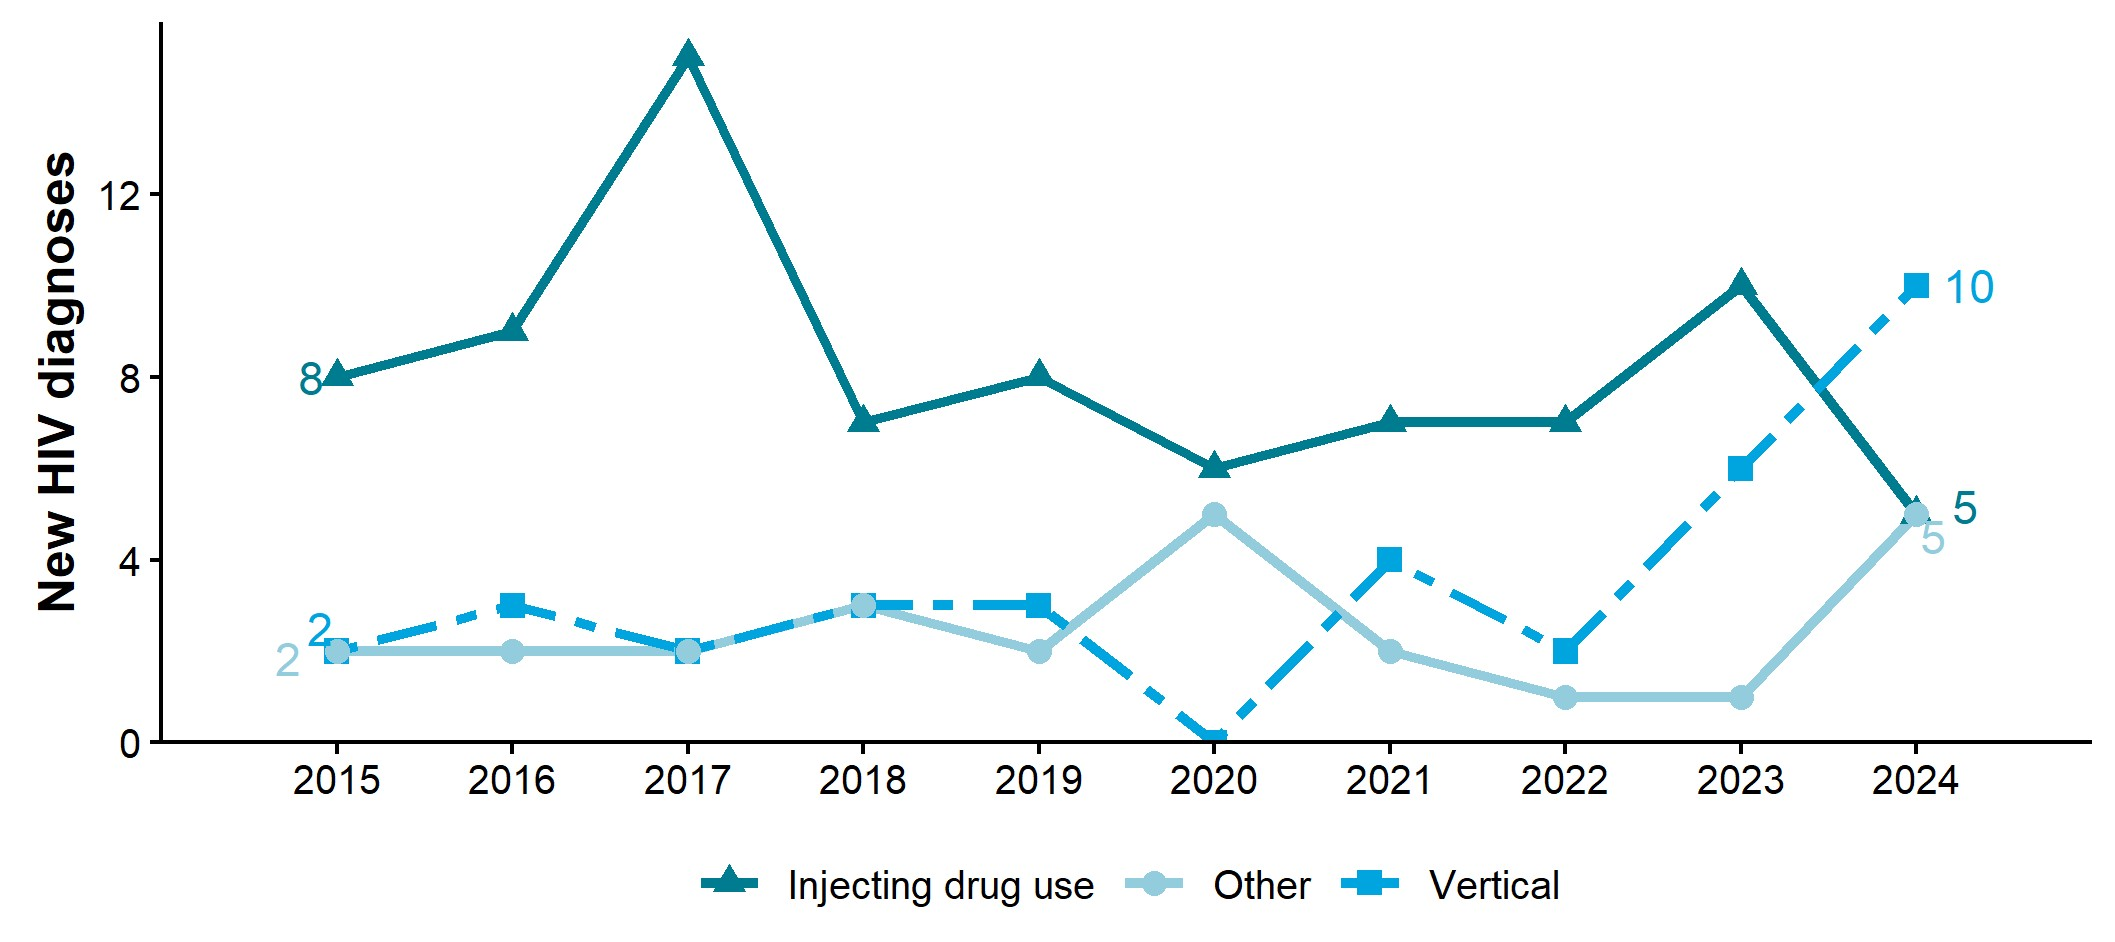
Figure 6. New HIV diagnoses detailed ‘other’ route of exposure (not adjusted for missing information), South East residents, 2015 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 6 is a line chart providing additional information on the HIV transmission routes grouped into ‘Other exposure route’ in Figure 5. The chart shows trends in new HIV diagnoses acquired through injecting drug use, vertical (mother-to-child) transmission, and other transmission routes, such as via blood or tissue, in South East residents from 2015 to 2024.
The chart shows that the number of new HIV diagnoses in South East residents whose probable route of HIV exposure belonged to any of these subcategories remained low throughout the 10-year period. An increase has been seen in vertical transmission since 2022, and the number of new HIV diagnoses in this group in 2024 (10 diagnoses) was 400% higher than it was in 2014 (2 diagnoses).
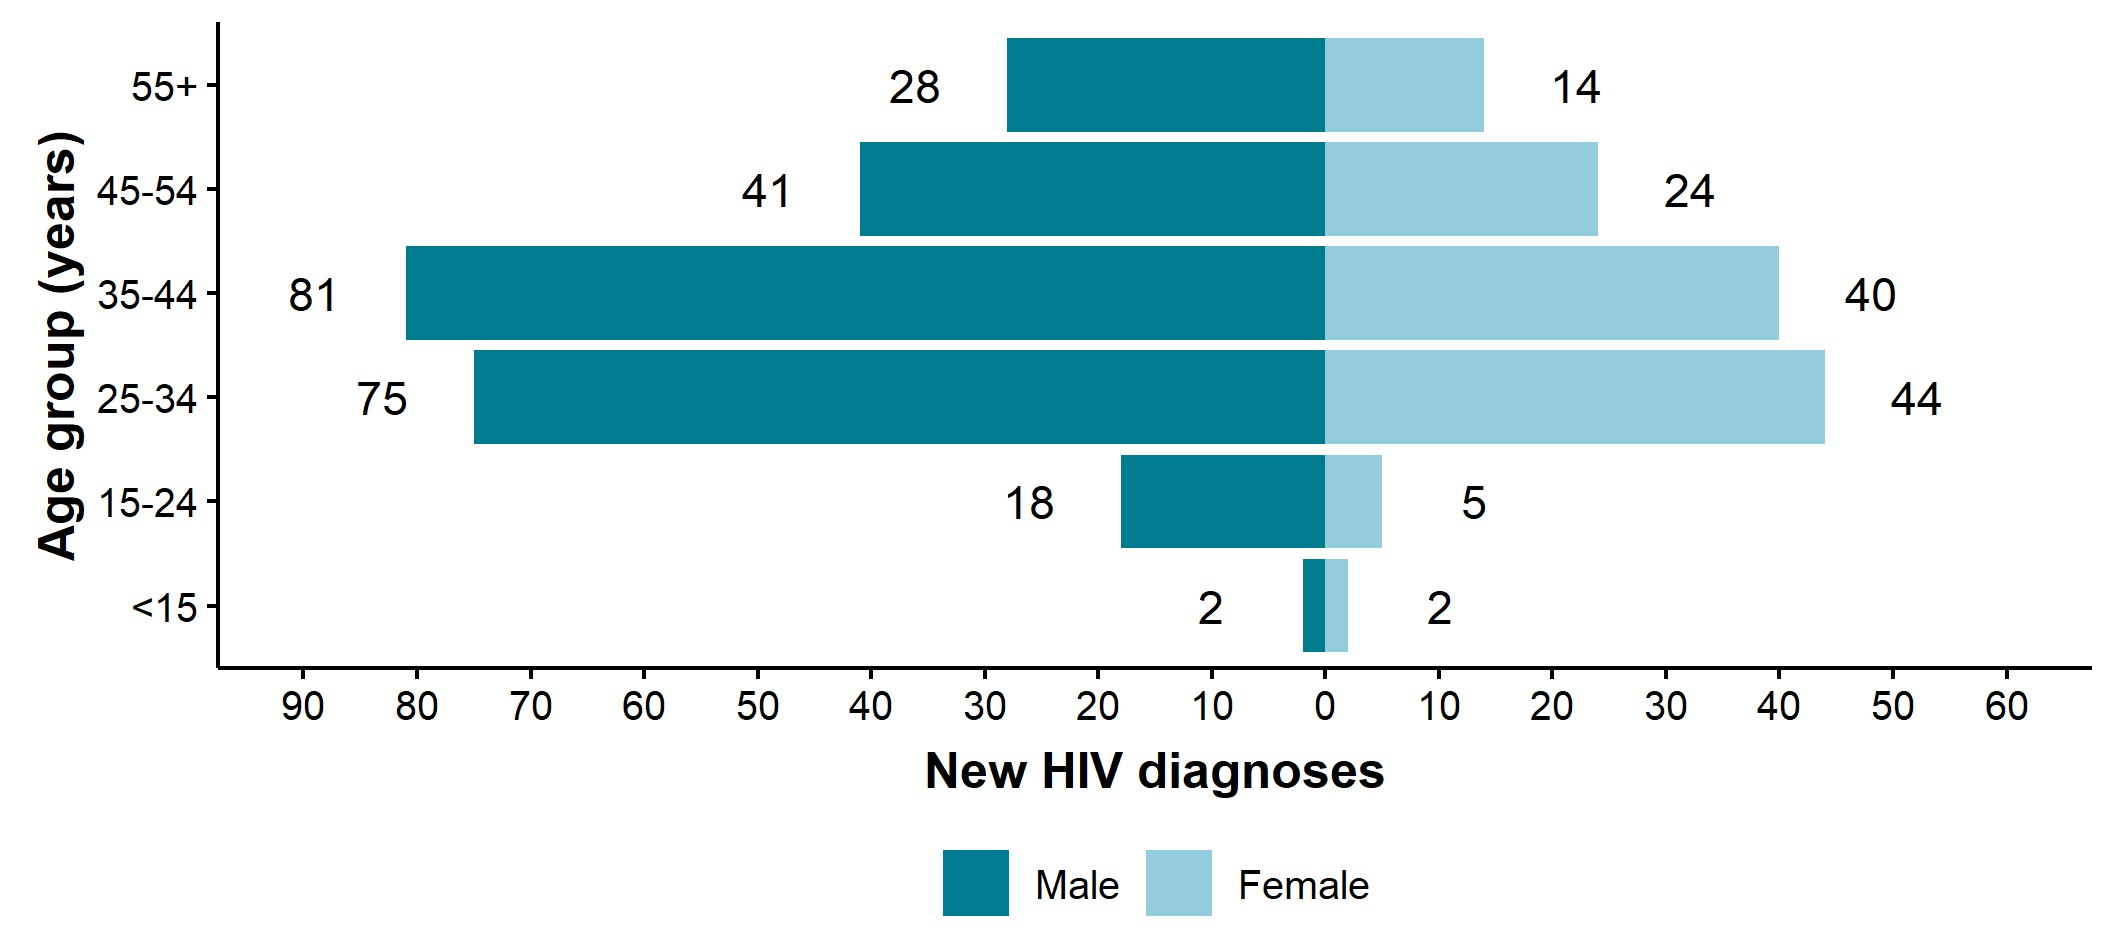
Figure 7. Number of new HIV diagnoses by age group and gender, South East residents, 2024
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infections and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Figure 7 is a pyramid chart showing the number of new HIV diagnoses by age group and sex in South East residents in 2024.
The male 35 to 44 year age group had the highest number of new HIV diagnoses (81), followed by the male 25 to 34 year age group (75). For females, the 25 to 34 year age group had the highest number of new HIV diagnoses (44), followed by the 35 to 44 year age group (40).
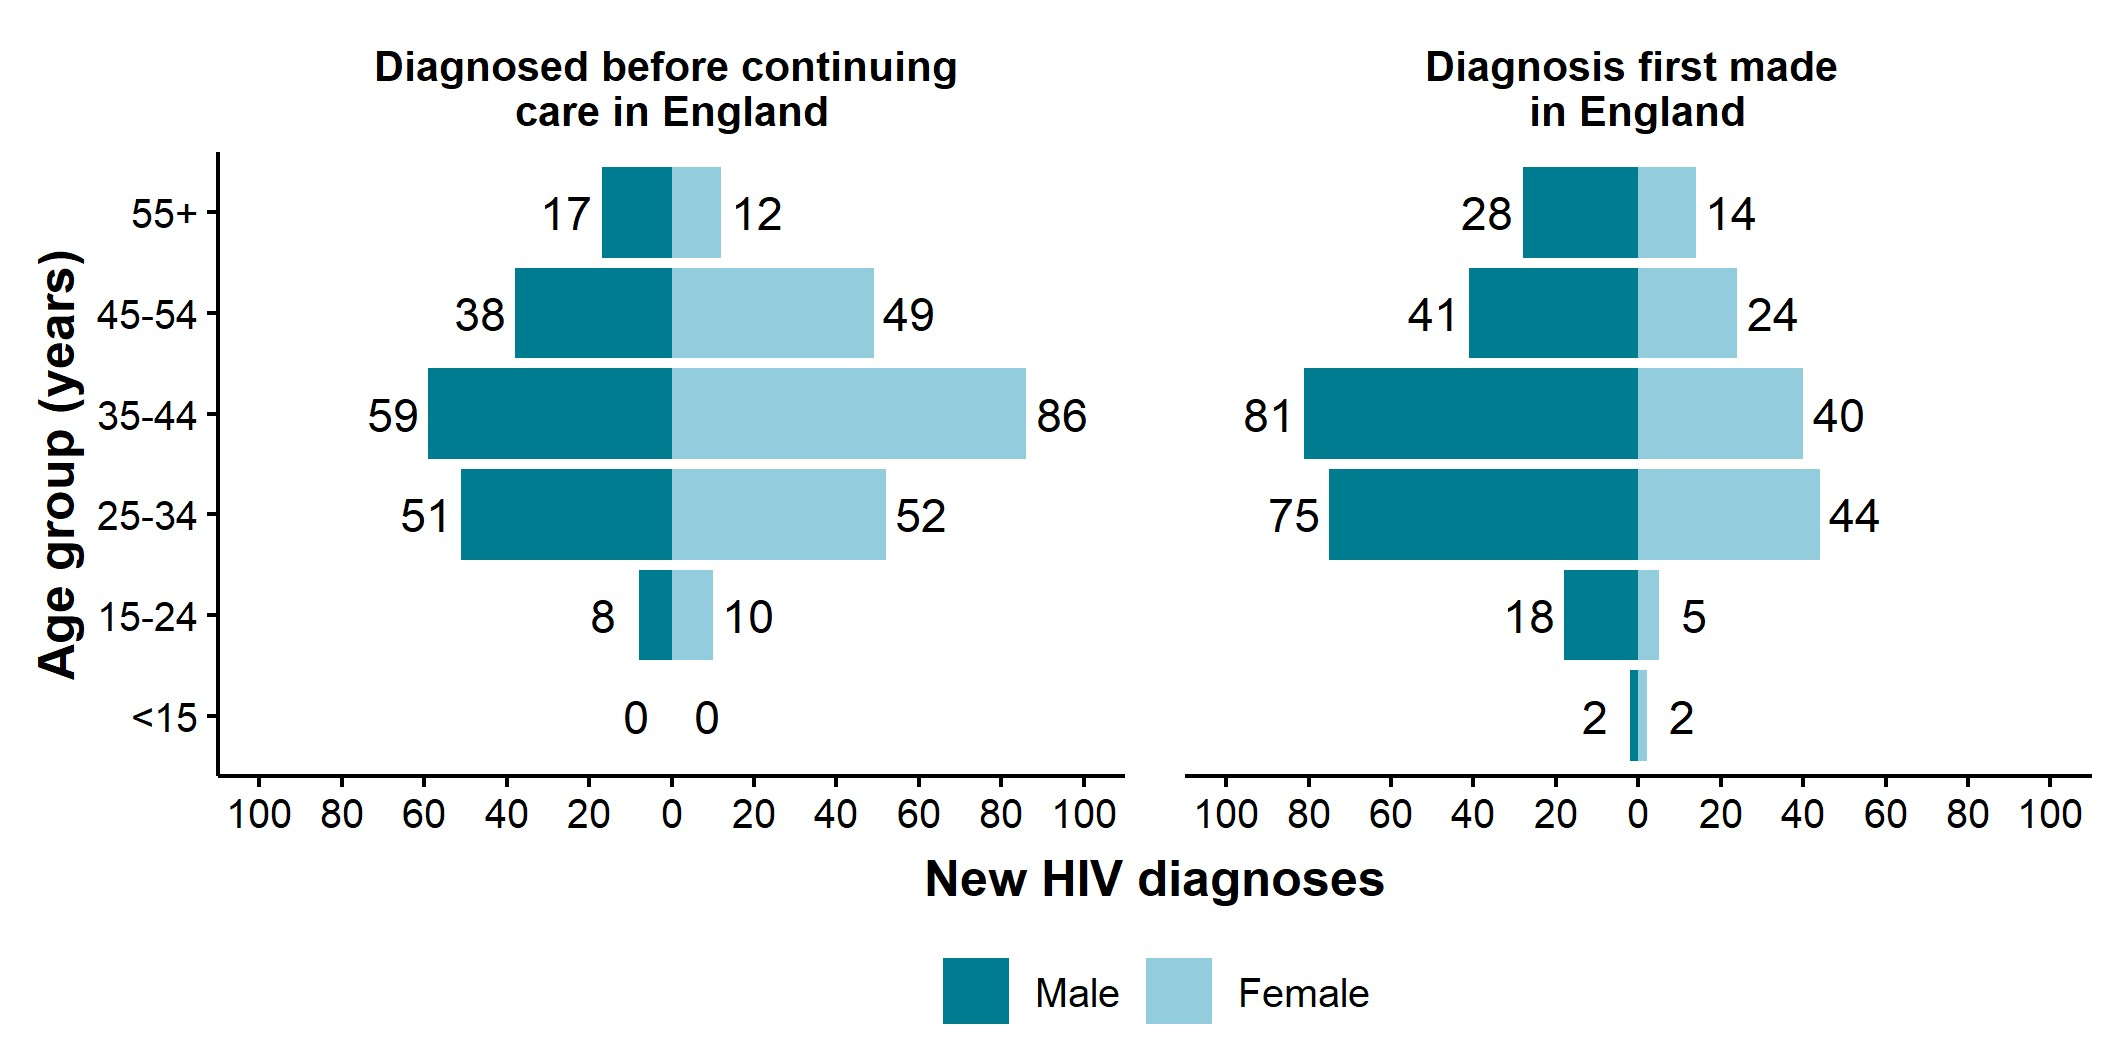
Figure 8. Number of new HIV diagnoses by age group and gender, split by whether first diagnosed in the UK or abroad, South East residents, 2024
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infections and transmission.
Figure 8 is a pair of pyramid charts showing the number of new HIV diagnoses in South East residents previously diagnosed abroad before continuing care in England and in those first diagnosed in England by age group and sex in 2024.
Among those previously diagnosed abroad before continuing care in England, females in the 35 to 44 year age group had the highest number of new HIV diagnoses (86). Among those first diagnosed in England, males in the 35 to 44 year age group had the highest number of new HIV diagnoses (81).
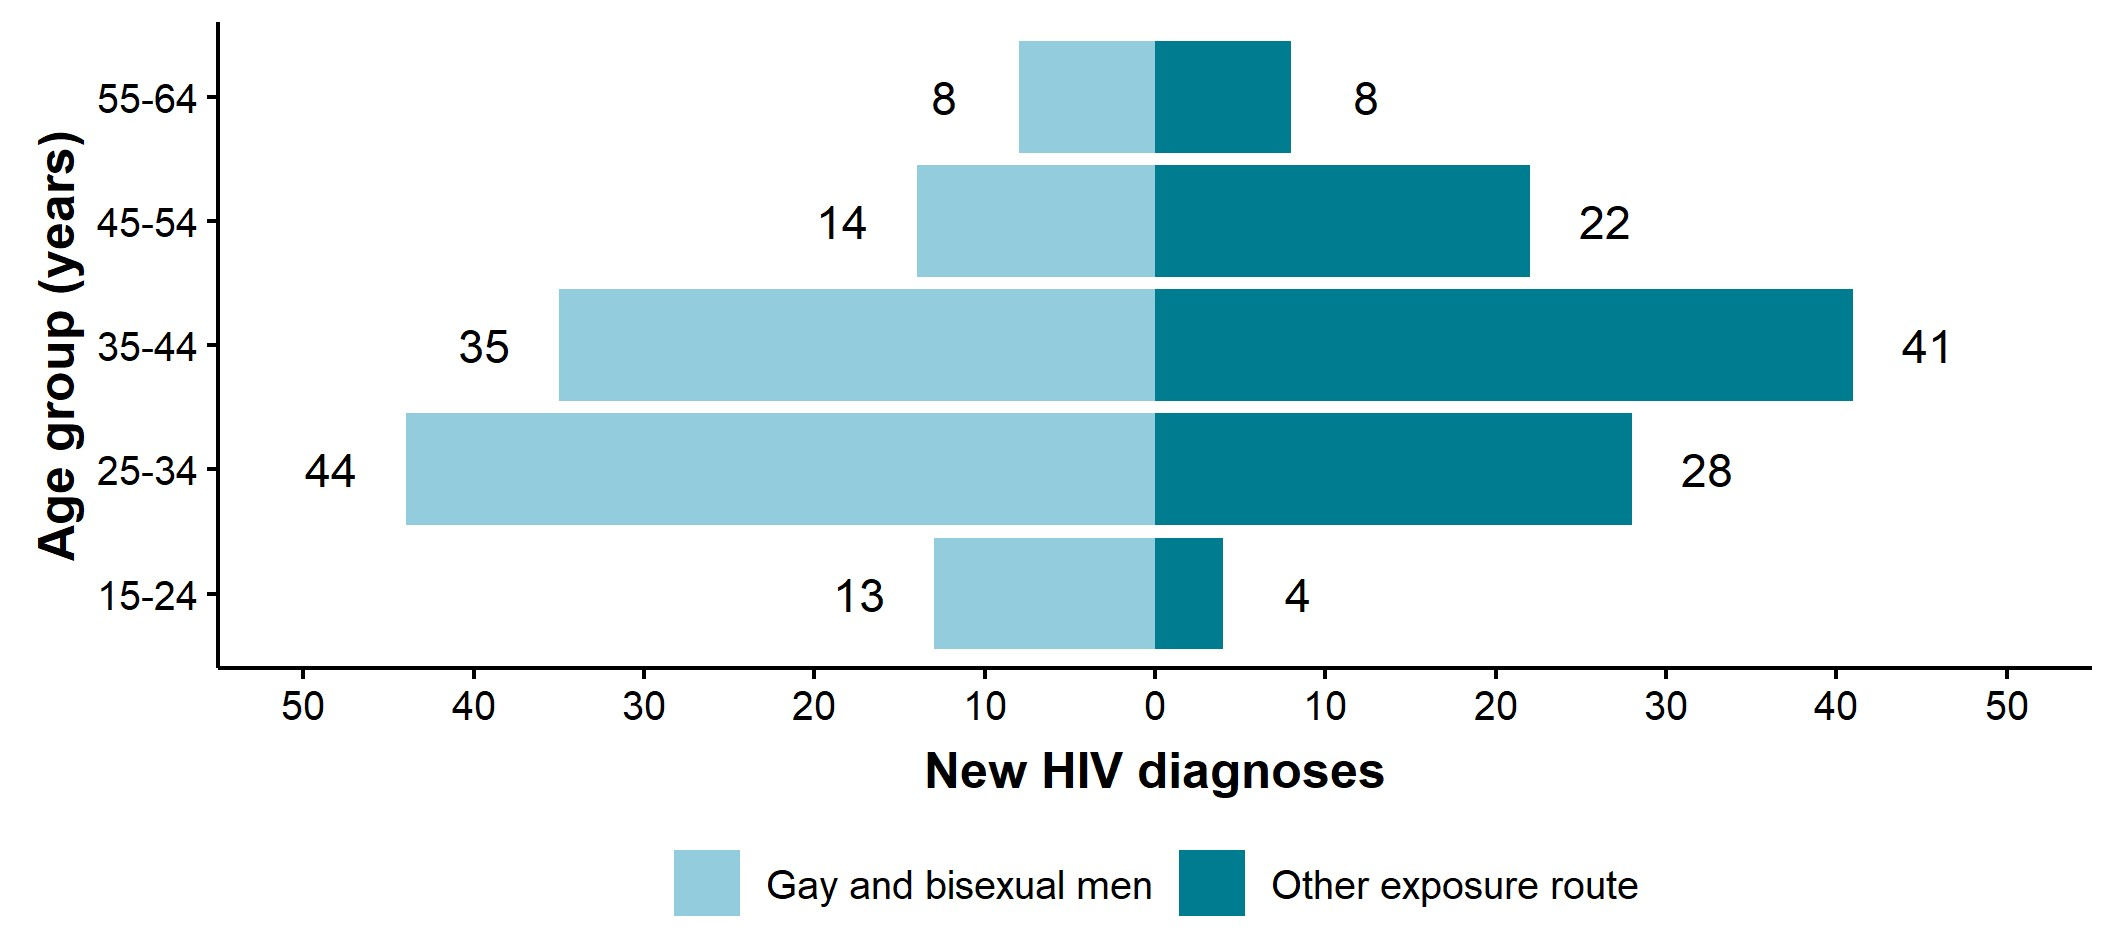
Figure 9. Number of new HIV diagnoses by age group and probable route of exposure, male South East residents aged 15 to 64 years, 2024
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Figure 9 is a pyramid chart showing the number of new HIV diagnoses for male South East residents aged 15 to 64 years by age group and probable route of exposure in 2024. Probable route of exposure has been split between ‘gay and bisexual men’ and ‘all other routes of exposure’.
For gay and bisexual men, the 25 to 34 year age group accounted for the highest number of new HIV diagnoses (44). For those who probably acquired HIV through all other exposure routes, the 35 to 44 year age group had the highest number of new HIV diagnoses (41). It is important to note that the left side of the pyramid is skewed towards the younger ages as they have a markedly higher proportion identifying as lesbian, gay, bisexual or another minority sexual orientation (LGB+) than the overall population (6).
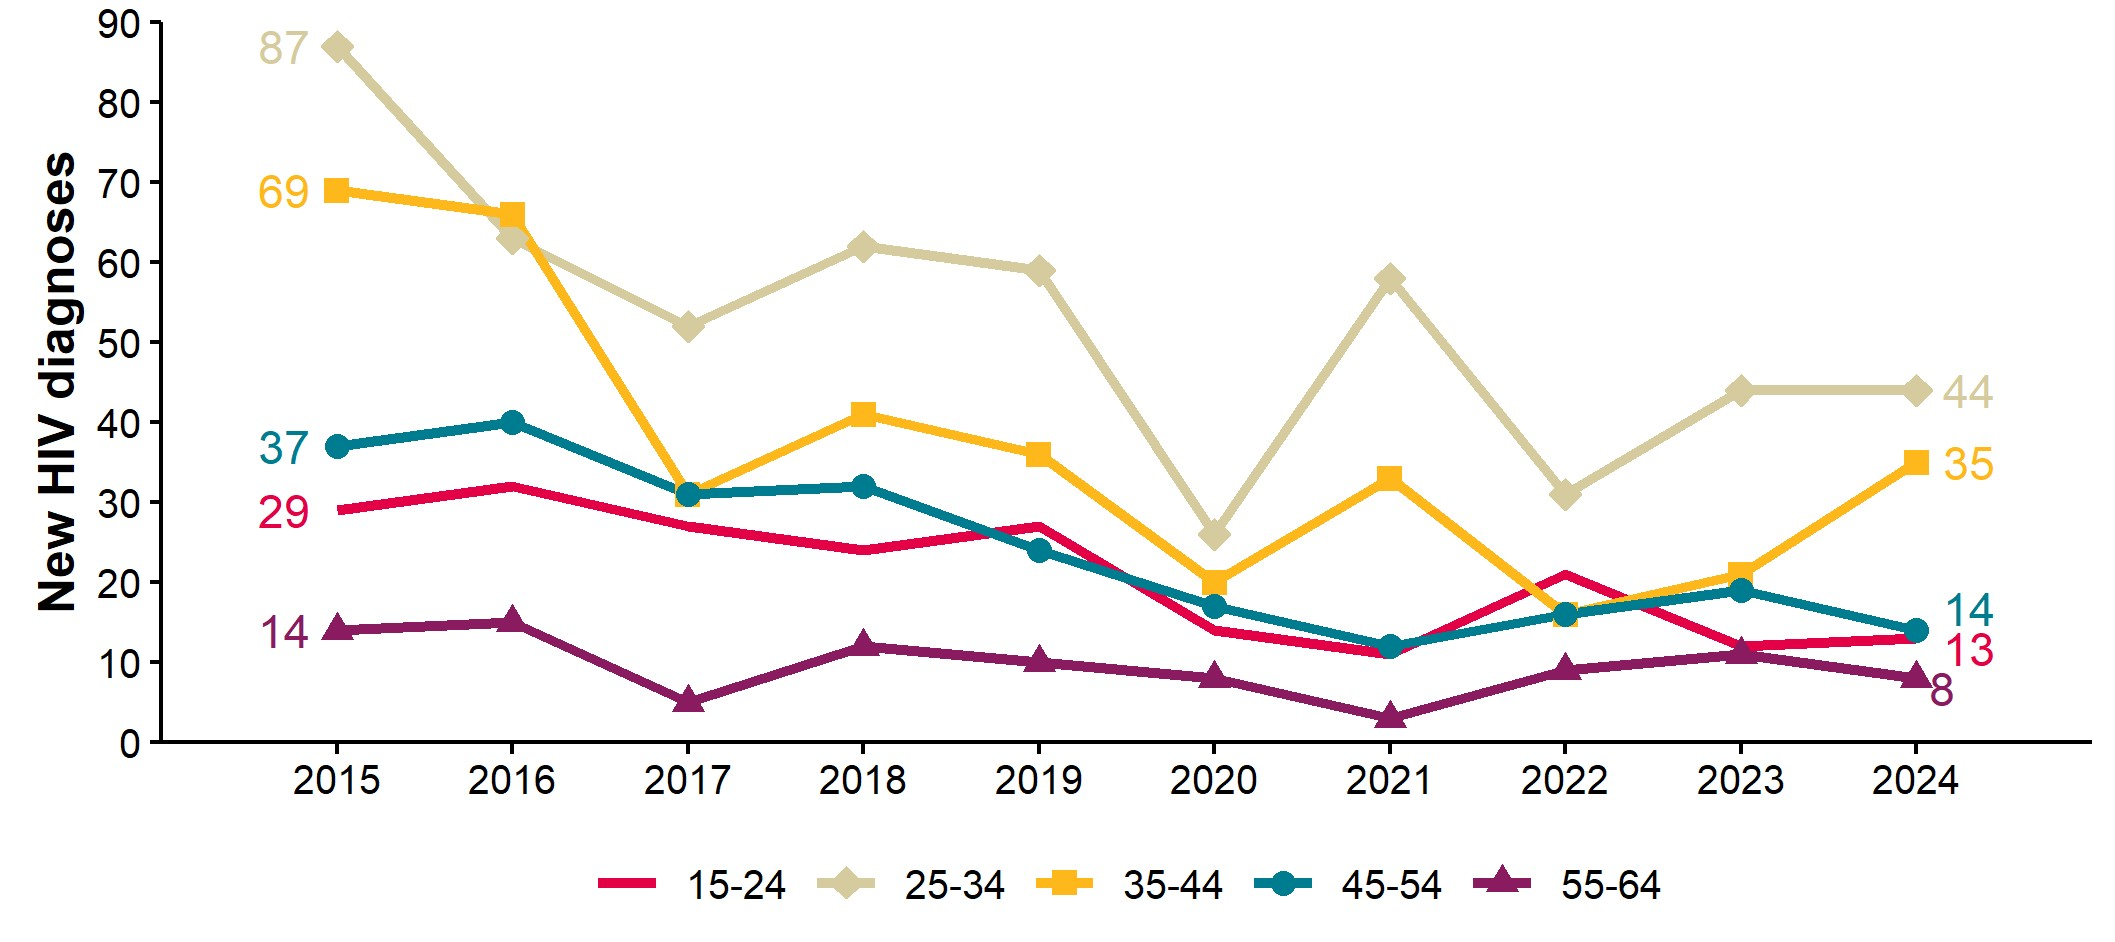
Figure 10. Number of new HIV diagnoses in gay and bisexual men by age group and year of first UK HIV diagnosis, South East residents aged 15 to 64 years, 2015 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 10 is a line chart showing the number of new HIV diagnoses in gay and bisexual men by age group and year of first HIV diagnosis for South East residents aged 15 to 64 years from 2015 to 2024.
Between 2015 and 2024, the number of new diagnoses decreased for all age groups. Between 2023 and 2024, the number of new diagnoses decreased for all age groups apart from the 15 to 24 year age group (8% increase from 12 to 13) and the 35 to 44 year age group (67% increase from 21 to 35). The 25 to 34 year age group had the highest number of new diagnoses every year between 2015 and 2024, apart from in 2016, when the 35 to 44 year age group had the highest number of new diagnoses. The number of new HIV diagnoses in the 25 to 34 year age group accounted for 39% of all new diagnoses in gay and bisexual men aged 15 to 64 years in South East residents in 2024.
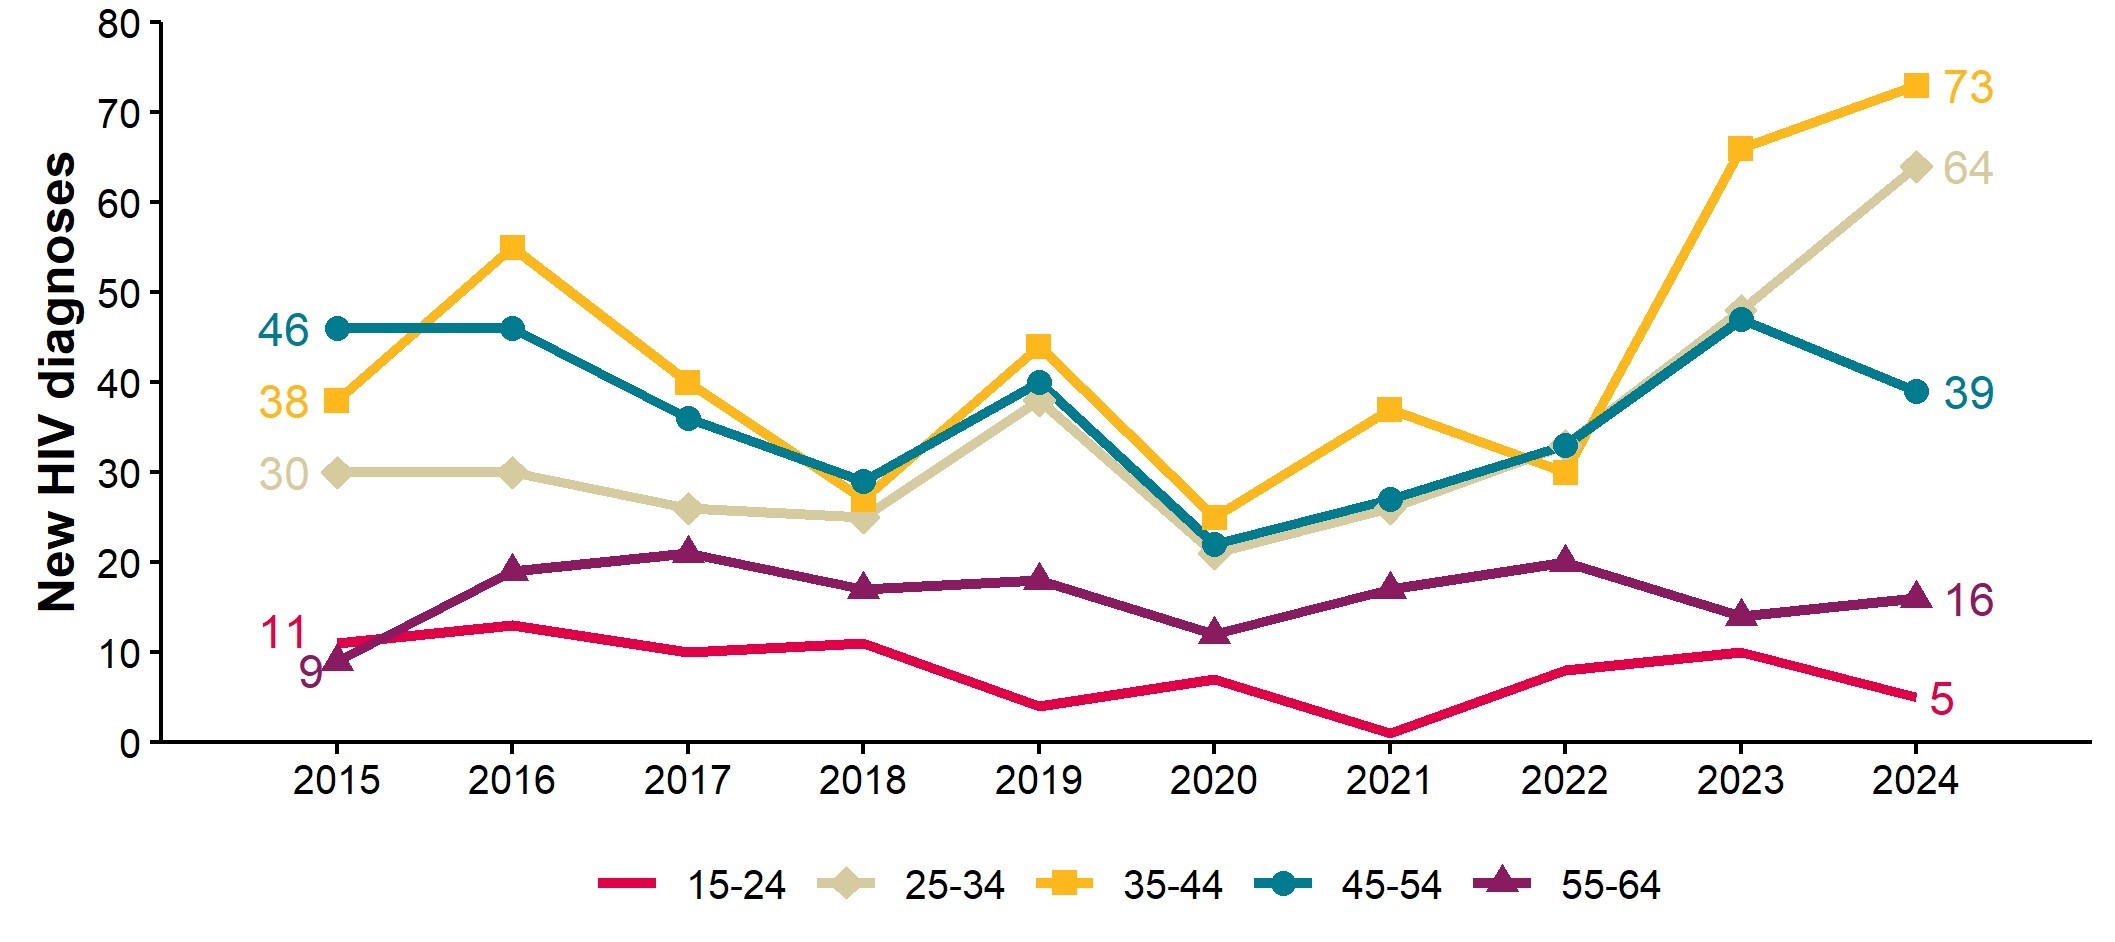
Figure 11. Number of new HIV diagnoses with a probable route of exposure through heterosexual sex by age group (in years) and year of first HIV diagnosis, South East residents aged 15 to 64 years, 2015 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 11 is a line chart showing the number of new HIV diagnoses with probable route of exposure through heterosexual sex by age group and year of first HIV diagnosis for South East residents aged 15 to 64 years from 2015 to 2024.
Between 2015 and 2024, the number of new HIV diagnoses with probable route of exposure through heterosexual sex increased for all age groups apart from a 55% decrease in the 15 to 24 year age group and a 15% decrease in the 45 to 54 year age group. The largest increase was of 113% in the 25 to 34 year age group, followed by 92% in the 35 to 44 year age group, and 78% in the 55 to 64 years age group. Those aged between 25 and 34 saw a dip in the number of diagnoses from 2019 to 2020 due to the COVID-19 pandemic, followed by a larger increase between 2020 and 2024 to the highest numbers in the last 10 years.
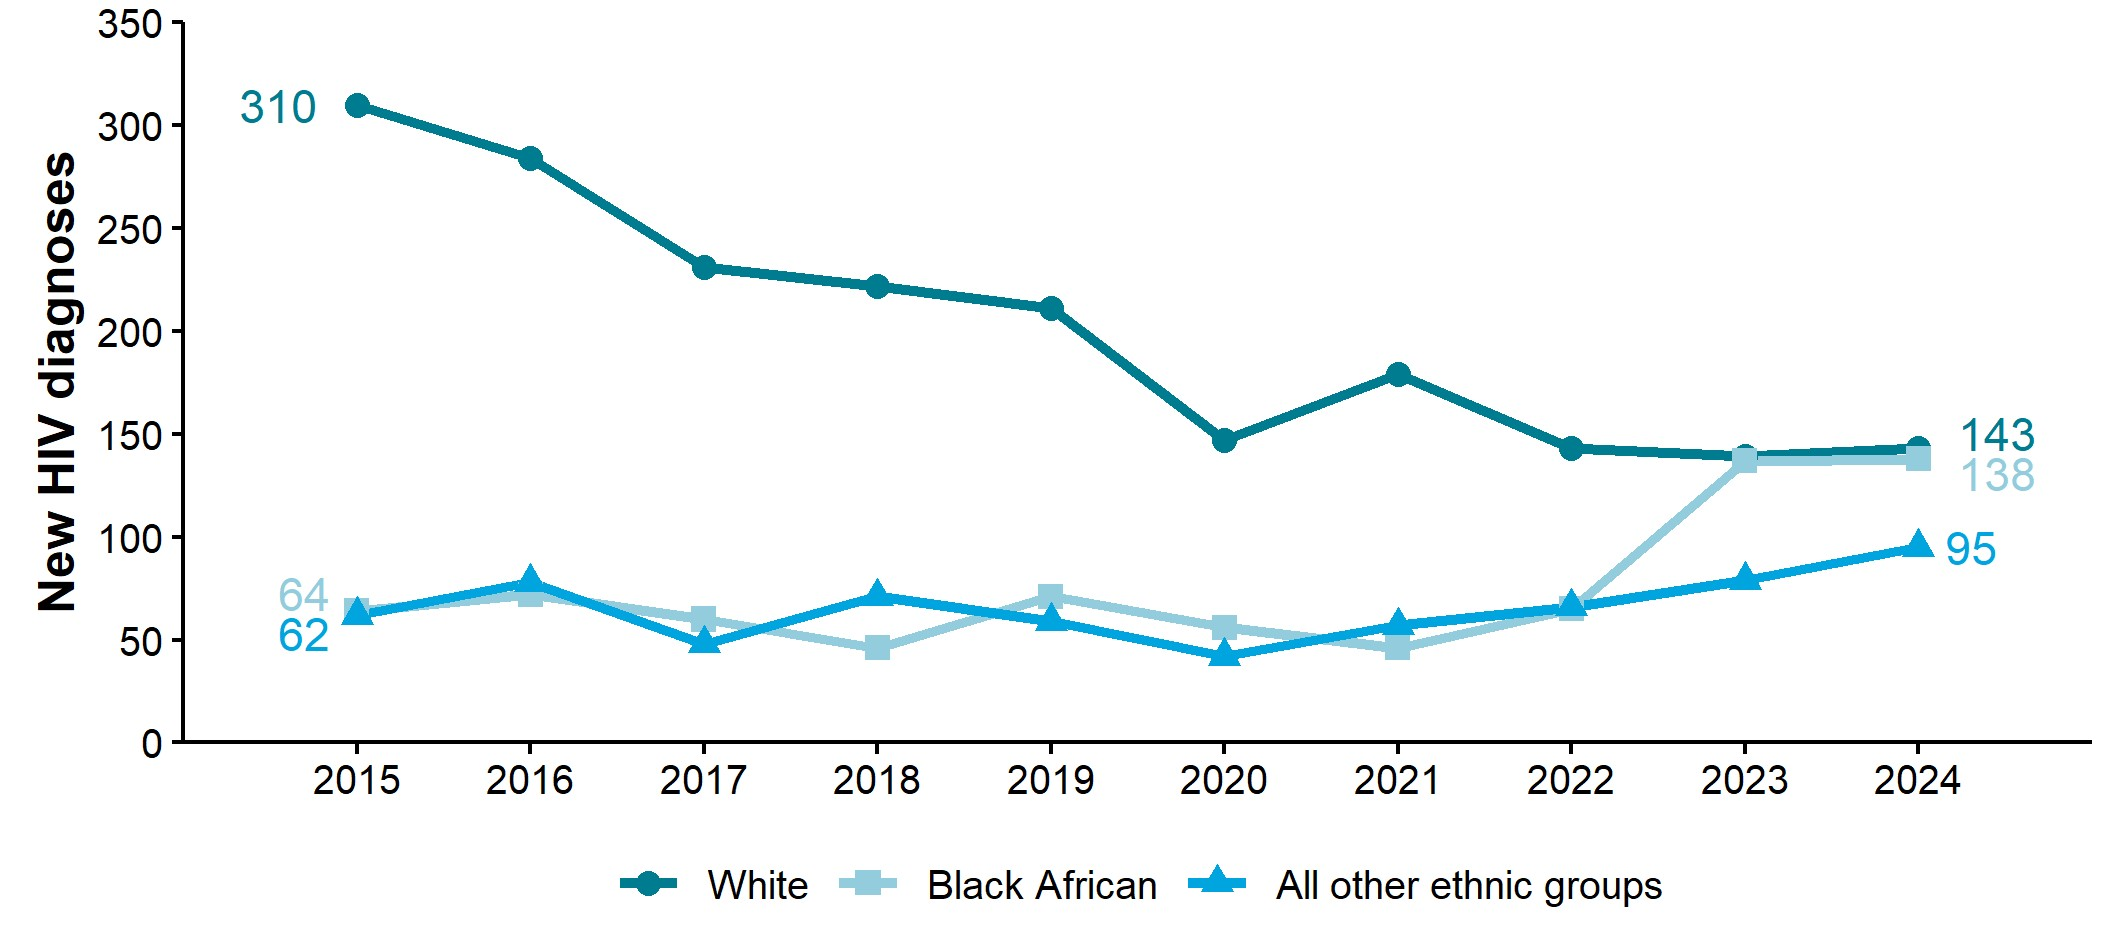
Figure 12. Number of new HIV diagnoses by ethnic group (adjusted for missing ethnic group information), South East residents, 2015 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 12 is a line chart showing the number of new HIV diagnoses in South East residents by ethnic group from 2015 to 2024. The White and Black African ethnic groups are represented as distinct categories, while all other ethnic groups have been combined into ‘All other ethnic groups’ due to smaller numbers of diagnoses.
Between 2015 and 2024, the number of new HIV diagnoses in the White ethnic group decreased by 54%, while numbers in the Black African ethnic group increased by 116% and numbers for All other ethnic groups increased by 53%. Between 2023 and 2024, all ethnic groups experienced an increase in the number of new HIV diagnoses, of which All other ethnic groups increased by 17%, the White ethnic group by 3%, and the Black African ethnic group by 1%.
It is important to emphasise that ethnic group is not a proxy for country or world region of birth. Ethnicity is a complex concept and is self-identified and reported within the limitations of the available options provided. It may incorporate cultural, religious and linguistic differences as well as differences in physical attributes and world region of origin. People may identify their ethnic group differently in different contexts or over time.
Age distributions differ by ethnic group. This is important when calculating rates, as these rates are for all ages. The White ethnic group has the oldest age distribution, depressing its rate as numbers of HIV diagnoses in the oldest age groups are lower. Other important determinants, such as deprivation and issues of stigma, also vary by ethnic group. Charts and tables by ethnic group should always be interpreted in the wider context of determinants and never in isolation.
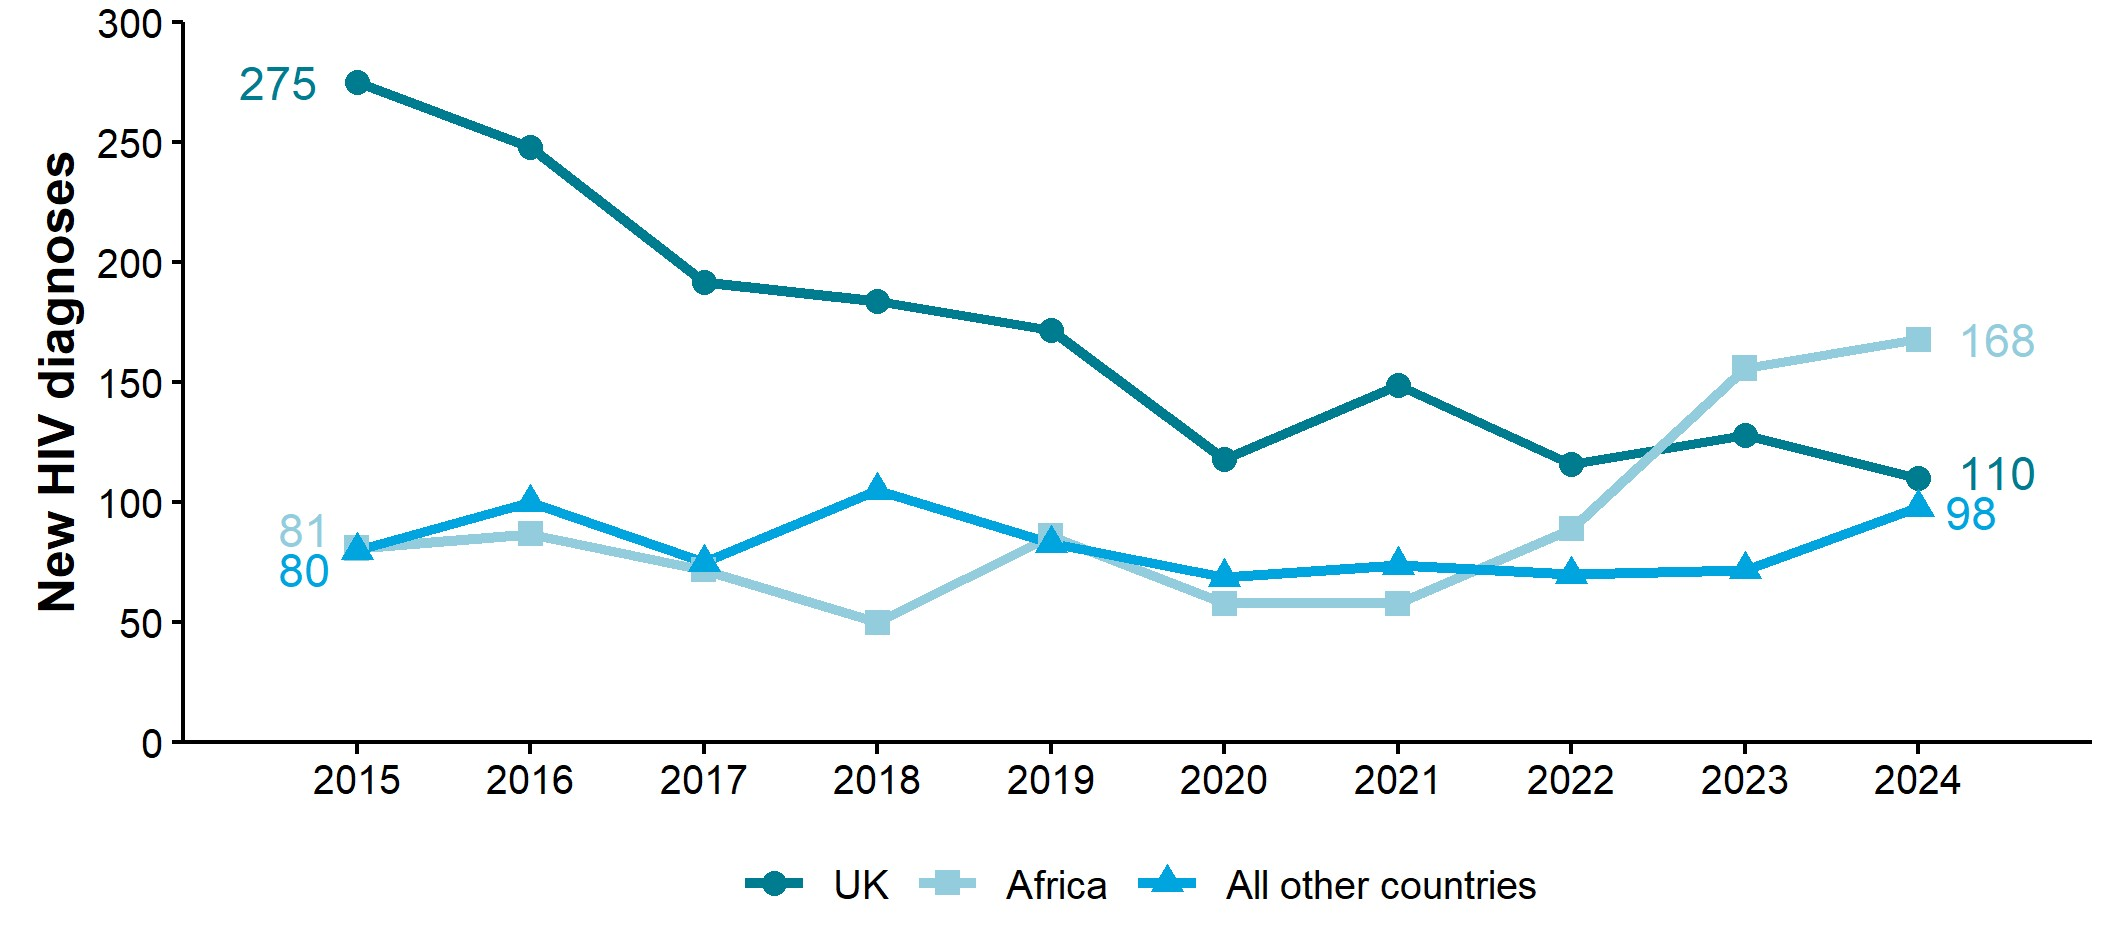
Figure 13. Number of new HIV diagnoses by world region of birth (adjusted for missing world region of birth information), South East residents, 2015 to 2024 [note 1]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 13 is a line chart showing the number of new HIV diagnoses in South East residents by world region of birth from 2015 to 2024. The UK and Africa are represented as distinct categories, and all other countries of birth are grouped into a single category.
Between 2015 and 2024, the number of new HIV diagnoses in those born in the UK decreased by 60% from 275 to 110, while it increased by 107% from 81 to 168 in those born in Africa, and by 23% from 80 to 98 in those born in All other countries. Between 2023 and 2024, the number of new HIV diagnoses in those born in the UK decreased by 14%, while it increased by 8% in those born in Africa, and by 36% in those born in All other countries.
Table 1. Number of new HIV diagnoses by ethnic group and whether born abroad, South East residents, 2020 to 2024 [note 1]
| Ethnic group | UK-born | Born abroad | Unknown country of birth |
|---|---|---|---|
| White | 480 | 158 | 41 |
| Black African | 8 | 375 | 21 |
| Black Caribbean | 5 | 19 | 1 |
| Other | 42 | 226 | 16 |
| Unknown | 12 | 35 | 94 |
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
Table 1 shows that the relationship between ethnic group and whether a person newly diagnosed with HIV was born abroad. Data is for the 5-year period 2020 to 2024. Those with a prior diagnosis abroad are excluded. To make it clear that there are differences in completeness of ascertainment of country of birth for different ethnic groups, numbers in this table are not adjusted for missing information.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Table 1 shows the number of new HIV diagnoses in South East residents by ethnic group and whether born abroad or not for the 5-year period 2020 to 2024. The number of diagnoses in any group containing a large proportion of people who were born abroad is sensitive to changes in migration patterns over time.
For the White ethnic group, country of birth was known for 94% of new HIV diagnoses, of which 75% were UK-born. For the Black African ethnic group, country of birth was known for 95% of new HIV diagnoses, of which 98% were born abroad. For the Black Caribbean ethnic group, country of birth was known for all but one new HIV diagnoses, of which 79% were born abroad. For the Other ethnic group, country of birth was known for 94% of new HIV diagnoses, of which 84% were born abroad.
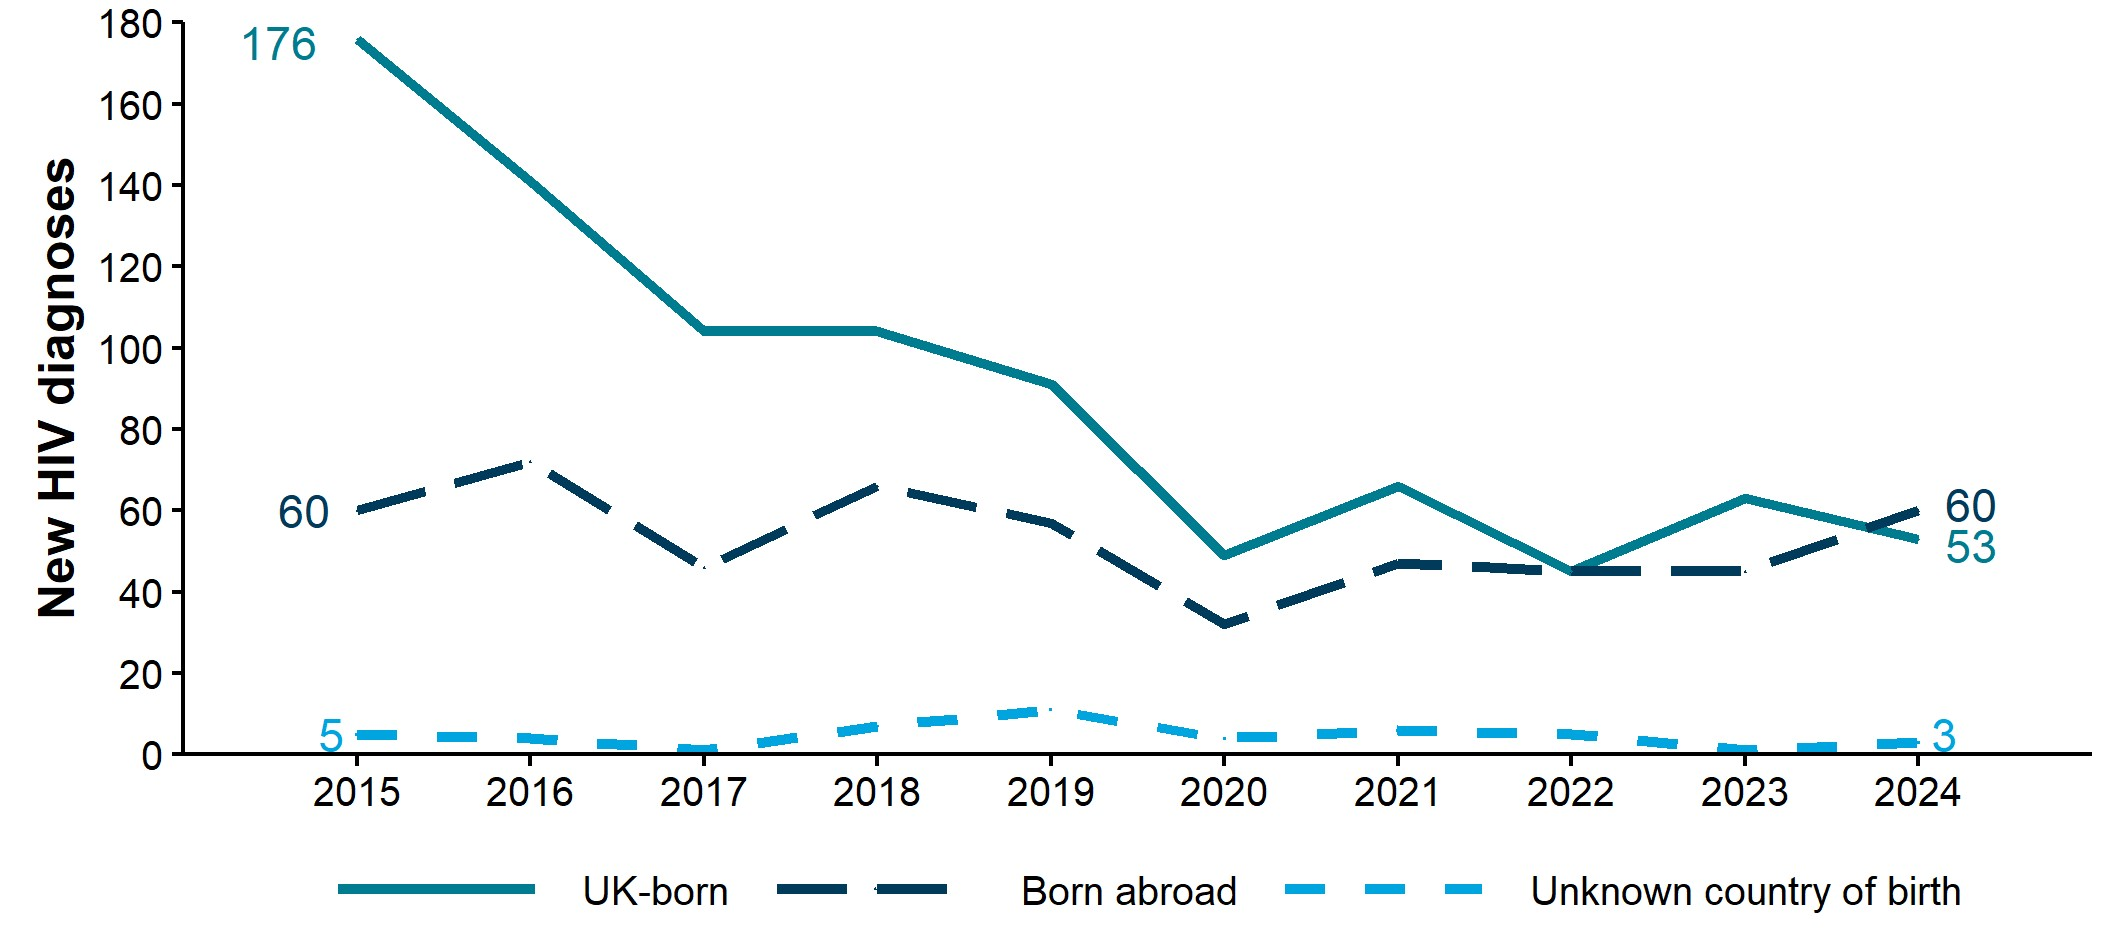
Figure 14. New HIV diagnoses in gay and bisexual men by whether born abroad, South East residents, 2015 to 2024 [note 1]
Sources: UKHSA, HANDD.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. Those with a prior diagnosis abroad are excluded.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 14 is a line chart showing the number of new HIV diagnoses in gay and bisexual men by whether born abroad or not for South East residents not previously diagnosed abroad for the 10-year period 2015 to 2024.
Between 2015 and 2024, the number of new HIV diagnoses in UK-born gay and bisexual men decreased by 70% from 176 to 53. The number of new HIV diagnoses in gay and bisexual men that were born abroad was 60 in both 2015 and 2024. In 2024, the number of new HIV diagnoses in gay and bisexual men was highest in those that were born abroad for the first time in the 10-year period.
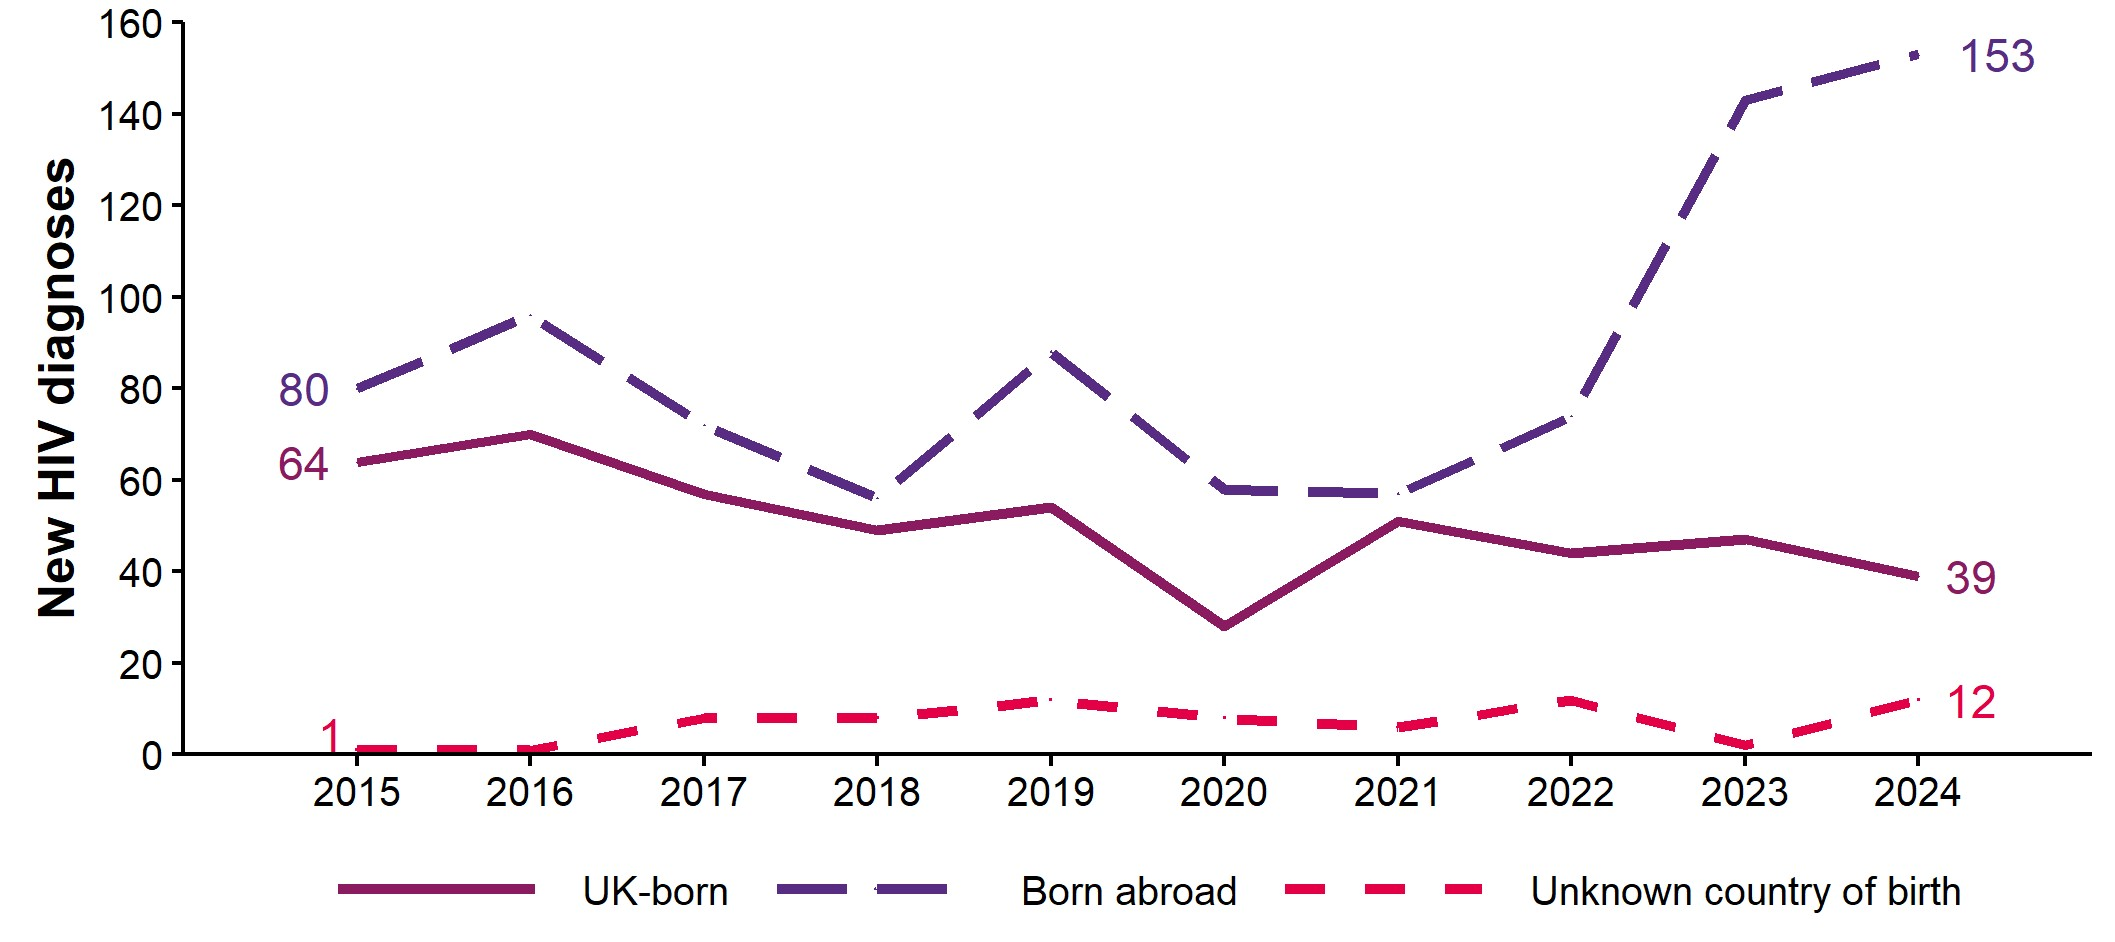
Figure 15. New HIV diagnoses in heterosexuals by whether born abroad, South East residents, 2015 to 2024 [note 1]
Sources: UKHSA, HANDD.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. Those with a prior diagnosis abroad are excluded.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 15 is a line chart showing the number of new HIV diagnoses in heterosexual South East residents not previously diagnosed abroad by whether born abroad or not for the 10-year period 2015 to 2024.
For UK-born heterosexuals, the number of new HIV diagnoses decreased by 39% from 64 in 2015 to 39 in 2024. For heterosexuals born abroad, the number of new HIV diagnoses increased by 91% from 80 in 2015 to 153 in 2024. The number of new HIV diagnoses in heterosexuals born abroad increased by 168% between 2021 and 2024.
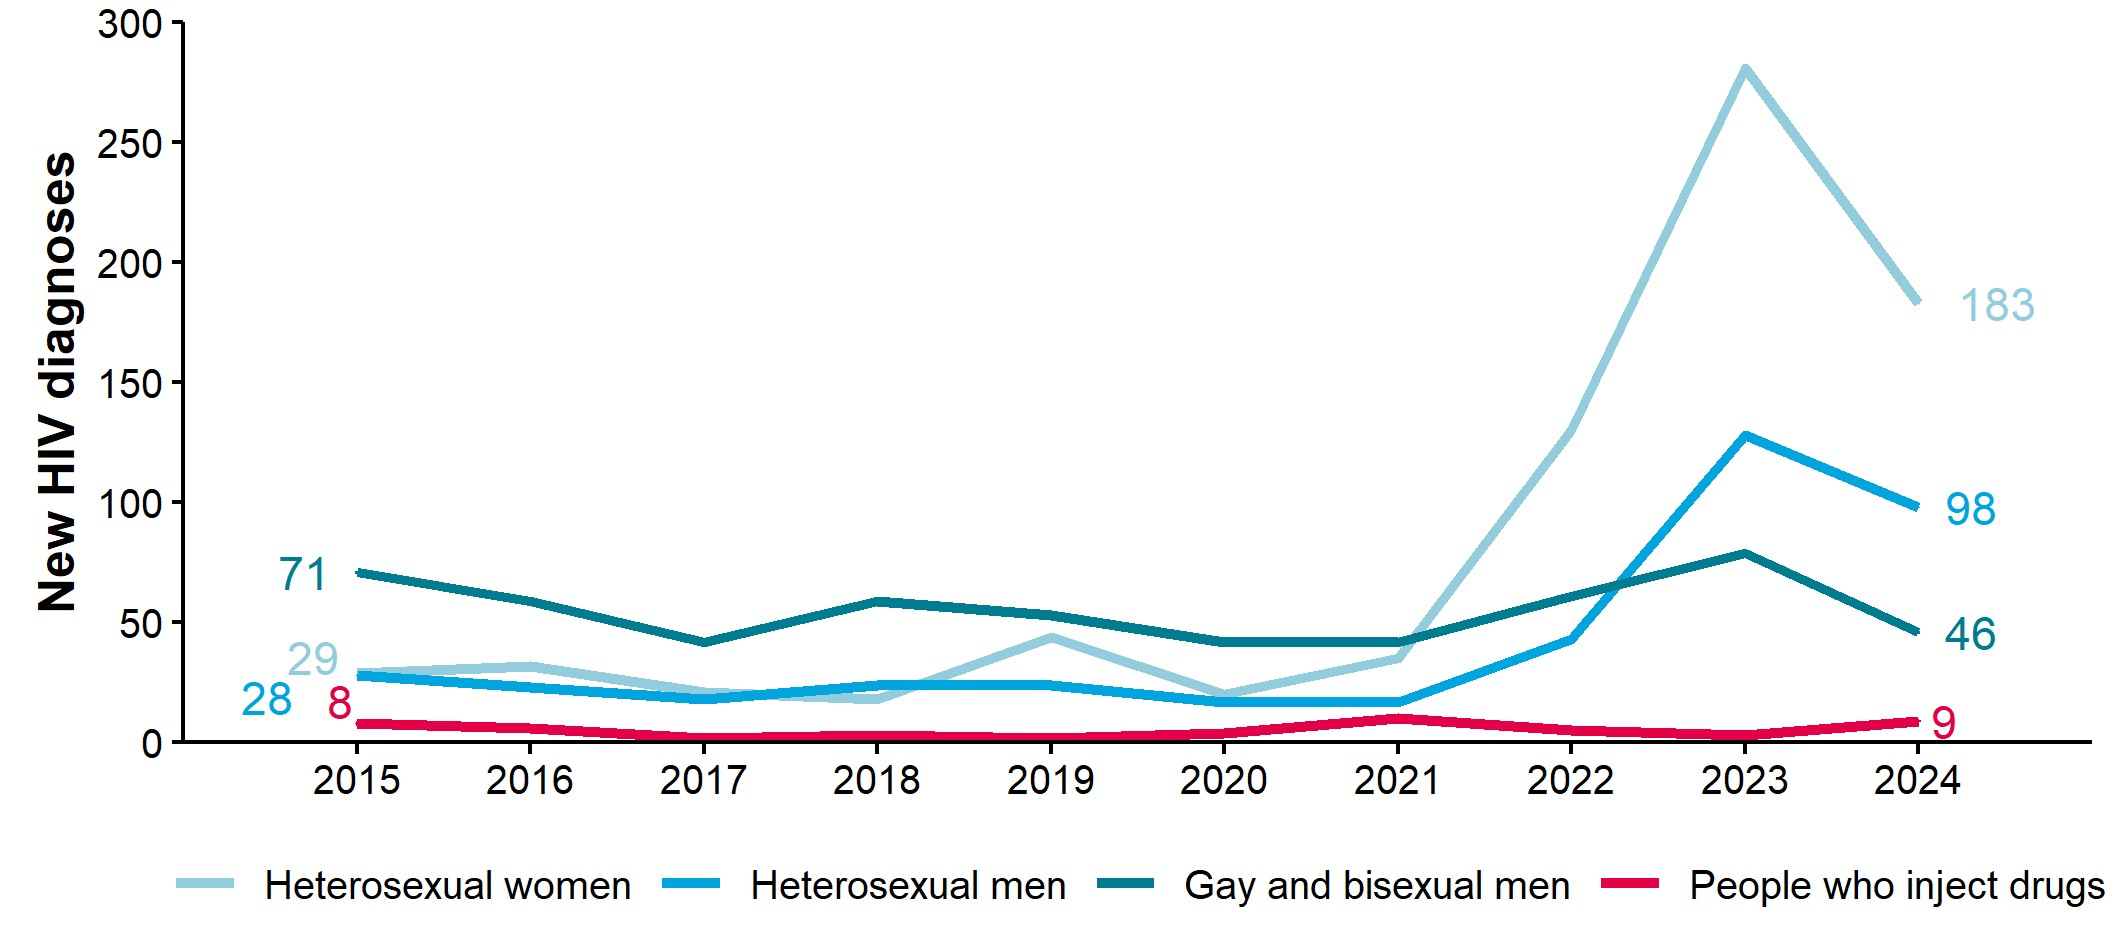
Figure 16. People diagnosed with HIV before continuing care in England by probable route of exposure, South East residents, 2015 to 2024 [note 1]
Sources: UKHSA, HANDD.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 16 is a line chart showing the number of people diagnosed with HIV before continuing care in England by probable route of exposure among South East residents for the 10-year period 2015 to 2024.
Between 2015 and 2024, the number of people diagnosed with HIV before continuing care in England increased for all groups apart from gay and bisexual men, where it decreased by 35% from 71 to 46. The number of people diagnosed with HIV before continuing care in England increased by 531% from 29 in 2015 to 183 in 2024 in heterosexual women, and by 250% from 28 to 98 in heterosexual men.
Between 2023 and 2024, the number of people diagnosed with HIV before continuing care in England decreased for all groups apart from people who inject drugs, where it increased by 200% from 3 to 9. The number of people diagnosed with HIV before continuing care in England decreased by 35% from 281 in 2023 to 183 in 2024 in heterosexual women, by 23% from 128 to 98 in heterosexual men, and by 42% from 79 to 46 in gay and bisexual men.
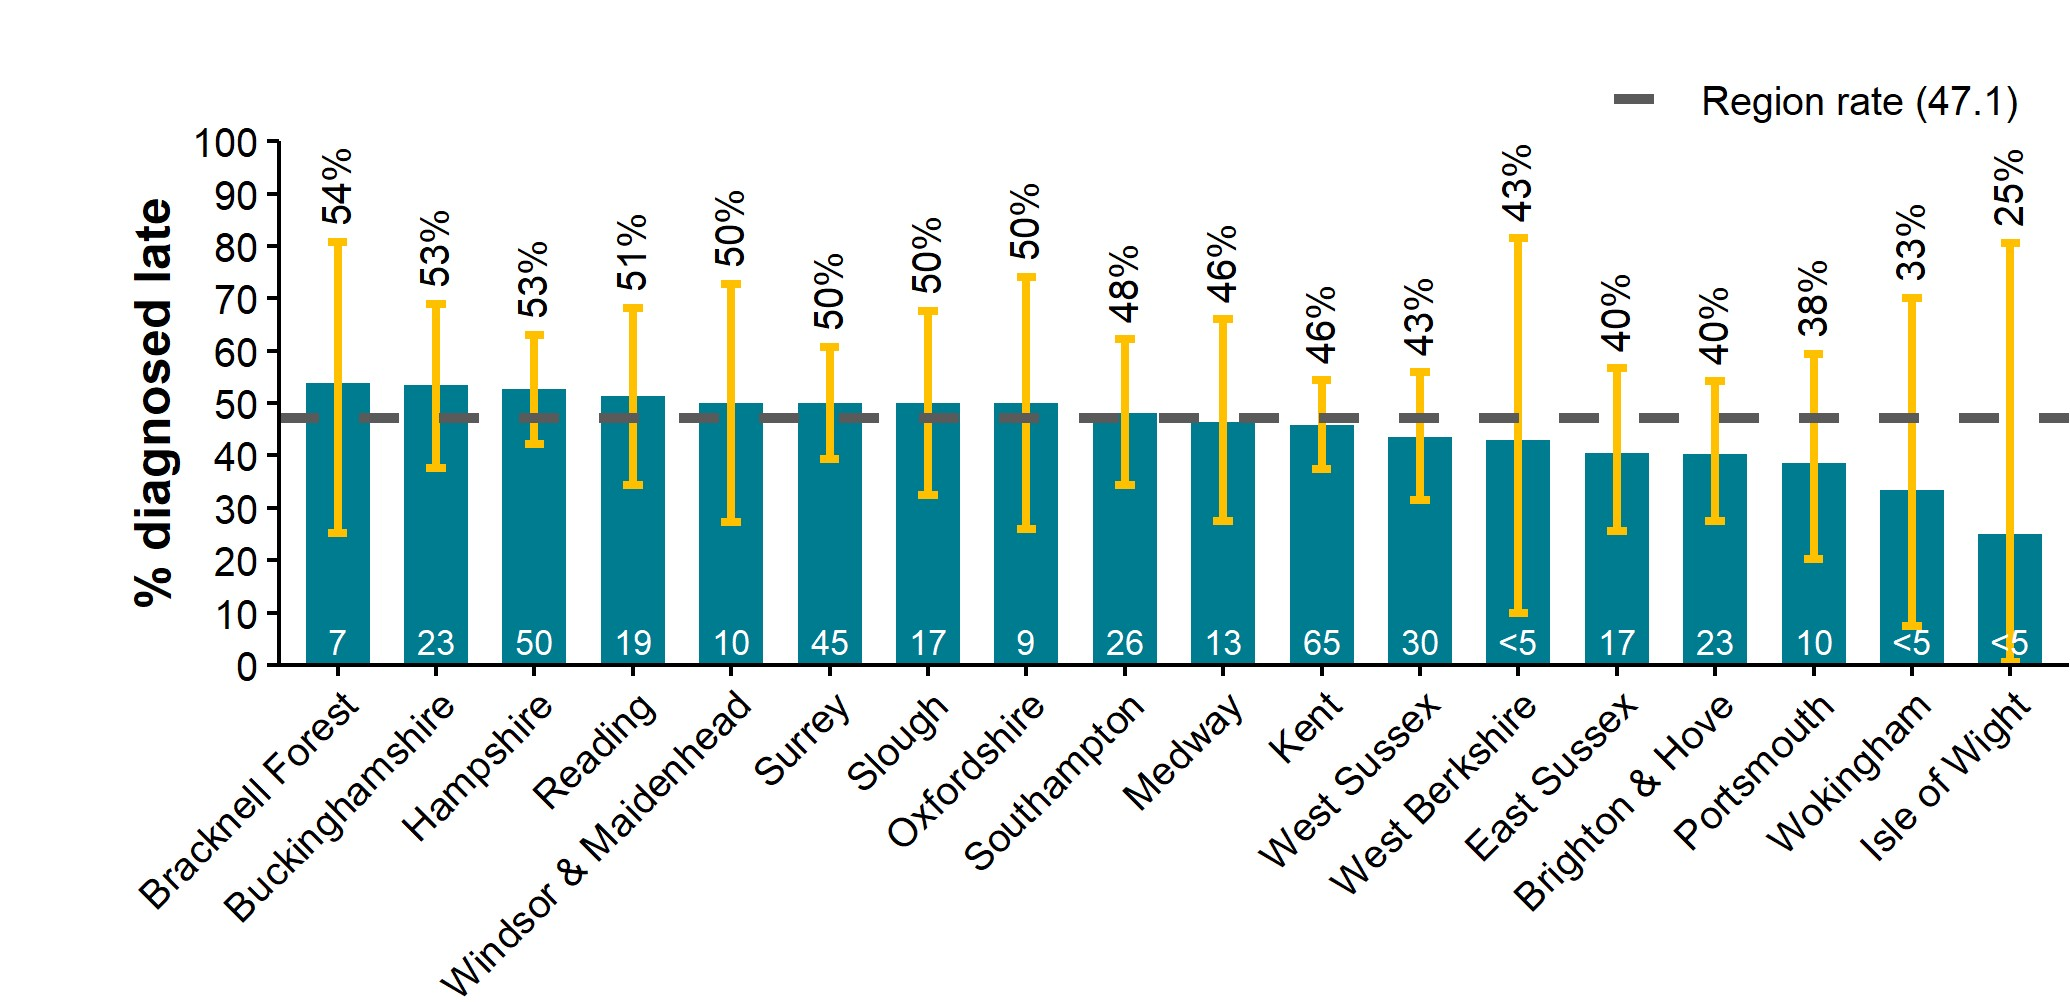
Figure 17. Percentage of new HIV diagnoses, by local authority of residence, that were diagnosed late, South East, aged 15 years and over, 2022 to 2024 [note 2]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
The number contained within each bar indicates the number of cases.
Note 2: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3. The underlying population will impact on the proportion diagnosed late, for example gay and bisexual men are less likely to be diagnosed late.
Figure 17 is a column chart showing the percentage of new HIV diagnoses that were diagnosed late in South East residents aged 15 years and over, by local authority, for the period 2022 to 2024. The dashed grey line shows the percentage of new HIV diagnoses that were diagnosed late for the South East as a whole. It is important to be aware that the percentages are sensitive to the geographical distribution of different exposure groups. Local authorities with higher proportions of gay and bisexual men tend to have a lower percentage of late diagnoses due to greater awareness of HIV and higher testing rates. In addition, confidence intervals are wide and tend to be wider for local authorities with fewer new HIV diagnoses.
The percentage of new HIV diagnoses that were diagnosed late in the South East was 47%. Bracknell Forest (54%), Buckinghamshire (53%), and Hampshire (53%) had the highest percentage of new HIV diagnoses that were diagnosed late. Isle of Wight (25%), Wokingham (33%), and Portsmouth (38%) had the lowest percentage of new HIV diagnoses that were diagnosed late.
Figure 18. Percentage and number of new HIV diagnoses by probable route of exposure that were diagnosed late, South East residents, aged 15 years and over, 2022 to 2024 [note 3]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 3: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3. Proportions are only shown for the gay and bisexual men, heterosexual men, heterosexual women, and injecting drug use exposure groups and are withheld for any of these categories if they contain fewer than 5 late diagnoses.
Figure 18 is a column chart showing the percentage and number of new HIV diagnoses estimated to have been made late by probable route of exposure in South East residents aged 15 years and over for the period 2022 to 2024.
Between 2022 and 2024, gay and bisexual men had the lowest percentage of new HIV diagnoses that were diagnosed late with 37% and heterosexual men had the highest percentage with 58%. Half of all new HIV diagnoses in heterosexual women and in people who inject drugs were diagnosed late. There are additional opportunities to be diagnosed via antenatal services for some women, and this may contribute partly to the difference in the proportion of late diagnoses between heterosexual men and women. The number of new HIV diagnoses in people who inject drugs is smaller and the confidence interval is much larger compared to the other groups.
Figure 19. Percentage and number of new HIV diagnoses by ethnic group that were diagnosed late, South East residents, aged 15 years and over, 2022 to 2024 [note 4]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 4: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3. Proportions are only shown for the White, Black African and Black Caribbean ethnic groups and are withheld for any of these ethnic group categories if they contain fewer than 5 late diagnoses. IPB means Indian/Pakistani/Bangladeshi.
Figure 19 is a column chart showing the percentage and number of new HIV diagnoses estimated to have been made late, by ethnic group, in South East residents aged 15 years and over for the period 2022 to 2024.
The Black African ethnic group and the Black Caribbean ethnic group had 49% and 46% of new HIV diagnoses that were diagnosed late, respectively, between 2022 and 2024. The confidence interval for the Black Caribbean group is much wider than for the other ethnic groups due to fewer diagnoses. The White ethnic group had 42% of new HIV diagnoses that were diagnosed late over the 3-year period.
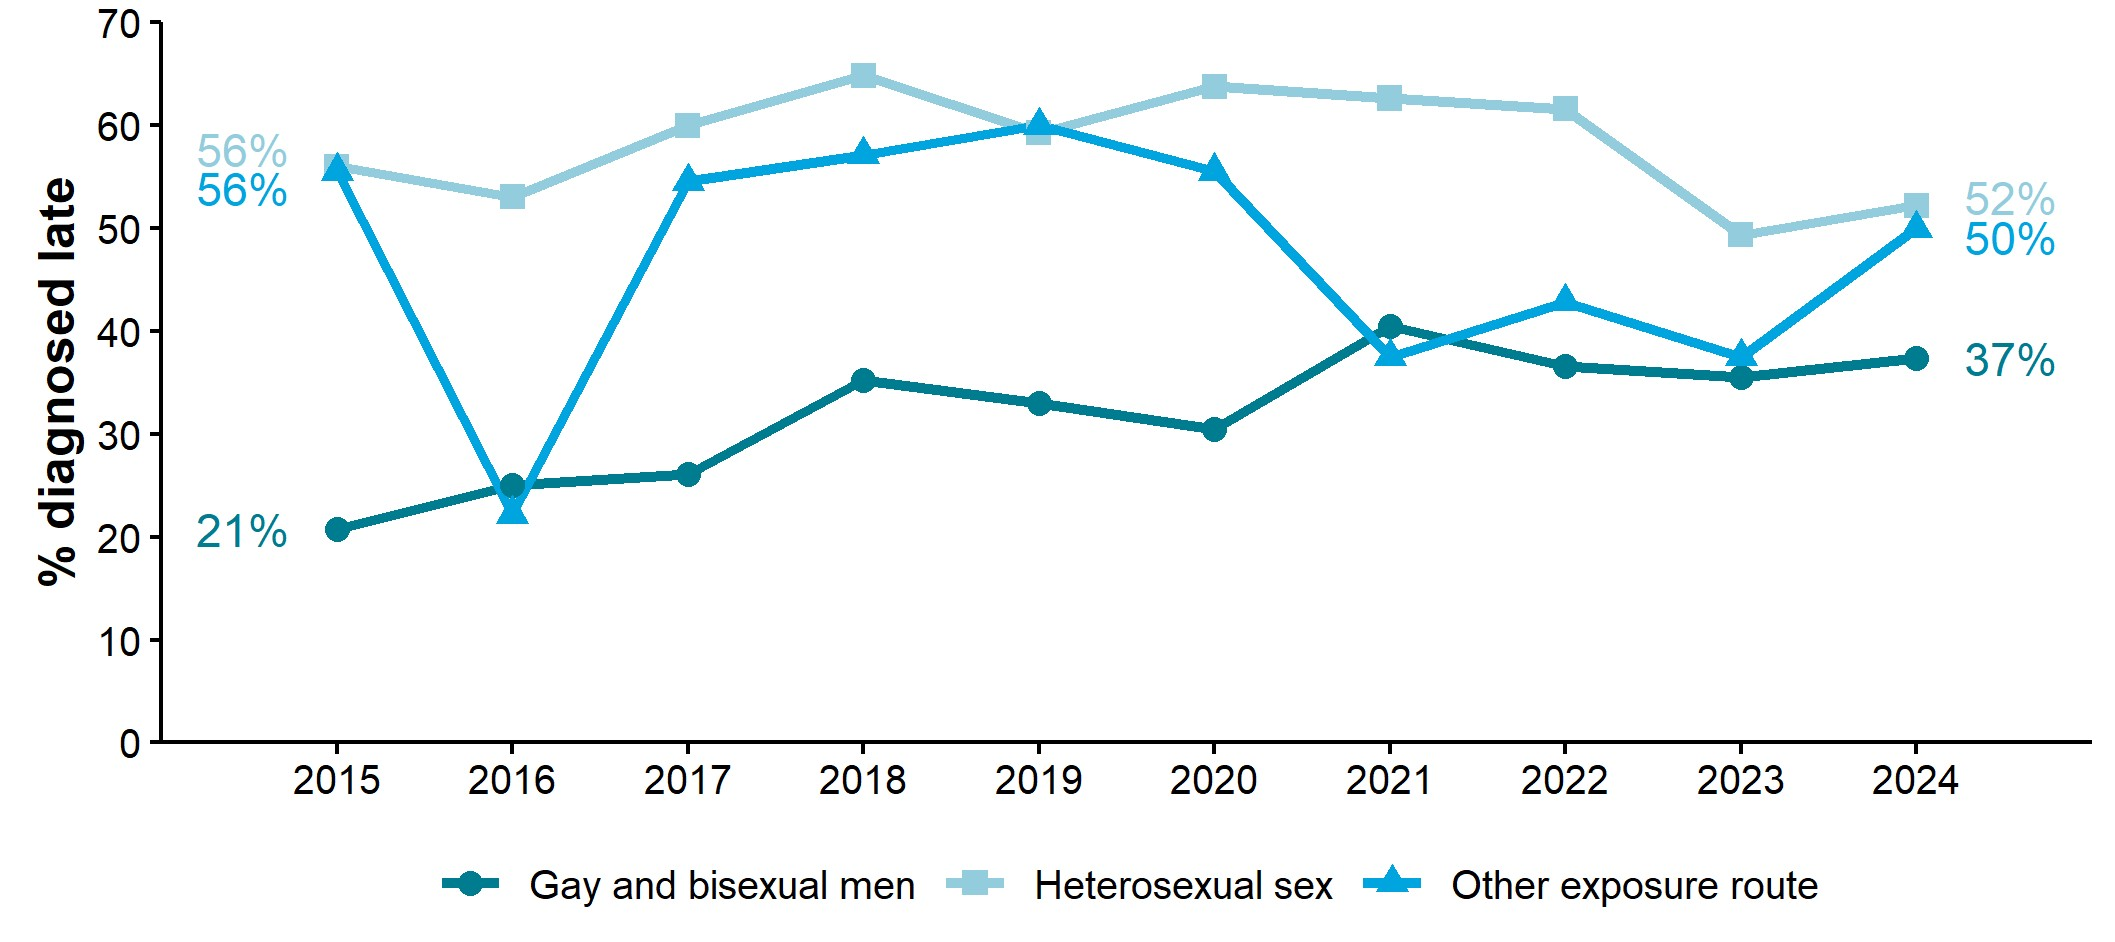
Figure 20. Percentage of new HIV diagnoses that were diagnosed late by probable route of exposure and year of first UK HIV diagnosis, South East residents, aged 15 years and over, 2015 to 2024 [note 5]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 20 is a line chart showing the percentage of new HIV diagnoses that were diagnosed late by probable route of exposure and year of first UK HIV diagnosis in South East residents aged 15 years and over between 2015 and 2024. Percentages in this chart can be less robust and should be interpreted as indicative of broad trends only as numbers in individual years may be small.
The percentage of new HIV diagnoses that were diagnosed late in gay and bisexual men increased from 21% in 2015 to 37% in 2024. The percentage of new HIV diagnoses that were diagnosed late decreased from 56% in 2015 to 50% for other exposure routes and from 56% to 52% for heterosexual sex as the route of exposure.
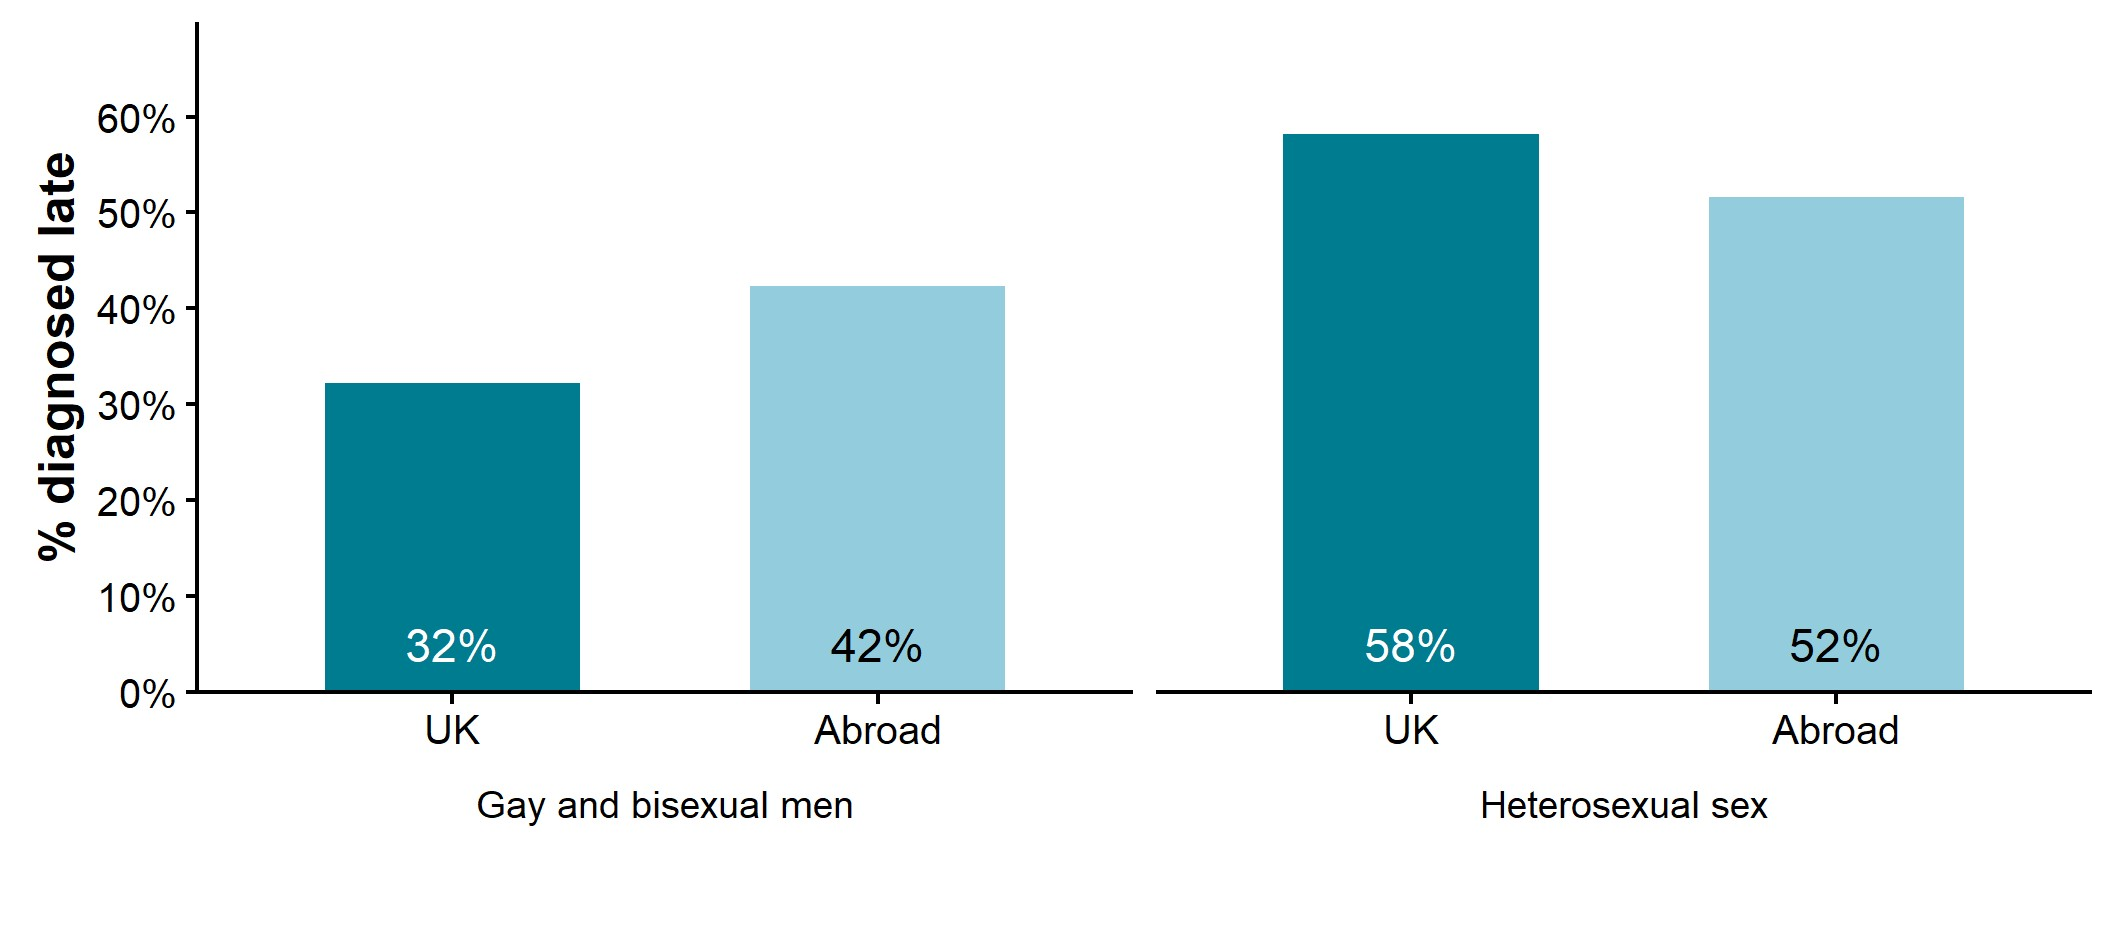
Figure 21. Percentage of new HIV diagnoses that were diagnosed late in gay and bisexual men and heterosexuals by whether born abroad, South East residents, aged 15 years and over, 2022 to 2024 [note 5]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 21 is a column chart showing the percentage of new HIV diagnoses that were diagnosed late by whether born in the UK or abroad, for gay and bisexual men and heterosexuals among South East residents aged 15 years and over, between 2022 and 2024.
Of new HIV diagnoses in gay and bisexual men, 32% of diagnoses were estimated to have been made late in those born in the UK and 42% in those born abroad. Of new HIV diagnoses in heterosexuals, 58% of diagnoses were estimated to have been made late in those born in the UK and 52% in those born abroad.
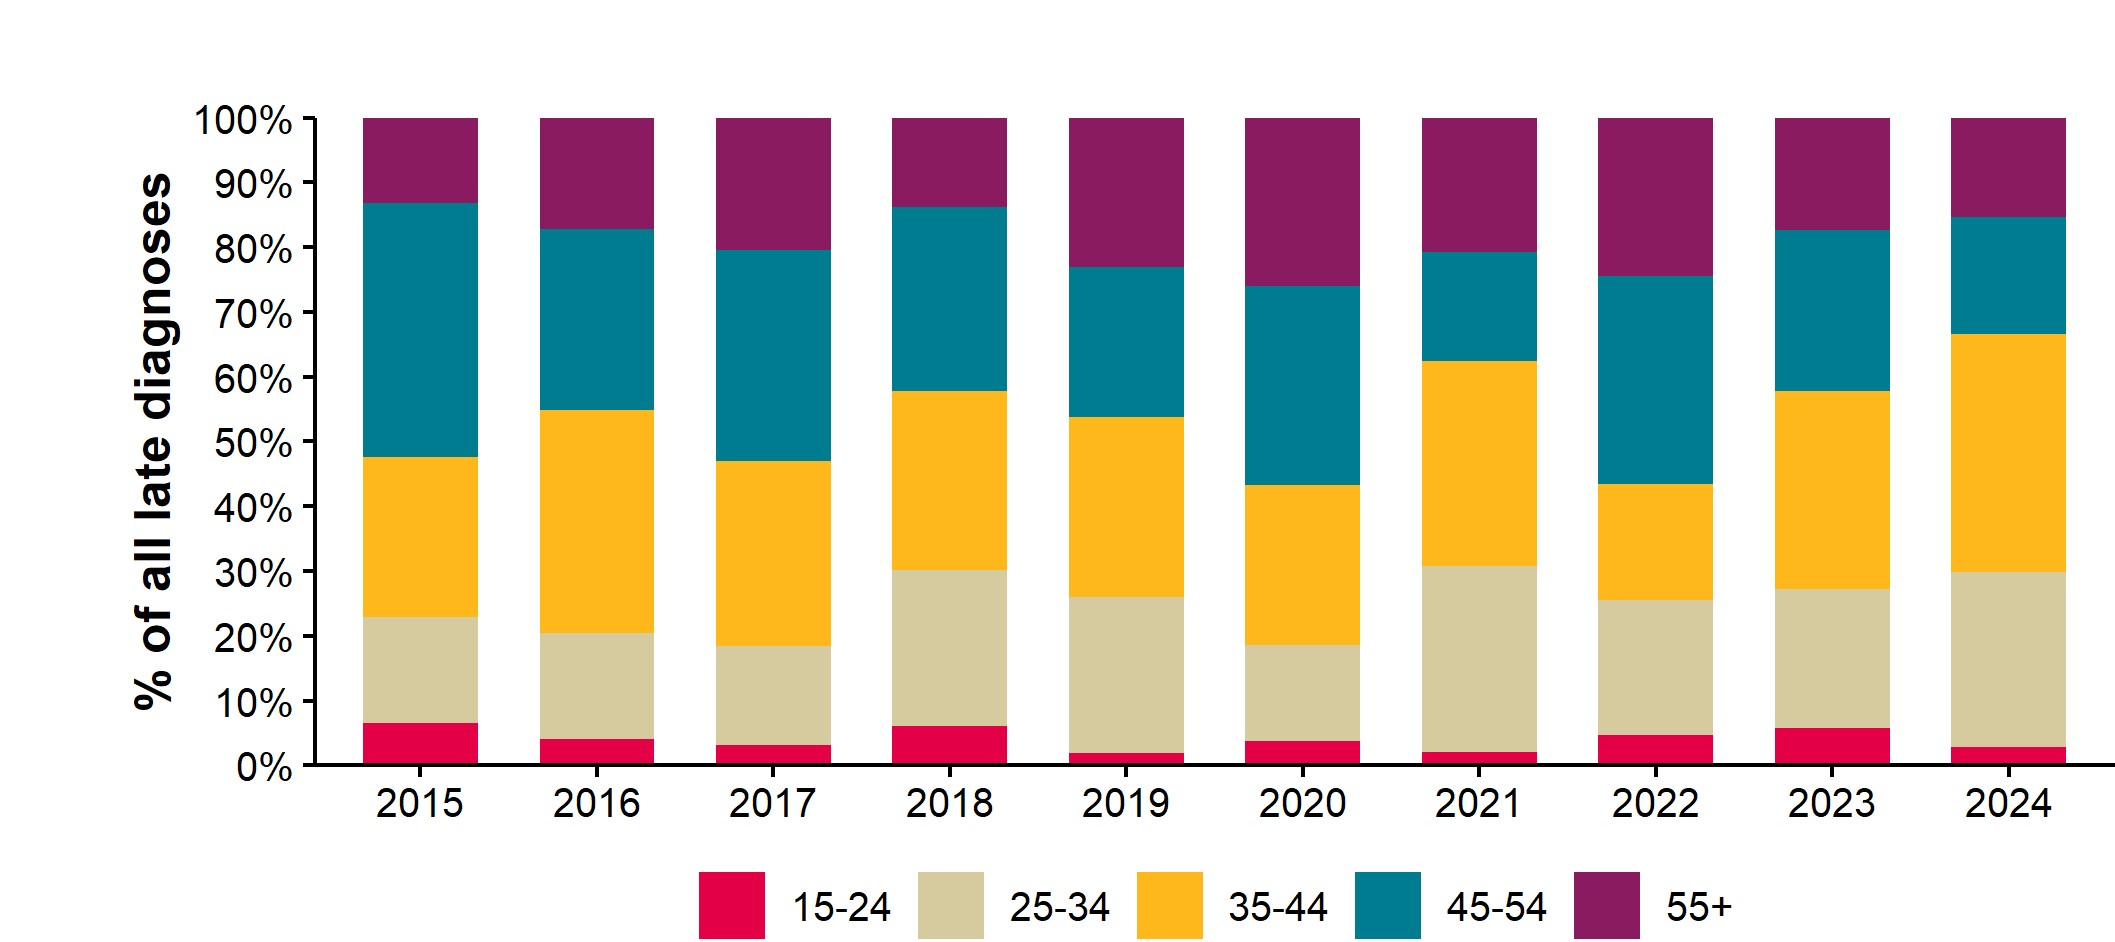
Figure 22. Age distribution of new HIV diagnoses that were diagnosed late by year of first HIV diagnosis, South East residents, aged 15 years and over, 2015 to 2024 [note 5]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 22 is a column chart showing the percentage of new HIV diagnoses estimated to have been made late, by age group and year of first HIV diagnosis, in South East residents aged 15 years and over, between 2015 and 2024. Unlike the previous charts showing new HIV diagnoses that were diagnosed late, the percentages in this chart indicate the proportion of late diagnoses by age group rather than showing the proportion of all new HIV diagnoses that were diagnosed late. Percentages in this chart are less robust and should be interpreted as indicative of broad trends only as they are by single year and numbers may be small when broken down by age group.
Those aged 15 to 24 years accounted for the smallest proportion of late diagnoses in each year over the 10-year period. In 2024, those aged 35 to 44 years represented the largest proportion of late diagnoses, followed by those aged 25 to 34 years and those aged 45 to 54 years. Those aged 55 years and above represented the second smallest proportion.
The 15 to 24, 45 to 64, and 55 and older age groups had a lower percentage of new HIV diagnoses that were diagnosed late in 2024 compared to 2023, while the 25 to 34, and 35 to 44 age groups had a higher percentage of new HIV diagnoses diagnosed late.
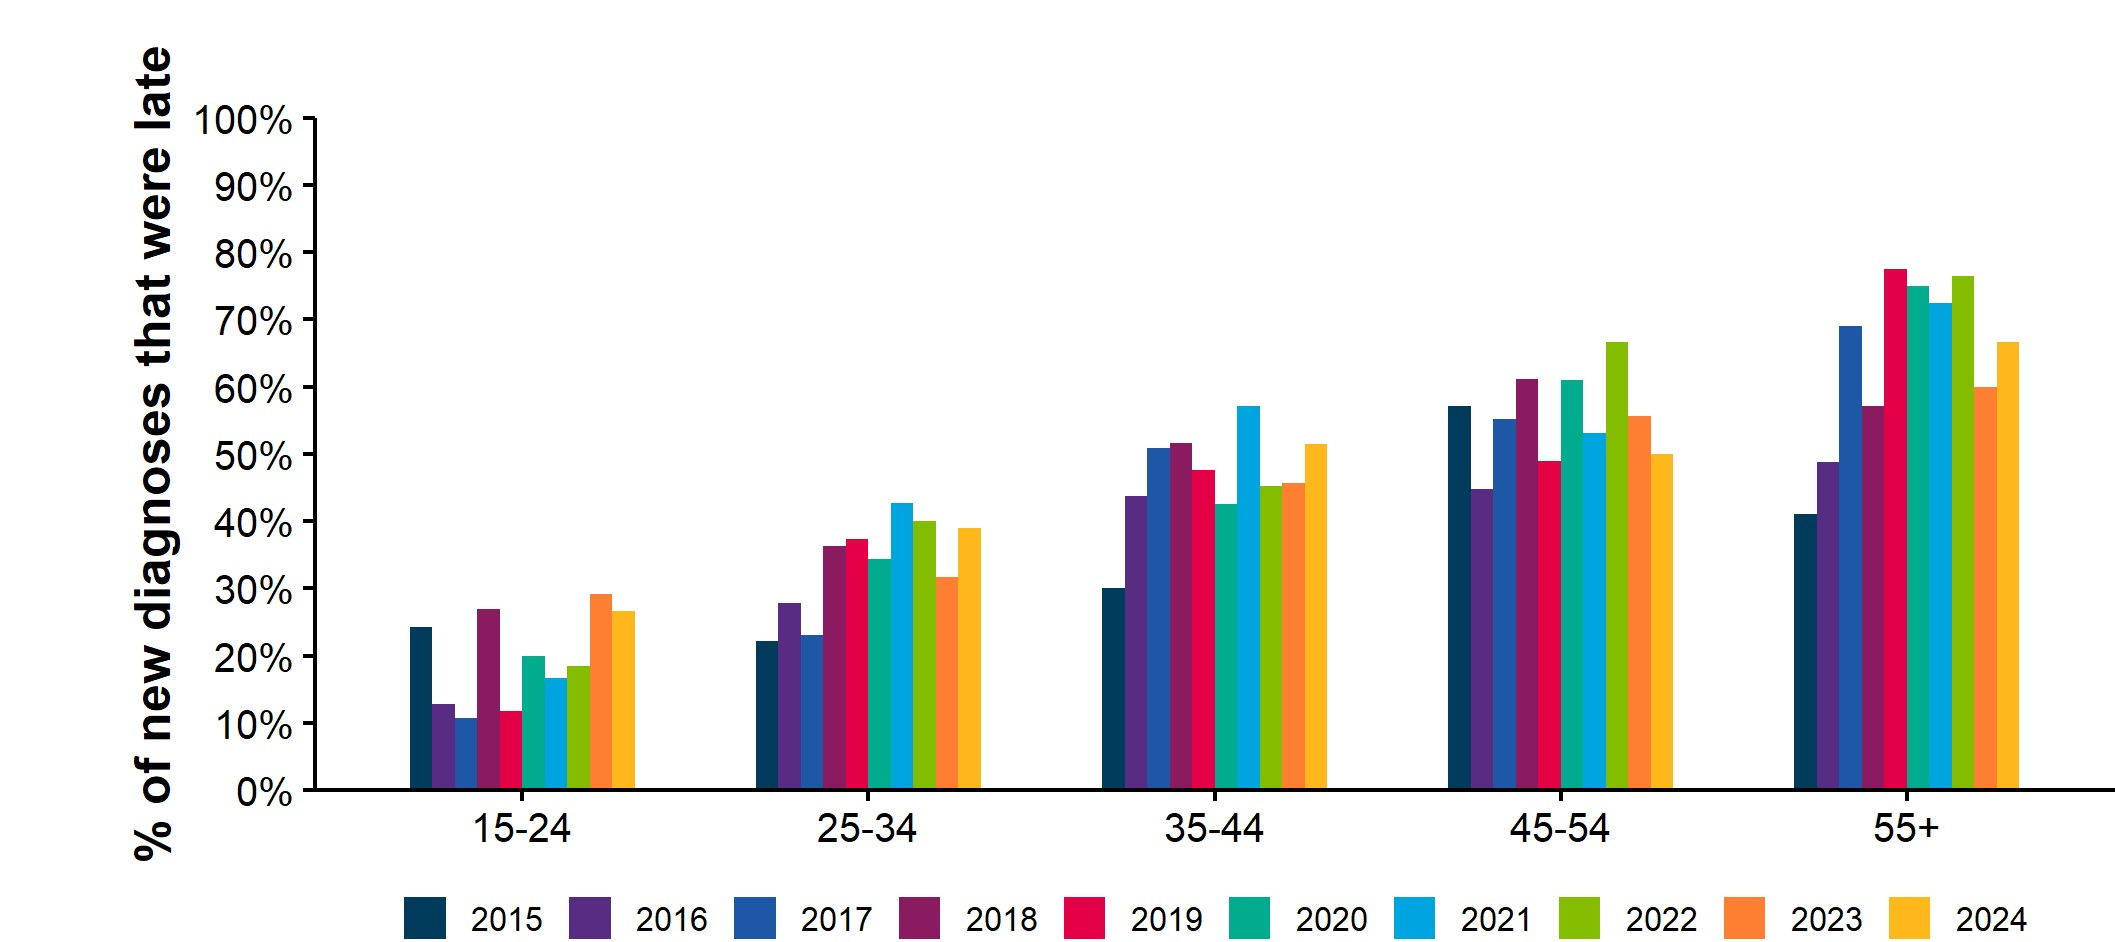
Figure 23. Percentage of all new diagnoses that were late by age by year of first HIV diagnosis, South East residents, aged 15 years and over, 2015 to 2024 [note 5]
Sources: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 23 is a column chart showing the percentage of new HIV diagnoses that were diagnosed late, by age group and year of first HIV diagnosis, in South East residents aged 15 years and over, between 2015 and 2024. Percentages in this chart are less robust and should be interpreted as indicative of broad trends only as they are by single year and numbers may be small when broken down by age group.
All age groups showed some fluctuation over the 10-year period. The older age groups tended to have a higher percentage of new HIV diagnoses diagnosed late. Compared to 2015, all age groups had a higher percentage of new HIV diagnoses diagnosed late in 2024 apart from the 45 to 54 age group.
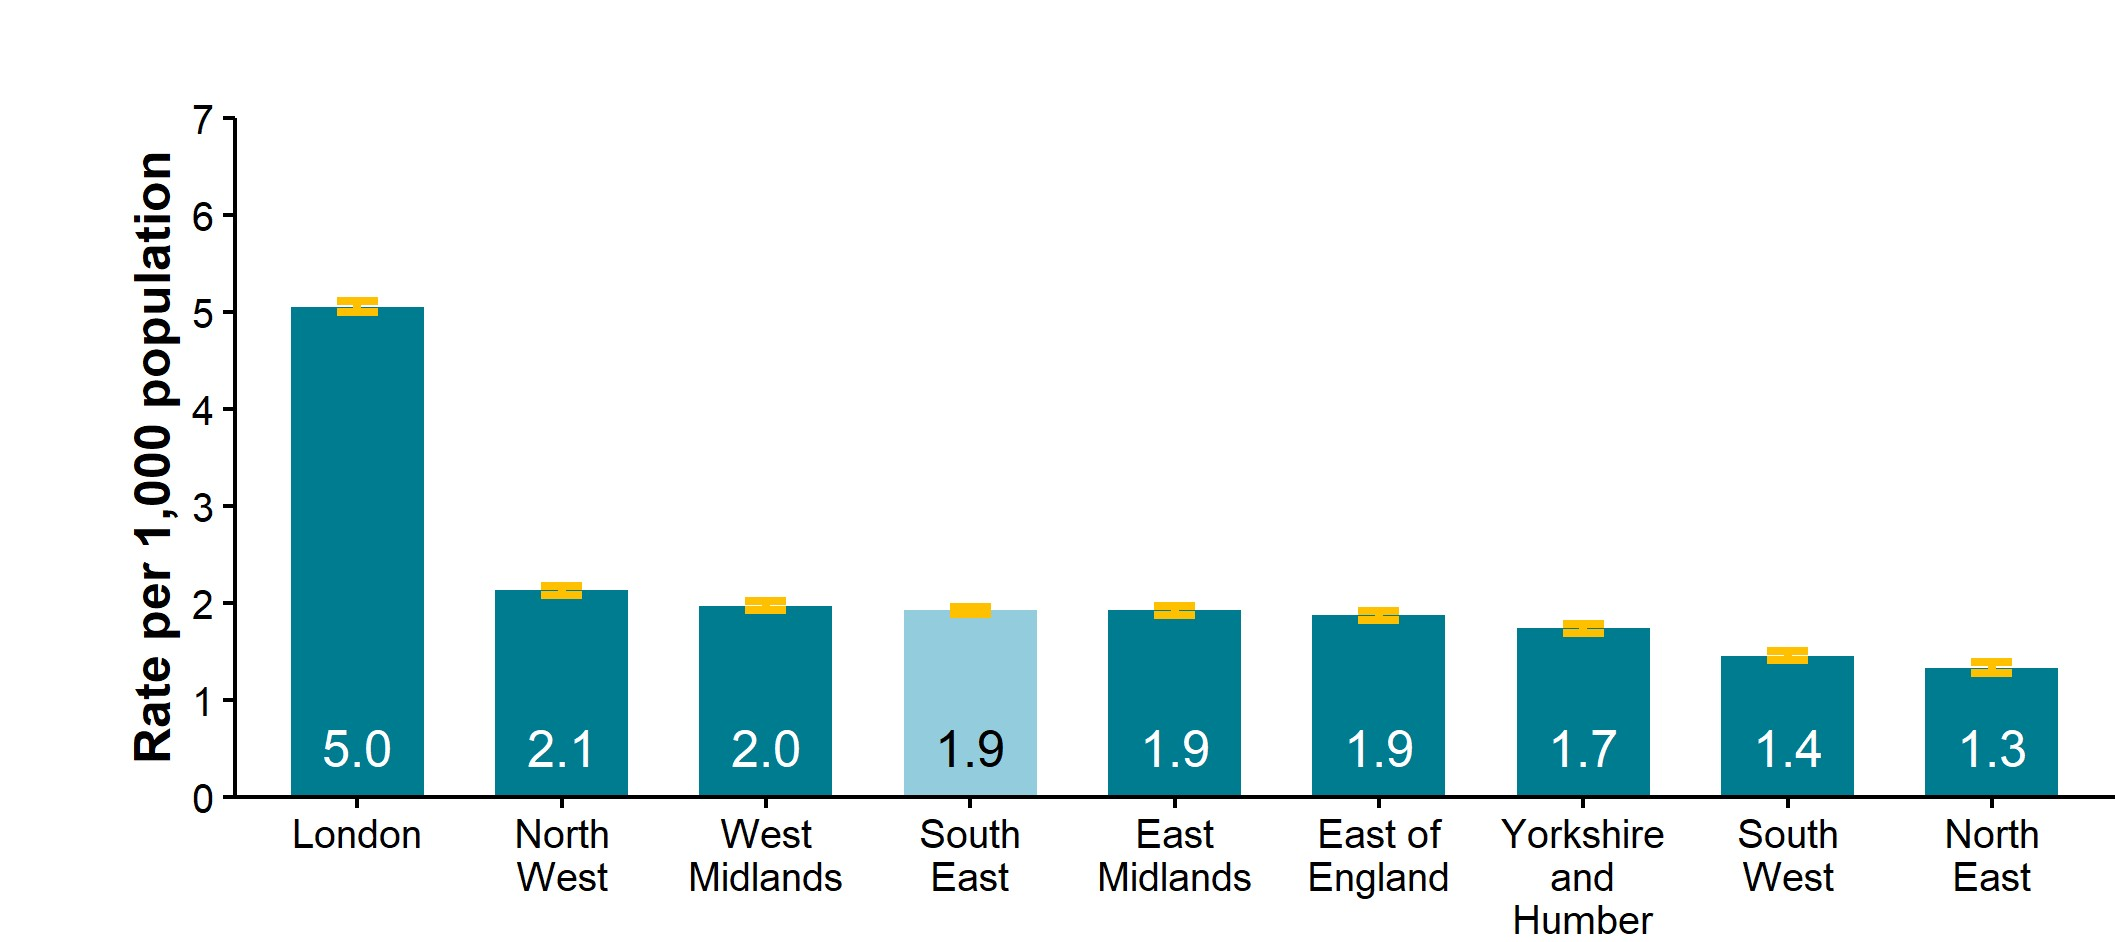
Figure 24. Diagnosed HIV prevalence per 1,000 residents aged 15 to 59 years by UKHSA region, 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 24 is a column chart showing the prevalence of diagnosed HIV as a rate per 1,000 residents aged 15 to 59 years by UKHSA region in 2024.
The South East had the fourth highest prevalence of diagnosed HIV (1.9 diagnoses per 1,000 residents aged 15 to 59). London had the highest prevalence (5.0), followed by the North West (2.1), and the West Midlands (2.0). The North East had the lowest prevalence of diagnosed HIV (1.3), and the South West had the second lowest prevalence (1.4).
Figure 25. Number of residents living with diagnosed HIV (all ages) and accessing care, the South East, 2015 to 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 25 is a line chart showing the number of South East residents living with diagnosed HIV and accessing HIV-related care between 2015 and 2024. That includes individuals first diagnosed abroad and continuing care in England. This number acts as a proxy for the number of people living with diagnosed HIV as everyone living with diagnosed HIV in the UK can access care for free.
The line reflects changes in new HIV diagnoses, mortality in those living with diagnosed HIV, and immigration patterns. The number may also have been affected by disruptions to care and changes in residence during the main COVID-19 pandemic year 2020. The number of residents living with HIV and accessing care increased from 9,627 in 2015 to 13,152 in 2024. This represents a 37% increase over the 10-year period. The number has increased steadily year-on-year, apart from a small reduction in 2020.
Figure 26. Number of residents living with diagnosed HIV and accessing care by probable route of exposure (adjusted for missing route information), the South East, 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 26 is a column chart showing the number of South East residents living with diagnosed HIV and accessing HIV-related care by probable route of exposure in 2024. The columns are arranged in descending order with regards to the number of residents diagnosed with HIV.
In 2024, the most common probable route of exposure among South East residents living with diagnosed HIV and accessing HIV-related care was heterosexual sex (6,544), followed by gay and bisexual men (6,072). 248 South East residents were probably exposed to HIV vertically, through mother to child transmission (before or at birth or via breastfeeding), 162 were probably exposed to HIV through injecting drug use, and 126 were probably exposed through blood products or as a healthcare worker.
Figure 27. Percentage of all residents with diagnosed HIV who are accessing care, by age group contribution, the South East, 2015 and 2024
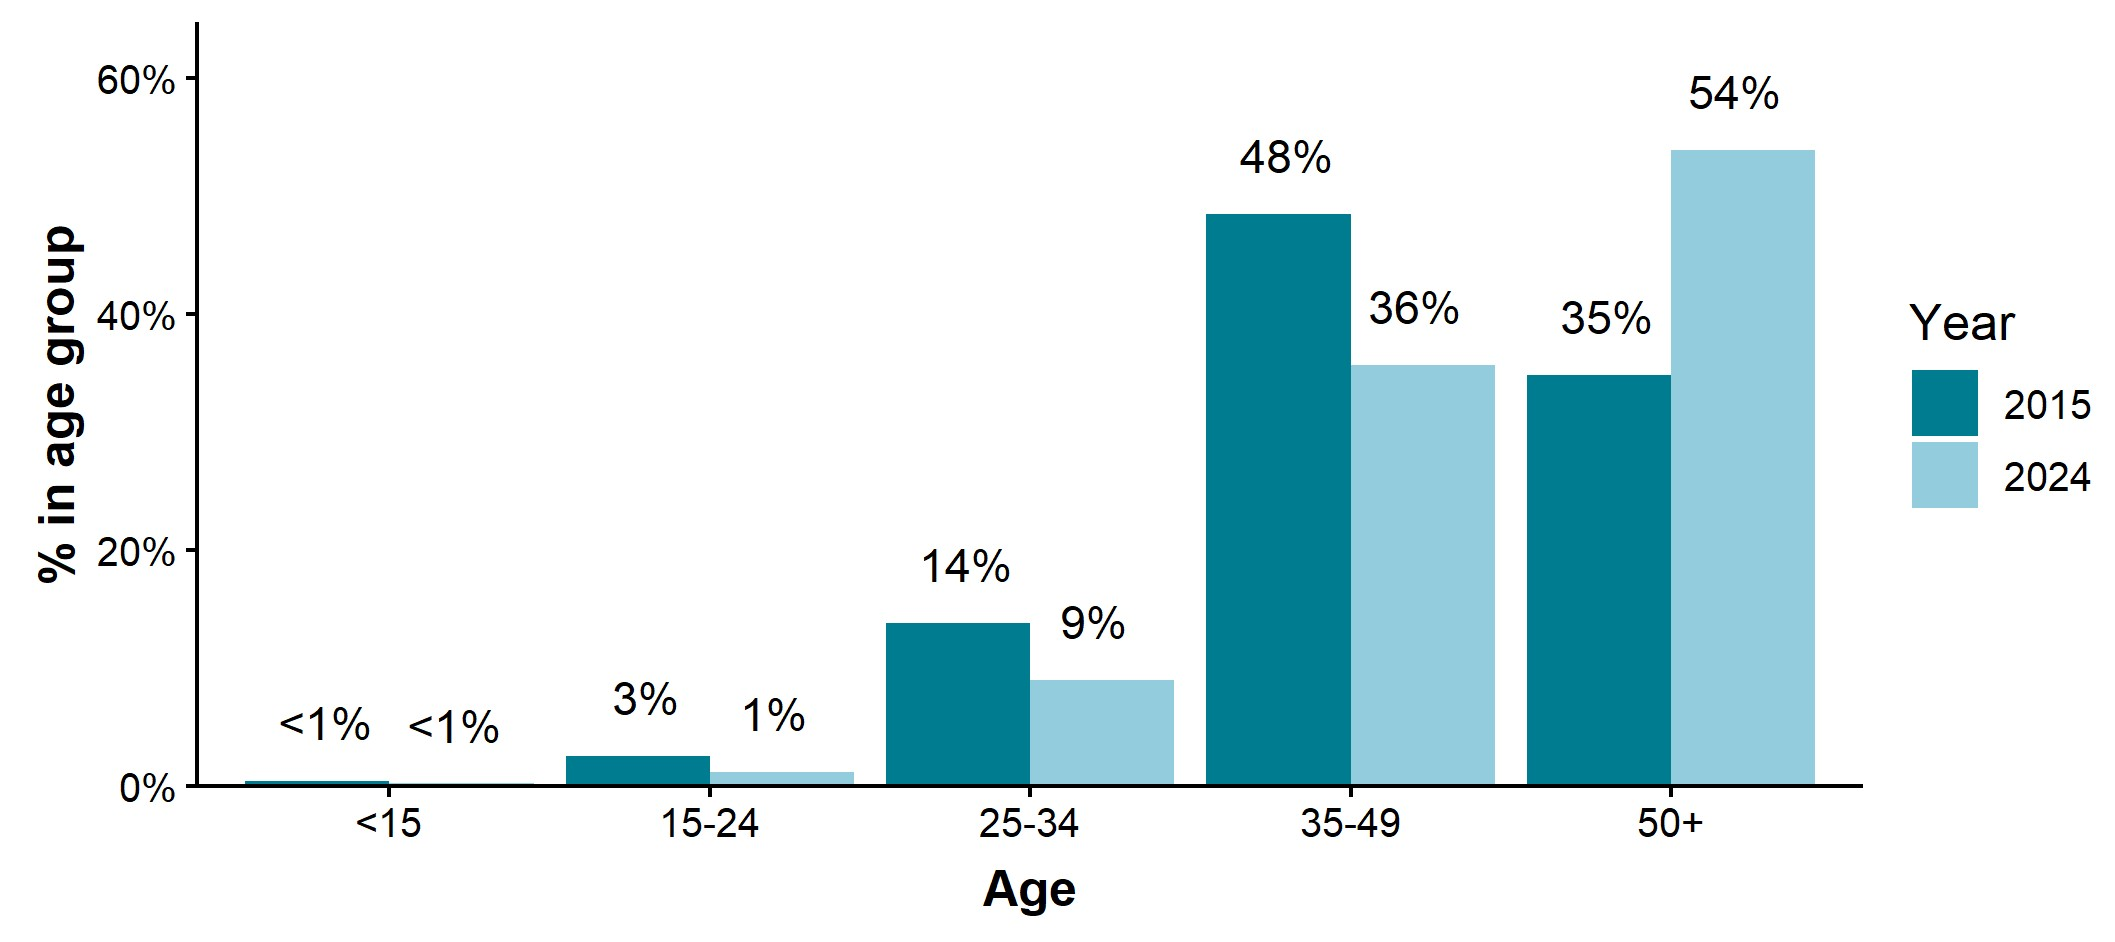
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 27 is a column chart showing the percentage of South East residents living with diagnosed HIV and accessing HIV-related care by age group in 2015 and 2024.
In 2015, the 35 to 49 year age group was the largest and accounted for 48% of people diagnosed and living with HIV. In 2024, the 50 years and older age group was the largest and accounted for 54% of people diagnosed and living with HIV. The 10-year comparison shows an ageing cohort as only the 50 years and over age group experienced an increase. Due to decreased transmission, fewer people acquire HIV, and due to effective treatment, fewer people diagnosed and living with HIV die prematurely.
Figure 28. Diagnosed HIV prevalence per 1,000 residents by ethnic group (all ages), the South East, 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 28 is a column chart showing the prevalence of diagnosed HIV as a rate per 1,000 South East residents in 2024. The data for this chart is not age-standardised and is thus sensitive to differences in age distribution. The columns are arranged in descending order with regards to the prevalence of diagnosed HIV.
The ethnic group with the highest prevalence was the Black African ethnic group (29.7 diagnoses per 1,000 residents), followed by the Other Black and unspecified ethnic group (12.8), the Black Caribbean ethnic group (4.7), and the Other and mixed ethnic group (2.3). The ethnic groups with the lowest prevalence were the Asian ethnic group (0.9 diagnoses per 1,000 residents) and the White ethnic group (0.9).
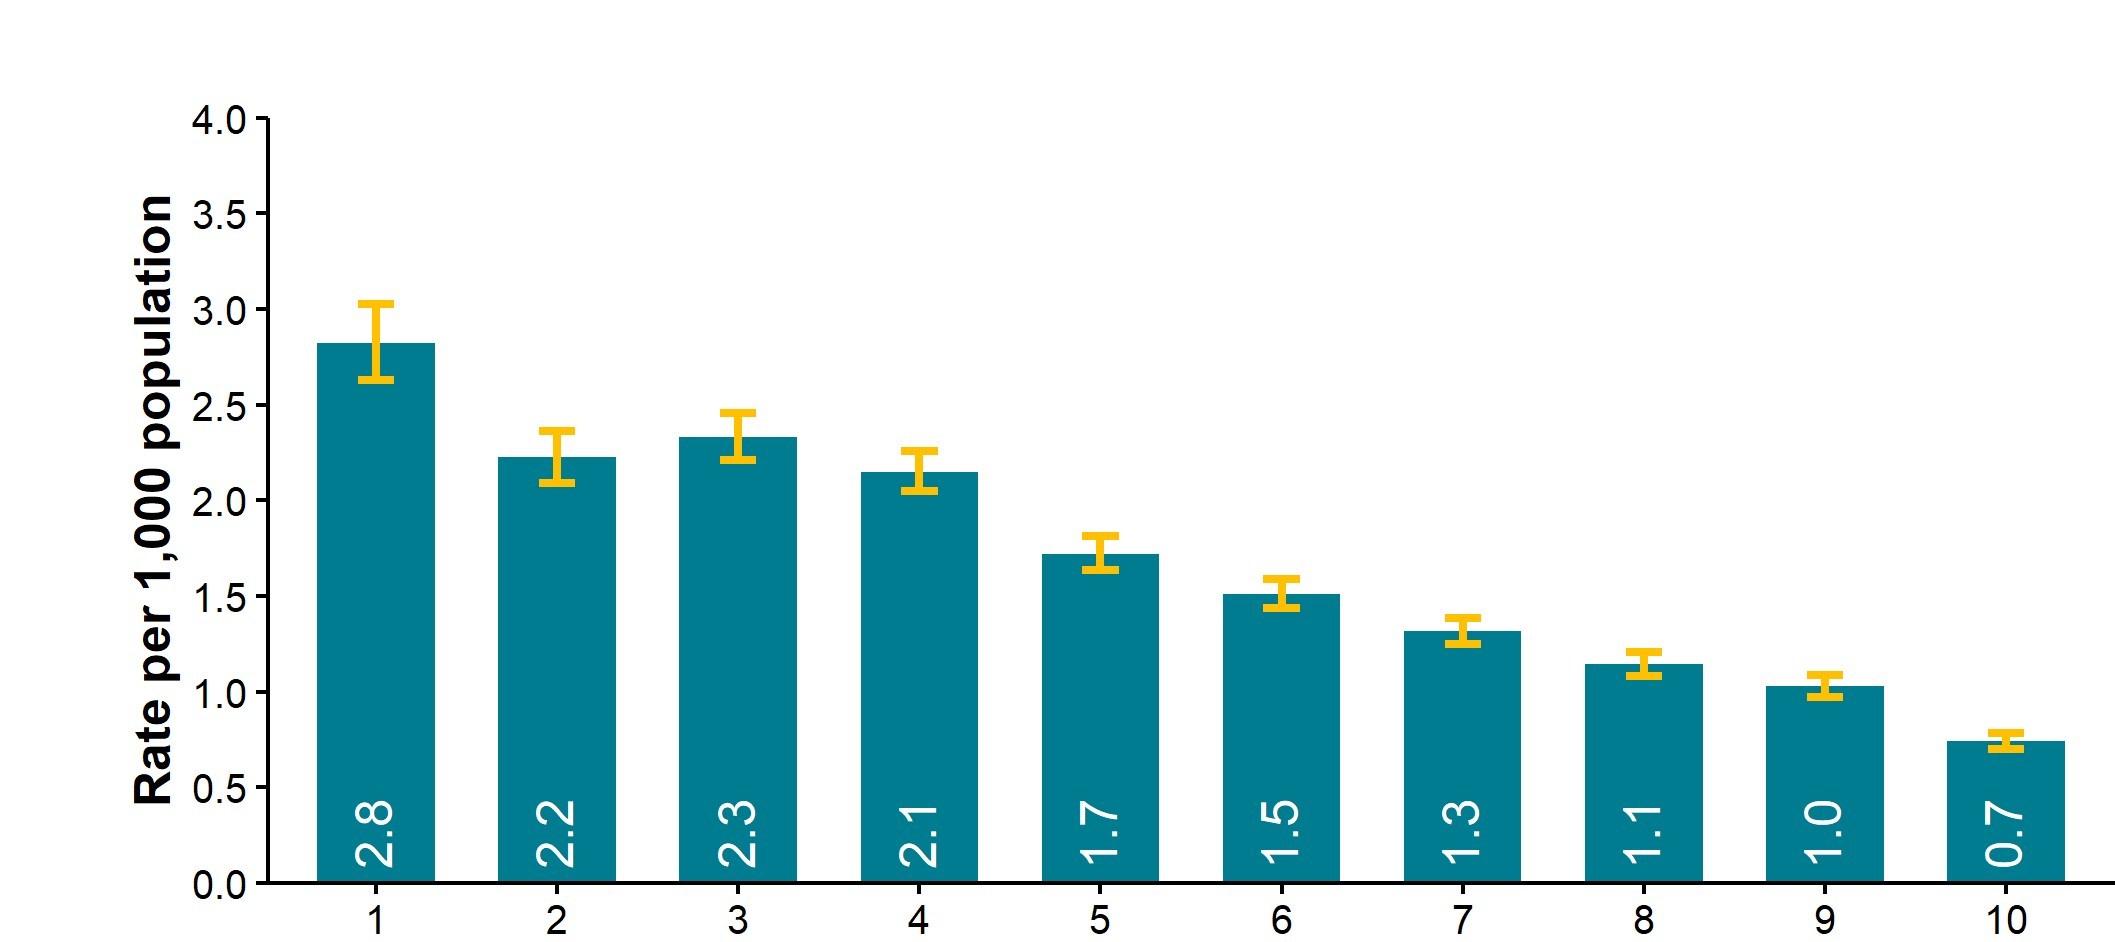
Figure 29. Diagnosed HIV prevalence per 1,000 population by Index of Multiple Deprivation decile, the South East, 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 29 is a column chart showing the prevalence of diagnosed HIV per 1,000 South East residents by Index of Multiple Deprivation (IMD) decile in 2024. The deciles are calculated for England as a whole and use lower super output area (LSOA) of residence. The data for this chart is not age-standardised and is thus sensitive to differences in age distribution.
The diagnosed prevalence was significantly higher for the more deprived areas and lower for the less deprived areas. The rate was 2.8 for IMD decile 1 (most deprived) and 0.7 for IMD decile 10 (least deprived). While not everyone who lives in an area of higher deprivation may be deprived, the differences in prevalence suggest that people living with diagnosed HIV are also at higher risk of additional stressors such as financial pressures. For some people this may have an impact on their ability to access HIV-related care and other services.
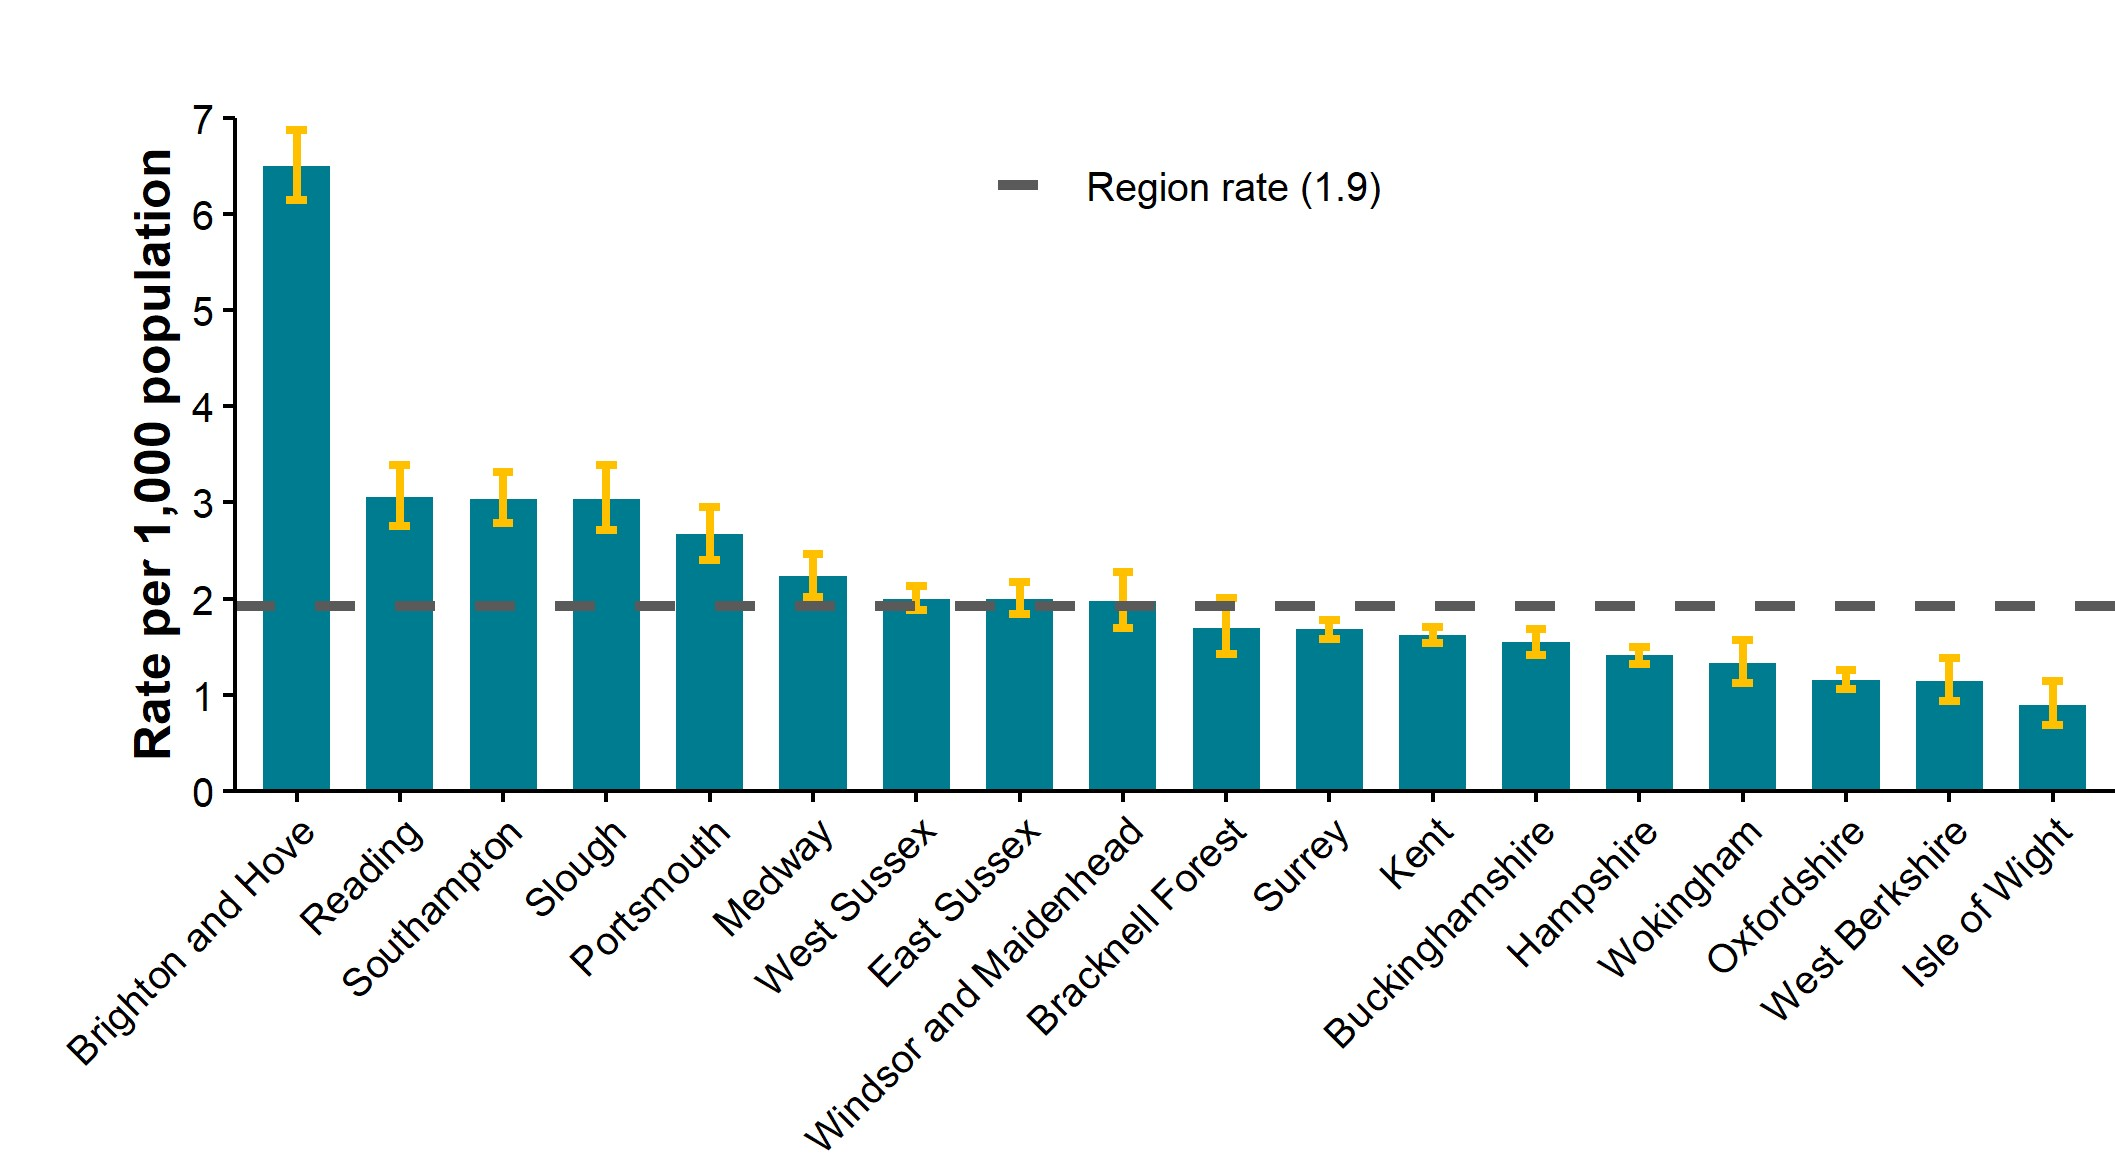
Figure 30. Diagnosed HIV prevalence per 1,000 residents aged 15 to 59 years by local authority, the South East, 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 30 is a column chart showing the prevalence of diagnosed HIV per 1,000 South East residents aged 15 to 59 years by local authority in 2024.
The local authority with the highest rate was Brighton and Hove (6.5 diagnoses per 1,000 residents aged 15 to 59 years), with more than twice the rate of the local authority with the second highest rate, Reading (3.1). The local authority with the lowest rate was Isle of Wight (0.9 diagnoses per 1,000 residents aged 15 to 59 years), followed by West Berkshire (1.1) and Oxfordshire (1.2).
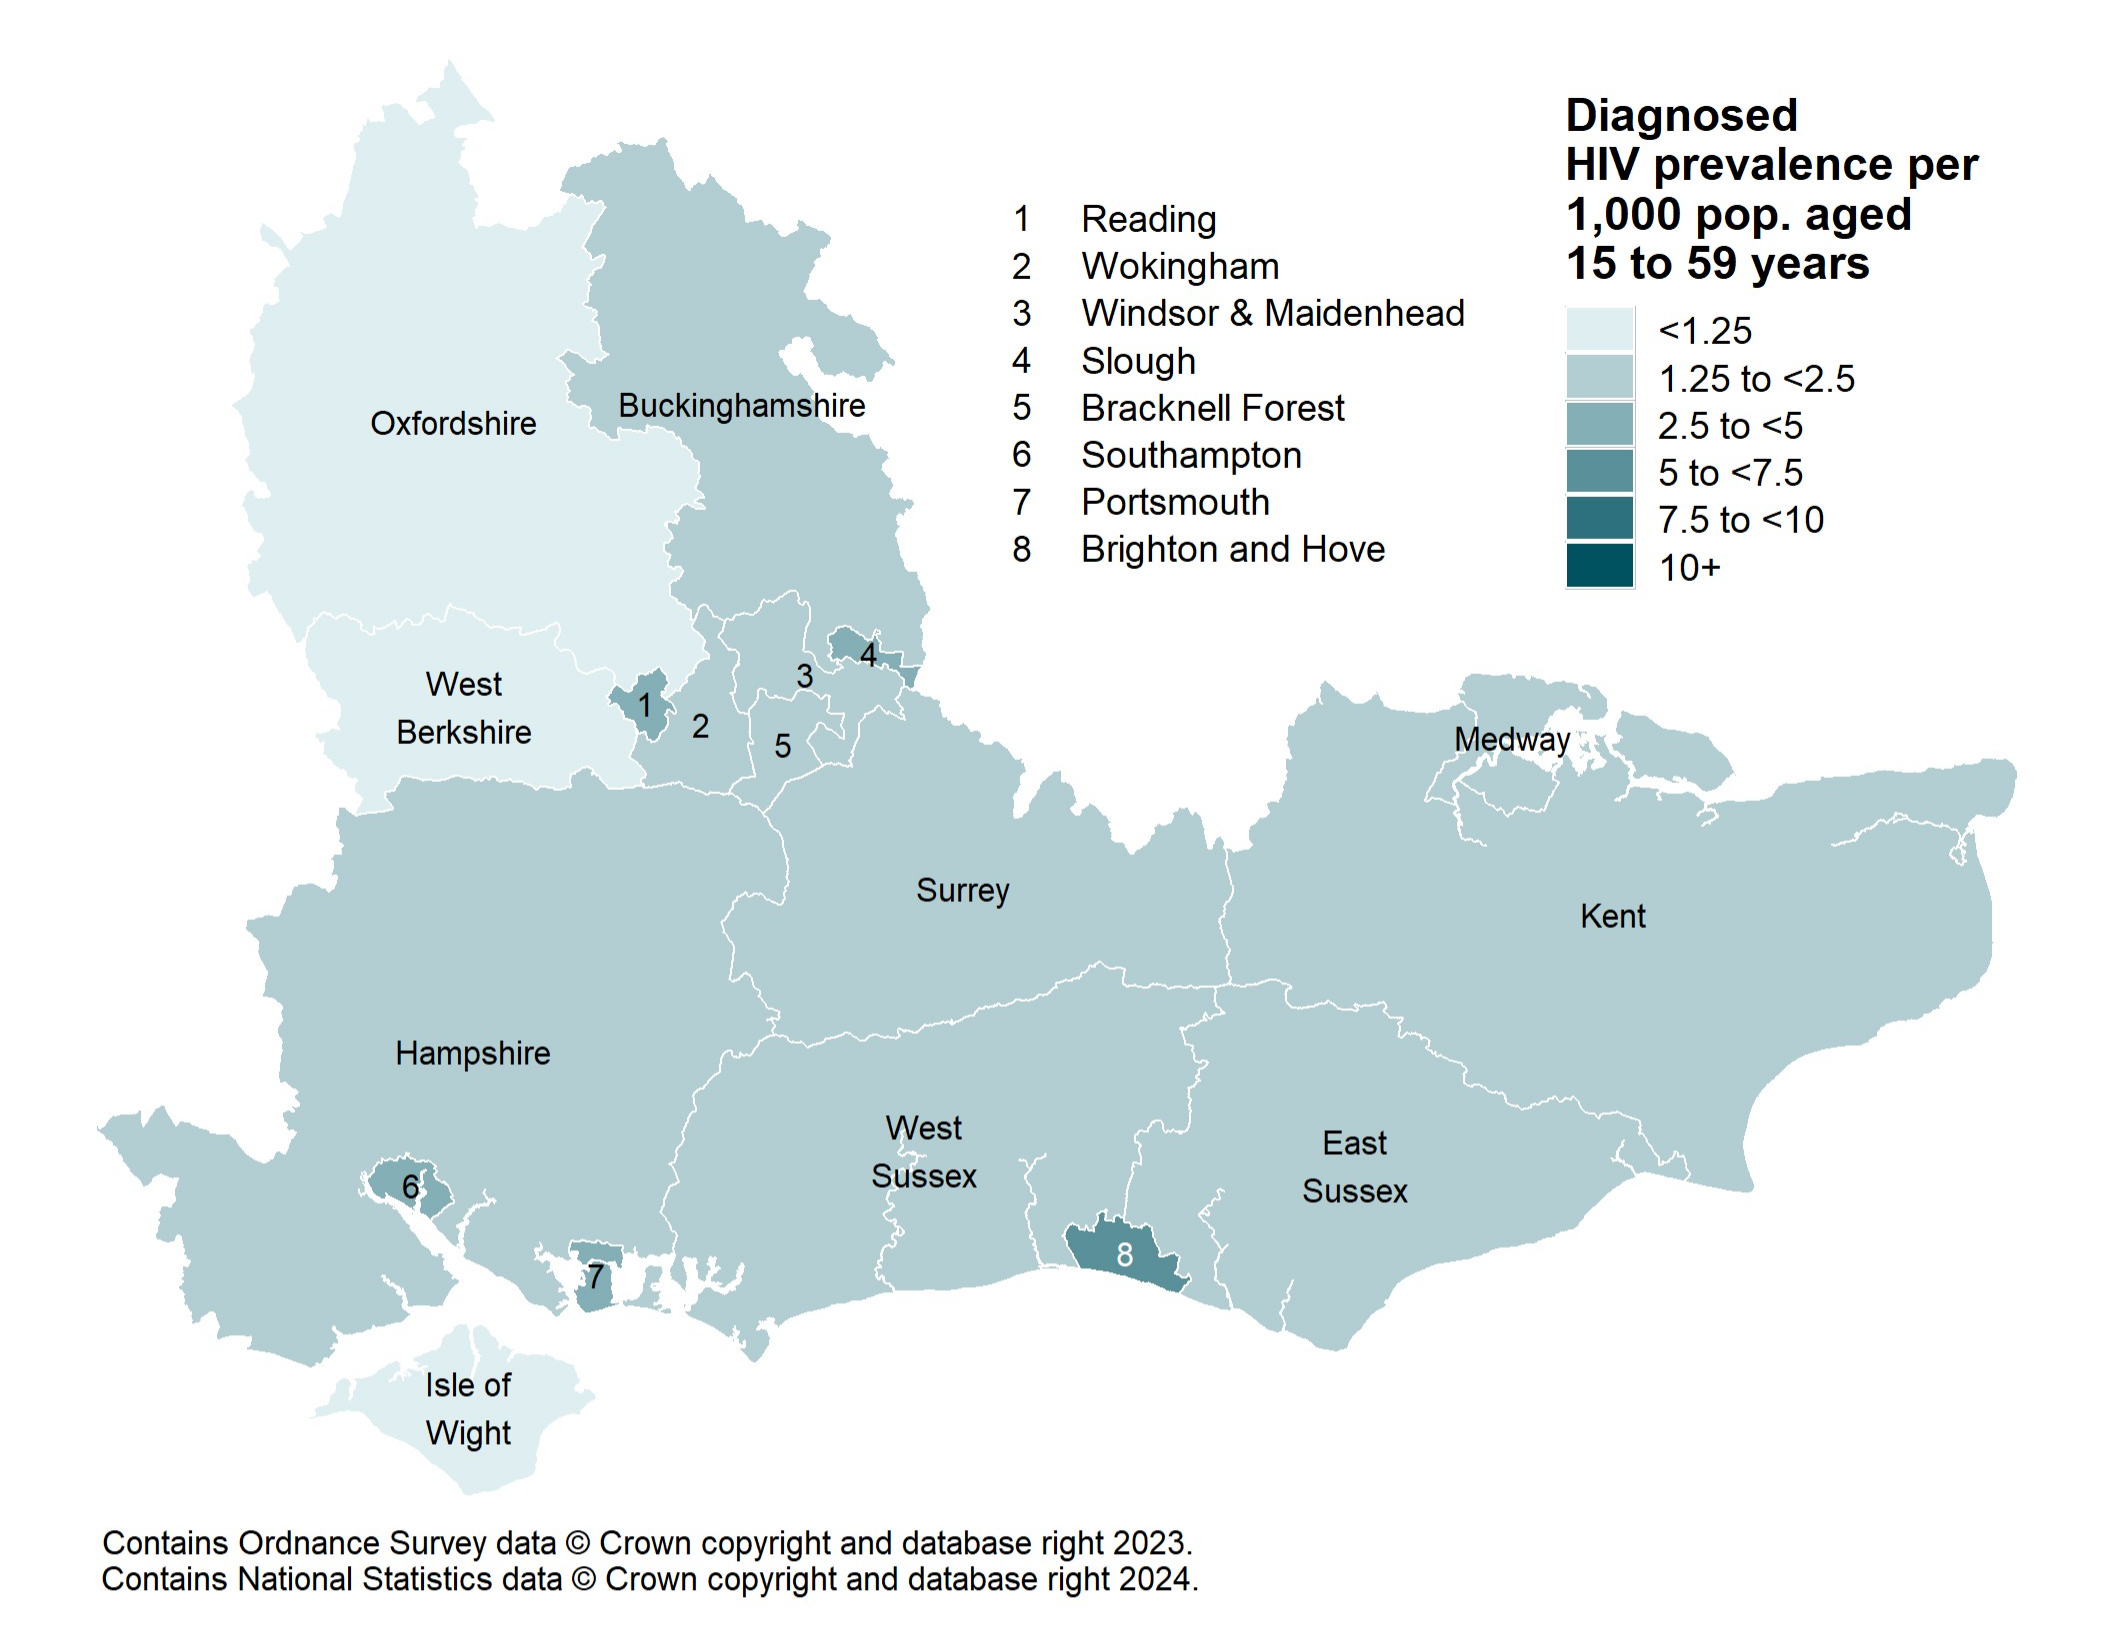
Figure 31. Diagnosed HIV prevalence per 1,000 residents aged 15 to 59 years by local authority, the South East, 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 31 is a map showing the prevalence of diagnosed HIV per 1,000 South East residents aged 15 to 59 years by local authority in 2024. The map is shaded in relation to 6 rate bands, from below 1.25 to 10 and above.
In the South East, no local authorities have rates in the 2 highest bands, and only Brighton and Hove have a rate in the third highest band of 5 to less than 7.5. Reading, Slough, Southampton, and Portsmouth have rates in the third lowest band of 2.5 to less than 5. The remaining local authorities have rates in the 2 lowest bands.
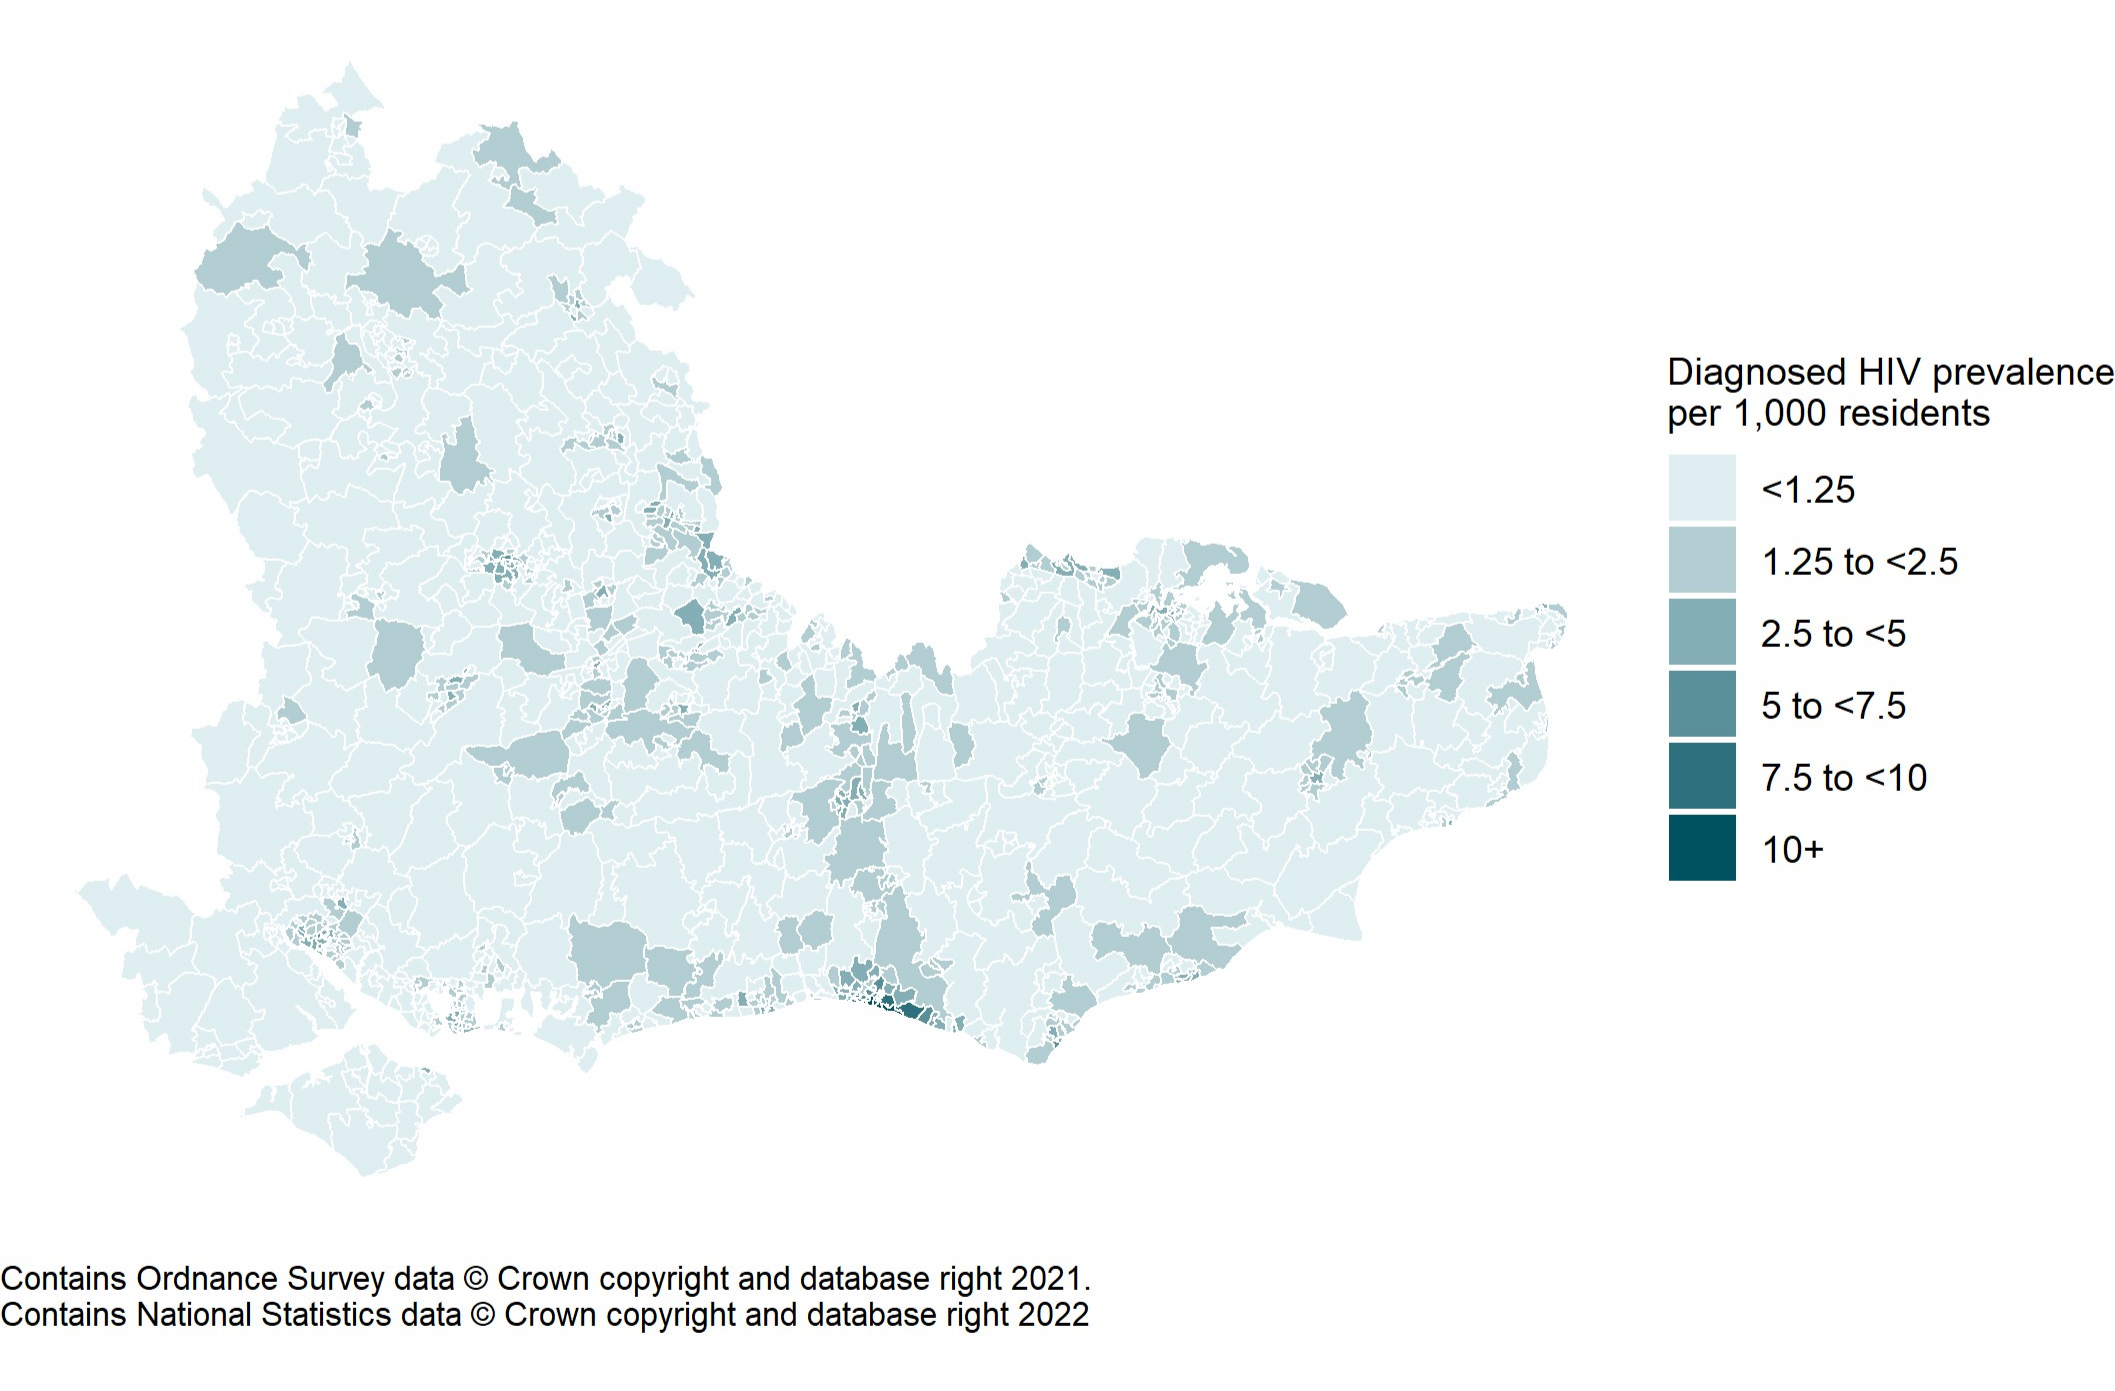
Figure 32. Diagnosed HIV prevalence per 1,000 residents (all ages) by middle super outer area of residence the South East, 2024
Sources: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 32 is a map showing the prevalence of diagnosed HIV per 1,000 South East residents by middle-layer super output area (MSOA) in 2024. The map is shaded in relation to 6 rate bands, from below 1.25 to 10 and above. Unlike the local authority level map, all ages are included in the rates. MSOAs consist of groups of lower-layer super output areas (LSOAs), have a consistent size, and a population of between 5,000 and 15,000 people. This map shows a more granular picture of the prevalence of diagnosed HIV across the South East.
Figure 33. HIV testing rate per 100,000 by population group, South East residents, 2020 to 2024 [note 6]
Sources: UKHSA, GUMCAD.
The proportion of eligible attendees at specialist sexual health services (SHS) who accepted a HIV test. An eligible attendee is defined as a patient attending specialist SHS at least once during a calendar year. Patients known to be HIV positive, or for whom a HIV test was not appropriate, or for whom the attendance was related to Sexual and Reproductive Health (SRH) care only, are excluded.
Note 6: ONS mid-2023 population estimates have been used to calculate HIV testing rates.
Figure 33 is a line chart showing the HIV testing rate per 100,000 population for all, male, and female South East residents between 2020 and 2024.
The HIV testing rate has steadily increased since the COVID-19 pandemic in 2020. In 2024, the testing rate was close to pre-pandemic levels and the testing rate in 2019. Throughout the 5-year period, females had a higher HIV testing rate than males. The overall HIV testing rate in the South East was 43% higher in 2024 than in 2020.
Table 2. People tested for HIV by population group, South East residents attending all SHSs, 2019 to 2024
| Gender or sexual orientation | 2019 | 2020 | 2021 | 2022 | 2023 | 2024 | % change 2019 to 2024 | % change 2023 to 2024 |
|---|---|---|---|---|---|---|---|---|
| Heterosexual men | 51,284 | 29,646 | 28,914 | 33,996 | 39,144 | 42,799 | -17% | 9% |
| Gay and bisexual men | 15,147 | 14,325 | 17,161 | 18,006 | 19,364 | 20,880 | 38% | 8% |
| All men | 83,247 | 57,957 | 61,007 | 68,188 | 75,613 | 81,182 | -2% | 7% |
| Hetero or bisexual women | 77,057 | 55,525 | 58,699 | 61,142 | 71,568 | 77,002 | 0% | 8% |
| All women | 105,703 | 77,517 | 81,423 | 85,471 | 97,726 | 102,170 | -3% | 5% |
| Total | 192,312 | 137,205 | 145,272 | 157,180 | 176,893 | 186,979 | -3% | 6% |
Sources: UKHSA, GUMCAD.
The totals for ‘All men’ and ‘All women’ include people tested from sexual orientation categories not shown in the table above.
Table 2 shows information on the number and percentage change in South East population groups attending all sexual health services for HIV testing between 2019 and 2024.
Testing increased for all groups in 2024 compared to 2023, and by 6% overall. Compared to 2020, the numbers for 2024 were higher for all groups, and by 36% overall. Compared to 2019, the numbers for 2024 were 3% lower overall. HIV testing is still lower than pre-pandemic in the South East, however, total testing numbers have increased year-on-year since.
Figure 34. HIV pre-exposure prophylaxis (PrEP) need and initiation/continuation in residents attending specialist sexual health services (SHSs), the South East, 2024
Sources: UKHSA, GUMCAD.
Figure 34 is a column chart showing information about PrEP need and use by gender and sexual orientation in the South East in 2024. The first column represents the percentage of South East residents attending specialist SHSs who were determined to be in need of PrEP based on clinical and other information. The second column shows the percentage of those in need of PrEP whose PrEP need was identified by the service, and the third column shows the percentage of those in need of PrEP for whom PrEP was initiated or continued. The second and third columns for each group must be looked at in relation to the first column. It is important to bear in mind that the chart represents percentage of need identified among attendees of the groups, and that the absolute numbers for the groups differ substantially. Further information on PrEP is available in the PrEP monitoring and evaluation framework.
Gay and bisexual men had the highest need for PrEP (68%). Of these 88% had their PrEP need identified, and PrEP was initiated or continued for 78%. Heterosexual men had the second highest need for PrEP (2%), much lower than gay and bisexual men. Of these 66% had their PrEP need identified, and of those 45% initiated or continued PrEP. Heterosexual women had the lowest need for PrEP (less than 1%). Of these 66% had their PrEP need identified, and of those 49% initiated or continued PrEP.
Information on data sources
- HIV and AIDS New Diagnoses and Deaths (HANDD) collects information on new HIV diagnoses, AIDS at diagnosis and deaths among people diagnosed with HIV. Information is received from laboratories, specialist SHSs, GPs and other services where HIV testing takes place in England, Wales and Northern Ireland. The Recent Infection Testing Algorithm (RITA) and CD4 surveillance scheme are linked to HANDD to assess trends in recent and late diagnoses. Data is deduplicated across regions and therefore figures may differ from country-specific data.
- The Survey of Prevalent HIV Infections Diagnosed (SOPHID) began in 1995 and was a cross-sectional survey of all adults living with diagnosed HIV infection who attend for HIV care in England, Wales and Northern Ireland. SOPHID collected information about the individual’s place of residence along with epidemiological data including clinical stage and antiretroviral therapy (ART). In 2015, SOPHID reporting in England was replaced by the HIV and AIDS Reporting System (HARS) which captures information at every attendance for HIV care.
- Date of data extract: October 2024. Updates to HANDD and SOPHID/HARS made after this date will not be reflected in this report.
- Confidence intervals for rates in the figures have been calculated to the 95% level using the Byar’s method; confidence intervals for percentages have been calculated to the 95% level using the Wilson Score method. Confidence intervals presented in the text are produced by Bayesian analysis.
- The most recent ONS mid-year estimates at the time of analysis were used as denominators for rates. Unless otherwise stated, for UTLAs 2024 estimates were used (published Jun-2024), for MSOAs 2022 estimates were used (published November 2024), for LTLAs 2021 estimates were used (published November 2022), and for LSOAs 2022 estimates were used (published November 2024).
- The data behind charts showing absolute numbers may have been adjusted for missing information; however, unless stated otherwise, the numbers in the summary section are the numbers as reported, that is, unadjusted counts. Where charts are displaying adjusted data this is indicated in the chart title. Where figures have been ‘adjusted for missing information’, this means that when unknown values are present (for example, route of probable exposure = ‘unknown’), they are proportionally distributed amongst other groups for the purposes of analysis (for example, if A = 12, B = 4, C = 2, and unknown = 6, the 6 ‘unknown’ values are distributed proportionally among groups A, B, and C to give A = 15, B = 6, C = 3).
- The denominators for all percentages exclude records for which information was unknown, that is, the proportion of new diagnoses where probable route of exposure was gay and bisexual men would be calculated using new diagnoses for which route of exposure was known as the denominator.
All analyses in this report are residence-based and reflect the patient’s place of residence at diagnosis.
Numbers may change as more information becomes available to assign area of residence to cases and historical data is refreshed accordingly.
More information
For more information on a whole range of sexual health indicators, see:
For more information on local sexual health data sources, see
For the annual epidemiological spotlight on STIs in South East 2024, see:
For the national HIV report: 2024 data, see:
Local authorities have access to additional HIV and STI intelligence via the Data Exchange and the HIV and STI web portal. They should also have received a set of tables containing HIV data specific to their authority. If they do not have access to this information, they should contact FES.SEaL@ukhsa.gov.uk
About the Field Service
The Field Service was established in 2018 as a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Real-time Syndromic Surveillance and Public Health Microbiology to strengthen the surveillance, intelligence and response functions of UKHSA.
You can contact your local Field Service team at FES.SEaL@ukhsa.gov.uk
If you have any comments or feedback regarding this report or the Field Service, contact josh.forde@ukhsa.gov.uk or tobias.martinsen@ukhsa.gov.uk
Acknowledgements
We would like to thank:
- local sexual health and HIV clinics for supplying the HIV data
- Institute of Child Health
- UKHSA Blood Safety, Hepatitis, Sexually Transmitted Infections and HIV Division (BSHSH) for collection, analysis and distribution of data
References
1. Brown AE, Shah A, Martin V, Chau C, Đuretić T. ‘People diagnosed with HIV before continuing care in England are extremely unlikely to pass on HIV in Englandv’ HIV Medicine 2025: volume 26, issue 10, pages 1,626 to 1,677
2. Shah A, Mackay N, Kitt H, Harrison C, Okumu-Camerra K, Ratna N, Schoemig V, Chau C, Martin V, Brown A, Đuretić T. ‘HIV testing, PrEP, new HIV diagnoses and care outcomes for people accessing HIV services: 2025 report. The annual official statistics data release (data to end of December 2024)’ UKHSA October 2025
3. Department of Health and Social Care. ‘Towards zero: an action plan towards ending HIV transmission, AIDS and HIV-related deaths in England 2022 to 2025’ UK Government White Paper 2022
4. Aghaizu A, Martin V, Kelly C, Kitt H, Farah A, Latham V, Brown AE, Humphreys C. ‘Positive Voices: the national survey of people living with HIV – findings from 2022’ UKHSA December 2023
5. Schoemig V, Martin V, Shah A, Okumu-Camerra K, Mackay N, Bera S, Kitt H, Kelly C, Kolawole T, Ratna N, Chau C, Đjuretić T, Brown A and others. ‘HIV Action Plan monitoring and evaluation framework 2024 report: report summarising progress from 2019 to 2023. November 2024’ UKHSA (accessed 19 September 2025)
6. Office for National Statistics (ONS) January 2023. ‘Sexual orientation by age and sex, England and Wales: Census 2021’ (accessed 19 September 2025)