Annual epidemiological spotlight on HIV in the East of England, 2024 data
Updated 26 October 2026

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/hiv-east-of-england-annual-data-spotlight/annual-epidemiological-spotlight-on-hiv-in-the-east-of-england-2024-data
Summary
The HIV Spotlight report is an annual report that provides an update on the epidemiology of HIV within the East of England. It highlights the number of new HIV diagnoses, diagnoses that are made late, testing patterns, PrEP uptake and individuals living with diagnosed HIV.
During 2024, UKHSA engaged in a stakeholders’ review on language use for HIV. Consequently, a number of changes have been made to the language used in this report. These include reference to gender identity, sexual orientation and probable route of exposure:
- for gay, bisexual and all men who have sex with men, the abbreviation is gay and bisexual men (instead of GBMSM or sex between men)
- for heterosexual men or men who acquired HIV through sex with women, we abbreviate as heterosexual men (instead of men exposed through sex with women)
- for heterosexual and bisexual women or women who acquired HIV through sex with men, we use heterosexual women (instead of women exposed through sex with men)
In previous Spotlights reports, counts of new HIV diagnoses included people diagnosed with HIV before continuing care in England (referred to as “previously diagnosed abroad”). These cases do not reflect HIV acquired in England and most of them are rapidly linked to care shortly after arrival, making the majority extremely unlikely to pass on HIV in England1. For this report, reflecting changes in national HIV statistics, reference to new HIV diagnoses now only includes diagnoses first made in England.
HIV remains an important public health priority in the East of England. The East of England UKHSA region covers the following 12 local authorities: Bedford Borough, Cambridgeshire, Central Bedfordshire, Essex, Hertfordshire, Luton, Milton Keynes, Norfolk, Peterborough, Southend-on-Sea, Suffolk and Thurrock.
In 2024, for East of England residents:
- 245 new HIV diagnoses in East of England residents in 2024, 9% of all England diagnoses
- 26% of new diagnoses were in gay and bisexual men
- 49% of new diagnoses were in Black Africans
- 49% of diagnoses were made late (2022 to 2024)
- 9,194 people were living with diagnosed HIV in the East of England
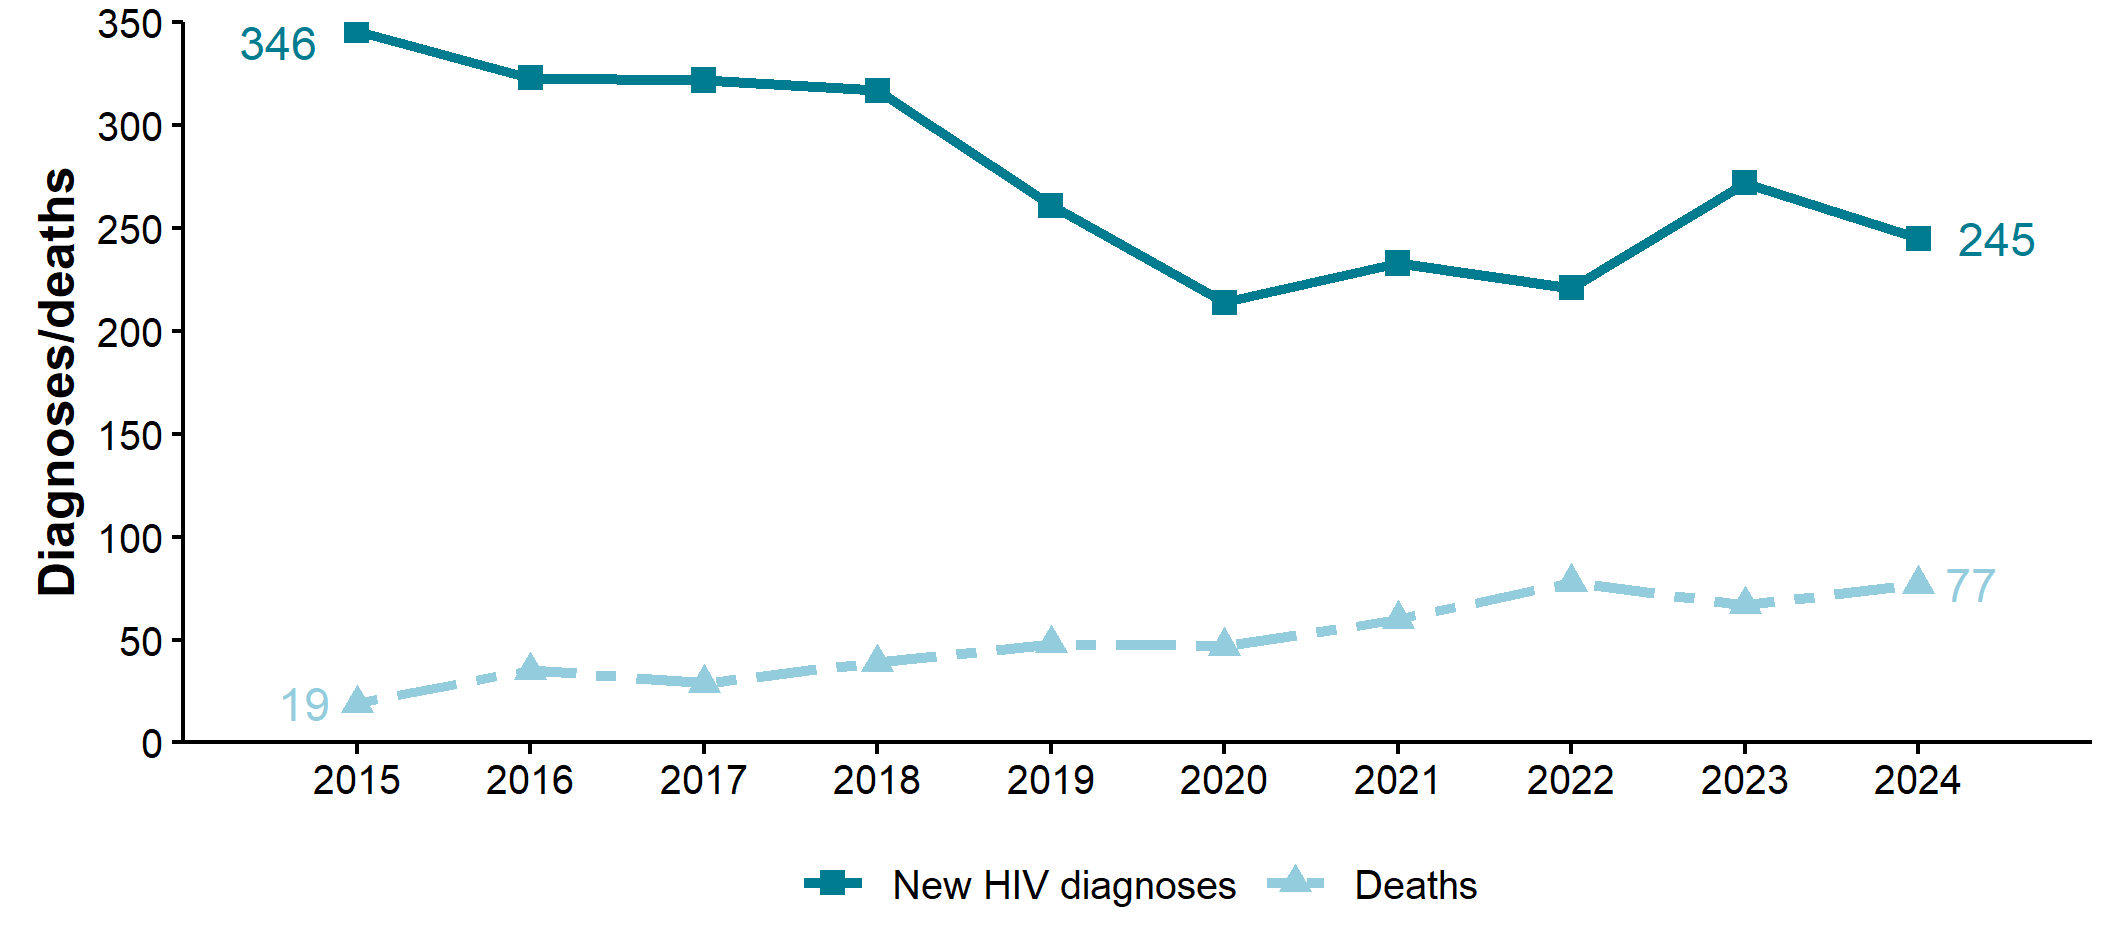
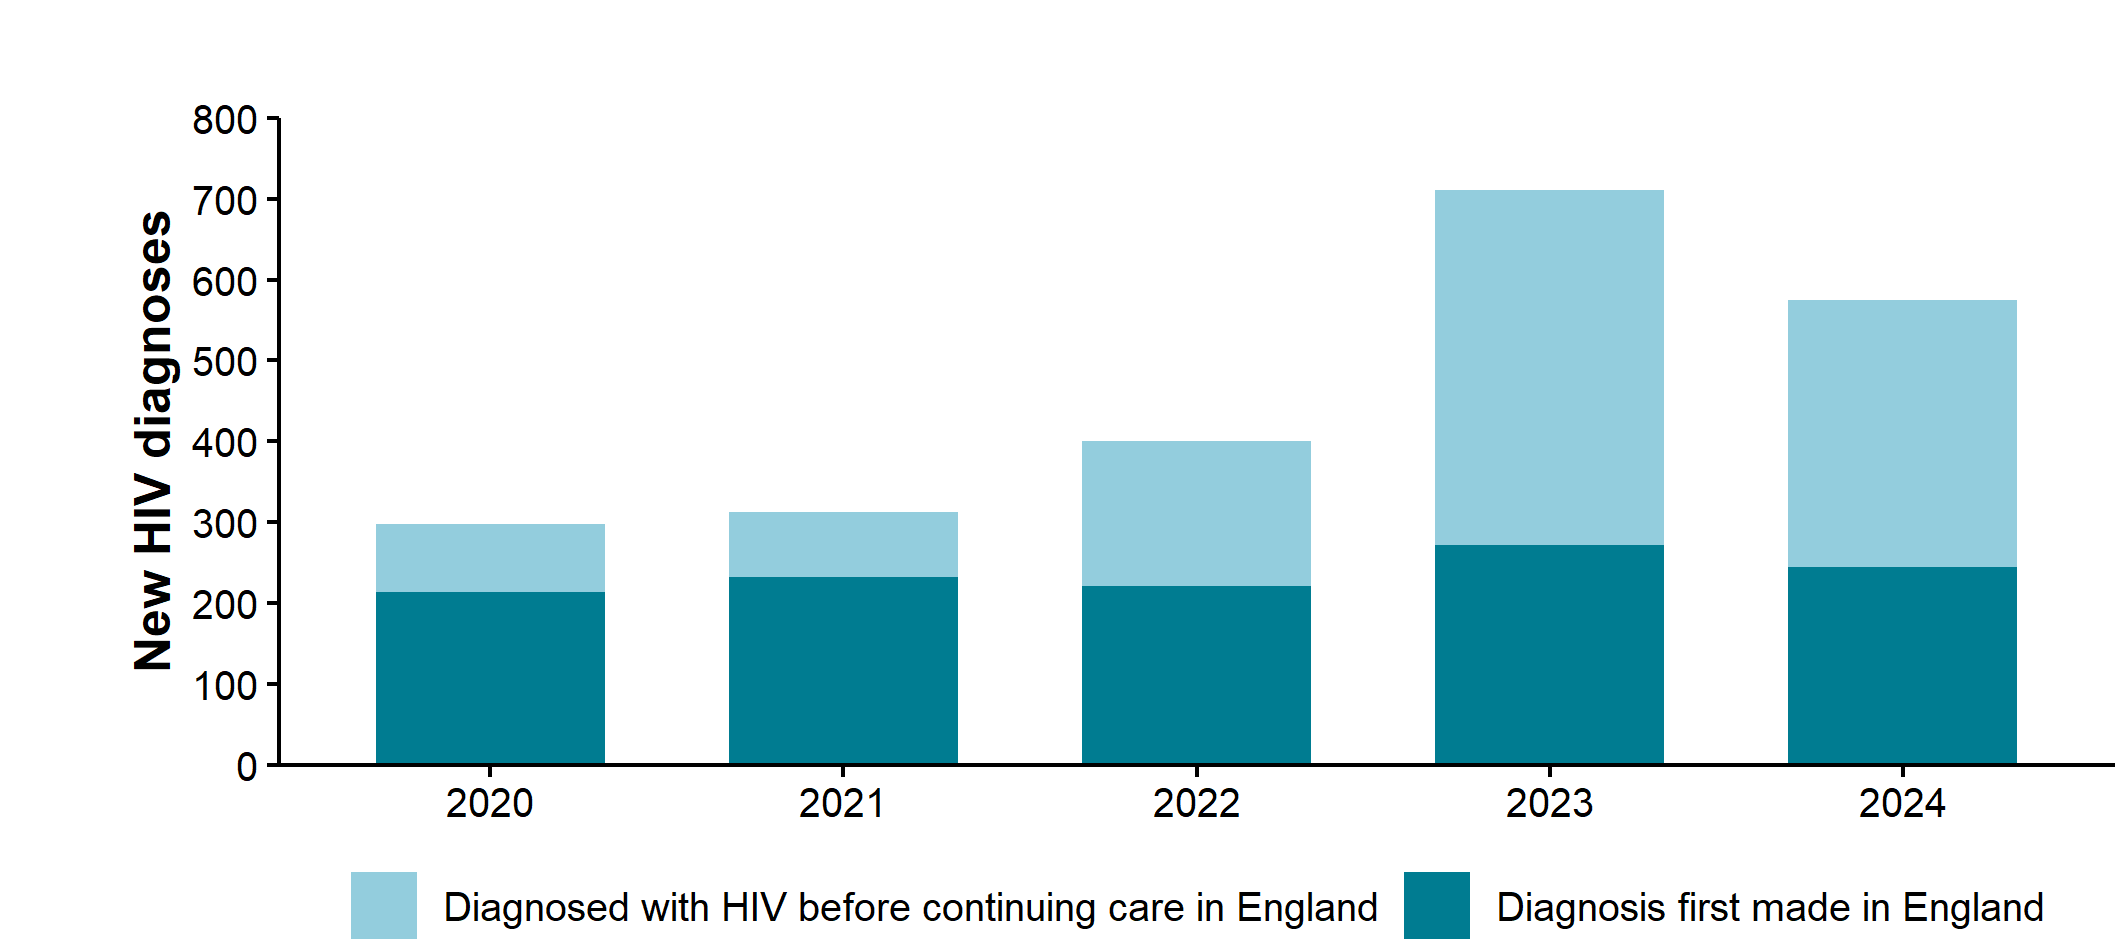
Overall, since 2015 there has been a declining trend in the number of new HIV diagnoses among East of England residents first diagnosed in England. There was some fluctuation in the COVID-19 years of 2020 to 2022, before increasing in 2023. In 2024, the number of new HIV diagnoses decreased from 272 in 2023, to 245 in 2024. New diagnoses in the East of England accounted for 9% of those in England. There were 330 HIV diagnoses in the East of England among individuals who had been diagnosed with HIV before continuing care in England, a reduction compared to 439 the year before.
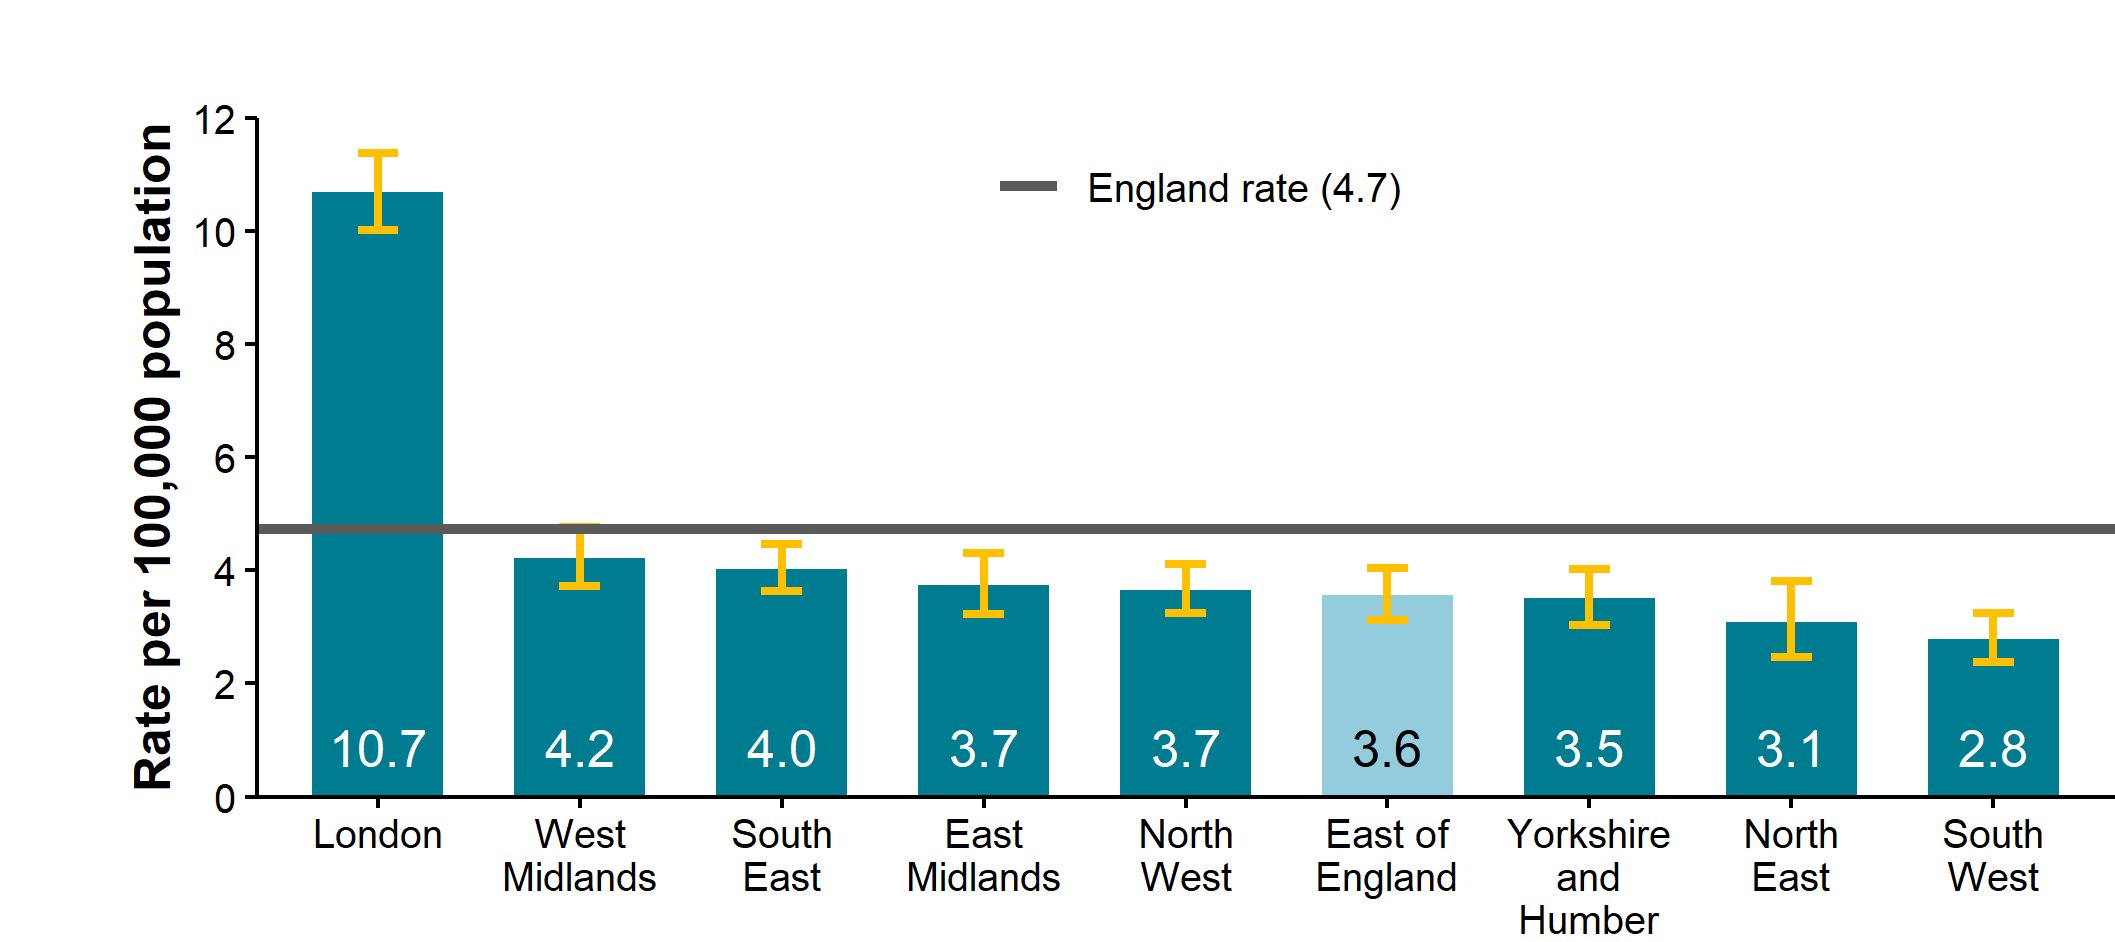
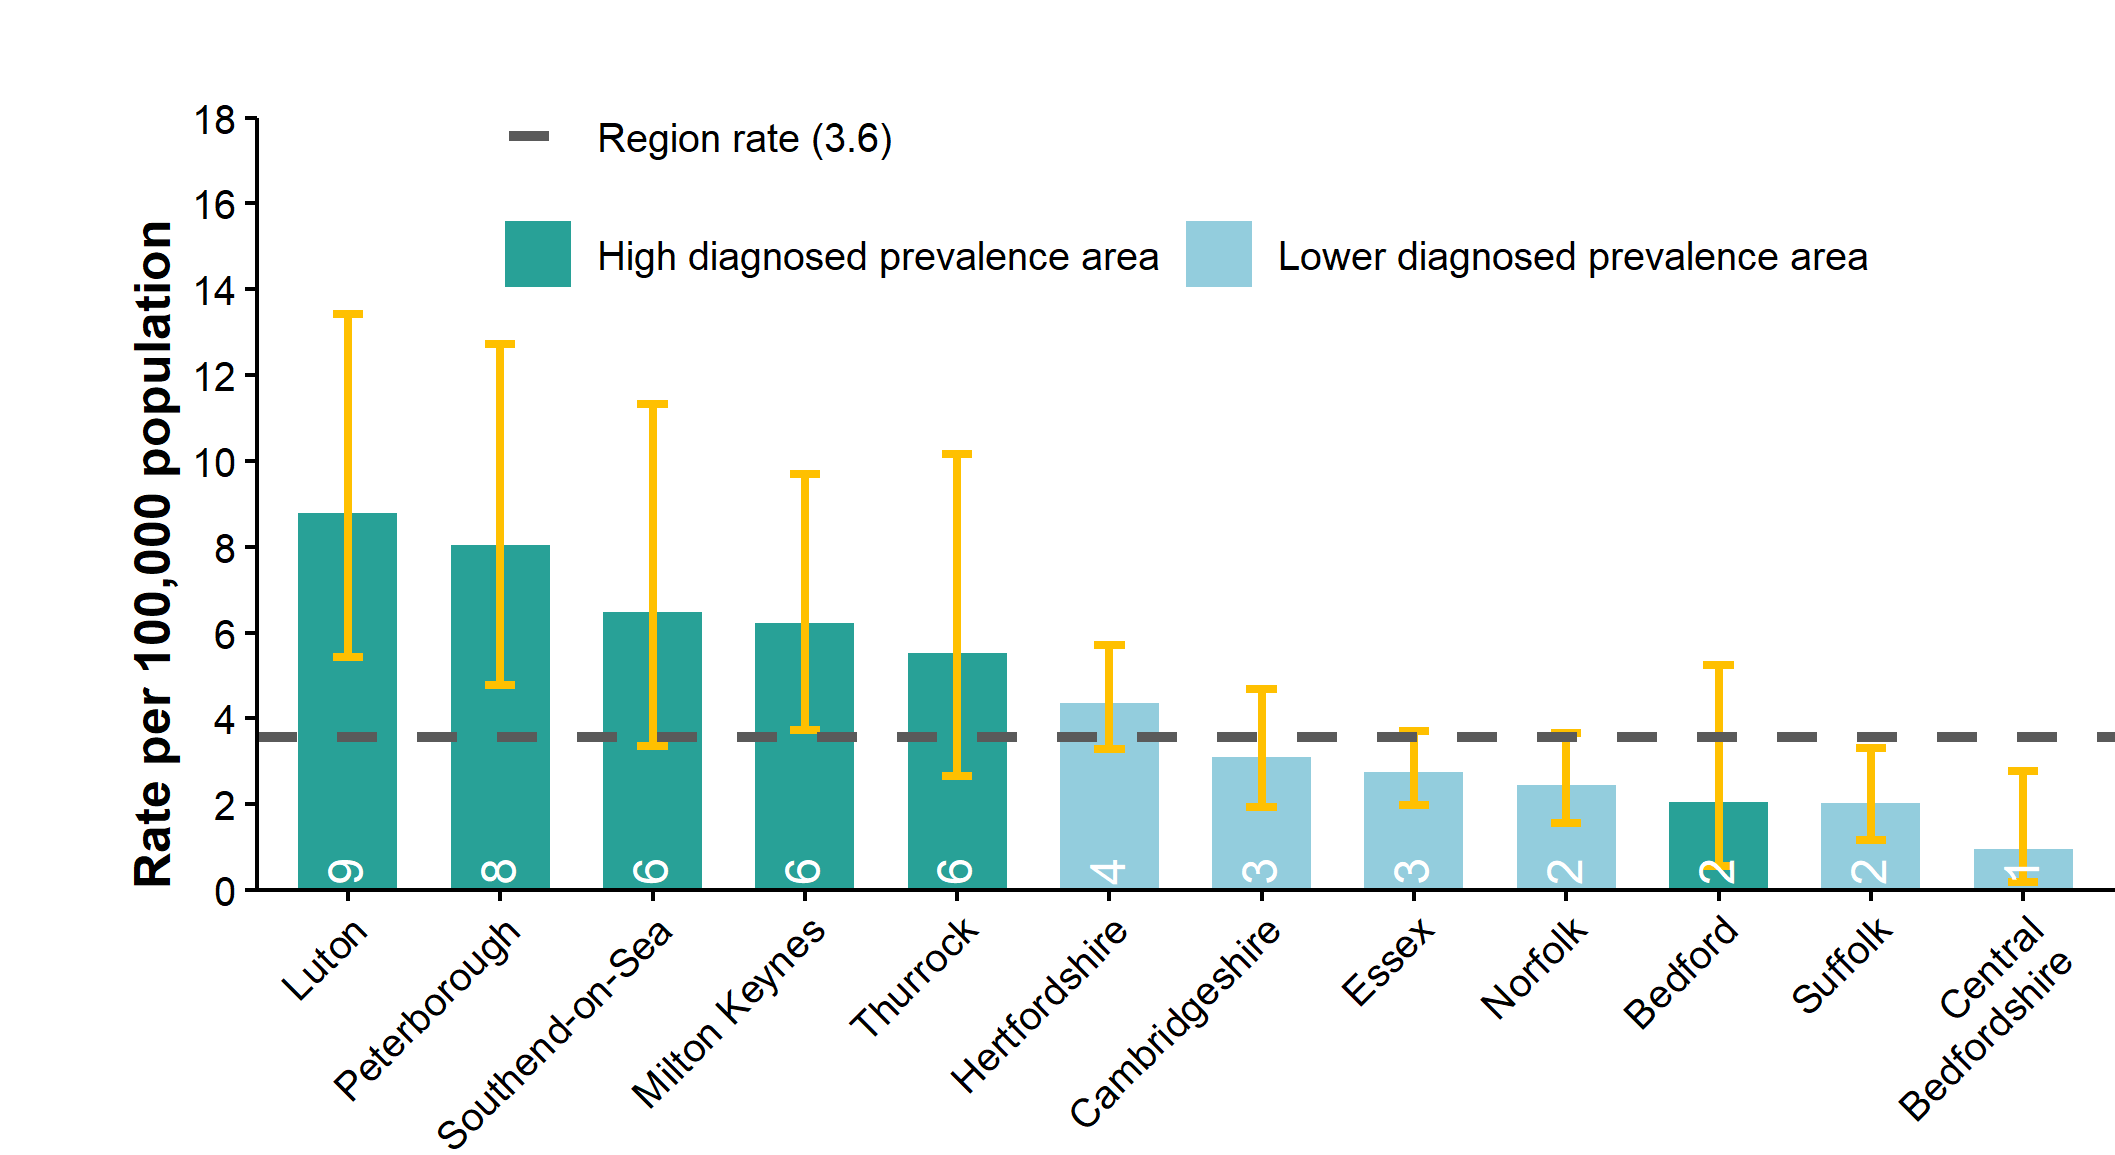
The East of England was the region with the fourth lowest rate of new HIV diagnoses with 3.6 per 100,000 significantly lower than the overall England rate (4.7 per 100,000). London was the region with the highest rate (10.7), and the South West had the lowest (2.8). By East of England upper tier local authority (UTLA), new HIV diagnoses rates ranged from 9 per 100,000 in Luton, to 1 per 100,000 in Central Bedfordshire. Peterborough (8), Southend-on-Sea (6), Milton Keynes (6) and Thurrock (6) all had rates higher than the regional (3.6) and national average (4.6).
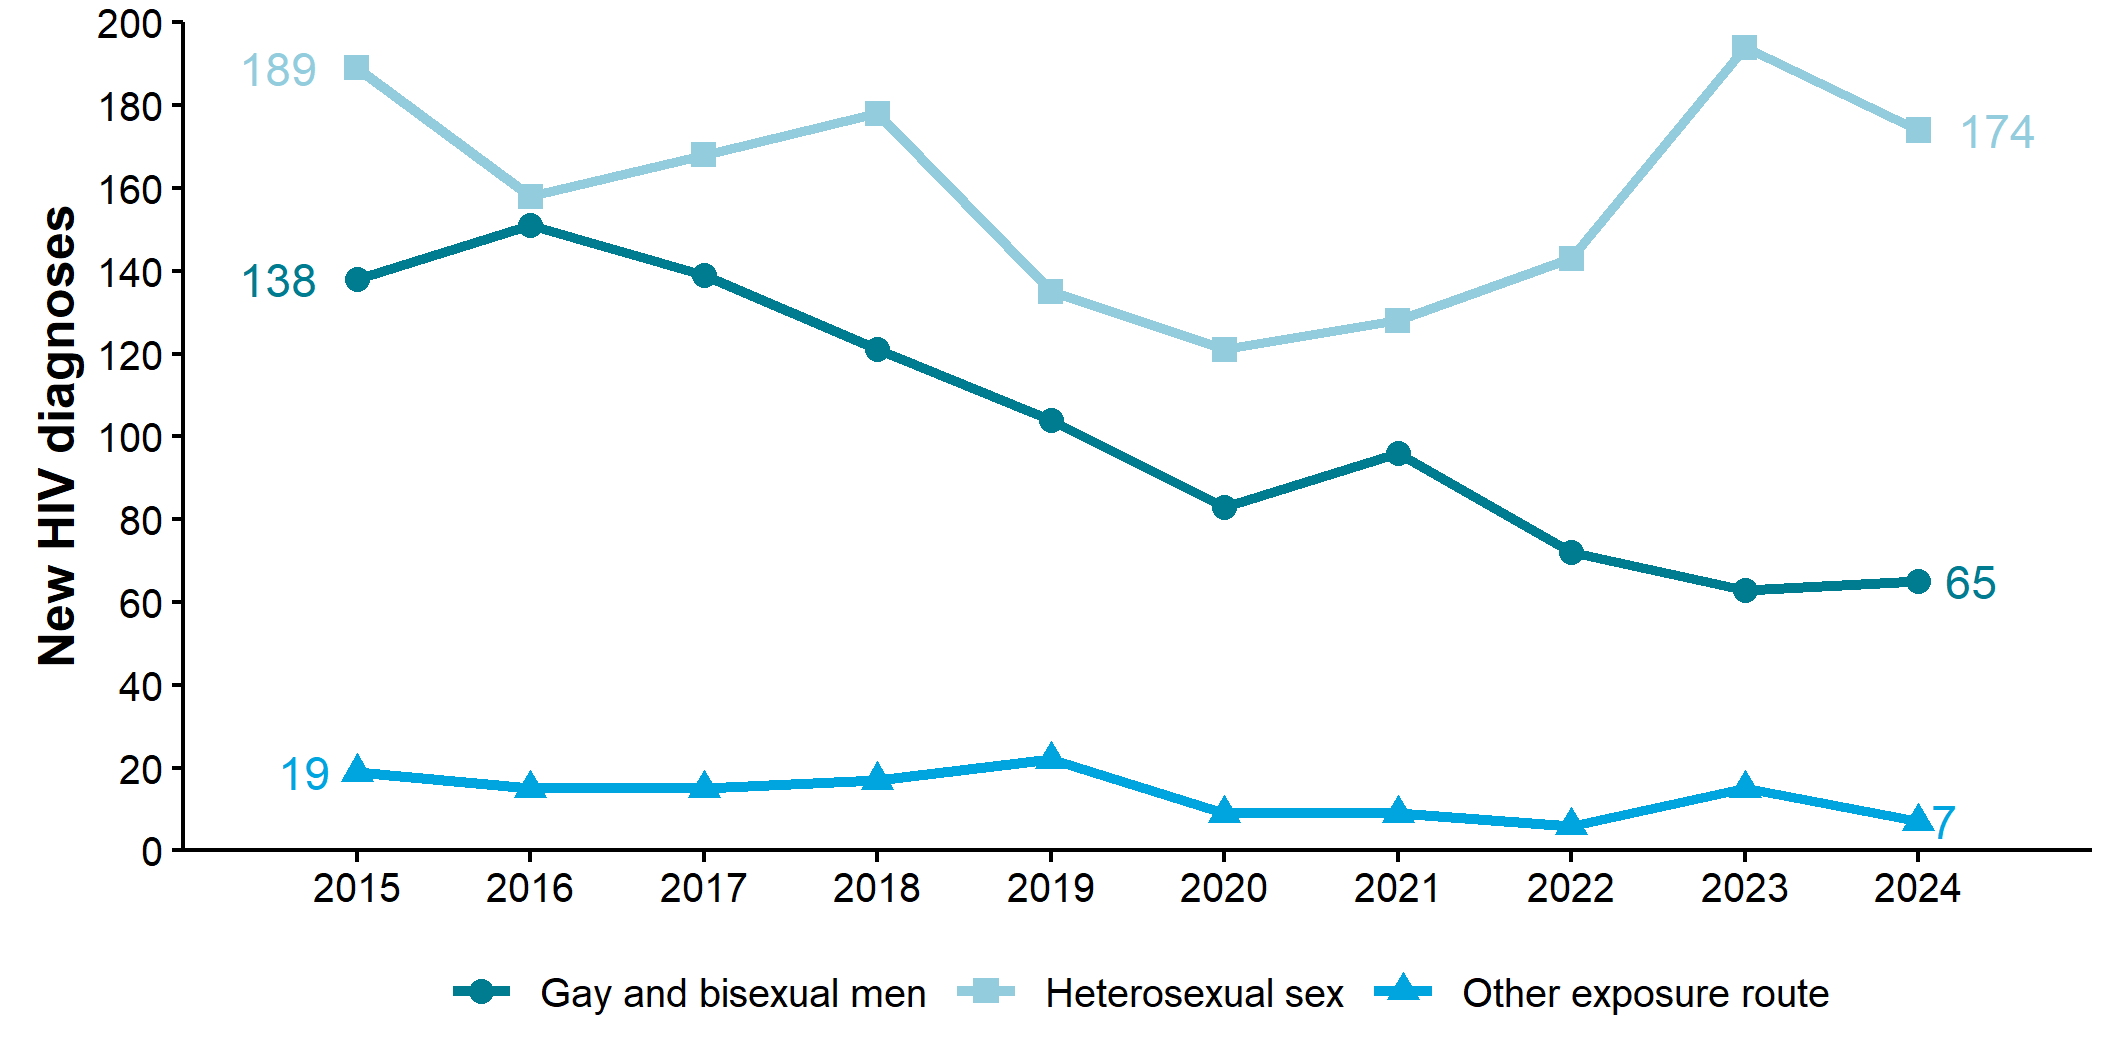
Over time, there has been a declining trend of new HIV diagnoses among the probable exposure category of sex between gay and bisexual men between 2015 and 2024. New diagnoses likely acquired through heterosexual sex reduced between 2015 and 2020, before increasing to 2023 and decreasing in the most recent year. New diagnoses among those with ‘other’ probable exposure routes (including injecting drug use and vertical transmission) have remained relatively low. In 2024, 71% of new diagnoses were among the exposure group of heterosexual sex, 27% sex between gay and bisexual men, and 4% other exposure routes.
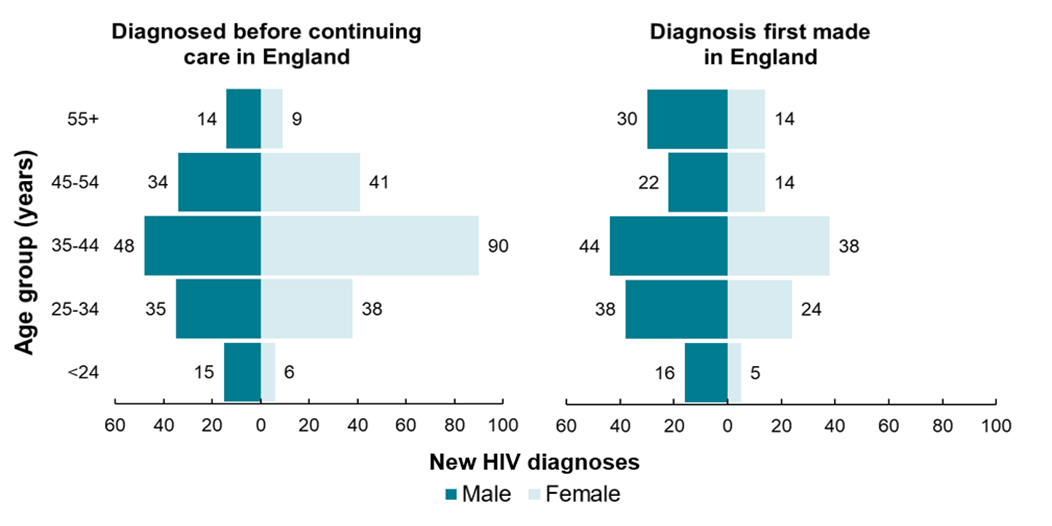
All HIV diagnoses include both those first diagnosed in England, and those diagnosed before continuing care in England. When looking at all HIV diagnoses by both age and sex, the distribution differs for those first diagnosed in England compared to those diagnosed with HIV before continuing care in England. Females make up 56% of those diagnosed with HIV before continuing care in England, particularly females aged 35-44. Whereas for individuals first diagnosed in England males accounted for 61% of new diagnoses.
Between 2021 and 2024 there were increases in new diagnoses first made in England among those of Black African ethnicity, whereas diagnoses decreased among those of White ethnicity. In 2024 Black Africans accounted for 49% of new diagnoses, compared to 29% in 2015. Increases were also seen between 2015 and 2024 for those with a world birth region of Africa, accounting for 51% of new diagnoses in 2024, while diagnoses decreased among those born in the UK.
Almost half of new diagnoses in the East of England were made late between 2022 and 2024. By UTLA this ranged from 58% in Milton Keynes to 34% in Luton. Between 2022 and 2024, 38% of gay and bisexual men were diagnosed late compared to 59% of heterosexual men and 48% of heterosexual women. Black Africans were also slightly more likely to be diagnosed late (52%) compared to those of White ethnicity (50%).
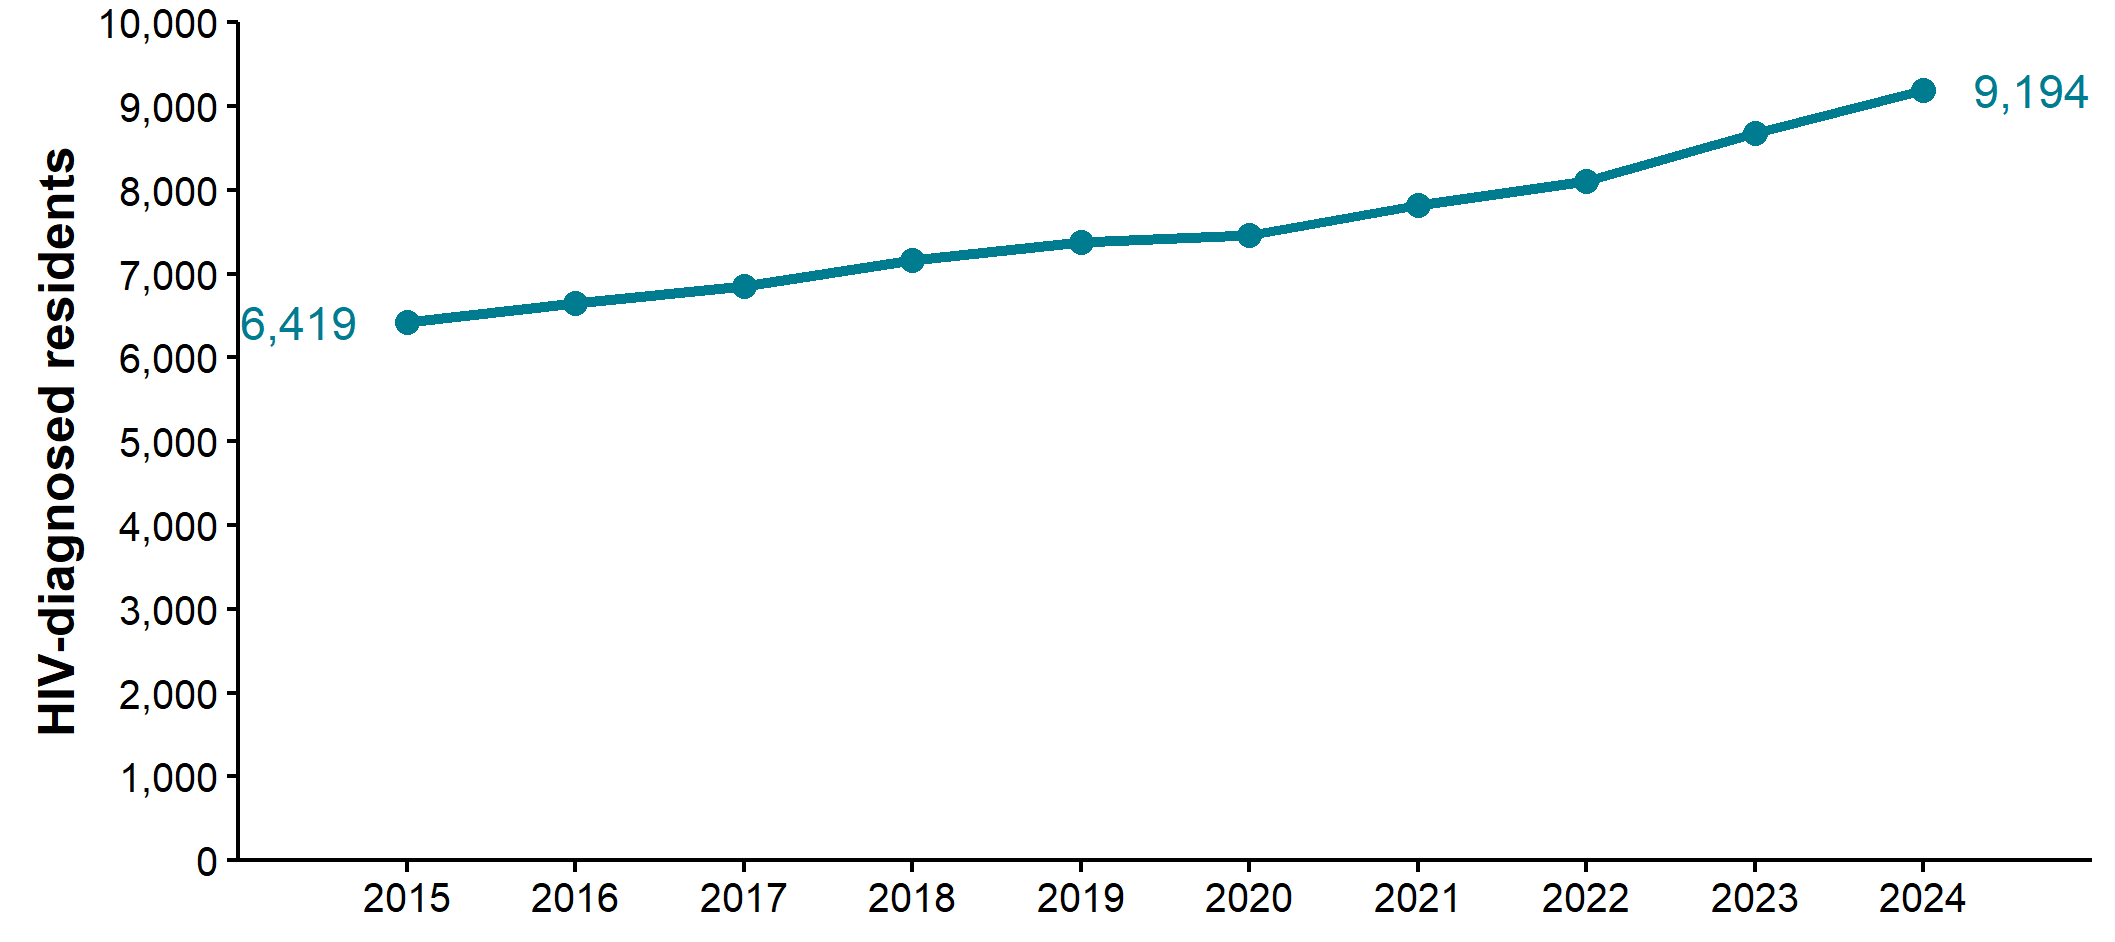
Between 2015 and 2024 there has been an increasing trend in the number of residents living with diagnosed HIV and accessing care, from 6,419 in 2015 to 9,194 in 2024. Of those diagnosed with HIV and accessing care, 65% were likely exposed through heterosexual contact, 31% were gay and bisexual men, 2% were vertical transmission, 1% injecting drug use.
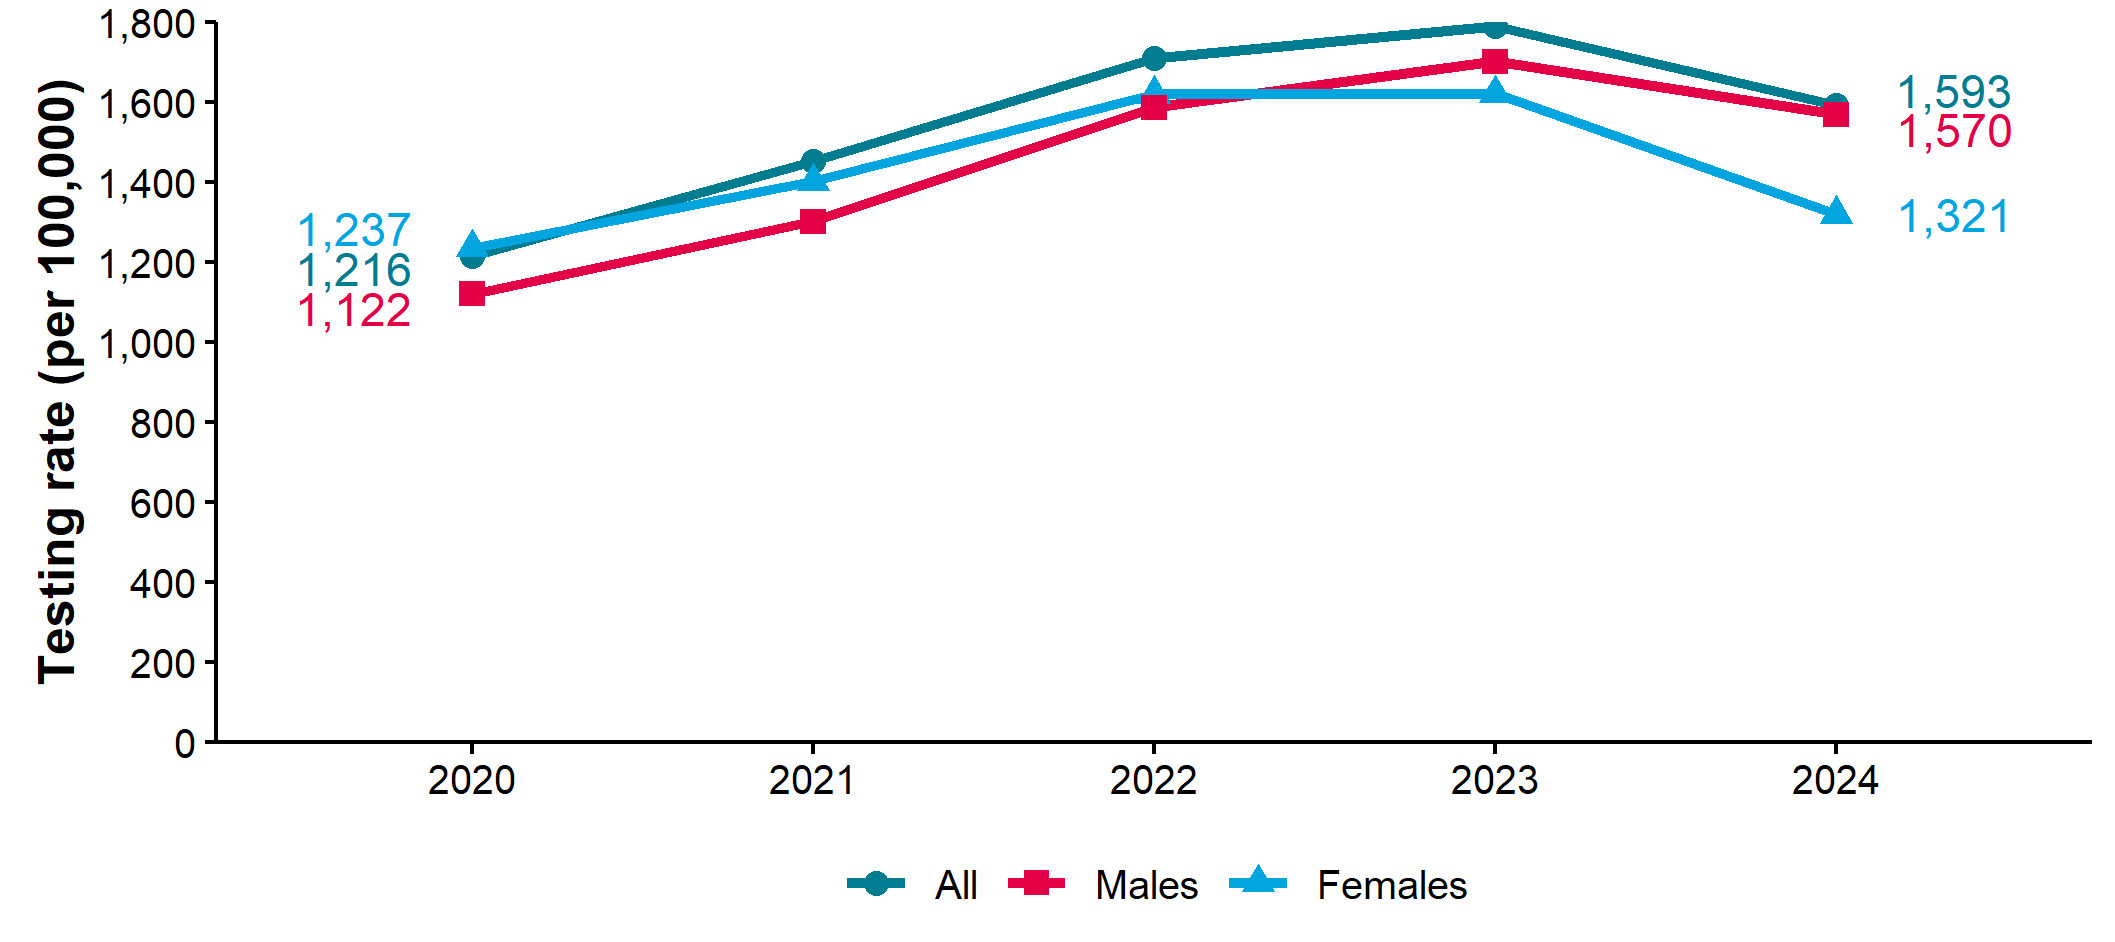
HIV testing at all sexual health services (SHSs) in the East of England has decreased when compared to pre-pandemic levels of 2019. In 2024 the testing rate was 1,593 per 100,000 compared to 1,982 in 2019. Overall HIV testing rates for in the East of England dropped sharply in 2020 before increasing to 2023 and decreasing in the most recent year. Between 2020 and 2022 the testing rate was higher among females than males, however in 2023 and 2024 male testing rates exceeded those of females.
New diagnoses
In 2024, 245 East of England residents were newly diagnosed with HIV, accounting for 9% of new diagnoses in England. This represents a fall of 10% from 2023.
The new diagnosis rate for East of England residents (4 per 100,000) was below that of England in 2024 (5 per 100,000).
In 2024, 26% of all new diagnoses in East of England residents were in gay and bisexual men (compared to 23% in 2023 and 40% in 2015). The number of gay and bisexual men resident in the East of England newly diagnosed with HIV (65, adjusted for missing information) was 53% lower than in 2015. Of the gay and bisexual men newly diagnosed with HIV 70% were White and 57% were UK-born.
Heterosexual contact was the largest route of exposure for new diagnoses in East of England residents in 2024 (71%). Infections in African born persons accounted for 67% of all heterosexually acquired cases in 2024 (n=100), compared to 54% (n=84) in 2015. Infections in UK born persons accounted for 19% of all heterosexually acquired cases in 2024.
Injecting drug use accounted for <1% of new diagnoses in East of England residents.
Black Africans represented 49% of all newly diagnosed East of England residents in 2024 (compared to 40% in 2023 and 29% in 2015). A small proportion of new diagnoses in 2024 were in Black Caribbeans (2%).
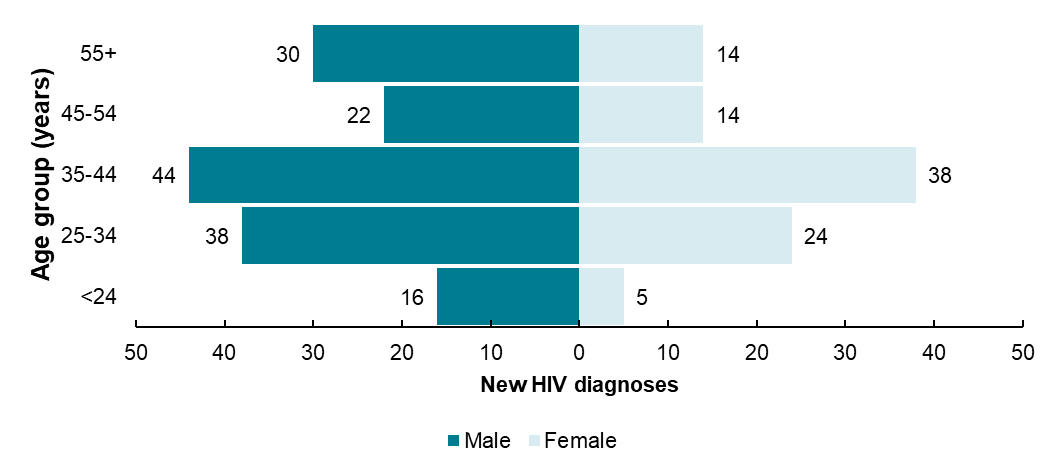
The number of new diagnoses was highest in the 35 to 44 year age group in both males and females in 2024.
Late diagnoses
Reducing late HIV diagnoses is one of the indicators in the Public Health Outcomes Framework and HIV Action Plan Monitoring and Evaluation Framework. People who are diagnosed late have a tenfold risk of mortality within one year of diagnosis compared to those diagnosed promptly and they have increased healthcare costs.
It is of particular concern that a large proportion of East of England residents with HIV are diagnosed late (49% from 2022 to 2024, compared to 43% in England), as defined by a CD4 count of less than 350 cells/mm at diagnosis.
In the East of England, heterosexuals were more likely to be diagnosed late (59% of males, 48% of females) than gay and bisexual men (38%). By ethnic group, Black Africans were more likely to be diagnosed late than the White population (52% and 50% respectively).
People living with diagnosed HIV
The 9,194 people living with diagnosed HIV in the East of England in 2024 was 6% higher than in 2023 and 43% higher than in 2015. This increase is partly due to the effectiveness of HIV treatment, which has reduced the number of deaths from HIV.
The diagnosed prevalence rate of HIV in the East of England in 2024 was 2 per 1,000 residents aged 15 to 59 years. This was equal to the 2 per 1,000 observed in England as a whole (small differences may be hidden by rounding). Six local authorities in the East of England had a diagnosed HIV prevalence in excess of 2 per 1,000 population aged 15 to 59 in 2024, which is the threshold for expanded HIV testing. They were Luton (3.9), Southend-on-Sea (3.5), Milton Keynes (3.4), Peterborough (2.9), Thurrock (2.6) and Bedford (2.5).
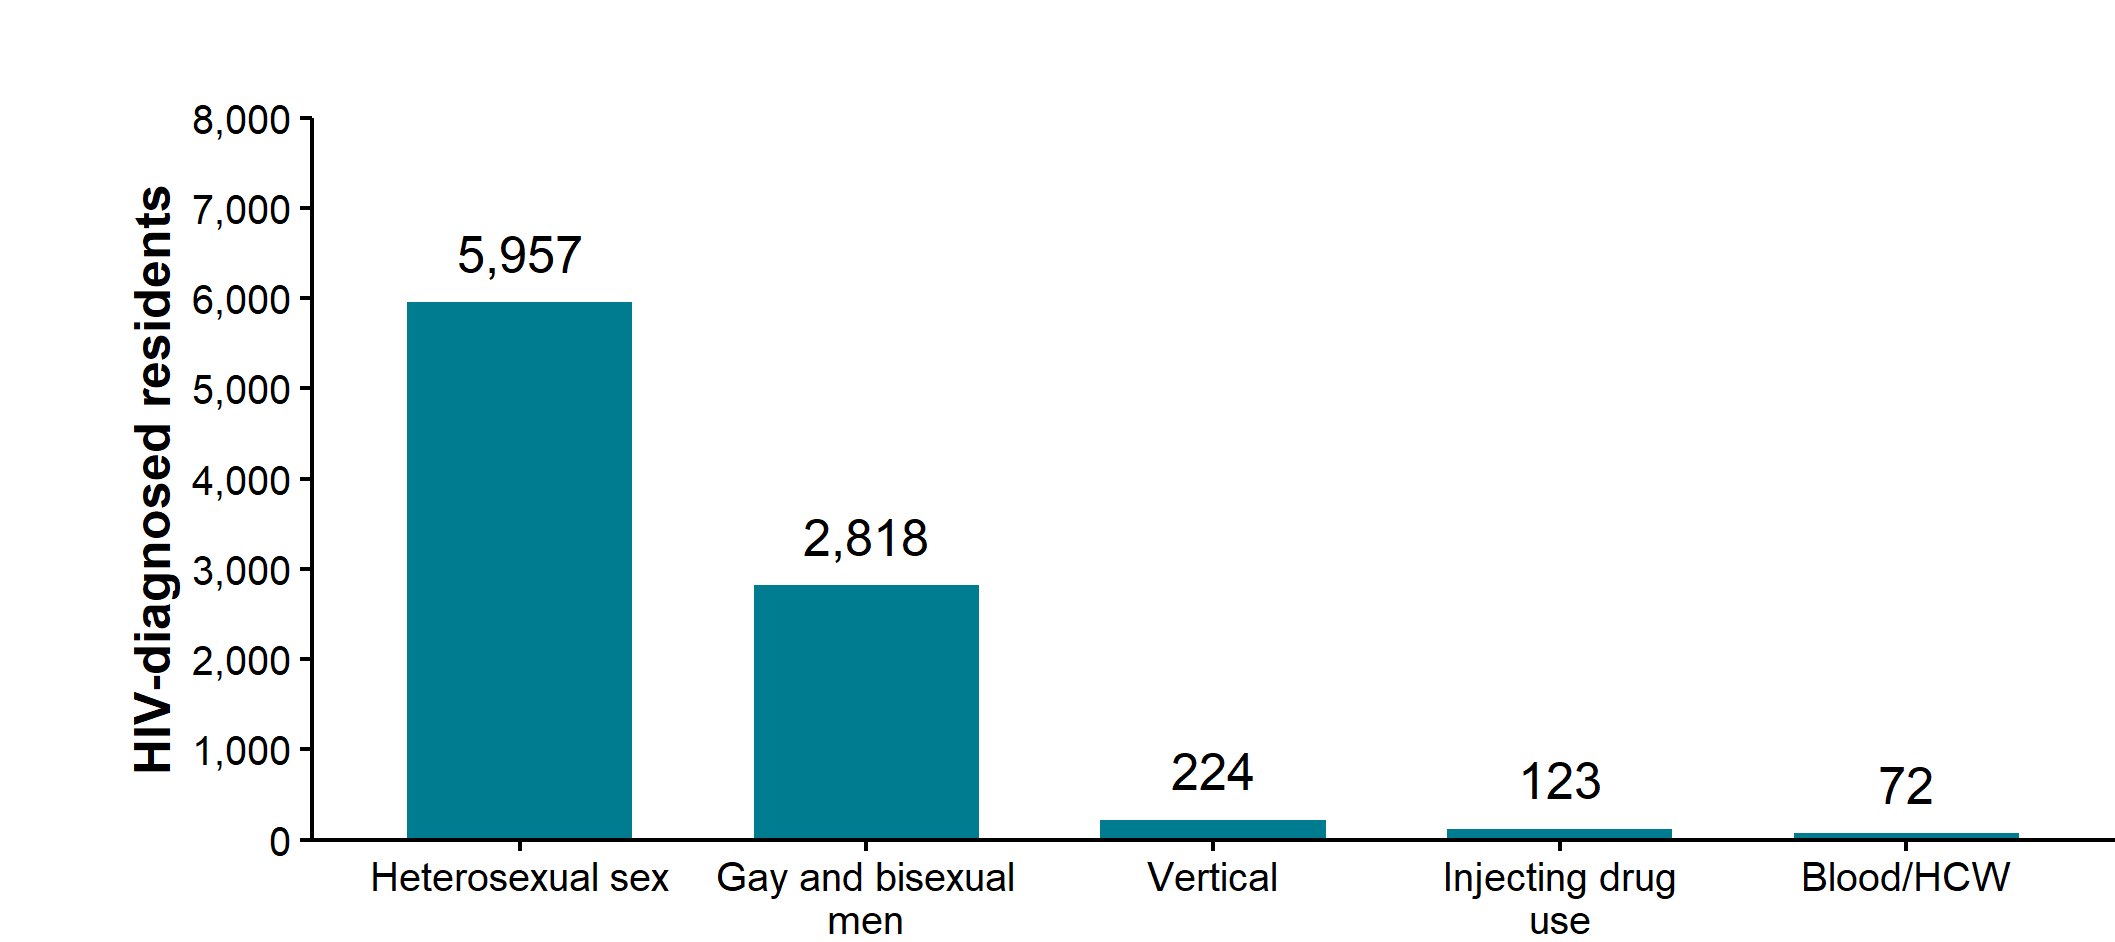
The 2 most common probable routes of exposure for East of England residents living with diagnosed HIV in 2024 were heterosexual sex (65%) and sex between gay and bisexual men (31%).
In 2024, 36% of those living with diagnosed HIV in the East of England were aged between 35 and 49 years, and 53% were aged 50 years and over (up from 32% in 2015). Males represented 56% of East of England residents living with diagnosed HIV in 2024 and females represented 44%.
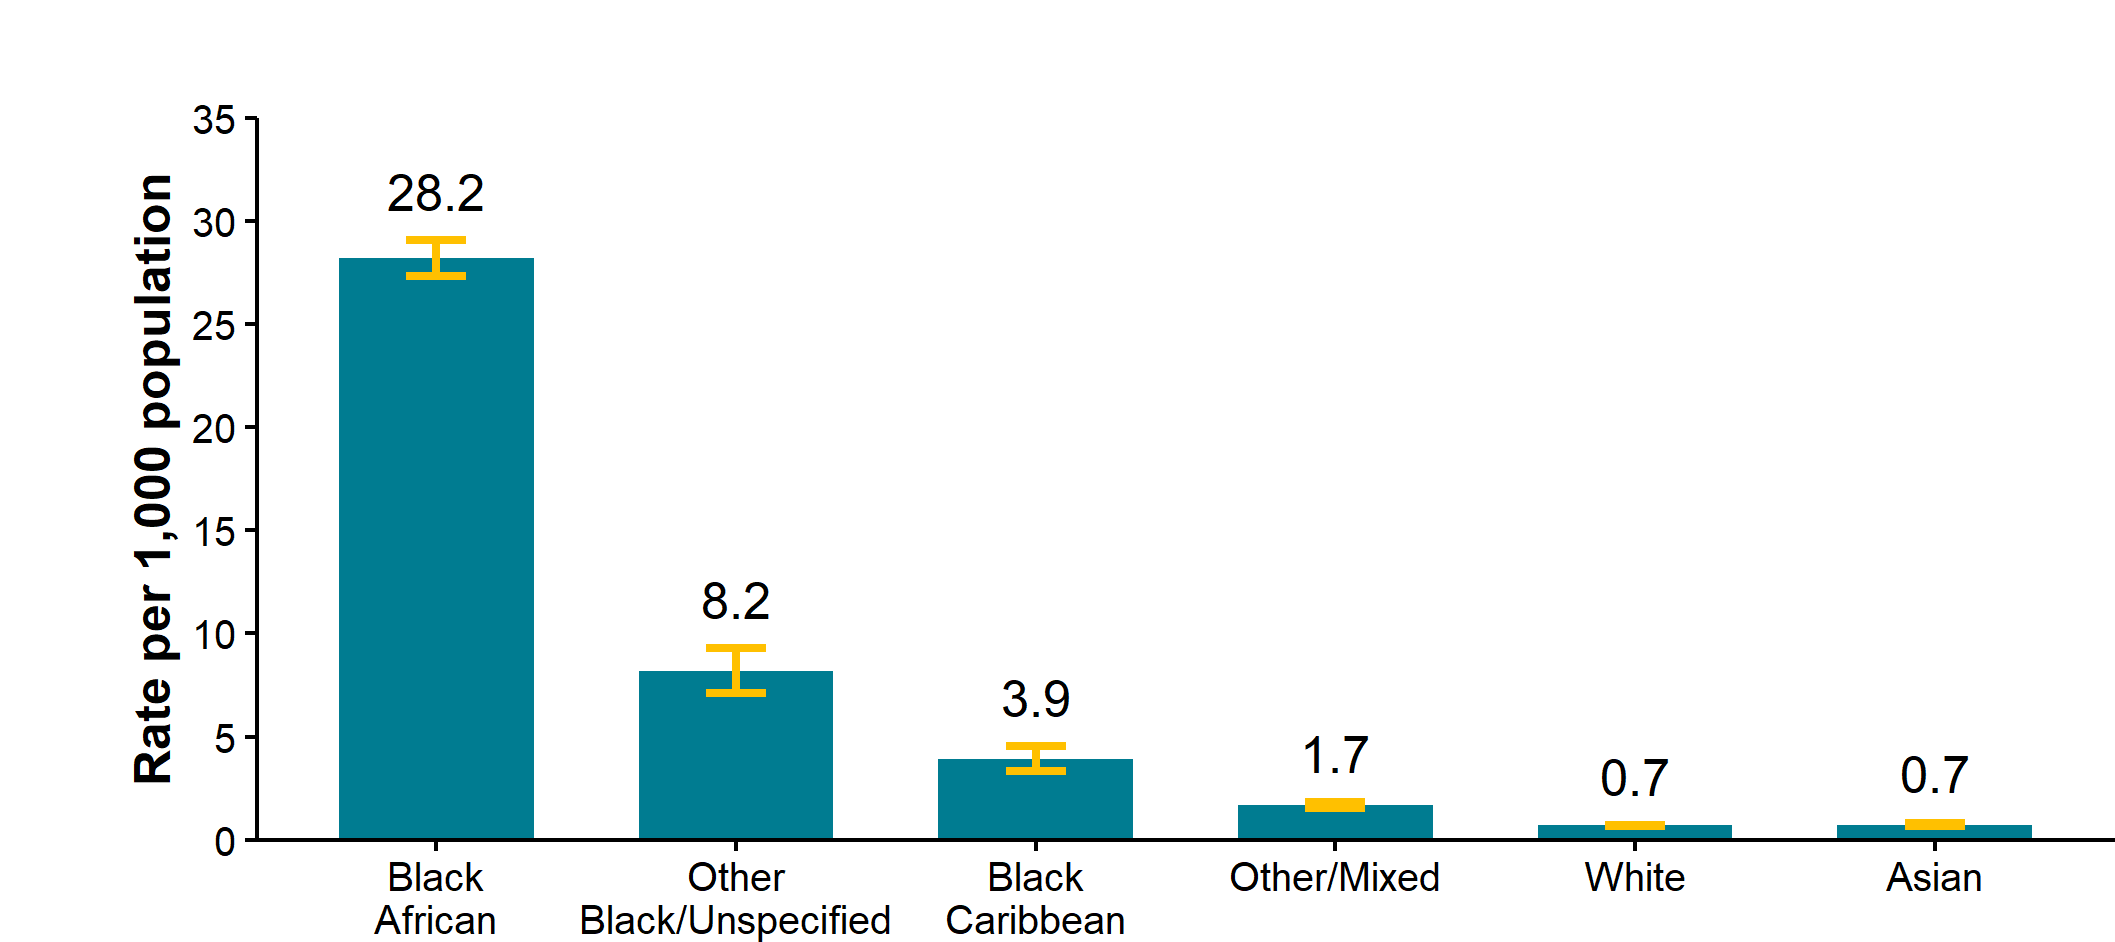
In 2024, 43% of East of England residents living with diagnosed HIV were White and 44% were Black Africans. However, due to the relative sizes of the White and Black African populations the rate per 1,000 population aged 15 to 59 years was much higher in Black Africans (28 per 1,000) than in the White population (1 per 1,000).
HIV testing
A total of 50,048 people were tested in specialist sexual health services (SHSs) in the East of England in 2024, an increase of 17% since 2020 and an increase of 12% since 2023. The HIV testing rate (per 100,000 population) at all SHSs in the East of England was 1,593, which compares to 2,843 across England. HIV testing rates in all SHSs (specialist and non-specialist services) in the East of England is higher in men (1,570) than women (1,321).
PrEP
In 2024, 8% of HIV-negative East of England residents accessing SHSs in England were defined as having a PrEP need, among whom 74% initiated or continued PrEP. Of those with PrEP need, 84% had this need identified at a clinical consultation. Among gay and bisexual men, the group with greatest need, these proportions were: 69%, 77% and 86%. Consistent use of PrEP can be an efficacious and effective intervention to prevent HIV acquisition. Despite PrEP being routinely available through specialist SHS, awareness, accessibility and uptake of primary prevention initiatives is variable for different population groups. Addressing this disparity is key to HIV prevention.
HIV in England
The HIV Action Plan for England, 2025 to 2030 was published on 1 December 2025. It sets UNAIDS 2025 ambitions to reduce HIV transmission (measured by new HIV diagnoses) and AIDS-related deaths by 90% between 2010 and 2030. New diagnoses among White gay and bisexual men are on track to reach the ambition, however further work is needed over the next 5 years for other population groups such as ethnic minorities gay and bisexual men, Black African and other ethnic minorities heterosexual populations. This is why HIV Official Statistics this year highlight progress along the HIV pathway for 5 population groups.
The number of people first diagnosed with HIV in England decreased by 2% in 2024 (2,838 in 2023 to 2,773)2. Gay and bisexual men accounted for almost 30% of new HIV diagnoses (810 of 2,773), with heterosexual men 23% (634) and heterosexual women 27% (749). Within and between these population groups, there remains evidence of considerable inequalities2. Further provision of services that are culturally competent and accessible to diverse populations is needed.
The number of new HIV diagnoses in England decreased by 6% (859 to 810) in 2024 for gay and bisexual men (2). However, this reduction was not seen consistently among all ethnic groups. While a reduction of 6% was observed among White gay and bisexual men (488 to 461), new HIV diagnoses increased among Black (15%, 80 to 92) and Asian (6%, 101 to 107) gay and bisexual men. Nearly half (48%, 386 of 810) of the gay and bisexual men newly diagnosed in England in 2024 were born abroad.
For heterosexuals, the number of new HIV diagnoses were similar in 2024 compared to 2023 (1,371 to 1,383), although numbers increased for heterosexual men (by 3%, 615 to 634) and decreased marginally for heterosexual women (by 1%, 755 to 749)2. As with gay and bisexual men, for heterosexuals, there was considerable variation between ethnic groups. Notably, new HIV diagnoses among Black African heterosexual men increased by 15% (231 to 265) but decreased by 5% among Black African heterosexual women (441 to 418). Of the heterosexual men newly diagnosed in 2024, 27% (170 of 634) were known to be born in the UK and 68% (431 of 634) abroad. Among women, 15% (116 of 749) were known to be born in the UK and 77% (580 of 749) abroad.
Overall, the number of people tested for HIV in sexual health services (SHSs) in England was 3% higher in 2024 than 2023 but has not fully recovered to pre-pandemic (2019) levels for all groups. Whereas testing increased markedly within specialist SHSs (9%), non-specialist online testing declined by 4% in 2024. The proportion of people tested through online consultations at all SHSs (compared to face-to-face) fell by 3%, continuing a year-on-year reduction in this proportion since a peak in 2021. There was a 7% decrease in the HIV testing rate in all SHSs in people aged 15 to 24 years. This compares to a continued increase in the HIV testing rate in all other age groups.
Testing increases were observed across gender and sexual orientation groups (gay and bisexual men, 2%; heterosexual men, 5%; heterosexual woman, 2%). Consistently increased testing for gay and bisexual men, coupled with an overall decline in HIV test positivity (0.3% in 2020 to 0.2% in 2024) suggests that there may be a reduction in transmission in this community. HIV test positivity in heterosexual men and women has remained similar in 2023 and 2024 (0.05% to 0.06%, and 0.08% to 0.08%, respectively). The programme of emergency departments (ED) opt-out testing for bloodborne viruses continues to be a successful approach for HIV diagnoses, contributing to 8% of all new HIV diagnoses in 2024.
The number of people diagnosed with HIV before continuing care in England fell markedly in 2024 (3,363 to 2,525) with a corresponding 15% drop in all HIV diagnoses (6,201 to 5,298). The reduction in the number of people diagnosed before continuing care in England was most pronounced in heterosexual women (33%), compared to reductions in heterosexual men (11%) and gay and bisexual men (21%). The decline in the number of people diagnosed before continuing care in England in 2024 varied by ethnic group. The largest proportionate reductions in numbers (compared to 2023) were seen in people of Black Other (30%; 79 to 55), Black African (28%; 2,196 to 1,587), Asian (25%; 228 to 172), Other or Mixed (25%; 288 to 216) and White (22%; 326 to 253) ethnicities.
The number of people receiving HIV pre-exposure prophylaxis (PrEP) via SHSs has been increasing on an annual basis since 2020, increasing by 7.7% between 2023 and 2024 (111,123 in 2024 versus 103,138 in 2023). However, inequalities in access remain. While the overall number of gay and bisexual men with unmet HIV PrEP need was highest, there is proportionally greater unidentified and unmet PrEP need among heterosexual men and women.
Despite a 2% decrease in the number of adults being diagnosed late between 2023 and 2024 (950 to 928), 42% (928 of 2,196) of the new HIV diagnoses were made at a late stage in England in 2024. Reductions in the number of late HIV diagnoses fell most among gay and bisexual men (11%) compared with heterosexual women (4%) and heterosexual men (1%). The percentage of new diagnoses that were late for all 3 groups remained similar to 2023 (45% to 46%, 53% to 52%, 31% to 30% for heterosexual women, heterosexual men, and gay and bisexual men, respectively). In 2024, half of adult Black African heterosexuals newly diagnosed with HIV were diagnosed late (285 of 572; 50%). People diagnosed late with HIV in England in 2023 were 10 times more likely to die within a year of their diagnosis, compared to those diagnosed promptly.
Provisional estimates are that 95% of all adults living with HIV in England are diagnosed, with 99% of diagnosed adults receiving treatment, and 98% of adults on treatment having suppressed viral loads.
HIV prevention messages
Using condoms consistently and correctly protects against HIV and other STIs such as chlamydia, gonorrhoea and syphilis. They can also be used to prevent unplanned pregnancy.
HIV testing is central to HIV prevention since it provides access to PrEP and health advice for people testing HIV negative, while a positive result leads to essential HIV care and treatment, supporting a long healthy life whilst preventing onwards transmission. Everyone should have an STI screen, including an HIV test, on at least an annual basis, if having condomless sex with new or casual partners. Gay and bisexual men should have tests for HIV and STIs annually, or every 3 months if having condomless sex with new or casual partners.
HIV PrEP is available for free from specialist SHSs and can be used to reduce an individual’s risk of acquiring HIV. Consistent use of PrEP can be an efficacious and effective intervention to prevent HIV acquisition. Despite PrEP being routinely available through specialist SHSs, awareness, accessibility and uptake of primary prevention initiatives such as HIV PrEP is variable for different population groups.
HIV post-exposure prophylaxis (PEP) can be used to reduce the risk of acquiring HIV following some sexual exposures. PEP is available for free from specialist SHSs and most emergency departments. Symptoms due to HIV may not appear for many years, and people who are unaware of living with HIV may not feel themselves to be a risk to others. Prevention messages should reinforce that anyone can acquire HIV regardless of age, gender, ethnicity, sexuality or religion, and it is important to challenge assumptions about who is at risk of acquiring HIV.
People living with diagnosed HIV who are on treatment and have an undetectable viral load are unable to pass on the virus to others during sex, even without PrEP or condoms. This is known as Undetectable = Untransmittable or U=U.
Stigma, anxiety and depression experienced by people with HIV affect their ability to seek healthcare, engage in treatment and remain in care. Reducing stigma in healthcare services will encourage people from seeking the healthcare services they need.
Specialist SHSs are free and confidential. They offer testing and treatment for HIV and STIs, condoms, vaccination, HIV PrEP and PEP. Clinic-based services are commissioned by local authorities for residents of all areas in England and online self-sampling for HIV and STIs is widely available. Information and advice about sexual health including how to access services is available at NHS.UK and from the national sexual health helpline on 0300 123 7123.
Local and regional prevention strategies
HIV prevention strategies at a local and regional level should consider inclusion of all actions published recently in the national HIV Action Plan for England (HIVAP). Below are some examples of how this could be done, focusing on each of the 5 HIVAP priorities:
Prevent
- ensure localities are aware that there is central funding for formula milk (and related sterilised equipment) for the infants of women living with HIV
- drive forward HIV service improvements and innovation with a focus on reducing inequalities in HIV testing, access to HIV PrEP and PEP
- collate evidence and best practice of HIV PrEP provision pilot studies
Test
- implement and monitor BHIVA, British Association for Sexual Health and HIV (BASHH) and British Infection Association (BIA) Adult HIV testing guidelines 2020, including opt-out in SHSs and reduce inequalities in HIV testing
- continue ED opt-out testing in very high and high prevalence HIV areas
- work with GP practices to promote HIV testing into routine primary care pathways
- scale up partner notification activities
- understand the drivers of late diagnosis in order to better focus interventions
Treat
- share learnings from UKHSA audits with local networks and encourage provision of peer support and psychological support within HIV treatment services
- ensure commissioning arrangements are in place with local providers for HIV peer support provision
- ensure local SHSs and HIV services engage with and learn from retention in care reviews to strengthen pathways
Thrive
- ensure services provide a holistic approach to HIV care for women, signposting to other services, such as partner violence services and menopause clinics, when needed
- improve the quality of life for people living with HIV, including promotion of U=U, particularly for older adults and people with complex health and care needs, by commissioning integrated, person-centred support services that address physical, mental and social wellbeing
Collaborate
- share culturally competent education and awareness of new technologies as they become available to enhance national messaging
- apply and promote the HIV Low Prevalence Toolkit to guide local planning, commissioning and evaluation and strengthen outreach, primary care partnerships and service visibility to ensure equitable access to prevention, treatment and care in low prevalence areas
East of England HIV Action Plan
In 2025, work commenced across the East of England to bring together new and existing HIV‑related priorities in a more coordinated and systematic way. A regional HIV Action Plan, structured around a 6‑pillar approach, was adopted to align with the ambitions of the national HIVAP outlined above. An additional cross‑cutting element focused on building foundations was included to ensure that regional activity is underpinned by robust data, intelligence and surveillance.
Each pillar is supported by a lead and deputy, alongside group members drawn from a broad range of regional partners, including commissioners, clinicians, public health specialists and colleagues from UKHSA. The East of England approach to HIV elimination was formally launched in January 2026 and is being delivered as a 5‑year programme.
Charts, tables and maps
Figure 1. Rate of new HIV diagnoses per 100,000 population (all ages) by UKHSA region of residence, 2024
Source: UKHSA, HIV & AIDS New Diagnoses and Deaths (HANDD). The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Figure 1 is a bar chart showing the rate of new HIV diagnoses per 100,000 population for all ages by UKHSA region of residence in 2024. 95% confidence intervals are displayed in yellow, the overall England rate (4.7 per 100,000) is shown as a grey line, and the East of England is in light blue.
The East of England (light blue) has the fourth lowest rate of new HIV diagnoses (3.6 per 100,000). The East of England rate is lower than the overall England rate, with confidence intervals below the England line.
London (10.7 per 100,000) has the highest rate of new HIV diagnoses, significantly higher than the rate for England overall, and all other regions. The rate for the West Midlands (4.2 per 100,000) is similar to the national rate, with confidence intervals crossing the national line. All other regions had a new HIV diagnosis rate significantly lower than England.
Figure 2. Rate of new HIV diagnoses per 100,000 population (all ages) by upper tier local authority of residence, East of England residents, 2024
Source: UKHSA, HIV & AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. HIV diagnosed prevalence (rate per 1,000 aged 15 to 59 years as per NICE testing guidelines). Lower diagnosed prevalence less than 2, high diagnosed prevalence 2 to 5, Extremely high diagnosed prevalence more than 5.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Colour coding of bars does not relate to new diagnosis but to the data in the diagnosed prevalence section later.
Figure 2 is a bar chart showing the rate of new HIV diagnoses per 100,000 East of England residents for all ages by upper tier local authority of residence for 2024. 95% confidence intervals are shown in yellow, and the overall East of England rate is a dashed line (3.6 per 100,000).
The shading of the bars reflects their status as either a high prevalence area in green (2 to 5 per 100,000), or low prevalence in light blue (less than 2 per 100,000). No upper tier local authorities in the East of England had an extremely high diagnosed prevalence of more than 5 per 100,000).
Luton, Peterborough, Southend-on-Sea, Milton Keynes, Thurrock and Bedford are all high diagnosed prevalence areas (green). Hertfordshire, Cambridgeshire, Essex, Norfolk, Suffolk and Central Bedfordshire are low diagnosed prevalence areas (light blue). There were no upper tier local authorities in the East of England with an extremely high diagnosed prevalence (more than 5).
Figure 3. New HIV diagnoses and deaths, the East of England, 2015 to 2024 [note 1]
Source: UKHSA, HIV & AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. Numbers may rise as we receive more reports and more information. This will impact on interpretation of trends in more recent years. New HIV diagnoses are shown by UK region of residence at diagnosis. Deaths are shown by UK region of death which in some instances may not be the same as UK region of residence at diagnosis. Region of death may not be known for all deaths, particularly for those in the most recent years. Numbers for these years should be interpreted as minimum numbers (deaths reported and allocated to a region of death to date) and not as a trend.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 3 is a line chart showing the number of new HIV diagnoses (teal) and deaths (light blue) among those diagnosed with HIV by year for 2015 to 2024. The deaths displayed are all cause deaths and include mortality due to AIDS and non-HIV related deaths.
Between 2015 and 2020 there was a declining trend in the number of new HIV diagnoses. From 2020, a year impacted by the COVID-19 pandemic, the number of new HIV diagnoses increased to a peak in 2023, before decreasing in the most recent year. Overall, between 2015 and 2024 the number of new HIV diagnoses decreased by 30% (from 346 in 2015 to 245 in 2024).
The number of deaths among individuals diagnosed with HIV shows an increasing trend, from 19 deaths in 2015 to 77 in 2024.
Figure 4. HIV diagnoses by whether a person had been diagnosed with HIV before continuing care in England, the East of England, 2020 to 2024 [note 1]
Source: UKHSA, HIV & AIDS New Diagnoses and Deaths (HANDD).
The number of diagnoses will depend on accessibility of testing as well as infection and transmission.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 4 is a bar chart showing the number of HIV diagnoses among East of England residents by whether they were first diagnosed in England (teal) or diagnosed with HIV before continuing care in England (light blue) from 2020 to 2024.
In 2020 and 2021, the number of HIV diagnoses for both those diagnosed before continuing care in England and diagnoses first made in England remained similar, with a higher proportion of diagnoses first made in England.
In 2023, the number of diagnoses among individuals who had been diagnosed abroad before continuing care in England increased substantially and for the first time exceeded the number of diagnoses first made in England, a pattern that was also seen nationally. In 2024, the number of diagnoses decreased, but remained higher than diagnoses first made in England.
Figure 5. New HIV diagnoses by probable route of exposure (adjusted for missing route information), East of England residents, 2015 to 2024 [note 1]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 5 is a line chart showing the number of new HIV diagnoses first diagnosed in England by probable route of infection for East of England residents by year of diagnoses from 2015 to 2024. Probable routes of infection shown are sex between gay and bisexual men (teal), heterosexual sex (light blue) and other exposure routes (blue). The data has been adjusted to account for missing probable route of infection.
Between 2015 and 2024, the number of new HIV diagnoses likely acquired through sex between gay and bisexual men shows an overall declining trend, decreasing from 138 new diagnoses in 2015 to 65 in 2024.
The trend for new diagnoses likely due to heterosexual sex fluctuated considerably between 2015 and 2024, however between 2020 and 2023 there were year on year increases before declining in 2024.
The trend for other infection routes fluctuates year on year due to small numbers. Overall, the number of new diagnoses decreased from 19 in 2015, to 7 in 2024.
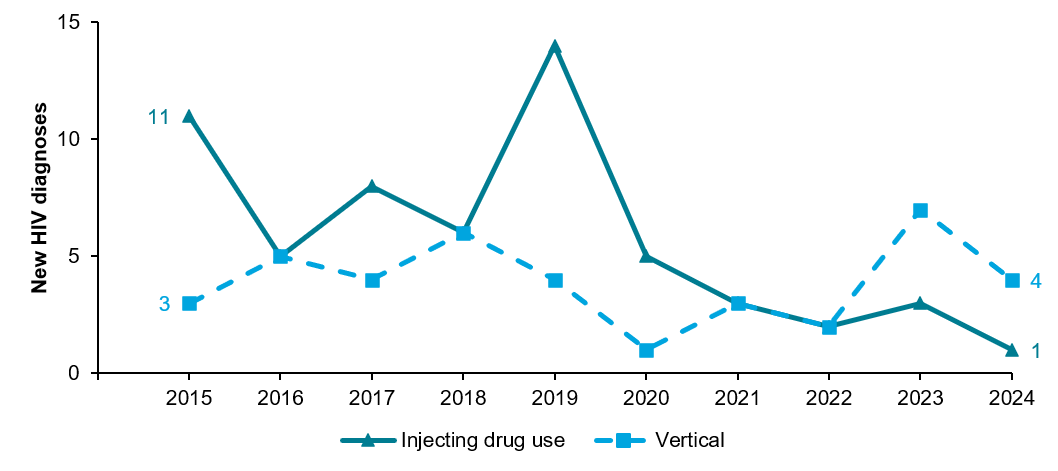
Figure 6. New HIV diagnoses detailed ‘other’ route of exposure (not adjusted for missing information), East of England residents, 2015 to 2024 [note 1]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 6 is a line chart showing the number of new HIV diagnoses among East of England residents first diagnosed in England by year of diagnoses from 2015 to 2024 for ‘other’ probable routes of exposure. Injecting drug use is shown in dark blue and vertical transmission as a blue dashed line. Due to small numbers, there is fluctuation from year to year for each exposure category.
Between 2015 and 2020, injecting drug use was the ‘other’ probable exposure category that accounted for the highest number of new diagnoses. In 2023 and 2024, vertical transmission accounted for the highest number of new diagnoses.
In 2024, by ‘other’ probable route of exposure there were 4 vertical transmissions (blue dashed line), and 1 injecting drug use (teal).
Figure 7. Number of new HIV diagnoses by age group and gender, East of England residents, 2024
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infections and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Figure 7 is an age-sex pyramid showing the number of new HIV diagnoses by age group and gender among East of England residents in 2024. Males are shown in teal on the left and females in light blue on the right.
Among males, the highest number of new HIV diagnoses were among those aged 35 to 44 (n=44), followed by those aged 25 to 34 (n=38).
Among females, the highest number of new diagnoses were also among those aged 35 to 44 (n=38), followed by 25 to 34 (n=24).
Figure 8. Number of new HIV diagnoses by age group and gender, split by whether first diagnosed in the UK or abroad, East of England residents, 2024
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infections and transmission.
Figure 8 is a chart showing 2 age-sex pyramids. Both pyramids show the number of new HIV diagnoses among East of England residents by age group and gender in 2024. The pyramid on the left shows those diagnosed before continuing care in England, and the pyramid on the right shows those first diagnosed in England. Males are shown in teal and females in light blue.
The age-sex distribution of HIV diagnoses in 2024 shows slightly different patterns for those first diagnosed in England and those diagnosed before continuing care in England.
A higher proportion of females are diagnosed before continuing care in England (56%, n=184) compared to males (44%, n=146). Whereas for those who were first diagnosed in England, males made up 61% of new diagnoses, compared to 39% of females (males n=150, females n=95).
By age group, for those diagnosed with HIV before continuing care in England the largest number of diagnoses in both males and females were among those aged 35 to 44 years, followed by those aged 25 to 35 and 45 to 54. Within the 35 to 44 age group, females accounted for 65% (n=90) of diagnoses. The fewest diagnoses were observed in the youngest (under 24) and oldest (55 and over) age groups.
For diagnoses first made in England, the highest number of diagnoses for both males and females were among the 25 to 34 and 35 to 44 age groups. Diagnoses in those aged 55 and over accounted for 19% of all diagnoses first made in England, compared to 7% in those diagnosed before continuing care in England.
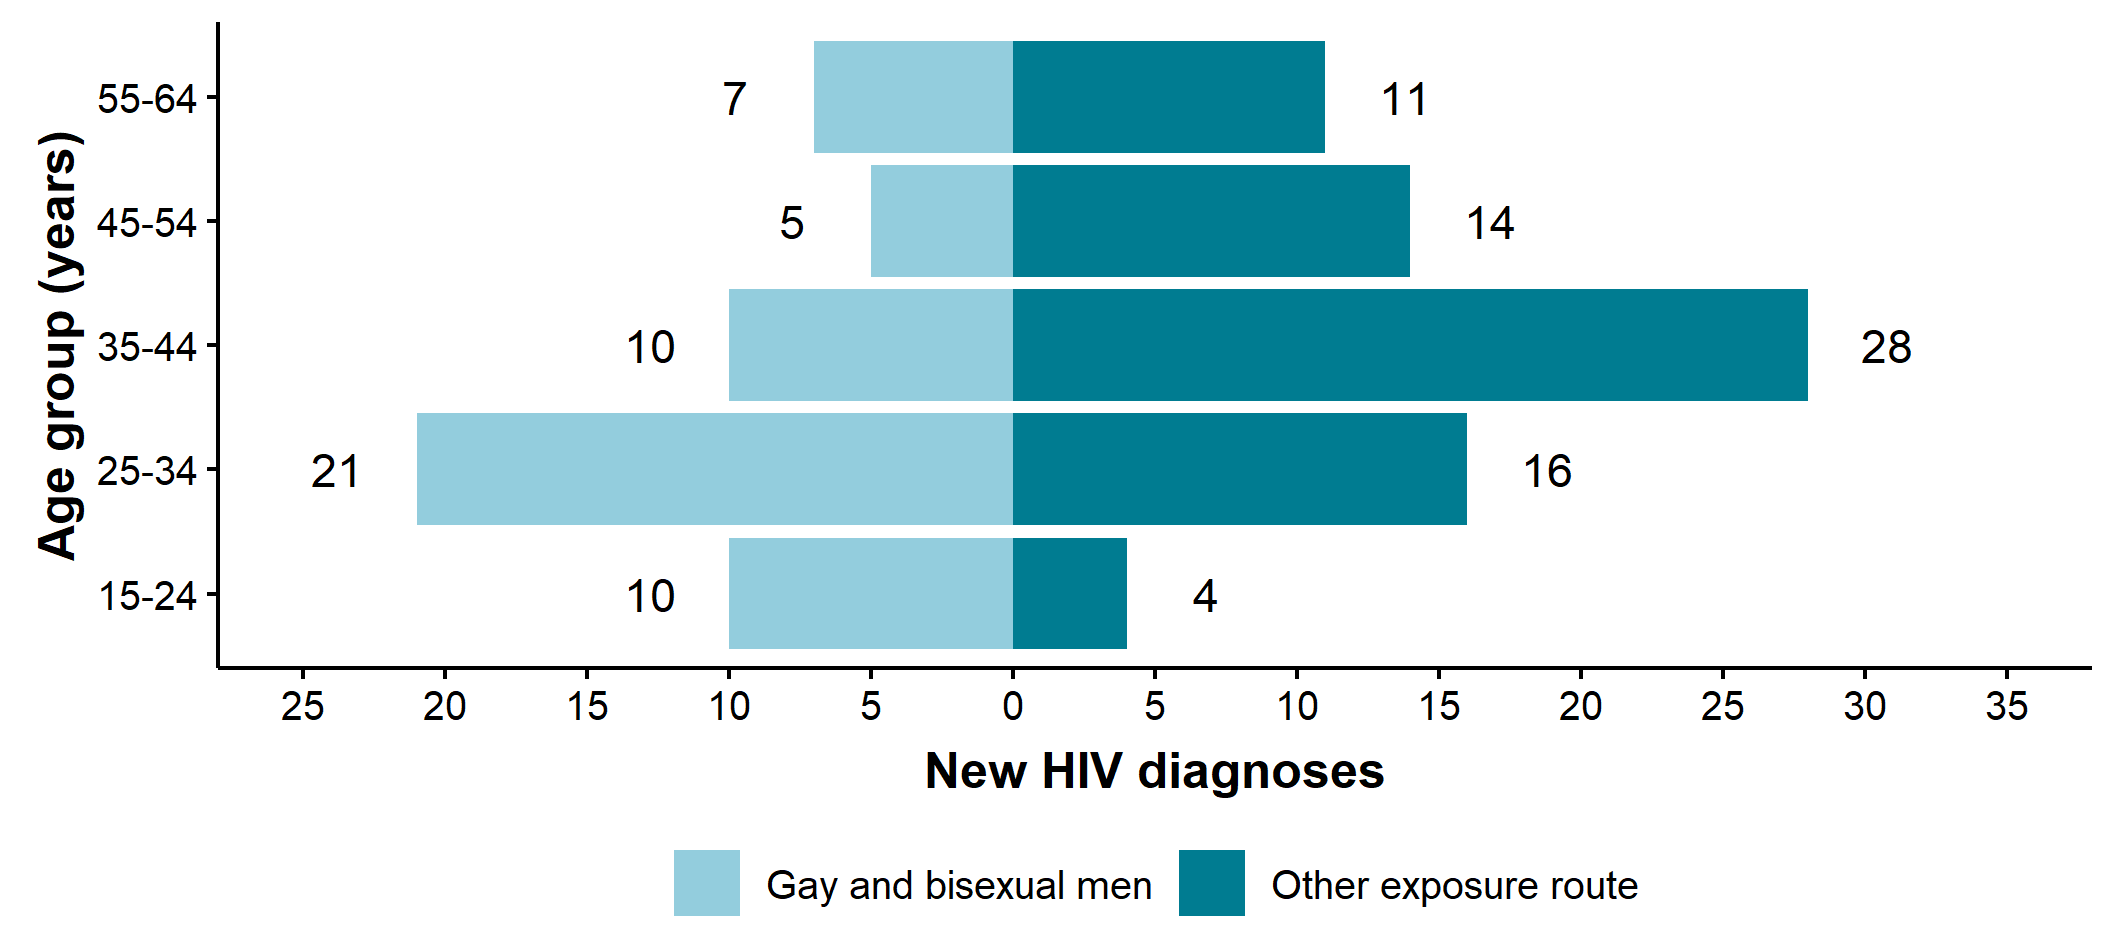
Figure 9. Number of new HIV diagnoses by age group and probable route of exposure, male East of England residents aged 15 to 64 years, 2024
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Figure 9 is an age-sex pyramid showing the number of new HIV diagnoses among male East of England residents aged 15 to 64 by age group and probable route of infection for 2024. Sex between gay and bisexual men is shown in light blue, and all other exposure routes in teal.
Among new HIV diagnoses likely acquired through sex between gay and bisexual men, those aged 25 to 34 had the highest number of new diagnoses (n=21), followed by those aged 15 to 24 (n=10) and 35 to 44 (n=10).
Among new HIV diagnoses likely due to all other exposure routes, those aged 35 to 44 had the highest number of new diagnoses (n=28), followed by those aged 25 to 34 (n=39).
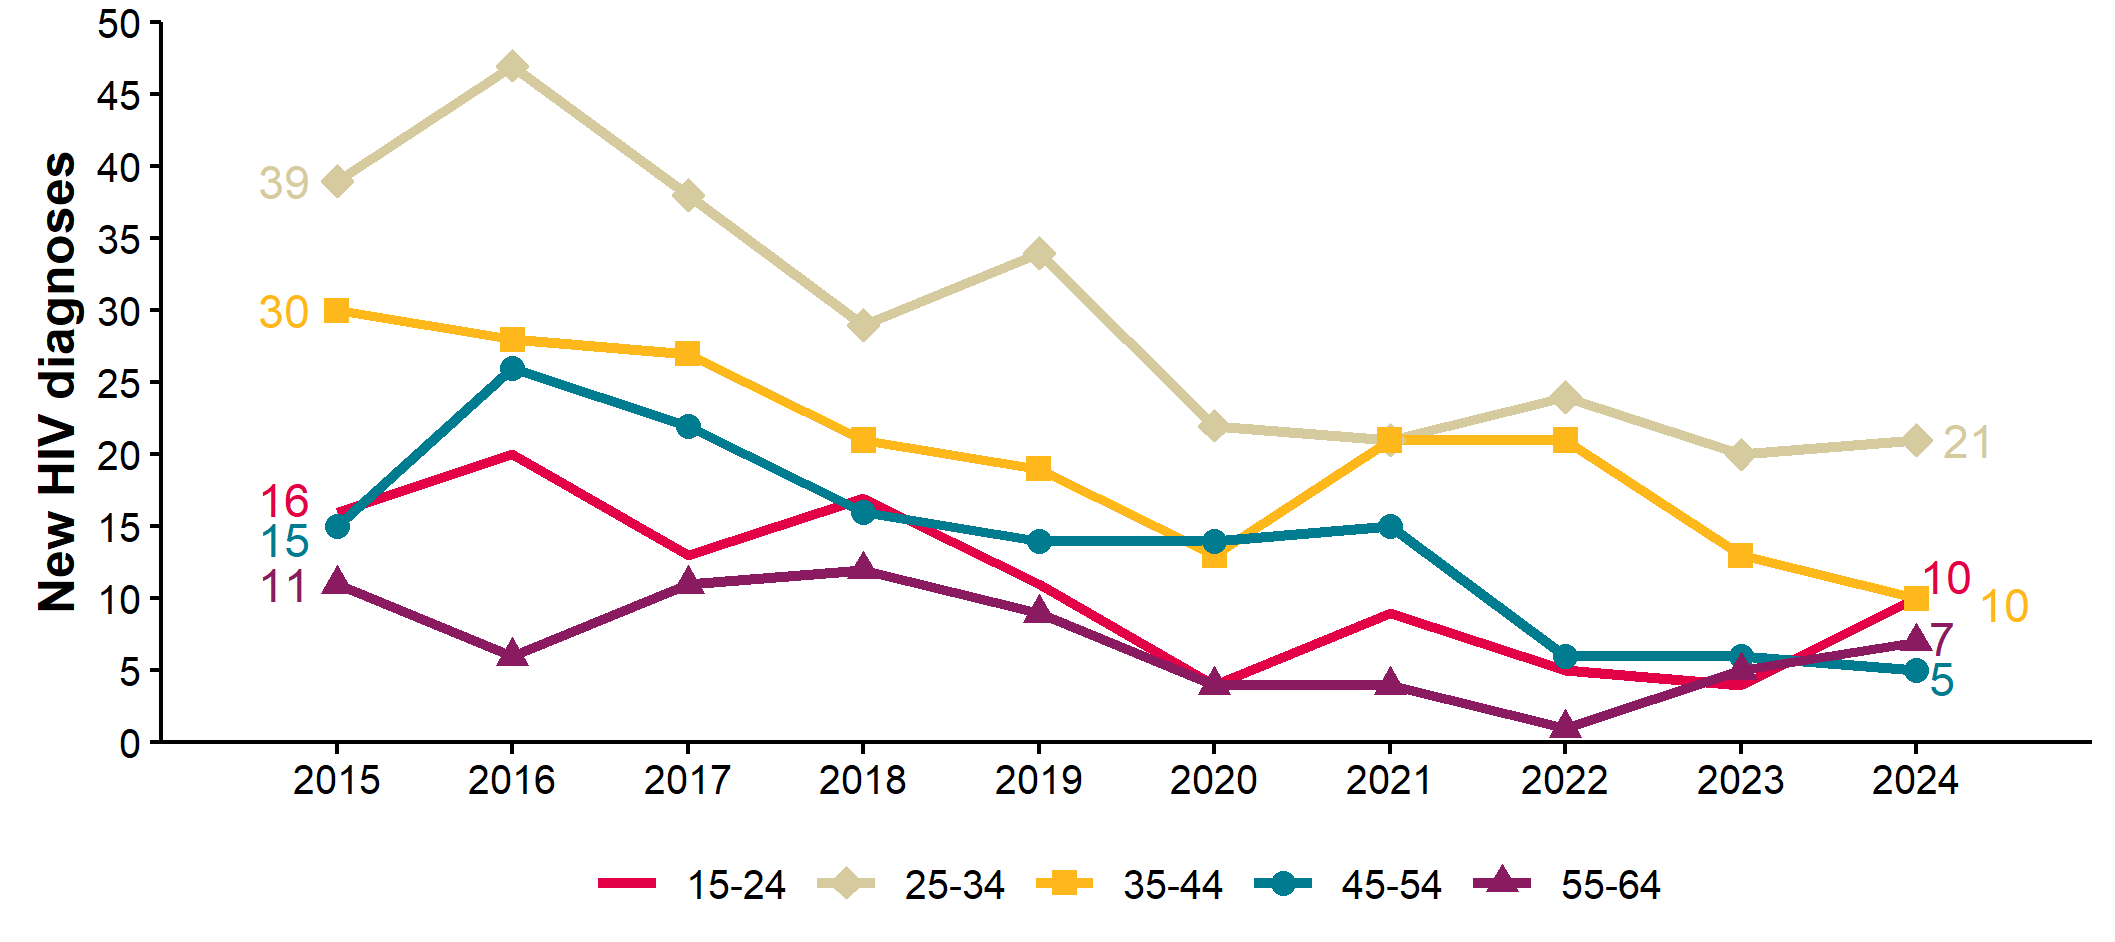
Figure 10. Number of new HIV diagnoses with a probable route of exposure through sex between gay and bisexual men by age group and year of first UK HIV diagnosis, East of England residents aged 15 to 64 years, 2015 to 2024 [note 1]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 10 is a line chart showing the number of new HIV diagnoses with the probable exposure route of sex between gay and bisexual men for East of England residents aged 15 to 64 by age group and year of first UK HIV diagnosis.
Overall, between 2015 and 2024 there has been a decrease in the number of new HIV diagnoses among all age groups although there are some fluctuations from year to year. Those aged 25 to 34 consistently have the highest number of new HIV diagnoses, followed by those aged 35 to 44.
In 2024, the highest number of new diagnoses were among those aged 25 to 34 (n=21), followed by 35 to 44 and 15 to 24 (n=10), 55 to 64 (n=7) and 45 to 54 (n=5).
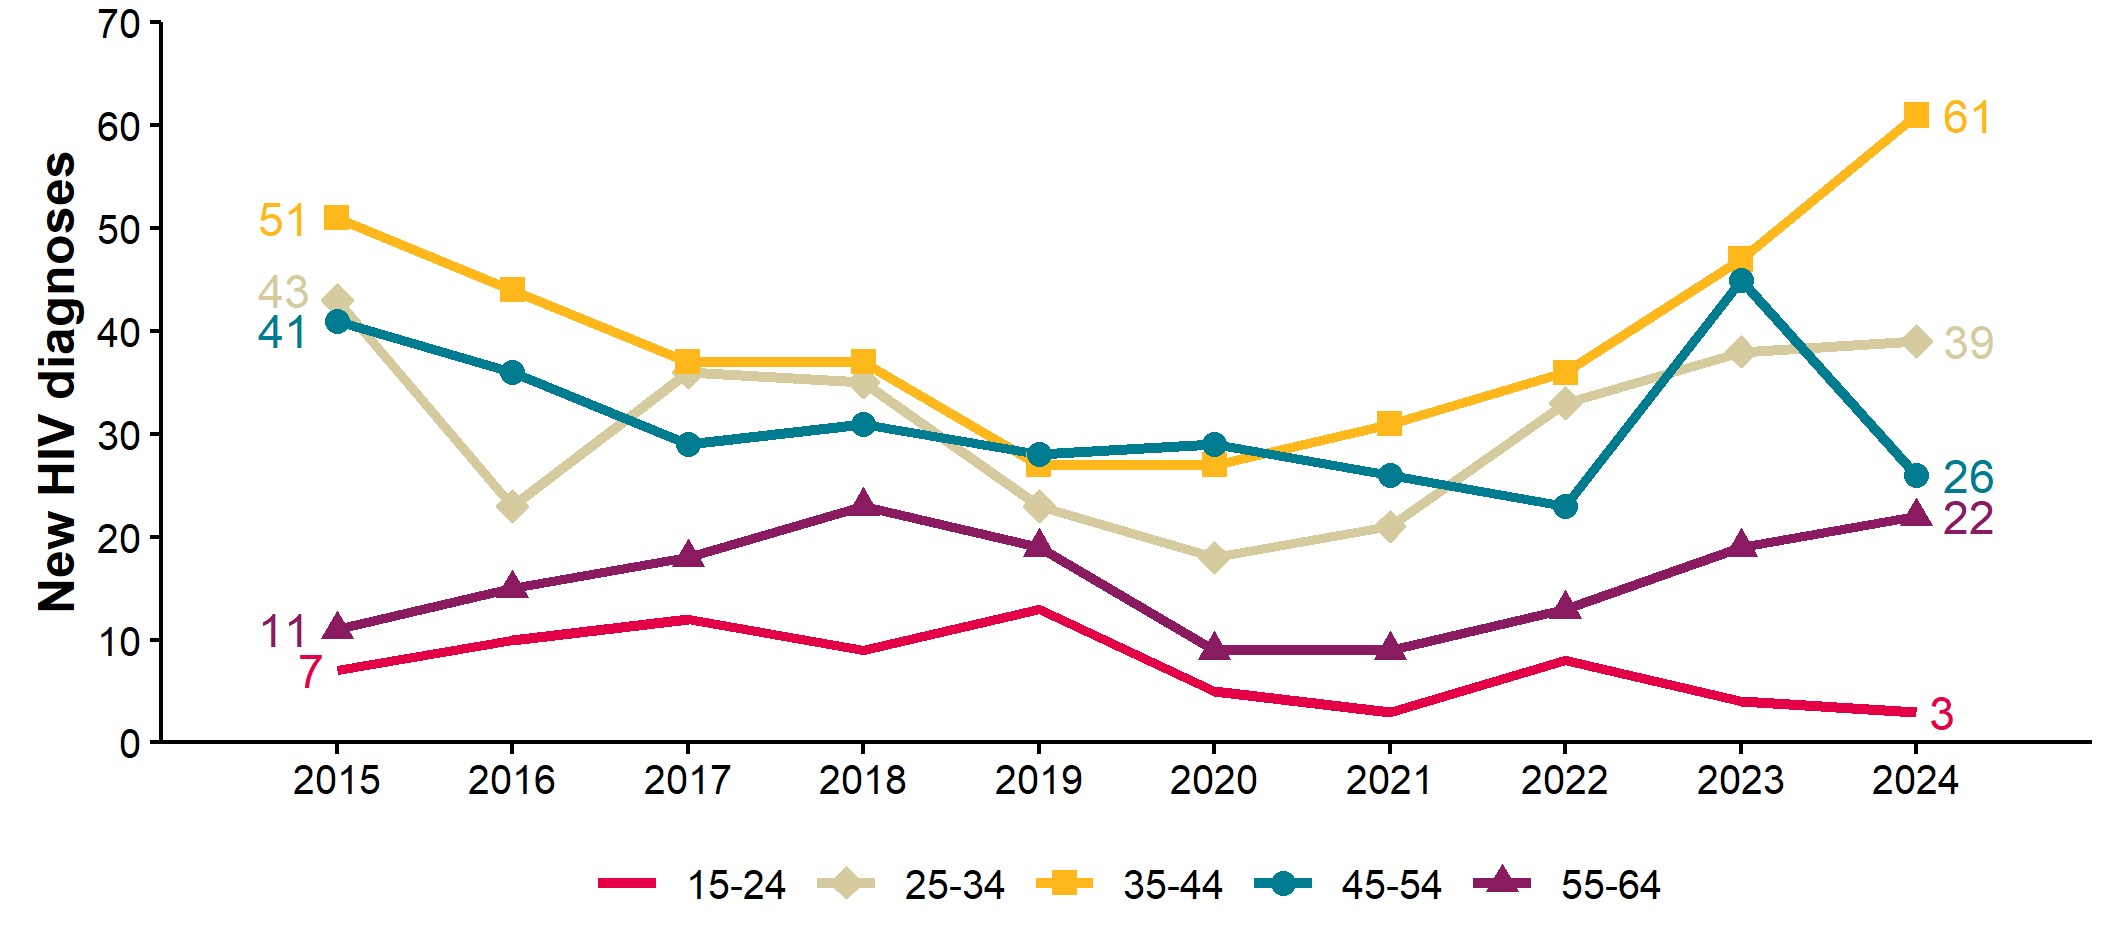
Figure 11. Number of new HIV diagnoses with a probable route of exposure through heterosexual sex by age group (in years) and year of first HIV diagnosis, East of England residents aged 15 to 64 years, 2015 to 2024 [note 1]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 11 is a line chart showing the number of new HIV diagnoses among East of England residents aged 15 to 64 with a probable exposure route of heterosexual sex by age group and year of first HIV diagnosis in the UK.
Between 2015 and 2021 in general a decreasing trend in the number of new HIV diagnoses was seen for each age group, however since 2021 increases were seen for almost all age groups. Between 2015 and 2024 there was an increase in the number of new HIV diagnoses among those aged 35 to 44 and 55 to 64, whereas decreases were seen for the 15 to 24, 45 to 54 and 25 to 34 age groups.
In 2024, the highest number of new HIV diagnoses were among those aged 35 to 44 (n=61), followed by 25 to 34 (n=39), 45 to 54 (n=26), 55 to 64 (n=22) and 15 to 24 (n=3).
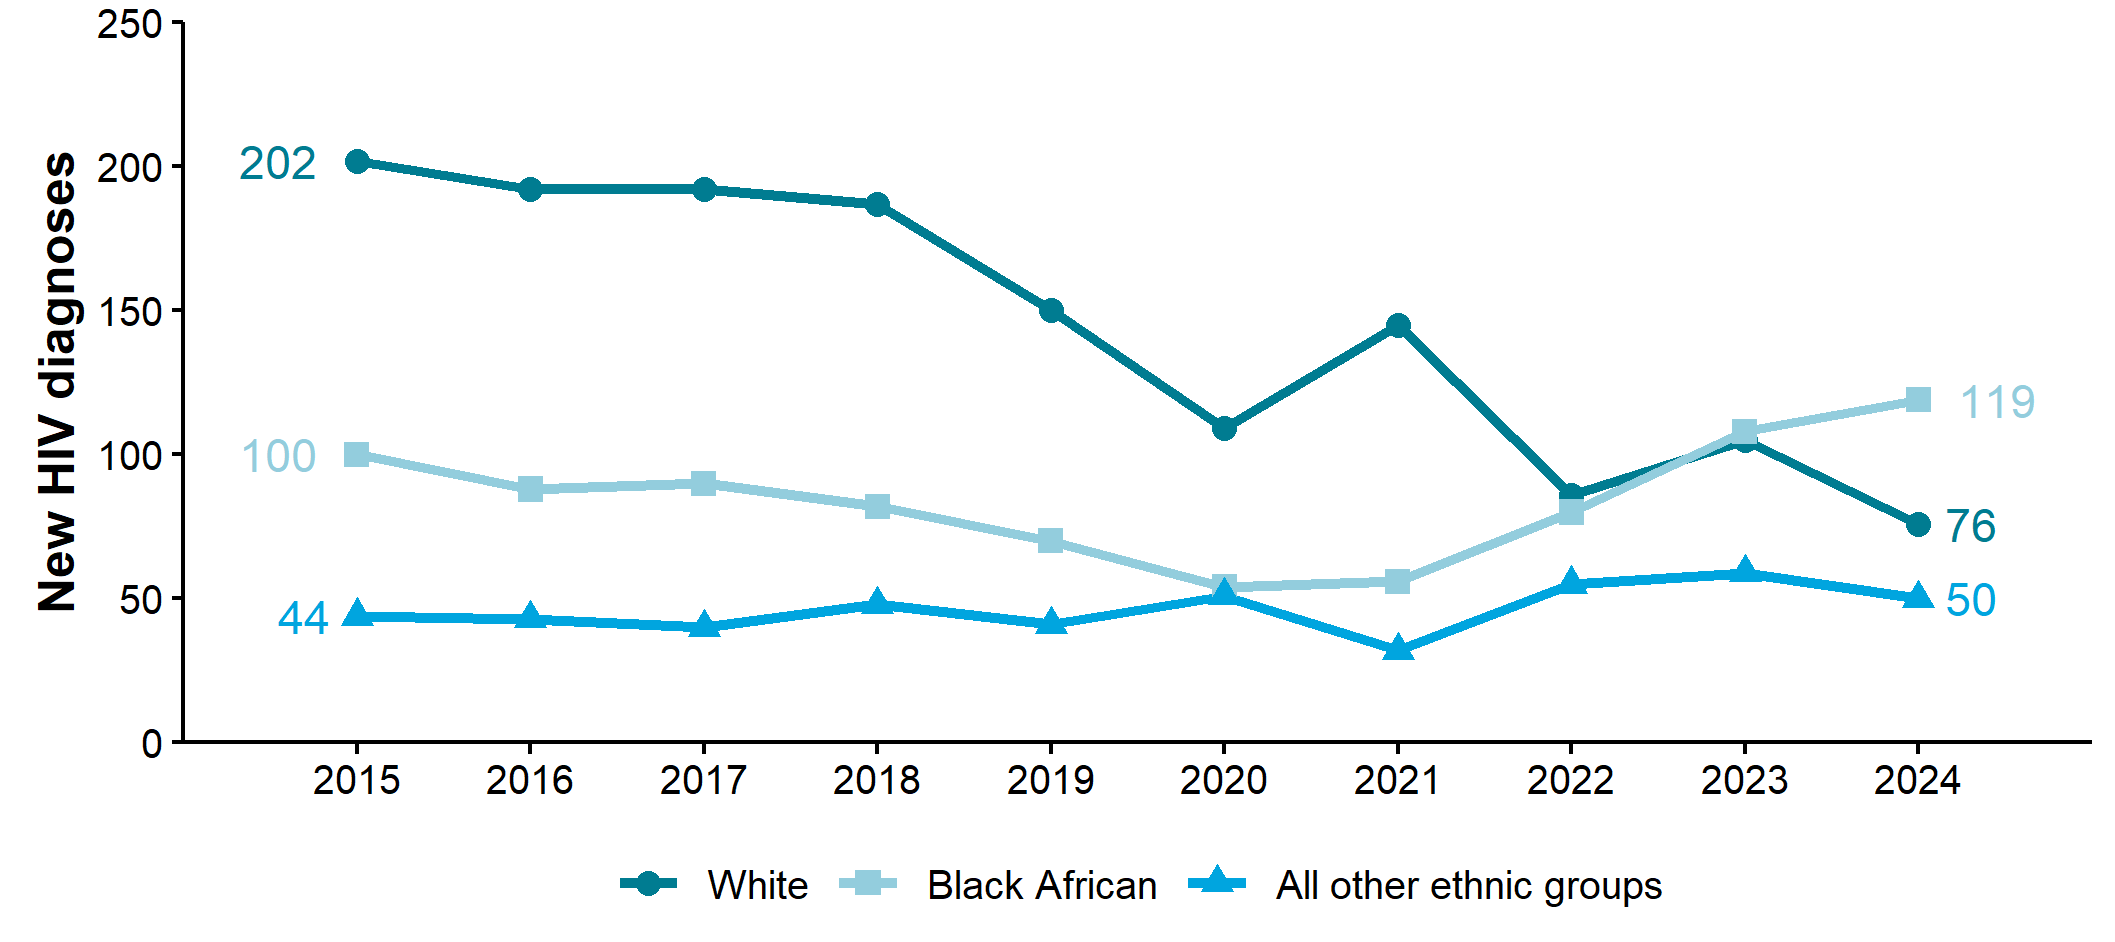
Figure 12. Number of new HIV diagnoses by ethnic group (adjusted for missing ethnic group information), East of England residents, 2015 to 2024 [note 1]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 12 is a line chart showing the number of new HIV diagnoses among East of England residents by ethnic group from 2015 to 2024. White ethnic group is shown in teal, Black African in light blue, and all other ethnic groups a blue line.
There has been an overall decrease in the number of new diagnoses made among those of White ethnicity. In 2024, there were 76 new diagnoses among those of White ethnicity, compared to 202 in 2015.
Between 2015 and 2020, the number of new HIV diagnoses among those of Black African ethnicity decreased. From 2021, the number of new HIV diagnoses among those of Black African ethnicity increased and in 2024 (n=119) there was a higher number of new diagnoses compared to 2015 (n=100). The number of new HIV diagnoses among Black Africans exceeded new diagnoses among White ethnicity in 2024.
For all other ethnicities, the number of new HIV diagnoses fluctuates from year to year, however in 2024 is slightly higher than in 2015.
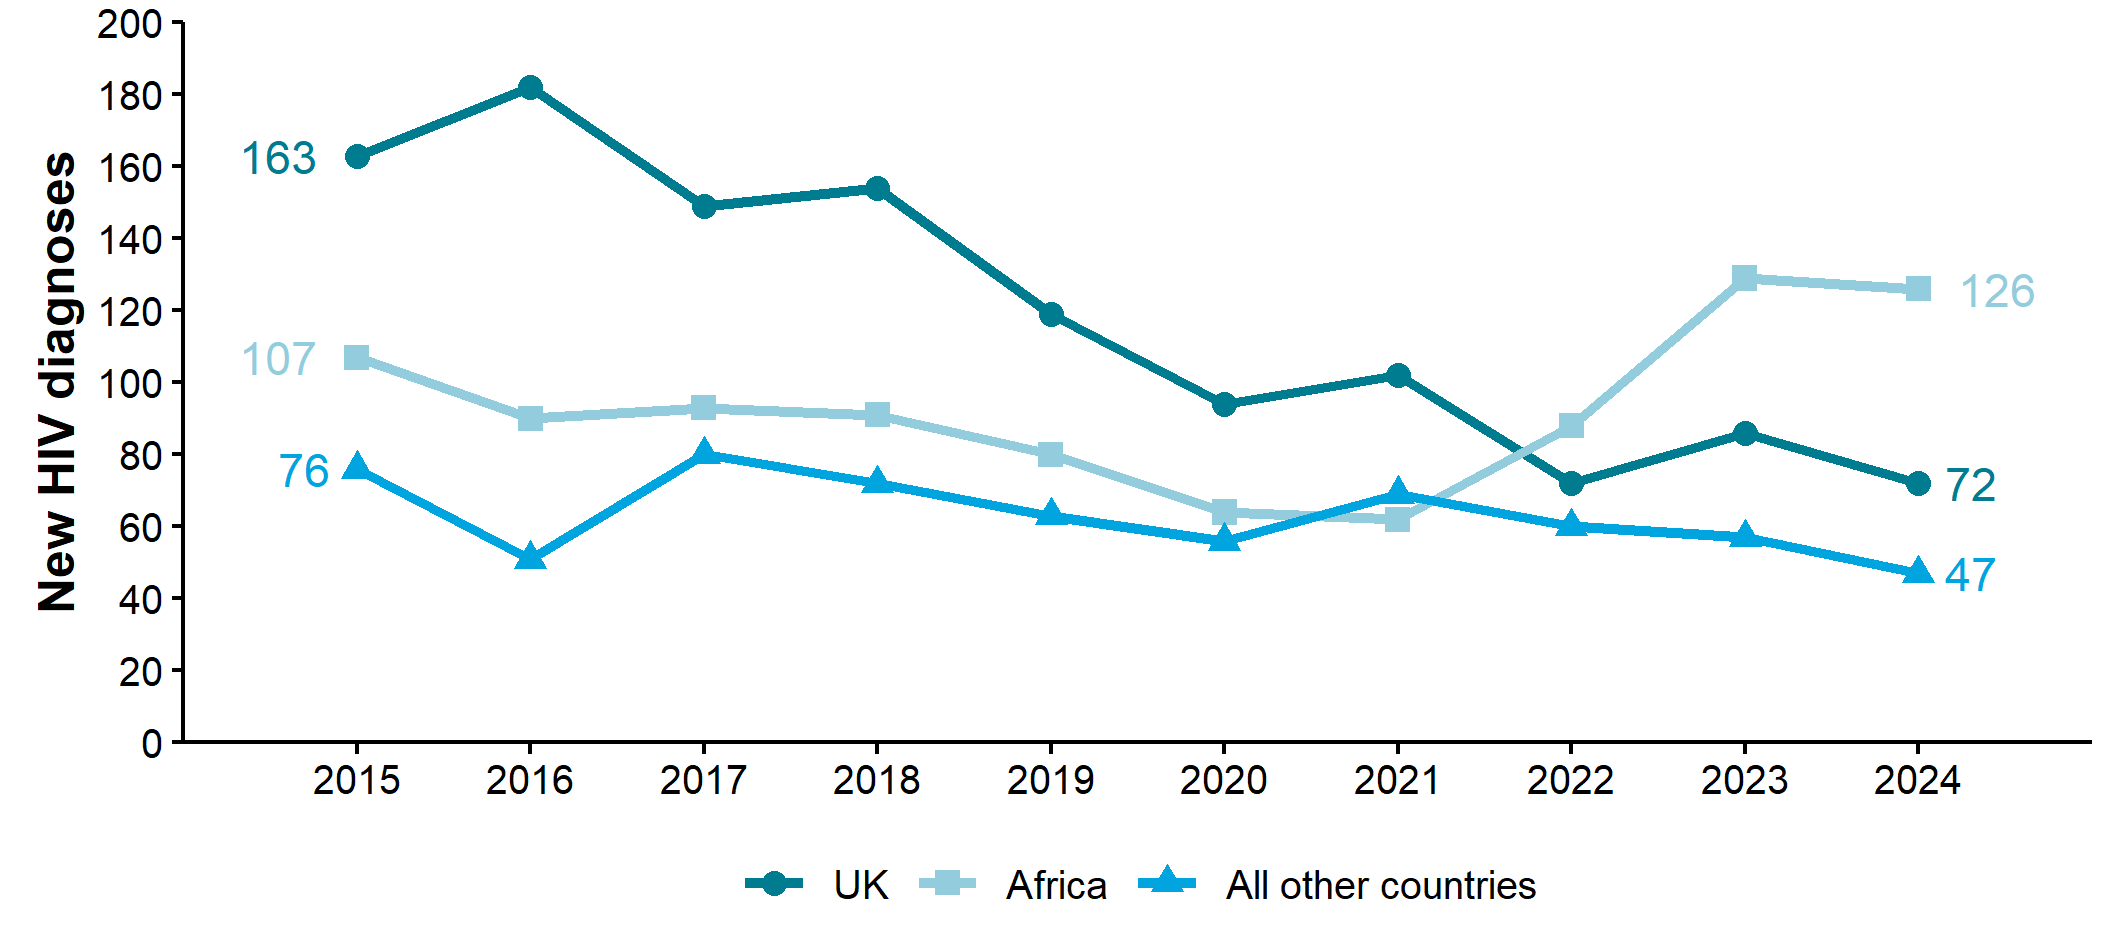
Figure 13. Number of new HIV diagnoses by world region of birth (adjusted for missing world region of birth information), East of England residents, 2015 to 2024 [note 1]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Due to a change in the definition of new HIV diagnoses, this figure no longer includes data for persons previously diagnosed abroad and differs from that included in previous reports.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 13 is a line chart showing the number of new HIV diagnoses first made in England among East of England residents by world region of birth between 2015 and 2024. The data is split by those born in the UK (teal), those born in Africa (light blue) and those born in all other countries (blue). The data has been adjusted to account for missing information.
Between 2015 and 2024, new diagnoses among people born in the UK declined from 163 diagnoses in 2015 to 72 in 2024, although there were some year-to-year fluctuations. A similar downwards trend was seen among individuals born in all other countries, decreasing from 76 in 2015 to 47 in 2024. Among those born in Africa, diagnoses reduced between 2015 and 2021, followed by a substantial increase in 2022 and 2023. In 2024 the number of new diagnoses among those born in Africa (n=126) exceeded the level in 2015 (n=107).
From 2015 to 2021, UK-born individuals accounted for the highest number of new HIV diagnoses, however in 2022 the number of diagnoses among Africa-born individuals exceeded those born in the UK. This pattern continued through to 2024. In 2015 UK-born individuals accounted for 47% of new diagnoses, compared to 31% among those born in Africa and 22% born in all other countries. By 2024 the proportion has shifted to 51% of diagnoses among those born in Africa, 29% among UK-born and 19% among those born in any other country.
Table 1. Number of new HIV diagnoses by ethnic group and whether born abroad, East of England residents, 2020 to 2024 [note 1]
| Ethnic group | UK-born | Born abroad | Unknown country of birth |
|---|---|---|---|
| White | 281 | 122 | 48 |
| Black African | 14 | 319 | 30 |
| Black Caribbean | 5 | 11 | 2 |
| Other | 32 | 137 | 27 |
| Unknown | 11 | 30 | 116 |
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD).
Table 1 shows that the relationship between ethnic group and whether a person newly diagnosed with HIV was born abroad. Data is for the 5-year period 2020 to 2024. Those with a prior diagnosis abroad are excluded. To make it clear that there are differences in completeness of ascertainment of country of birth for different ethnic groups, numbers in this table are not adjusted for missing information.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Table 1 shows the number of new HIV diagnoses among East of England residents by ethnic group and whether born in the UK or abroad for the 5-year period between 2020 and 2024.
The table shows that for those of White ethnicity, most cases were among those who were UK-born (n=281), compared to those born abroad (n=122). Among those of Black African ethnicity, a higher number were born abroad (n=319) than in the UK (n=14). During the 5-year time period there were low numbers of individuals of Black Caribbean ethnicity diagnosed with HIV, although a higher number were born abroad (n=11) compared to in the UK (n=5). A higher number of those in Other ethnic groups were born abroad (n=137) than born in the UK (n=32).
The table also shows the large number of records with an unknown country of birth and unknown ethnic groups. Whilst unknowns are present among all categories in the table, a large number of records (n=116) had both an unknown ethnic group and country of birth, accounting for nearly 10% of new diagnoses between 2020 and 2024.
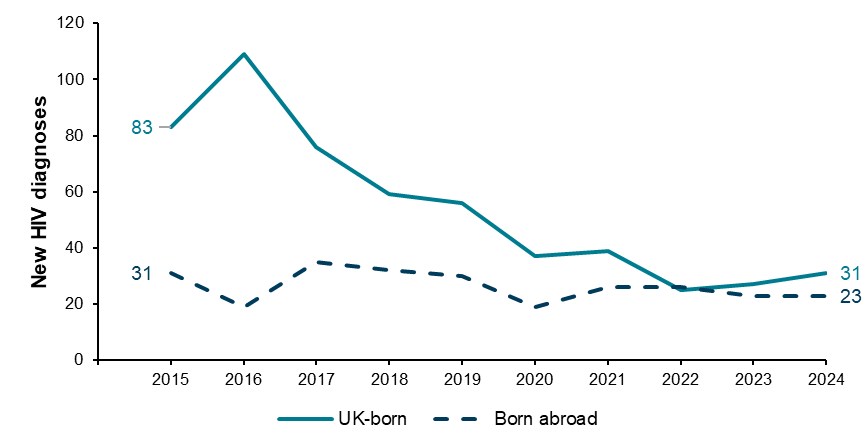
Figure 14. New HIV diagnoses with a probable route of exposure through sex between gay and bisexual men by whether born abroad, East of England residents, 2015 to 2024 [note 1]
Source: UKHSA, HANDD.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. Those with a prior diagnosis abroad are excluded.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 14 is a line chart showing the number of new diagnoses between 2015 and 2024 among those with a probable exposure route of sex between gay and bisexual men, East of England residents, by whether born in the UK or abroad. The chart shows individuals who are UK-born (solid teal), those who are born abroad (dark blue dashed line) and those with an unknown country of birth (blue dashed line).
In 2024 there were 58 new HIV diagnoses with the probable exposure route of sex between gay and bisexual men, 31 were UK-born and 23 were born abroad. Overall, there has been a declining trend in the number of new HIV diagnoses among this probable exposure route who were born in the UK, from 83 in 2015, to 31 in 2024. The number of new HIV diagnoses among those who were born abroad has fluctuated between 2015 and 2024 but has overall reduced from 31 new diagnoses in 2015 to 23 in 2024. The number with an unknown country of birth is low.
Between 2015 and 2024 the highest number of new HIV diagnoses with the probable exposure route of sex gay and bisexual men has consistently been among those who were UK-born, with the exception of 2022 where there was a similar number of diagnoses among individuals born in the UK and abroad.
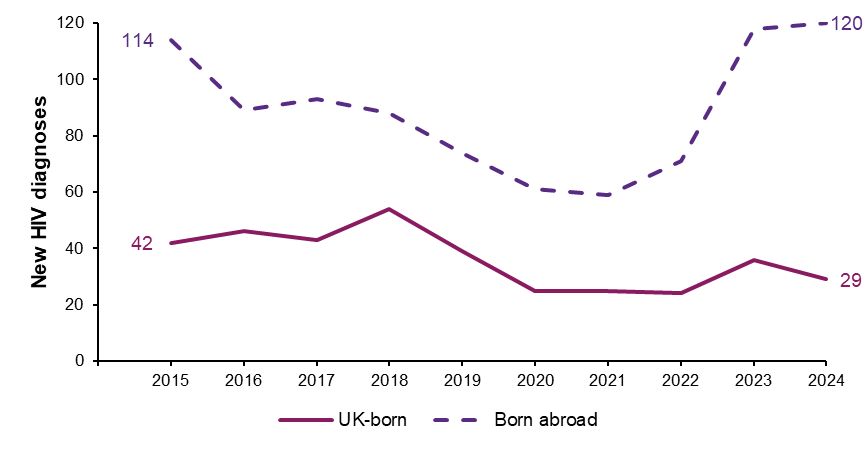
Figure 15. New HIV diagnoses with a probable route of exposure through heterosexual sex by whether born abroad, East of England residents, 2015 to 2024 [note 1]
Source: UKHSA, HANDD.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission. Those with a prior diagnosis abroad are excluded.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 15 is a line chart showing the number of new diagnoses between 2015 and 2024 among those with a probable exposure route of heterosexual sex East of England residents by whether they were born in the UK or abroad. The chart shows individuals who are UK-born (purple), those who are born abroad (dark purple dashed line) and those with an unknown country of birth (pink dashed line).
In 2024, there were 156 new HIV diagnoses among heterosexuals, 130 were born abroad, 29 were UK-born and 7 had an unknown country of birth. Consistently between 2015 and 2024, the highest number of new HIV diagnoses among heterosexuals were among those born abroad.
Between 2015 and 2021, there was a decreasing trend in the number of new diagnoses among heterosexuals born abroad, before increasing sharply in 2022 and 2023. The number of new diagnoses in 2024 (120) is slightly higher than in 2015 (114). The number of new diagnoses among those who were UK-born showed an increasing trend between 2015 and 2108, before decreasing to 2022. In 2023 diagnoses increased before decreasing in the most recent year. Overall, between 2015 and 2024 the number of new diagnoses decreased from 42 to 29. The number of new diagnoses among individuals with an unknown country of birth is low.
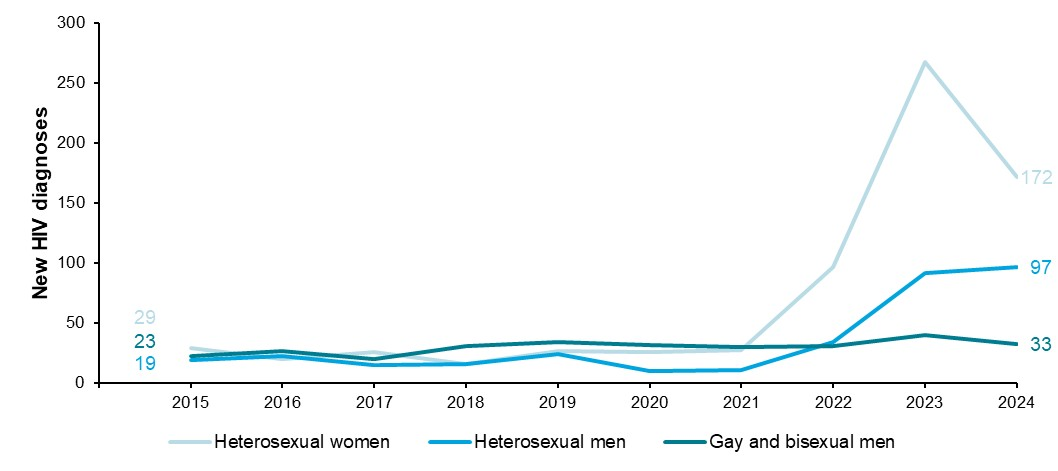
Figure 16. People diagnosed with HIV before continuing care in England by probable route of exposure, East of England residents, 2015 to 2024 [note 1]
Source: UKHSA, HANDD.
The number of new diagnoses will depend on accessibility of testing as well as infection and transmission.
Note 1: numbers may rise as further reports are received and more information is obtained. This is more likely to affect more recent years, particularly 2024.
Figure 16 is a line chart showing the number of HIV diagnoses in individuals who were diagnosed with HIV before continuing care in England by probable route of exposure for East of England residents between 2015 and 2024. Heterosexual women are shown in light blue, heterosexual men in blue and gay and bisexual men in teal. Diagnoses among other groups are small and not shown in the chart.
Between 2015 and 2021, for all probable routes of exposure the numbers of individuals diagnosed with HIV before continuing care in England remained low and relatively stable.
Among heterosexual women, the number of diagnoses increased substantially in 2022 and 2023, before reducing in 2024. In 2024, there were 172 new diagnoses, compared to 29 in 2015.
Diagnoses among heterosexual men also increased between 2022 and 2024, although not as steeply as among heterosexual women. In 2024 there were 97 new diagnoses, compared to 19 in 2015.
Diagnoses among gay and bisexual men remained relatively stable through the time period, showing a slight increase from 23 new diagnoses in 2015, to 33 in 2024.
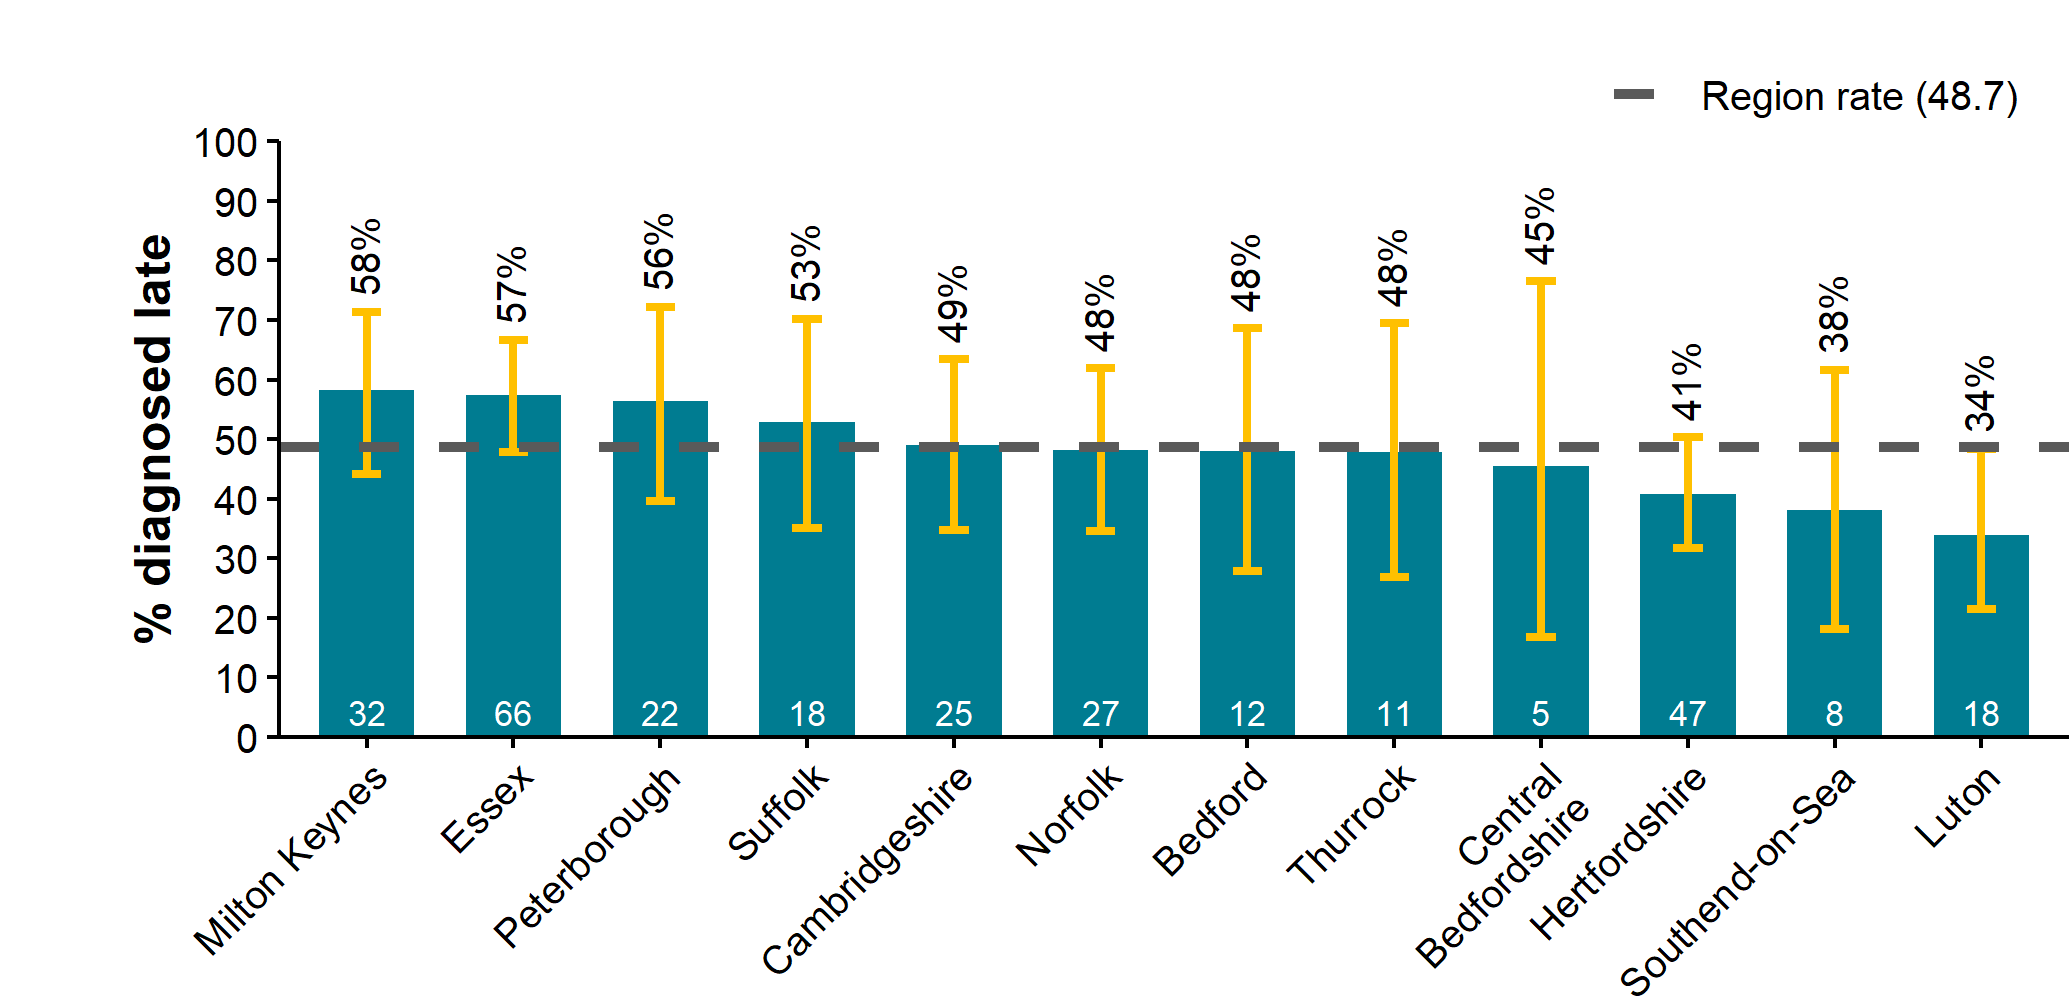
Figure 17. Percentage of new HIV diagnoses, by local authority of residence, that were diagnosed late, East of England, aged 15 years and over, 2022 to 2024 [note 2]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
The number contained within each bar indicates the number of cases.
Note 2: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3. The underlying population will impact on the proportion diagnosed late, for example, gay and bisexual men are less likely to be diagnosed late.
Figure 17 is a bar chart of the percentage of new HIV diagnoses that were diagnosed late among East of England residents aged 15 and over by local authority of residence for the 3-year period 2022 to 2024. The number of late diagnoses is shown within the teal bars, the percentage of late diagnoses are shown above the bars, confidence intervals are shown in yellow, and the regional total of 48.7% is shown by the grey dashed line.
The highest proportion of late diagnoses were made in Milton Keynes (58%), followed by Essex (57%), Peterborough (56%), and Suffolk (53%). These local authorities all have a higher proportion of late diagnoses compared to the regional average (48.7%).
Cambridgeshire (49%), Norfolk (48%), Bedford (48%) and Thurrock (48%) all have a similar proportion of late diagnoses compared to East of England overall (48.7%).
Luton (34%) has the lowest proportion of late diagnoses, followed by Southend-on-Sea (38%), Hertfordshire (41%), Central Bedfordshire (45%). These local authorities all have a lower percentage of late diagnoses than the East of England overall (48.7%). Confidence intervals for all local authorities overlap with the regional average.
Very high proportions of late diagnoses are seen at district level, with 100% of new diagnoses made late in West Suffolk, 86% in North Norfolk, 80% in East Suffolk and 73% in Fenland.
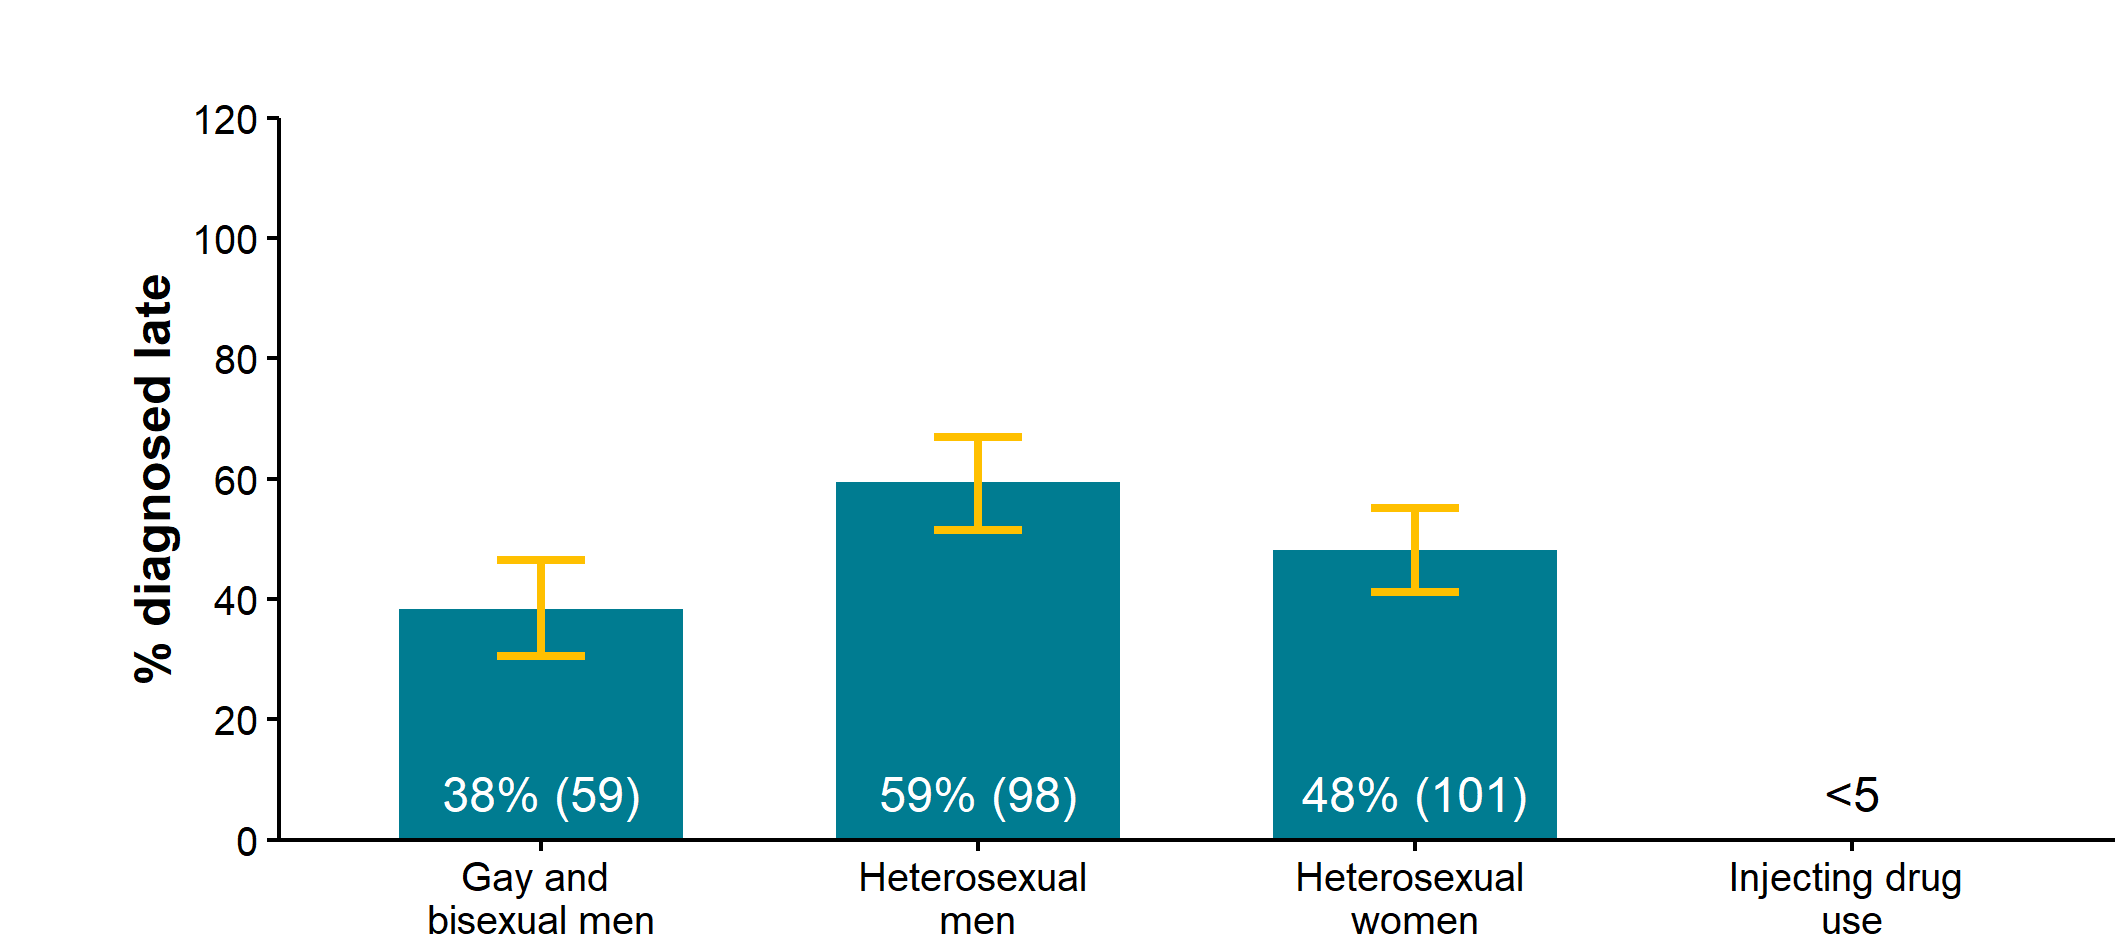
Figure 18. Percentage and number of new HIV diagnoses by probable route of exposure that were diagnosed late, East of England residents, aged 15 years and over, 2022 to 2024 [note 3]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 3: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3. Proportions are only shown for the gay and bisexual men, heterosexual men, heterosexual women, and injecting drug use exposure groups and are withheld for any of these categories if they contain fewer than 5 late diagnoses.
Figure 18 is a bar chart showing the percentage and number of new HIV diagnoses in East of England residents aged 15 and over who were diagnosed late by probable route of infection for the 3-year period 2021 to 2024. Confidence intervals are shown in yellow.
Heterosexual men had the highest percentage of late diagnoses (59%, n=98), followed by heterosexual women (48%, n=101) and gay and bisexual men (38%, n=59).
The probable exposure route of injecting drug use had numbers too small to analyse.
The confidence intervals for heterosexual males do not cross with those for gay and bisexual men, indicating a significant difference.
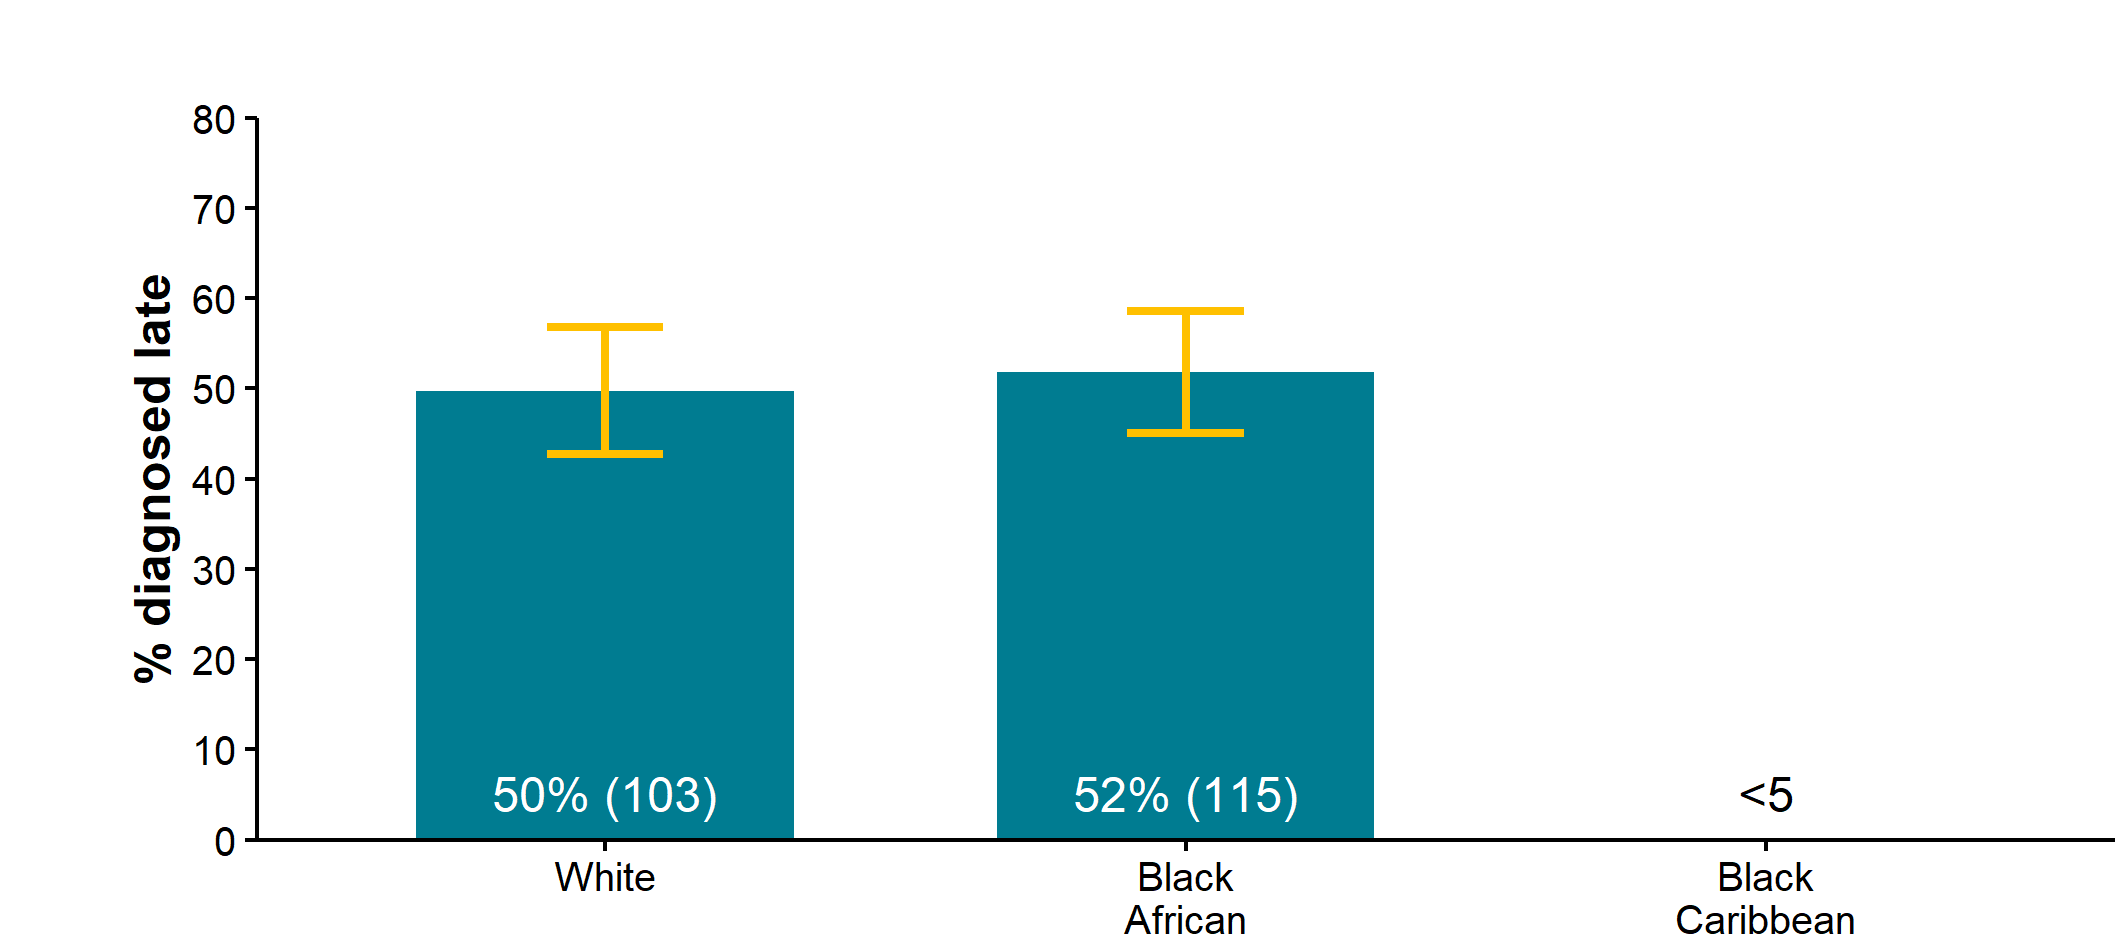
Figure 19. Percentage and number of new HIV diagnoses by ethnic group that were diagnosed late, East of England residents, aged 15 years and over, 2022 to 2024 [note 4]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 4: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3. Proportions are only shown for the White, Black African and Black Caribbean ethnic groups and are withheld for any of these ethnic group categories if they contain fewer than 5 late diagnoses. IPB means Indian/Pakistani/Bangladeshi.
Figure 19 is a bar chart showing the percentage and number of new HIV diagnoses in the East of England among residents aged 15 and over that were diagnosed late by ethnic group for the 3-year period 2022 to 2024. Confidence intervals are shown in yellow.
The proportion of late diagnoses was slightly higher among individuals of Black African ethnicity (52%), compared to those of White ethnicity (50%). However, the confidence intervals for both ethnic groups cross, indicating no statistical difference.
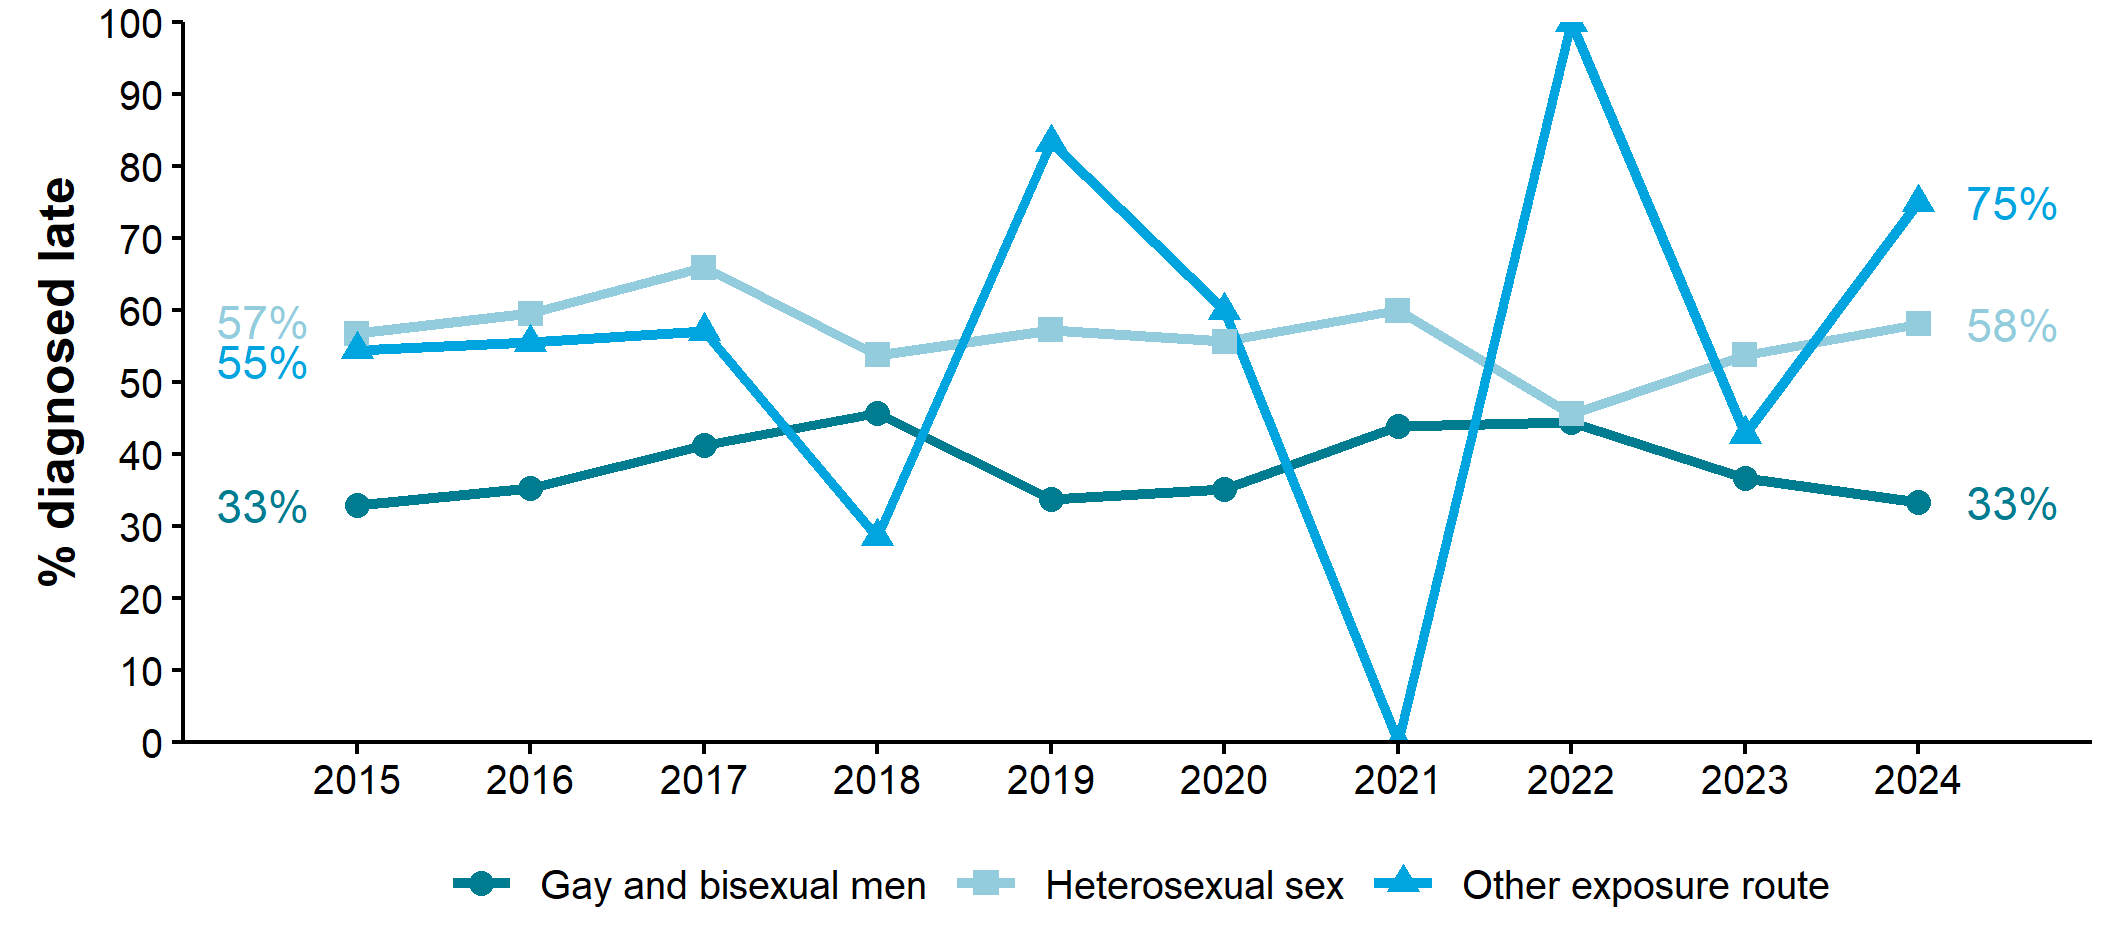
Figure 20. Percentage of new HIV diagnoses that were diagnosed late by probable route of exposure and year of first UK HIV diagnosis, East of England residents, aged 15 years and over, 2015 to 2024 [note 5]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 20 is a line chart showing the percentage of new HIV diagnoses among East of England residents aged 15 and over that were diagnosed late, by probable route of infection and year of diagnosis. Gay and bisexual men are shown in teal, heterosexual sex is shown in light blue and other infection routes are shown in blue.
Due to low numbers, the percentage of late diagnoses among those with other infection routes fluctuates widely from year to year. In 2024 75% of diagnoses with other infection routes were diagnosed late.
The percentage of late diagnoses among those with the probable infection route of heterosexual sex has small fluctuations from year to year. For the past 2 time periods, the proportion of late diagnoses increased, to 58% of new diagnoses in 2024.
The percentage of late diagnoses among gay and bisexual men, increased between 2015 and 2018, before decreasing in 2019. In 2021, the proportion increased again before declining to 33% in 2024.
Late diagnoses are consistently higher among the probable exposure route of heterosexual sex, compared to gay and bisexual men.
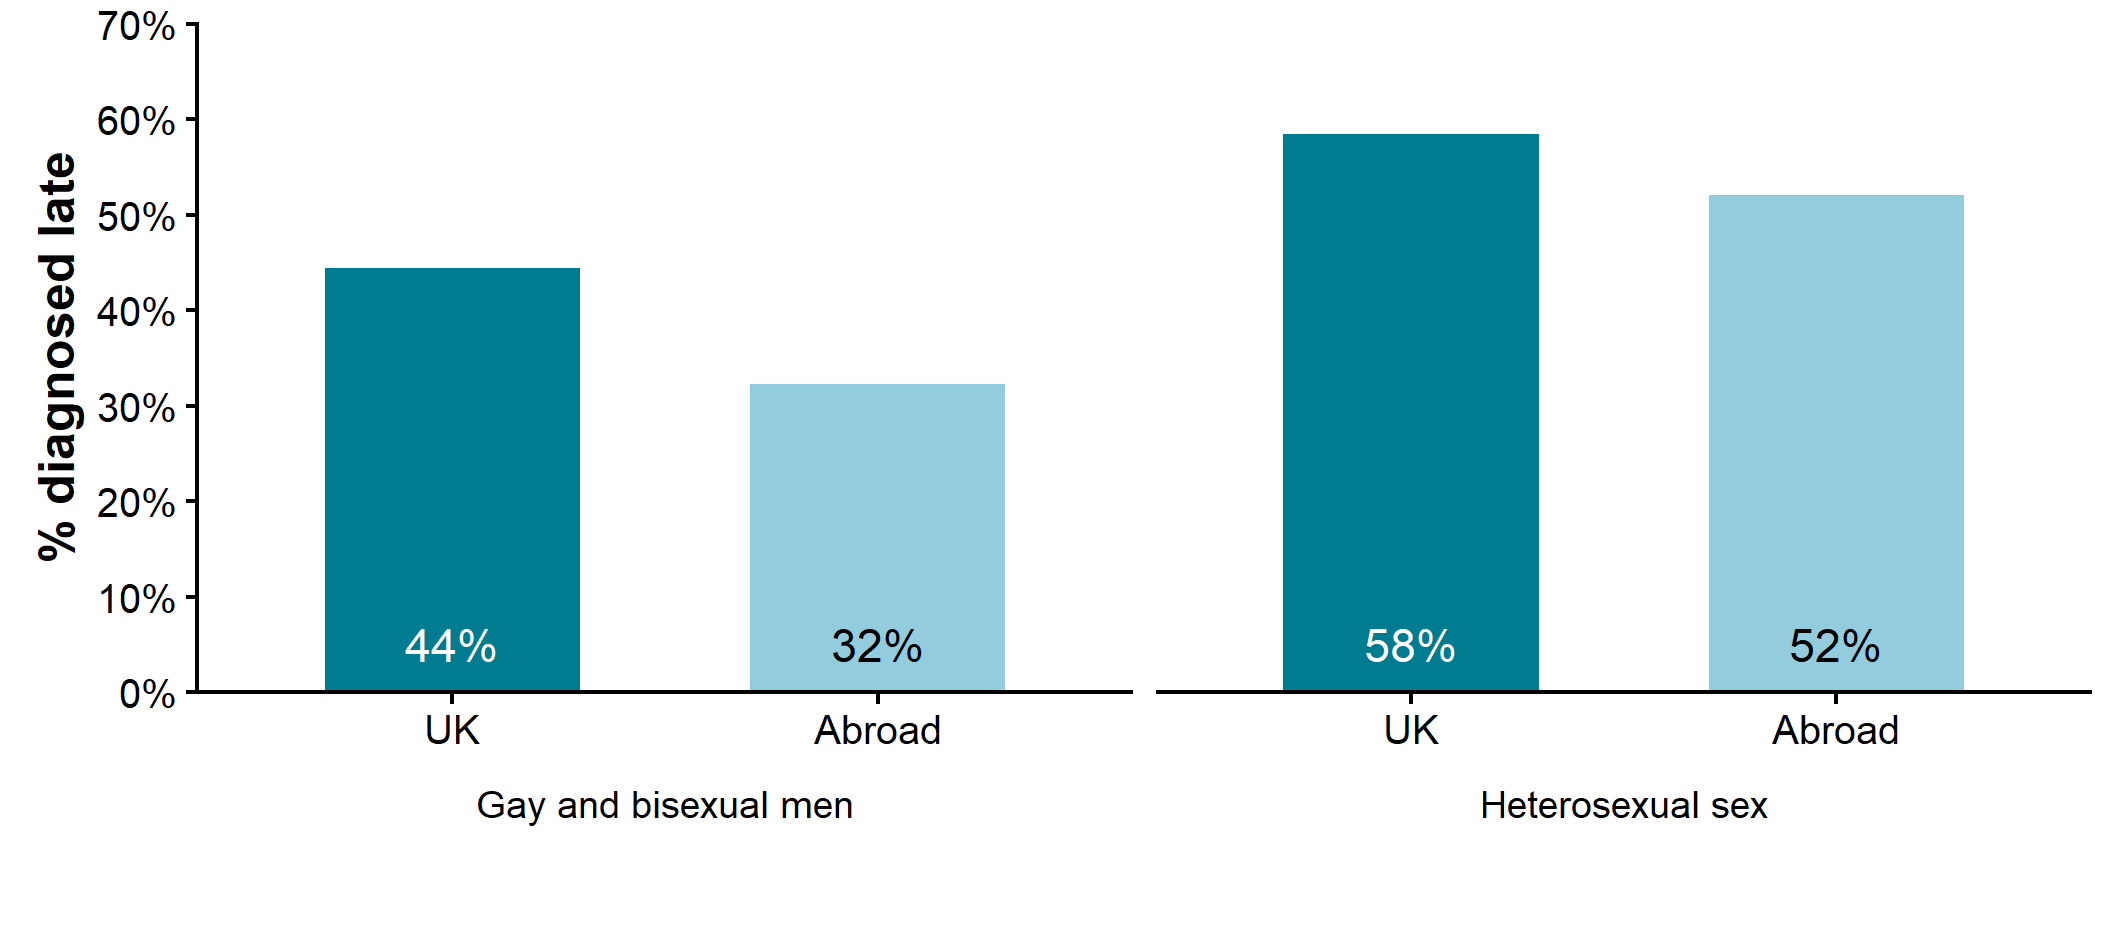
Figure 21. Percentage of new HIV diagnoses that were diagnosed late in gay and bisexual men and heterosexuals by whether born abroad, East of England residents, aged 15 years and over, 2022 to 2024 [note 5]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 21 is a bar chart showing the percentage of new HIV diagnoses in East of England residents aged 15 and over that were diagnosed late in gay and bisexual men and heterosexuals by whether they were born in the UK (teal) or abroad (light blue). Data is shown combined for the 3-year period 2022 to 2024.
For both gay and bisexual men, and heterosexuals, the proportion of late diagnoses was higher among those who were born in the UK compared to born abroad. Although, the difference was greater among gay and bisexual men.
There was a higher proportion of gay and bisexual men diagnosed late were UK-born (44%), compared to born abroad (32%). Similarly, a higher proportion of heterosexuals born in the UK (58%) were diagnosed late compared to those born abroad (52%).
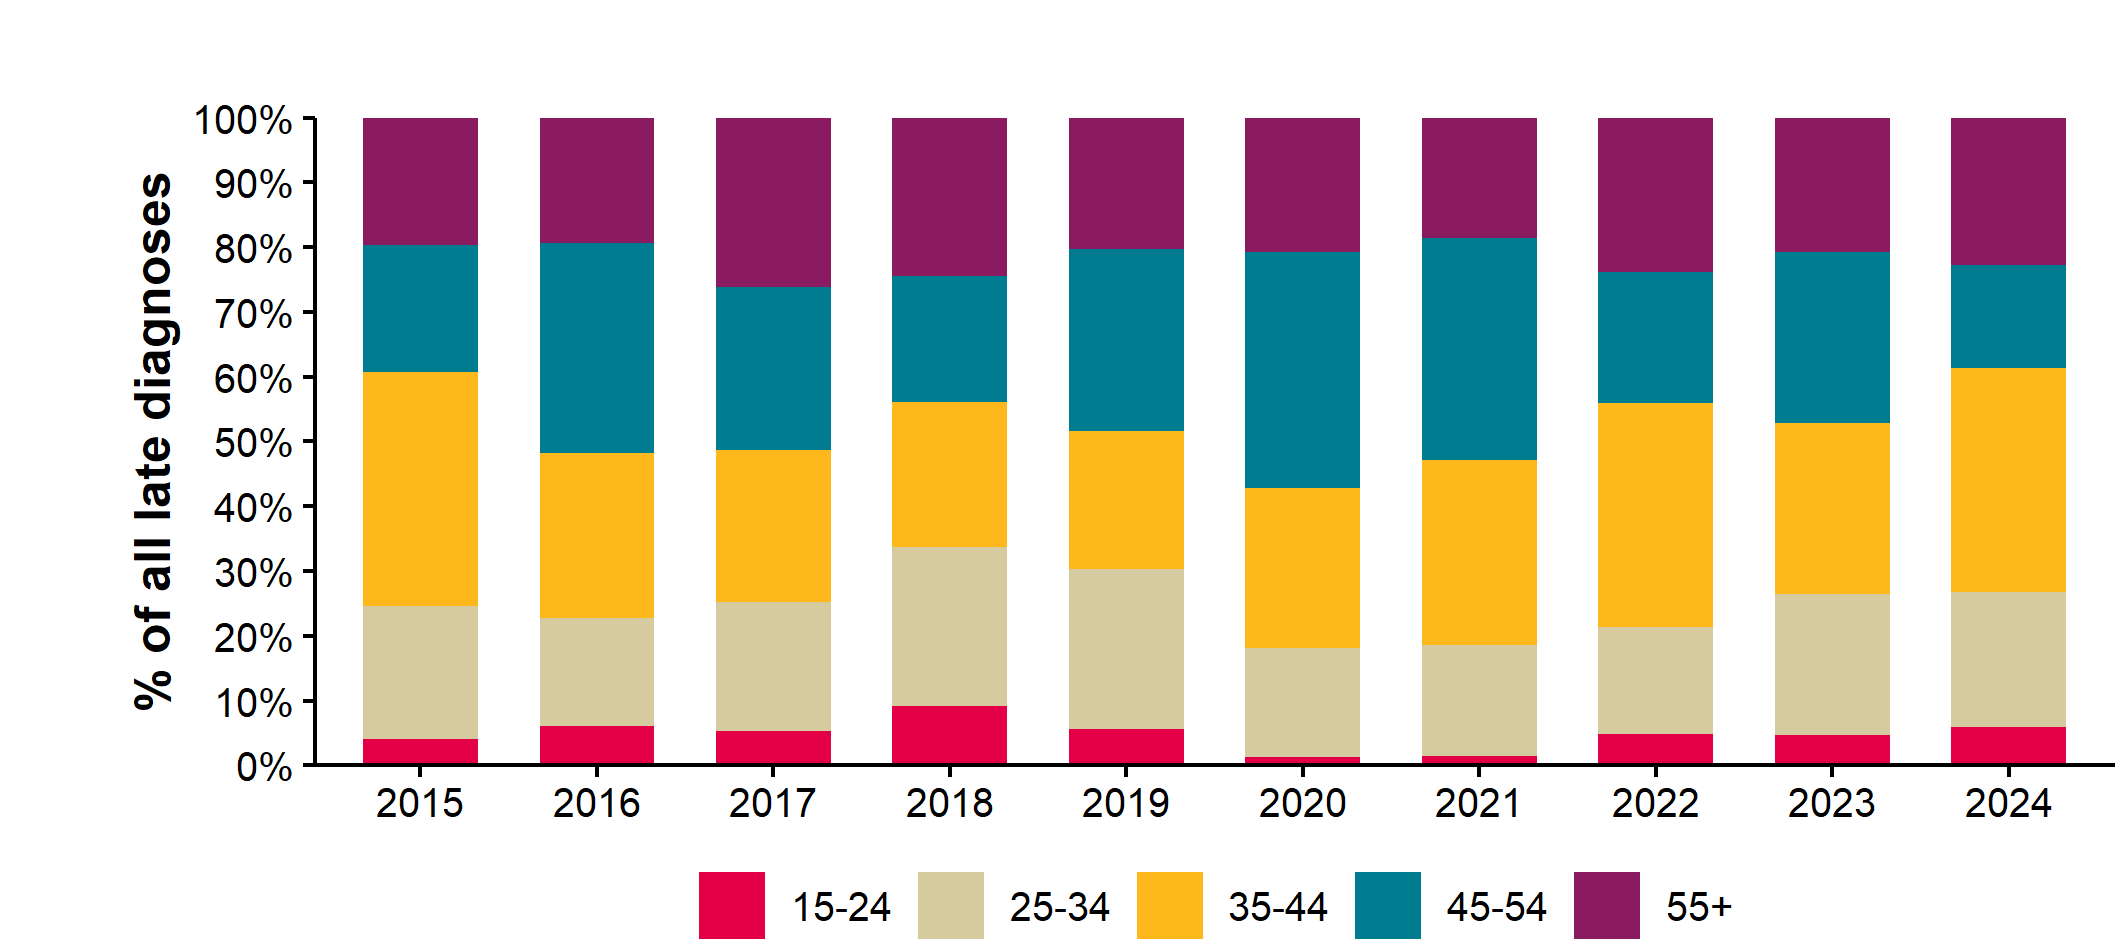
Figure 22. Age distribution of new HIV diagnoses that were diagnosed late by year of first HIV diagnosis, East of England residents, aged 15 years and over, 2015 to 2024 [note 5]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 22 is a bar chart showing the age distribution of new HIV diagnoses among East of England residents aged 15 and over that were diagnosed late by age group and year of HIV diagnosis. The age groups displayed on the chart are 15 to 24 (pink), 25 to 34 (beige), 35 to 44 (yellow), 45 to 54 (teal) and 55 and over (purple).
Between 2015 and 2024, those aged 15 to 24 consistently accounted for the lowest proportion of late diagnoses.
Of the new diagnoses that were diagnosed late in 2024, the largest proportion were among those aged 35 to 44, followed by those aged 25 to 34, 55 and over, 45 to 54 and finally 15 to 24.
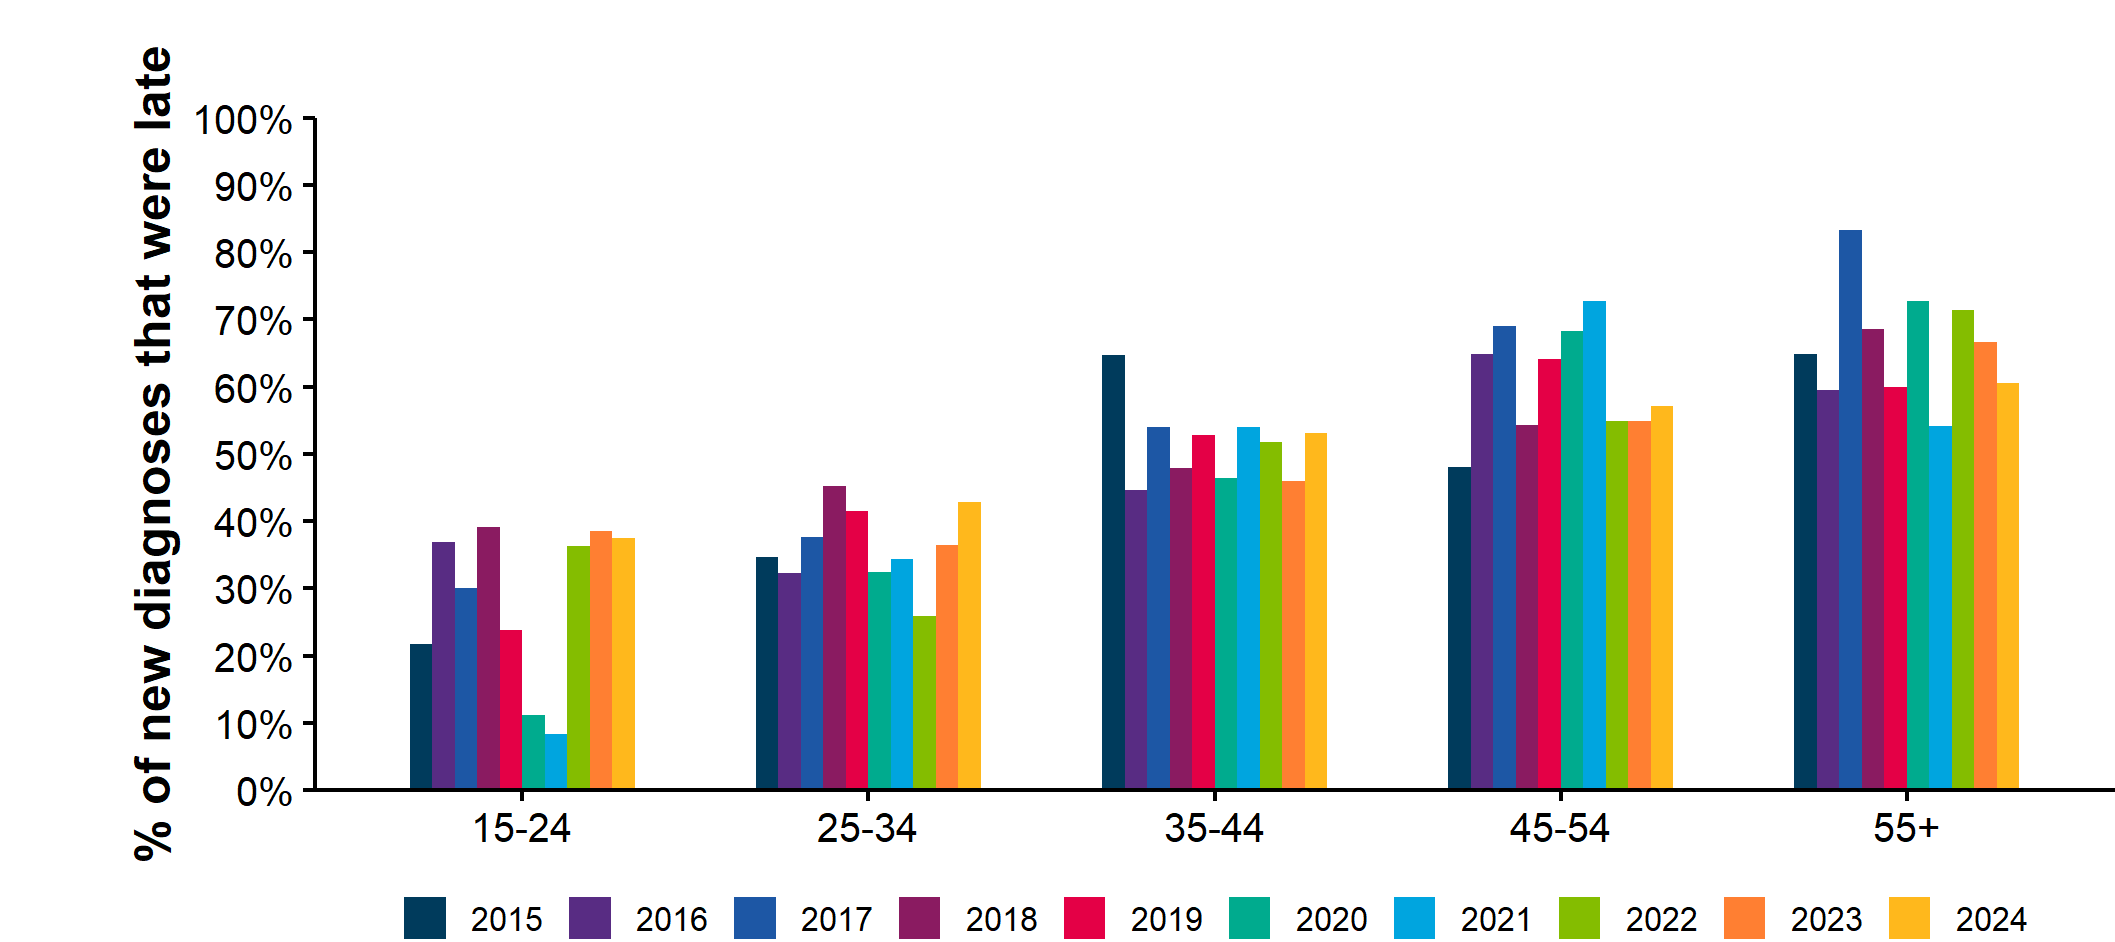
Figure 23. Percentage of all new diagnoses that were late by age by year of first HIV diagnosis, East of England residents, aged 15 years and over, 2015 to 2024 [note 5]
Source: UKHSA, HIV and AIDS New Diagnoses and Deaths (HANDD), HIV and AIDS Reporting System (HARS).
Note 5: only includes new diagnoses in those aged 15 years or older with no prior diagnosis abroad and for which a CD4 count was reported within 91 days of diagnosis; late diagnosis defined as CD4 count <350 cells/mm3.
Figure 23 is a bar chart showing the percentage of new diagnoses that were diagnosed late among East of England residents aged 15 and over by age group and year of diagnosis.
In general, the proportion of new diagnoses that were diagnosed late is higher in the older age groups, and lower in the younger age groups, showing an increasing trend between each age group.
Among those aged 15 to 25 years old, the proportion of late diagnoses decreased between 2019 and 2021, before increasing substantially in 2022 and remaining high in 2023 and 2024.
The proportion of late diagnoses among those aged 25 to 34 decreased from 2019 to 2022, before increasing in 2023 and 2024.
For those aged 35 to 44, the proportion of late diagnoses fluctuates from year to year. In 2024 the proportion of late diagnoses increased compared to 2023.
Among those aged 45 to 54, between 2015 and 2021 the proportion of late diagnoses showed an increasing trend before reducing in 2022 and remaining similar to 2024.
The proportion of late diagnoses among those aged 55 and over fluctuated widely between 2015 and 2022. From 2022 the proportion of late diagnoses decreased to 2024.
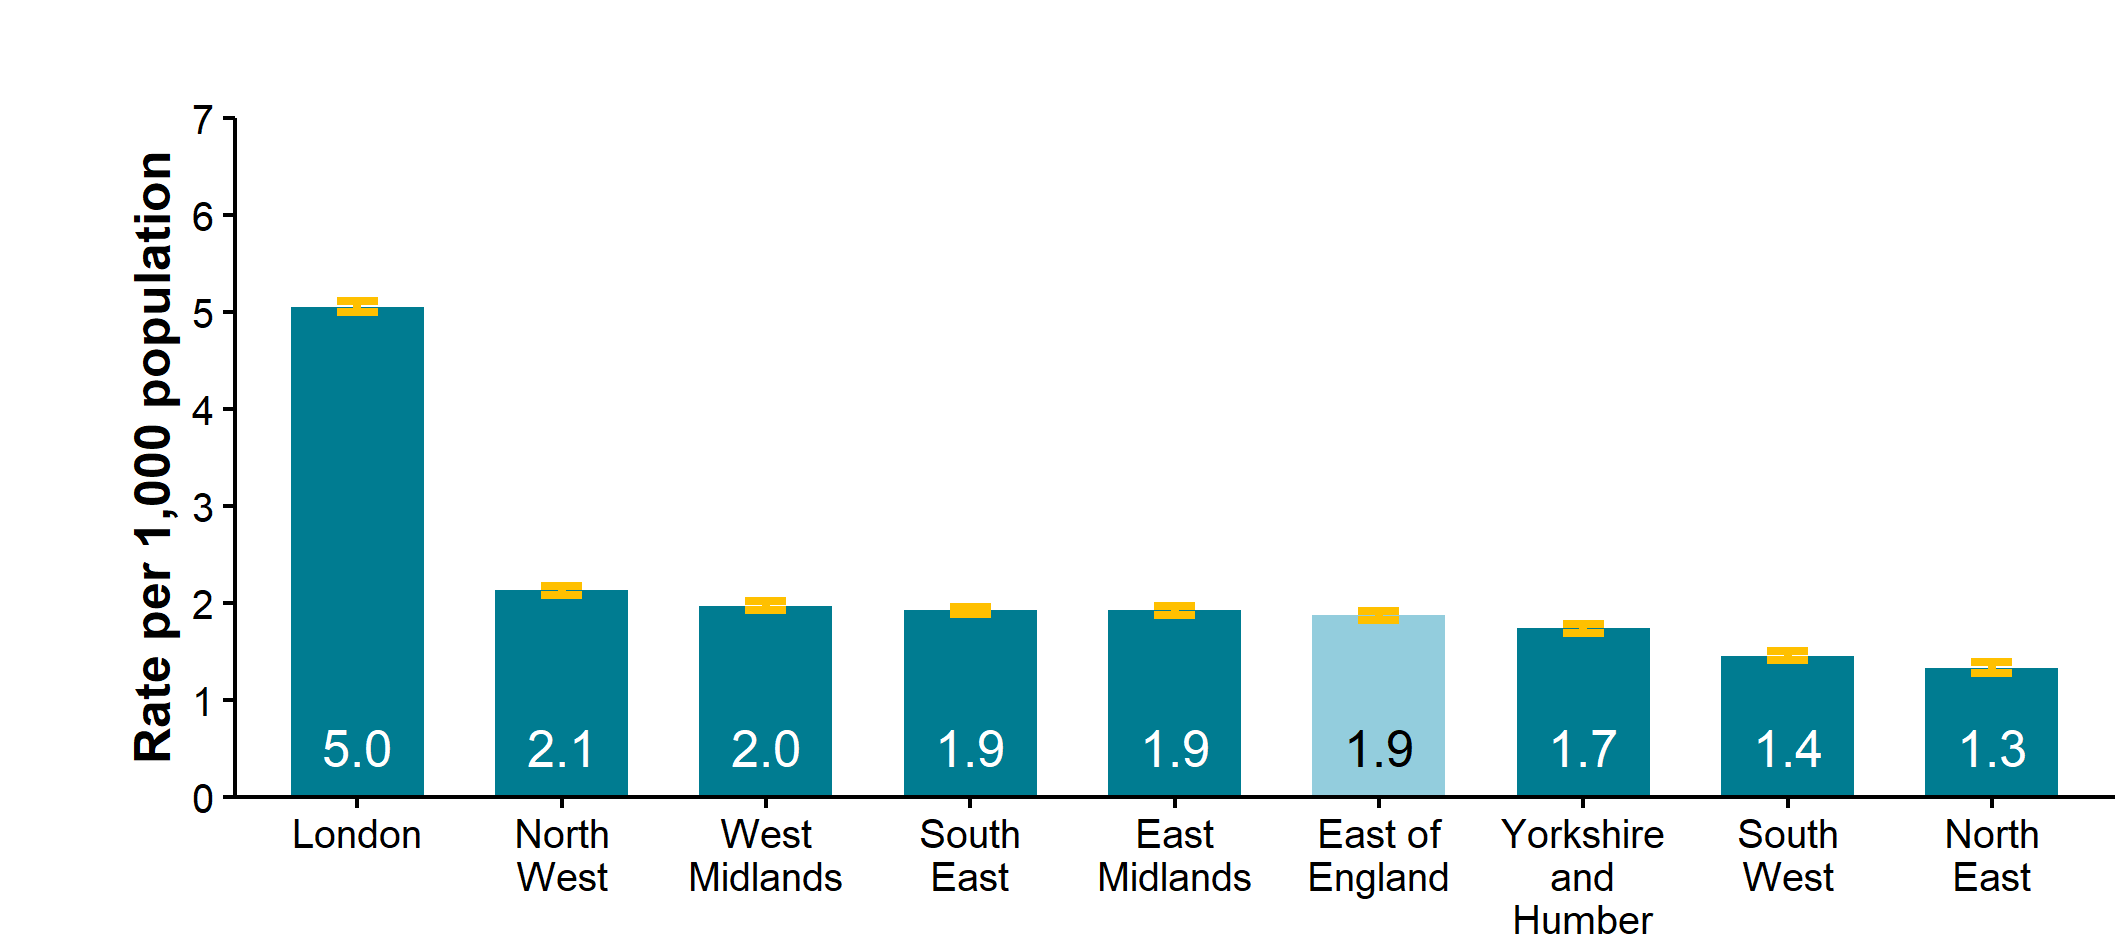
Figure 24. Diagnosed HIV prevalence per 1,000 residents aged 15 to 59 years by UKHSA region, 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 24 is a bar chart of diagnosed HIV prevalence per 1,000 residents aged 15 and 59, by UKHSA region in 2024.
The East of England has the fourth lowest HIV diagnosed prevalence of all UKHSA regions, with 1.9 per 1,000 residents. London is the region with the highest HIV diagnosed prevalence with 5.0 per 1,000, and the North East is the region with the lowest with 1.3 per 1,000.
Figure 25. Number of residents living with diagnosed HIV (all ages) and accessing care, the East of England, 2015 to 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 25 is a line chart showing the number of East of England residents living with diagnosed HIV and accessing care in the East of England between 2014 and 2023.
Between 2015 and 2024, there has been an increasing trend in the number of residents living with diagnosed HIV and accessing care, from 6,419 in 2015 to 9,194 in 2024.
Figure 26. Number of residents living with diagnosed HIV and accessing care by probable route of exposure (adjusted for missing route information), the East of England, 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 26 is a bar chart showing the number of East of England residents in 2024 living with diagnosed HIV and accessing care by probable route of infection. The data in this chart has been adjusted to account for missing data.
The highest number of individuals living with diagnosed HIV and accessing care were among those likely exposed by heterosexual sex (5,957), followed by sex between gay and bisexual men (2,818), mother to child transmission (224), injecting drug use (123), and blood/healthcare worker (72).
Figure 27. Percentage of all residents with diagnosed HIV who are accessing care, by age group contribution, the East of England, 2015 and 2024
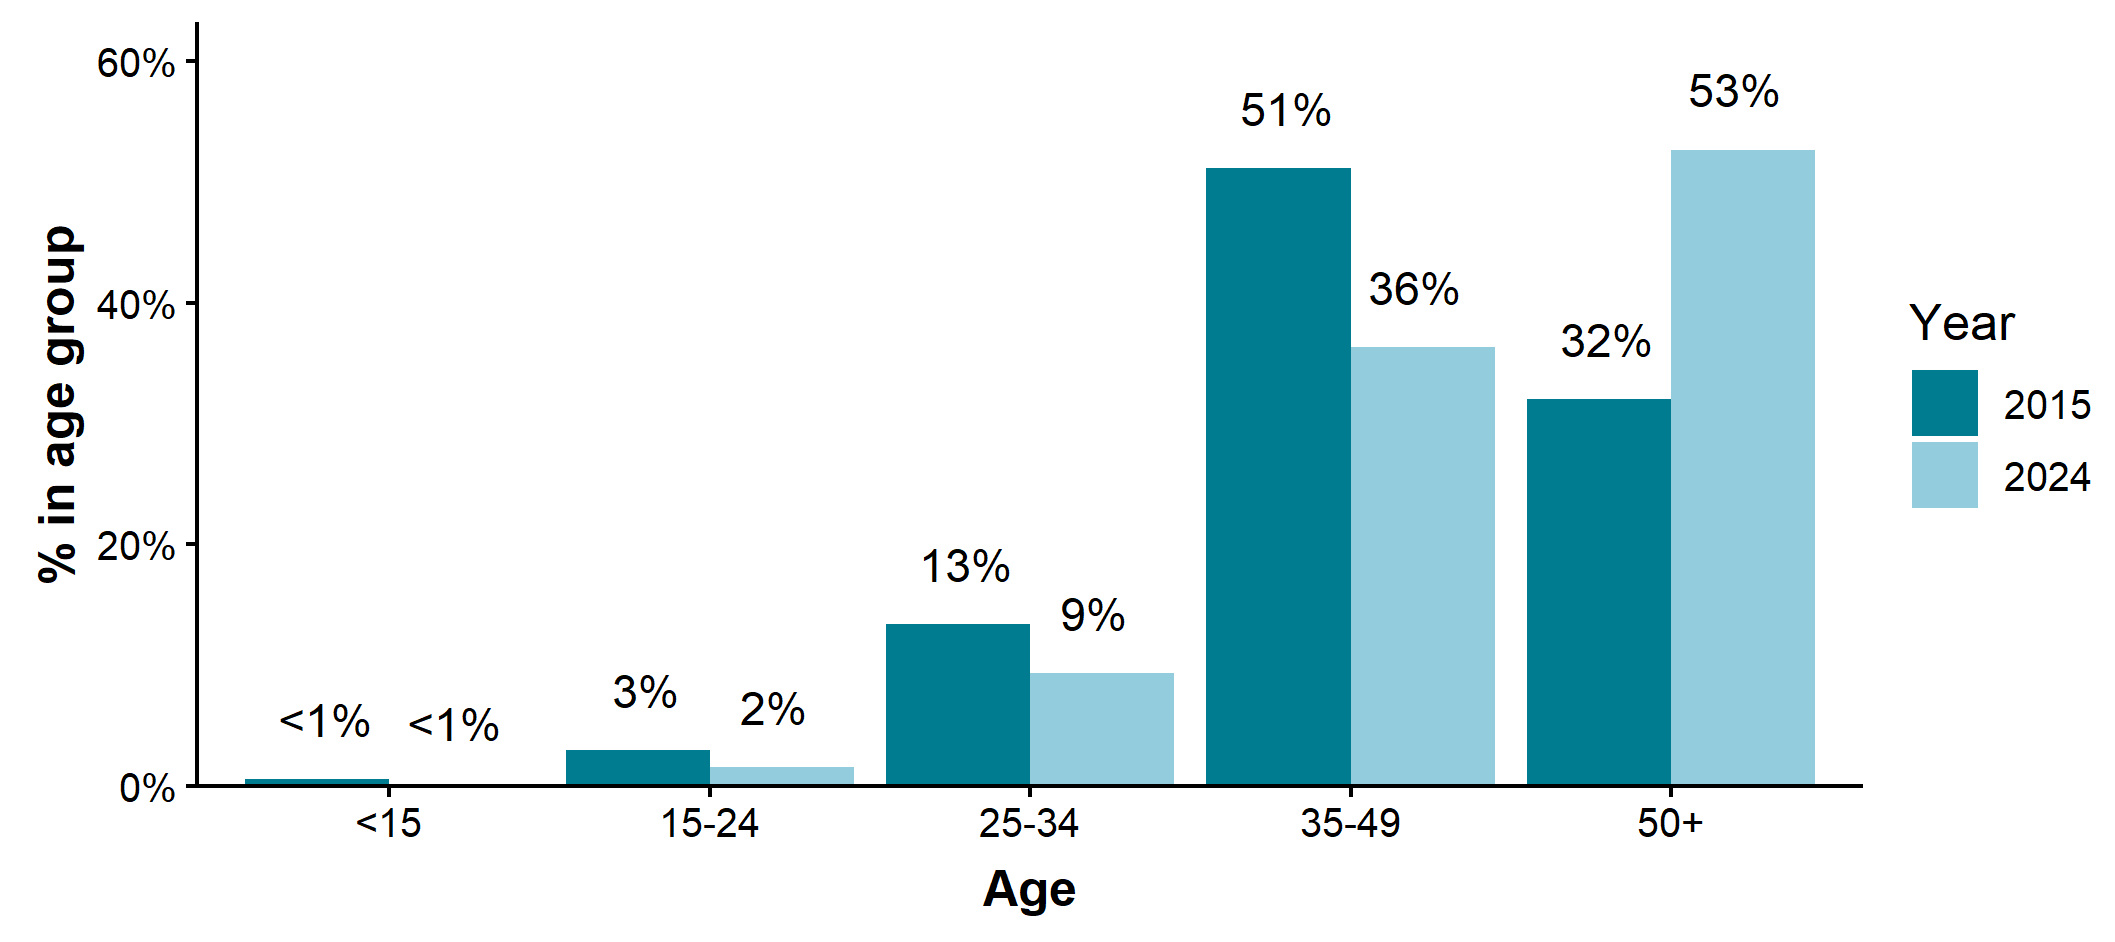
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 27 is a bar chart showing the percentage of East of England residents diagnosed with HIV and accessing care by age group in 2015 (teal) and 2024 (light blue).
In 2015, the highest proportion of individuals living with diagnosed HIV and accessing care was among those aged 35-49, accounting for over half (51%) of residents living with HIV and accessing care. Followed by those aged 50 and over (32%), 25 to 34 (13%), 15 to 24 (3%) and aged under 15 (less than 1%).
Between 2015 and 2024, the age demographic of residents living with diagnosed HIV and accessing care has shifted, with a higher proportion being aged 50 and over than in 2015. Over half of those living with diagnosed HIV and accessing care in 2024 were aged 50 and over (53%), followed by those aged 35 to 59 (36%), 25 to 34 (9%), 15 to 24 (2%) and aged under 15 (less than 1%). This pattern reflects an ageing population living with HIV.
Figure 28. Diagnosed HIV prevalence per 1,000 residents by ethnic group (all ages), the East of England, 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 28 is a bar chart showing the diagnosed HIV prevalence per 1,000 residents of all ages, by ethnic group among East of England residents in 2024. Confidence intervals are shown in yellow.
The Black African ethnic group had the highest diagnosed HIV prevalence rate of 28.2 per 1,000. The confidence intervals for the Black African ethnic group are higher and do not cross with those for any other ethnic group, suggesting a significantly higher rate. Other Black/Unspecified had the second highest diagnosed prevalence rate of 8.2 per 1,000, significantly lower than the Black African ethnic group and higher than all other ethnic groups. Followed by Other/Mixed (1.7 per 1,000), White (0.7 per 1,000) and Asian (0.7 per 1,000).
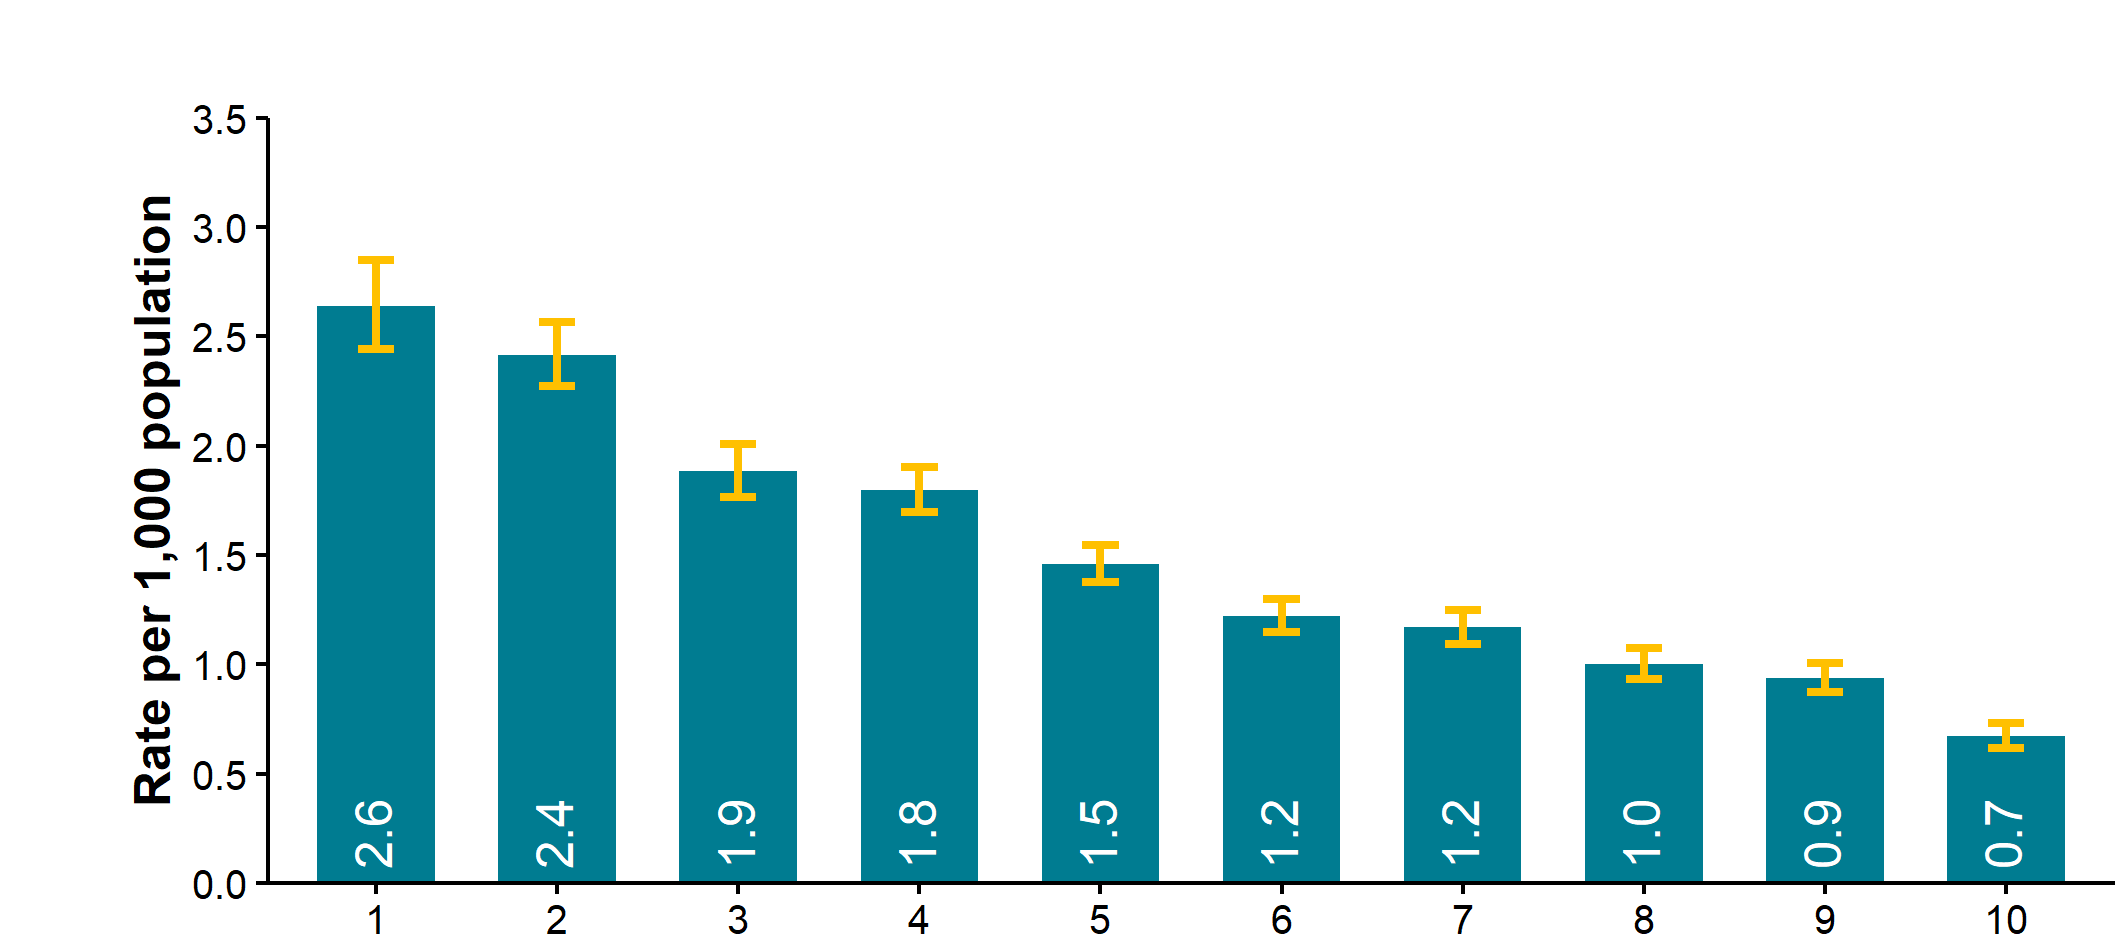
Figure 29. Diagnosed HIV prevalence per 1,000 population by Index of Multiple Deprivation decile, the East of England, 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 29 is a bar chart showing the rate of HIV diagnosis per 1,000 population by Index of Multiple Deprivation decile in the East of England in 2024. Decile 1 is the most deprived 10%, and decile 10 is the least deprived 10%. Confidence intervals are shown in yellow.
The HIV diagnosed prevalence rate increases as the level of deprivation increased. From 0.7 per 1,000 in the least deprived decile (decile 10), to 2.6 per 1,000 in the most deprived decile (decile 1). The confidence intervals for the most and least deprived deciles do not cross, indicating a significant difference.
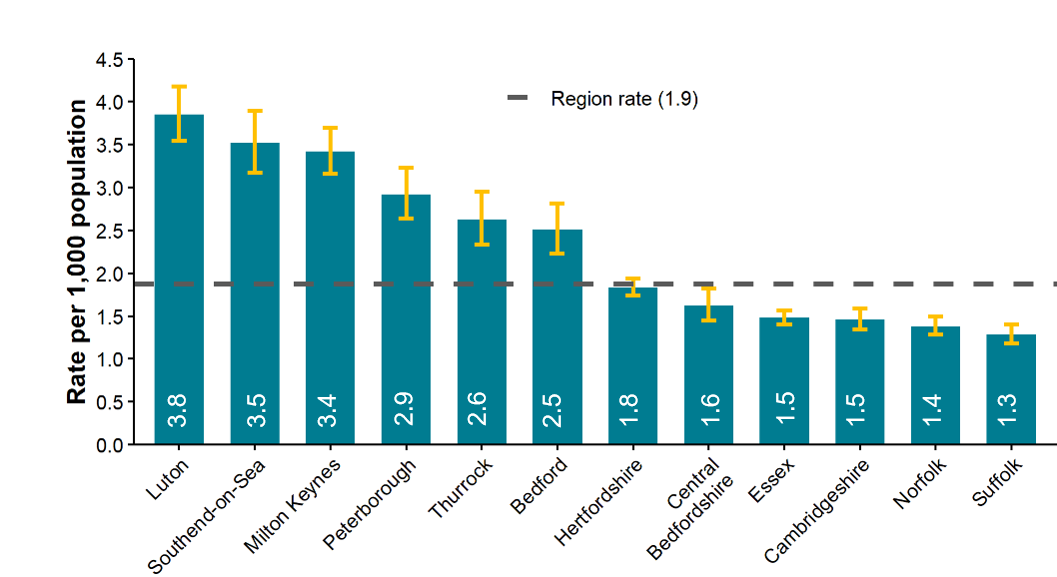
Figure 30. Diagnosed HIV prevalence per 1,000 residents aged 15 to 59 years by local authority, the East of England, 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 30 is a bar chart showing the diagnosed HIV prevalence rate per 1,000 East of England residents aged 15 to 59 years by East of England local authority in 2024. Confidence intervals are shown in yellow, and the regional rate (1.9 per 1,000) is shown as a dashed line.
Luton has the highest HIV diagnosed prevalence rate of 3.8 per 1,000, followed by Southend-on-Sea (3.5), Milton Keynes (3.4), Peterborough (2.9), Thurrock (2.6) and Bedford (2.5). These local authorities all had rates higher than the regional average (1.9) and their confidence intervals do not cross the regional line.
Suffolk has the lowest HIV diagnosed prevalence rate (1.3), followed by Norfolk (1.4), Cambridgeshire (1.5), Essex (1.5) Central Bedfordshire (1.6), and Hertfordshire (1.8). All these local authorities have rates lower than the regional rate (1.9), confidence intervals for all areas apart from Hertfordshire do not cross the regional rate.
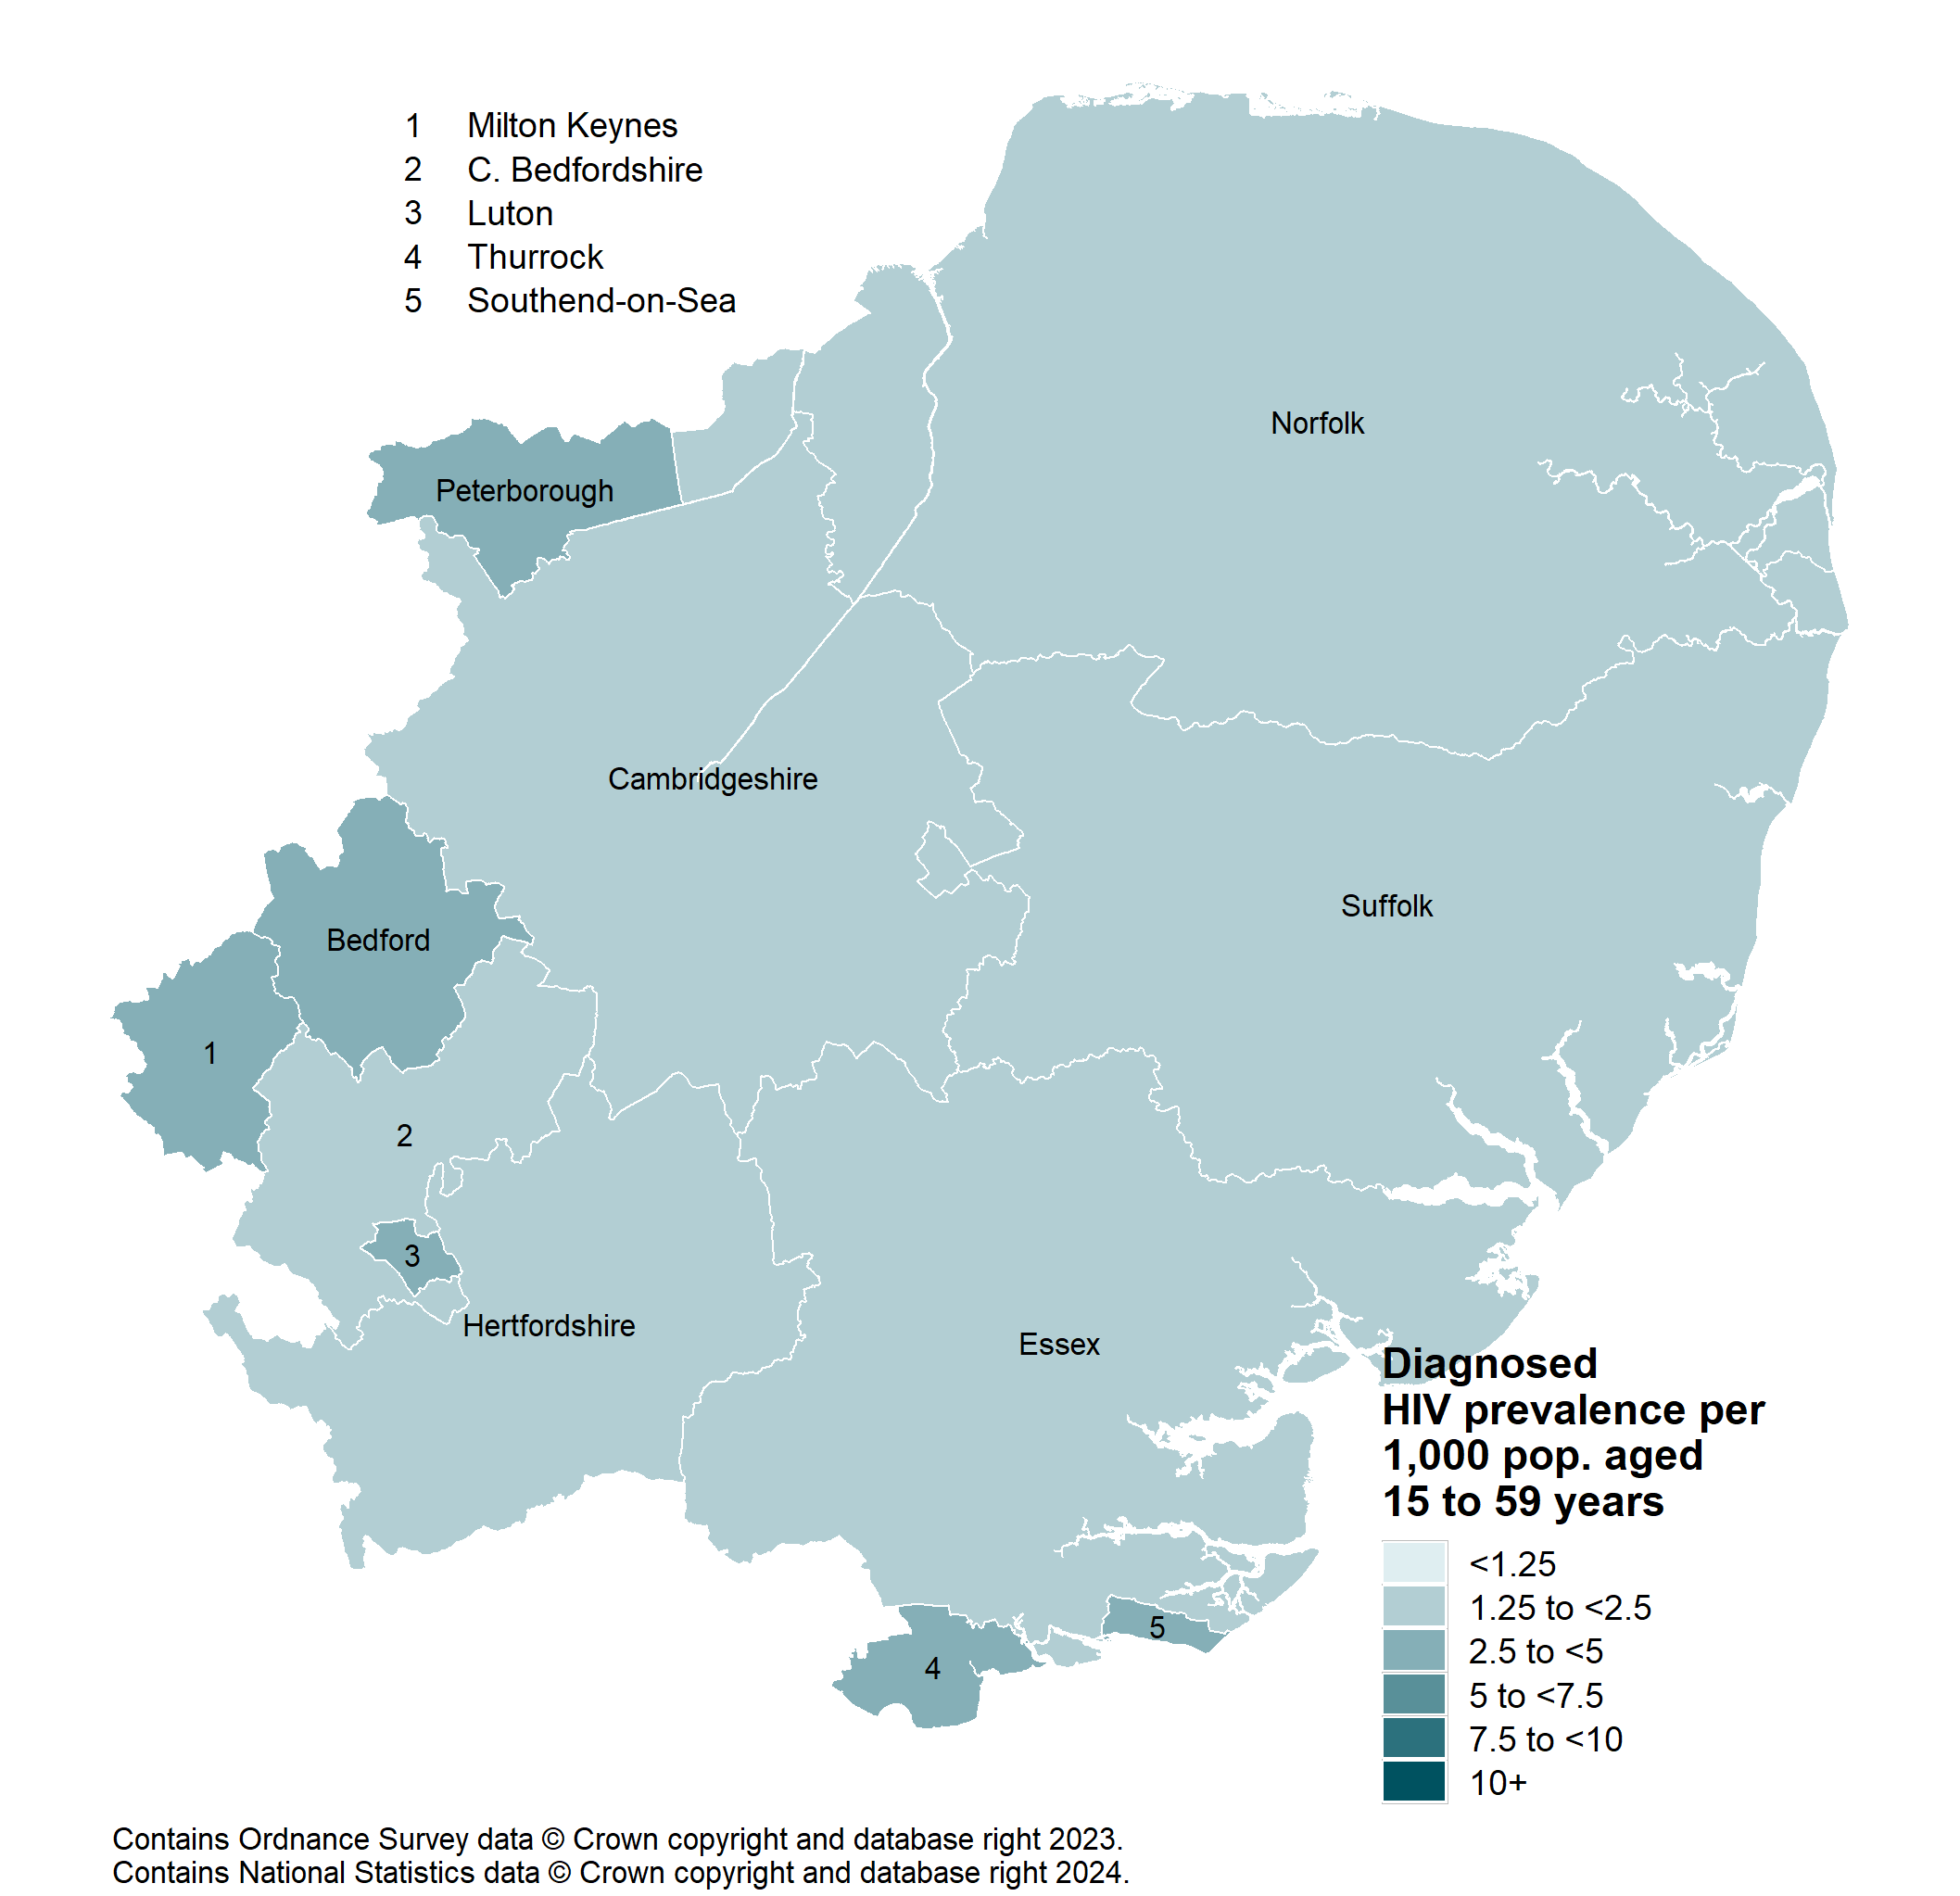
Figure 31. Diagnosed HIV prevalence per 1,000 residents aged 15 to 59 years by local authority, the East of England, 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 31 is a map showing the diagnosed HIV prevalence per 1,000 residents aged 15 to 59 by local authority in England in 2024. Local authorities are colour coded based on diagnosed HIV prevalence rate, a darker blue indicates a higher rate, and a lighter blue indicates a lower rate.
The map shows the distribution of diagnosed HIV prevalence per 1,000 around local authorities in the East of England. None of the local authorities have a diagnosed HIV prevalence rate of greater than 5 per 1,000 (mid to dark blue).
The map shows that the areas of the region with higher diagnosed prevalence rates are Luton, Southend-on-Sea, Milton Keynes, Peterborough, Thurrock and Bedford.
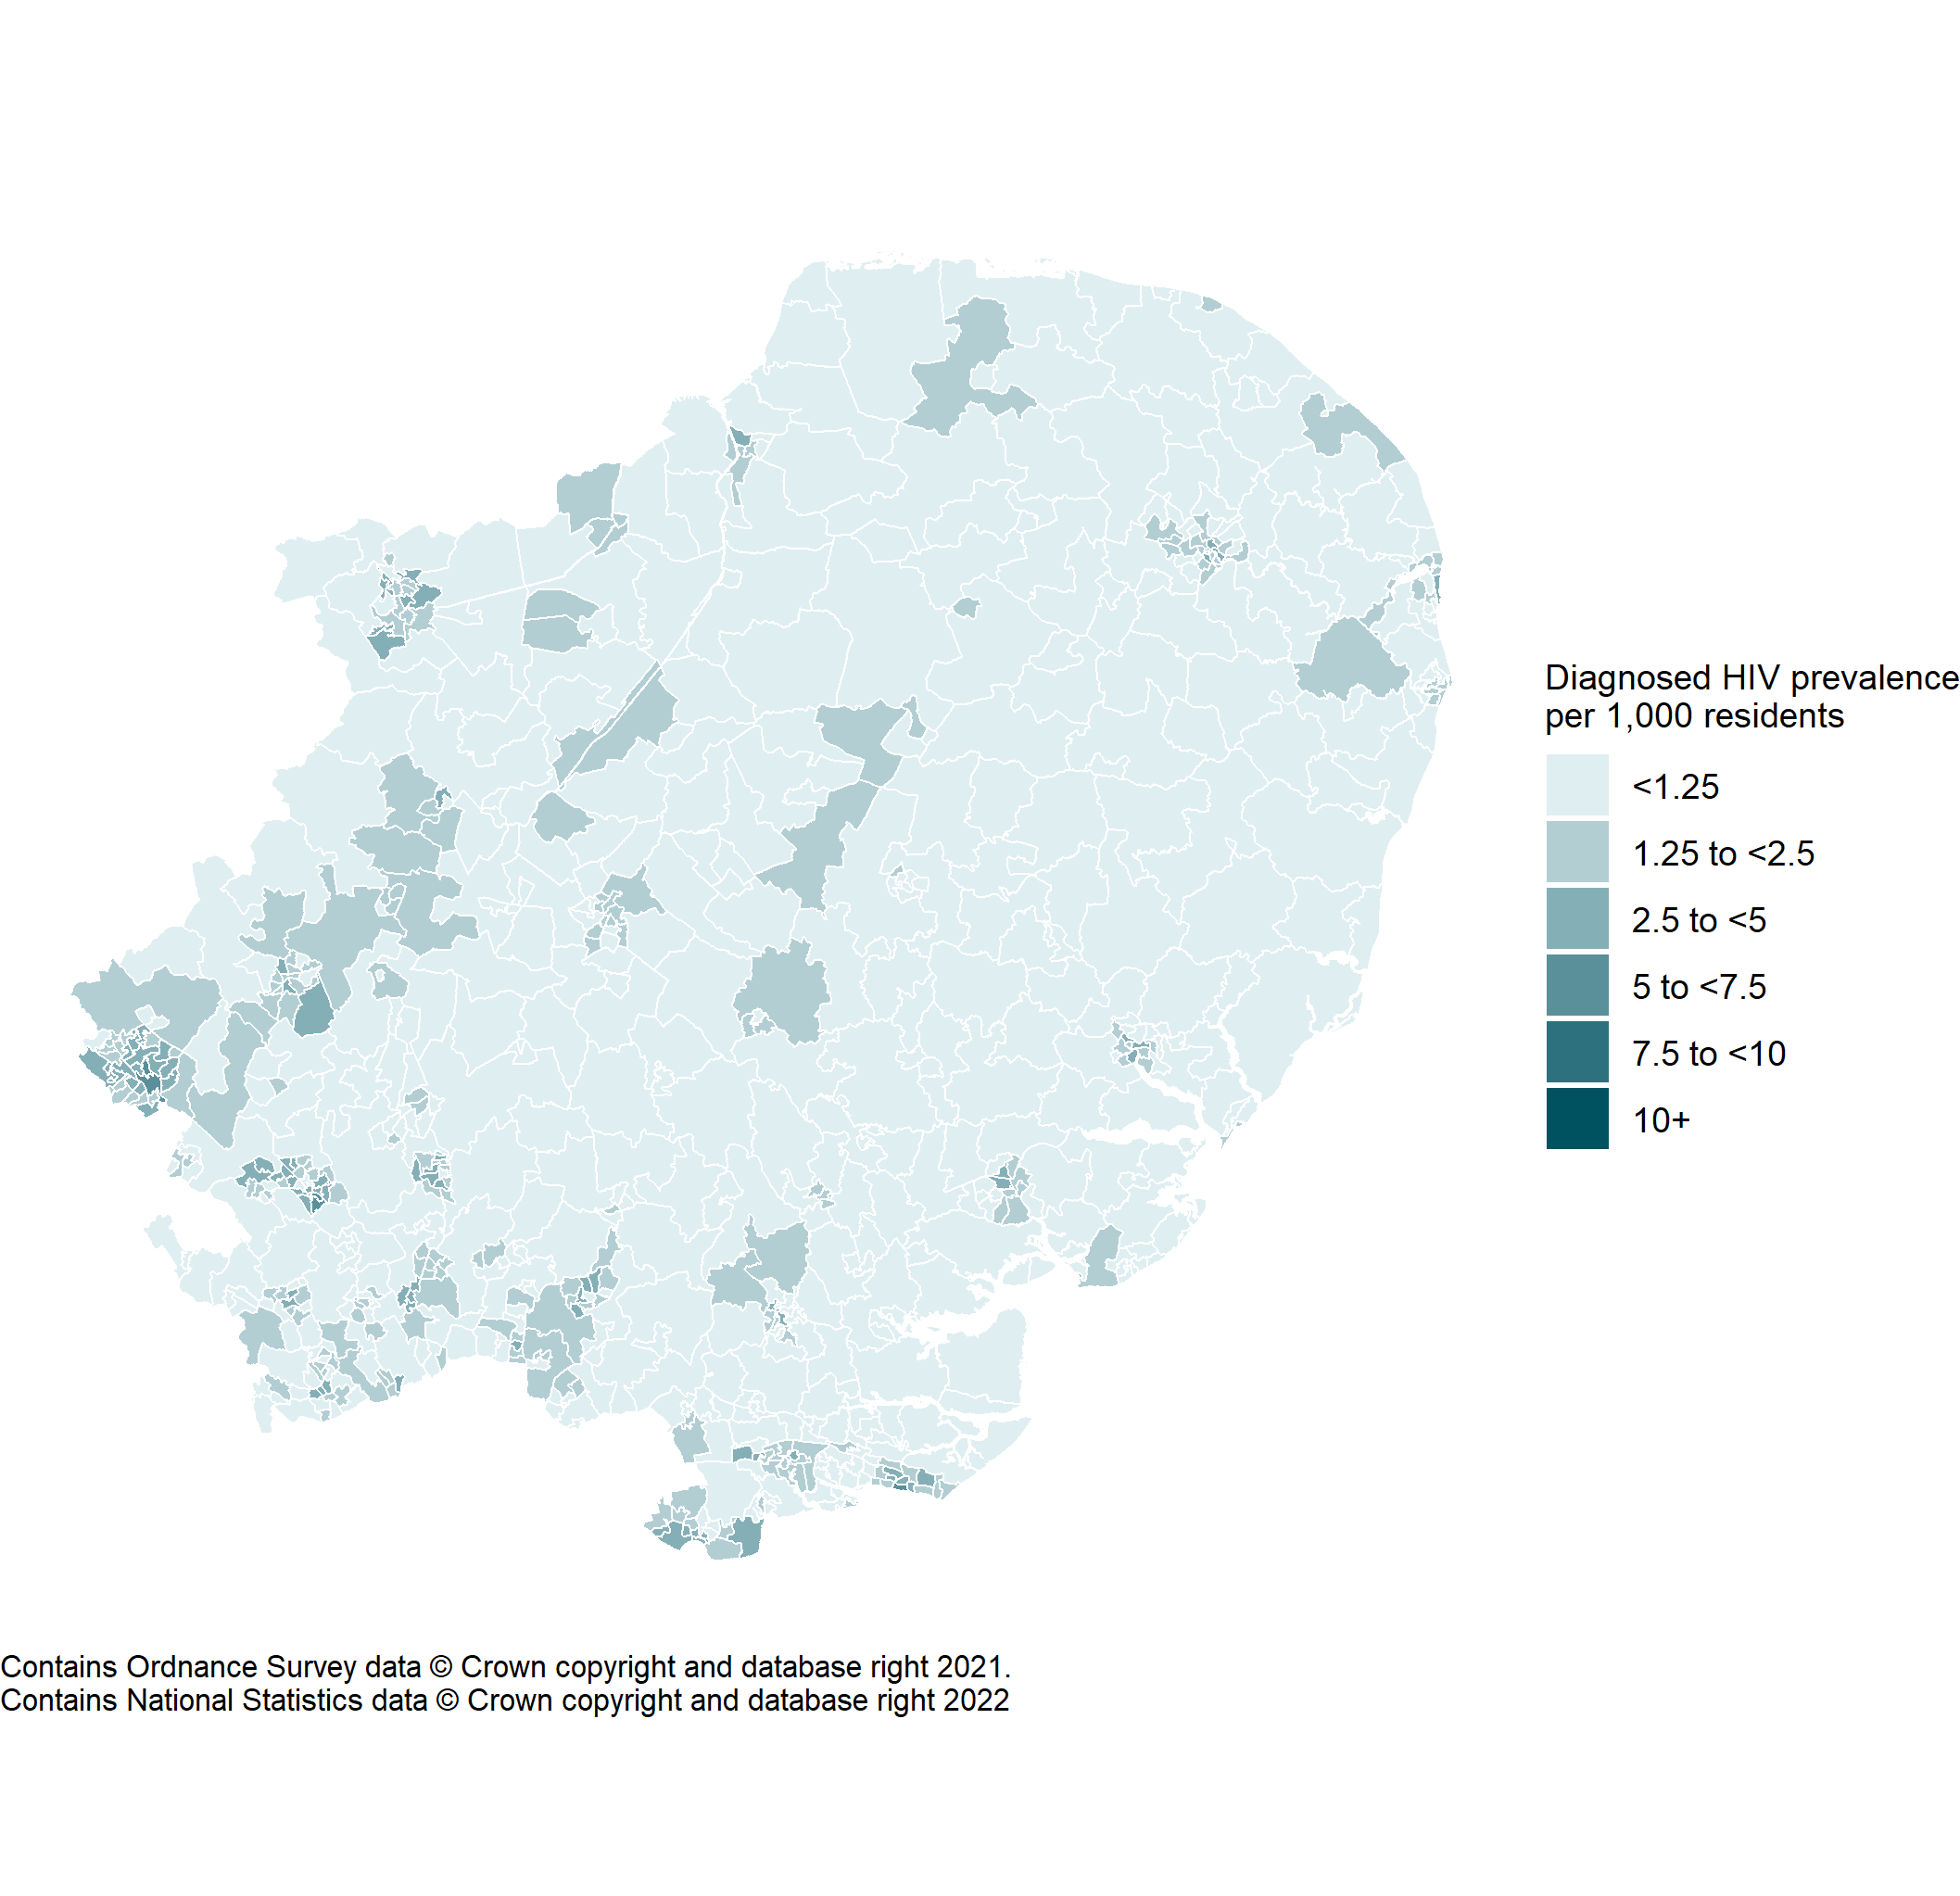
Figure 32. Diagnosed HIV prevalence per 1,000 residents (all ages) by middle super outer area of residence the East of England, 2024
Source: UKHSA, HIV and AIDS Reporting System (HARS).
Figure 32 is a map showing the diagnosed HIV prevalence rate per 1,000 East of England residents of all ages by middle super output area (MSOA) of residence in the East of England in 2024. MOSA’s are colour coded based on HIV prevalence rate, lower rates are indicated by a lighter blue and higher rates by darker blue.
The majority of MSOAs in the East of England have a diagnosed HIV prevalence rate of less than 1.25 per 1,000 (light blue). Some MSOAs, particularly around the more densely populated areas of Milton Keynes, Peterborough and the outskirts of London show higher diagnosed prevalence rates.
Figure 33. HIV testing rate per 100,000 by population group, East of England residents, 2020 to 2024 [note 6]
Source: UKHSA, GUMCAD.
The proportion of eligible attendees at all sexual health services (SHS) who accepted a HIV test. An eligible attendee is defined as a patient attending specialist SHS at least once during a calendar year. Patients known to be HIV positive, or for whom a HIV test was not appropriate, or for whom the attendance was related to Sexual and Reproductive Health (SRH) care only, are excluded.
Note 6; ONS mid-2023 population estimates have been used to calculate HIV testing rates.
Figure 33 is a line chart showing the trend in HIV testing rate per 100,000 at sexual health services (SHSs) by population group (males, females, all) in East of England residents between 2020 and 2024.
Testing rates among all population groups between 2020 and 2023 increased. Between 2023 and 2024 the testing rates for all decreased. In 2024, testing rates have not returned to the pre-pandemic levels of 2019.
Between 2020 and 2022 males had a higher testing rate than females, however in 2023 and 2024 the testing rate was higher among females. In 2024, testing rate among males was 1,321 per 100,000, and 1,570 per 100,000 among females. The overall testing rate in 2024 was 1,593 per 100,000.
Table 2. People tested for HIV by population group, East of England residents attending all SHSs, 2020 to 2024
| Gender or sexual orientation | 2020 | 2021 | 2022 | 2023 | 2024 | % change 2020 to 2024 | % change 2023 to 2024 |
|---|---|---|---|---|---|---|---|
| Heterosexual men | 21,637 | 22,730 | 27,388 | 27,894 | 22,472 | 4% | -19% |
| Gay and bisexual men | 10,897 | 14,377 | 15,251 | 14,802 | 13,087 | 20% | -12% |
| All men | 33,461 | 38,177 | 43,994 | 45,882 | 42,448 | 27% | -7% |
| Hetero and bisexual women | 37,916 | 42,805 | 46,798 | 44,170 | 30,755 | -19% | -30% |
| All women | 39,266 | 44,259 | 48,481 | 48,490 | 40,475 | 3% | -17% |
| Total | 74,671 | 88,111 | 98,985 | 102,317 | 92,091 | 23% | -10% |
Source: UKHSA, GUMCAD.
The totals for ‘All men’ and ‘All women’ include people tested from sexual orientation categories not shown in the table above.
Table 2 shows the number of East of England residents tested for HIV at all sexual health services (SHSs) by gender and sexual orientation from 2020 to 2024, and the percentage change between the years.
When comparing the number of individuals tested in 2024 compared to 2020, testing among men of all sexual orientations and women overall has increased, however testing for hetero/bisexual women decreased.
Overall, there was a 23% increase in the number of HIV tests between 2020 and 2024. The largest percentage increase between 2020 and 2024 was observed for men overall, with a 27% increase, followed by gay and bisexual men (20%), heterosexual men (4%) and women overall (3%). Decreases were seen in hetero/bisexual women (-19%).
Between 2023 and 2024, decreases were seen among all gender and sexual orientation groups, with the largest percentage decreases seen among women. Testing among hetero/bisexual women decreased by 30%, followed by heterosexual men (-19%), all women (-17%), gay and bisexual men (-12%) and all men (-7%). Overall, there was a 10% decrease in the number of tests at all sexual health services between 2023 and 2024.
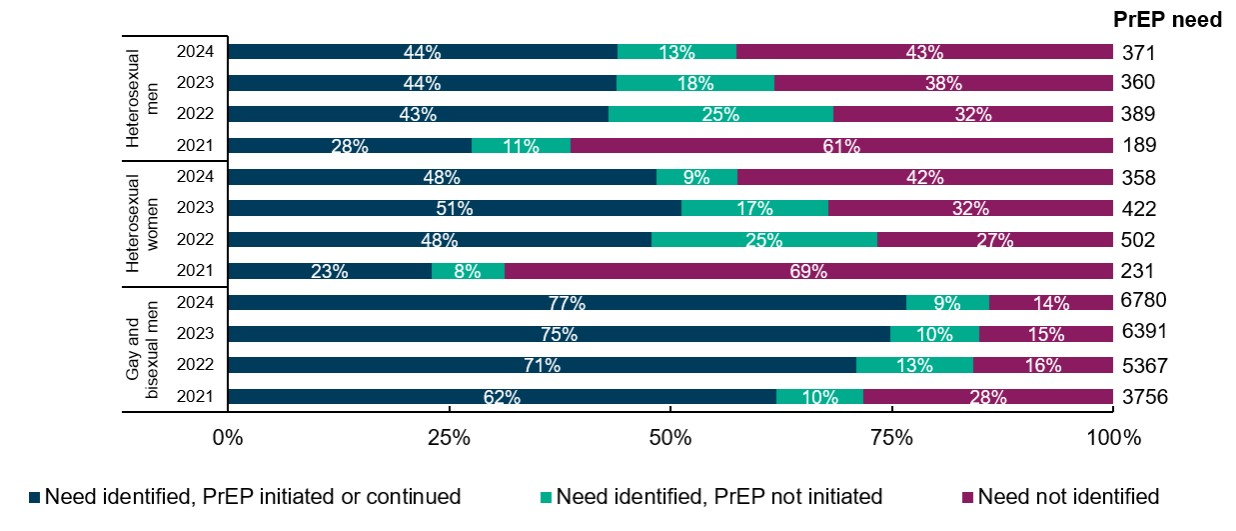
Figure 34. HIV pre-exposure prophylaxis (PrEP) need, identification and initiation/continuation in residents attending specialist sexual health services (SHSs), the East of England, 2024
Source: UKHSA, GUMCAD.
Figure 34 is a chart showing information about PrEP need and use by gender and sexual orientation in 2024. On the right is the number of individuals by year and gender identity and sexual orientation who were identified as having a PrEP need. The dark blue represents the proportion of those with PrEP need who had that need identified and who either initiated or continued PrEP, the green represents the proportion with a PrEP need identified but who did not initiate PrEP and the purple the proportion who did not have their need identified.
Figure 34 is a chart showing for East of England residents by gender and sexual orientation the proportion attending specialist sexual health services (SHSs) who had PrEP need identified and initiated or continued PrEP, who had the need identified and did not initiate PrEP and those who did not have PrEP need identified.
The figure shows that PrEP need is not identified consistently between gender and sexual orientation in the East of England. Gay and bisexual men have the lowest proportion of PrEP need not identified and the highest proportion of those with PrEP need identified either initiating or continuing PrEP. PrEP need was more likely to be not identified for both heterosexual men and women, although in 2024 the need was more likely to be identified than in 2021.
Information on data sources
-
HIV and AIDS New Diagnoses and Deaths (HANDD) collects information on new HIV diagnoses, AIDS at diagnosis and deaths among people diagnosed with HIV. Information is received from laboratories, specialist SHSs, GPs and other services where HIV testing takes place in England, Wales and Northern Ireland. The Recent Infection Testing Algorithm (RITA) and CD4 surveillance scheme are linked to HANDD to assess trends in recent and late diagnoses. Data is deduplicated across regions and therefore figures may differ from country-specific data.
-
The Survey of Prevalent HIV Infections Diagnosed (SOPHID) began in 1995 and was a cross-sectional survey of all adults living with diagnosed HIV infection who attend for HIV care in England, Wales and Northern Ireland. SOPHID collected information about the individual’s place of residence along with epidemiological data including clinical stage and antiretroviral therapy (ART). In 2015, SOPHID reporting in England was replaced by the HIV and AIDS Reporting System (HARS) which captures information at every attendance for HIV care.
-
Date of data extract: October 2024. Updates to HANDD and SOPHID/HARS made after this date will not be reflected in this report.
-
Confidence intervals for rates in the figures have been calculated to the 95% level using the Byar’s method; confidence intervals for percentages have been calculated to the 95% level using the Wilson Score method. Confidence intervals presented in the text are produced by Bayesian analysis.
-
The most recent ONS mid-year estimates at the time of analysis were used as denominators for rates. Unless otherwise stated, for UTLAs 2024 estimates were used (published June 2024), for MSOAs 2022 estimates were used (published November 2024), for LTLAs 2021 estimates were used (published November 2022), and for LSOAs 2022 estimates were used (published November 2024).
-
The data behind charts showing absolute numbers may have been adjusted for missing information; however, unless stated otherwise, the numbers in the summary section are the numbers as reported, that is, unadjusted counts. Where charts are displaying adjusted data this is indicated in the chart title. Where figures have been ‘adjusted for missing information’, this means that when unknown values are present (for example, route of probable exposure = ‘unknown’), they are proportionally distributed amongst other groups for the purposes of analysis (for example, if A = 12, B = 4, C = 2, and unknown = 6, the 6 ‘unknown’ values are distributed proportionally among groups A, B, and C to give A = 15, B = 6, C = 3).
-
The denominators for all percentages exclude records for which information was unknown, that is, the proportion of new diagnoses where probable route of exposure was gay and bisexual men would be calculated using new diagnoses for which route of exposure was known as the denominator.
All analyses in this report are residence-based and reflect the patient’s place of residence at diagnosis.
Numbers may change as more information becomes available to assign area of residence to cases and historical data is refreshed accordingly.
More information
For more information on a whole range of sexual health indicators, see:
For more information on local sexual health data sources, see:
For the annual epidemiological spotlight on STIs in East of England 2024, see:
For the national HIV report 2024, see:
Local authorities have access to additional HIV and STI intelligence via the Data Exchange and the HIV and STI web portal. They should also have received a set of tables containing HIV data specific to their authority. If they do not have access to this information, contact eoe.stihiv@ukhsa.gov.uk
About the Field Service
The Field Service was established in 2018 as a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Real-time Syndromic Surveillance and Public Health Microbiology to strengthen the surveillance, intelligence and response functions of UKHSA.
You can contact your local FS team at eoe.stihiv@ukhsa.gov.uk
If you have any comments or feedback regarding this report or the Field Service, contact eoe.stihiv@ukhsa.gov.uk
Acknowledgements
We would like to thank:
- local sexual health and HIV clinics for supplying the HIV data
- Institute of Child Health
- UKHSA Blood Safety, Hepatitis, Sexually Transmitted Infections and HIV Division (BSHSH) for collection, analysis and distribution of data
References
1. Brown Alison E, Shah Ammi, Martin Veronique, Chau Cuong, Djuretic Tamara. ‘People diagnosed with HIV before continuing care in England are extremely unlikely to pass on HIV in England’ HIV Medicine 2025: volume 26, issue 10, pages 1,626 to 1,627
2. Shah Ammi, Mackay Neil, Kitt Hannah, Harrison Catriona, Okumu-Camerra Kadeen, Ratna Natasha and others. ‘HIV testing, PrEP, new HIV diagnoses and care outcomes for people accessing HIV services: 2025 report’ The annual official statistics data release (data to end of December 2024)