Quarterly vaccination coverage statistics for children aged up to 5 years in the UK (COVER programme): April to June 2026
Published 24 September 2026

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/statistics/cover-of-vaccination-evaluated-rapidly-cover-programme-2026-to-2027-quarterly-data/quarterly-vaccination-coverage-statistics-for-children-aged-up-to-5-years-in-the-uk-cover-programme-april-to-june-2026
Publication date: 24 September 2026
Health Protection Report
Volume 20 Number 9
This report of the Cover of Vaccination Evaluated Rapidly (COVER) programme presents quarterly coverage data for children in the UK who reached their first, second, or fifth birthday during the evaluation quarter (April to June 2026).
The data tables accompanying this report contain full coverage data by country, region, and upper tier local authority (UTLA).
Main points
In comparison with the previous quarter:
-
coverage in England measured in children aged 12 months decreased by 0.6 percentage points for the 6-in-1 vaccine; decreased by 1.6 percentage points for the PCV1 vaccine; decreased by 0.3 percentage points for the rotavirus vaccine; and increased by 1.0 percentage point for the MenB vaccine
-
coverage in the UK measured in children aged 12 months decreased by 0.6 percentage points for the 6-in-1 vaccine; decreased by 1.6 percentage points for the PCV1 vaccine; decreased by 0.3 percentage points for the rotavirus vaccine; and increased by 0.9 percentage points for the MenB vaccine
-
coverage of the first dose of MMR measured at 24 months (in children who first became eligible between April 2025 and June 2025) remained stable in England and decreased by 0.1 percentage points in the UK
-
coverage of the first dose of MMR measured in children aged 5 years decreased by 0.3 percentage points in England, largely reflecting vaccinations delivered in April 2022 to June 2022
-
UK coverage for the pre-school booster (dTaP/IPV) decreased by 1.4 percentage points and MMR2 decreased by 1.3 percentage points, reflecting vaccinations that should have been delivered between August 2024 and October 2024
-
both Scotland and Wales exceeded the 95% World Health Organization (WHO) target for coverage for both the 6-in-1 and MMR1 vaccines measured at 5 years
-
in England, vaccination coverage varies geographically and is lowest for all antigens in London as well as in more deprived areas
-
vaccination coverage measured this quarter remains below peaks in coverage reported in the previous 10-year period, and for a number of antigens, represents a continuation of an ongoing declining trend in coverage
Coverage at 12 months
Compared with the previous quarter, UK coverage of the 6-in-1 measured at 12 months decreased by 0.6 percentage points to 89.5%, PCV1 coverage decreased by 1.6 percentage points to 89.8%, rotavirus decreased by 0.3 percentage points to 87.9%, and MenB increased by 0.9 percentage points to 91.6%.
In England, 12-month coverage of the 6-in-1 decreased by 0.6 percentage points to 89.2%, PCV1 coverage decreased by 1.6 percentage points to 89.5%, rotavirus decreased by 0.3 percentage points to 87.6%, and MenB increased by 1.0 percentage point to 91.4%. This is the first COVER report including children affected by the change to the childhood immunisation schedule of the PCV being administered at 16 weeks rather than 12, and the second dose of MenB being administered at 12 weeks rather than 16. Compared to the previous quarterly report, children included in this report had 4 weeks fewer between point of eligibility and point of measurement to receive PCV and 4 weeks more to receive the second dose of MenB.
Across England excluding London (as this was the region with the lowest coverage), 6-in-1 coverage at 12 months was 90.4%, 1.2 percentage points higher than the overall England coverage; PCV1 coverage was 90.7%, 1.2 percentage points higher than the overall England coverage; rotavirus coverage was 88.7%, 1.1 percentage points higher than the overall England coverage, and MenB was 92.4%, 1.0 percentage point higher than the overall England coverage.
In Scotland and Wales, coverage was at or above 92% for all antigens at 12 months except for rotavirus, which was 91.1% in Scotland and 90.6% in Wales. In Northern Ireland coverage was above 84% for all antigens.
Compared to the previous quarter, 6-in-1 coverage decreased in all regions: the East of England (1.0 percentage point), London (0.5 percentage points), the Midlands (0.4 percentage points), the North East and Yorkshire (0.7 percentage points), the North West (0.8 percentage points), the South East (0.3 percentage points), and the South West (0.3 percentage points).
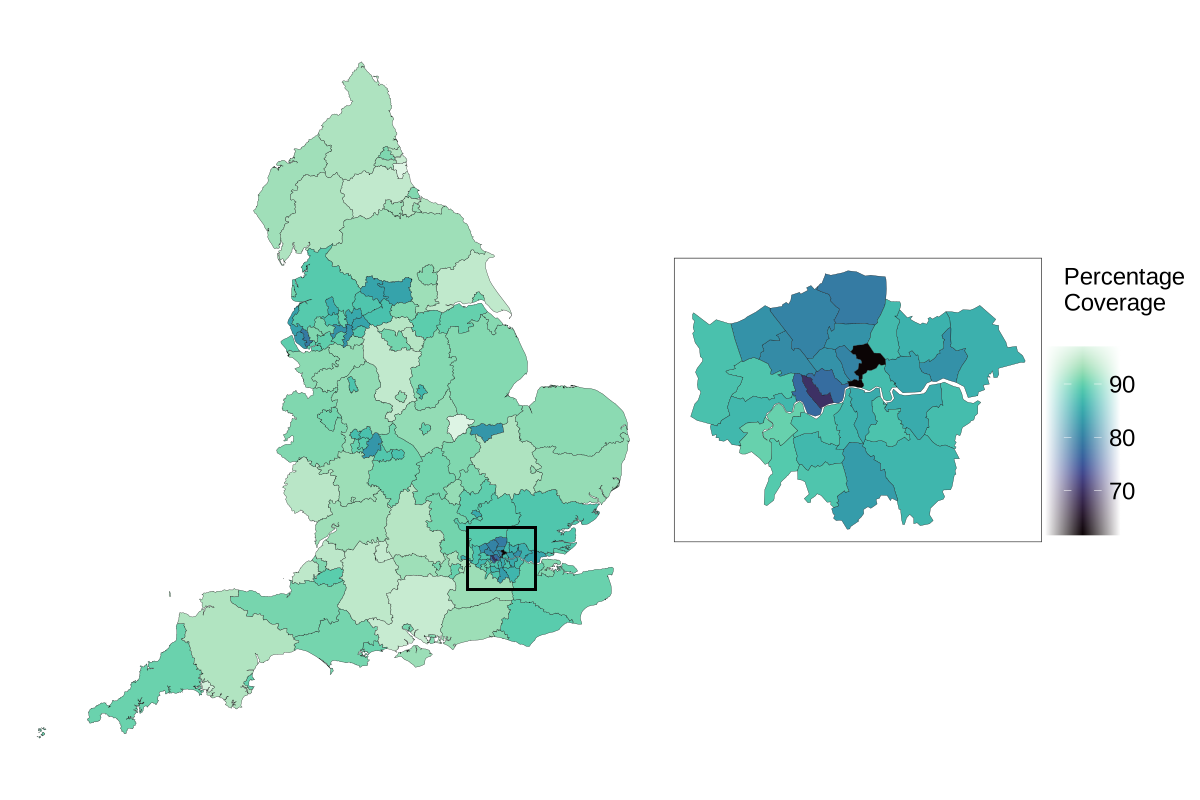
Coverage varies by geography. Full coverage data by country, NHS England region, UK Health Security Agency (UKHSA) region, and UTLA is contained in the data tables accompanying this report. Coverage for the 6-in-1 vaccine for quarter 1 2026 to 2027 by UTLA measured in children aged 12 months is presented in Figure 1.
Figure 1. Coverage of the 6-in-1 vaccine measured in children aged 12 months in England for quarter 1 2026 to 2027 by UTLA
Source of vaccine coverage data: UK Health Security Agency.
Source of boundaries: Office for National Statistics licensed under the Open Government Licence v.3.0. Contains OS data © Crown copyright and database right 2025.
Coverage of the 6-in-1 vaccine measured at 12 months varies by UTLA. The data underlying Figure 1 is available in the accompanying data file.
In England over the last 10 years, coverage of the 6-in-1 peaked in quarter 3 of 2016 to 2017 at 93.4%, 4.2 percentage points higher than the current quarter coverage of 89.2% (Figure 2a).
Figure 2a. Coverage of the primary course of the 6-in-1 vaccine in England measured at 12 months between quarter 2 2016 to 2017 and quarter 1 2026 to 2027 [note 1]
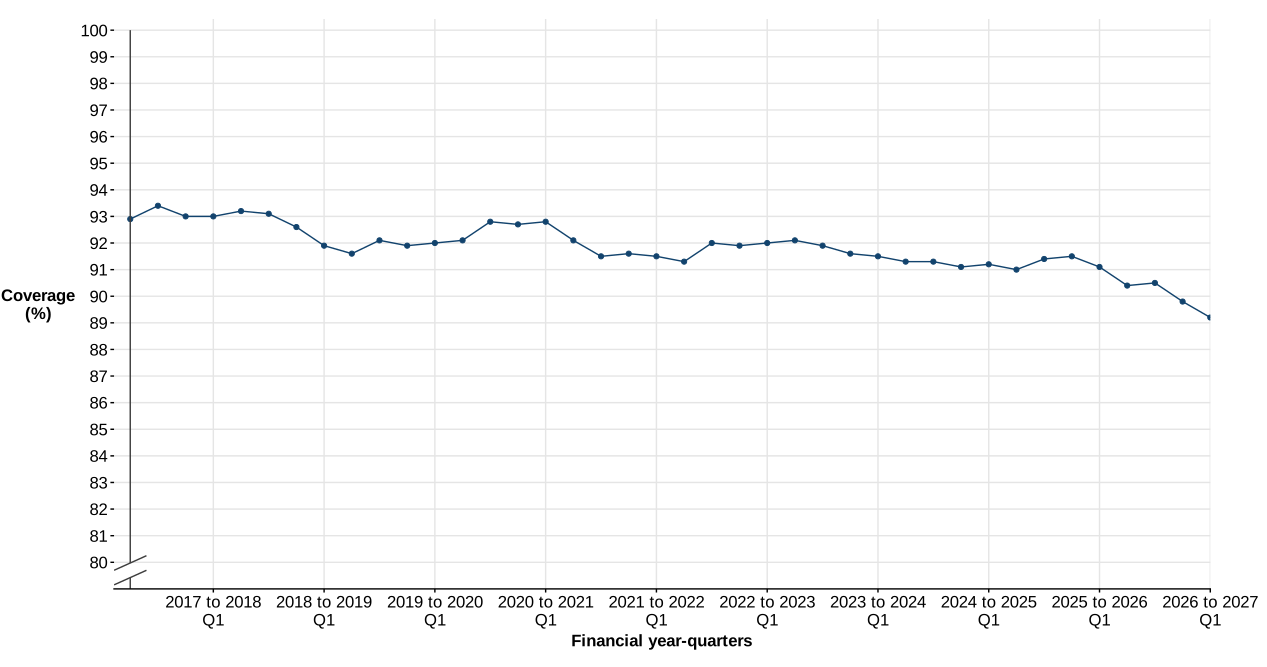
Note 1: the 5-in-1 (DTaP/IPV/Hib3) vaccine was used prior to August 2017 when it was replaced with the 6-in-1 vaccine (DTaP/IPV/Hib/HepB3). As a result, from quarter 4 of 2018 to 2019, coverage of the 6-in-1 vaccine is reported rather than the 5-in-1.
Coverage of PCV1 peaked in quarter 2 of 2022 to 2023 at 94.1%, 4.6 percentage points higher than the current quarter coverage of 89.5% (Figure 2b).
Figure 2b. Coverage of the PCV vaccine in England measured at 12 months between quarter 2 2016 to 2017 and quarter 1 2026 to 2027 [note 2]
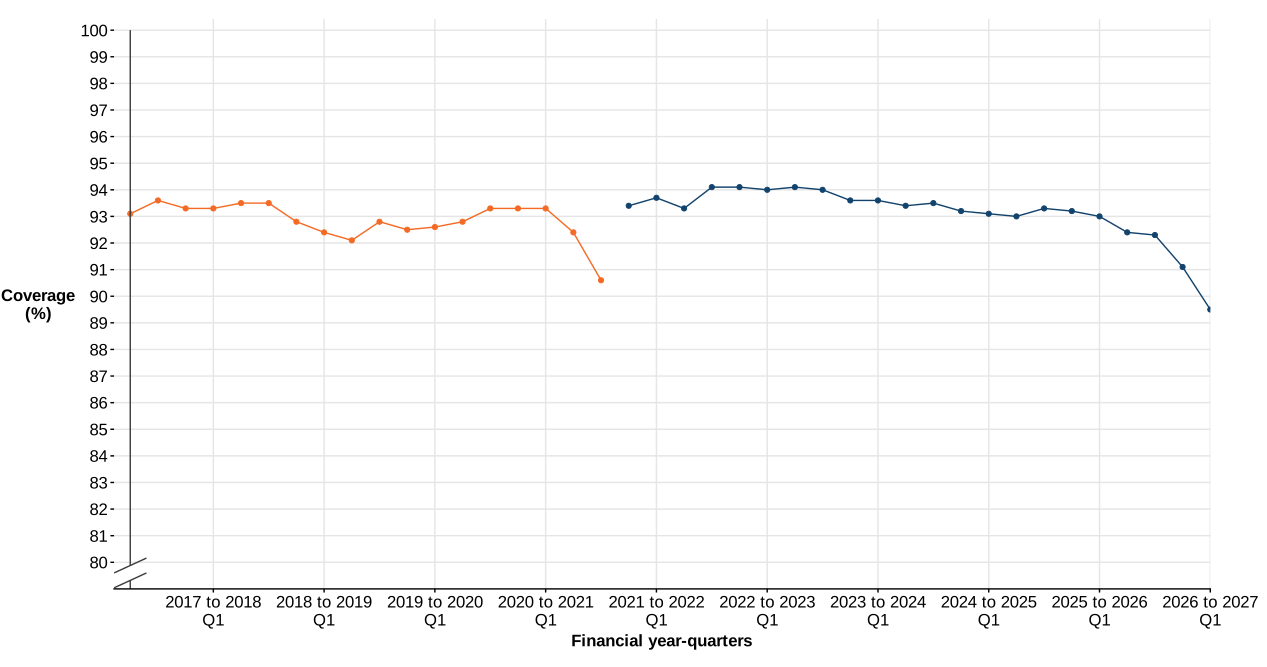
Note 2: from quarter 4 (January to March) 2020 to 2021, PCV1 rather than PCV2 is reported to reflect the change in the PCV schedule.
MenB peaked in quarter 1 of 2020 to 2021 at 93.0%, 1.6 percentage points higher than the current quarter coverage of 91.4% (Figure 2c).
Figure 2c. Coverage of the MenB vaccine in England measured at 12 months between quarter 2 2016 to 2017 and quarter 1 2026 to 2027
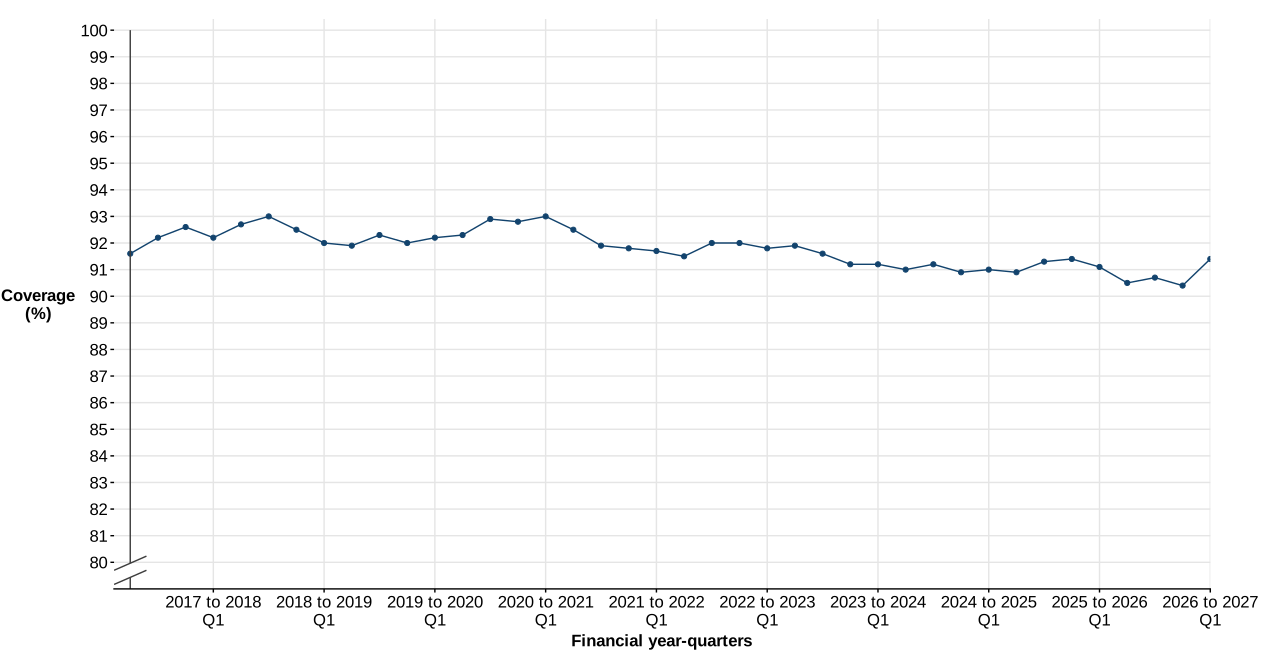
Rotavirus peaked in quarter 1 of 2020 to 2021 at 91.0%, 3.4 percentage points higher than the current quarter coverage of 87.6% (Figure 2d).
Figure 2d. Coverage of the rotavirus vaccine in England measured at 12 months between quarter 2 2016 to 2017 and quarter 1 2026 to 2027
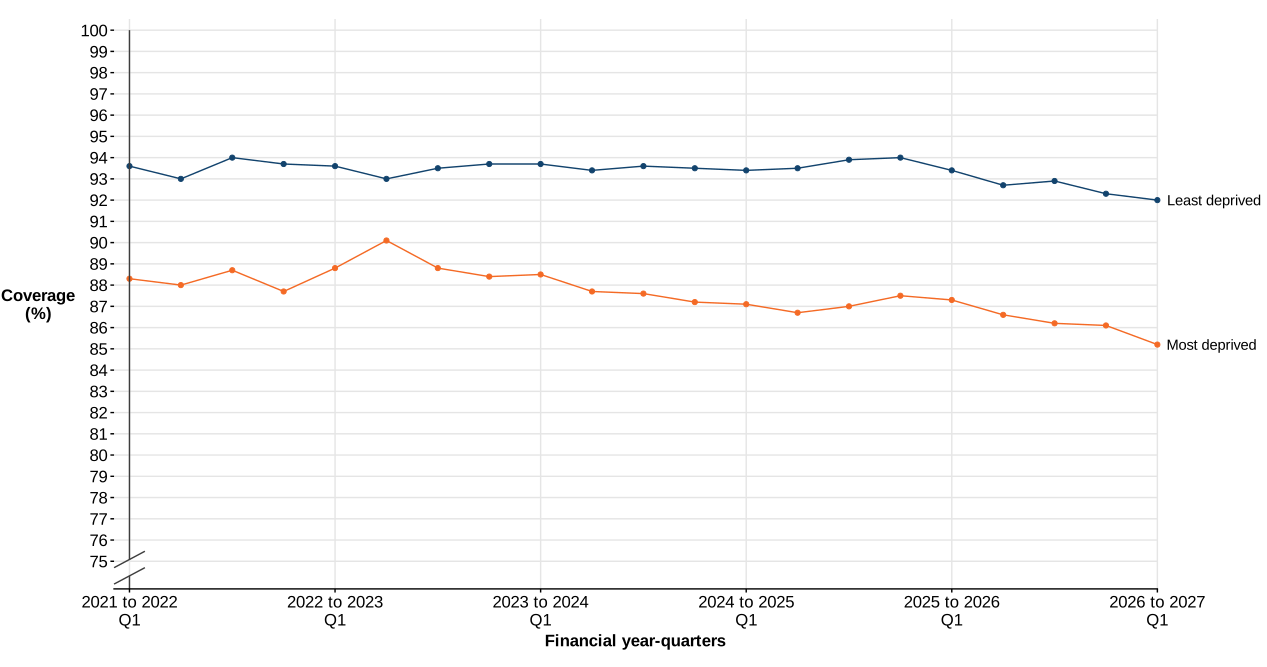
Based on the 2025 Index of Multiple Deprivation (IMD) scores at the UTLA level, in the 30 least deprived UTLAs, coverage of the 6-in-1 decreased by 0.3 percentage points to 92.0%. In comparison, in the 30 most deprived UTLAs, coverage of the 6-in-1 decreased by 0.9 percentage points to 85.2%, 6.8 percentage points lower than the 30 least deprived UTLAs. The difference in coverage between these groups has been increasing in the last 6 years, with coverage in the least deprived group remaining relatively stable and coverage in the most deprived group decreasing (Figure 3).
Figure 3. Coverage of the primary course of the 6-in-1 vaccine in the 30 most and least deprived local authorities in England, measured at 12 months
Coverage at 24 months
In the UK, compared with the previous quarter, coverage of the 6-in-1 vaccine decreased by 0.3 percentage points to 92.3%, PCV booster coverage remained stable at 87.5%, MMR1 coverage decreased by 0.1 percentage points to 87.7%, and MenB booster coverage decreased by 0.2 percentage points to 86.8%.
In England, 24-month coverage of the 6-in-1 decreased by 0.3 percentage points to 92.0%, PCV booster coverage remained stable at 87.1%, MMR1 coverage remained stable at 87.3%, and MenB booster coverage decreased by 0.2 percentage points to 86.3%.
Across England excluding London (as this was the region with the lowest coverage), 6-in-1 coverage at 24 months was 93.1%, 1.1 percentage points higher than the overall England coverage; PCV booster coverage was 88.9%, 1.8 percentage points higher than the overall England coverage; MMR1 was 89%, 1.7 percentage points higher than the overall England coverage; and MenB booster coverage was 88.2%, 1.9 percentage points higher than the overall England coverage.
In Scotland and Wales, coverage was above 90% for all antigens at 24 months. In Northern Ireland coverage was above 84% for all antigens.
Compared to the previous quarter, MMR1 coverage decreased in the East of England (0.1 percentage points), the North East and Yorkshire (0.5 percentage points), the North West (0.9 percentage points), and the South East (0.1 percentage points).
There was an increase in MMR1 coverage in London (0.2 percentage points), the Midlands (0.6 percentage points), and the South West (0.2 percentage points).
Coverage varies by geography. Full coverage data by country, region, and UTLA is contained in the data tables accompanying this report.
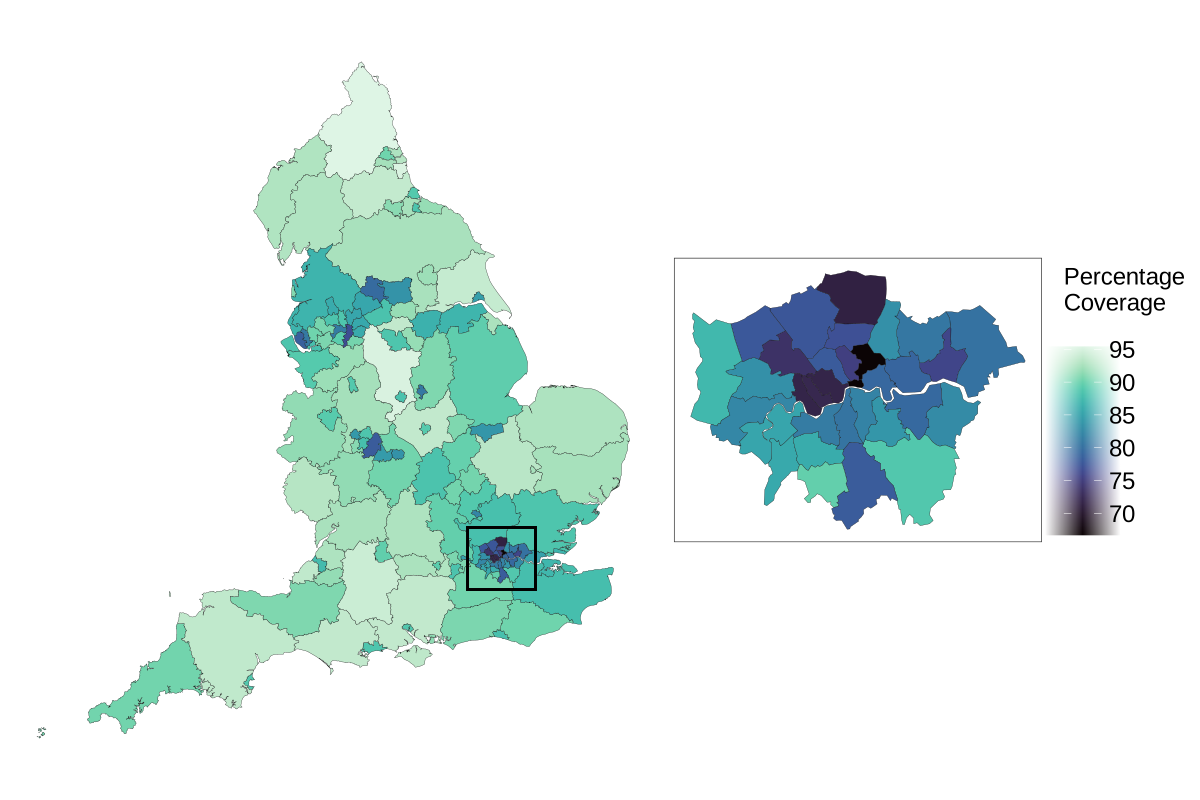
Coverage for the MMR1 vaccine for quarter 1 2026 to 2027 by UTLA measured at 24 months is presented in Figure 4.
Figure 4. Coverage of MMR1 vaccine measured in children aged 24 months in England for quarter 1 2026 to 2027 by UTLA
Source of vaccine coverage data: UK Health Security Agency.
Source of boundaries: Office for National Statistics licensed under the Open Government Licence v.3.0. Contains OS data © Crown copyright and database right 2025.
Coverage of the MMR vaccine measured at 24 months varies by UTLA. The data underlying Figure 4 is available in the accompanying data file.
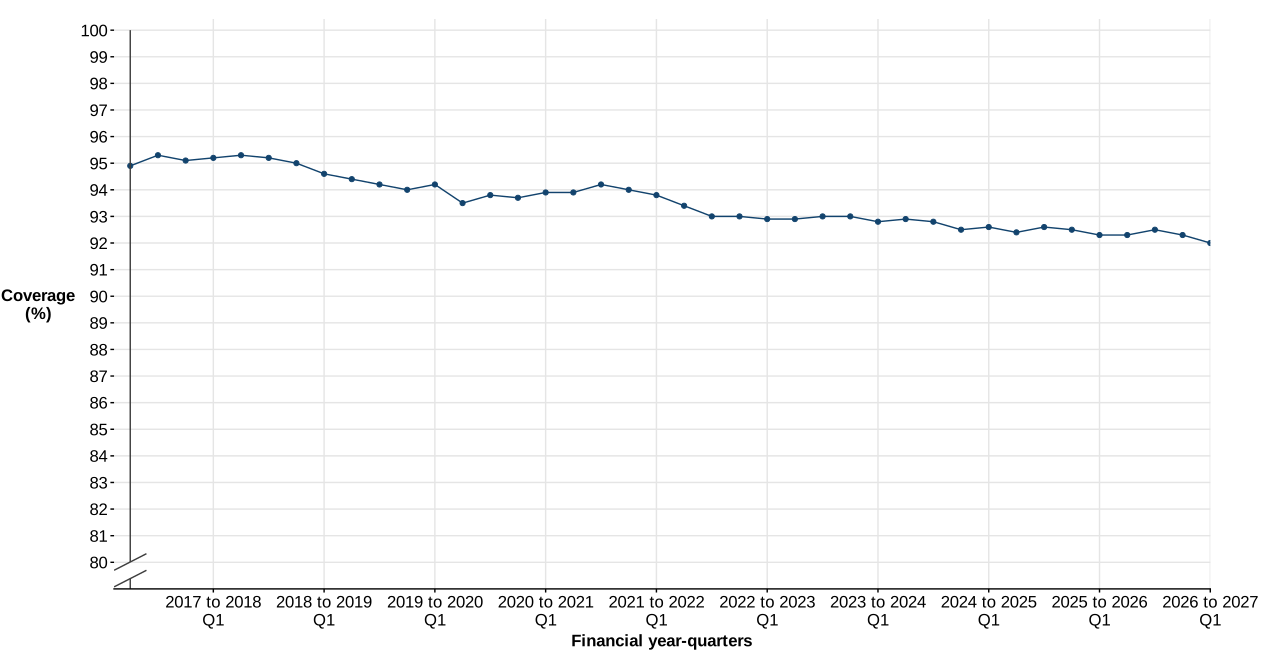
In England over the last 10 years, coverage of the 6-in-1 peaked in quarter 2 of 2017 to 2018 at 95.3%, 3.3 percentage points higher than the current quarter coverage of 92.0% (Figure 5a).
Figure 5a. Coverage of the primary course of the 6-in-1 vaccine in England measured at 24 months between quarter 2 2016 to 2017 and quarter 1 2026 to 2027 [note 1]
Note 1: the 5-in-1 (DTaP/IPV/Hib3) vaccine was used prior to August 2017 when it was replaced with the 6-in-1 vaccine (DTaP/IPV/Hib/HepB3). As a result, from quarter 4 of 2018 to 2019, coverage of the 6-in-1 vaccine is reported rather than the 5-in-1.
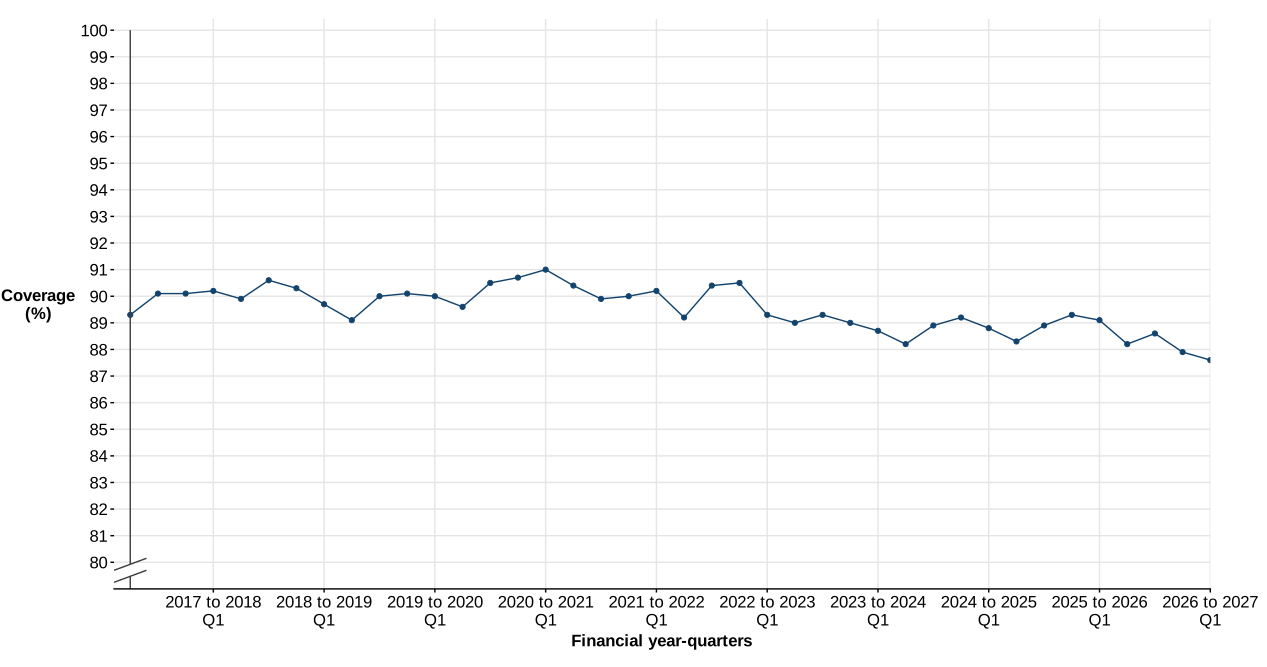
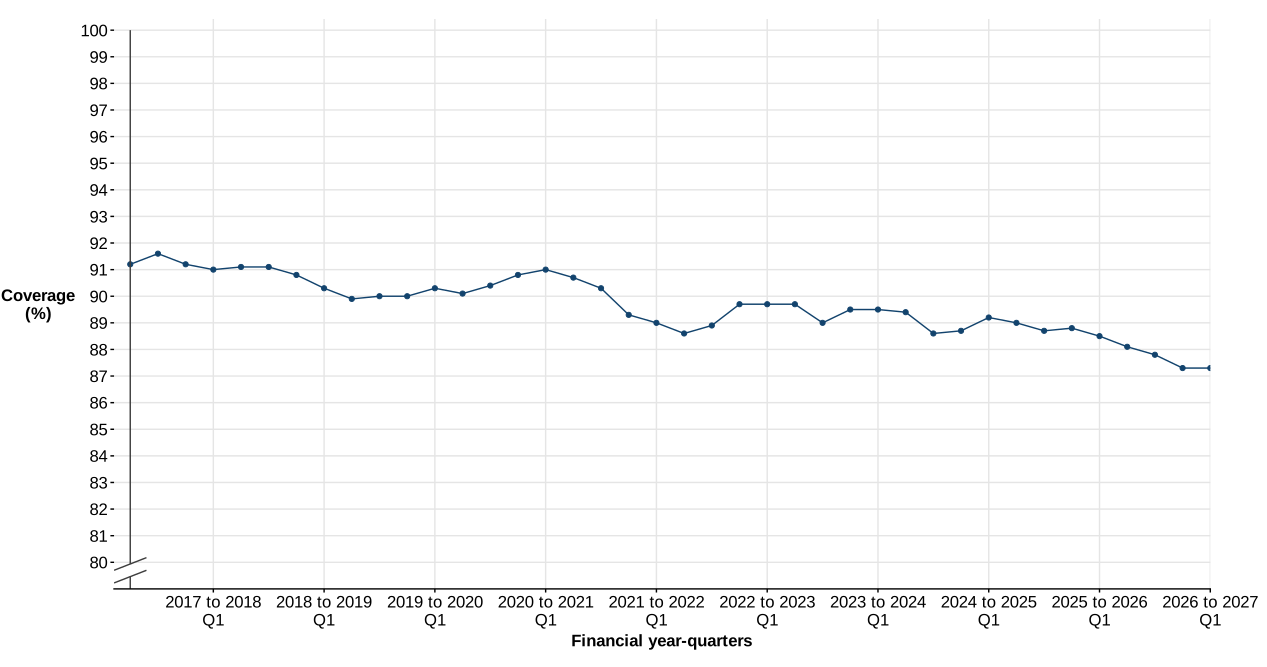
MMR1 peaked in quarter 3 of 2016 to 2017 at 91.6%, 4.3 percentage points higher than the current quarter coverage of 87.3% (Figure 5b).
Figure 5b. Coverage of the MMR1 in England measured at 24 months between quarter 2 2016 to 2017 and quarter 1 2026 to 2027
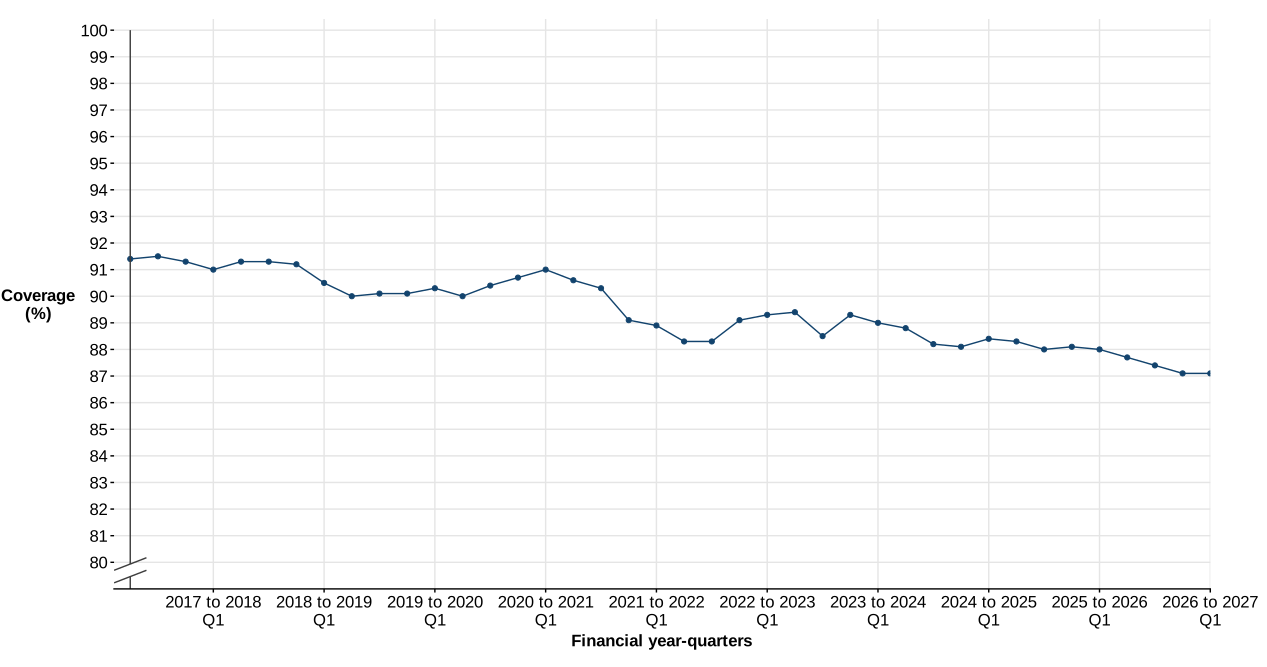
Coverage of the PCV booster peaked in quarter 3 of 2016 to 2017 at 91.5%, 4.4 percentage points higher than the current quarter coverage of 87.1% (Figure 5c).
Figure 5c. Coverage of the PCV booster in England measured at 24 months between quarter 2 2016 to 2017 and quarter 1 2026 to 2027
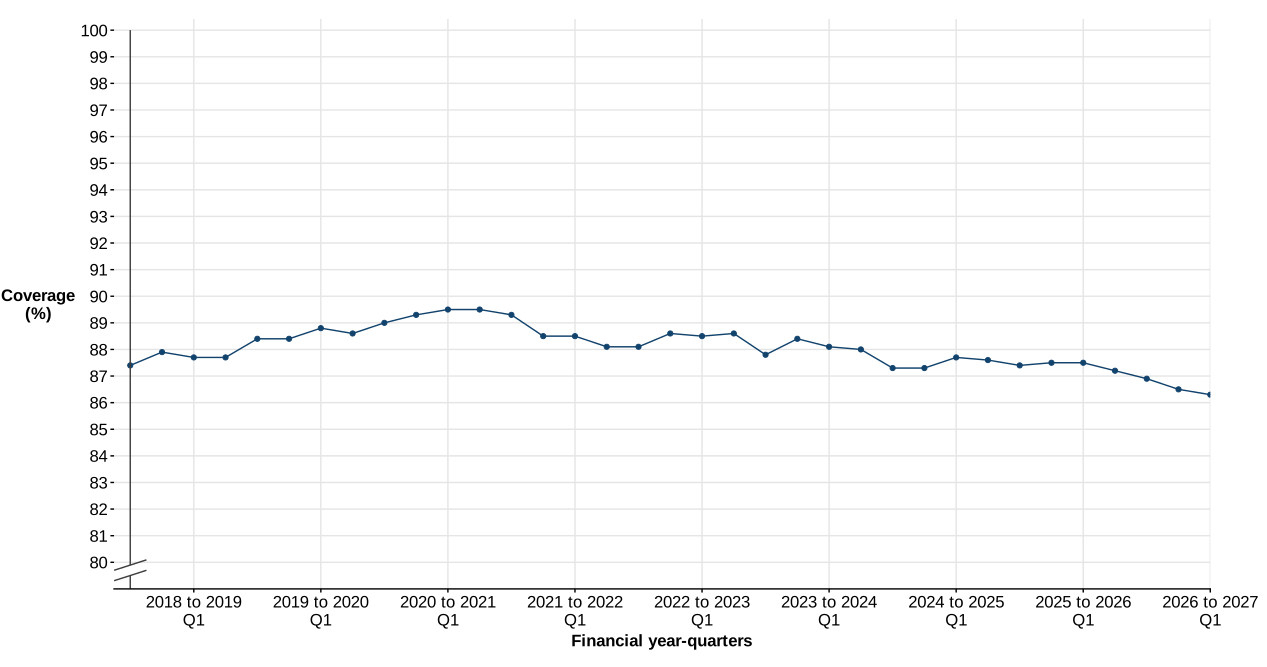
The MenB booster peaked in quarter 2 of 2020 to 2021 at 89.5%, 3.2 percentage points higher than the current quarter coverage of 86.3% (Figure 5d).
Figure 5d. Coverage of the MenB booster in England measured at 24 months between quarter 3 2017 to 2018 and quarter 1 2026 to 2027
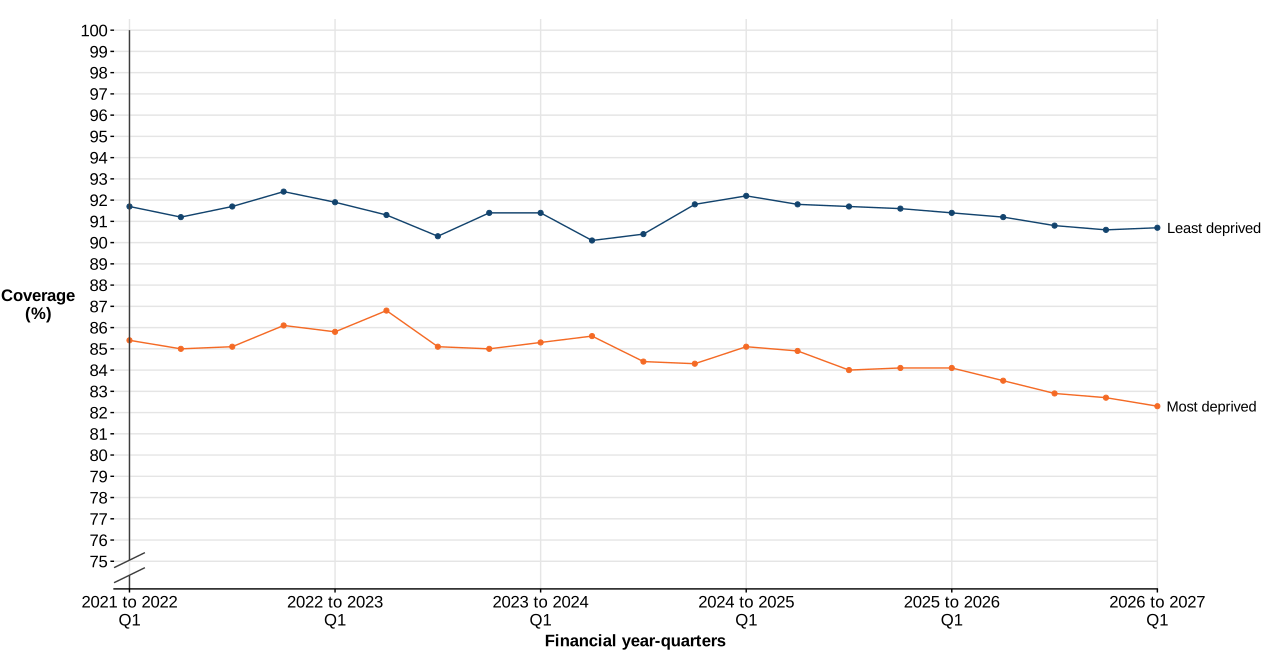
Based on the 2025 IMD scores at the UTLA level, in the 30 least deprived UTLAs, coverage of MMR increased by 0.1 percentage points to 90.7%. In comparison, in the 30 most deprived UTLAs, coverage of MMR decreased by 0.4 percentage points to 82.3%, 8.4 percentage points lower than the 30 least deprived UTLAs. The difference in coverage between these groups has been increasing in the last 6 years, with coverage in the least deprived group remaining relatively stable and coverage in the most deprived group decreasing (Figure 6a).
Figure 6a. Coverage of the MMR1 vaccine in the 30 most and least deprived local authorities in England, measured at 24 months
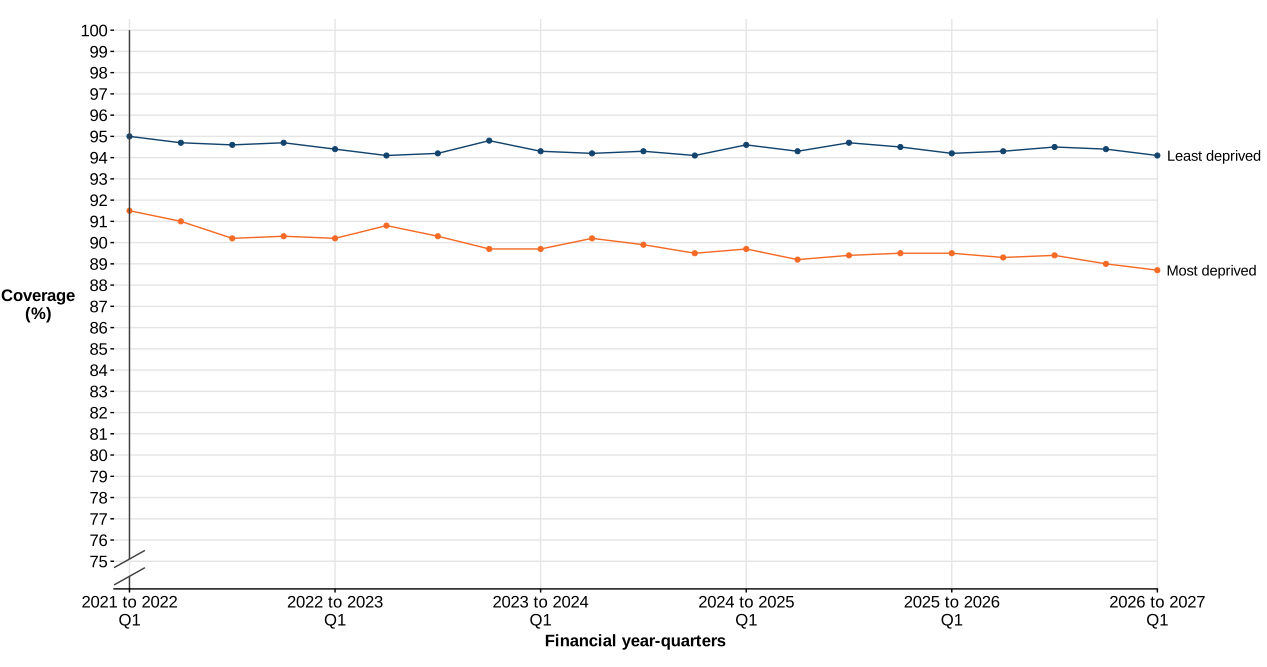
For the 6-in-1, the gap has remained relatively stable over time. Coverage in the most deprived UTLAs dropped by 0.3 percentage points, as did coverage in the least deprived UTLAs (Figure 6b).
Figure 6b. Coverage of the primary course of the 6-in-1 vaccine in the 30 most and least deprived local authorities in England, measured at 24 months
Coverage at 5 years
For the 6-in-1 vaccine, coverage in the UK decreased by 0.3 percentage points to 93.4%, and MMR1 decreased by 0.2 percentage points to 92.6%. Coverage at 5 years for these vaccines primarily reflects vaccinations delivered 4 years ago.
MMR2 and the preschool booster (dTaP/IPV) are given from age 3 years and 4 months and reflect vaccinations that should have been delivered between August 2024 and October 2024.
MMR2 coverage decreased by 1.3 percentage points to 83.3% and the dTaP/IPV booster decreased by 1.4 percentage points to 82.1%.
In England, coverage at 5 years of the 6-in-1 decreased by 0.4 percentage points to 93%, MMR1 coverage decreased by 0.3 percentage points to 92.2%, MMR2 coverage decreased by 1.5 percentage points to 82.6%, and dTaP/IPV booster coverage decreased by 1.6 percentage points to 81.1%.
Across England excluding London (as this was the region with the lowest coverage), 6-in-1 coverage at 5 years was 94.1%, 1.1 percentage points higher than the overall England coverage; MMR1 was 93.7%, 1.5 percentage points higher than the overall England coverage; MMR2 was 85.7%, 3.1 percentage points higher than the overall England coverage; and dTaP/IPV booster coverage was 84.5%, 3.4 percentage points higher than the overall England coverage.
Scotland and Wales met or exceeded the 95% WHO target for coverage for both the 6-in-1 and MMR1 vaccines measured at 5 years, while coverage for both in Northern Ireland was above 92%.
Compared to the previous quarter, MMR1 coverage decreased in the East of England (0.4 percentage points), London (0.4 percentage points), the Midlands (0.5 percentage points), the North East and Yorkshire (0.4 percentage points), the South East (0.3 percentage points), and the South West (0.1 percentage points).
There was an increase in MMR1 coverage in the North West (0.3 percentage points).
Coverage of MMR2 also decreased in all regions: the East of England (1.3 percentage points), London (2.6 percentage points), the Midlands (1.3 percentage points), the North East and Yorkshire (1.8 percentage points), the North West (0.2 percentage points), the South East (1.3 percentage points), and the South West (1.0 percentage point).
Coverage varies by geography. Full coverage data by country, region, and UTLA is contained in the data tables accompanying this report.
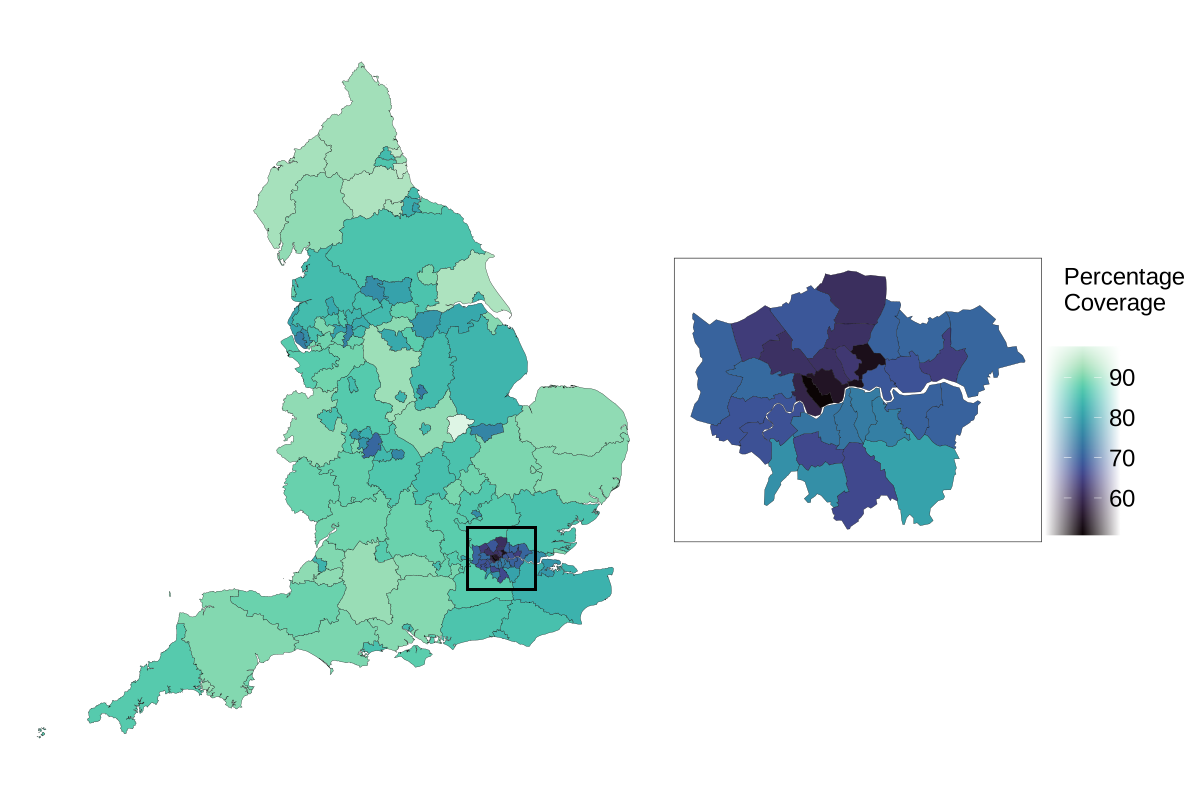
Coverage for the MMR2 vaccine for quarter 1 2026 to 2027 by UTLA measured in children aged 5 years is presented in Figure 7.
Figure 7. Coverage of MMR2 vaccine measured in children aged 5 years in England for quarter 1 2026 to 2027 by UTLA
Source of vaccine coverage data: UK Health Security Agency.
Source of boundaries: Office for National Statistics licensed under the Open Government Licence v.3.0. Contains OS data © Crown copyright and database right 2025.
Coverage of the MMR2 vaccine measured at 5 years varies by UTLA. The data underlying Figure 7 is available in the accompanying data file.
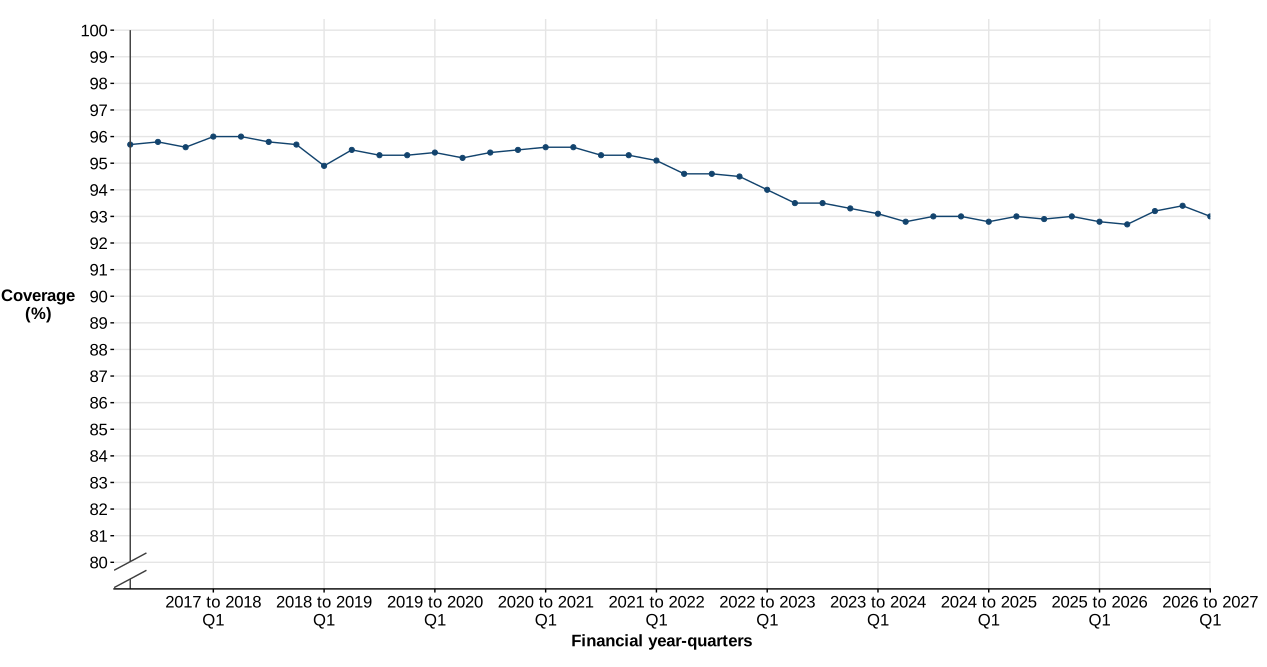
In England over the last 10 years, coverage of the 6-in-1 peaked in quarter 2 of 2017 to 2018 at 96.0%, 3.0 percentage points higher than the current quarter coverage of 93.0% (Figure 8a).
Figure 8a. Coverage of the primary course of the 6-in-1 vaccine in England measured at 5 years between quarter 2 2016 to 2017 and quarter 1 2026 to 2027 [note 1]
Note 1: the 5-in-1 (DTaP/IPV/Hib3) vaccine was used prior to August 2017 when it was replaced with the 6-in-1 vaccine (DTaP/IPV/Hib/HepB3). As a result, from quarter 4 of 2018 to 2019, coverage of the 6-in-1 vaccine is reported rather than the 5-in-1.
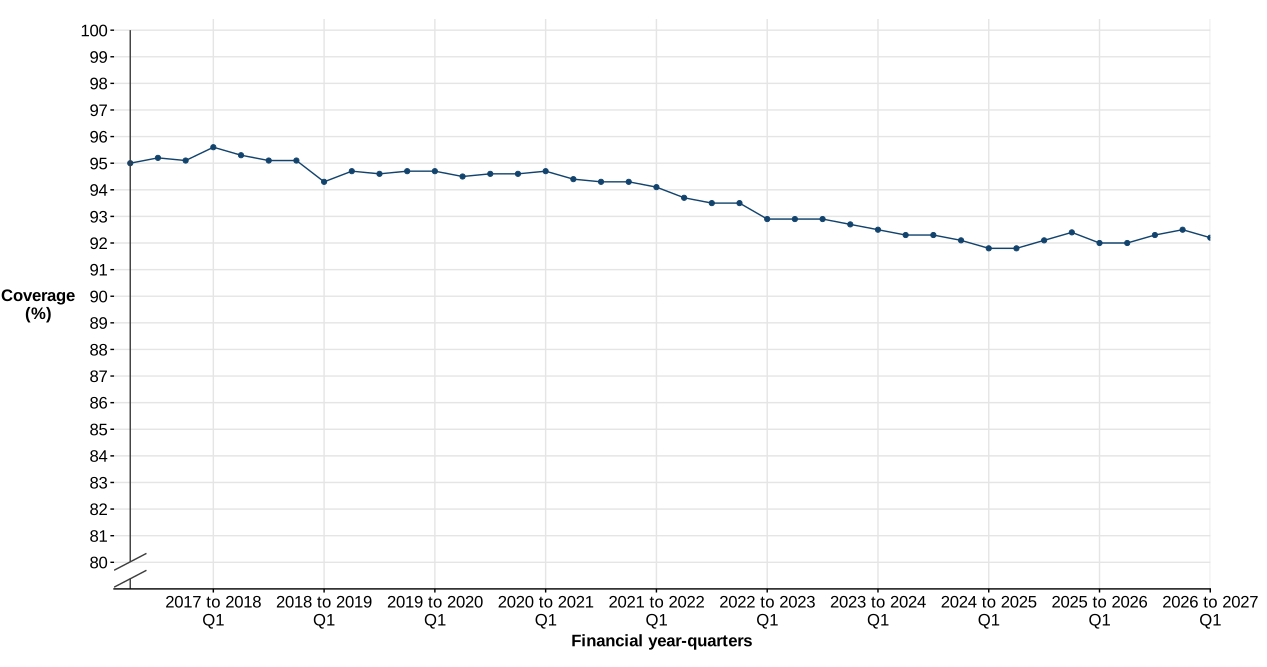
MMR1 peaked in quarter 1 of 2017 to 2018 at 95.6%, 3.4 percentage points higher than the current quarter coverage of 92.2% (Figure 8b).
Figure 8b. Coverage of MMR1 in England measured at 5 years between quarter 2 2016 to 2017 and quarter 1 2026 to 2027
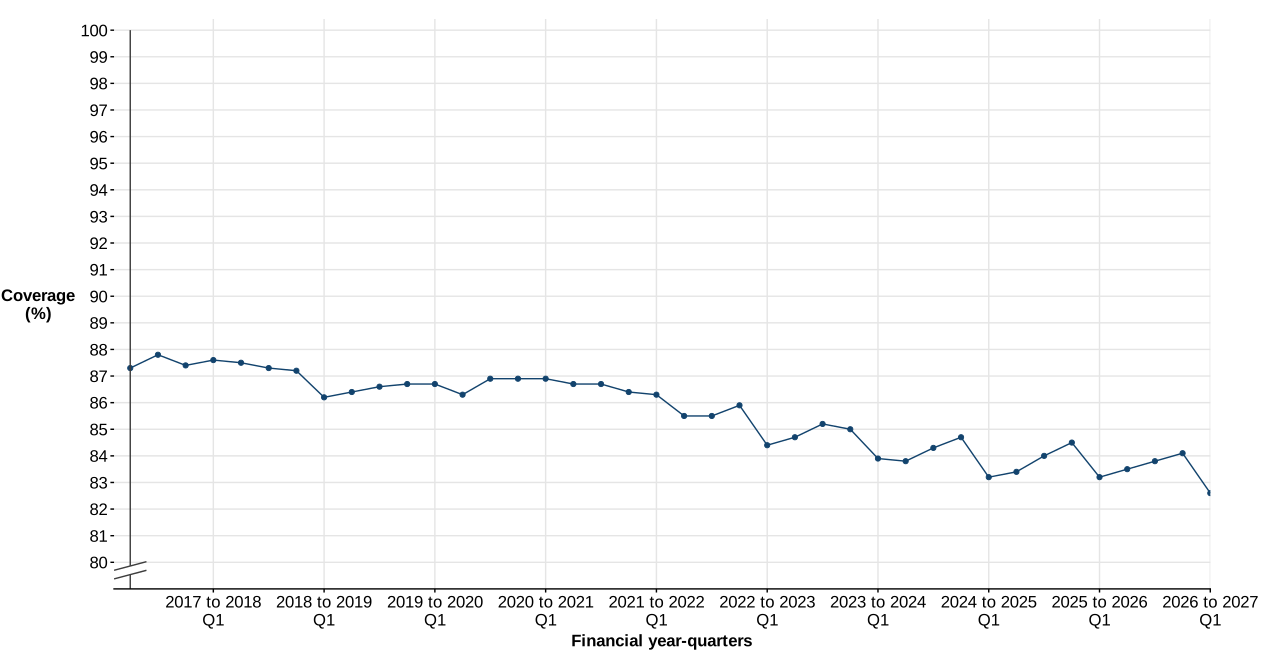
MMR2 peaked in quarter 3 of 2016 to 2017 at 87.8%, 5.2 percentage points higher than the current quarter coverage of 82.6% (Figure 8c).
Figure 8c. Coverage of MMR2 in England measured at 5 years between quarter 2 2016 to 2017 and quarter 1 2026 to 2027
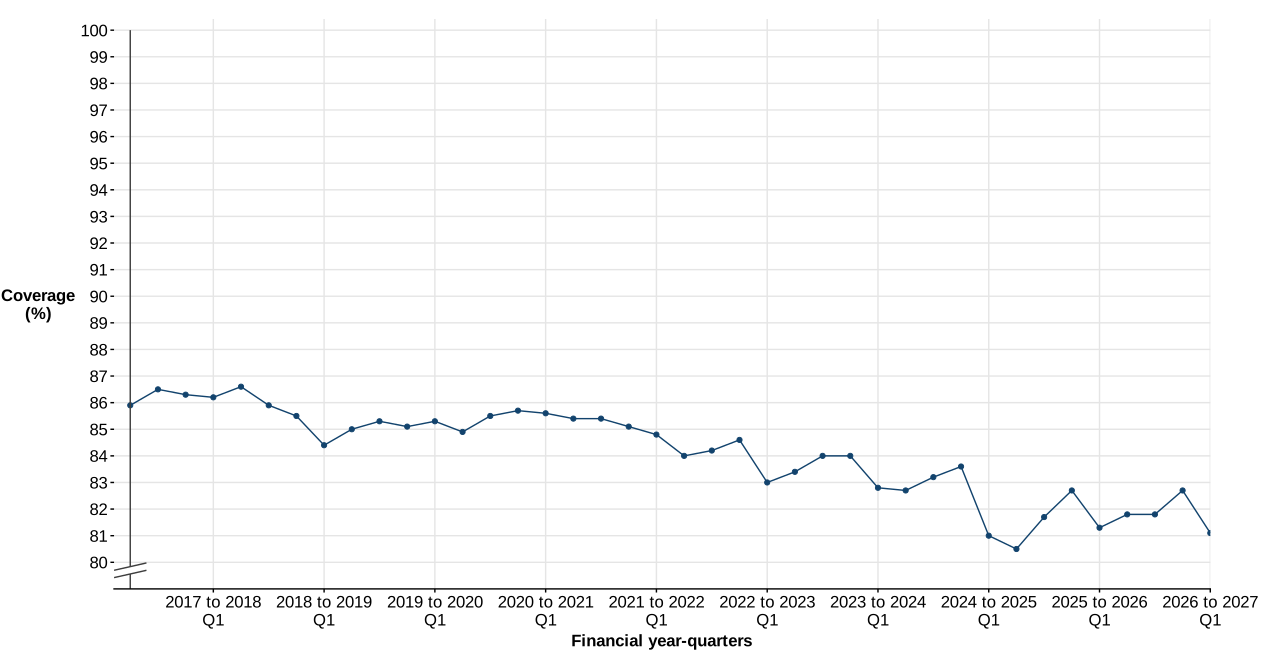
Coverage of the dTaP/IPV booster peaked in quarter 2 of 2017 to 2018 at 86.6%, 5.5 percentage points higher than the current quarter coverage of 81.1% (Figure 8d).
Figure 8d. Coverage of pre-school booster (dTaP/IPV) in England measured at 5 years between quarter 2 2016 to 2017 and quarter 1 2026 to 2027
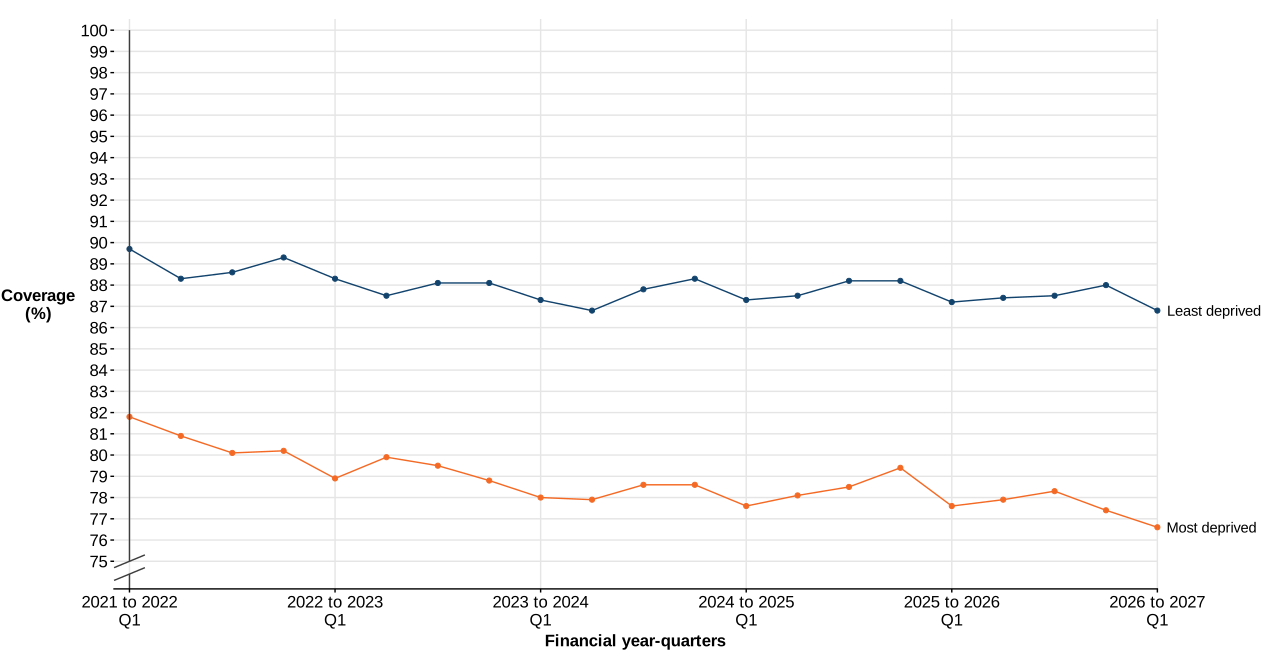
Based on the 2025 IMD scores at the UTLA level, in the 30 least deprived UTLAs, coverage of MMR2 decreased by 1.2 percentage points to 86.8%. In the 30 most deprived UTLAs, coverage of MMR2 decreased by 0.8 percentage points to 76.6%, 10.2 percentage points lower than the 30 least deprived UTLAs (Figure 9a).
Figure 9a. Coverage of the MMR2 vaccine in the 30 most and least deprived local authorities in England, measured at 5 years
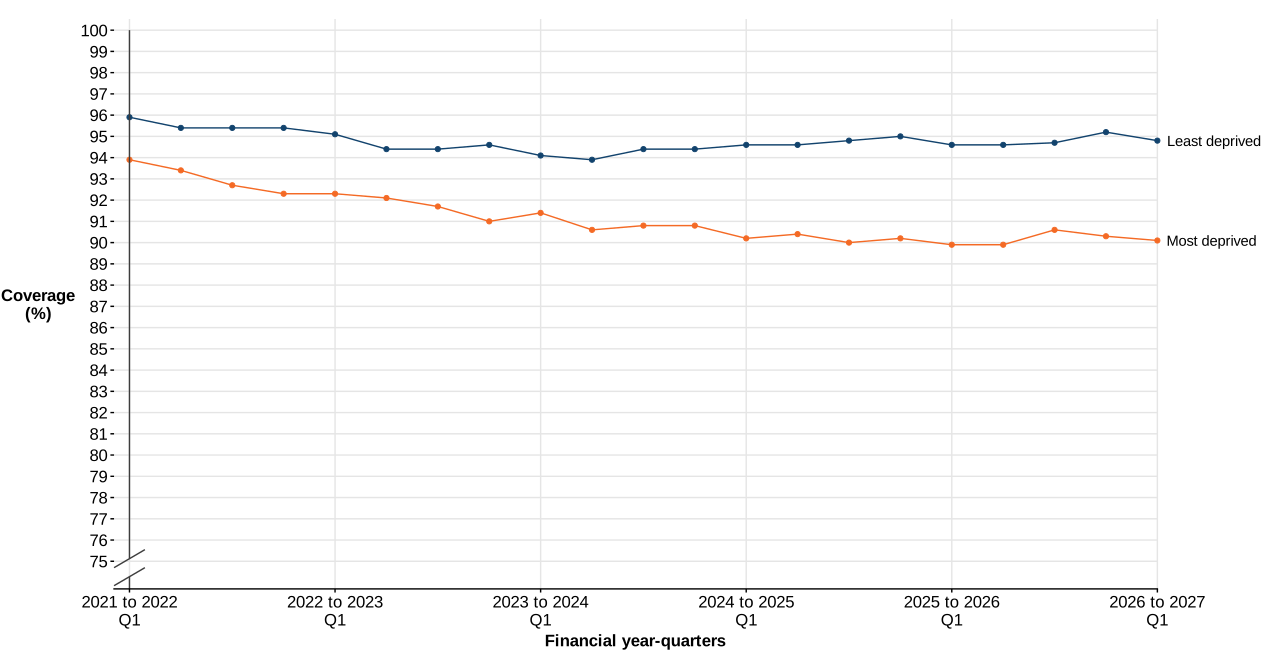
Similarly, coverage of the 6-in-1 vaccine in the 30 least deprived UTLAs decreased by 0.4 percentage points to 94.8% while it decreased by 0.2 percentage points to 90.1% in the 30 most deprived UTLAs (Figure 9b).
Figure 9b. Coverage of the primary course of the 6-in-1 vaccine in the 30 most and least deprived local authorities in England, measured at 5 years
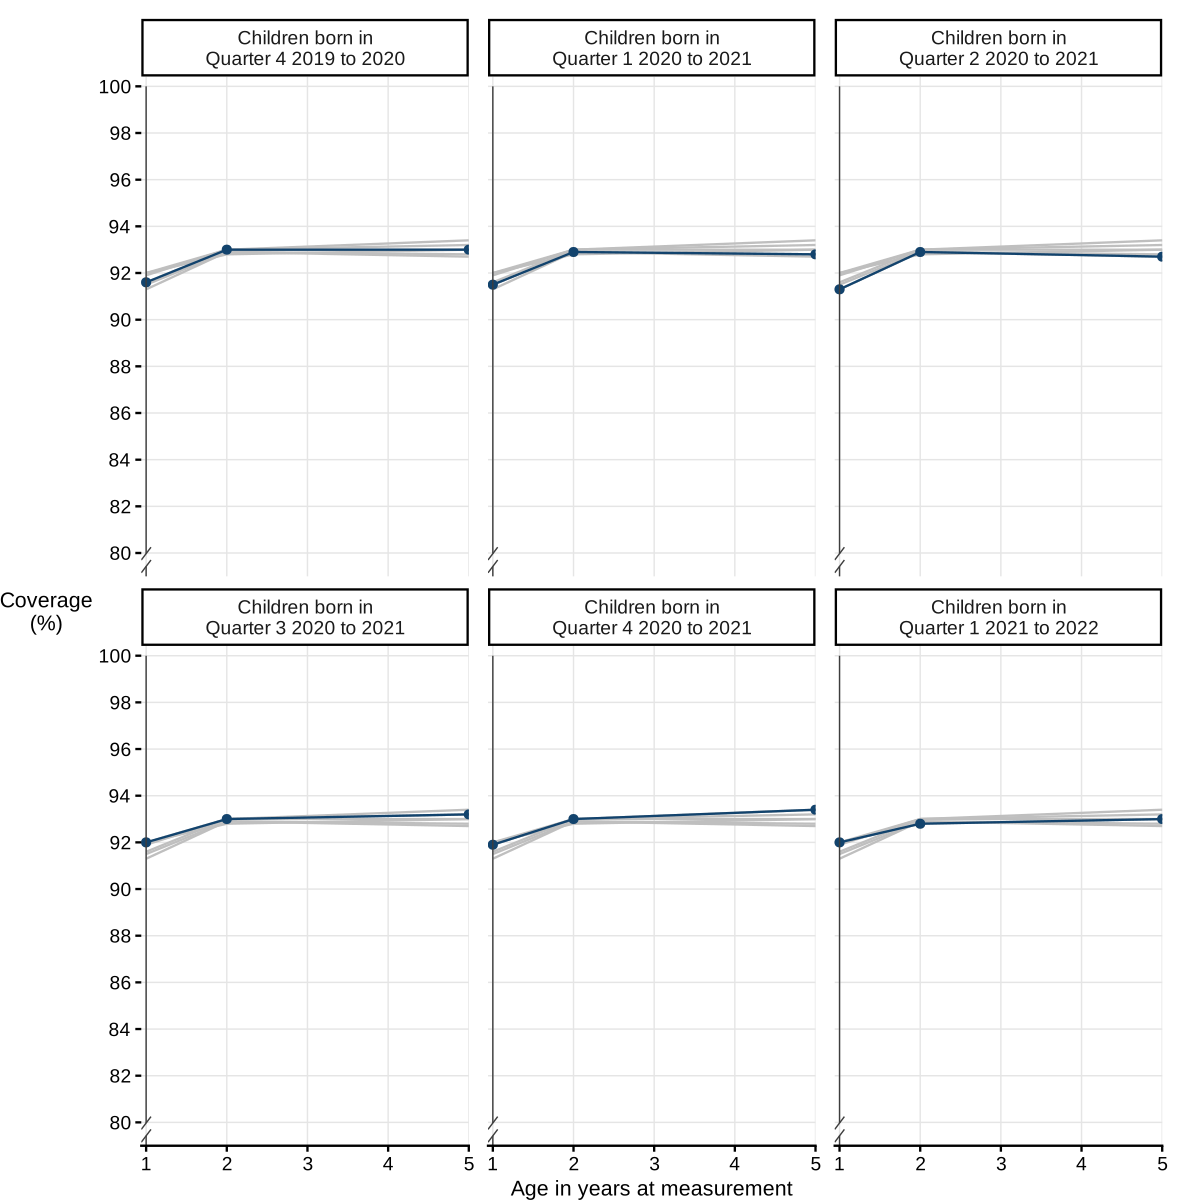
Children aged 5 years in this quarter were born in quarter 1 2021 to 2022. Aged 12 months, coverage for the 6-in-1 was 92.0%. By 24 months it was 92.8%, and this quarter at 5 years it is 93.0% (Figure 10). As a note, birth cohorts over time do not necessarily include the same children due to population movement.
Figure 10. Coverage of the 6-in-1 vaccine across England measured in children aged 5 years when they were aged 12 months, 24 months, and 5 years
Neonatal hepatitis B vaccine coverage: England
National coverage at 12 months for 5 doses of a HepB-containing vaccine increased by 0.6 percentage points to 94.0% compared with the previous quarter (as seen in the previous quarterly report). Coverage of 6 doses of a HepB-containing vaccine reported for children who reached 2 years of age in the quarter (those born April to June 2024) decreased by 1.0 percentage point to 88.6% compared with the last quarter (89.6%) (see the data tables accompanying this report).
The quality of neonatal HepB vaccine data is variable and coverage by regions can be based on small numbers. As such, comparisons of percentages should be considered alongside denominators. Where an area reported no vaccinated children, a check was made to ensure that this was zero reporting rather than absence of available data.
Neonatal BCG vaccine coverage: England
The data captures BCG coverage at age 3 months for children born January to March 2026 and at age 12 months for children born April to June 2025; it was provided for all local authorities in England and is published in the data tables accompanying this report. Measured at 3 months, coverage in England was 77.1% and measured at 12 months, it was 84.4%.
Data sources and methodology
Please see the quality and methodology information report for more information on all the reports.
Data was received from all health boards in Wales, Scotland and Northern Ireland. In England, local teams and Child Health Record Departments provided data for all UTLAs and the associated general practices.
In this report and the accompanying data set, Hackney is included in the City of London and the Isles of Scilly is included in Cornwall. For selective programmes, Rutland is included in Leicestershire. Cumbria is now reported as Cumberland and Westmorland and Furness.
Coverage statistics should be considered in light of the uncertainty in the numbers of children recorded in child health information systems nationally. This uncertainty is linked to population movement and is therefore likely to have greater impact in urbanised areas with higher levels of population turnover such as London. Coverage may be underestimated in these areas and reported falls in coverage over time should be interpreted with caution due to the relationship with underlying trends in population movement. Consequently, in 14 UTLAs in London, children not registered with a GP are excluded from the data set. The 14 UTLAs affected are: Greenwich, Hammersmith and Fulham, Kensington and Chelsea, Lambeth, Lewisham, Southwark, Westminster, Bexley, Brent, Bromley, Ealing, Harrow, Hillingdon, and Hounslow. Work is underway to better understand the scale and impact of population errors on reported coverage to ensure they are consistent and comparable over time and between regions.
All English data was collected through NHS Digital’s Strategic Data Collection Service. Individual local authority and GP data, including numerators, denominators, coverage and relevant caveats where applicable, is available in the data tables associated with this report. GP-level data was censored when individual values were less than 5.
These statistics are subject to both scheduled revisions and unscheduled corrections and are therefore marked as provisional. In addition to correction of any errors made during the production of these statistics, unscheduled corrections also include the correction of errors later identified within the source data received by UKHSA. Revisions and corrections are made timely and transparently in line with UKHSA’s published Revisions and corrections policy.
Supplementary statistics are published separately from the COVER collection to provide more timely, provisional estimates to support staff delivering the childhood immunisation programme. The provisional estimates differ from the official figures published in this report, because they use different data sources and methodologies. The provisional estimates are based on GP data, meaning unregistered individuals are not included so figures do not capture the entire eligible population. COVER reports remain the official source for childhood vaccination coverage data.
Background information
This publication is released on a quarterly basis and aligns with financial quarters. The analysis follows this pattern; any discussion of quarters aligns with the financial year whereby quarter 1 starts in April.
Children who reached their first birthday in this quarter would have been scheduled to receive their primary course (third dose) of the combined diphtheria, tetanus, acellular pertussis vaccine, inactivated poliomyelitis vaccine, haemophilus influenzae type b vaccine and hepatitis B vaccine (DTaP/IPV/Hib/HepB3 or 6-in-1 vaccination) which protects against diphtheria, tetanus, pertussis (whooping cough), polio, haemophilus influenzae type b (Hib) and hepatitis B, and a single dose of PCV (protecting against pneumococcal disease) at the age of 16 weeks, August 2025 to October 2025. They would have also been scheduled to receive their primary course (second dose) of MenB vaccine which protects against meningococcal group B disease and 2 doses of rotavirus vaccine at age 12 weeks, July 2025 to September 2025.
Except for the rotavirus vaccine, which is only offered up to 6 months of age, all other vaccines are available to children in the current cohort at any time and would have been captured in this report if given by their first birthday. Children born to hepatitis B surface antigen (HBsAg) positive mothers who reached their first birthday in this quarter should also have received monovalent hepatitis B vaccine at birth and at 4 weeks of age.
Children who reached their second birthday would have been scheduled to receive their primary course (third dose) of the 6-in-1 vaccination August 2024 to October 2024, and their first MMR vaccination, a Hib/MenC booster (protecting against haemophilus influenzae type b and meningococcal group C disease), MenB booster and PCV booster at one year of age April 2025 to June 2025. Children born to HBsAg positive mothers, who reached their second birthday in this quarter (born April to June 2024), were scheduled to receive a third dose monovalent hepatitis B vaccine at one year of age.
Children who reached their fifth birthday would have been scheduled to receive their primary course (third dose) of the 6-in-1 vaccination August 2021 to October 2021, their first MMR and the Hib/MenC booster April 2022 to June 2022, their pre-school diphtheria, tetanus, acellular pertussis and polio (dTaP/IPV) booster, and second-dose MMR from August 2024 to October 2024.
Coverage of the Hib/MenC booster at 24 months and 5 years is no longer reported due to changes to the routine childhood schedule as of 1 July 2025.
Children born in areas where the TB incidence is greater than or equal to 40 per 100,000 or who are born to parents or grandparents from TB endemic areas were eligible for a BCG vaccination at 28 days. Coverage is measured at 3 months of age and 12 months of age for this selective immunisation.
In July 2025 and January 2026, the routine childhood schedule changed. The full routine immunisation schedule sets out the schedule for all childhood immunisations.
Related statistics
Further information and contact details
The submission and publication dates for this report series are available as are additional information for immunisation practitioners and other health professionals. For any questions or comments regarding this report, please email cover@ukhsa.gov.uk.
Official statistics
Our statistical practice is regulated by the Office for Statistics Regulation (OSR). OSR sets the standards of trustworthiness, quality and value in the Code of Practice for Statistics that all producers of official statistics should adhere to. You can contact OSR by emailing regulation@statistics.gov.uk or via the OSR website.
UKHSA is committed to ensuring that these statistics comply with the Code of Practice for Statistics. This means users can have confidence in the people who produce UKHSA statistics because our statistics are robust, reliable and accurate. Our statistics are regularly reviewed to ensure they support the needs of society for information.
UKHSA has conducted a formal review of these statistics. Following this review, an implementation plan has been developed to continue to improve the trustworthiness, quality, and value of these statistics. Key continuous improvements made will be highlighted within future releases of these statistics for transparency.