Sexually transmitted infections quarterly report, England: provisional data, September 2026
Updated 16 September 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/sti-quarterly-surveillance-reports-provisional-data/sexually-transmitted-infections-quarterly-report-england-provisional-data-september-2026
Interpretation notes are available for the data on diagnoses of syphilis and gonorrhoea data in England.
Diagnoses of syphilis and gonorrhoea by gender identity and sexual orientation from January 2019 to March 2026
Main points
Diagnoses of infectious syphilis (primary, secondary and early latent stages) at sexual health services (SHSs) in England decreased in quarter 1 (January to March) 2026 to 1,721 (982 in gay, bisexual and other men who have sex with men [GBMSM] and 739 in other groups), down from 1,975 (1,159 in GBMSM and 816 in other groups) in the previous quarter. There has been an overall decrease in infectious syphilis diagnoses among GBMSM since quarter 3 2024 and a relatively stable trend in other groups over the same period (Figure 1a).
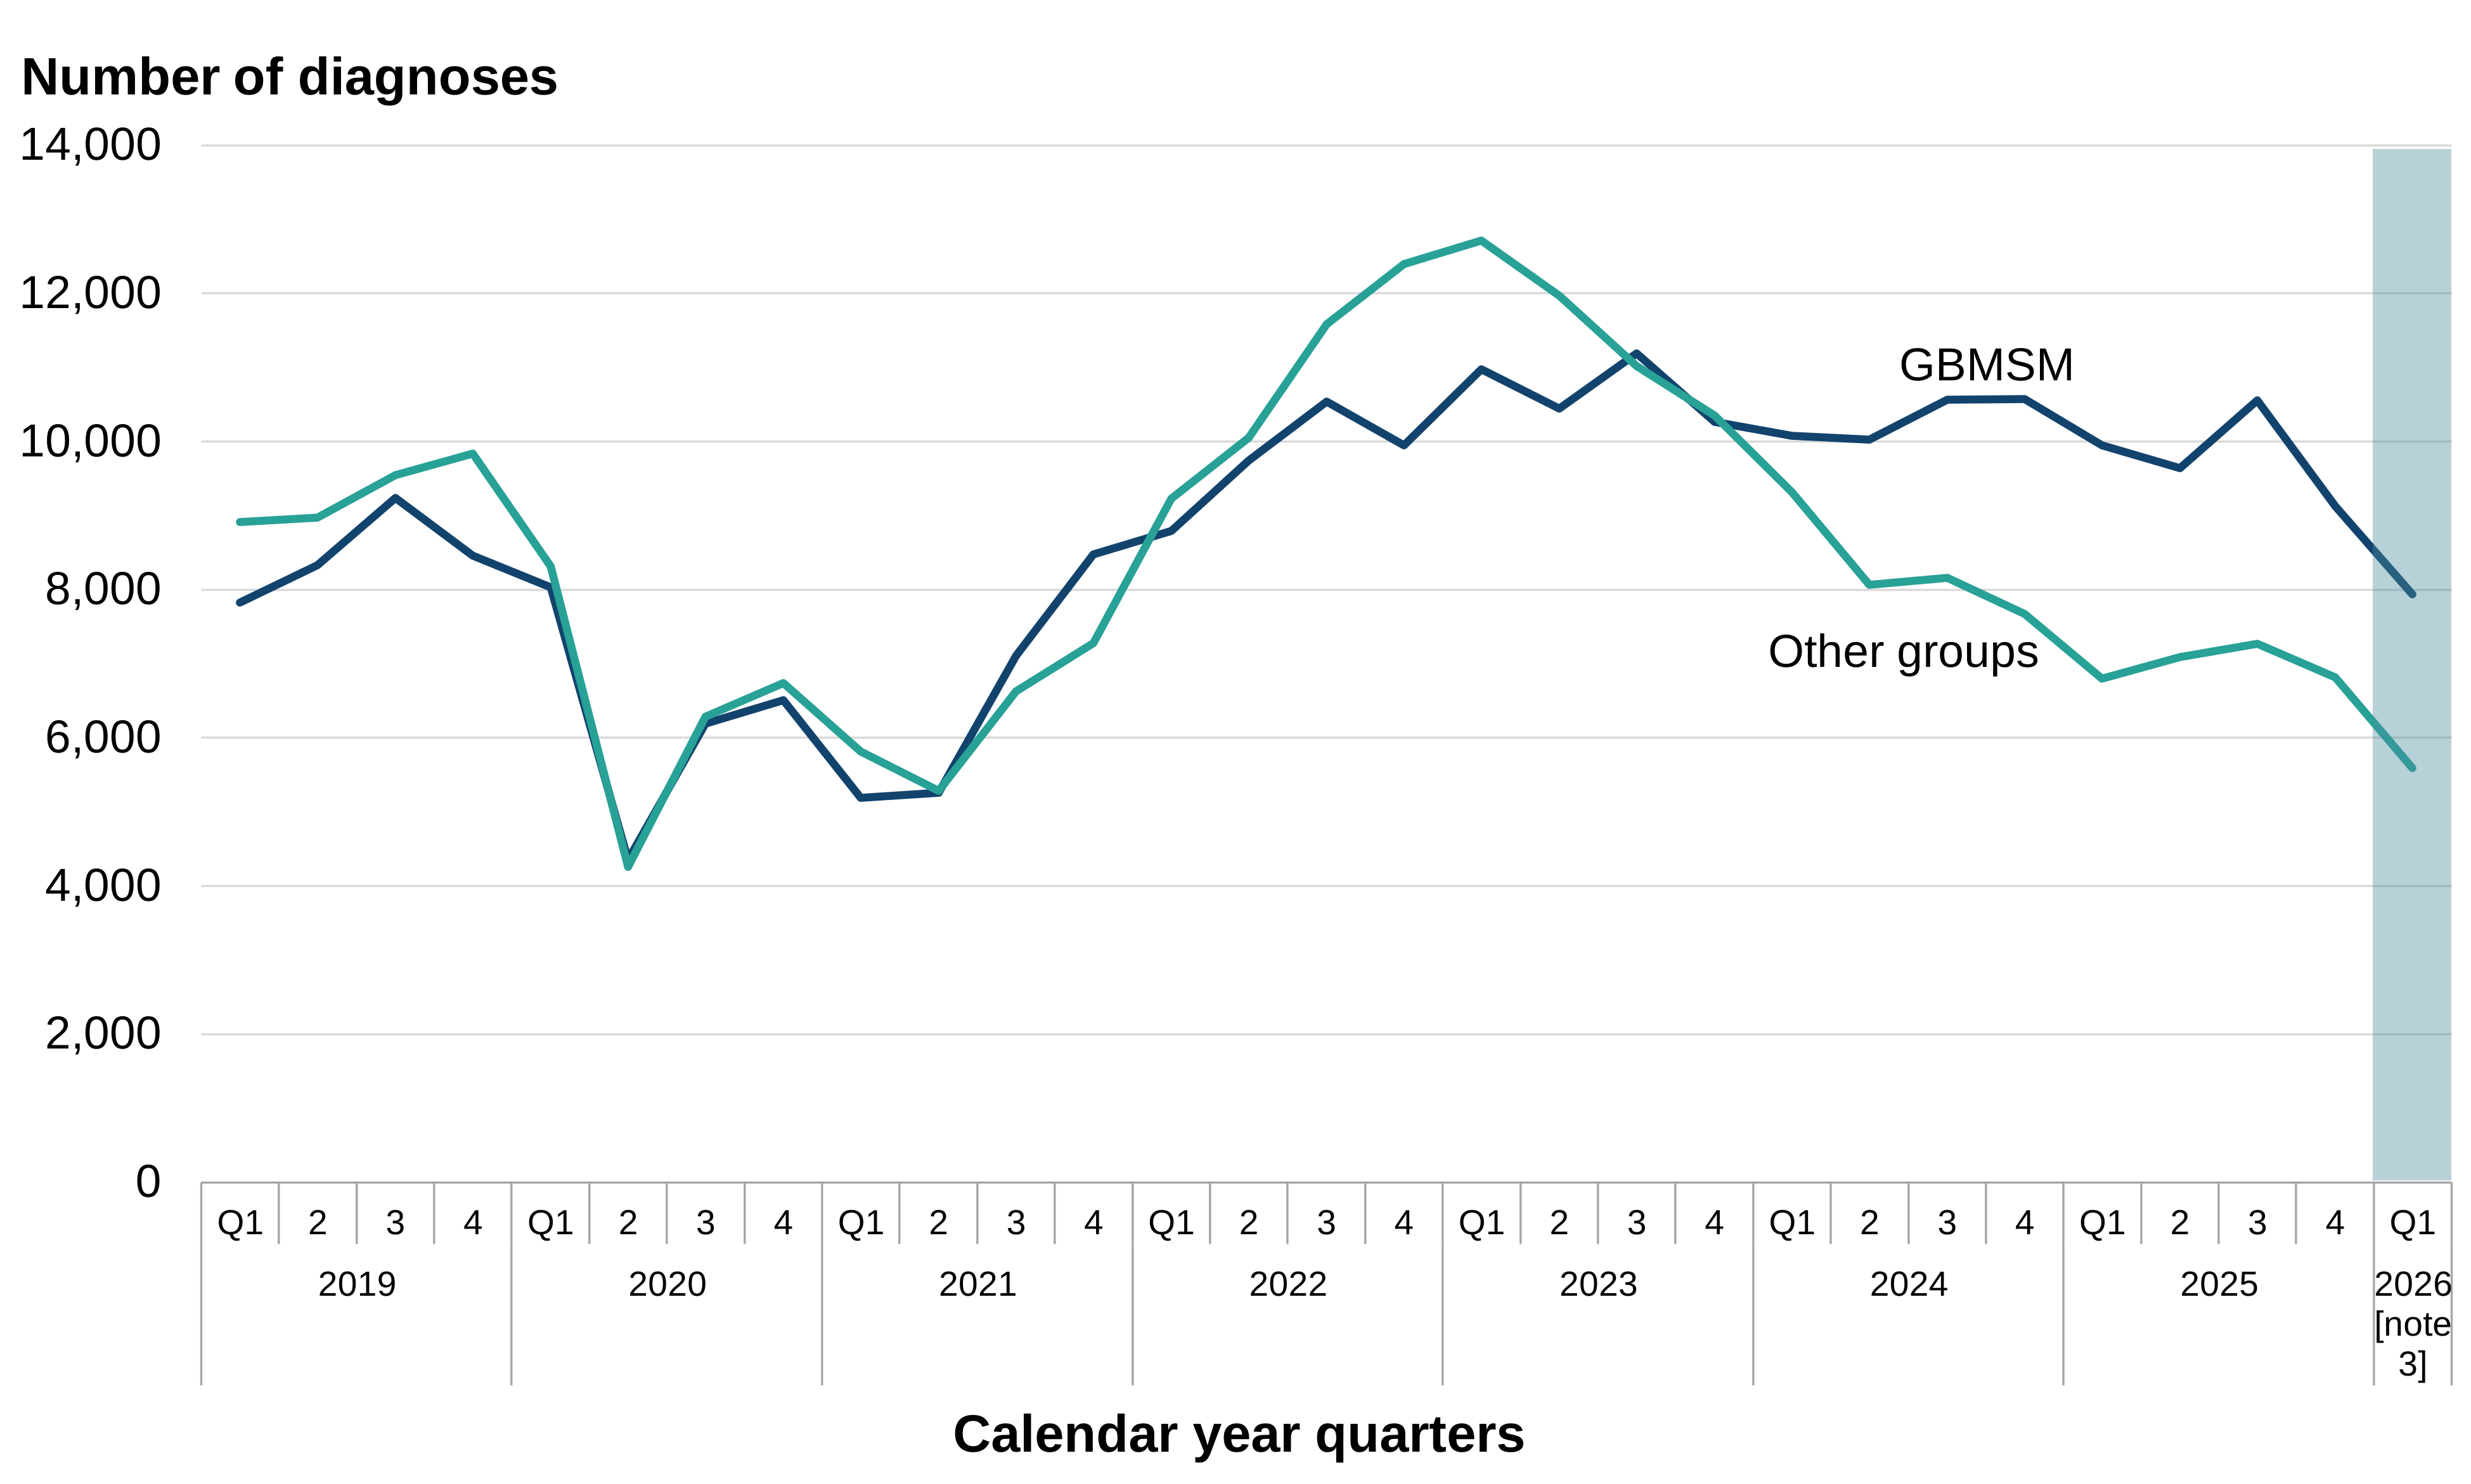
There were 13,529 diagnoses of gonorrhoea (7,938 in GBMSM and 5,591 in other groups) at SHSs in England in quarter 1 (January to March) 2026, lower than 15,942 (9,129 in GBMSM and 6,813 in other groups) in the previous quarter. The decrease in GBMSM is a continuation of the preceding downward trajectory since quarter 3 (July to September) 2025, while gonorrhoea diagnoses in other groups have been decreasing since early 2023 (Figure 1b).
Between January and March 2026, there were 14,247 reported consultations at SHSs in England by people prescribed doxycycline post-exposure prophylaxis (doxyPEP) (Figure 2a).
Between January 2026 and March 2026, provision of 11,943 first doses and 11,129 second doses of 4-component serogroup B meningococcal (4CMenB) vaccine for gonorrhoea prevention were reported by SHSs in England (Figure 2b).
Background information
There has been an overall increasing trend in infectious syphilis and gonorrhoea diagnoses since the early 2000s. A marked but temporary decline in diagnoses of both infections was seen during 2020 and 2021, largely explained by a fall in testing during disruption to SHSs caused by the COVID-19 pandemic.
The number of STI diagnoses has been stratified into GBMSM and other groups to follow trends that may be related to targeted preventative interventions (such as doxyPEP and 4CMenB vaccine, both of which were introduced nationally in summer 2025) and allow interpretation of overall long-term trends in light of these changes. More information about the UK Health Security Agency (UKHSA)’s planned analyses to assess the impact of doxyPEP and 4CMenB on STIs is published on GOV.UK.
Figures 1a and 1b show data on diagnoses of infectious syphilis and gonorrhoea by gender identity and sexual orientation in England by quarter.
These provisional quarterly figures will likely be an undercount but can be used to monitor indicative trends in the data in a timely way. The annual STI official statistics will be published around 6 months after the end of the data collection year with more complete figures and additional breakdowns.
Also see the Sexual and reproductive health in England: local and national data guide for other presentations of STI data.
Figure 1a. Diagnoses of infectious syphilis [note 1] by gender identity and sexual orientation [note 2] in England by quarter, January 2019 to March 2026
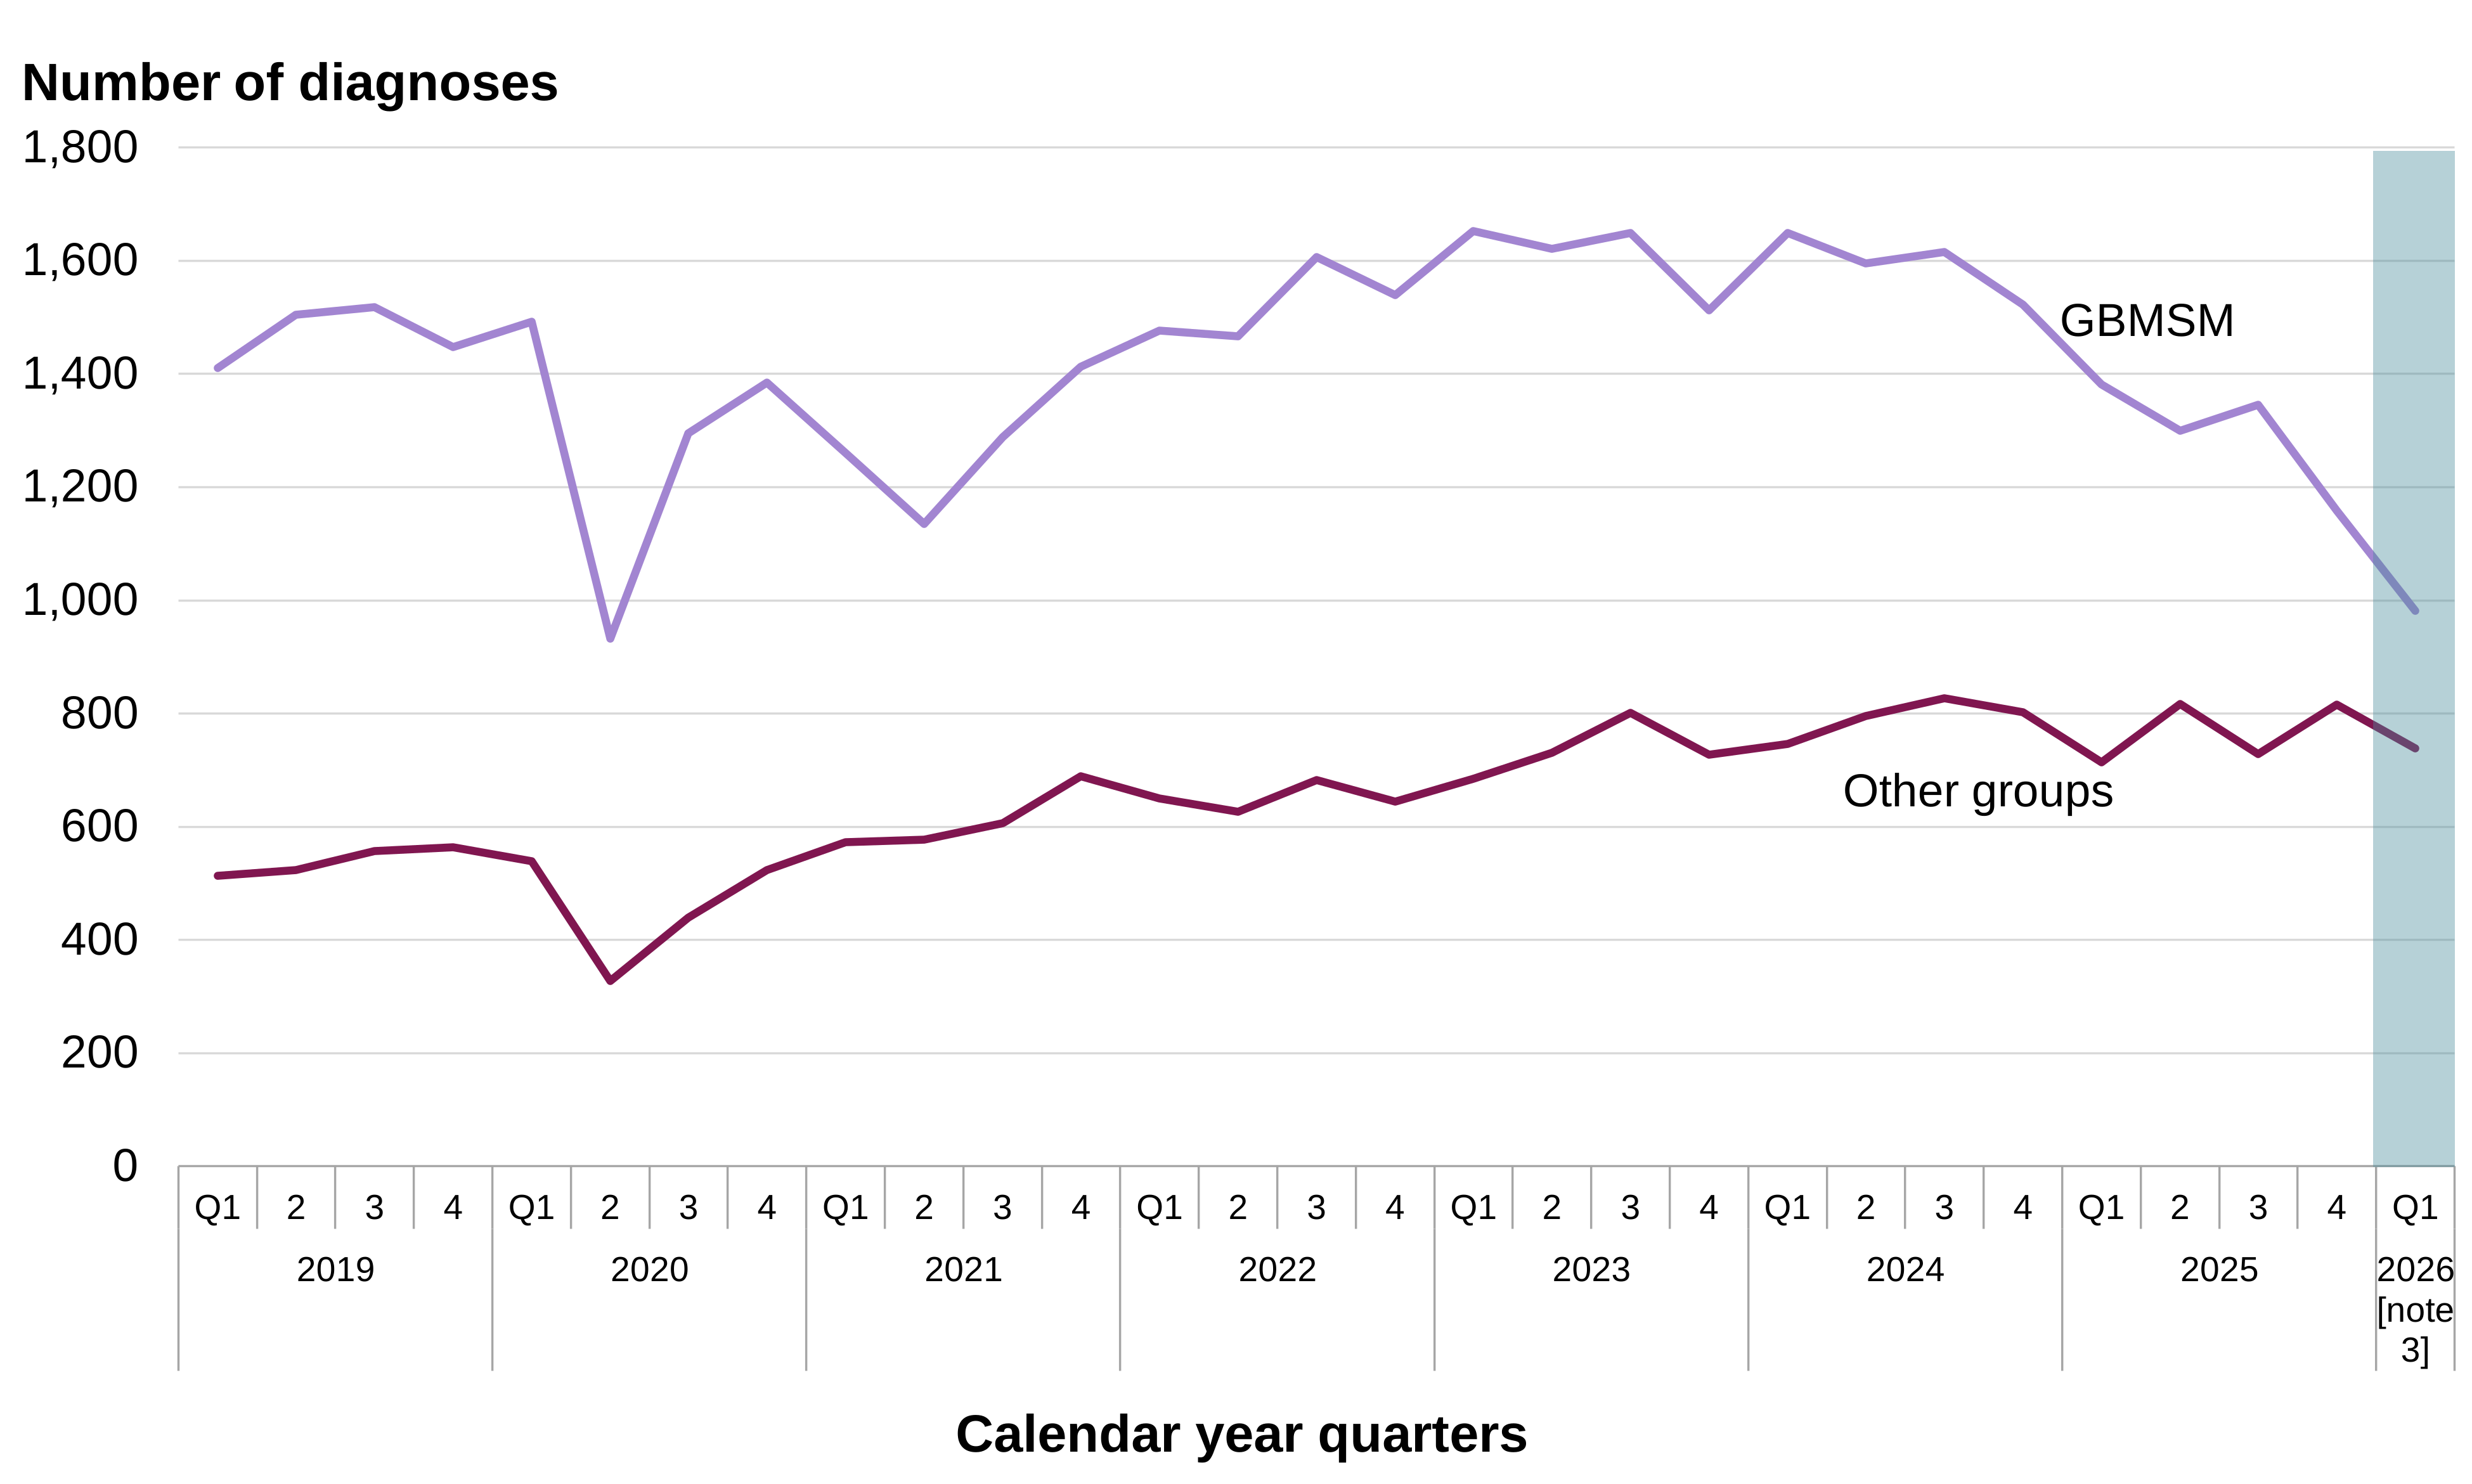
Figure 1b. Diagnoses of gonorrhoea by gender identity and sexual orientation [note 2] in England by quarter, January 2019 to March 2026
Source: data from routine returns to the GUMCAD STI Surveillance System.
Note 1: infectious syphilis refers to primary, secondary and early latent stages.
Note 2: the category ‘Other groups’ is comprised of heterosexual men and women, lesbians, and people where information about their gender identity or sexual orientation was not reported.
Note 3: data for the most recent quarter, shown in the shaded part of the graph, is likely to increase as delayed data submissions are received.
Trends in doxyPEP use and 4CMenB vaccine doses in SHS attendees
The national provision of doxyPEP and 4CMenB vaccine began in quarter 3 (July to September) 2025. Both interventions are provided by SHSs offering face-to-face consultations (reporting GUMCAD data to UKHSA). The figures published here present the earliest available data and will be under-reported during the initial period while the interventions are fully implemented and reported through routine GUMCAD submissions.
DoxyPEP figures for quarter 1 (January to March) 2026 include data from 135 of 219 (62%) of face-to-face SHSs. These services reported doxyPEP use at 14,247 consultations (Figure 2a). Table 1a shows the number and percentage of face-to-face SHSs reporting doxyPEP.
4CMenB vaccine figures for quarter 1 (January to March) 2026 include data from 171 of 219 (78%) face-to-face SHSs. These services reported provision of 11,943 first doses and 11,129 second doses of 4CMenB vaccine for gonorrhoea prevention in England (Figure 2b). Table 1b shows the number and percentage of face-to-face SHSs reporting 4CMenB vaccine doses.
See Table 2 for details of the completeness of GUMCAD data, submitted by online and face-to-face SHSs for 2026.
Figure 2a reports use of doxyPEP and Figure 2b reports doses of 4CMenB vaccine given in each quarter of the calendar year.
Figure 2a. Number of consultations recording doxyPEP use [note 4] at SHSs reporting these data [note 5] in England, July 2025 to March 2026
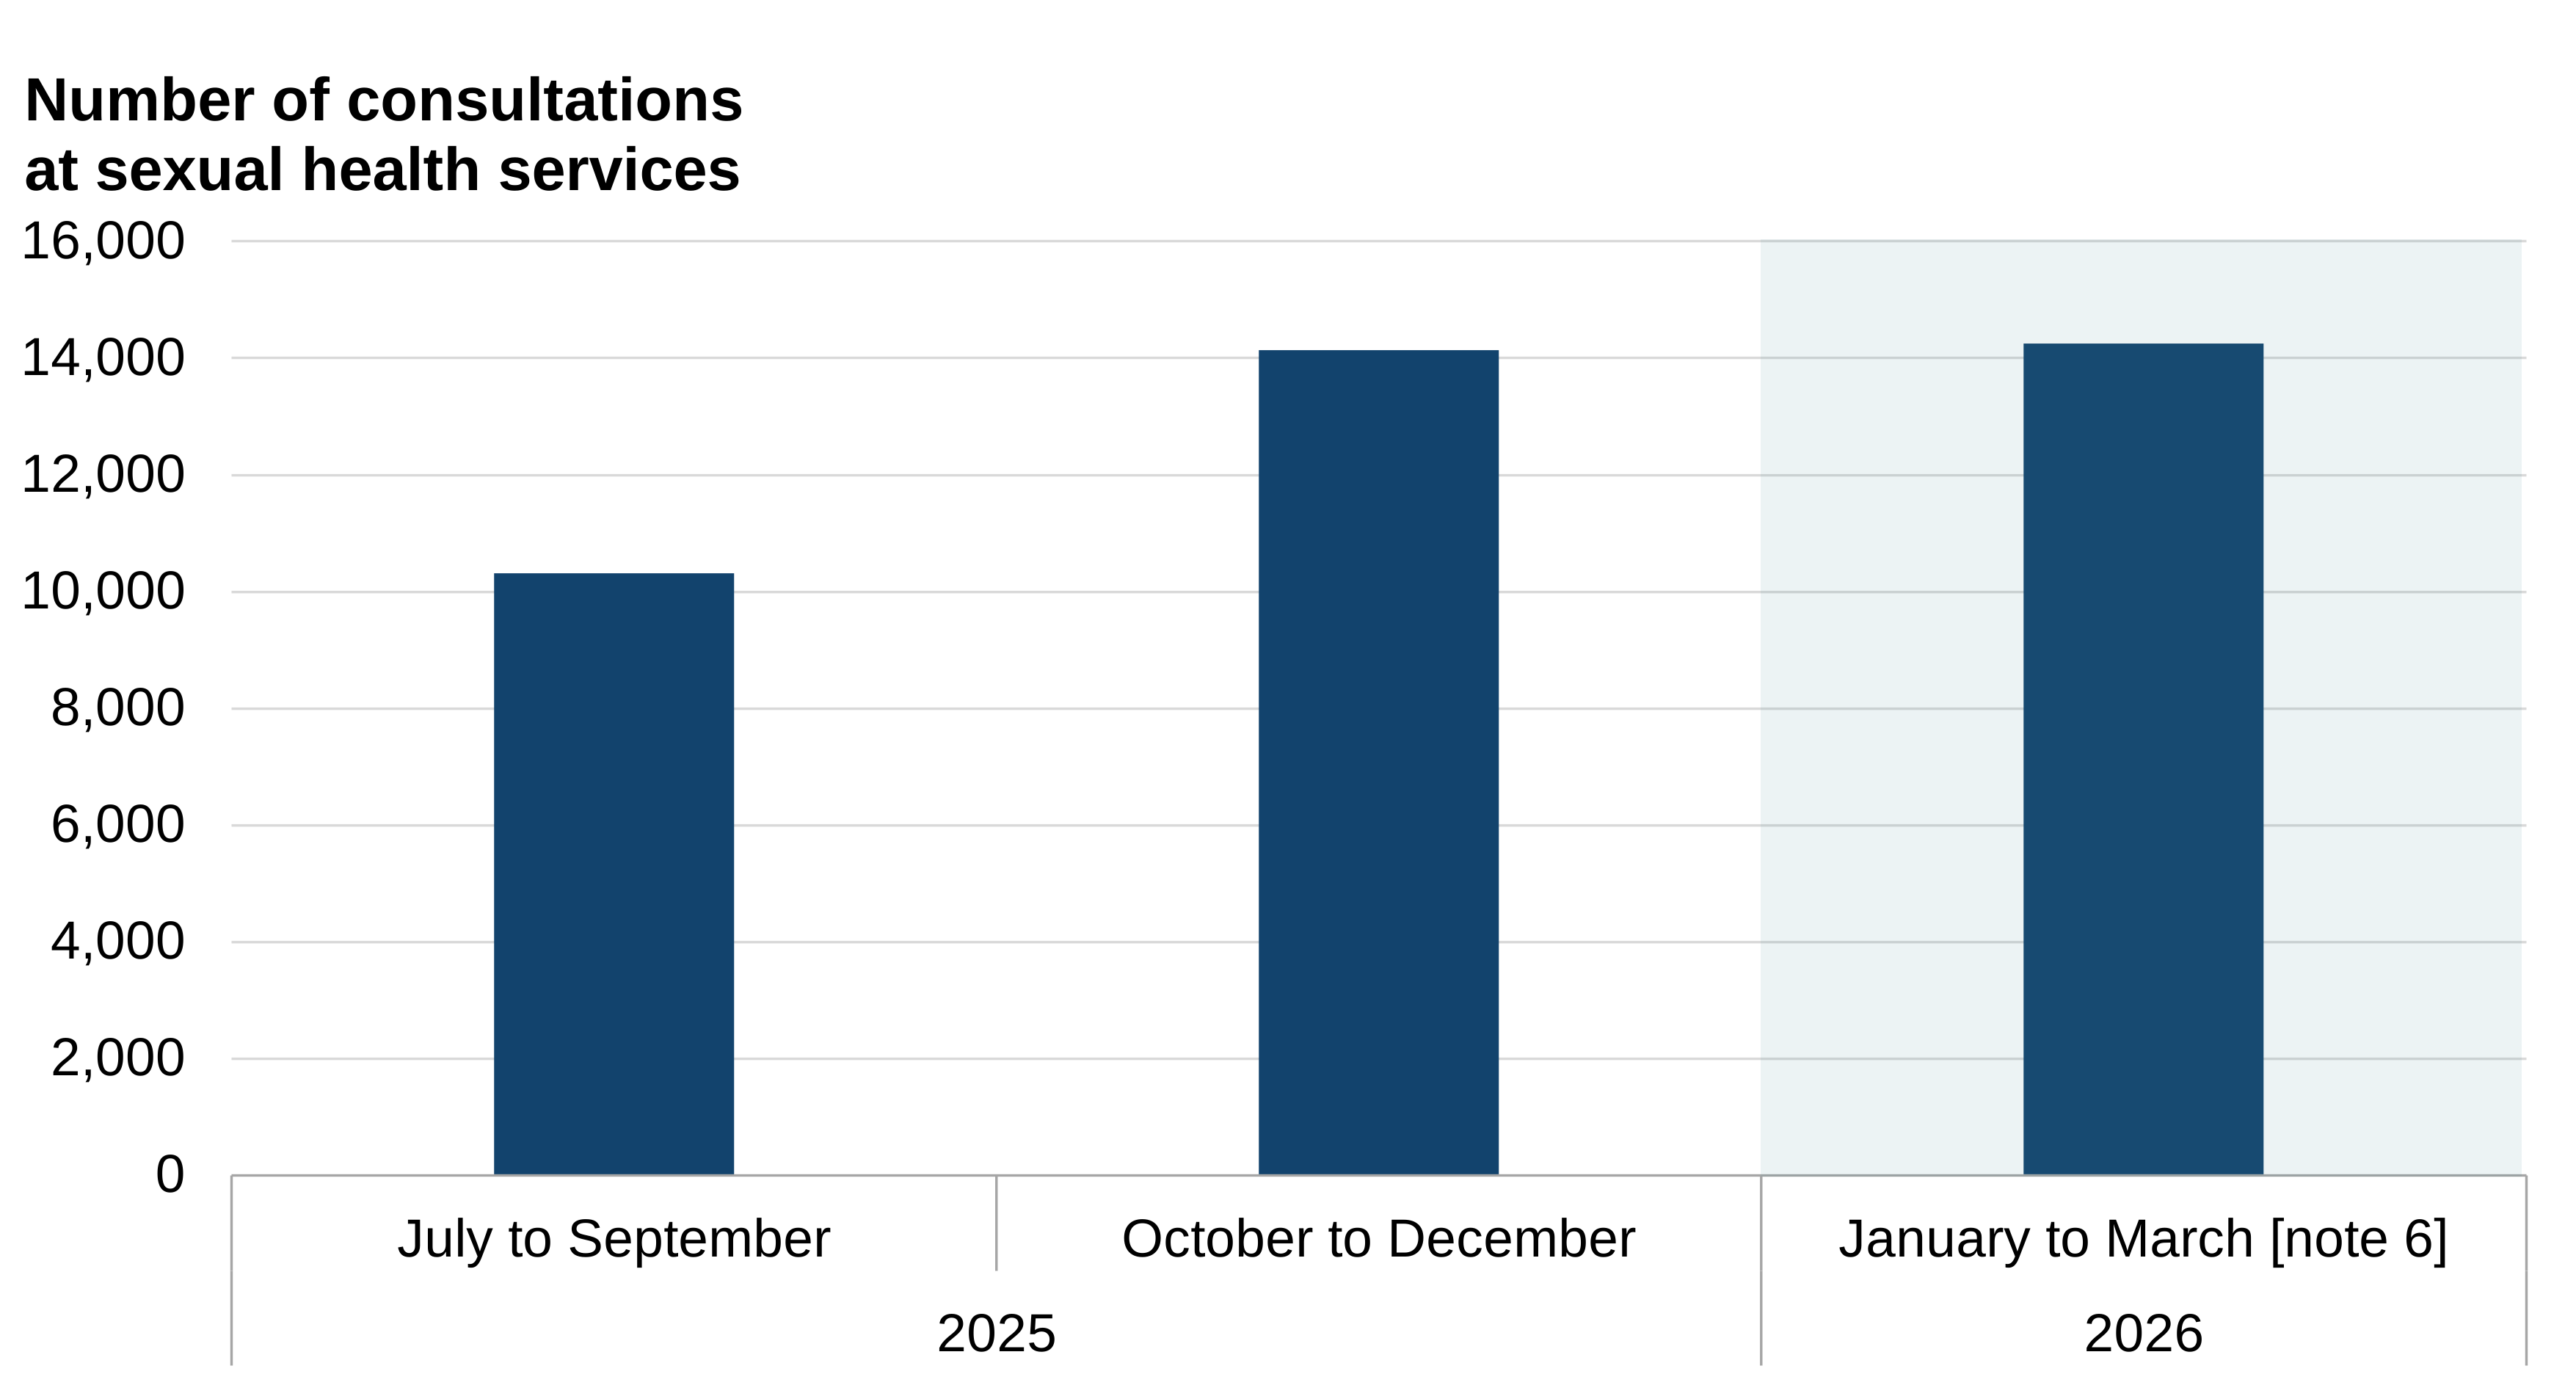
Table 1a. Number and percentage of face-to-face SHSs reporting doxyPEP
| July to September 2025 | October to December 2025 | January to March 2026 | |
|---|---|---|---|
| SHSs | 99 out of 221 (45%) | 129 out of 218 (59%) | 135 out of 219 (62%) |
Figure 2b. Number of doses of 4CMenB vaccine for gonorrhoea prevention provided by SHSs reporting these data [note 5] in England, July 2025 to March 2026
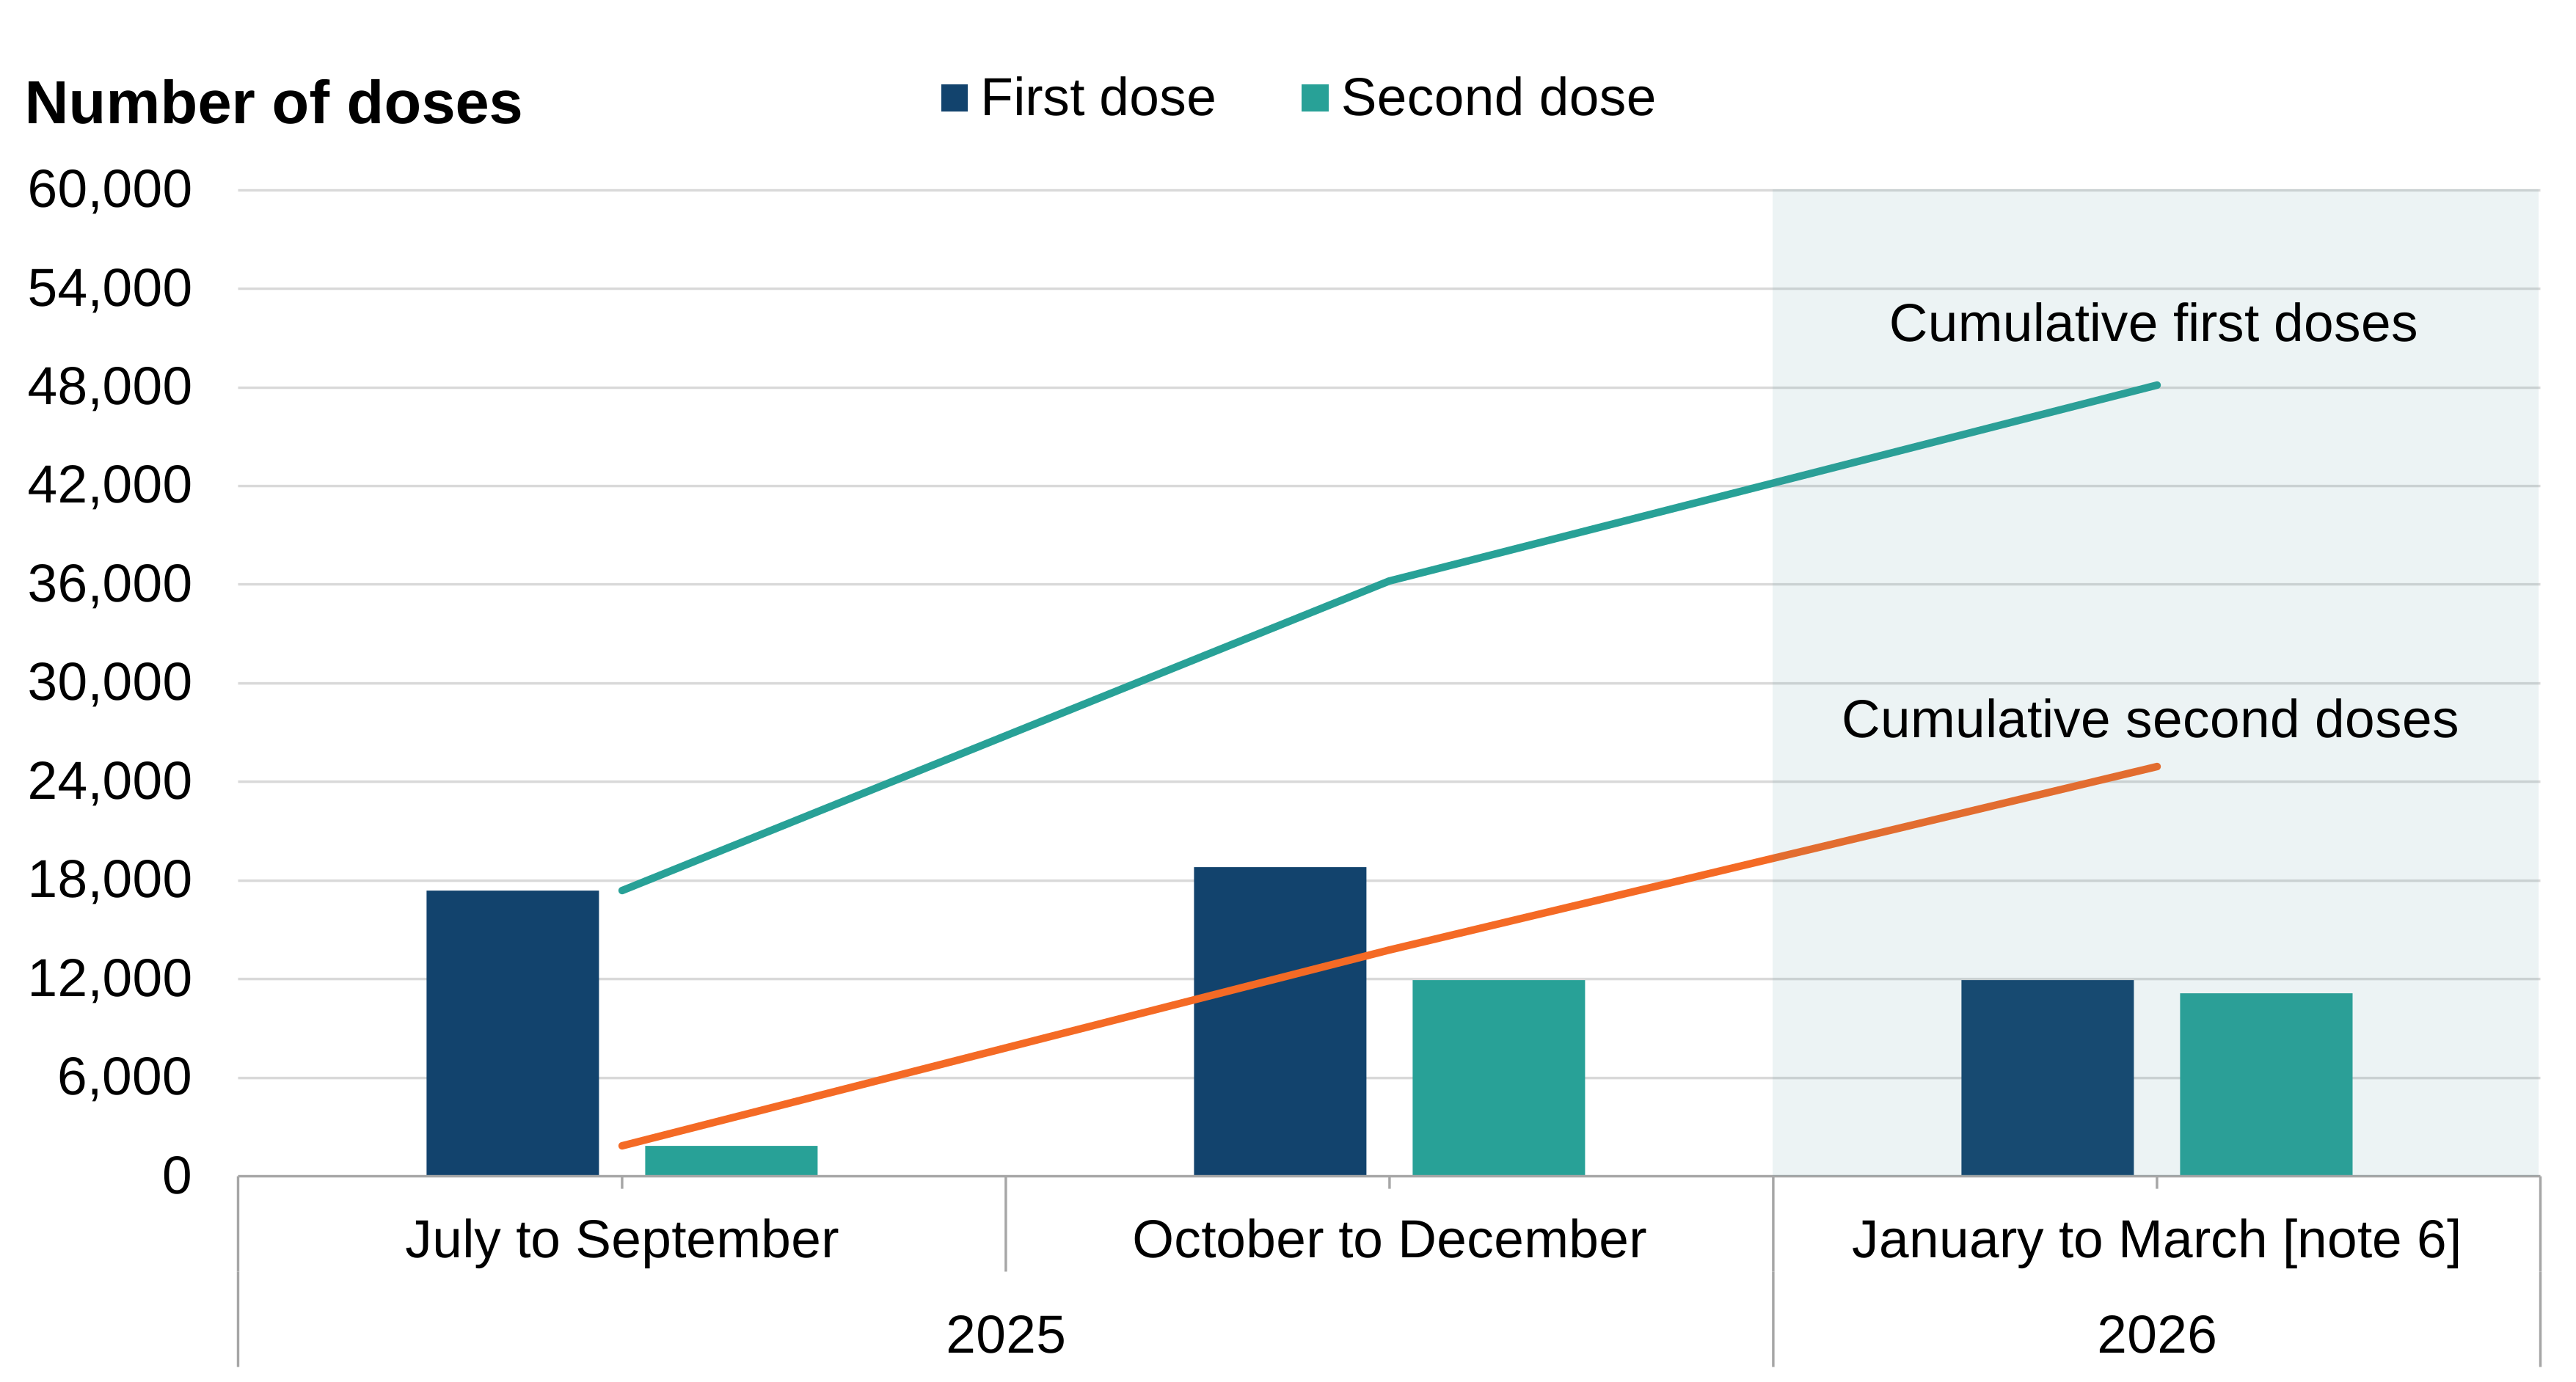
Table 1b. Number and percentage of face-to-face SHSs reporting 4CMenB vaccine doses
| July to September 2025 | October to December 2025 | January to March 2026 | |
|---|---|---|---|
| SHSs | 162 out of 221 (73%) | 182 out of 219 (83%) | 171 out of 219 (78%) |
Source: data from routine returns to the GUMCAD STI Surveillance System.
Note 4: figures include doxyPEP provided at any local authority-commissioned SHS or privately obtained.
Note 5: all SHSs are not yet reporting surveillance codes to indicate provision of doxyPEP and 4CMenB as of March 2026. Adoption and complete reporting of these new surveillance codes in GUMCAD will improve over time.
Note 6: data for the most recent quarter, shown in the shaded part of the graph, is likely to increase as delayed submissions are received.
Details on GUMCAD submission completeness are available in Table 2.
Table 2. GUMCAD submission completeness in England, 2026
| GUMCAD submissions | Quarter 1 (January to March) |
Quarter 2 (April to June) |
Quarter 3 (July to September) |
Quarter 4 (October to December) |
|---|---|---|---|---|
| Required | 225 | Not applicable | Not applicable |
Not applicable |
| Received | 205 | Not applicable | Not applicable |
Not applicable |
| Completeness | 91% | Not applicable | Not applicable |
Not applicable |
All diagnoses of ceftriaxone-resistant Neisseria gonorrhoeae to 31 August 2026
Main points
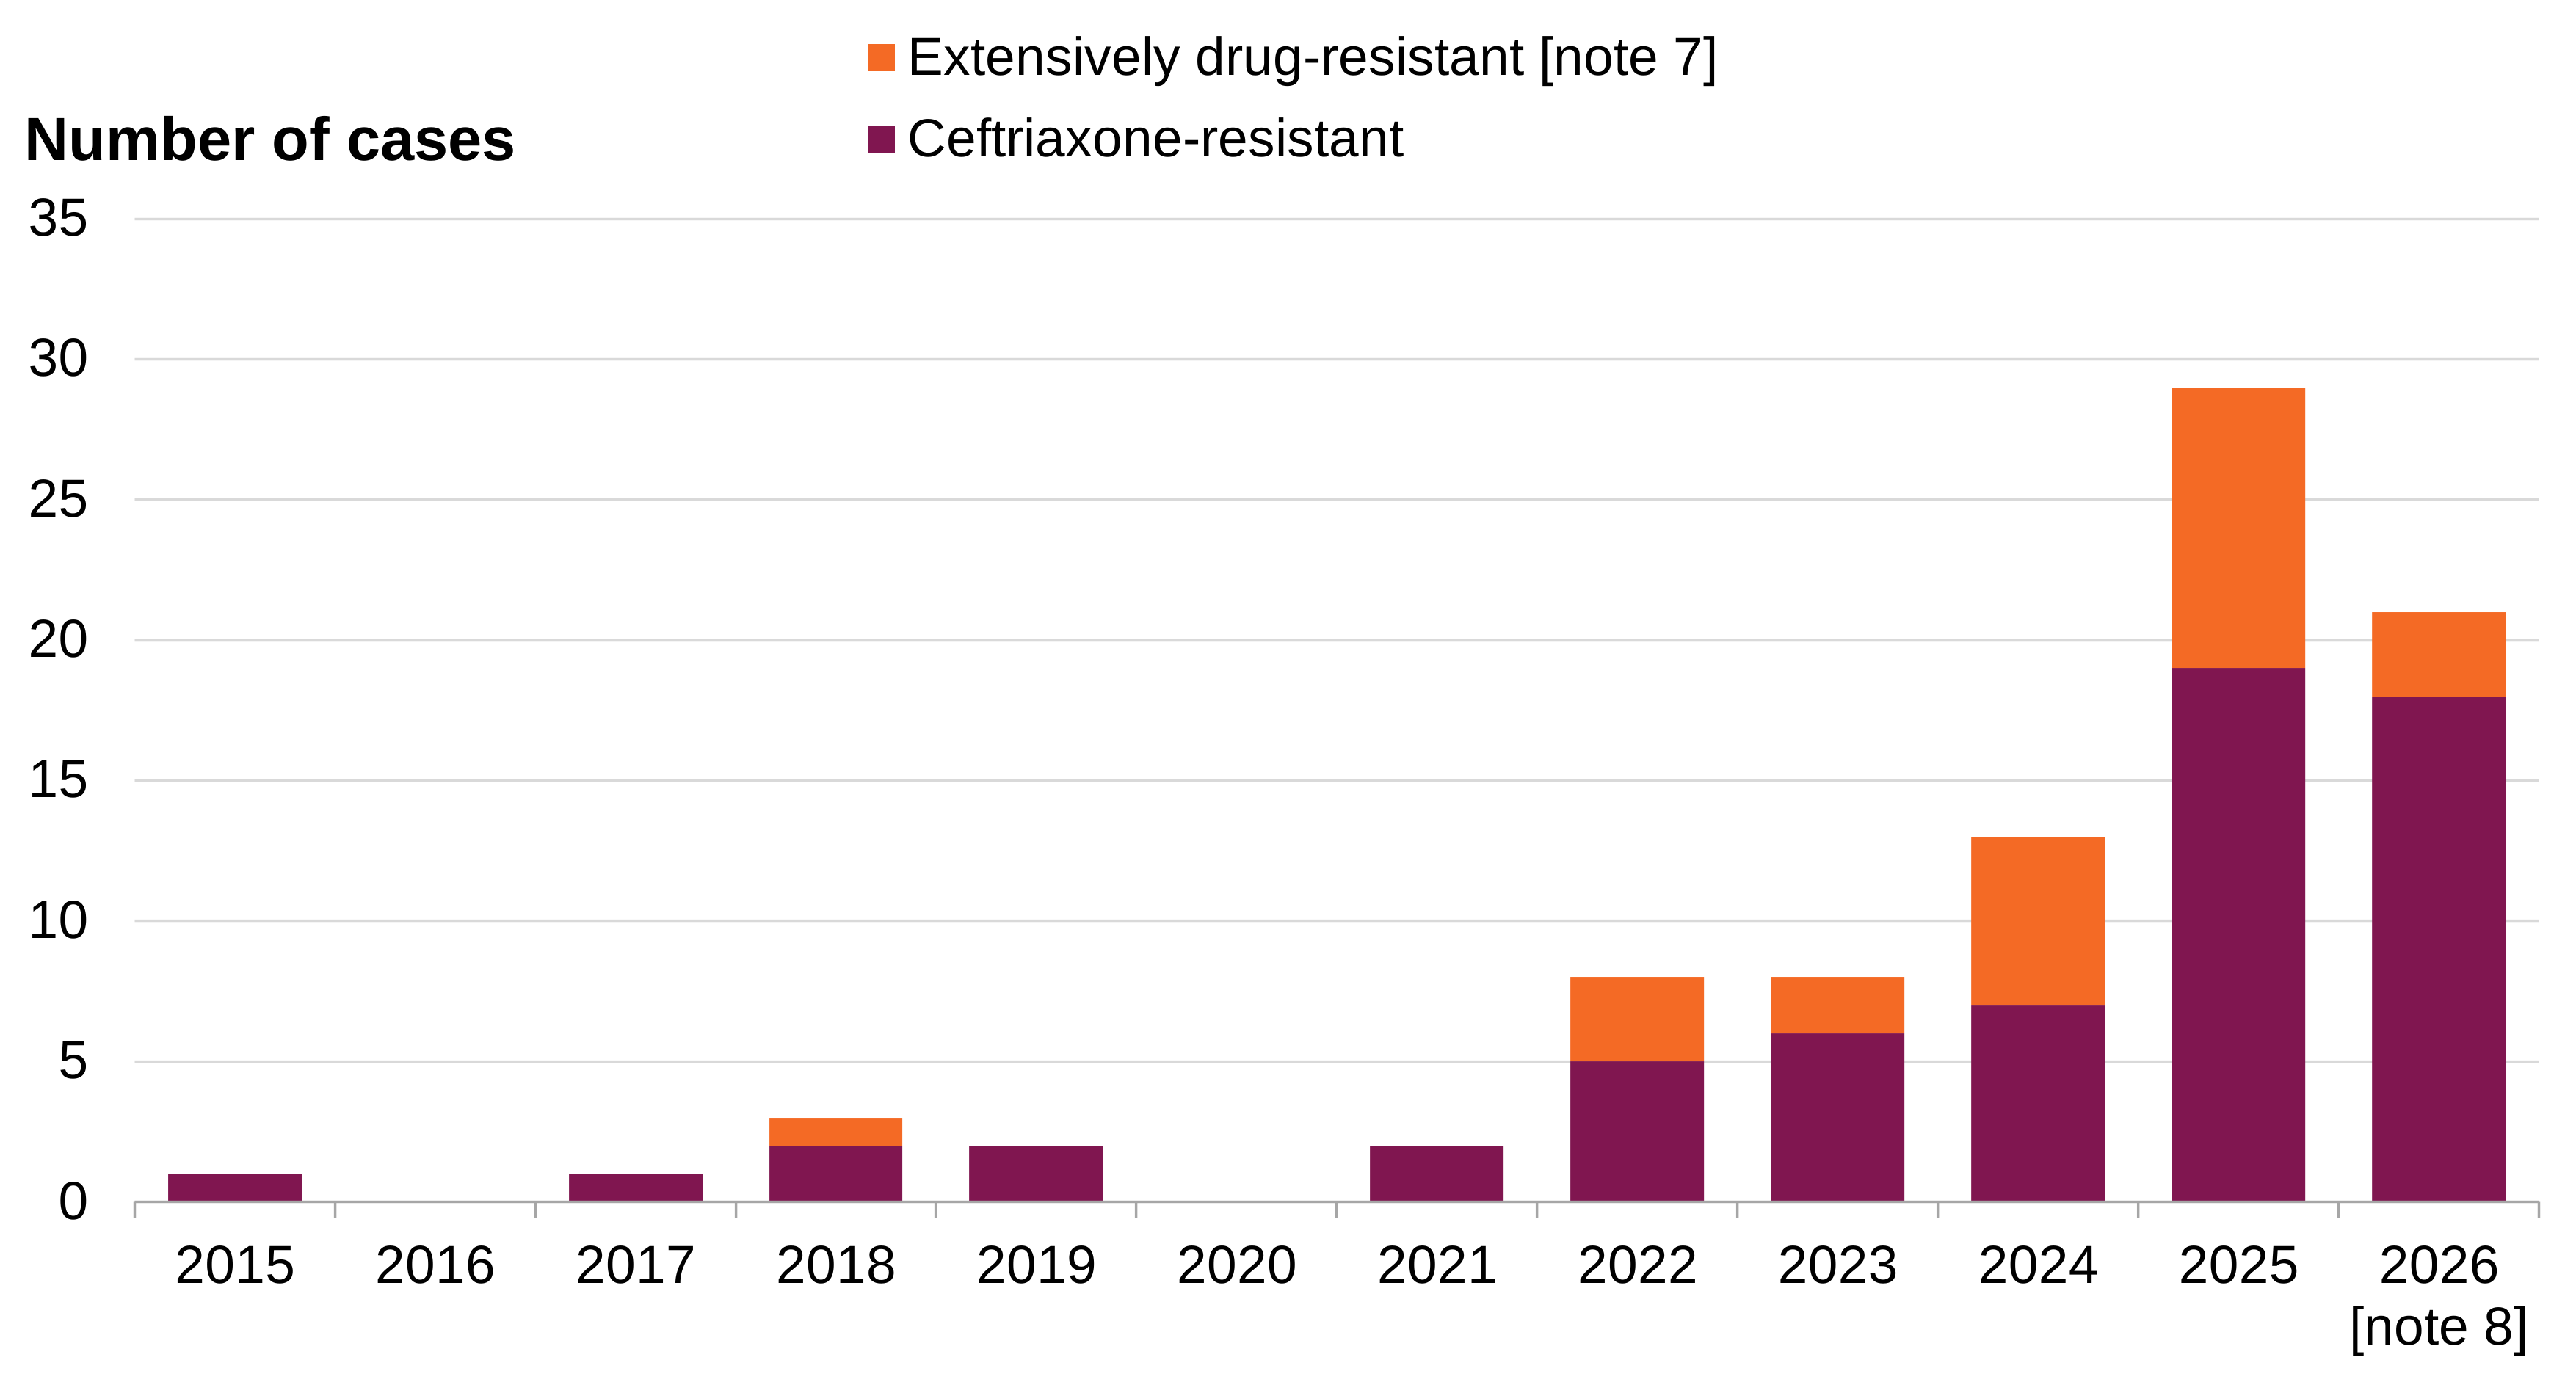
Ceftriaxone-resistant Neisseria gonorrhoeae (the bacterium that causes gonorrhoea) was first detected in England in 2015. By 31 August 2026, a total of 88 cases had been reported in England, an increase of 4 cases since publication of the last quarterly report in June 2026. Of these 88 cases, 25 were extensively drug-resistant (XDR), that is, resistant to first- and second-line antibiotics (Figure 3).
The frequency of detecting ceftriaxone-resistant Neisseria gonorrhoeae has increased since 2021. There were 29 cases reported in 2025 which is more than double the number of cases (13) reported in 2024. The elevated frequency of detection has continued into 2026 and there have been 21 cases reported to date.
Background information
Neisseria gonorrhoeae has developed resistance to every class of antibiotics used to treat it, and cephalosporins are the last remaining class of antibiotics available for use as empirical monotherapy. The currently recommended first-line therapy is 1g ceftriaxone (a cephalosporin) and, while the vast majority of gonorrhoea cases in England are susceptible to ceftriaxone, cases of ceftriaxone-resistant Neisseria gonorrhoeae detected in England are increasing. Most ceftriaxone-resistant cases are associated with travel to or from the Asia-Pacific region, where the prevalence of ceftriaxone resistance is high. However, in 2026, there has been evidence of transmission within England, with 3 individuals and a cluster of 5 individuals, with no known travel links.
Guidance is available on the management of ceftriaxone-resistant gonorrhoea. Suspected ceftriaxone treatment failures should be reported to UKHSA via the ‘Gonorrhoea treatment failure report form’ on the HIV and STI Data Exchange. For any queries, please contact grasp.enquiries@ukhsa.gov.uk
Ceftriaxone-resistant isolates should be referred to the UKHSA sexually transmitted infections reference laboratory (STIRL). Annual data on trends in antimicrobial resistance and decreased susceptibility in gonococcal infection in England and Wales are published in the Gonococcal resistance to antimicrobials surveillance programme (GRASP) report.
Figure 3. Number of cases of infection with ceftriaxone-resistant Neisseria gonorrhoeae in England, January 2015 to 31 August 2026
Source: referrals to the STIRL at UKHSA from SHSs in England.
Note 7: extensively drug-resistant (XDR) infections are defined as resistant to both first- and second-line treatment options and to other antibiotics.
Note 8: 2026 shows data from January to 31 August 2026.