National flu and COVID-19 surveillance report: 8 October 2026 (week 41)
Updated 8 October 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/statistics/national-flu-and-covid-19-surveillance-reports-2026-to-2027-season/national-flu-and-covid-19-surveillance-report-8-october-2026-week-41
This report summarises the information from the surveillance systems which are used to monitor COVID-19 (caused by severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2)), influenza, respiratory syncytial virus (RSV) and diseases caused by other seasonal respiratory viruses in England. The report is based on data up to week 40 of 2026 between 28 September and 4 October 2026.
Main points
The main messages of this report are:
-
influenza activity increased and is circulating at baseline levels
-
COVID-19 activity increased and is circulating at low levels
-
respiratory syncytial virus (RSV) activity remained low and is circulating at baseline levels
Seasonal reports
Annual reports for the 2025 to 2026 season:
Summary of all respiratory virus activity
Influenza activity
Influenza activity increased and is circulating at baseline levels. Emergency department (ED) attendances for influenza-like-illness (ILI) increased and were above seasonally expected levels. The number of influenza-confirmed acute respiratory infection (ARI) incidents in the community was stable compared with the previous week.
Weekly influenza vaccine uptake for the 2026 to 2027 season is reported for the first time this season. Data is for week 40 (up to 4 October 2026). Compared with the equivalent week last season (2025 to 2026), vaccine uptake is lower in those aged 65 years and over, 6 months to under 65 years in clinical risk groups, and 2 and 3-year-olds. Vaccine uptake is comparable for pregnant women. Some data relating to uptake in pharmacies was unavailable or incomplete at the time of reporting. Findings should be interpreted with caution, particularly in those aged 65 years or older, 6 months to under 65 years in risk groups and pregnant women, as results may be subject to change when additional data become available.
| Indicator | Trend | Level [note 1] | Comments |
|---|---|---|---|
| Laboratory surveillance | Increasing | Low | Influenza positivity increased with a positivity rate on the most recent Sunday of 6.5% compared with 5.0% on the previous Sunday |
| ILI general practice (GP) consultations | Increasing | Baseline | The weekly ILI consultation rate increased to 5.6 per 100,000 registered population in participating GP practices compared with 4 per 100,000 in the previous week |
| GP swabbing positivity | Increasing | Baseline | In week 40, among all tested samples, 10.0% were positive for influenza, compared with 7.6% in the previous week |
| Hospital admissions | No trend | Baseline | The overall weekly hospital admission rate for influenza hospitalisations was 1.97 per 100,000 |
| Intensive care units (ICU)/High-dependency unit (HDU) admissions | No trend | Baseline | The overall weekly hospital admission rate for influenza ICU-HDU remained was 0.06 per 100,000 |
COVID-19 activity
COVID-19 activity increased across some indicators and is circulating at low levels. ED attendances for COVID-19-like illness increased and were above seasonally expected levels. The number of COVID-19 confirmed acute respiratory infections (ARI) incidents increased compared with the previous week.
By the end of week 40 2026 (week ending 4 October 2026) 10.2% of all people aged 75 years and over, and 4.1% of all people aged under 75 years with a weakened immune system, had been vaccinated with an autumn 2026 dose since 1 October 2026.
| Indicator | Trend | Level [note 1] | Comments |
|---|---|---|---|
| Laboratory surveillance | Increasing | Low | COVID-19 PCR (polymerase chain reaction) positivity in hospital settings increased with a positivity rate on the most recent Sunday of 9.1% compared with 7.9% on the previous Sunday |
| GP swabbing positivity | Stable | Moderate | In week 40, among all tested samples, 10.8% were positive for SARS-CoV-2, compared with 10.9% in the previous week |
| Hospital admissions | Increased | Baseline | The overall weekly hospital admission rate for COVID-19 increased to 2.04 per 100,000 compared with 1.75 per 100,000 in the previous week |
| ICU/HDU admissions | Remained low | Baseline | The overall weekly ICU or HDU admission rate for COVID-19 remained low at 0.06 per 100,000 compared with 0.05 per 100,000 in the previous week |
Respiratory syncytial virus activity
RSV activity remained low and is circulating at baseline levels. ED attendances for acute bronchiolitis remained low and below seasonally expected levels.
| Indicator | Trend | Level [note 1] | Comments |
|---|---|---|---|
| Laboratory surveillance | Increasing | Baseline | RSV positivity increased to 0.5% compared with 0.3% in the previous week. |
| GP swabbing positivity | Decreasing | Baseline | In week 40, among all tested samples, 0.7% were positive for RSV compared with 0.9% in the previous week |
| Hospital admissions | Remained low | Baseline | The overall weekly hospital (excl ICU-HDU) admission rate for RSV remained low at 0.11 per 100,000 compared with 0.13 per 100,000 in the previous week |
Other viruses
| Indicator | Trend | Level [note 1] | Comments |
|---|---|---|---|
| Adenovirus | Decreasing | Baseline | Adenovirus positivity (laboratory surveillance) decreased to 0.9% compared with 1.3% in the previous week |
| Human metapneumovirus (hMPV) | Decreasing | Baseline | hMPV positivity (laboratory surveillance) decreased to 0.1% compared with 0.2% in the previous week |
| Parainfluenza | Increasing slightly | Baseline | Parainfluenza positivity (laboratory surveillance) increased slightly to 2.5% compared with 2.2% in the previous week |
| Rhinovirus | Decreasing slightly | Moderate | Rhinovirus positivity (laboratory surveillance) decreased slightly to 17.3% compared with 18.6% in the previous week |
Note 1: these indicators use the moving epidemic method (MEM) and the mean standard deviation method (MSD) to define thresholds to determine their respective levels of activity. Further information on these methods can be found in Influenza surveillance in Europe: establishing epidemic thresholds by the Moving Epidemic Method and Setting thresholds to determine COVID-19 activity levels using the mean standard deviation (MSD) method, England, 2022 to 2024. The MEM approach is well-established for some influenza surveillance indicators, however, for other indicators both the MEM and MSD are experimental and may be subject to future revision. Influenza laboratory surveillance and GP swabbing positivity have transitioned from using MEM to using MSD. These approaches will be considered alongside expert opinion and triangulation of other data sources.
Laboratory surveillance
Laboratory-confirmed cases
The Second Generation Surveillance System (SGSS) captures test result information for notifiable infectious diseases, including COVID-19 and influenza, from laboratories in England. The unified sample dataset (USD) stores all SARS-CoV-2 test results reported to SGSS, Respiratory DataMart and UKHSA laboratories, and is used to calculate the percentage of tests positive for SARS-CoV-2 among all SARS-CoV-2 tests conducted.
COVID-19 cases
As of 4 October 2026, there were a total of 1,638 COVID-19 cases identified in hospital settings in week 40, increasing from 1,328 cases in the previous week.
SARS-CoV-2 (COVID-19) PCR positivity in hospital settings increased in week 40, with a rolling 7-day positivity rate of 9.1% up to Sunday 4 October 2026 compared with 7.9% for the same period on the previous Sunday.
Positivity rates were highest among those aged 85 years and over with a rolling 7-day positivity rate of 13.1% up to Sunday 4 October 2026. This has increased compared to 10.4% in the same age group on the previous Sunday.
Figure 1. Weekly confirmed COVID-19 episodes tested in hospital settings, England
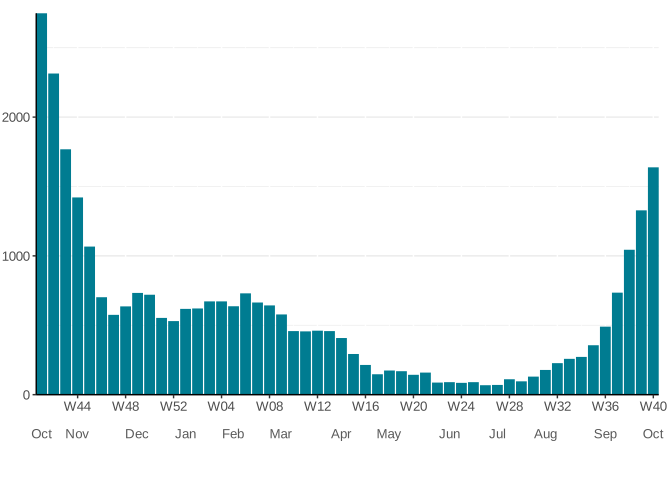
Figure 2. Rolling 7-day positivity of tests positive for SARS-CoV-2 among all reported SARS-CoV-2 tests, England 2022 to present [note 2] [note 3]
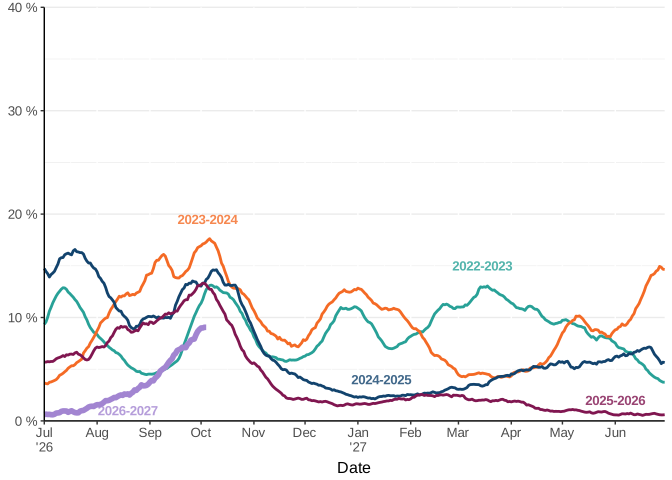
Note 2: data from previous seasons is aligned by day.
Note 3: testing policy and practice may change over time which can impact positivity rates, therefore comparisons over time should be interpreted with caution. Notable changes in testing policy occurred during 2022 to 2023, which are outlined in the data quality report.
Figure 3. Rolling 7-day positivity of tests positive for SARS-CoV-2 among all reported SARS-CoV-2 tests by age group, England [note 4]
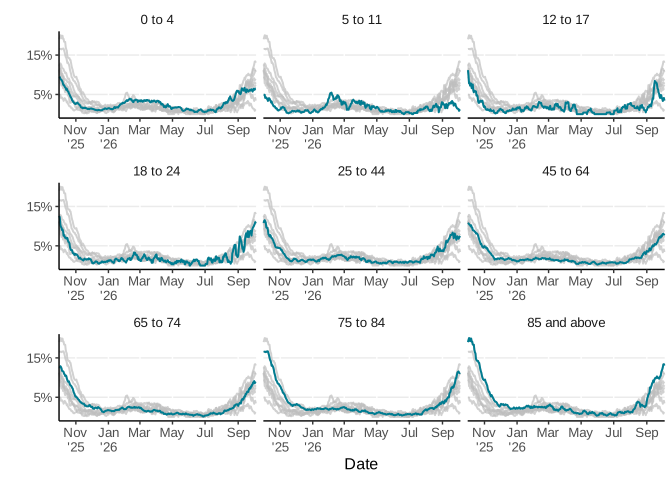
Note 4: the highlighted line corresponds to the age group in the subplot title, grey lines correspond to all other age groups.
Influenza cases
Influenza positivity increased in week 40, with a rolling 7-day positivity rate of 6.5% up to Sunday 4 October 2026. This is compared with 5.0% on the previous Sunday.
By type, influenza A positivity increased in week 40, with a rolling 7 day positivity rate of 5.8% up to Sunday 4 October 2026. Influenza B positivity increased in the same week, with a rolling 7 day positivity rate of 0.4% up to Sunday 4 October 2026.
Influenza A positivity rates were highest among those aged between 18 and 24 years, with a rolling 7-day positivity rate of 28.1% up to Sunday 4 October 2026. This has increased from 24.4% in the same age group on the previous Sunday.
Influenza B positivity rates for the same period were highest among those aged between 5 and 11 years, with a rolling 7-day positivity rate of 1.5%. This has decreased slightly from 1.6% in the same age group on the previous Sunday.
Due to an ongoing data quality issue resulting in more tests than usual being removed, historical positivity for influenza may be slightly lower in reports published from week 25 2026 onwards. Historical estimates will be updated once the affected data has been rectified.
Figure 4. Rolling 7-day positivity of tests positive for influenza among all reported influenza tests, England 2022 to present [note 2]
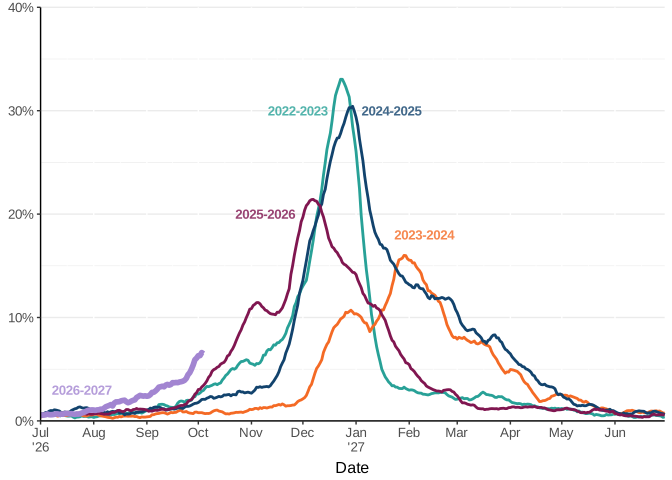
Note 2: data from previous seasons is aligned by day.
Figure 5. Rolling 7-day positivity of tests positive for each influenza type among all reported influenza type tests, England [note 4]
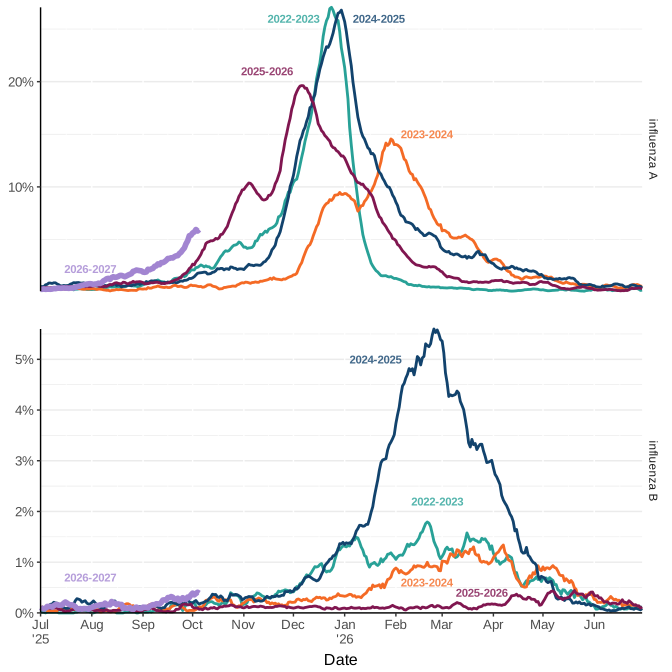
Note 2: data from previous seasons is aligned by day.
Figure 6. Rolling 7-day positivity of tests positive for each influenza type among all reported influenza type tests by age group, England [note 4]
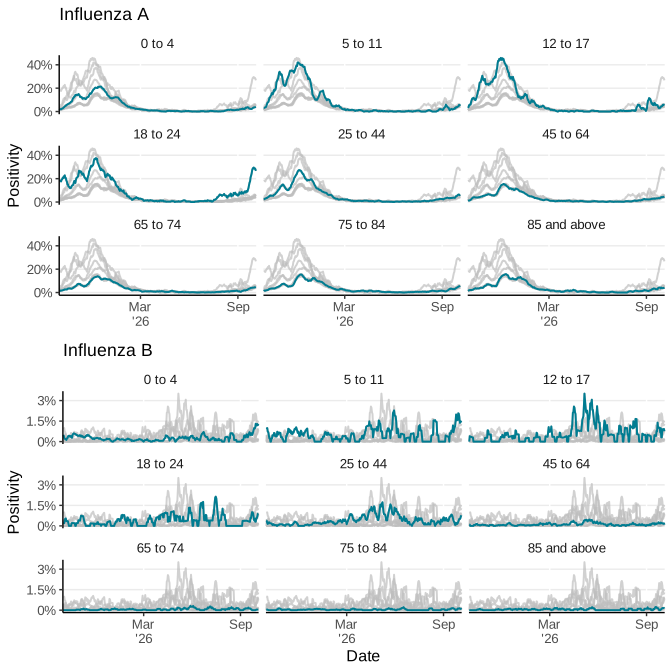
Note 4: the highlighted line corresponds to the age group in the subplot title, grey lines correspond to all other age groups.
RSV positivity
RSV swab-positivity based PCR test results reported through SGSS have been included as a pilot indicator from week 49 2025 onwards.
RSV positivity increased in week 40, with a rolling 7-day positivity rate of 0.5% up to Sunday 4 October 2026, compared with 0.4% up to the previous Sunday.
RSV positivity rates were highest in those aged between 0 and 4 years with a rolling 7-day positivity rate of 3.5% up to Sunday 4 October 2026 in week 40. This has increased from 2.4% in the same age group on the previous Sunday.
Figure 7. Rolling 7-day positivity of tests positive for RSV among all reported RSV tests in SGSS, England
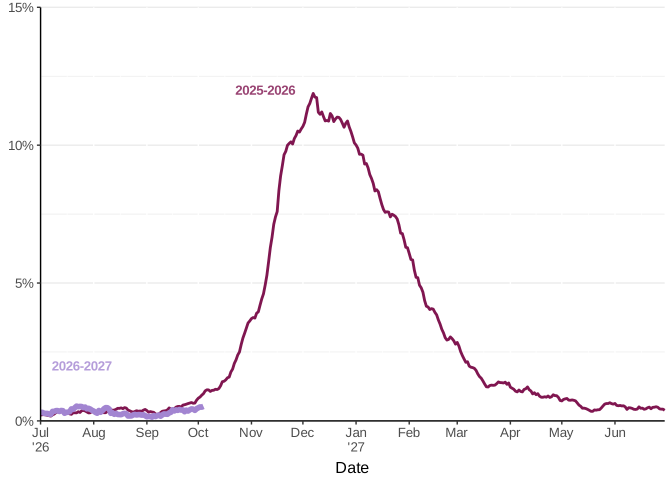
Figure 8. Rolling 7-day positivity of tests positive for RSV among all reported RSV tests in SGSS by age group, England [note 4]
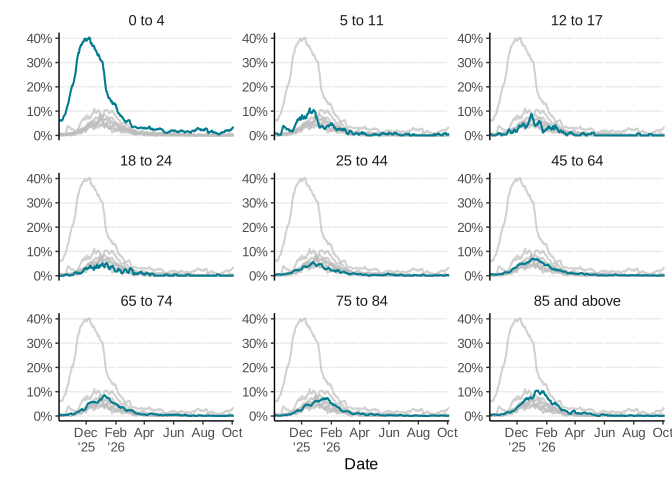
Note 4: the highlighted line corresponds to the age group in the subplot title, grey lines correspond to all other age groups.
Respiratory DataMart System
Respiratory DataMart is a sentinel laboratory-based surveillance system where participating laboratories report positive and negative test results for a number of respiratory viruses from samples primarily taken in hospital. A small proportion of primary care samples are also included in this reporting.
In week 40, data is based on reporting from 9 out of the 14 sentinel laboratories.
In week 40, 2,765 respiratory specimens reported through the Respiratory DataMart System were tested for influenza. There were 156 positive samples for influenza: 88 influenza A (not subtyped), 40 influenza A (H3N2), 18 influenza A (H1N1)pdm09, and 12 influenza B. Overall, influenza positivity increased slightly to 5.6% in week 40 compared with 5.3% in the previous week.
In week 40, 3,396 respiratory specimens reported through the Respiratory DataMart System were tested for SARS-CoV-2. There were 258 positive samples for SARS-CoV-2. SARS-CoV-2 positivity increased slightly to 7.6% compared with 6.8% in the previous week, with the highest positivity in those aged 80 years and over at 10.6%.
RSV positivity increased to 0.5%, with the highest positivity in those aged under 5 years at 4.4%.
Adenovirus positivity decreased to 0.9%, with the highest positivity in those aged under 5 years at 4.4%.
Human metapneumovirus (hMPV) positivity decreased to 0.1%, with the highest positivity in those aged 80 years and over at 0.5%.
Parainfluenza positivity increased slightly to 2.5%, with the highest positivity in those aged under 5 years at 8.7%.
Rhinovirus positivity decreased slightly to 17.3%, with the highest positivity in those aged under 5 years at 34.4%.
DataMart data is provisional and subject to retrospective updates.
Figure 9a. Respiratory DataMart weekly percentage of tests positive for influenza, SARS-CoV-2, RSV and rhinovirus, England [note 5]
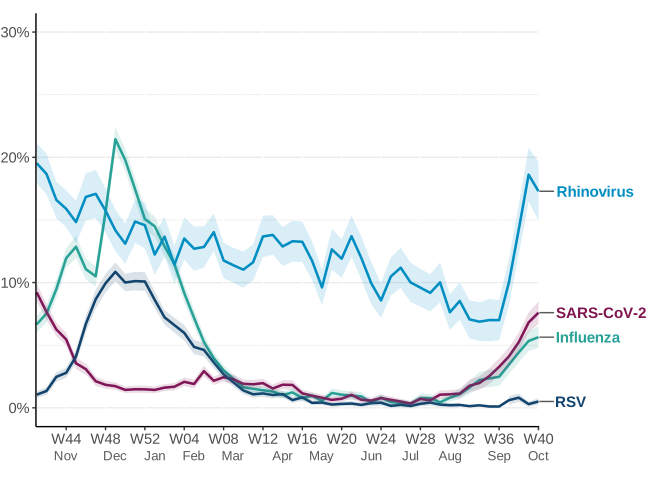
Note 5: shading represents 95% confidence intervals.
Figure 9b. Respiratory DataMart weekly percentage of tests positive for adenovirus, hMPV and parainfluenza, England [note 5]
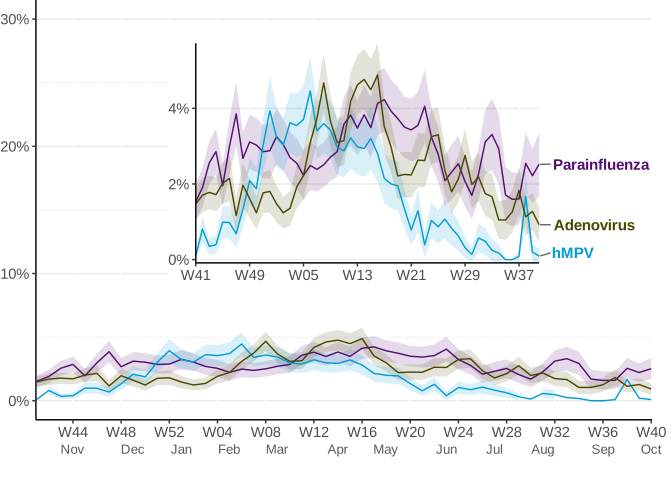
Note 5: shading represents 95% confidence intervals.
Figure 10. Respiratory DataMart weekly cases by influenza subtype, England
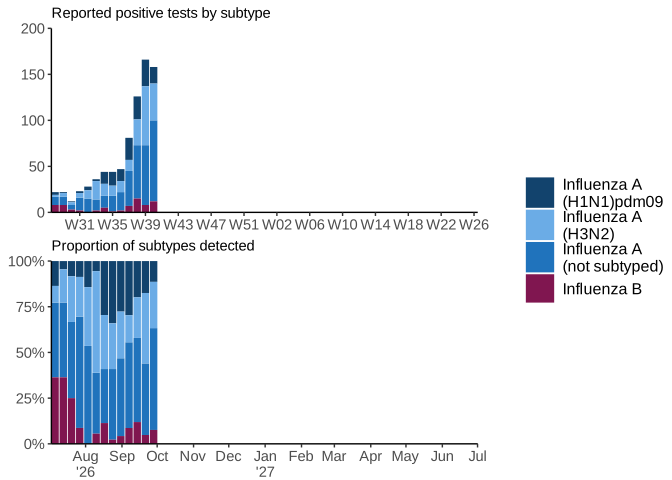
Figure 11. Respiratory DataMart weekly percentage testing positive for RSV by season, England
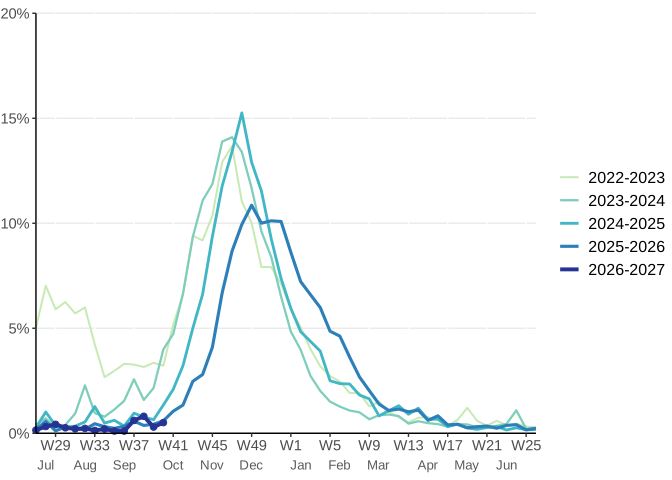
Figure 12. Respiratory DataMart weekly percentage testing positive for RSV by age, England [note 4]
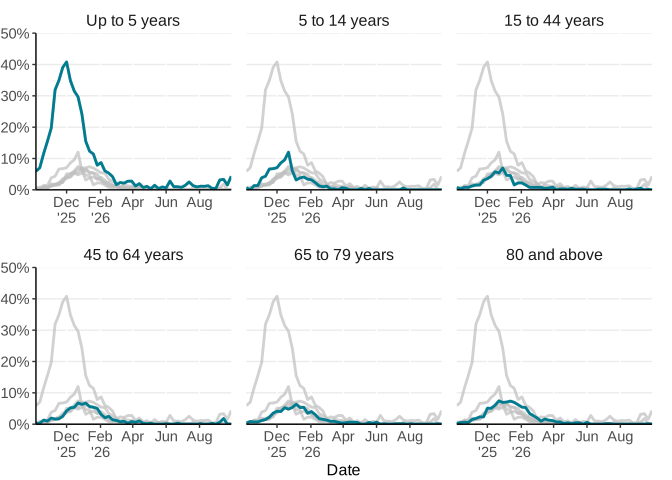
Note 4: the highlighted line corresponds to the age group in the subplot title, grey lines correspond to all other age groups.
SARS-CoV-2 lineages
UKHSA conducts genomic surveillance of SARS-CoV-2 lineages.
This section provides an overview of circulating lineages in England, derived from data on sequenced PCR-positive SARS-CoV-2 samples in SGSS.
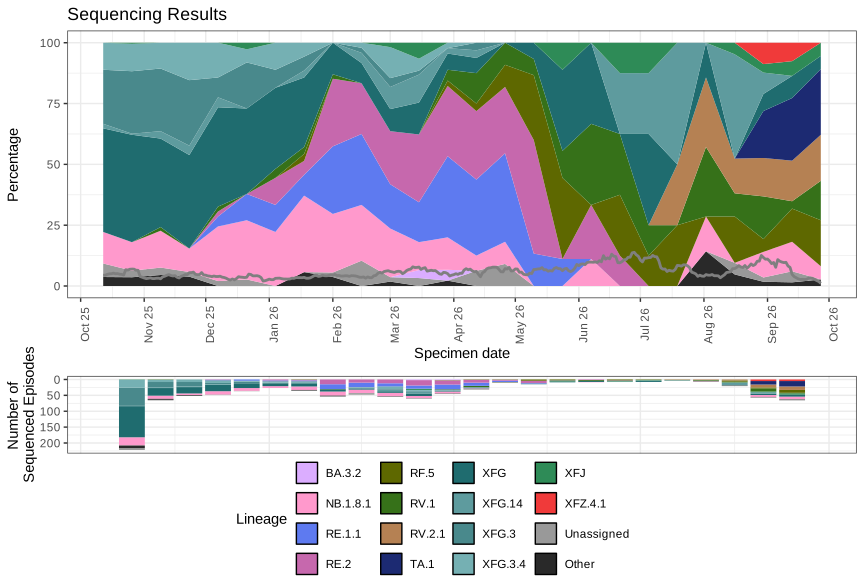
The prevalence of UKHSA-designated lineages among sequenced cases is presented in Figure 13.
To account for reporting delays, we report the proportion of lineages within COVID-19 cases that have had a sequenced positive sample between 31 August 2026 and 13 September 2026.
Of those sequenced in this period:
-
25.8% was classified as TA.1
-
16.7% was classified as RV.2.1
-
13.6% was classified as RF.5
-
12.1% was classified as NB.1.8.1
-
9.1% was classified as XFG
-
7.6% was classified as XFZ.4.1
-
6.1% was classified as XFJ
-
3.0% was classified as RV.1
Note that low sequencing numbers, especially within the latest reporting period, will impact the accuracy of the prevalence estimates. These most recent figures should therefore be interpreted with caution.
Note that lineages will be grouped independently from their parent lineage once they reach sufficient prevalence, and may be re-grouped into their parent lineage if their prevalence subsequently falls. The data quality report contains more information on lineage groupings.
Figure 13. Prevalence of SARS-CoV-2 lineages amongst available sequenced cases for England from 29 September 2025 to 27 September 2026
Influenza virus characterisation
Analysis of viruses from primary and secondary care shows that circulating A(H1N1)pdm09 viruses show low genetic diversity and all belong to clade D.3.1.1.
Observations published from the WHO influenza vaccine composition meeting (VCM) in September 2026 suggest low reactivity of some viruses within the D.3.1.1 subclade with post-infection ferret antisera raised against A/Missouri/11/2025 (H1N1)pdm09-like virus – the A(H1N1)pdm09 component in 2026 Southern and 2026/2027 Northern Hemisphere cell and egg based influenza vaccines - and human sera post-vaccination with the Southern Hemisphere vaccine 2026.
It is not yet clear how vaccine effectiveness against clinical disease may be affected by these observations. Vaccines typically still provide protection against severe clinical disease when drifted strains are seen with only a modest reduction in effectiveness.
The characterisation of circulating A(H3N2) viruses show that A(H3N2) viruses are currently showing low genetic diversity. All sequenced viruses to date belong to genetic subclade K.
To date, only a small number of influenza B viruses have been detected, which show some genetic diversity.
Genetic characterisation
Between week 35 2026 (week ending 30 August 2026) and week 40 2026 (week ending 4 October 2026), the UKHSA respiratory virus unit (RVU) has genetically characterised 92 seasonal influenza viruses, and identified 44 influenza A(H1N1)pdm09 viruses, 41 influenza A(H3N2) viruses, and 7 influenza B viruses. Details of the characterised viruses by subtype are shown in Tables 1, 2 and 3. The RVU has not yet confirmed the detection of live attenuated influenza vaccine (LAIV) viruses in any influenza A/B positive sample, collected from children aged between 2 and 16 years of age by genome sequencing.
Table 1. Number of influenza A H1N1(pdm09) viruses characterised by genetic analysis at the UKHSA Respiratory Virus Unit since week 35 2026
| Clade | Subclade | Detections |
|---|---|---|
| 5a.2a.1 | D.3.1.1 | 44 |
Table 2. Number of influenza A(H3N2) viruses characterised by genetic analysis at the UKHSA Respiratory Virus Unit since week 35 2026
| Clade | Subclade | Detections |
|---|---|---|
| 2a.3a.1 | K (J.2.4.1) | 41 |
Table 3. Number of influenza B viruses characterised by genetic analysis at the UKHSA Respiratory Virus Unit since week 35 2026
| Clade | Subclade | Detections |
|---|---|---|
| V1A.3a.2 | C.3.1 | 1 |
| V1A.3a.2 | C.5.6 | 5 |
| V1A.3a.2 | C.5.6.1 | 1 |
Antigenic characterisation
UKHSA RVU performs antigenic characterisation of influenza A(H1N1)pdm09, influenza A(H3N2) and influenza B viruses using haemagglutination inhibition (HI) assays. Data from these assays are used to compare how similar the currently circulating influenza viruses are to the strains included in seasonal influenza vaccines, and to monitor for changes in circulating influenza viruses. Similarity of currently circulating influenza strains to vaccine strains is defined as having an antibody titre within 4-fold when compared to reference viruses representative of the vaccine strain. Antigenic characterisation of viruses in the current reporting period is underway.
Influenza virus antiviral susceptibility surveillance
Influenza positive samples are screened for mutations in the virus neuraminidase (NA) and the cap-dependent endonuclease of the polymerase acidic protein (PA) genes known to confer neuraminidase inhibitor (oseltamivir and zanamivir) or baloxavir resistance, respectively. Results from this surveillance are given in table 4. There have been no detections with mutations related to reduced susceptibility or resistance to oseltamivir and/or reduced susceptibility to baloxavir.
Table 4. Oseltamivir, zanamivir and baloxavir marboxil antiviral susceptibility results of influenza positive samples tested at UKHSA-RVU since week 35 of 2026 using whole genome sequencing
| Subtype | Interpretation | Detections | Relevant mutations (in gene) | Antiviral use if known |
|---|---|---|---|---|
| H1N1pdm09 | Normal inhibition (oseltamivir and zanamivir) | 44 | None (NA) | Not applicable |
| H1N1pdm09 | Normal susceptibility (baloxavir marboxil) | 41 | None (PA) | Not applicable |
| H3N2 | Normal inhibition (oseltamivir and zanamivir) | 41 | None (NA) | Not applicable |
| H3N2 | Normal susceptibility (baloxavir marboxil) | 40 | None (PA) | Not applicable |
| B Victoria | Normal inhibition (oseltamivir and zanamivir) | 7 | None (NA) | Not applicable |
| B Victoria | Normal susceptibility (baloxavir marboxil) | 7 | None (PA) | Not applicable |
Community surveillance
Acute respiratory infection incidents (ARI)
Data is presented on viral ARI incidents in different settings that are reported to UKHSA health protection teams (HPTs).
Please note that reporting practices are known to vary between seasons and between regions. Any interpretation of temporal and regional trends should consider the likelihood of differences in reporting of ARI incidents over time and between regions.
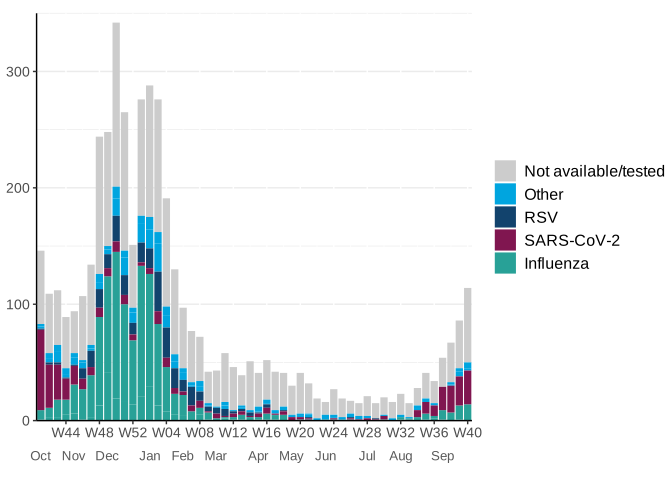
There were 114 new ARI incidents reported in week 40 in England. These included:
-
99 incidents from care homes, of which 21 were due to SARS-CoV-2, 12 were due to influenza A, 5 were due to other pathogens and 1 was due to multiple pathogens. No pathogen was reported in 60 incidents
-
6 incidents from hospitals, of which 4 were due to SARS-CoV-2 and 1 was due to influenza A. No pathogen was reported in 1 incident
-
1 incident from educational settings for which no tests were available
-
no incidents from prisons
-
8 incidents from other settings, of which 4 were due to SARS-CoV-2, 1 was due to influenza A and 1 was due to multiple pathogens. No pathogen was reported in 2 incidents
Figure 14. Number of ARI incidents by setting, England
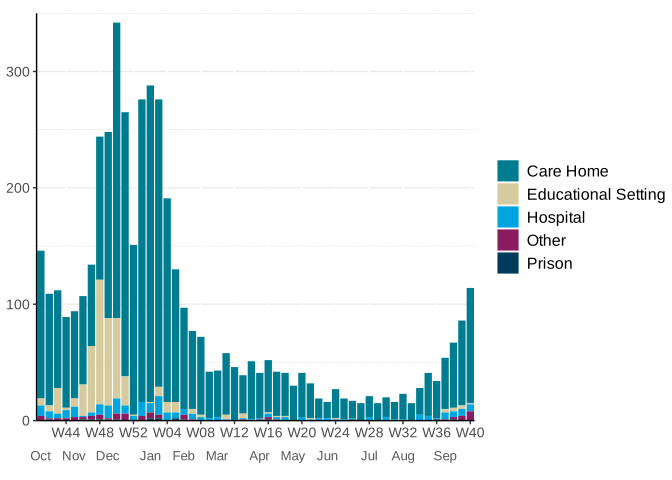
Figure 15. Number of ARI incidents in all settings by virus type, England
Syndromic surveillance
Syndromic surveillance collects data from various healthcare sources where presentations are classified by patterns of symptoms compatible with specific infections. In some settings, the syndromic diagnosis can be supplemented by (rapid) testing. In this report, ED attendances are displayed. Further details and data from other syndromic surveillance systems can be found in the syndromic surveillance weekly summaries.
During the week ending on 04 October 2026, ED attendances for acute respiratory infections increased and were above seasonally expected levels. ED attendances for COVID-19-like illness remained stable. ED attendance for influenza-like illness increased and were above seasonally expected levels. ED attendance for acute bronchiolitis (a syndrome related to RSV infection) were stable and below seasonally expected levels.
Daily NHS 111 acute respiratory infection triaged calls continued to increase in line with seasonally expected baselines. Increases in calls and online assessments for acute respiratory infection stabilised in children aged up to 14 years during the past week, but continued to increase in older age groups over 15 years.
GP in-hours consultation rates for upper respiratory tract infections increased, most notably in adults aged over 45 years but broadly in line with seasonal expectations. There were further increases in COVID-19-like consultation rates. Influenza-like illness consultation rates increased and were above levels expected for the time of year with increases noted in adults, particularly those aged 15 to 44 years.
GP out-of-hours daily contacts for ‘acute respiratory infections’ and ‘difficulty breathing or wheeze or asthma’ increased in line with seasonally expected baselines. Both of these indicators were stable or decreased in the under 15 years age groups but increased in the over 15 years age groups. Daily influenza-like illness contacts stabilised nationally.
Figure 16a. Daily emergency department attendances for acute respiratory infection nationally, England [note 6]
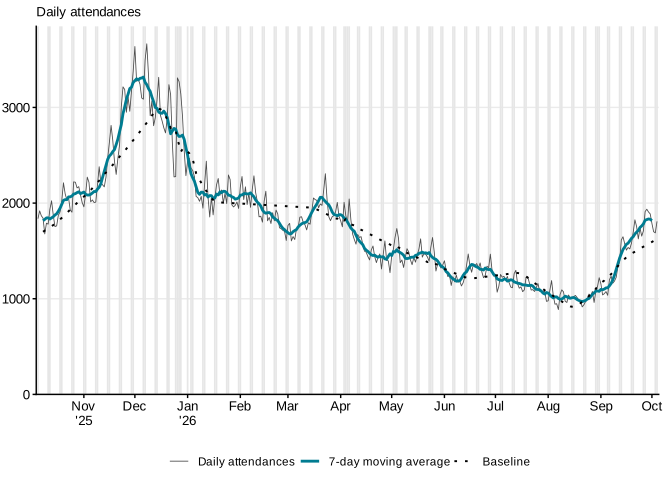
Note 6: 7-day moving average is adjusted for bank holidays. Grey columns show weekends and bank holidays.
Figure 16b. Daily emergency department attendances for acute respiratory infection by age group, England [note 7]
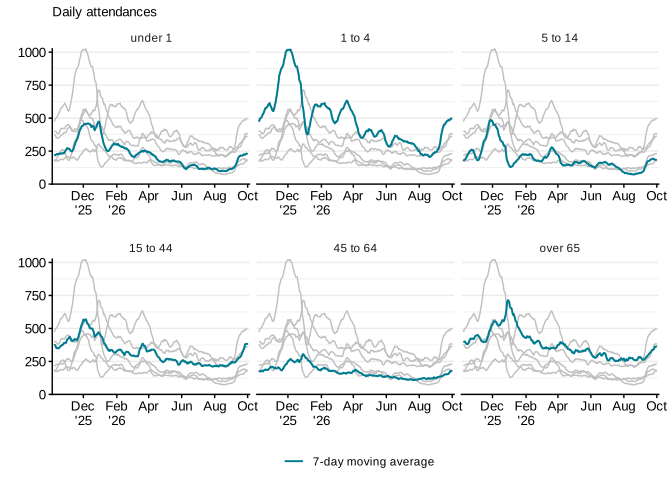
Note 7: the coloured line is the 7-day moving average by age group. Grey lines show the other age groups. The y-axis shows daily attendances. It is adjusted for bank holidays.
Figure 17a. Daily emergency department attendances for COVID-19-like illness nationally, England [note 6]
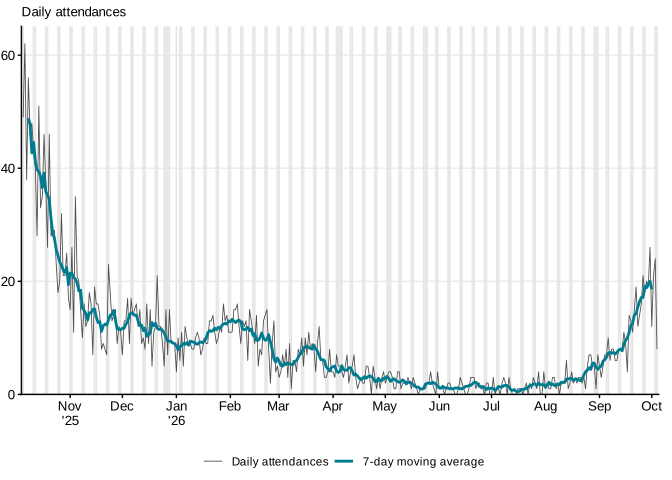
Note 6: 7-day moving average is adjusted for bank holidays. Grey columns show weekends and bank holidays.
Figure 17b. Daily emergency department attendances for COVID-19-like illness by age group, England [note 7]
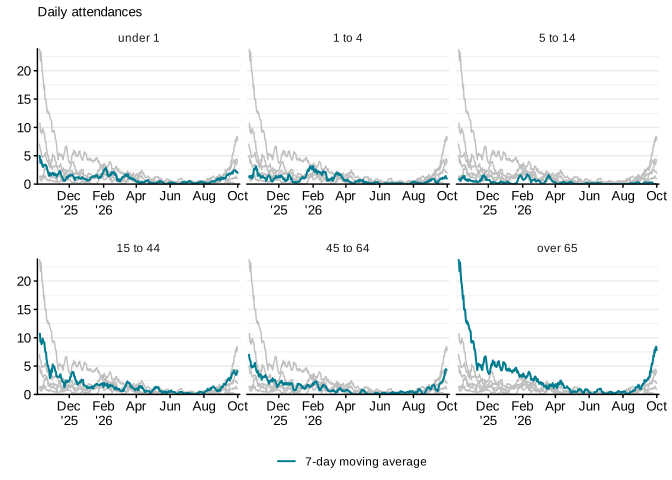
Note 7: the coloured line is the 7-day moving average by age group. Grey lines show the other age groups. The y-axis shows daily attendances. It is adjusted for bank holidays.
Figure 18a. Daily emergency department attendances for ILI nationally, England [note 6]
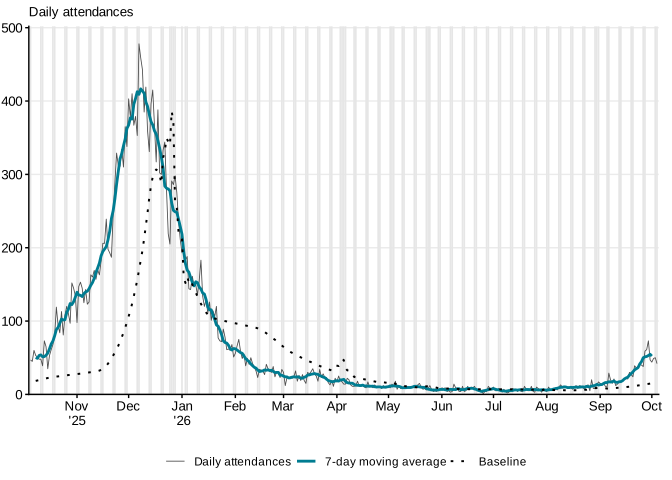
Note 6: 7-day moving average is adjusted for bank holidays. Grey columns show weekends and bank holidays.
Figure 18b. Daily emergency department attendances for ILI by age group, England [note 7]
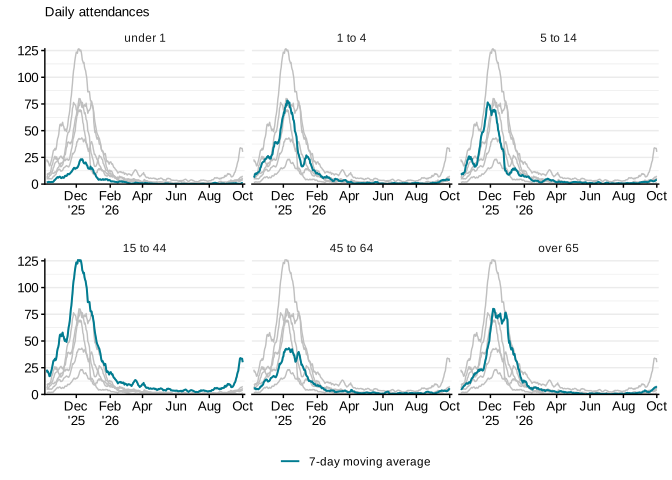
Note 7: the coloured line is the 7-day moving average by age group. Grey lines show the other age groups. The y-axis shows daily attendances. It is adjusted for bank holidays.
Figure 19a. Daily emergency department attendances for acute bronchiolitis nationally, England [note 6]
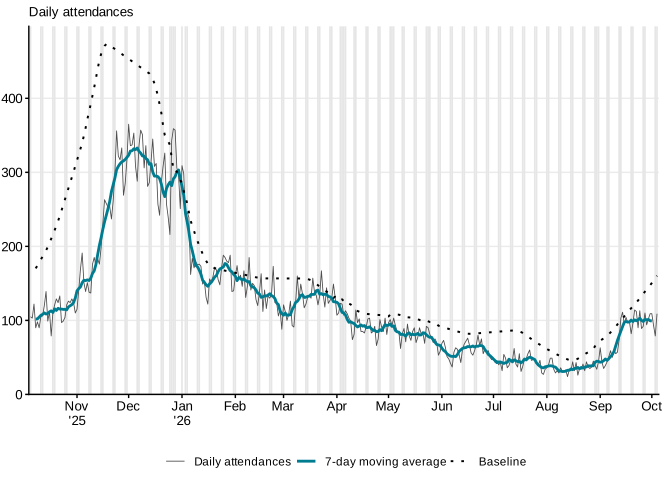
Note 6: 7-day moving average is adjusted for bank holidays. Grey columns show weekends and bank holidays.
Figure 19b. Daily emergency department attendances for acute bronchiolitis by age group, England [note 7]
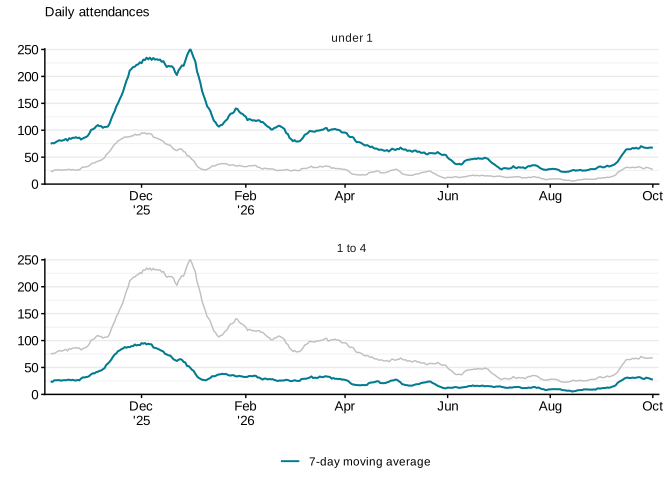
Note 7: the coloured line is the 7-day moving average by age group. Grey lines show the other age groups. The y-axis shows daily attendances. It is adjusted for bank holidays.
Primary care surveillance
Primary care surveillance is undertaken in collaboration with the Royal College of General Practitioners (RCGP) Research and Surveillance Centre (RSC), using a national sentinel surveillance system of around 2,000 GP practices covering over 20 million registered patients of all ages across England. More information on the methodology can be found in the data quality report.
RCGP clinical indicators (England)
The weekly ILI consultation rate through the RCGP surveillance increased to 5.6 per 100,000 registered population in participating GP practices in week 40 compared with 4.0 per 100,000 in the previous week.
This rate is in the baseline activity level (Figure 20). By age group, the highest rates were seen in those aged between 15 and 44 years (7.2 per 100,000), and those aged between 1 and 4 years (5.3 per 100,000).
The lower respiratory tract infections (LRTI) consultation rate increased to 79.5 per 100,000 in week 40 compared with 70.3 per 100,000 in the previous week.
Further details are available in the weekly RSC communicable and respiratory disease report for England.
Figure 20. RCGP ILI consultation rates per 100,000, all ages, England
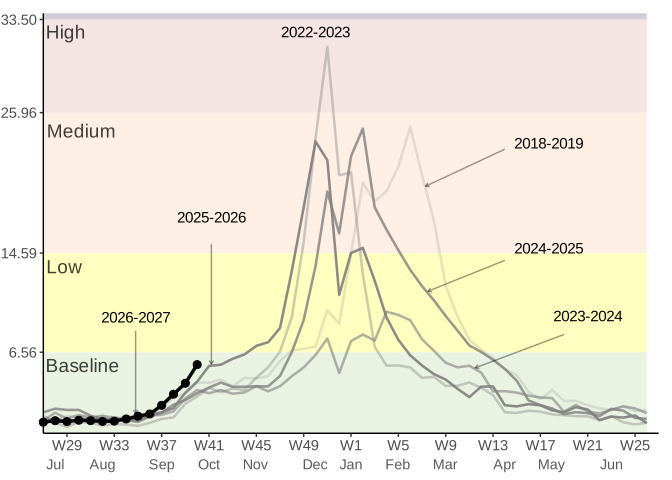
MEM thresholds are based on data from the 2018 to 2019 season to the 2025 to 2026 season. Note the 2019 to 2020, 2020 to 2021 and 2021 to 2022 seasons have been removed.
RCGP sentinel swabbing scheme in England
From week 40 2025, the RCGP sentinel swabbing scheme testing capability has been expanded to the UKHSA Bristol laboratory in addition to the UKHSA Colindale laboratory.
Samples sent to Colindale are tested for influenza A and B, RSV A and B, SARS-CoV-2, hMPV, adenovirus, seasonal coronavirus and enterovirus/rhinovirus while samples sent to Bristol are tested for influenza A and B, RSV and SARS-CoV-2.
A total of 542 samples were taken in week 40 2026 through the GP sentinel swabbing, 305 were tested and 83 tested positive (Figure 21). Starting from week 40 2025, samples with more than 7 days between the sample collection date and the symptom onset date have been excluded.
In week 40 2026, influenza positivity was 10.0%, SARS-CoV-2 positivity was 10.8%, and RSV positivity was 0.7%. Of the 305 samples tested, 52.8% were from the South West. Due to proximity to one of the testing laboratories, samples from the South West tend to be tested more rapidly than those from other parts of the country therefore the latest week’s data may not be fully representative of the country as a whole and should be interpreted with caution.
In week 39 2026, influenza positivity was 7.6%, SARS-CoV-2 positivity was 10.9%, RSV positivity was 0.9%, adenovirus positivity was 2.2%, hMPV positivity was 0.0%, seasonal coronavirus positivity was 2.8%, and enterovirus/rhinovirus positivity was 33.8%. In week 39 2026, 188 samples were tested for influenza, SARS-CoV-2 and RSV only, and a further 142 samples were tested for an extended panel of respiratory viruses. As testing and reporting schedules differ between pathogens, denominators vary and estimates for the most recent week may be subject to revision.
Due to the number of samples which have not yet been categorised, data should be interpreted with caution when compared with previous weeks. The weekly positivity is not calculated when the number of samples with a result is fewer than 50.
Figure 21. Number of samples tested for respiratory viruses in England by week, GP sentinel swabbing scheme [note 8] [note 9]
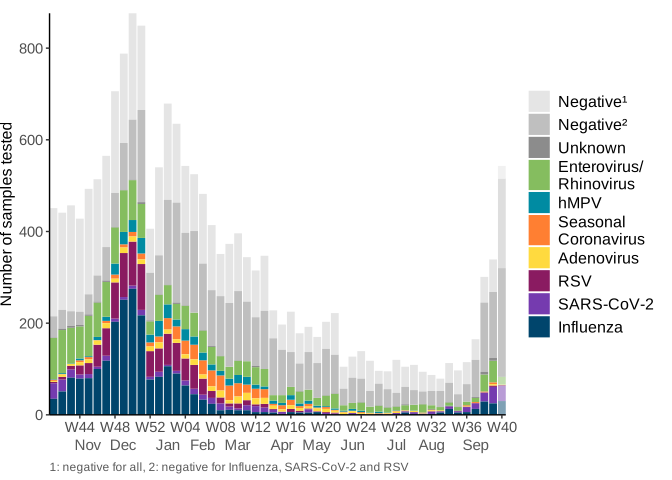
Note 8: unknown category corresponds to samples with no result yet.
Note 9: Due to proximity to one of the testing laboratories, samples from the South West tend to be tested more rapidly than those from other parts of the country therefore the latest week’s data may not be fully representative of the country as a whole and should be interpreted with caution.
Figure 22. Percentage of detected respiratory virus among samples with completed testing for each virus in England by week, GP sentinel swabbing scheme [note 9]
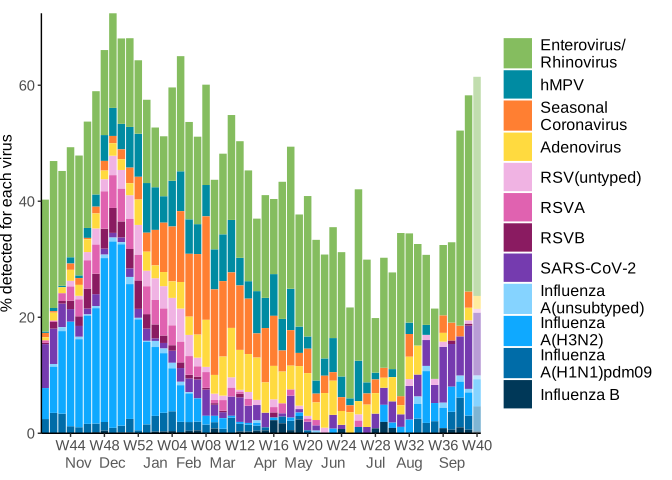
Note 9: Due to proximity to one of the testing laboratories, samples from the South West tend to be tested more rapidly than those from other parts of the country therefore the latest week’s data may not be fully representative of the country as a whole and should be interpreted with caution.
Figure 23. Percentage of detected respiratory viruses among samples with completed testing for each virus in England by age group, GP sentinel swabbing scheme, week 37 to week 40 [note 9]
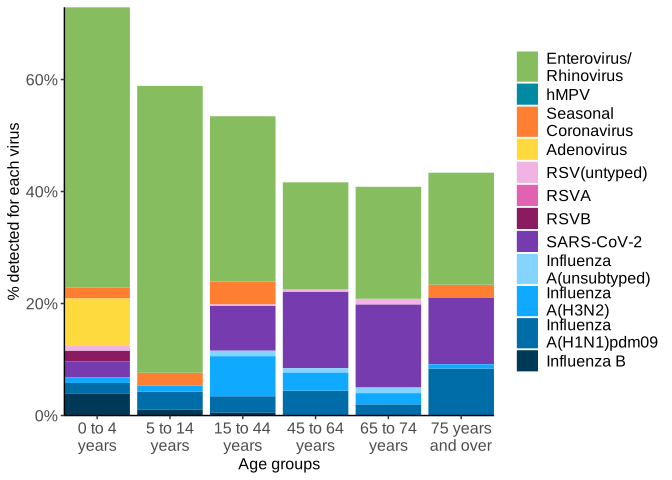
Note 9: Due to proximity to one of the testing laboratories, samples from the South West tend to be tested more rapidly than those from other parts of the country therefore the latest week’s data may not be fully representative of the country as a whole and should be interpreted with caution.
Figure 24. Weekly positivity for SARS-CoV-2, influenza and RSV in England, GP sentinel swabbing scheme [note 5] [note 9]
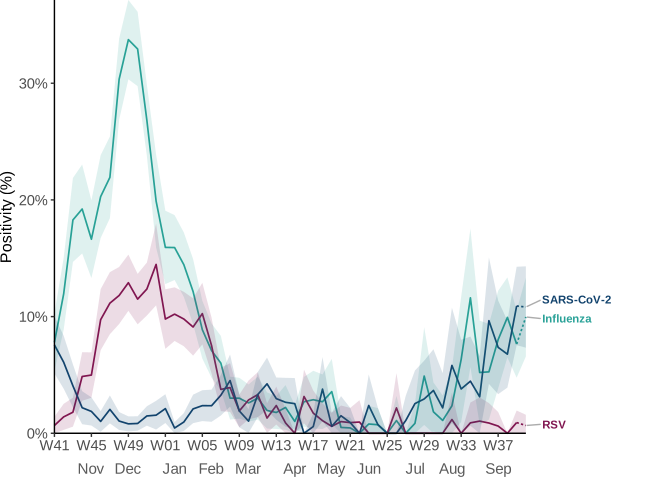
Note 5: shading represents 95% confidence intervals.
Note 9: Due to proximity to one of the testing laboratories, samples from the South West tend to be tested more rapidly than those from other parts of the country therefore the latest week’s data may not be fully representative of the country as a whole and should be interpreted with caution.
Secondary care surveillance
COVID-19 hospital and ICU or HDU admissions
Surveillance of COVID-19 hospitalisations to all levels of care and admissions to intensive care units (ICU) or high dependency units (HDU) are both mandatory, with data required from all acute NHS trusts in England.
SARI Watch data is provisional and subject to retrospective updates. ICU or HDU admission rates may also be affected by lags from admission to hospital to an ICU or HDU ward. Rates are presented per 100,000 trust catchment population.
COVID-19 hospitalisations for all levels of care in week 40 2026 based on 97 NHS trusts in England were as follows:
-
the overall weekly hospital admission rate for COVID-19 increased to 2.04 (compared with 1.75 per 100,000 in the previous week)
-
hospital admission rates for COVID-19 were highest in the West Midlands region (increasing to 3.28 per 100,000 compared with 2.77 in the previous week). See the supplementary graphs and data file for regional breakdowns
-
the highest hospital admission rate for COVID-19 was in those aged 85 years and over (increasing to 20.30 per 100,000 compared with 16.46 in the previous week)
COVID-19 ICU-HDU admissions in week 40 2026 based on 83 NHS trusts in England were as follows:
-
the overall ICU or HDU rate for COVID-19 remained low at 0.06 per 100,000 (compared with 0.05 per 100,000 in the previous week). Note that with low rates in critical care, small random fluctuations may occur
-
ICU or HDU admission rates for COVID-19 were highest in the London region (increasing to 0.14 per 100,000 compared with 0.08 in the previous week). See the supplementary graphs and data file for regional breakdowns
-
the highest ICU or HDU admission rate for COVID-19 was in those aged 85 years and over (increasing to 0.42 per 100,000 compared with 0.10 in the previous week)
Figure 25. Weekly overall COVID-19 hospital admission rates per 100,000 trust catchment population reported through SARI Watch mandatory surveillance, England
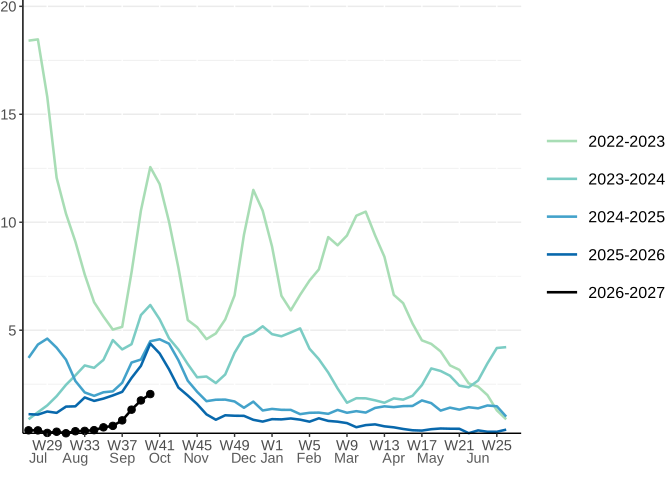
Figure 26. Weekly hospital admission rate by age group for new COVID-19 positive cases reported through SARI Watch mandatory surveillance, England [note 10]
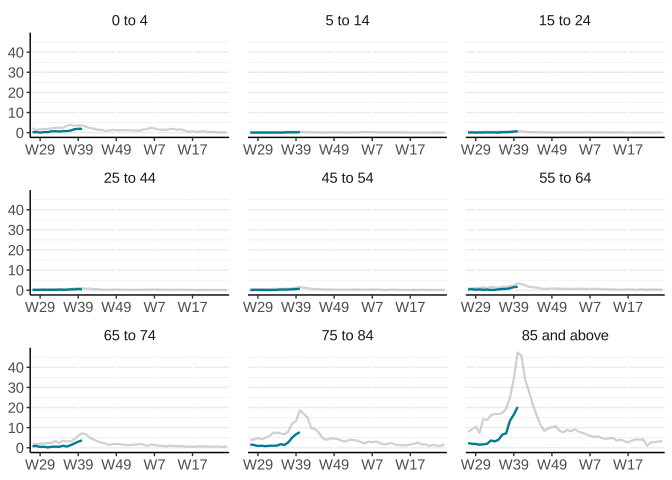
Note 10: the highlighted line corresponds to the most recent 2026 to 2027 season, grey lines correspond to the previous 2025 to 2026 season.
Figure 27. Weekly overall COVID-19 ICU or HDU admission rates per 100,000 trust catchment population reported through SARI Watch mandatory surveillance, England
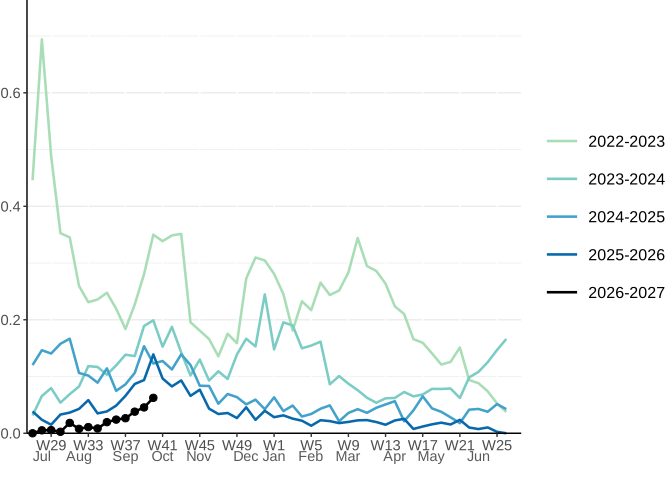
Figure 28. Weekly ICU or HDU admission rate by age group for new COVID-19 positive cases reported through SARI Watch mandatory surveillance, England [note 10]
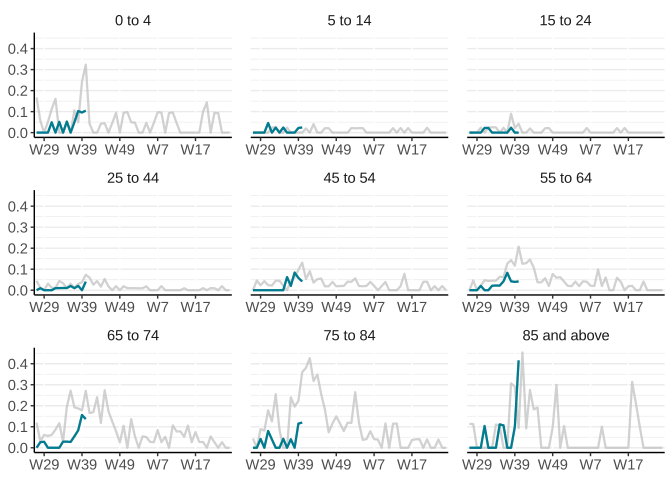
Note 10: the highlighted line corresponds to the most recent 2026 to 2027 season, grey lines correspond to the previous 2025 to 2026 season.
Influenza hospital and ICU or HDU admissions
From the 2026 to 2027 season, surveillance of influenza hospitalisations to all levels of care was expanded to all acute NHS trusts in England as a pilot initiative. Previously this was a sentinel collection involving a small network of contributing NHS trusts. Surveillance of admissions to ICU or HDU for influenza is mandatory with data required from all acute NHS trusts in England.
SARI Watch data is provisional and subject to retrospective updates. Rates are presented per 100,000 trust catchment population.
Influenza hospitalisations to all levels of care in week 40 2026 based on 25 NHS trusts in England were as follows:
-
the overall weekly hospital admission rate for influenza was 1.97 per 100,000. This surveillance formally starts in week 40 so a comparison to the previous week is not possible.
-
this rate is in the baseline impact range (less than 2.15 per 100,000)
-
hospital admission rates for influenza were highest in those aged 85 years and over (11.06 per 100,000)
-
see the respiratory virus section of the data dashboard for regional breakdowns
-
there were 234 new hospital admissions for influenza (219 influenza A(subtype unknown), 6 influenza A(H1N1)pdm09, 1 influenza A(H3N2), and 8 influenza B)
Influenza ICU-HDU admissions in week 40 2026 based on 92 NHS trusts in England were as follows:
-
the overall weekly hospital admission rate for influenza was 0.06 per 100,000. This surveillance formally starts in week 40 so a comparison to the previous week is not possible.
-
this rate is in the baseline impact range (less than 0.09 per 100,000)
-
see the respiratory virus section of the data dashboard for regional breakdowns
-
there was 24 new ICU or HDU admission for influenza (19 influenza A(subtype unknown), 4 influenza A(H1N1)pdm09, 1 influenza A(H3N2), and 0 influenza B)
Figure 29. Weekly overall influenza hospital admission rates per 100,000 trust catchment population with MEM thresholds, reported through SARI Watch surveillance, England
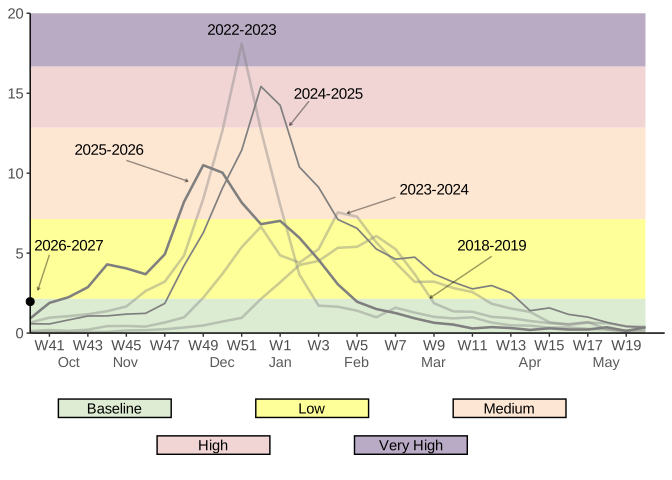
Figure 30. Weekly influenza hospital admissions by influenza type, reported through SARI Watch surveillance, England
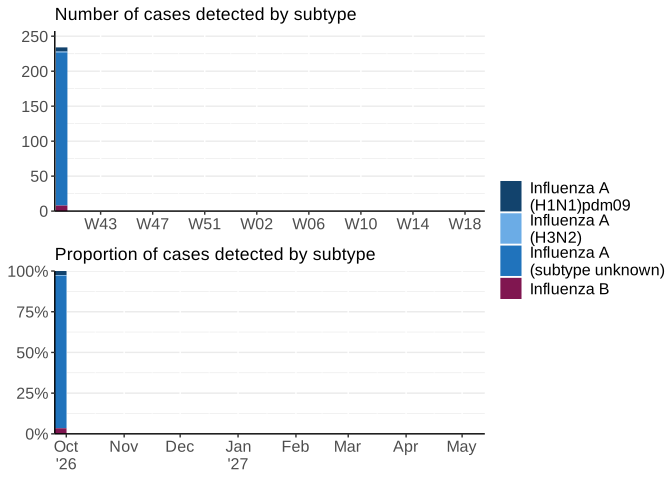
Figure 31. Weekly hospital admission rate by age group for new influenza reported through SARI Watch surveillance, England [note 10]
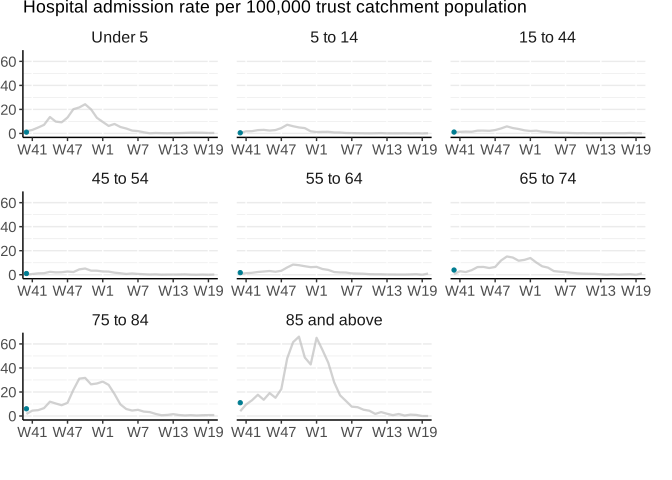
Note 10: the highlighted line corresponds to the most recent 2026 to 2027 season, grey lines correspond to the previous 2025 to 2026 season.
Figure 32. Weekly overall influenza ICU or HDU admission rates per 100,000 trust catchment population with MEM thresholds, reported through SARI Watch mandatory surveillance, England
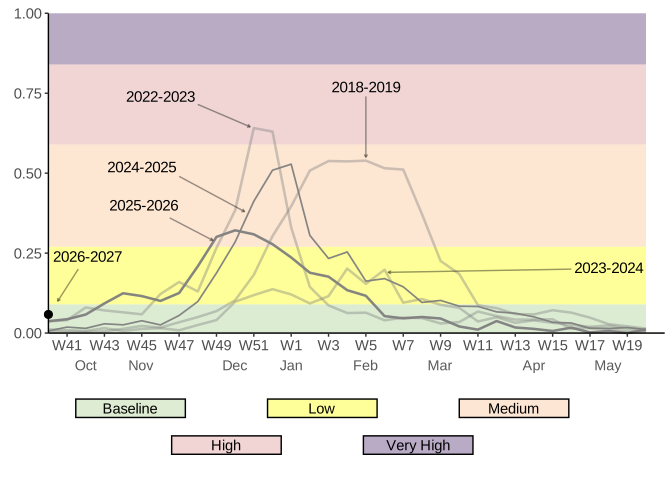
Figure 33. Weekly influenza ICU or HDU admissions by influenza type, reported through SARI Watch mandatory surveillance, England
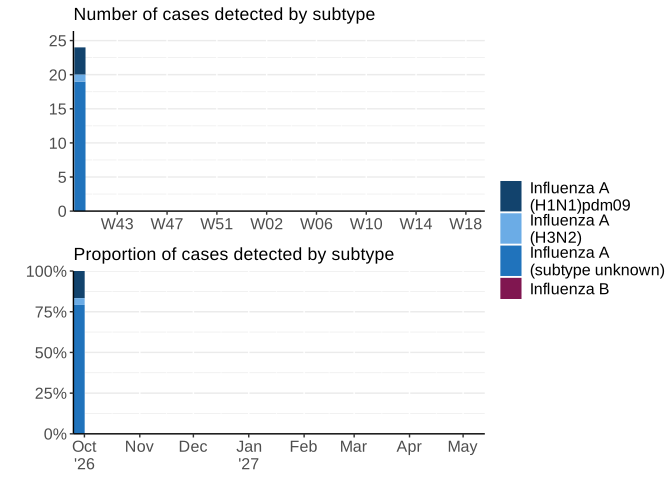
Figure 34. Weekly ICU or HDU admission rate by age group for new influenza cases, reported through SARI Watch mandatory surveillance, England [note 10]
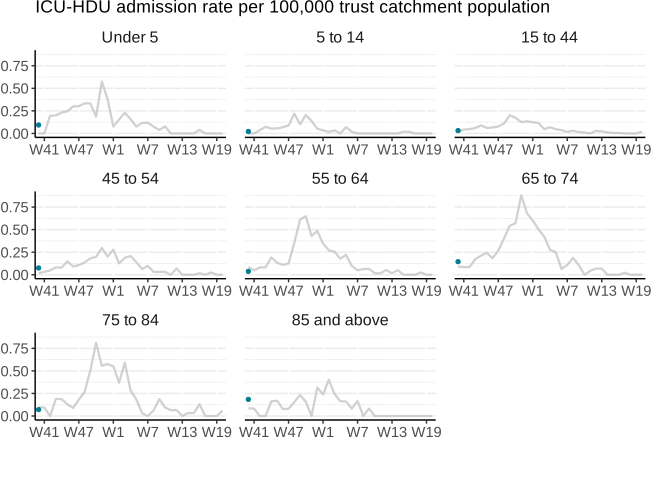
Note 10: the highlighted line corresponds to the most recent 2026 to 2027 season, grey lines correspond to the previous 2025 to 2026 season.
RSV hospital admissions
Surveillance of respiratory syncytial virus (RSV) hospitalisations (excluding ICU or HDU admissions) is based on data from a small sentinel network of acute NHS trusts in England submitting data voluntarily. Trusts submit weekly aggregate counts of new RSV admissions and these are summed and converted to rates per 100,000 trust catchment population by linking to catchment populations of participating trusts in that week.
SARI Watch data is provisional and subject to retrospective updates. Refer to the data quality report for details on the new trust catchment population for calculating rates. The new denominator has also been applied retrospectively to the 2024 to 2025 and 2025 to 2026 seasons for consistency. The data quality report includes further details on SARI Watch RSV data and other collections.
RSV hospitalisations, excluding ICU or HDU admissions, in week 40 2026 were based on 14 sentinel NHS trusts in England:
-
the overall weekly hospital admission rate for RSV remained low at 0.11 per 100,000 (compared with 0.13 per 100,000 in the previous week)
-
in children aged under 5 years, the hospitalisation rate for RSV remained stable at 1.92 per 100,000 (compared with 1.89 per 100,000 in the previous week)
-
in adults aged 75 years and over, the hospitalisation rate for RSV decreased to 0.00 per 100,000 (compared with 0.18 per 100,000 in the previous week). Broken down further, rates were 0.00 per 100,000 in those aged between 75 and 84 years, and 0.00 per 100,000 in those aged 85 years and over in week 40
RSV ICU-HDU admissions in week 40 2026 were based on 14 sentinel NHS trusts in England:
- the overall weekly ICU-HDU admission rate for RSV remained low at 0.01 per 100,000 (compared with 0.01 per 100,000 in the previous week)
Figure 35. Weekly overall hospital admission rates (excluding ICU or HDU) of RSV positive cases per 100,000 population reported through SARI Watch sentinel surveillance, England [note 11]
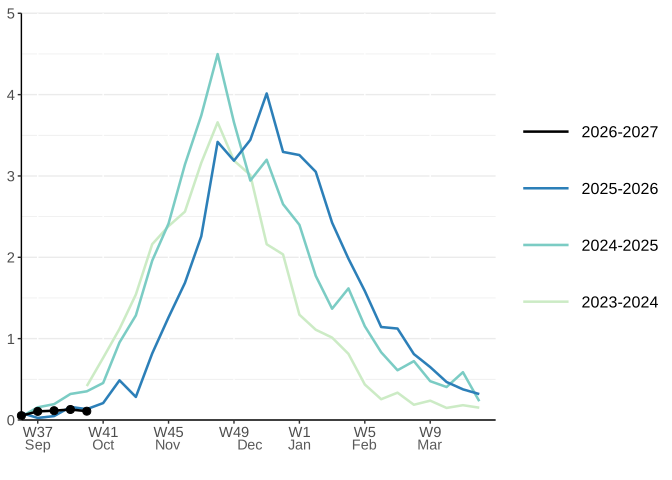
Note 11: Surveillance commenced from week 40 in the 2023 to 2024 season. In subsequent seasons this was from week 36. As the surveillance will conclude in week 12 in the 2026 to 2027 season, the time series is truncated to week 12 for consistency across all seasons.
Figure 36. Weekly hospital admission rates (excluding ICU or HDU) of RSV positive cases per 100,000 population in those aged under 5 years and aged over 75 years reported through SARI Watch sentinel surveillance, England [note 11]
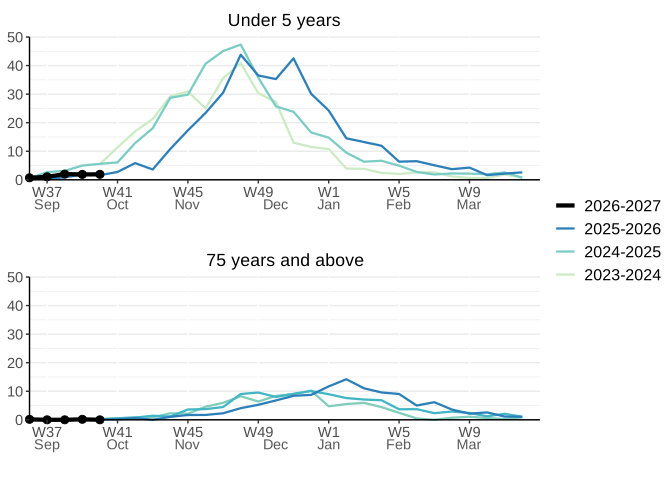
Note 11: Surveillance commenced from week 40 in the 2023 to 2024 season. In subsequent seasons this was from week 36. As the surveillance will conclude at week 12 in the 2026 to 2027 season, the time series has been truncated to week 12 for consistency across all seasons.
Figure 37. Weekly hospital admission rates (excluding ICU or HDU) by age group for RSV cases reported through SARI Watch sentinel surveillance, England [note 10]
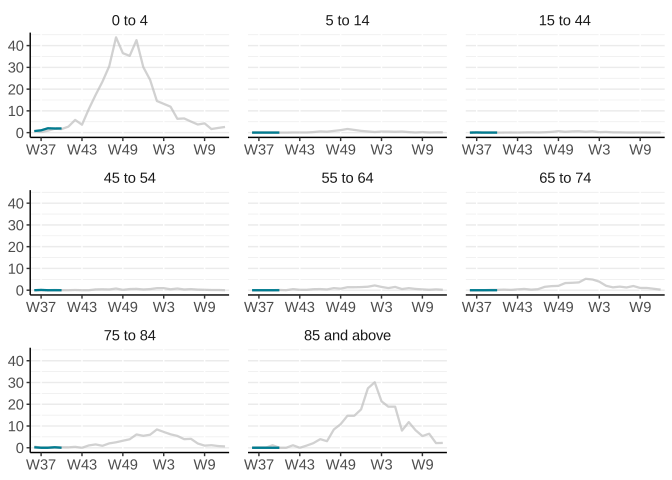
Note 10: the highlighted line corresponds to the most recent 2026 to 2027 season, grey lines correspond to the previous 2025 to 2026 season.
ECMO admissions
Surveillance of extra corporeal membrane oxygenation (ECMO) admissions is based on data from severe respiratory failure (SRF) centres in the UK. Refer to the data quality report for additional information.
SARI Watch data is provisional and subject to retrospective updates (the figure below may vary from those presented in previous reports). Please note that data from week 26 2026 is from SRF units in England only until further notice.
There was one new ECMO admission reported in week 40 2026 in adults:
- due to a suspected ARI
Figure 38. Laboratory confirmed ECMO admissions in adults (COVID-19, influenza and non-COVID-19 confirmed) to severe respiratory failure centres in the UK [note 12]
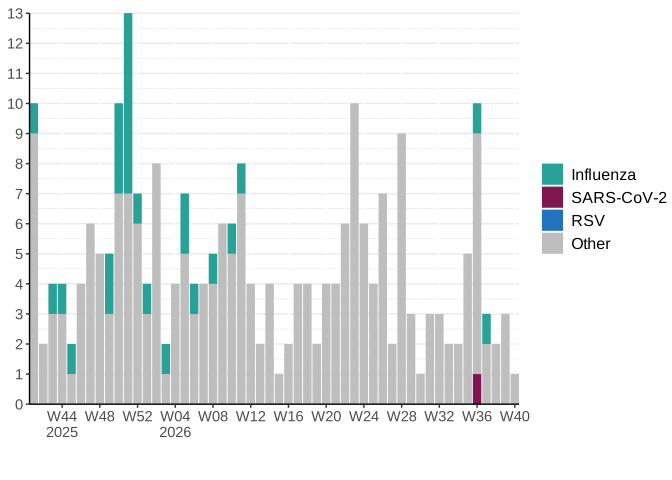
Note 12: The other group includes other viral, bacterial or fungal ARI, suspected ARI, non-infection (such as asthma, primary cardiac and trauma) and sepsis of non-respiratory origin.
Vaccine coverage
COVID-19 vaccine uptake in England
Cumulative data up to the end of week 40 2026 (Sunday 4 October 2026) was extracted from the Immunisation Information System (IIS). Data is extracted on the next working day following the end of reporting week (Monday 5 October 2026). Age is calculated as age on date of extraction.
Data is provisional and subject to change following further validation checks. Any changes to historic figures will be reflected in the most recent publication.
Autumn 2026 campaign
The autumn 2026 data reported below covers any dose administered from 1 October 2026 (ISO Week 40) provided there is at least 20 days from the previous dose. Eligible groups for the campaign are defined in the Green Book chapter on COVID-19. By the end of week 40 2026 (week ending 4 October 2026), 10.2% (606,893 / 5,957,927) of all people aged 75 years and over, and 4.1% (61,899 / 1,523,543) of all people aged under 75 years with a weakened immune system, who are living and resident in England had been vaccinated with an autumn 2026 dose since 1 October 2026 (Figure 39).
Figure 39. Cumulative weekly COVID-19 vaccine uptake by target group in England [note 13]
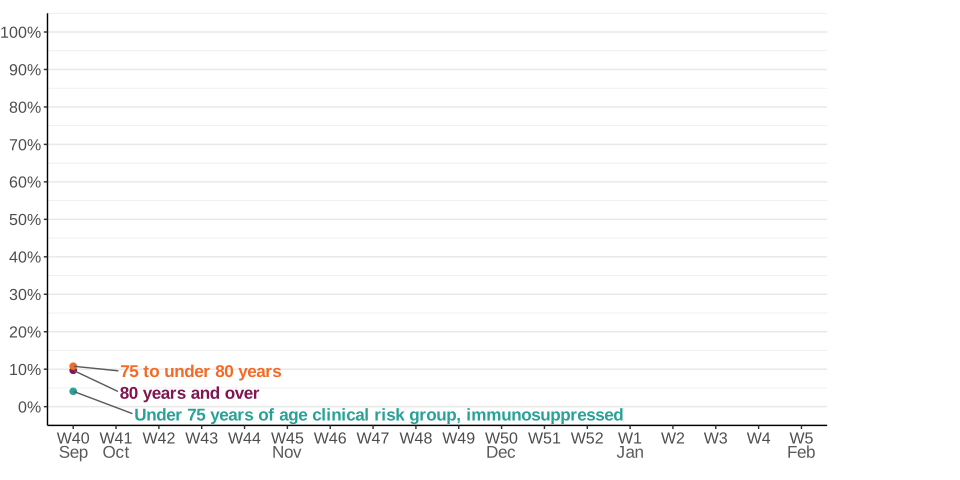
Note 13: the month is taken from the Monday of an international organisation for standardisation (ISO) week.
For data on the real-world effectiveness of the COVID-19 vaccines, see the epidemiology of COVID-19 in England reports.
For COVID-19 management information on the number of COVID-19 vaccinations provided by the NHS in England, see the COVID-19 vaccinations webpage.
For UK COVID-19 daily vaccination figures and definitions, see the Vaccinations section of the UK COVID-19 dashboard.
Influenza vaccination
Influenza vaccine uptake in GP patients
Weekly vaccine uptake data is provisional.
Influenza vaccination is reported by GP practice through the ImmForm website. ImmForm provides a secure online platform for vaccine uptake data collection for several immunisation surveys, including the seasonal influenza vaccine uptake collection. Details can be found at sources of surveillance data for influenza, COVID-19 and other respiratory viruses.
For the 2026 to 2027 season’s vaccination programme, as in the previous two seasons, children and pregnant women have been eligible since 1 September. For this current season and the previous two season (2026 to 2027, 2025 to 2026 and 2024 to 2025 seasons respectively), adult groups (excluding pregnant women) were eligible from 1 October, rather than 1 September as in previous seasons. See the Timing section of the annual flu letter for more information.
Up to the end of week 40 of 2026 (Sunday 4 October 2026), the provisional proportion of people in England who had received an influenza vaccine this season in targeted groups was as follows:
Adults (98.7% of GP practices reporting through ImmForm):
-
4.9% in those aged under 65 years in a clinical risk group
-
16.4% in all pregnant women
-
9.9% in all those aged over 65 years
Children (98.8% of GP practices reporting):
-
16.5% in children aged 2 years
-
16.4% in children aged 3 years
Figure 40. Cumulative weekly influenza vaccine uptake by target group in England [note 14] [note 15]
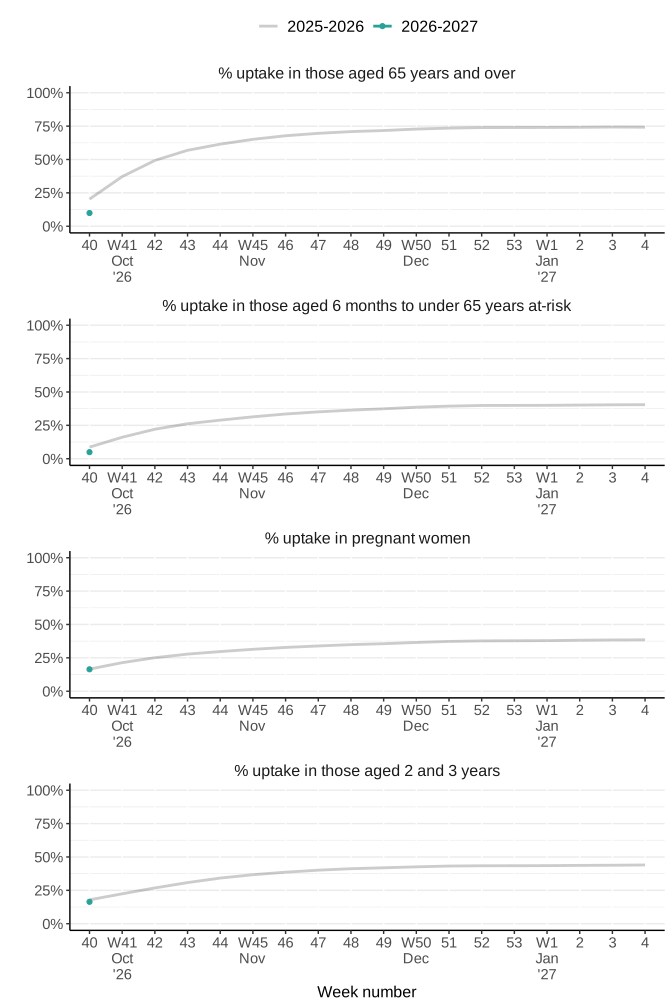
Note 14: On 26 November 2026, monthly vaccine uptake data will be published for the first time this season, which covers influenza vaccinations given between 1 September and 31 October 2026 for GP patients, school-aged-children and frontline healthcare workers.
Note 15: Some data relating to uptake in pharmacies was unavailable or incomplete at the time of analysis; therefore, findings should be interpreted with caution, particularly in those aged 65 years or older, 6 months to under 65 years in risk groups and pregnant women, as results may be subject to change when additional data become available.
International updates
For further information on the global respiratory virus situation see the World Health Organization (WHO) Global respiratory virus weekly updates.
For further information on respiratory viruses in Europe see the European Respiratory Virus Surveillance Summary (ERVISS).
For further information on respiratory viruses in the Americas see Pan American Health Organisation Influenza, SARS-CoV-2, RSV and other respiratory viruses.
For further information on respiratory viruses in the United States of America see Centre for Disease Control respiratory virus activity levels.
For further information on respiratory viruses in Canada see the Canadian respiratory virus surveillance report.
For further information on respiratory viruses in Australia see Australian Respiratory Surveillance Reports.
Data sources and methodology
For additional information regarding data sources, see the data quality report.
Background information
Related statistics
National flu and COVID-19 surveillance reports: 2025 to 2026 season
Weekly national flu reports (historic)
Influenza in the UK, annual epidemiological reports
Epidemiology of COVID-19 in England
Weekly all-cause mortality surveillance report
Further information and contact details
Feedback and contact information
To provide feedback and for all queries relating to this document, contact respdsr.enquiries@ukhsa.gov.uk
Official statistics
Our statistical practice is regulated by the Office for Statistics Regulation (OSR). OSR sets the standards of trustworthiness, quality and value in the Code of Practice for Statistics that all producers of official statistics should adhere to.
You are welcome to contact us directly by emailing respdsr.enquiries@ukhsa.gov.uk with any comments about how we meet these standards.
Alternatively, you can contact OSR by emailing regulation@statistics.gov.uk or via the OSR website.
UKHSA is committed to ensuring that these statistics comply with the Code of Practice for Statistics. This means users can have confidence in the people who produce UKHSA statistics because our statistics are robust, reliable and accurate. Our statistics are regularly reviewed to ensure they support the needs of society for information.