Spotlight on sexually transmitted infections in Yorkshire and Humber: 2025 data
Updated 8 October 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/sexually-transmitted-infections-yorkshire-and-humber-data/spotlight-on-sexually-transmitted-infections-in-yorkshire-and-humber-2025-data
Summary
STIs represent an important public health problem in Yorkshire and Humber. This report aims to provide key intelligence about STIs in the Yorkshire and Humber region of England. It presents data on new diagnoses, consultations and screening in sexual health services (SHS) and the National Chlamydia Screening Programme (NCSP).
Data is mostly focused on activity in Yorkshire and Humber in 2025. Where appropriate, data for the past 5 or 10 years is provided to understand trends and data from other regions and England as a whole is presented for comparison. Data at the upper tier local authority level is also presented. For a broader context see Sexually transmitted infections and screening for chlamydia in England 2025.
Some data is provided over a 10-year period to highlight trends relative to 2019 or earlier to allow for a comparison to sexual health service provision and sexually transmitted infection (STI) diagnoses prior to the COVID-19 pandemic during 2020 and 2021. Whilst the data shows that access to services have improved following the impact of the COVID-19 pandemic, it is important to note that trends in STI testing, diagnoses and patterns of sexual behaviour remain difficult to interpret between 2019 and 2022.
25,823 new STIs were diagnosed in the Yorkshire and Humber population in 2025, a rate of 455 diagnoses per 100,000, this is a decrease of 9% from 28,314 new STIs in 2024. Of all UK Health Security Agency (UKHSA)’s regions Yorkshire and Humber has the fourth highest rate of new STIs in England, the same position as in 2024. Rates by upper tier local authority ranged from 250 new STI diagnoses per 100,000 in North Yorkshire to 647 new STI diagnoses per 100,000 in City of Kingston upon Hull. This is a change from 2024, when the local authority with the highest rate was Leeds, and City of Kingston upon Hull was third highest of the Yorkshire and Humber local authorities.
Overall, there was a decrease in the number of new STIs diagnosed in the Yorkshire and Humber in 2025. 4 of the 5 main STIs saw decreases whilst syphilis diagnoses increased by <0.5%. Gonorrhoea decreased by 16%, chlamydia decreased by 12%, genital herpes decreased by 3% and genital warts decreased by 7%. This is broadly consistent with what is being seen nationally, although syphilis numbers nationally have seen a 13.5% decrease (see Sexually transmitted infections and screening for chlamydia in England, 2025).
Rates of new STIs vary slightly between men and women (434 and 415 per 100,000, respectively). Where gender and sexual orientation are known, gay, bisexual and other men who have sex with men (GBMSM) account for 16% of the Yorkshire and Humber population diagnosed with a new STI excluding chlamydia diagnoses reported via CTAD (57% of those diagnosed with syphilis and 49% of those diagnosed with gonorrhoea).
STIs disproportionately affect young people. Yorkshire and Humber residents aged between 15 and 24 years accounted for 44% of all new STI diagnoses in 2025. A steep decline has been seen in genital warts diagnosis rates in females aged 15 to 19 following the introduction in 2008 of vaccination against human papillomavirus (HPV), the virus which causes genital warts, for girls. Recent years have seen fluctuating rates though, with a 98% decrease in Yorkshire and Humber from 2016 to 2025.
UKHSA recommends that local areas should be working towards achieving a chlamydia detection rate no lower than 3,250 per 100,000 among women aged 15 to 24 years and this is an indicator in the Public Health Outcomes Framework. In 2025, the chlamydia detection rate among Yorkshire and Humber women aged 15 to 24 years was 1,362 per 100,000 this is a small decrease from 1,661 per 100,000 in 2024.
Amongst those with known ethnicity, the White ethnic group has the highest number of new STI diagnoses in Yorkshire and Humber: 18,177 (78%). Although only 5% of new STIs are in the Black African ethnic group, they have the highest rate of 1,148 (excluding combined other ethnic groups) which is 3 times the rate seen in the White ethnic group (388 per 100,000). The highest rate of new diagnoses is in the all other black ethnic groups combined at 1,600 per 100,000. Where country of birth was known, 84% of the Yorkshire and Humber population diagnosed with a new STI in 2025 (excluding chlamydia diagnoses reported via CTAD) were UK born.
Overall, the highest rates of new diagnoses per 100,000 were seen in females aged 20 and 24 years and in the black African ethnic group (excluding combined other ethnic groups). These groups may benefit from more targeted health promotion messaging.
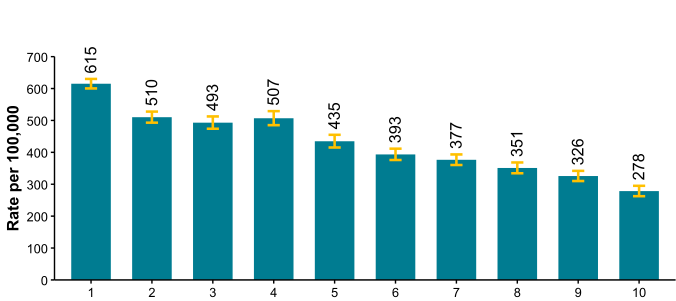
Deprivation remains strongly associated with rates of STIs in Yorkshire and Humber. The rate of new STIs among people who lived in the most deprived areas (615 per 100,000) was 2.2 times higher than the rate for people who live in the least deprived areas (278 per 100,000).
The distribution of consultations across the service types has stabilised in the last 3 years following changes in service use during and after the pandemic. The number of consultations at sexual health services (SHSs) in Yorkshire and Humber has continued to decrease from the peak of 348,958 in 2023 to 314,809 in 2025. This decrease was seen in face-to-face, online and telephone appointments, with the largest decrease (33%) in the number of telephone consultations.
Prevention messages
Prevention messages include:
Sexual health clinics are free, confidential and available to everyone. They provide testing, post-exposure prophylaxis and treatment for STIs and HIV, as well as vaccination and contraception.
Using condoms consistently and correctly with new or casual partners protects against HIV and other STIs.
Testing is recommended if you have had sex without a condom with a new or casual partner in the last 3 months, or if a partner has tested positive for an STI. In addition:
- women and other people with a womb aged under 25 who are sexually active should have a chlamydia test after sex with a new partner or annually
- gay and bisexual men (GBMSM) with new or casual partners should test for HIV and STIs annually or every 3 months if having sex without condoms with new or casual partners
Prevention medications (known as pre- and post-exposure prophylaxis) can prevent HIV and some STIs:
- doxycycline post-exposure prophylaxis (doxyPEP) is recommended to people at risk of syphilis to reduce their chance of infection. DoxyPEP is available at specialist sexual health clinics
- HIV pre-exposure prophylaxis (PrEP) reduces an individual’s risk of getting HIV. PrEP is available from specialist sexual health clinics
- HIV post-exposure prophylaxis (PEP) can be taken after sex to reduce the risk of getting HIV. PEP is available for free from most sexual health clinics and most emergency departments
Vaccination can prevent some STIs and blood-borne viruses:
- GBMSM can get the hepatitis A and hepatitis B vaccines from specialist sexual health clinics. These vaccines are also available for other people with a higher risk of exposure to these viruses
- GBMSM aged 45 years and younger can get the human papillomavirus (HPV) vaccine from specialist sexual health clinics. This protects against genital warts and some forms of cancer
- GBMSM who have a recently had multiple sexual partners or an STI and other people at higher risk are eligible for a meningococcal B disease vaccine (4CMenB) which can protect against gonorrhoea
- mpox vaccination is available for people at increased risk, including GBMSM who have recently had multiple sexual partners
- hepatitis B and HPV vaccines are also part of the routine childhood vaccination program. Catch-up vaccines are available for people who missed them at school
STIs in Yorkshire and Humber
Overview
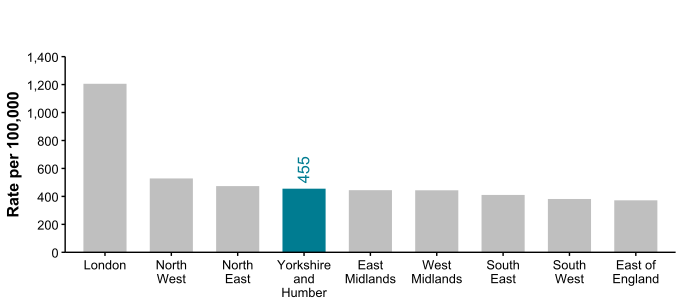
Figure 1. New STI diagnosis rates by UKHSA region of residence, England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 1 is a column chart showing new STI diagnosis rates by English UKHSA region for the year 2025. Rates are per 100,000 population and are not age-restricted or adjusted. UKHSA regions are shown in descending order with Yorkshire and Humber represented by a teal shading.
The chart shows that London reported the highest rate of new STI diagnoses per 100,000 population in 2025, followed by the North West and North East. Yorkshire and Humber has the fourth highest rate of new STI diagnoses (455 per 100,000).
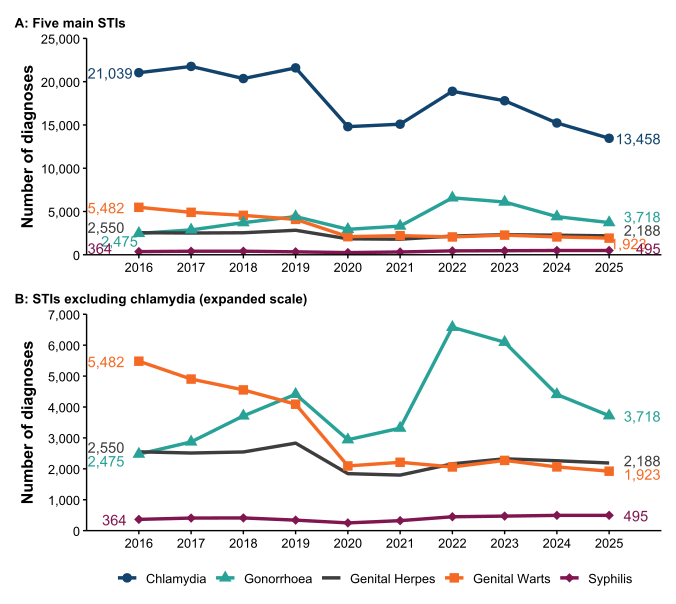
Figure 2. Number of diagnoses of the 5 main STIs (Yorkshire and Humber, 2016 to 2025): A) all 5 STIs B) excluding chlamydia (expanded scale)
Data sources: GUMCAD, CTAD.
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
Figure 2a and 2b are 2 line charts showing trends in the number of diagnoses of the 5 main STIs (chlamydia, genital herpes, genital warts, gonorrhoea and syphilis) in Yorkshire and Humber residents from 2016 to 2025. Figure 2a shows all 5 main STIs, figure 2b excludes chlamydia.
The charts show chlamydia (13,458 diagnoses in 2025) as the top line in the chart, which reflects the fact that this is the most prevalent STI in the Yorkshire and Humber population and accounts for 52% of new STI diagnoses in 2025.
Gonorrhoea is the second most prevalent STI in the Yorkshire and Humber population in 2025 (3,718) accounting for 14% of new STI diagnoses. Following a sharp increase in the number of gonorrhoea diagnoses between 2021 and 2022 (3,316 compared to 6,579, 98% increase), the number has decreased in 2025 and is now below pre-pandemic levels.
In 2025 the number of syphilis diagnoses is similar to 2024 with 495 diagnoses. This follows a continuous year on year increase in syphilis diagnoses since 2016 (excluding the pandemic period) when the number of diagnoses was 364.
The number of genital herpes (2,188) and genital warts (1,923) have decreased compared to 2024 (2,261 and 2,062, respectively).
Table 1. Percentage change in new STI diagnoses, Yorkshire and Humber
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 21,593 | 15,227 | 13,458 | -38% | -12% |
| Genital herpes | 2,831 | 2,261 | 2,188 | -23% | -3% |
| Genital warts | 4,090 | 2,062 | 1,923 | -53% | -7% |
| Gonorrhoea | 4,412 | 4,405 | 3,718 | -16% | -16% |
| Syphilis | 340 | 494 | 495 | 46% | <0.5% change |
| Other | 4,268 | 3,865 | 4,041 | -5% | 5% |
| All new STIs | 37,534 | 28,314 | 25,823 | -31% | -9% |
Data sources: GUMCAD, CTAD.
See notes for Figure 2. See New STIs section for a list of diagnoses that are included in the other STIs.
Table 1 shows the number of diagnoses of each of the 5 main STIs (these correspond to the final points on the lines in Figures 2a and 2b), new STIs and other STIs for Yorkshire and Humber residents in 2019, 2024 and 2025. 2 columns follow these. The first shows percentage change from 2019 (a pre-pandemic reference point) to 2025, while the second shows percentage change from 2024 to 2025. Together these columns summarise the changes seen in the previous chart. This is especially useful for less common STIs such as syphilis as changes for these STIs can be hard to see in charts which are scaled to include infections with much higher numbers, such as chlamydia.
Table 1 shows that between 2024 and 2025 new STI diagnoses decreased by 9%. Percentage changes between 2024 and 2025 for each STI were varied, with the greatest changes being a 16% decrease for gonorrhoea and a 12% decrease for chlamydia. Only diagnoses for syphilis and other STIs increased between 2024 and 2025 (<0.5% and +5%).
Over the 6 year period from 2019 to 2025 there have been more substantial changes, with significant decreases for all STIs except syphilis which has increased by 46%. Notable decreases were seen in the number of diagnoses of genital warts and chlamydia (-53% and -38%). It is important to note the impact of COVID-19 on sexual health services and individuals’ behaviour during this time.
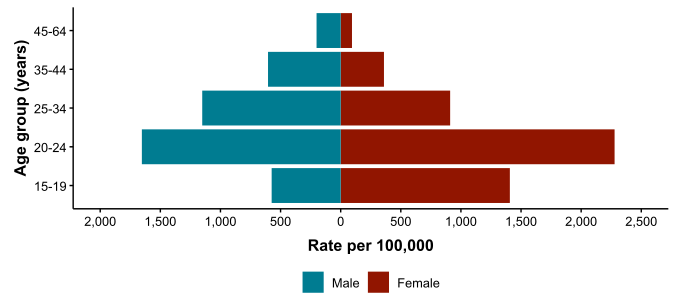
Figure 3. Rates of new STIs per 100,000 by age group (for those aged 15 to 64 years only) and gender, Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 3 is a type of bar chart called an age-sex pyramid displaying the rate of new STI diagnoses in Yorkshire and Humber residents in 2025 by age group and gender (male compared to female). Rates are by 100,000 population in each group. 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years, 45 to 64 years. Data on those aged less than 15 years is not presented given the high sensitivity of this data. Rates for those aged 65 or older are withheld to ensure that no deductive disclosure is possible for the less than 15 years age group. The proportion of STIs in those aged less than 15 years and those older than 64 years is very low accounting for 1% of diagnoses in 2025.
The chart shows that rates of new STIs per 100,000 population in Yorkshire and Humber in 2025 were highest in those aged 20 to 24 years for both females and males (2,278 and 1,654 per 100,000 respectively), followed by 15 to 19 year olds in females (1,407) and 25 to 34 year olds in males (1,152).
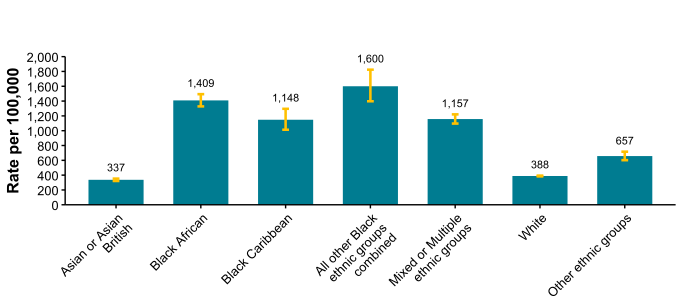
Figure 4. Rates of new STIs per 100,000 by ethnic group, Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021.
Figure 4 is a column chart displaying the rate of new STI diagnoses in Yorkshire and Humber residents in 2025 by ethnic group. Rates are by 100,000 population in each group. 5 categories of ethnic group are displayed: Asian or Asian British, Black African, Black Caribbean, Mixed or Multiple ethnic groups and White. There are also 2 combined other groups, all other Black ethnic groups and other ethnic groups.
The chart shows that the rate of new STIs per 100,000 is highest in all other Black ethnic groups at 1,600 per 100,000 population. The second highest is black African at 1,409 per 100,000.
Table 2. Percentage of new STI diagnoses by ethnic group, Yorkshire and Humber, 2025
| Ethnic group | Number | Percentage (excluding unknown) |
|---|---|---|
| Asian or Asian British | 1,641 | 7% |
| Black African | 1,140 | 5% |
| Black Caribbean | 261 | 1% |
| All other Black ethnic groups combined | 224 | 1% |
| Mixed or Multiple ethnic groups | 1,354 | 6% |
| White | 18,177 | 78% |
| Other ethnic groups | 520 | 2% |
| Unknown | 2,506 |
Data sources: GUMCAD, CTAD and ONS Census 2021.
Table 2 shows the number and percentage of new STI diagnoses in Yorkshire and Humber residents in 2025 by ethnic group.
Table 2 shows that of the 23,317new STI diagnoses where the ethnic group was provided, the majority were in people of white ethnicity, followed by Asian or Asian British (78% and 7% respectively). Ethnicity was not recorded for 2,506 new diagnoses, highlighting the need to understand why there is this gap in ethnicity data collection.
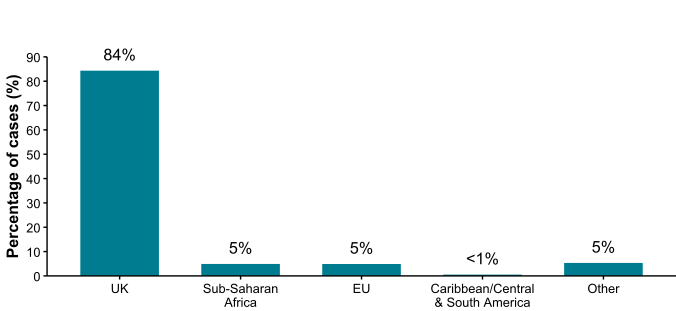
Figure 5. Percentage of new STI diagnoses by world region of birth [note], Yorkshire and Humber, 2025
Data source: GUMCAD data only.
Note: data on country of birth is not collected by CTAD. All information about world region of birth is based on diagnoses made in specialist and non-specialist services which report to GUMCAD.
Figure 5 is a column chart showing the proportion of Yorkshire and Humber residents who were diagnosed with a new STI in 2025 by their world region of birth. 4 categories are displayed: UK, European Union (EU), sub-Saharan Africa, Caribbean and Central and South America. All other world regions of birth are combined given the small numbers in the Yorkshire and Humber.
The chart shows that the majority (84%) of those diagnosed with a new STI in 2025 were born in the UK. Of the remaining 16%, 5% were born in the EU, 5% in sub-Saharan Africa and less than 1% in the Caribbean or Central and South American region. The remaining 5% of diagnoses were among individuals born in other world regions not displayed in the chart.
Figure 6. Rates of new STIs per 100,000 by decile of deprivation [note], Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Index of Multiple Deprivation and Census 2021 mid-year estimates.
Note: deciles run from 1 to 10 in order of decreasing deprivation, with 1 being the decile for the most deprived area. Deprivation is based on 2021 LSOAs, which are available for 96% of GUMCAD data reported in 2025.
Figure 6 is a column chart which shows the rate of new STI diagnoses in Yorkshire and residents is 2025 by decile of deprivation. Deciles run from 1 to 10 in order of decreasing deprivation. Rates are by 100,000 population in each decile.
The chart shows that the rate of new STI diagnoses per 100,000 population decreases with the decile of deprivation. Those in decile 1 have the highest rate of new STI diagnoses at 615 per 100,000, whilst those in decile 10 have the lowest rate of 278 per 100,000.
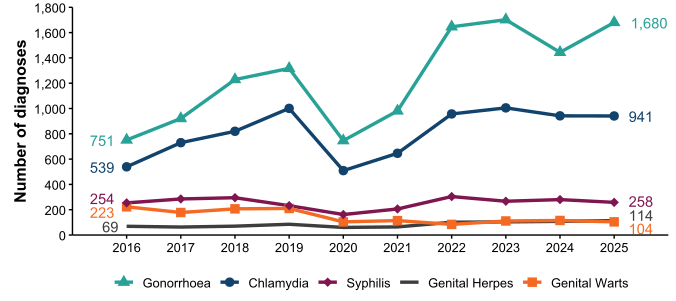
Figure 7. Diagnoses of the 5 main STIs among GBMSM [note], Yorkshire and Humber, 2016 to 2025
Data source: GUMCAD data only.
Note: data on sexual orientation is not collected by CTAD. All information about GBMSM is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services.
Figure 7 is a line chart displaying showing trends in the number of diagnoses of the 5 main STIs (chlamydia, genital herpes, genital warts, gonorrhoea and syphilis) among GBMSM in Yorkshire and Humber from 2016 to 2025.
This chart shows that amongst GBMSM, the largest number of diagnoses are for gonorrhoea. Between 2024 and 2025 there has been an increase in diagnoses of gonorrhoea (+16%) and genital herpes (+6%) amongst GBMSM. Diagnoses in the other 3 main STIs have decreased in 2025. Over the longer time period between 2016 and 2025 the number of diagnoses for 4 of the 5 main STIs has increased, with a decrease in genital wart diagnoses. Data in 2020 and 2021 should be interpreted with caution due to the impact of the COVID-19 pandemic.
Table 3. Percentage change in new STI diagnoses among GBMSM [note], Yorkshire and Humber
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 1,001 | 942 | 941 | -6% | <0.5% change |
| Genital herpes | 85 | 108 | 114 | 34% | 6% |
| Genital warts | 210 | 115 | 104 | -50% | -10% |
| Gonorrhoea | 1,317 | 1,444 | 1,680 | 28% | 16% |
| Syphilis | 232 | 280 | 258 | 11% | -8% |
| Other | 358 | 376 | 386 | 8% | 3% |
| All new STIs | 3,203 | 3,265 | 3,483 | 9% | 7% |
Data source: GUMCAD data only.
Note: see notes for Figure 7 (including asterisk). See New STIs section for a list of diagnoses that are included in the other STIs.
Table 3 shows the number of diagnoses of each of the 5 main STIs, other STIs and new STIs among GBMSM in 2019, 2024 and 2025. 2 columns follow this one. The first shows percentage change from 2019 (a pre-pandemic reference point) to 2025, while the second shows percentage change 2024 to 2025. Together these columns summarise the changes seen in the previous chart. This is especially useful for less common STIs as changes for these can be hard to see in charts which are scaled to include infections with much higher numbers.
Table 3 shows that between 2024 and 2025 the number of new STI diagnoses in GBMSM has increased by 7%. The number of new gonorrhoea, genital herpes and other diagnoses have increased while the number of genital warts and syphilis diagnoses have decreased. Chlamydia diagnoses have remained stable.
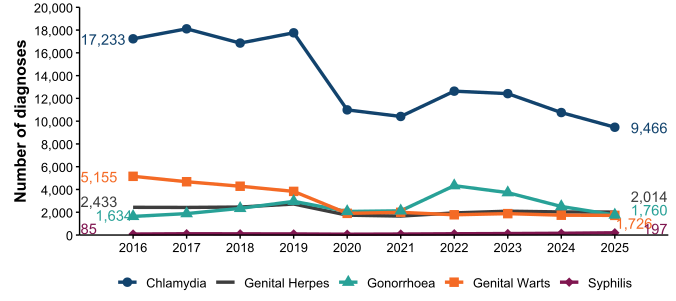
Figure 8. Diagnoses of the 5 main STIs among heterosexual men and all women [note], Yorkshire and Humber, 2016 to 2025
Data source: GUMCAD data only.
Note: data on sexual orientation is not collected by CTAD. All information here is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services. Cases are defined here as GUMCAD records where gender is specified as male and sexual orientation is specified as heterosexual, or gender was specified as female, or gender was not specified but orientation was specified as heterosexual. GUMCAD records where sexual orientation was not specified for males or unknown gender individuals are excluded.
Figure 8 is a line chart displaying trends in the number of diagnoses of the 5 main STIs (chlamydia, genital herpes, genital warts, gonorrhoea and syphilis) among heterosexual men and all women in Yorkshire and Humber between 2016 and 2025.
The chart shows that amongst heterosexual men and all women the most common STI is chlamydia. Between 2016 and 2025 there has been an increase in the number gonorrhoea (from 1,634 to 1,760) and syphilis (from 85 to 197) diagnoses. The number of chlamydia, genital warts and genital herpes diagnoses have decreased. Data in 2020 and 2021 should be interpreted with caution due to the impact of the COVID-19 pandemic.
Table 4. Percentage change in new STI diagnoses among heterosexual men and all women [note], Yorkshire and Humber
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 17,759 | 10,756 | 9,466 | -47% | -12% |
| Genital herpes | 2,724 | 2,027 | 2,014 | -26% | -1% |
| Genital warts | 3,831 | 1,741 | 1,726 | -55% | -1% |
| Gonorrhoea | 2,958 | 2,505 | 1,760 | -41% | -30% |
| Syphilis | 95 | 153 | 197 | 107% | 29% |
| Other | 3,831 | 3,188 | 3,480 | -9% | 9% |
| All new STIs | 31,198 | 20,370 | 18,643 | -40% | -8% |
Data source: GUMCAD data only.
Note: see notes for Figure 8 (including asterisk). See New STIs section for a list of diagnoses included in the other STIs.
Table 4 shows the number of diagnoses of each of the 5 main STIs, other STIs and new STIs among heterosexuals and all women in 2019, 2024 and 2025. 2 columns follow this one. The first shows percentage change from 2019 (a pre-pandemic reference point) to 2025, while the second shows percentage change from 2024 to 2025. Together these columns summarise the changes seen in the previous chart. This is especially useful for less common STIs as changes for these STIs can be hard to see in charts which are scaled to include infections with much higher numbers.
In 2025 the number of new STI diagnoses among heterosexuals and all women has decreased by 8%. Compared to 2024, the number of new syphilis and other diagnoses have increased while the number of chlamydia, gonorrhoea, genital warts and genital herpes diagnoses have decreased.
Figure 9. Rate of new STI diagnoses per 100,000 by upper tier local authority, Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
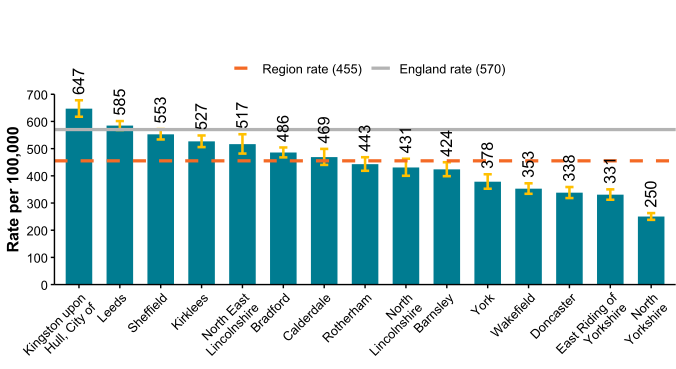
Figure 9 is a column chart which displays the rate of new STI diagnoses in 2025 by Yorkshire and Humber local authority of residence. Rates are by 100,000 population and for all ages. Local authorities are shown in descending order. The overall Yorkshire and Humber and England rates are represented as dashed and solid lines, respectively.
The chart shows that the regional rate of new STI diagnoses for Yorkshire and Humber is 455 per 100,000. This is lower than the England rate of 570 per 100,000. City of Kingston upon Hull and Leeds have a higher rate than both the Yorkshire and Humber and England rates (647 and 585 per 100,000 respectively).
Figure 10. Rate of new STI diagnoses (excluding chlamydia diagnoses among people aged under 25 years) [note] per 100,000 by upper tier local authority, Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
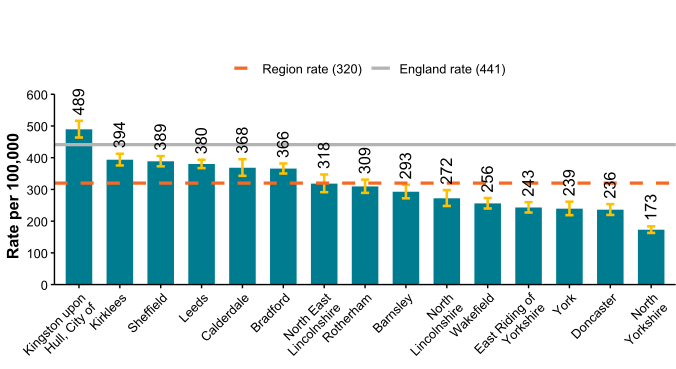
Like Figure 9, Figure 10 is a column chart displaying the rate of new STI diagnoses in 2025 by Yorkshire and Humber local authority, however for this chart, chlamydia diagnoses in those aged less than 25 years are excluded. This is because this age group is actively targeted for screening for chlamydia. Variations in the local implementation of screening may distort the new STI rate and removing diagnoses for the affected age group helps us address this issue. As with the previous chart, the Yorkshire and Humber and England rates are superimposed as dashed and solid lines, respectively.
The charts show that, excluding chlamydia diagnoses in residents under 25 years of age, the regional rate of new STI diagnoses for Yorkshire and Humber is 320 per 100,000 population. This is lower than the England rate of 441 per 100,000. Within Yorkshire and Humber, City of Kingston upon Hull has the highest rate and is above the England rate (489 per 100,000).
Figure 11. Map of new STI rates per 100,000 by upper tier local authority, Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
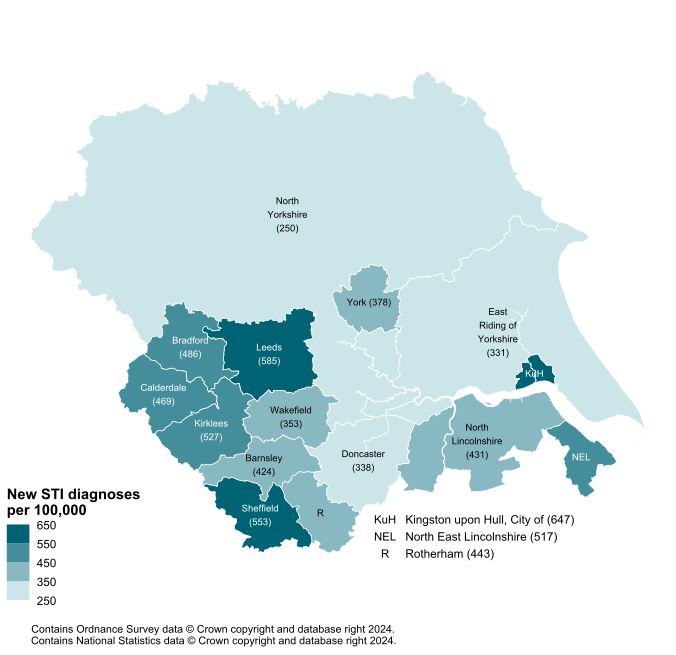
Figure 11 is a map showing the rate of new STI diagnosis per 100,000 population for Yorkshire and Humber local authorities in 2025, as presented in chart 9 above. Again, it shows that City of Kingston upon Hull and Leeds have the highest rates of new STI diagnoses across the region in 2025. North Yorkshire and East Riding of Yorkshire have the lowest rates.
Figure 12. Map of new STI rates per 100,000 by middle super output area (MSOA21), Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
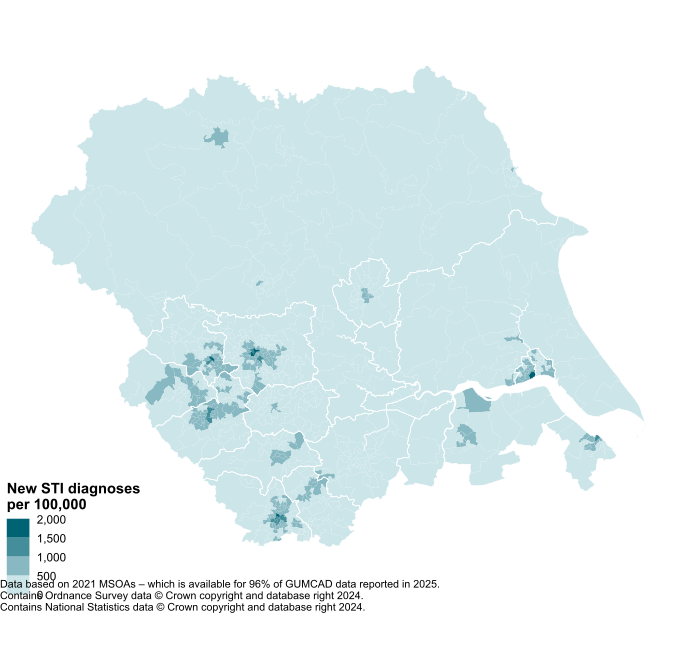
Figure 12 is a map showing the rate of new STI diagnosis per 100,000 population for Yorkshire and Humber MSOA in 2025. This chart highlights that a small number of MSOAs with very high rate can impact the rate at the UTLA level.
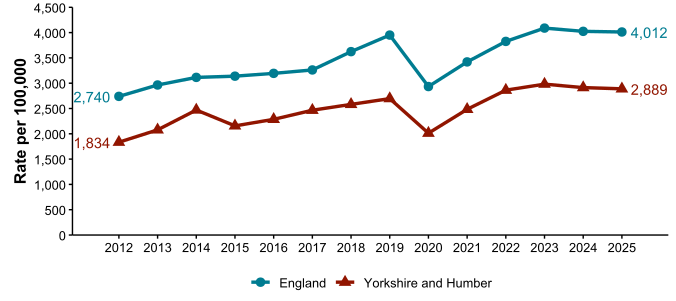
Figure 13. STI testing rate (excluding chlamydia in under 25 year olds) [note] per 100,000, Yorkshire and Humber, 2012 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 13 is a line chart showing trends in the STI testing rate for the Yorkshire and Humber and England from 2012 to 2025. Rates are per 100,000 residents aged 15 to 64 years but excludes tests for chlamydia in those aged less than 25 years, as previously described in Figure 10.
The chart shows that the rate of STI testing, excluding chlamydia in under 25 year olds, has increased similarly in England and Yorkshire and Humber between 2012 and 2025. Both show a decline in 2020 due to the COVID-19 pandemic and a plateauing in recent years.
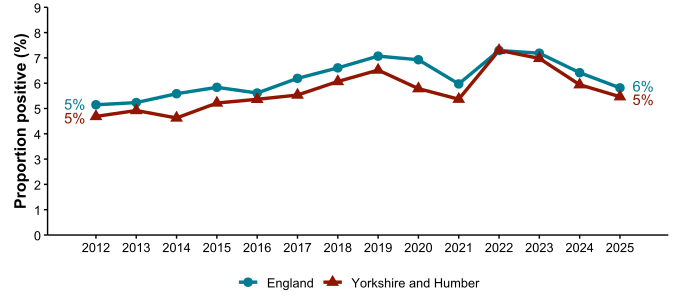
Figure 14. STI testing positivity rate (excluding chlamydia in under 25 year olds) [note], Yorkshire and Humber, 2012 to 2025
Data sources: GUMCAD, CTAD.
Note: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 14 is a line chart showing trends in STI testing positivity for Yorkshire and Humber and England from 2012 to 2025. Whereas Figure 12 showed the STI testing rate, this chart shows the proportion of tests that were positive.
The graph shows that STI positivity, excluding chlamydia in under 25 year olds, has a similar trend for both England and Yorkshire and Humber between 2012 and 2025. Both show an increase in 2022 following the COVID-19 pandemic, followed by a year-on-year decrease to 2025.
Table 5. Number of diagnoses of new STIs by UKHSA region of residence, data source and Sexual Health Service Type, 2025
| X | UKHSA region of residence |
GUMCAD: specialist SHSs |
GUMCAD: non-specialist SHSs [note] |
CTAD | Total |
|---|---|---|---|---|---|
| East Midlands | 13,724 (61%) |
4,076 (18%) |
4,711 (21%) |
22,511 | |
| East of England | 17,420 (68%) |
2,042 (8%) |
6,139 (24%) |
25,601 | |
| London | 79,241 (72%) |
10,529 (10%) |
19,826 (18%) |
109,596 | |
| North East | 9,111 (70%) |
1,703 (13%) |
2,264 (17%) |
13,078 | |
| North West | 31,340 (77%) |
4,738 (12%) |
4,816 (12%) |
40,894 | |
| South East | 28,757 (75%) |
1,649 (4%) |
7,914 (21%) |
38,320 | |
| South West | 14,333 (64%) |
3,777 (17%) |
4,360 (19%) |
22,470 | |
| West Midlands | 20,450 (74%) |
4,133 (15%) |
2,877 (10%) |
27,460 | |
| Yorkshire and Humber | 18,720 (72%) |
1,636 (6%) |
5,467 (21%) |
25,823 |
Data sources: GUMCAD, CTAD.
Note: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
Table 5 summarises new STI diagnoses for each UKHSA English region in 2025 by the surveillance system through which they were reported and, for GUMCAD, whether they were reported by specialist or non-specialist SHSs.
In 2025 London reported the largest number of new STI diagnoses (109,596), followed by the North West and South East (40,894, and 38,320 respectively). In Yorkshire and Humber 72% of diagnoses were reported by specialist SHSs, whilst 6% were reported by non-specialist SHSs.
Table 6. Number of diagnoses of the 5 main STIs by STI, data source and Sexual Health Service type, Yorkshire and Humber, 2025
| 5 main STIs | GUMCAD: specialist SHSs | GUMCAD: non-specialist SHSs [note] | CTAD | Total |
|---|---|---|---|---|
| Chlamydia | 7,179 (53%) |
812 (6%) |
5,467 (41%) |
13,458 |
| Genital herpes | 2,177 (99%) |
11 (1%) |
- | 2,188 |
| Genital warts | 1,913 (99%) |
10 (1%) |
- | 1,923 |
| Gonorrhoea | 2,935 (79%) |
783 (21%) |
- | 3,718 |
| Syphilis | 492 (99%) |
3 (1%) |
- | 495 |
Data sources: GUMCAD, CTAD.
Note: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
Table 6 summarises diagnoses of the 5 main STIs for Yorkshire and Humber residents in 2025 by the surveillance system through which they were reported and, for GUMCAD, whether they were reported by specialist or non-specialist sexual health services (SHSs).
In Yorkshire and Humber all chlamydia diagnoses were made by specialist SHSs as were the majority of all other STI diagnoses. Chlamydia diagnoses were the most common STI diagnoses made in non-specialist SHSs.
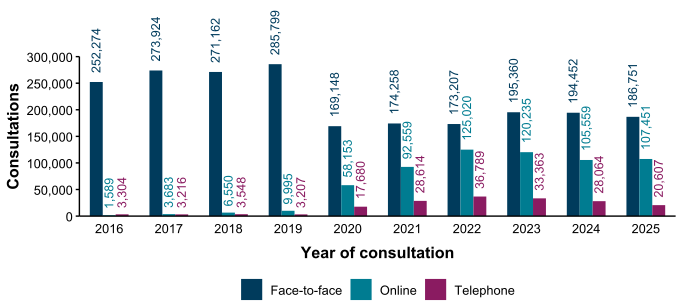
Figure 15. Consultations by service medium, Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Figure 15 is a column chart that shows the number of sexual health consultations for Yorkshire and Humber residents between 2016 and 2025 by consultation medium. 3 categories are presented: face-to-face clinic appointment, online and telephone appointments.
The chart shows that the number of consultations has increased in this 10 year period. Between 2024 and 2025 the number of telephone and face-to-face consultations have decreased.
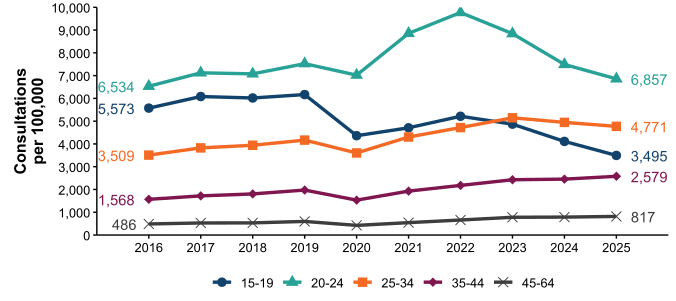
Figure 16. All consultations by age group, Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Figure 16 is a line chart displaying trend lines of all consultations of Yorkshire and Humber residents, by age group between 2016 and 2025. Rates are by 100,000 population in each age group. As in previous figures, 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years and 45 to 64 years.
The chart shows that those aged between 20 and 24 have the highest consultation rates in Yorkshire and Humber. The lowest consultation rates are in those aged 45 to 64. In 2025 there has been a decrease in consultations for all age groups except the 35 to 44 age group which has seen a continuing increase that began in 2020.
Chlamydia
Figure 17. Number of chlamydia diagnoses, Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, CTAD.
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
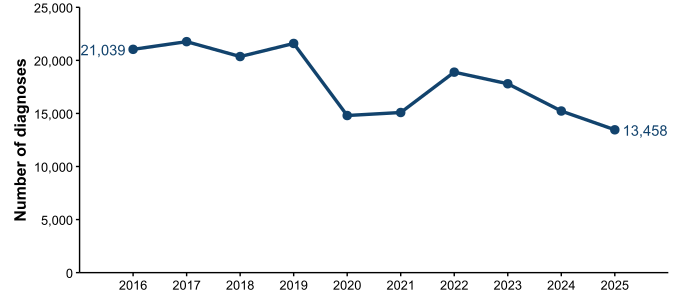
Figure 17 is a line chart showing the trend in the number of diagnoses of chlamydia, in Yorkshire and Humber residents from 2016 to 2025.
Between 2016 and 2025 the number of chlamydia diagnoses have decreased 36% from 21,039 to 13,458. Data in 2020 and 2021 should be interpreted with caution due to the impact of the COVID-19 pandemic.
Figure 18. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only), Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
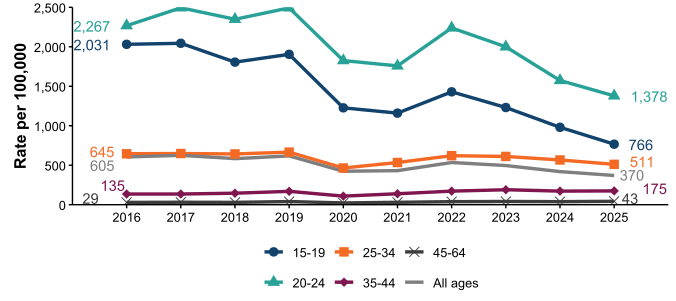
Figure 18 is a line chart displaying trend lines of the rate of chlamydia diagnoses in Yorkshire and Humber residents by age group over the past 10 years (2016 to 2025). Rates are by 100,000 population in each age group. As in previous charts 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years and 45 to 64 years.
The chart shows that in 2025 the 20 to 24 year age group continue to have the highest rate per 100,000 (1,378), followed by the 15 to 19 year age group (766). Compared to 2024, chlamydia rates declined across most age groups, with the largest drops in younger cohorts (20 to 24 years: −12%, 15 to 19 years: −22%).
Figure 19. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only) and gender, Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
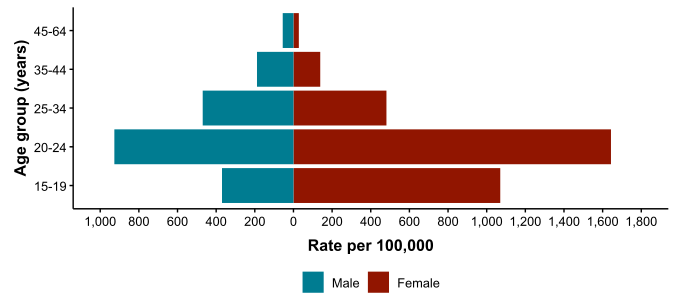
Figure 19 is an age-sex pyramid displaying the rate of chlamydia diagnoses in Yorkshire and Humber residents in 2025 by age group and gender (male compared to female). Rates are by 100,000 population in each group. As in previous graphs 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years, 45 to 64 years.
The chart shows that the highest rates in both females and males were in those aged 20 to 24 years, followed by 15 to 19 year olds in females and 25 to 34 year olds in males.
Figure 20. Chlamydia detection rate per 100,000, females aged 15 to 24 years by upper tier local authority of residence, Yorkshire and Humber, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
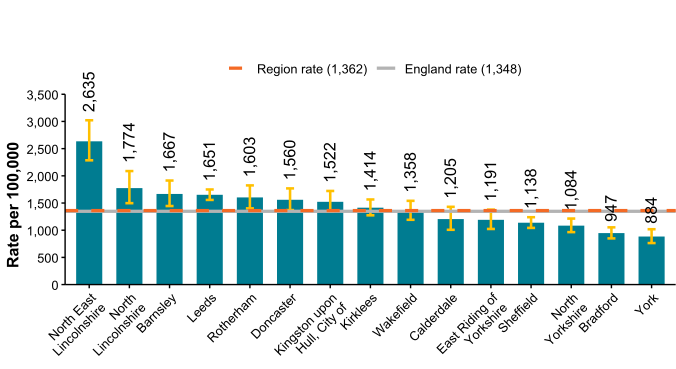
Figure 20 is a column chart which displays the rate chlamydia diagnoses in females aged 15 to 24, in 2025 by Yorkshire and Humber local authority of residence. Rates are by 100,000 population and for all ages. Local authorities are shown in descending order. The overall Yorkshire and Humber and England rates are represented as dashed and solid lines, respectively.
In 2025, North East Lincolnshire had the highest chlamydia diagnosis rate among females aged 15 to 24 out of the Yorkshire and Humber local authorities (2,635 per 100,000), exceeding the England rate (1,348). York recorded the lowest rate (884 per 100,000).
Gonorrhoea
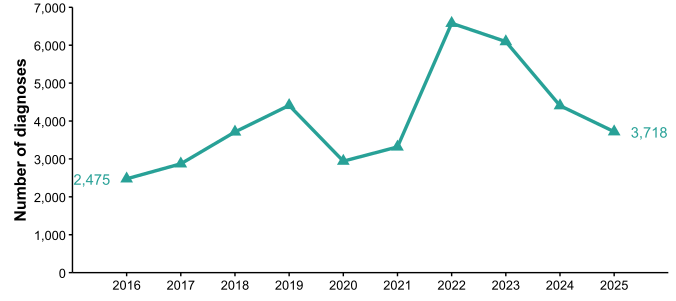
Figure 21. Number of gonorrhoea diagnoses, Yorkshire and Humber, 2016 to 2025
Data source: GUMCAD.
Figure 21 is a line chart showing the trend in the number of diagnoses of gonorrhoea, in Yorkshire and Humber residents from 2016 to 2025.
The chart shows gonorrhoea diagnoses have increased from 2,475 in 2016 to 3,718 diagnoses in 2025, representing a 50% increase.
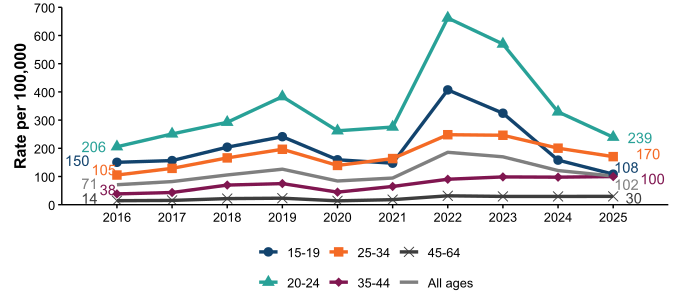
Figure 22. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only), Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 22 is a line chart displaying trend lines of the rate of gonorhoea diagnoses in Yorkshire and Humber residents by age group over the past 10 years (2016 to 2025). Rates are by 100,000 population in each age group. As in previous charts 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years and 45 to 64 years.
The chart shows that those aged 20 to 24 years continue to have the highest rate of gonorrhoea in 2025 (239 per 100,000). In 2025 those aged 25 to 34 have the second highest rate (170 per 100,000) for a second consecutive year following decreases in the rate of those aged 15 to 19 (108 per 100,000).
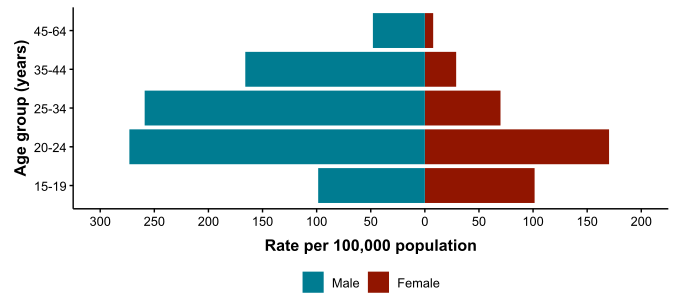
Figure 23. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only) and gender, Yorkshire and Humber, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 23 is an age-sex pyramid displaying the rate of gonorrhoea diagnoses in Yorkshire and Humber residents in 2025 by age group and gender (male compared to female). Rates are by 100,000 population in each group. As in previous graphs 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years, 45 to 64 years.
The chart shows that the highest rates in both females and males were in those aged 20 to 24 years, followed by 15 to 19 year olds in females and 25 to 34 year olds in males.
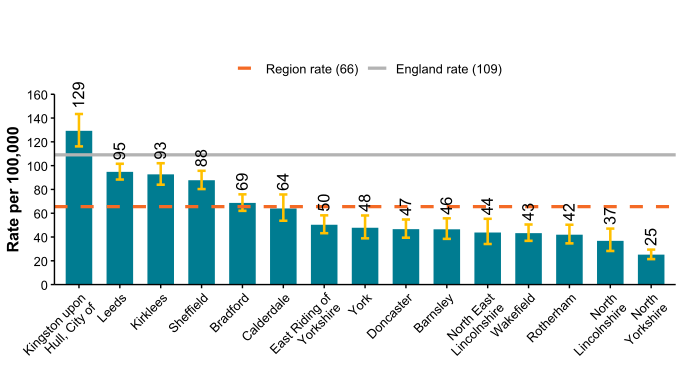
Figure 24. Rate of gonorrhoea diagnoses per 100,000 by upper tier local authority, Yorkshire and Humber, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 24 is a column chart which displays the rate gonorrhoea diagnoses in 2025 by Yorkshire and Humber local authority of residence. Rates are by 100,000 population and for all ages. Local authorities are shown in descending order. The overall Yorkshire and Humber and England rates are represented as dashed and solid lines, respectively.
In 2025, City of Kingston upon Hull had the highest gonorrhoea diagnosis rate among Yorkshire and Humber local authorities (129 per 100,000), exceeding the England rate (109). North Yorkshire recorded the lowest rate (25 per 100,000).
Genital warts
Figure 25. Number of genital warts diagnoses, Yorkshire and Humber, 2016 to 2025
Data source: GUMCAD.
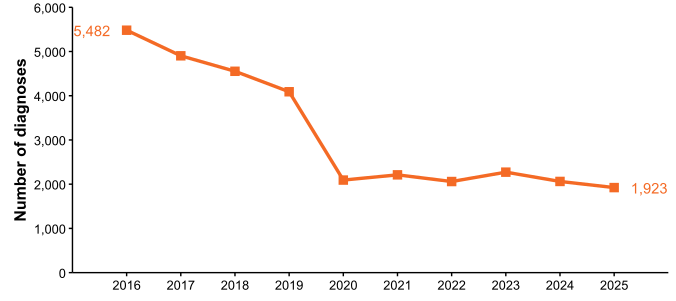
Figure 25 is a line chart showing the trend in the number of diagnoses of genital warts, in Yorkshire and Humber residents from 2016 to 2025.
The chart shows genital wart diagnoses have decreased from 5,482 in 2016 to 1,923 diagnoses in 2025, representing a decrease of 65%.
Figure 26. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only), Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
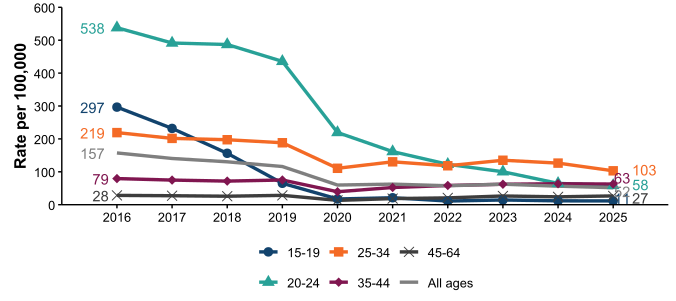
Figure 26 is a line chart displaying trend lines of the rate of genital wart diagnoses in Yorkshire and Humber residents by age group over the past 10 years (2016 to 2025). Rates are by 100,000 population in each age group. As in previous charts 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years and 45 to 64 years.
The chart shows that those aged 25 to 34 years have the highest rate of genital warts in 2025 (103 per 100,000). Significant decreases over time are seen in the 15 to 19 and 20 to 24 years age groups due to the introduction of the HPV vaccination in 2008.
Figure 27. Rates of genital warts per 100,000 aged 15 to 19 and 20 to 24 years by gender, Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
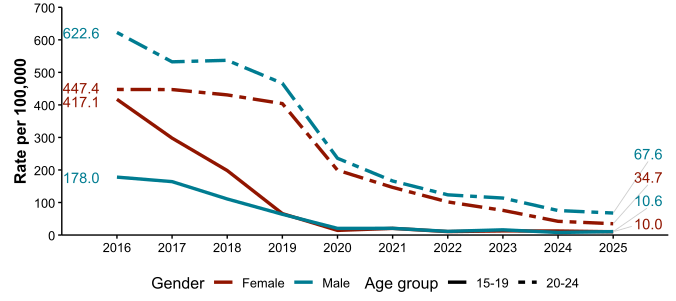
Figure 27 is line graph showing the rate per 100,000 of genital warts in Yorkshire and Humber, split by male and female in the 15 to 19 and 20 to 24 age groups.
The rate of genital warts per 100,000 is highest in the males aged 20 to 24 age group (67.6). In the 15 to 19 year age group the rate is similar for males and females at 10.6 and 10.0 respectively.
Figure 28. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only) and gender, Yorkshire and Humber, 2025
Data sources: GUMCAD, ONs Census 2021 mid-year estimates.
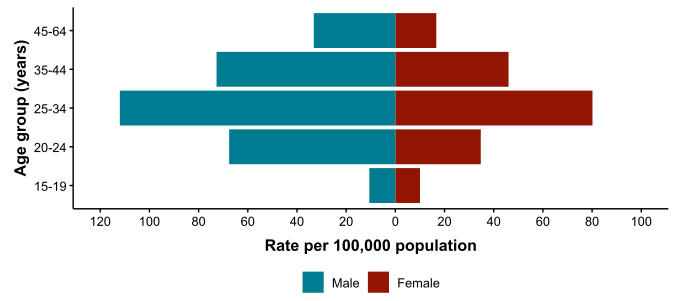
Figure 28 is an age-sex pyramid displaying the rate of genital wart diagnoses in Yorkshire and Humber residents in 2025 by age group and gender (male compared to female). Rates are by 100,000 population in each group. As in previous graphs 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years, 45 to 64 years.
The chart shows that the highest rates in both females and males were in those aged 25 to 34 years, followed by those aged 35 to 44 years.
Syphilis
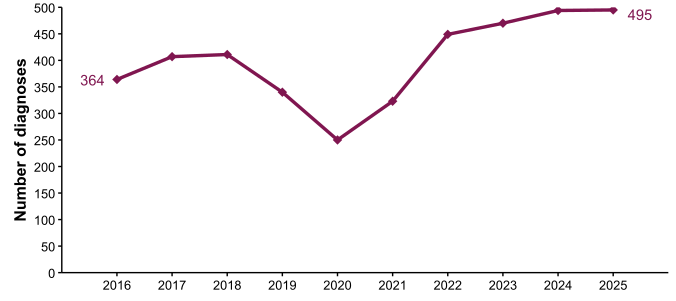
Figure 29. Number of syphilis diagnoses, Yorkshire and Humber, 2016 to 2025
Data source: GUMCAD.
Figure 29 is a line chart showing the trend in the number of diagnoses of syphilis, in Yorkshire and Humber residents from 2016 to 2025.
The chart shows syphilis diagnoses have increased from 364 in 2016 to 495 diagnoses in 2025, representing an increase of 36%.
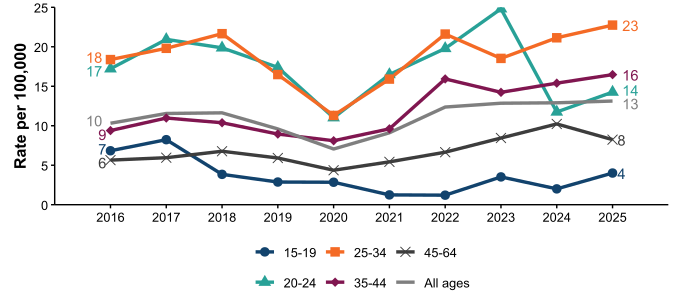
Figure 30. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only), Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 30 is a line chart displaying trend lines of the rate of syphilis diagnoses in Yorkshire and Humber residents by age group over the past 10 years (2016 to 2025). Rates are by 100,000 population in each age group. As in previous charts 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years and 45 to 64 years.
The chart shows that those aged 25 to 34 years have the highest rate of syphilis in 2025 (23 per 100,000). In 2025 there has been an increase across all age categories except in those aged 45 to 64 (8 per 100,000). The rate of syphilis diagnoses is higher in older age groups compared to the distribution of the other main STIs.
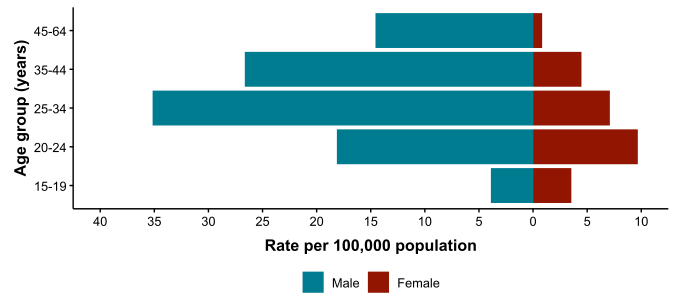
Figure 31. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only) and gender, Yorkshire and Humber, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 31 is an age-sex pyramid displaying the rate of syphilis diagnoses in Yorkshire and Humber residents in 2025 by age group and gender (male compared to female). Rates are by 100,000 population in each group. As in previous graphs 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years, 45 to 64 years.
The chart shows that the highest rate for males is in those aged 25 to 34 and for females the highest rate is in those aged 20 to 24. Overall, there is a higher burden of disease in males than females.
Genital herpes
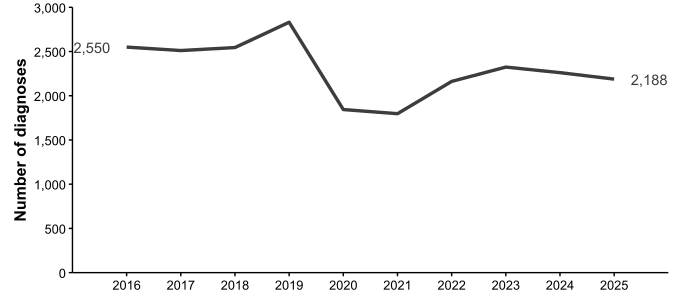
Figure 32. Number of genital herpes diagnoses, Yorkshire and Humber, 2016 to 2025
Data source: GUMCAD.
Figure 32 is a line chart showing the trend in the number of diagnoses of genital herpes, in Yorkshire and Humber residents from 2016 to 2025.
The chart shows genital herpes diagnoses have decreased from 2,550 in 2016 to 2,188 diagnoses in 2025, representing a decrease of 14%.
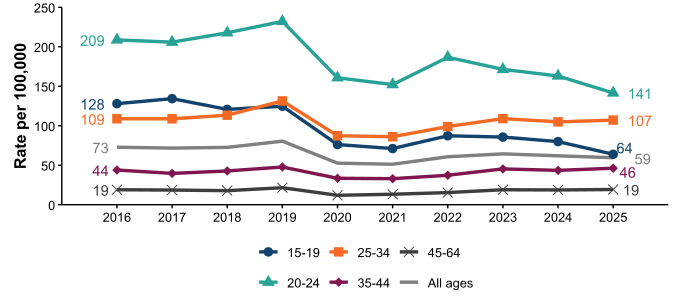
Figure 33. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only), Yorkshire and Humber, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Yorkshire and Humber residents by age group over the past 10 years (2016 to 2025). Rates are by 100,000 population in each age group. As in previous charts 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years and 45 to 64 years.
The chart shows that those aged 20 to 24 years have the highest rate of genital herpes in 2025 (141 per 100,000). Overall the rates in each age group are broadly similar to 2024.
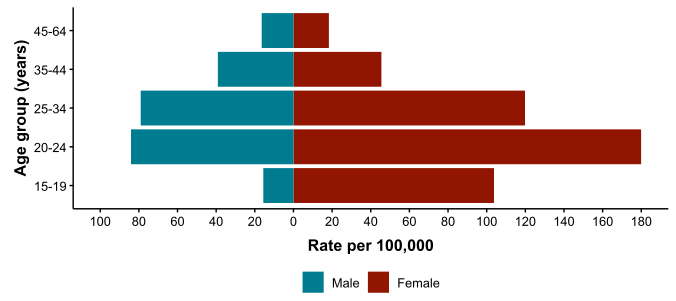
Figure 34. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only) and gender, Yorkshire and Humber, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 34 is an age-sex pyramid displaying the rate of genital herpes diagnoses in Yorkshire and Humber residents in 2025 by age group and gender (male compared to female). Rates are by 100,000 population in each group. As in previous graphs 5 age groups are displayed: 15 to 19 years, 20 to 24 years, 25 to 34 years, 35 to 44 years, 45 to 64 years.
The chart shows that the highest rates in both females and males were in those aged 20 to 24 years, followed by 25 to 34 year olds.
Information on data sources
Find more information on local sexual health data sources in the UKHSA guide.
The gender and age group chart is restricted to those aged 15 to 64 years as information about STIs in those aged less than 15 years is considered highly sensitive. Analyses specific to this group are not provided in routine outputs. Rates for those aged 65 or older are withheld to ensure that no deductive disclosure is possible for the less than 15 years age group. The proportion of STIs in those aged less than 15 years or older than 64 years is very low.
GUMCAD surveillance system
This disaggregate reporting system collects information about attendances and diagnoses at specialist (Level 3) and non-specialist (Level 2) sexual health services. Information about the patient’s area of residence is collected along with demographic data and other variables. GUMCAD superseded the earlier KC60 system and can provide data from 2009 onwards. GUMCAD is the main source of data for this report.
Due to limits on how much personally identifiable information sexual health clinics are able to share, it is not possible to deduplicate between different clinics. There is a possibility that some patients may be counted more than once if they are diagnosed with the same infection (for infection specific analyses) or a new STI of any type (for new STI analyses) at different clinics during the same calendar year.
CTAD surveillance system
CTAD collects data on all local authority and NHS or NHS-commissioned chlamydia testing carried out in England. CTAD is comprised of all chlamydia (NAATs) tests for all ages (with the exception of conjunctival samples), from all venues and for all reasons. CTAD enables unified, comprehensive reporting of all chlamydia data, to effectively monitor the impact of the NCSP through estimation of the coverage of population screening, proportion of all tests that are positive and detection rates.
For services which report to GUMCAD and for which CTAD does not receive data on the patient’s area of residence (for example, SHSs), information about chlamydia diagnoses is sourced from GUMCAD data.
CTAD does not collect information about sexual orientation or country of birth. Reports from CTAD are excluded from figures in this report which relate to analyses by sexual orientation or world region of birth.
New STIs
New STI diagnoses comprise diagnoses of the following:
- chancroid
- Lymphogranuloma venereum (LGV)
- donovanosis
- chlamydia
- gonorrhoea
- genital herpes (first episode)
- HIV (acute and AIDS defining)
- Molluscum contagiosum
- non-specific genital infection (NSGI)
- non-specific pelvic inflammatory disease (PID) and epididymitis
- chlamydial PID and epididymitis (presented in chlamydia total)
- gonococcal PID and epididymitis (presented in gonorrhoea total)
- scabies
- pediculosis pubis
- syphilis (primary, secondary and early latent)
- trichomoniasis and genital warts (first episode)
- Mycoplasma genitalium
- shigella
Calculations
Confidence Intervals were calculated using Byar’s method for numerators >= 10. For small numerators Byar’s method is less accurate and so an exact method based on the Poisson distribution is used.
ONS mid-year population estimates for 2024 were used as a denominator for rates (other than by ethnic group) for 2025. ONS estimates of population by ethnic group for the year 2021 were used as a denominator for rates by ethnic group for 2025. This is the first time that new estimates of population by ethnic group have been available since 2011. This must be considered if comparing rates for 2025 in this report with rates by 2024 in last year’s report, as the rates in the last report used the 2011 estimates.
Interpreting trends
When interpreting trends in the number of STI diagnoses it is important to consider the potential impact of changes to testing, vaccination programmes and the availability of interventions (such as prophylaxis). Specifically, diagnostic testing for gonorrhoea and genital herpes now includes in some areas highly sensitive testing using nucleic acid amplification tests. Additionally, there is some screening of GBMSM at extra-genital sites. Where in place, both will have led to increased case ascertainment of gonorrhoea and genital herpes. Local testing practices for all STIs may vary.
More information
As of 2020, all analyses for this report include data from non-specialist (Level 2) SHSs and enhanced GP services as well as specialist (Level 3) SHSs.
For further information, see the online Sexual and Reproductive Health Profiles.
For more information about HIV data, see the separate HIV Spotlight report.
For more information about local sexual health data sources, see the UKHSA guide.
Local authorities have access to The Summary Profile of Local Authority Sexual Health (SPLASH) Reports (accessible from the Sexual and Reproductive Health Profiles) and the SPLASH supplement reports via the HIV and STI Data exchange.
About the Field Services
The Field Services were established in 2018 as a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Real-time Syndromic Surveillance and Public Health Microbiology to strengthen the surveillance, intelligence and response functions of UKHSA.
You can contact your local Field Services team at YHFS@ukhsa.gov.uk
Acknowledgements
We would like to thank the following:
- local SHSs for supplying the SHS data
- local laboratories for supplying the CTAD data
- UKHSA Blood Safety, Hepatitis, Sexually Transmitted Infections (STI) and HIV Division for collection, analysis and distribution of data