Laboratory confirmed cases of measles, mumps and rubella, England: April to June 2026
Updated 29 October 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/measles-mumps-and-rubella-lab-confirmed-cases-in-england-2026/laboratory-confirmed-cases-of-measles-mumps-and-rubella-england-april-to-june-2026
Data as of 5 October 2026
Introduction
Measles, mumps and rubella are notifiable diseases; healthcare professionals are legally required to inform their local Health Protection Team (HPT) of any suspected case. National enhanced surveillance including oral fluid (OF) testing of all suspected cases is provided through the Virus Reference Department (VRD) at Colindale to support and monitor progress towards WHO measles and rubella elimination targets (1).
Two WHO indicators are of prime importance for measuring the performance of national measles and rubella surveillance systems. These are:
- The rate of laboratory investigations (at least 80% of suspected cases).
- The annual rate of discarded cases (at least 2 per 100,000 population)
To achieve these targets, the focus of the UK Health Security Agency (UKHSA) is to ensure that all suspected cases are appropriately tested. IgM serology testing is the gold standard test for confirming or discarding a suspected acute measles or rubella case. Oral fluid IgM testing is a suitable alternative that is minimally invasive. Recent infection is confirmed by the presence of virus specific IgM. Cases can be confirmed by molecular detection of viral RNA in these samples, with subsequent sequencing for molecular surveillance.
Samples that have been confirmed positive for measles or rubella in a proficient laboratory (this includes local laboratories as well as the National Reference Laboratory) are included in this report. Samples that are referred to, or tested at, the National Reference Laboratory are further sequenced and entered on the WHO global Measles Nucleotide Surveillance (MeaNS2) or the Rubella Nucleotide Surveillance (RubeNS2) system, respectively, which are hosted by the National Reference Laboratory. Genotyping and further characterisation of measles and rubella is used to support investigation of transmission pathways and sources of infection.
Data presented here are for the second quarter of 2026 (April to June). However, details of the most recent epidemiology are published at Measles epidemiology 2023 to 2026.
The analyses are executed using the onset date of a rash or other symptoms, and regional breakdown figures relate to the Government Office Regions. Hospitalisation statistics have been derived from the Secondary Uses Service and Emergency Care Data Sets. Travel related data is retrieved from UKHSA’s case incident management system (CIMS).
Historical annual and quarterly measles, mumps and rubella epidemiological data are available here from 2013 onwards:
The results from all samples tested at Colindale are reported using UKHSA’s laboratory information system MOLIS. The results are then reported back to the respective general practitioner (GP) and local HPT.
Overview
Table 1. Total suspected cases of measles, mumps and rubella reported to HPTs with breakdown of:
a) number of suspected cases
b) number (%) tested by Oral Fluid (OF)
c) other samples referred onto the Virus Reference Department (VRD) Colindale
d) cases confirmed at the VRD
e) cases confirmed at regional, local NHS hospital and private laboratories only
f) percentage of suspected cases confirmed
g) discard rate per 100,000 population: weeks 13 to 26 of 2026
| Notification | Number of suspected cases [note 1] |
Number (%) tested by oral fluid (OFK) [note 2] |
Other samples received by VRD | Samples IgM positive or viral detection at VRD (Cases confirmed at VRD) |
Cases confirmed at regional, local NHS hospital and private laboratories only [note 3] |
% of suspected cases confirmed [note 4] |
Discard rate based on negative tests per 100,000 population [notes 5 and 6] |
|---|---|---|---|---|---|---|---|
| Measles | 1,804 | 862 (47.8%) | 299 | 470 | 55 | 29.1% | 2.18 |
| Mumps | 1,338 | 643 (48.1%) | 695 | 42 | 10 | 3.9% | 2.19 |
| Rubella | 82 | 39 (47.6%) | 21 | 2 | 0 | 2.4% | 0.14 |
Note 1: This represents all cases reported from health professionals to HPTs in England.
Note 2: For surveillance purposes, suspected measles and rubella cases should be sent an OFK by the HPT. Many cases will also undergo local diagnostic testing in parallel; however, only positive results are reported to UKHSA.
Note 3: Laboratories are required to report locally confirmed measles and rubella cases to UKHSA.
Note 4: Negative PCR results from local NHS and private laboratories are not routinely reported to UKHSA and therefore the estimated discard rate is an underestimate.
Note 5: Percentage confirmed = (cases confirmed at the VRD + cases confirmed at regional, local NHS hospital and private laboratories) ÷ suspected notifications × 100
Note 6: The WHO has set a target for an annual discard rate of 2 cases per 100,000 population, which translates to a quarterly target of 0.5 per 100,000. It’s important to note that we have proportionally adjusted the annual target to ensure there is consistent testing across each quarter.
Measles
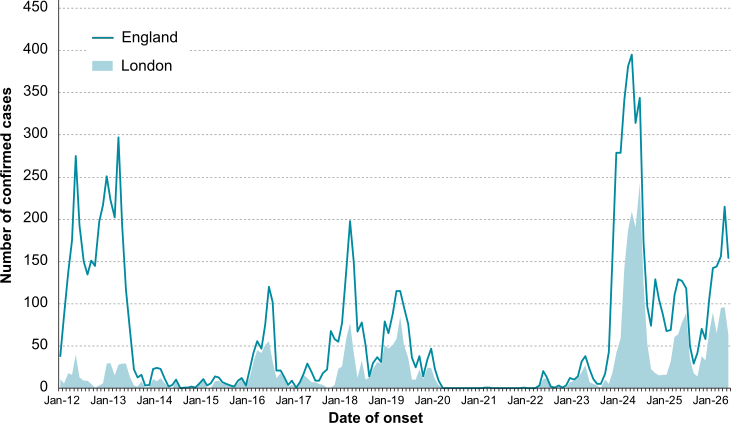
In the period between April to June 2026, there were 525 laboratory confirmed cases of measles reported in England, an increase of 35.7% from the previous quarter (n=387) (2) (Figure 1). Almost half of these cases were in London (48.4%, 254 out of 525), 12.6% (66 out of 525) were in the East of England, 12.2% (64 out of 525) in the North West, 11.2% (59 out of 525) in the Yorkshire and Humber and 10.3% (54 out of 525) in the West Midlands but all regions had at least 1 case reported during this period. Further details of the latest epidemiology are available (3).
Of the 525 cases reported this quarter, 59 (11.2%) were classified as imported and 19 were import-related. The majority, 56.2% (295 out of 525), of cases were in children aged 10 years or younger. Twenty-one (4%) cases were previously vaccinated with one dose of the MMR vaccine and 25 (4.8%) with at least two doses.
This quarter, Scotland reported 5 laboratory confirmed measles cases and Wales reported 1 case. No cases were reported in Northern Ireland.
All suspected cases of measles and rubella should be reported promptly to Health Protection Teams, a risk assessment conducted, and an Oral Fluid kit (OFK) sent for surveillance purposes even if local diagnostic testing is underway. Of the 1,804 suspected measles cases reported to UKHSA this quarter only 29.1% were subsequently confirmed through laboratory testing.
Figure 1. Laboratory confirmed cases of measles by month of onset of rash or symptoms reported, London and England: January 2012 to June 2026
Using NHS number, 523 of the 525 laboratory-confirmed measles cases were linked to secondary care datasets for the period from 5 days before to 10 days their onset of measles symptoms. Of these 523, 31.9% of cases attended A&E only with no admission (167 out of 523). 44.4% of cases had a primary measles-related reason for admission (232 out of 523).
Globally, based on provisional WHO data reported up to September 2026, measles transmission remains widespread. A total of 138,680 laboratory confirmed measles cases were reported during this period. The WHO European Region accounted for approximately 9% (4) of global cases with the following countries reporting the highest case numbers in the Region: Kazakhstan (n= 7,127), Russian Federation (n= 1,257), and Türkiye (n= 1,103) (5).
Given the continued high measles incidence globally, importations into England remain likely. This continues to pose a risk to under‑vaccinated communities. In 2026, measles importations in England were linked to travel from Pakistan (n=13), India, United States, Saudi Arabia, and Bangladesh (n=4 respectively) although cases were reported among travellers returning from a further 26 countries.
Mumps
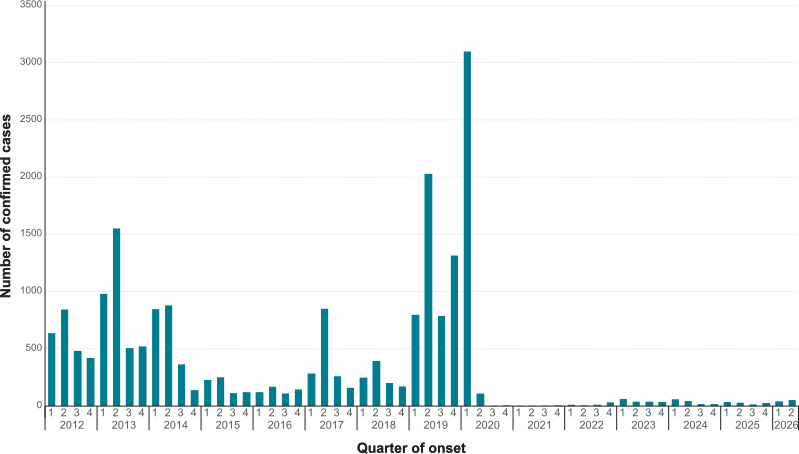
In England, there were 52 laboratory confirmed mumps infections in the period between April to June 2026, an increase of 23.8% since last quarter (n=42).
The majority of cases, 71.2% (37 out of 52), were in young people and adults aged 15 years and older: 3.8% (2 out of 52) were vaccinated with at least one dose of MMR and 13.5% (7 out of 52) had received two doses.
Note: Mumps surveillance and data processing methods changed in 2026. Comparisons with years prior to 2026 should therefore be interpreted with caution, as observed differences may partly reflect changes in surveillance rather than true changes in mumps activity.
Figure 2. Laboratory confirmed cases of mumps by year and quarter in England: January 2012 to June 2026
Rubella
This quarter, there were two laboratory confirmed cases of acute rubella infection in adults resident in Yorkshire and Humber. Both cases were reported to be unvaccinated against rubella.
These are the first laboratory-confirmed cases of rubella in the UK since 2023.
References
1. Public Health England (2019). ‘UK Measles and rubella elimination strategy 2019’
2. UKHSA (2026). ‘Laboratory confirmed cases of measles, rubella and mumps in England: January to March 2026 [version 2]’. Health Protection Report volume 20 number 5
3. UKHSA (2026). ‘Confirmed cases of measles in England by month, age, region and upper tier local authority: 2026’
4. WHO (2026). Measles and Rubella Global Update, October 2026
5. WHO (2026). ‘Measles/Rubella (MR) Dashboard. Summary table: cases by year and final classification’