Children’s public health nursing: workforce and activity report, 2025
Updated 17 September 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/statistics/childrens-public-health-nursing-workforce-and-activity-2025/childrens-public-health-nursing-workforce-and-activity-report-2025
Introduction
These official statistics in development provide information on the children’s public health nursing workforce and national delivery of the healthy child programme in 2025.
The data is based on returns from 145 local councils in England. Six local councils did not submit a return. We applied a correction factor to produce national estimates and account for the missing returns.
This is the first data collection to include antenatal data. Most local councils submitted a return, but some returns contained incomplete or missing data. Use caution when interpreting the data. Work is underway to improve the quality of data returned for future publications.
It is important to note that these statistics are not directly comparable with the following publications:
-
Health visitor service delivery data provides quarterly metrics through an interim reporting system. Local councils submit data voluntarily
-
NHS workforce statistics cover NHS providers only. Approximately three-quarters of local councils commission NHS providers. Others use charities or private providers or deliver services themselves. NHS workforce statistics therefore report fewer staff than this publication
Alongside this commentary, we have published:
- a methodology, which explains the survey and the methods used to analyse the data
- data tables containing the complete aggregated data set
These are available on the Children’s public health nursing: workforce and activity report, 2025 page.
Main points
This publication has 2 main sections.
The first is workforce, which covers the number of people working in health visiting and school nursing teams across England. The second section relates to activity, including the delivery of the 5 statutory health and development reviews for children aged 0 to 5 across England broken down by region as well as delivery of school nursing services.
The main points outlined in the data are that:
- from January to December 2025, the estimated workforce was 14,126 whole-time equivalent (WTE) staff for health visiting services and 4,405 WTE for school nursing services. WTE converts the hours worked by full-time and part-time staff into an equivalent number of full-time posts
- from January to December 2025, observed data showed that 2,030,178 statutory health and development reviews were carried out in England. Of these:
- 194,145 were antenatal reviews
- 472,574 were new birth reviews
- 447,944 were 6 to 8 week reviews
- 473,881 were 9 to 15 month reviews
- 441,634 were 2 to 2 and a half year reviews
Children’s public health nursing workforce
This section gives information on the children’s public health nursing workforce. It covers health visiting and school nursing.
SCPHN stands for specialist community public health nurse. This refers to registered nurses or midwives who have completed the Specialist Community and Public Health Nursing qualification according to standards set by the Nursing and Midwifery Council. SCPHN is a registration category, with health visitors and school nurses being a type of SCPHN.
Health visiting workforce
The main points outlined in this data are that:
- in 2025, the estimated health visiting workforce in England was 14,126 WTE - this includes SCPHN health visitors and other skill-mix roles working in health visiting teams
- the total estimated number of SCPHN health visitors was 6,909 WTE
- the total estimated number of other clinical roles within the health visiting workforce (for example, registered nurses, nursery nurses and other non-administrative staff) was 5,073 WTE
- the total estimated number of management, administrative and other administrative support roles was 2,143 WTE
- 49% of the total workforce (including administrative and management staff) were qualified SCPHNs
- the vacancy rate for health visitor roles was 4.5% and 3.0% across non-clinical roles
- there were 2.2 WTE health visitors per 1,000 children aged 0 to 5. The rate across different local councils ranged from 0.9 WTE to 4.9 WTE health visitors per 1,000 children aged 0 to 5
Figure 1: health visiting workforce by role type in England, 2025 (uncorrected)
| Role in the health visiting team | Number of staff (WTE) |
|---|---|
| Health visitors | 6,649 |
| Non-registered staff (for example, nursery nurses) | 2,843 |
| Registered nurses | 1,389 |
| Admin | 972 |
| Management | 777 |
| Other clinical staff (for example, specialist psychologist) | 377 |
| Other administrative support roles | 314 |
| Other support roles (for example, breast feeding adviser) | 274 |
Source: children’s public health nursing - workforce and activity, 2025 data return
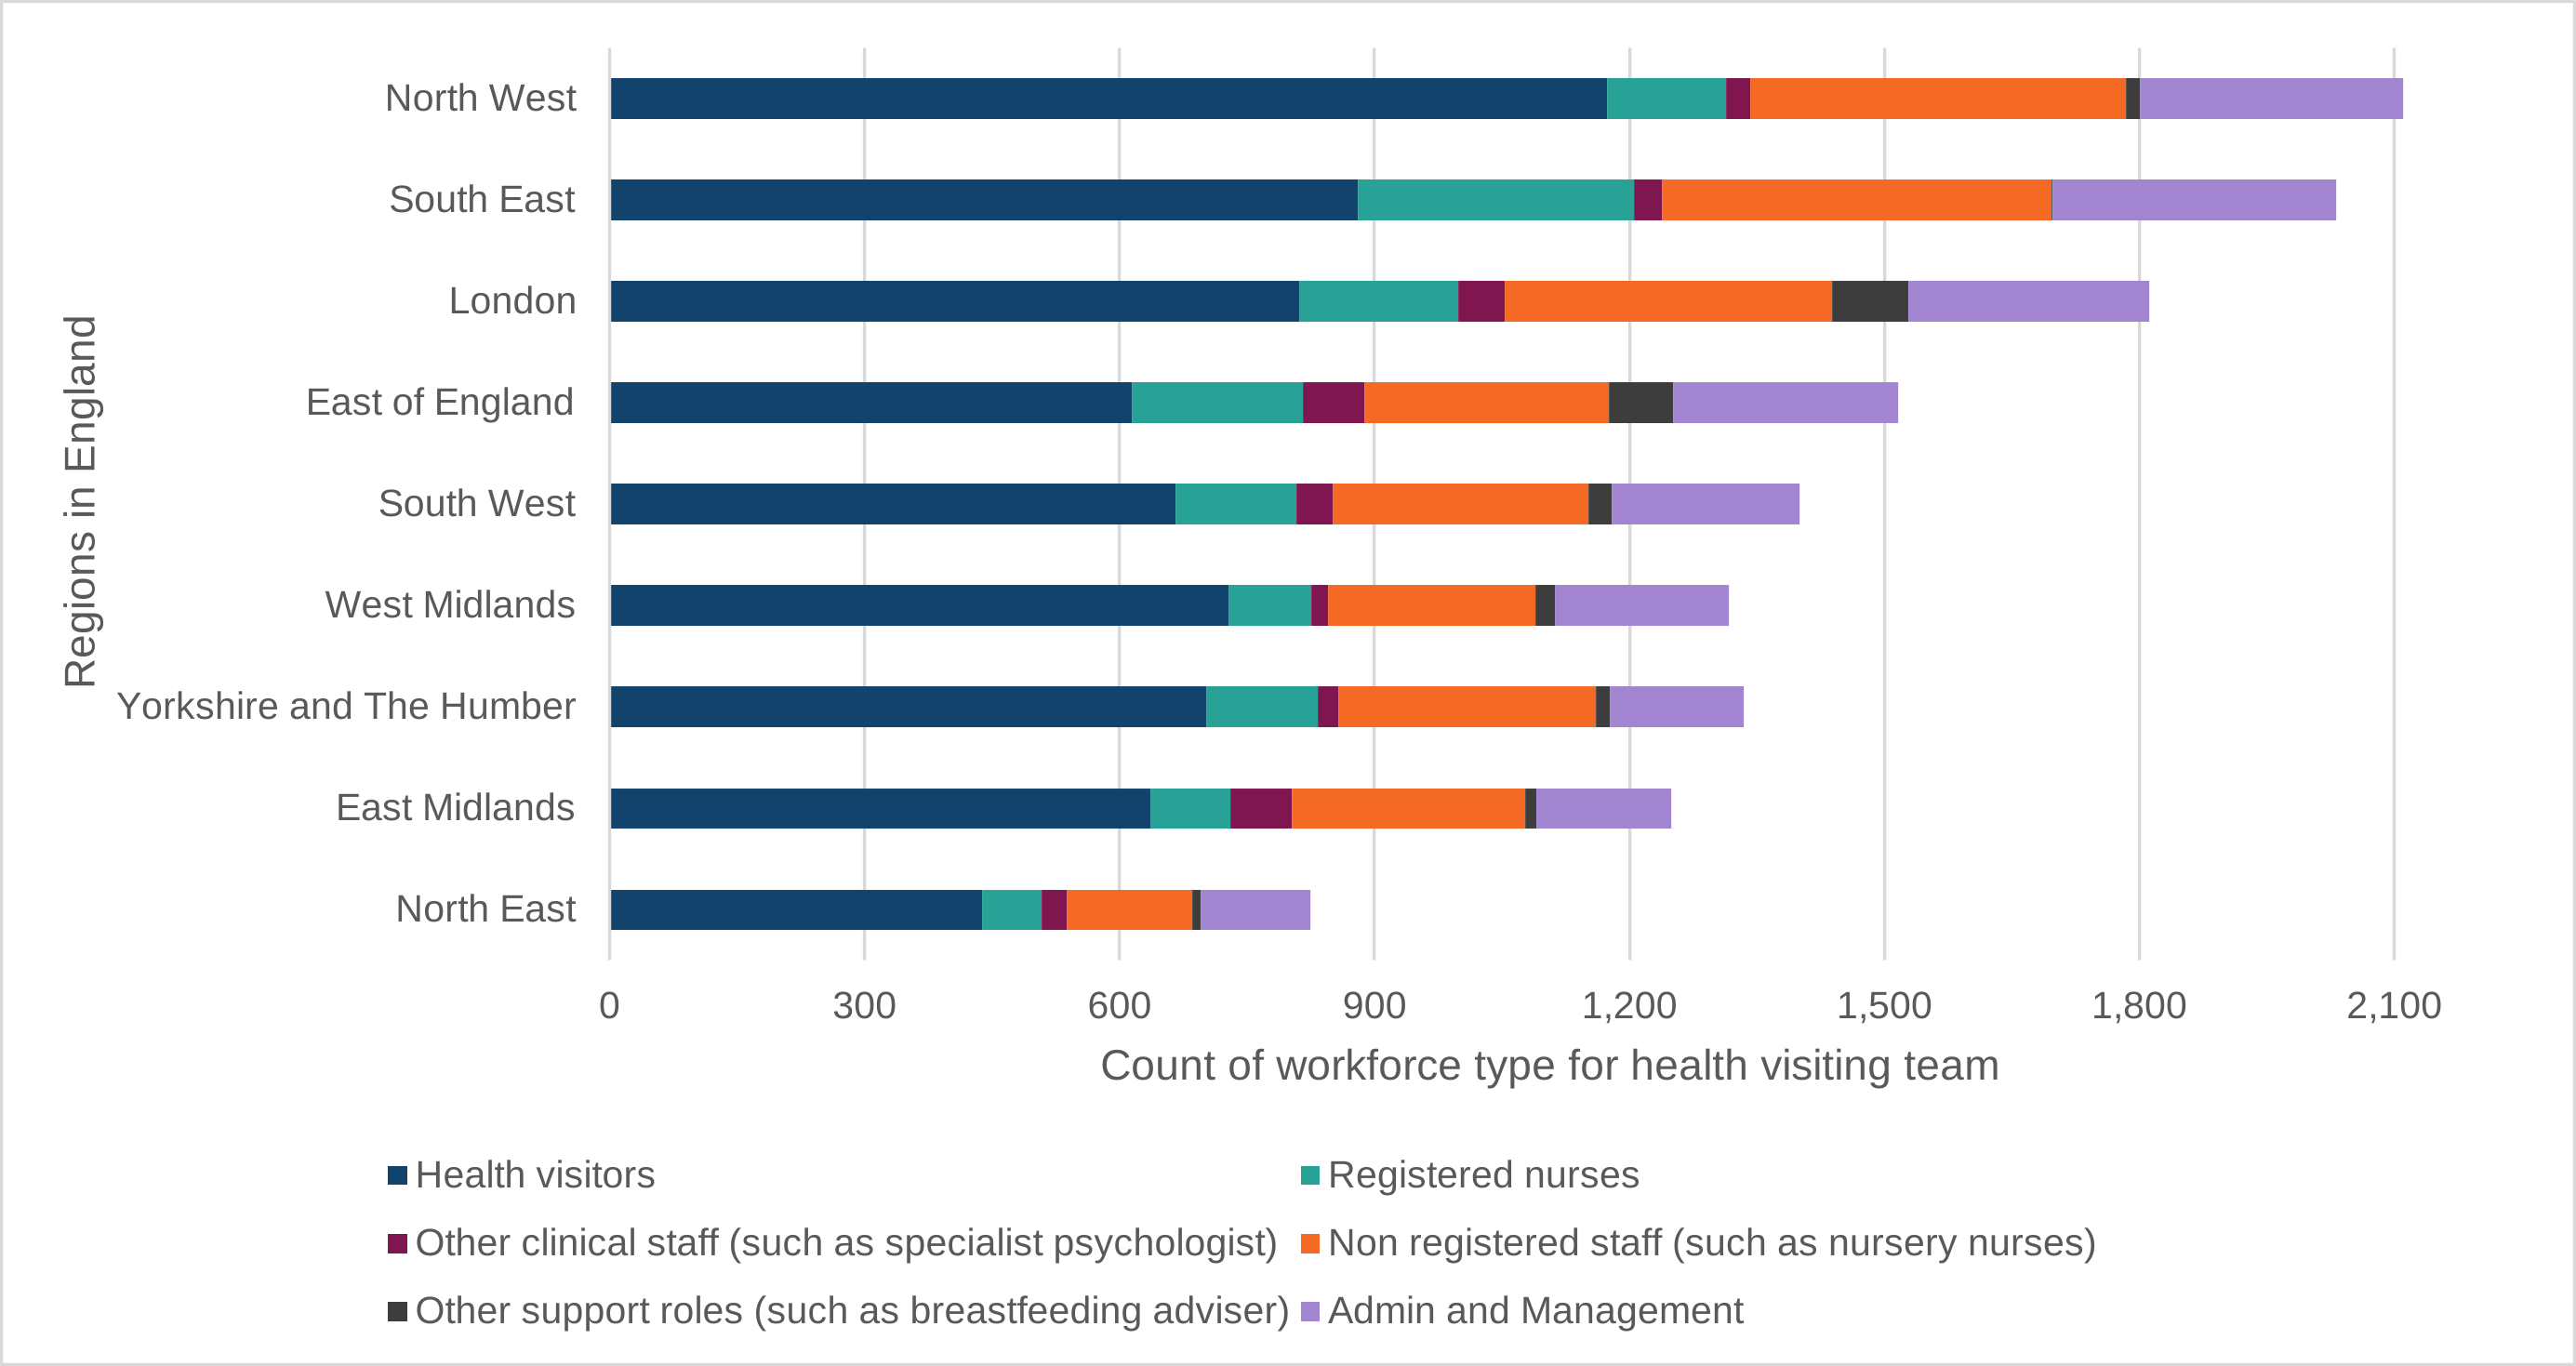
Figure 2: composition of health visiting team by role across regions in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 2 shows the percentage composition of health visiting teams by role across the 9 regions of England in 2025. Health visitors formed the largest staff group in every region, ranging from 41% in the East of England to 56% in the North West. Non-registered staff were generally the second-largest group, while registered nurses accounted for a larger share of the workforce in the South East than elsewhere. Other clinical staff and support roles each represented a small proportion of the workforce in all regions.
This data can be found in table 1 in the data tables published alongside this report.
Table 1: percentage of staff by role in health visiting teams across regions in England, 2025
| Region name | Health visitors | Registered nurses | Other clinical staff | Non-registered staff | Other support roles | Admin and management |
|---|---|---|---|---|---|---|
| North East | 53% | 8% | 4% | 18% | 1% | 16% |
| North West | 56% | 7% | 1% | 21% | 1% | 15% |
| Yorkshire and the Humber | 53% | 10% | 2% | 23% | 1% | 12% |
| East Midlands | 51% | 7% | 6% | 22% | 1% | 13% |
| West Midlands | 55% | 7% | 2% | 19% | 2% | 16% |
| East of England | 41% | 13% | 5% | 19% | 5% | 17% |
| London | 45% | 10% | 3% | 21% | 5% | 16% |
| South East | 43% | 16% | 2% | 23% | 0% | 16% |
| South West | 48% | 10% | 3% | 21% | 2% | 16% |
School nursing workforce
The main points outlined in this data are that:
- in 2025, the estimated school nursing workforce was 4,405 WTE
- the total estimated number of school nurses (SCPHN-qualified) was 1,434 WTE and the total estimated number of other clinical roles within the school nursing workforce (for example, registered nurses and other non-administrative staff) was 2,229 WTE
- the total estimated number of management, administrative and other administrative support roles was 742 WTE
- 33% of the total workforce (including administrative and management staff) were qualified SCPHNs
- the vacancy rate for school nursing roles was 4.7%
- there were 0.11 WTE school nurses per 1,000 young people aged 5 to 19. The rate across different local councils ranged from 0.01 WTE to 0.41 WTE school nurses per 1,000 young people aged 5 to 19
- the average (mean) number of school nurses per secondary school was 0.4 WTE. The rate across different local councils ranged from 0.06 WTE to 2.09 WTE school nurses per secondary school
Figure 3: school nursing workforce by role type in England, 2025 (uncorrected)
| Role in the school nursing team | Number of staff (WTE) |
|---|---|
| School nurses | 1,380 |
| Registered nurses | 1,078 |
| Non-registered staff (for example, nutritionist) | 727 |
| Admin | 330 |
| Management | 286 |
| Other clinical staff (for example, specialist psychologist) | 189 |
| Other clinical support roles (for example, breastfeeding adviser) | 151 |
| Other non-user facing roles | 99 |
Source: children’s public health nursing - workforce and activity, 2025 data return
The estimated school nursing workforce in England in 2025 totalled 4,405 WTE in 2025. Other clinical roles formed the largest workforce group, followed by school nurses. Management, administrative and support roles represented a smaller proportion of the workforce.
This data can be found in table 2 in the data tables published alongside this report.
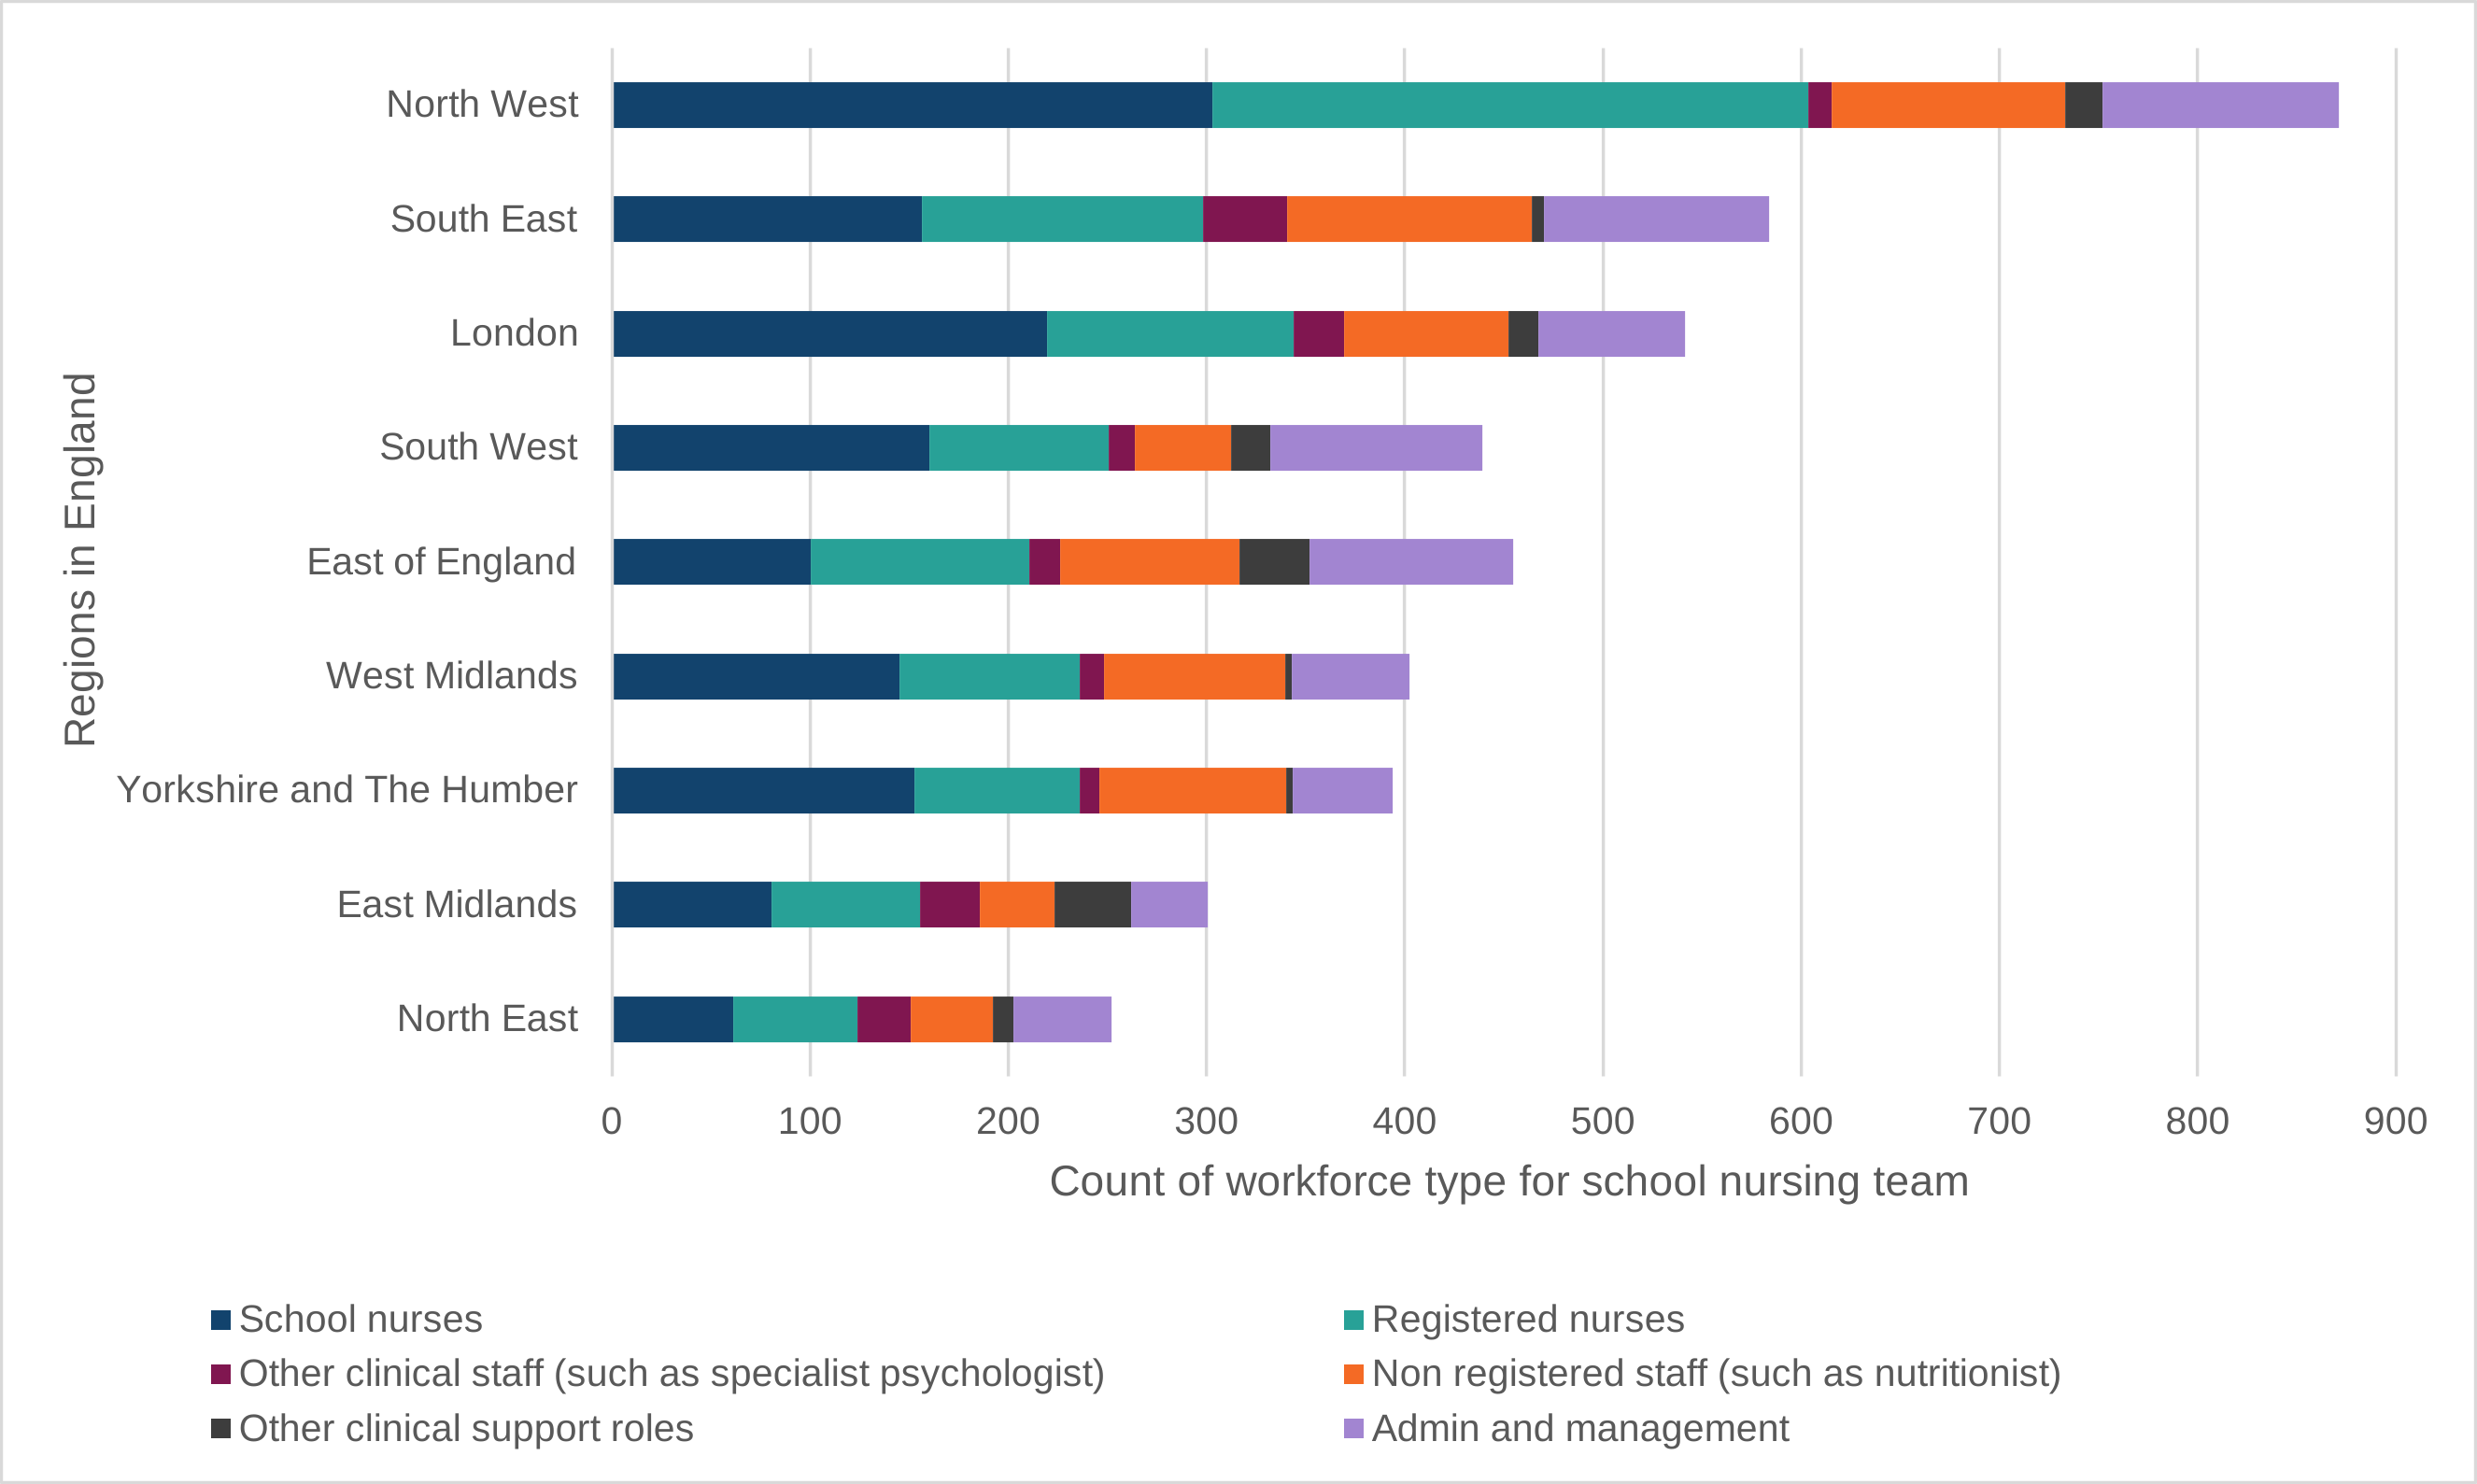
Figure 4: composition of school nursing team by role across regions in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 4 shows the percentage composition of school nursing teams by role across the 9 regions of England in 2025. School nurses and registered nurses accounted for the largest proportions of staff across most regions. The balance of roles varied across England, with some regions having larger proportions of non-registered staff or admin and management staff. Other clinical staff and other clinical support roles generally formed the smallest proportions of the workforce.
This data can be found in table 2 in the data tables published alongside this report.
Table 2: percentage of staff by role in school nursing teams across regions in England, 2025
| Region name | School nurses | Registered nurses | Other clinical staff | Non-registered staff | Other clinical support roles | Admin and management |
|---|---|---|---|---|---|---|
| North East | 24% | 25% | 11% | 16% | 4% | 20% |
| North West | 35% | 34% | 1% | 14% | 2% | 14% |
| Yorkshire and the Humber | 39% | 21% | 3% | 24% | 1% | 13% |
| East Midlands | 27% | 25% | 10% | 13% | 13% | 13% |
| West Midlands | 36% | 23% | 3% | 23% | 1% | 15% |
| East of England | 22% | 24% | 3% | 20% | 8% | 23% |
| London | 41% | 23% | 5% | 15% | 3% | 14% |
| South East | 27% | 24% | 7% | 21% | 1% | 20% |
| South West | 36% | 21% | 3% | 11% | 5% | 24% |
Service activity
The following sections describe delivery of the national healthy child programme in 2025. This includes:
- statutory health and development reviews for children aged 0 to 5 years
- non-statutory targeted reviews (but not further support)
- school nursing activity
The data shows where health and development reviews took place, who delivered them and how many local councils had a school nursing service.
The national healthy child programme guidance recommends that carrying out reviews in the home is best practice for the antenatal review, new birth review and 6 to 8 week review. The guidance recommends home visits for the 9 to 15 month and 2 to 2 and a half year reviews but does not require them. Health visitors should conduct all statutory health and development reviews.
The denominator for all health and development review metrics below is the total number of completed reviews for each statutory review. Some totals do not add up to 100% because of missing data or incomplete data returns.
The statistics (except where a correction factor has been applied) do not include data from the 6 local councils that did not respond to the survey. The methodology explains this in more detail.
The charts also show a high degree of unknown, other or incomplete data as a result of incomplete returns. Care should be taken when drawing conclusions from the charts in this section. The full aggregated data set is available in the accompanying data tables.
There is a large difference in the number of antenatal reviews carried out compared with the other 4 statutory health and development reviews. This is the first time antenatal data has been reported in this way, and the returns reflect a known gap in service provision. Work is underway to address this.
The main points on service delivery in this data are that in the period of January to December 2025:
- there were 2,030,178 statutory health and development reviews carried out in England, of which:
- 194,145 were antenatal reviews
- 472,574 were new birth reviews
- 447,944 were 6 to 8 week reviews
- 473,881 were 9 to 15 month reviews
- 441,634 were 2 to 2 and a half year reviews
- 1,789,777 statutory health and development reviews were carried out in person in England (88% of reviews carried out within this period), of which:
- 164,674 were antenatal reviews
- 450,093 were new birth reviews
- 392,927 were 6 to 8 week reviews
- 400,791 were 9 to 15 month reviews
- 381,292 were 2 to 2 and a half year reviews
- health visitors carried out:
- 82% of all antenatal reviews
- 87% of all new birth reviews
- 73% of all 6 to 8 week reviews
- 26% of all 9 to 15-month reviews
- 20% of all 2 to 2 and a half year reviews
- nationally, 76% of referred eligible women were offered an antenatal review, with 74.5% of those offered receiving a review. Therefore, 57% of referred women had completed reviews. The data shows that some women were not referred, so overall national coverage for the antenatal review is lower
Tables 3 and 4 summarise who carried out each of the statutory health and development reviews and where they were carried out. They show the percentage of reviews carried out by SCPHNs compared with non-SCPHNs and the percentage delivered in the family home, a clinic or family hub. The tables also include where contacts were only made remotely. The total number of reviews reported was used as the denominator in both tables.
Table 3: percentage of health and development reviews carried out at home, in a clinic or family hub, or as a remote contact, 2025
| Reviews | Total number of reviews | Home visits | Clinic or family hub | Remote contact (not review) |
|---|---|---|---|---|
| Antenatal | 194,145 | 76% | 9% | 28% |
| New birth | 472,574 | 94% | 1% | 1% |
| 6 to 8 weeks | 447,944 | 65% | 23% | 3% |
| 9 to 15 months | 473,881 | 39% | 46% | 4% |
| 2 to 2 and a half years | 441,634 | 37% | 50% | 1% |
Note: remote contact includes telephone, questionnaire, letter or video.
Table 4: percentage of health and development reviews carried out by SCPHNs and other staff, by statutory review
| Reviews | Total number of reviews | SCPHN | Non-SCPHN |
|---|---|---|---|
| Antenatal | 194,145 | 82% | 10% |
| New birth | 472,574 | 87% | 6% |
| 6 to 8 weeks | 447,944 | 73% | 16% |
| 9 to 15 months | 473,881 | 26% | 58% |
| 2 to 2 and a half years | 441,634 | 21% | 63% |
Note: non-SCPHN staff includes registered nurses, non-registered support staff and other staff.
0 to 5 service activity
References to SCPHN in figures 5, 7, 9, 11 and 13 mean health visitor. All SCPHNs working in services for children aged 0 to 5 years are health visitors.
Antenatal review
An antenatal review takes place between 28 weeks of pregnancy and birth. It focuses on preparing for parenthood and early identification of need. Best practice is for a health visitor to carry out the antenatal review in the family home.
This is the first time antenatal data has been published. Some regions had many councils with no location data. This explains the lower percentages in figure 6.
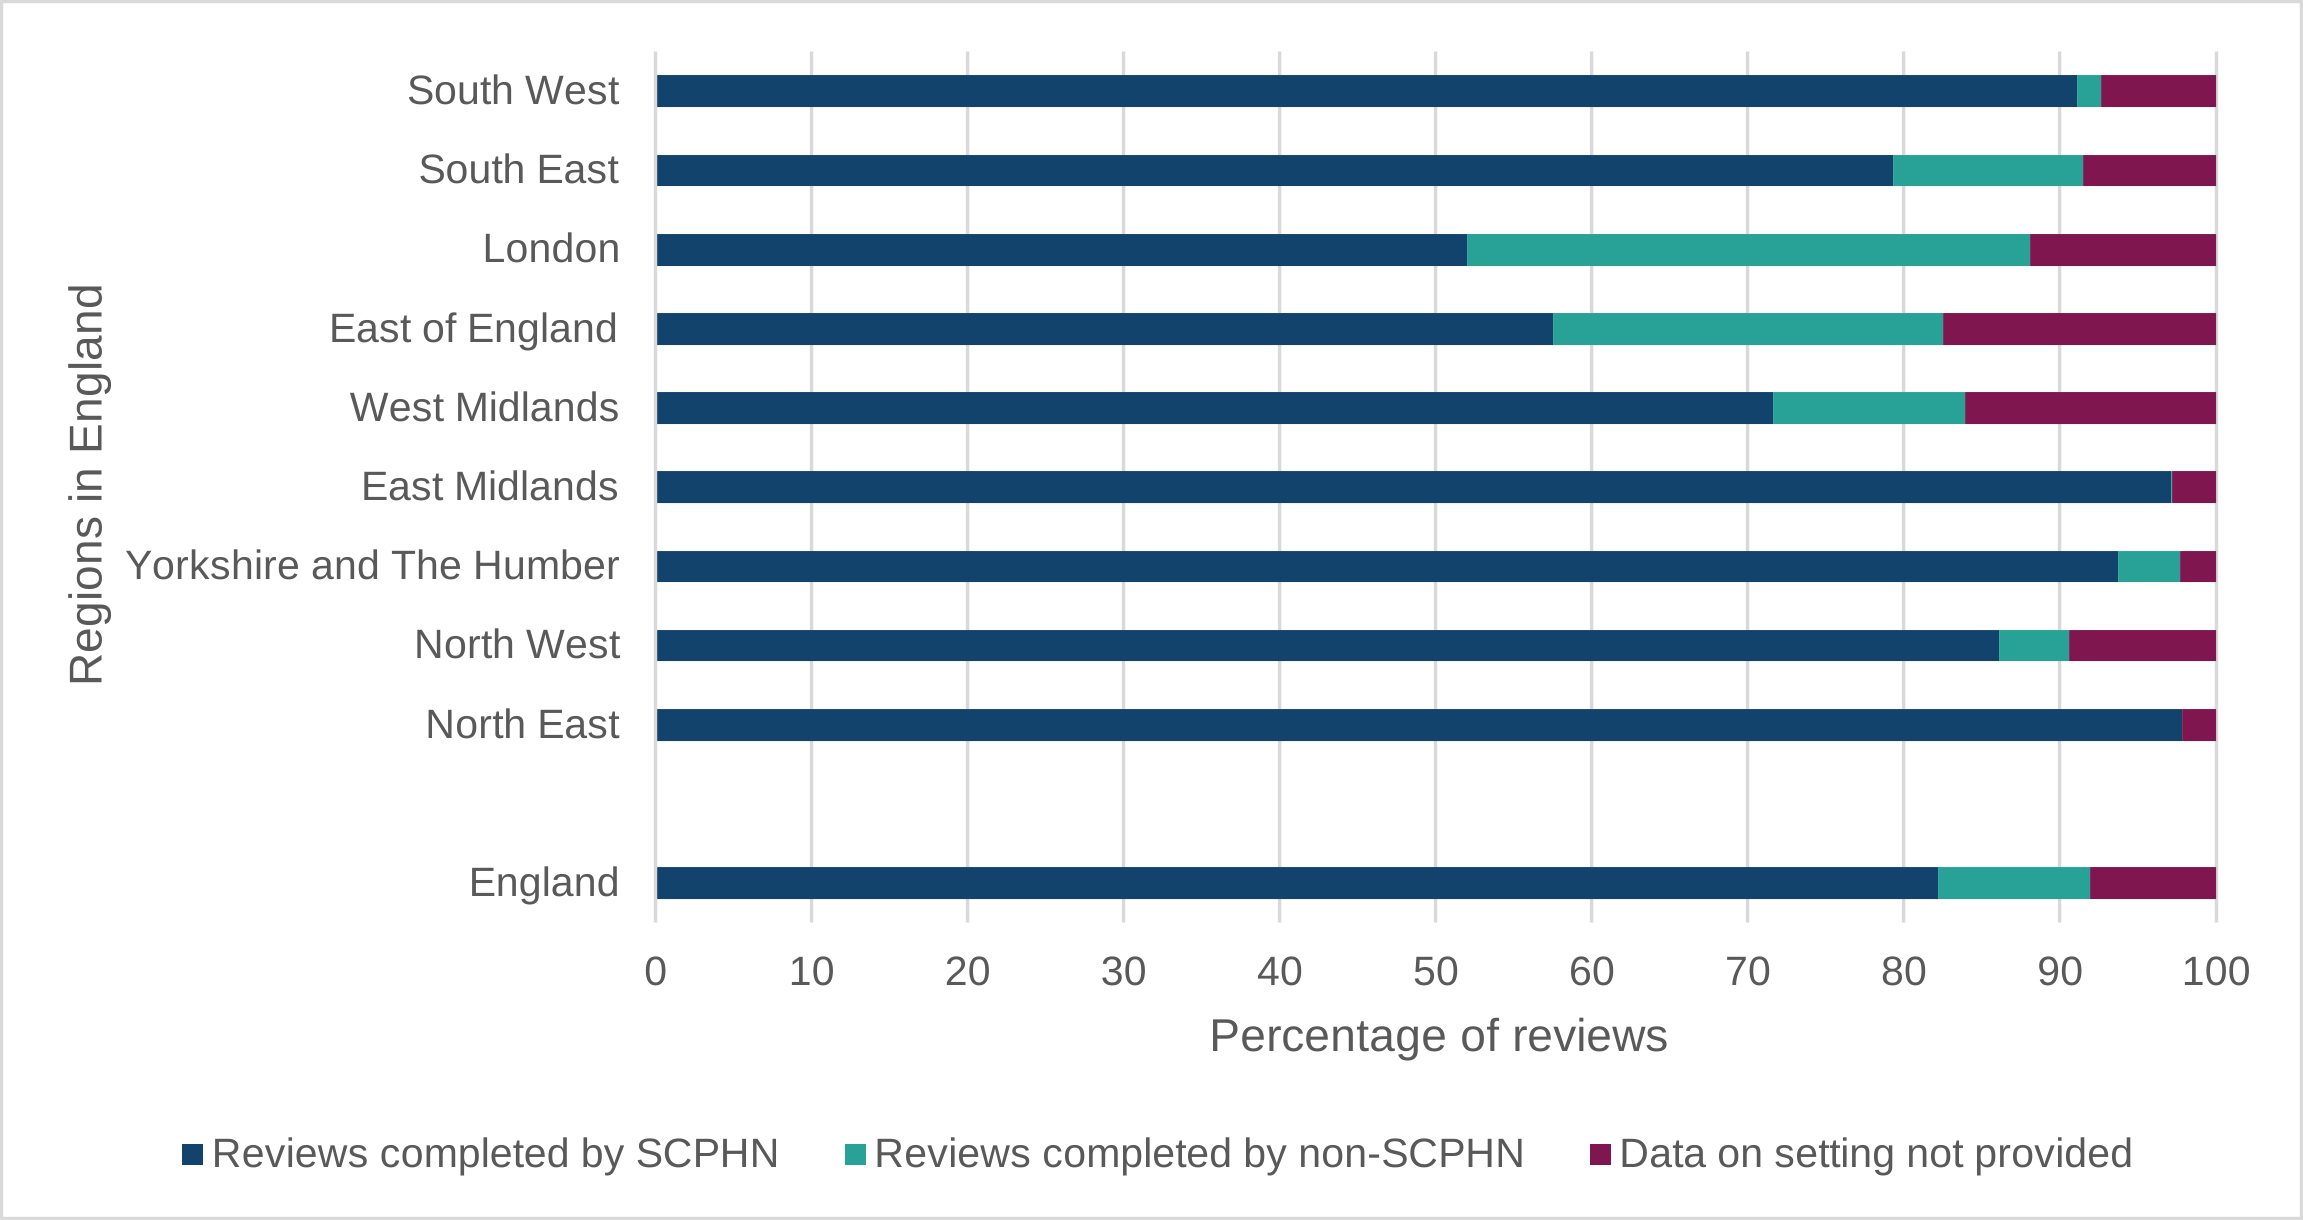
Figure 5: percentage of antenatal reviews carried out by staff type (SCPHN compared with non-SCPHN) in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 5 shows the percentage of antenatal reviews carried out by SCPHNs and non-SCPHN staff, and reviews with no staff-type data reported across England and the 9 English regions in 2025. Nationally, SCPHN staff carried out most antenatal reviews (82%). Missing staff-type data varied between regions and exceeded 15% in the East of England and West Midlands.
This data can be found in table 5 in the data tables published alongside this report.
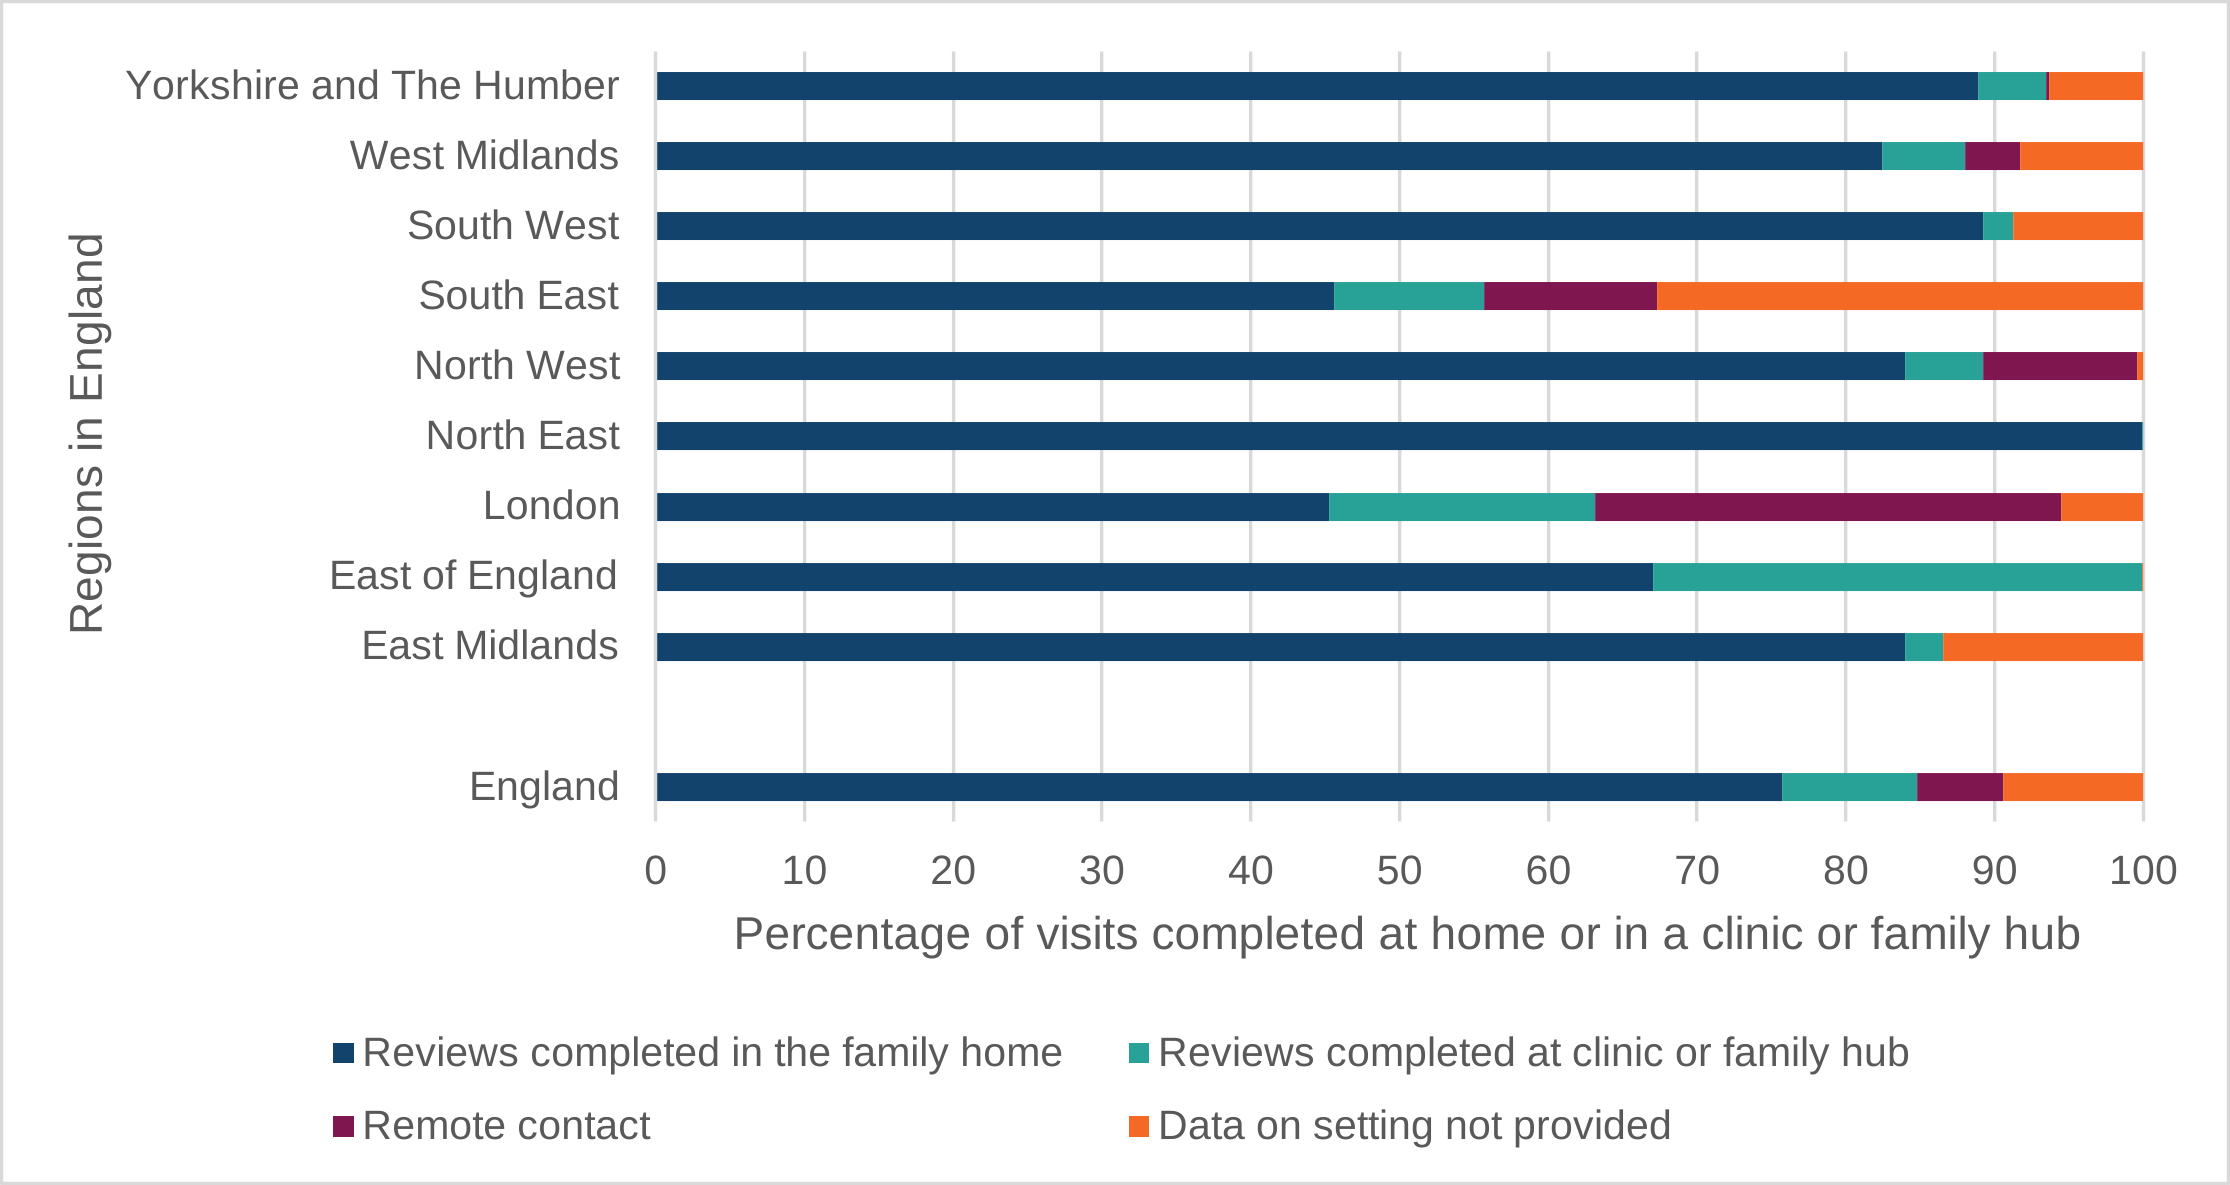
Figure 6: percentage of antenatal reviews carried out at home or in a clinic or family hub in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 6 shows the percentage of antenatal reviews carried out in the family home, in a clinic or family hub, remotely or with no setting data reported for England and the 9 English regions in 2025. Nationally, most antenatal reviews took place in the family home.
This data can be found in table 5 in the data tables published alongside this report.
New birth review
The new birth review takes place when a baby is aged between one day and 2 weeks old. It focuses on early postnatal health, bonding and safety. Best practice is for a health visitor to carry out the new birth review in the family home.
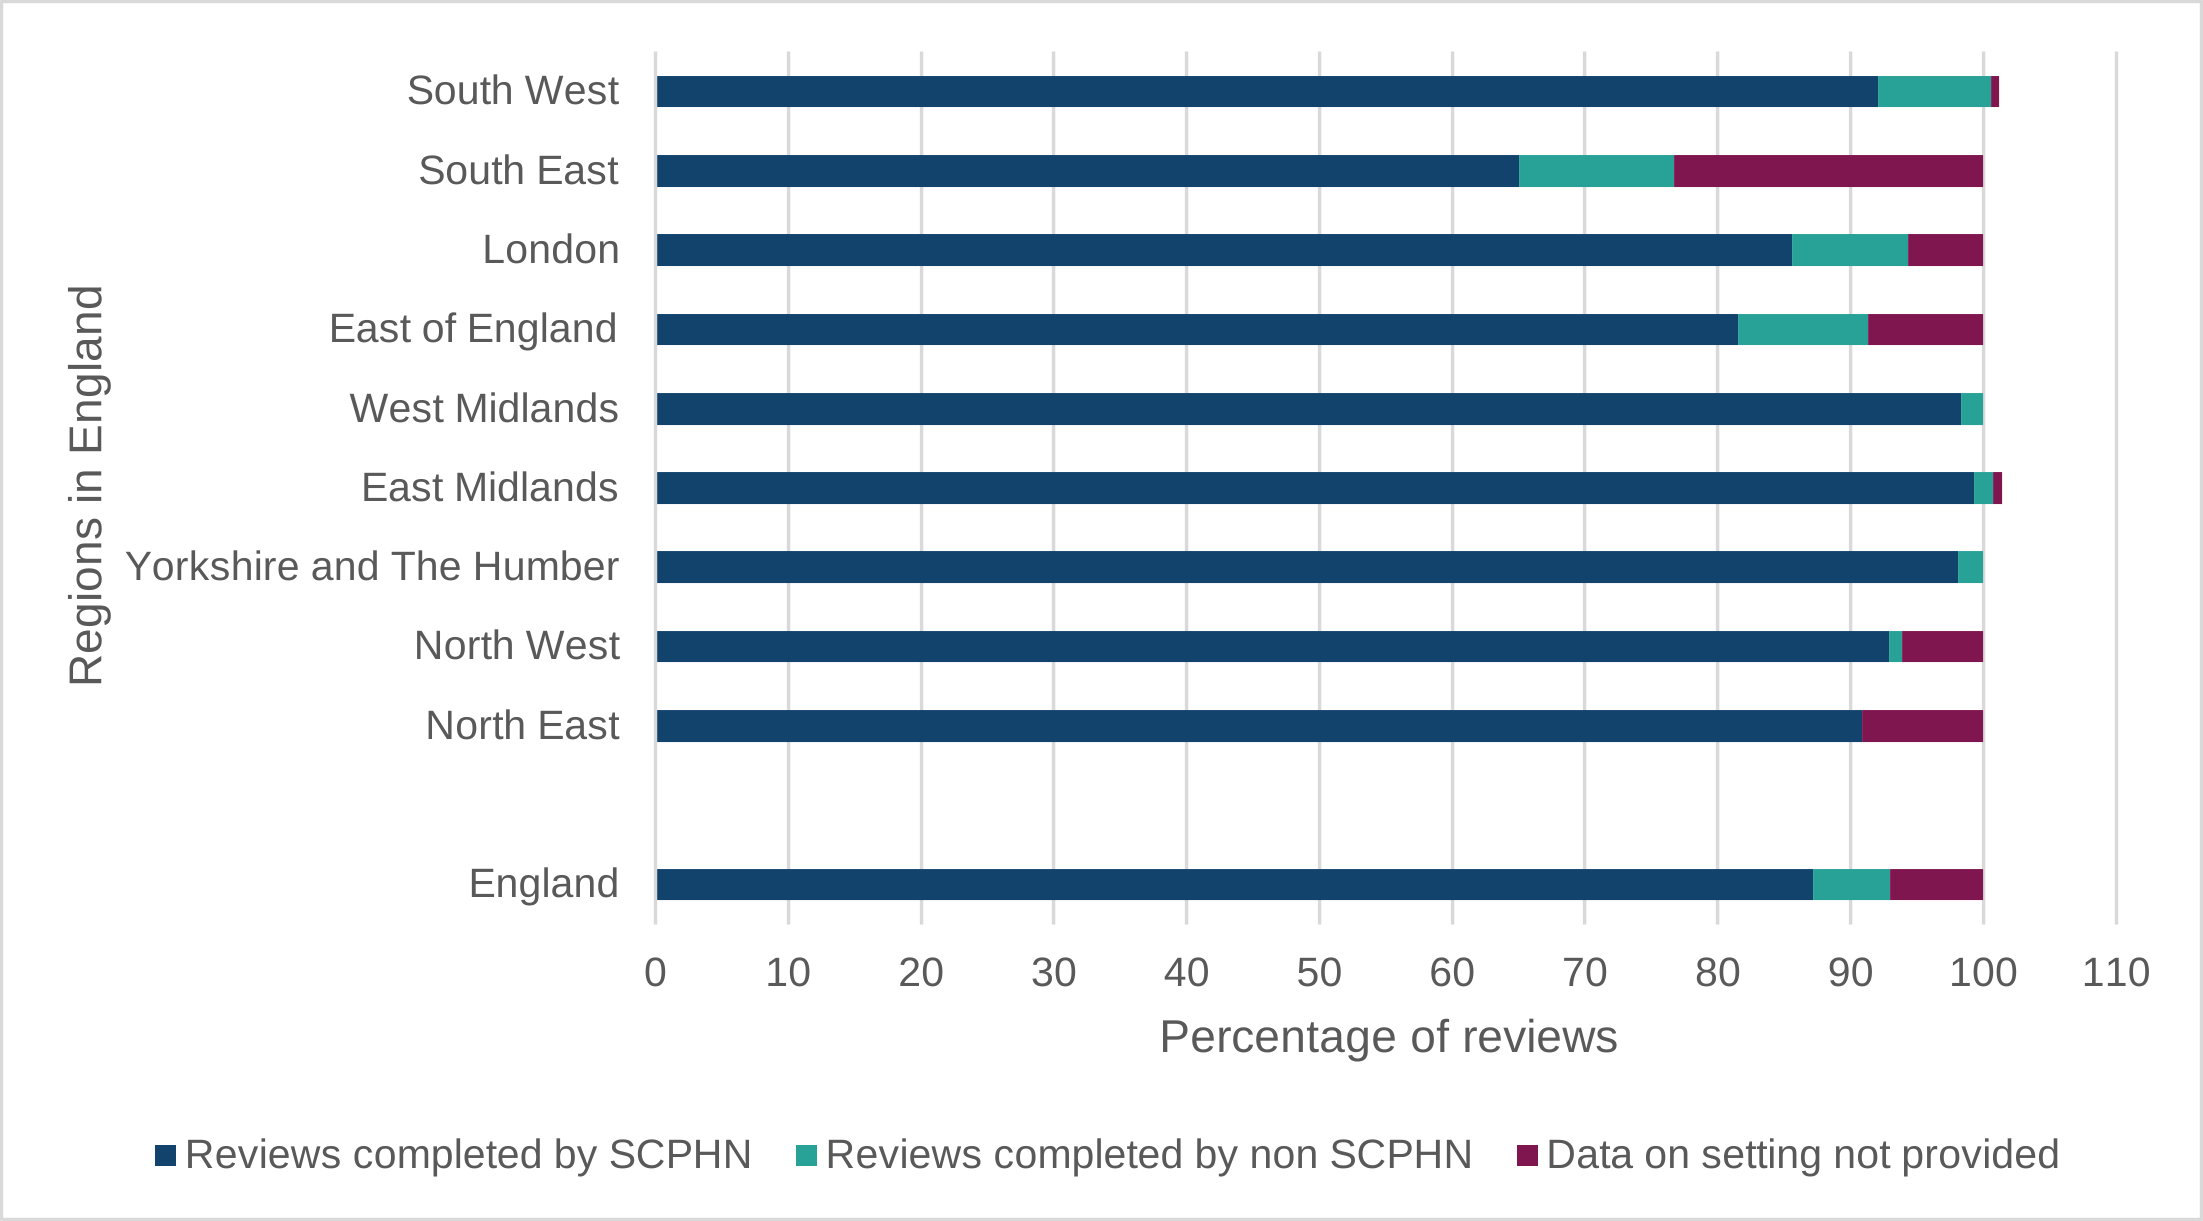
Figure 7: percentage of new birth reviews carried out by staff type (SCPHN compared with non-SCPHN) in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 7 shows the percentage of new birth visits carried out by SCPHNs and non-SCPHN staff, and visits with no staff-type data reported for England and the 9 English regions in 2025. SCPHN staff carried out most new birth visits nationally and in every region.
This data can be found in table 5 in the data tables published alongside this report.
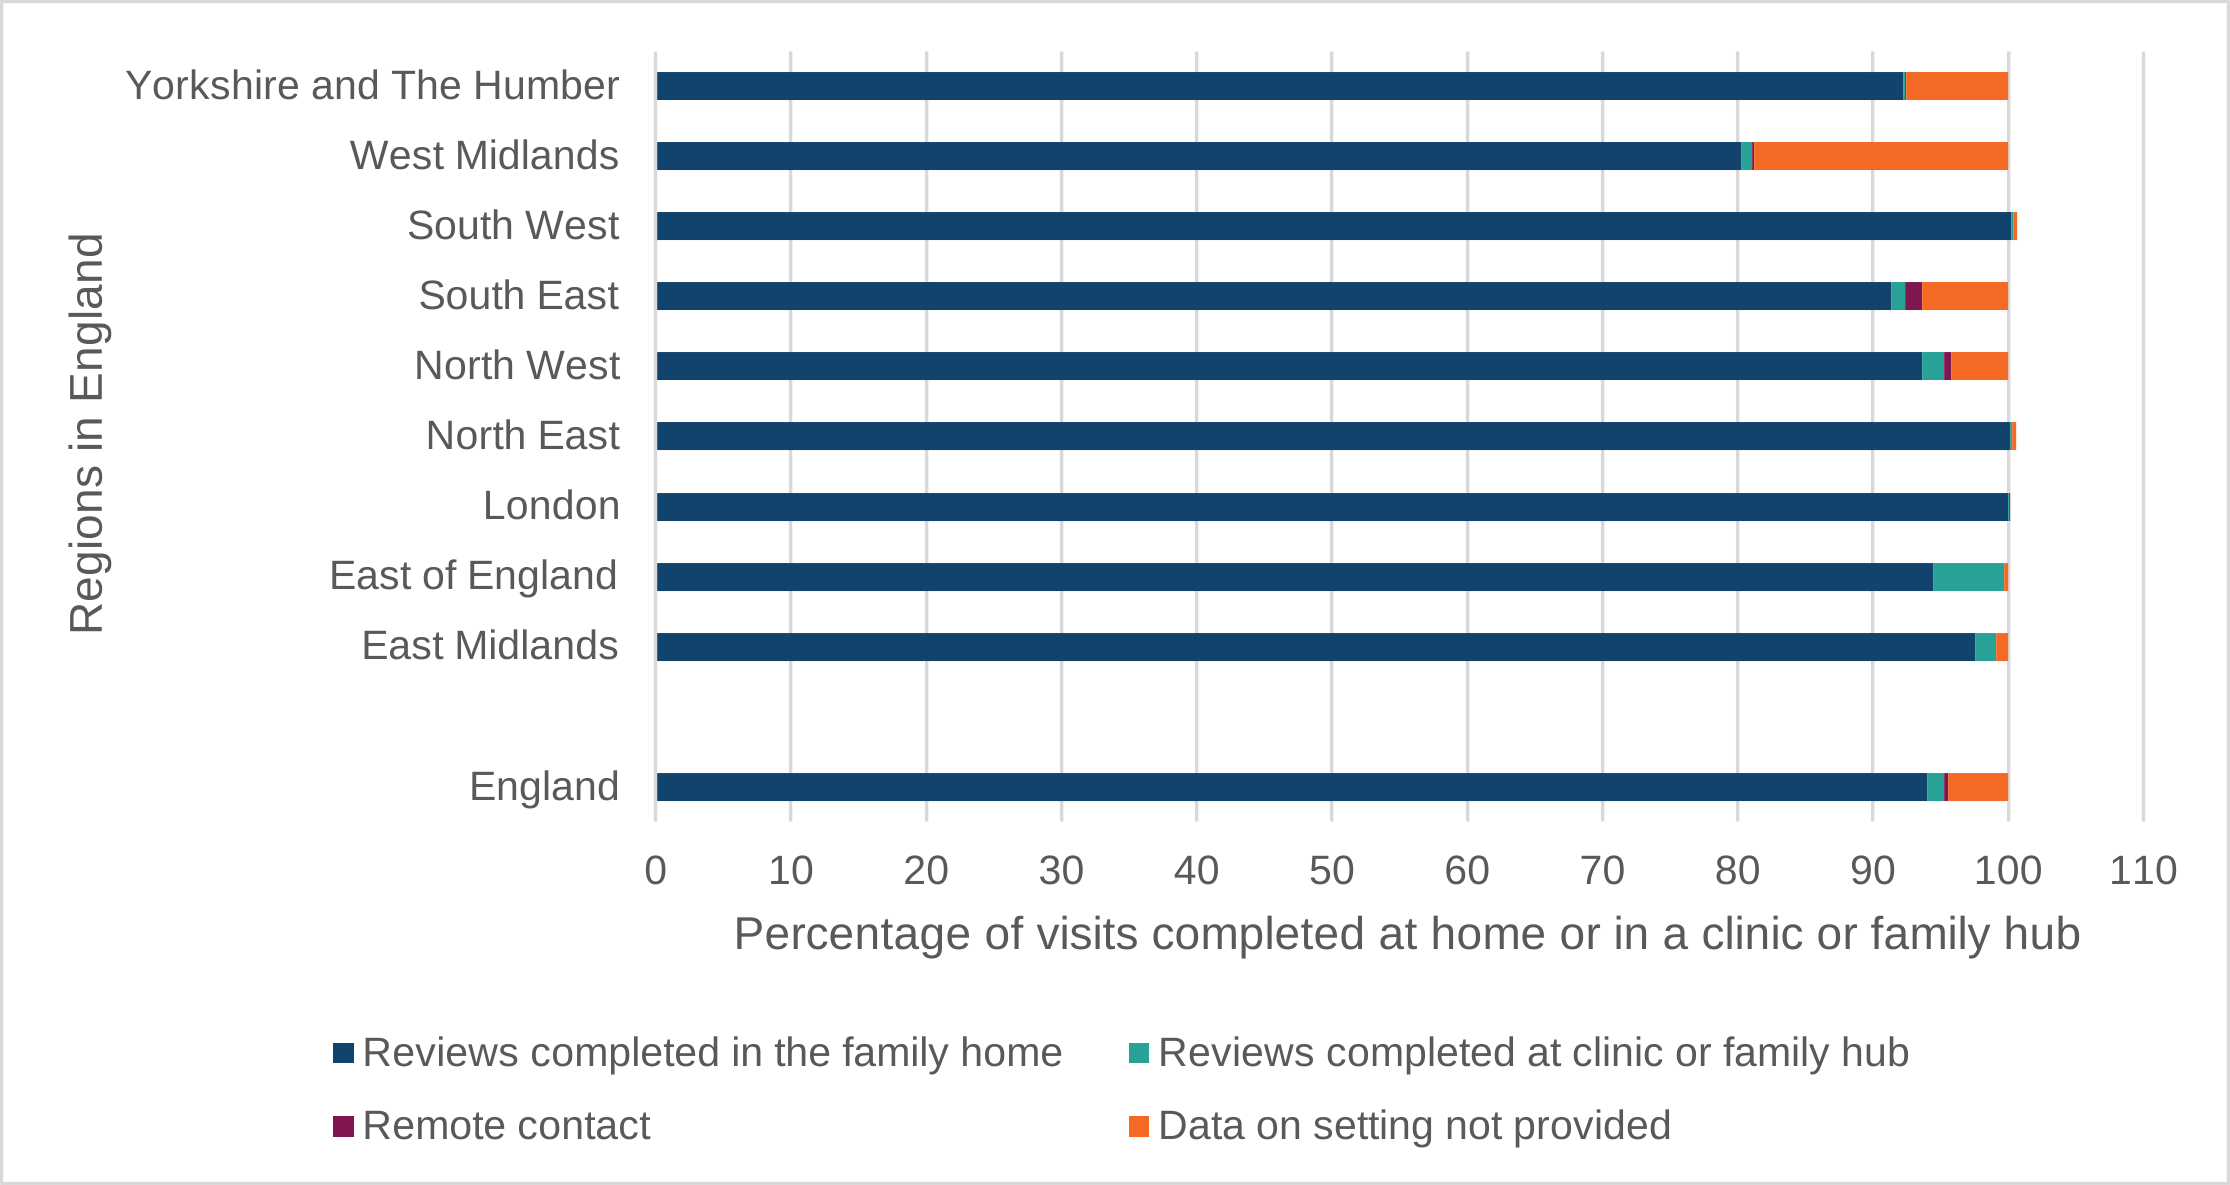
Figure 8: percentage of new birth reviews carried out at home or in a clinic or family hub in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 8 shows the percentage of new birth visits carried out in the family home, in a clinic or family hub, remotely or with no setting data reported for England and the 9 English regions in 2025. Home visits accounted for the vast majority of new birth visits nationally and were the dominant delivery model in every region. Clinic, family hub and remote delivery represented only a small proportion of visits, although some regions reported higher levels of missing setting data, particularly the West Midlands and South East.
This data can be found in table 5 in the data tables published alongside this report.
6 to 8 week health and development review
The 6 to 8 week review takes place when a baby is 6 to 8 weeks old. It focuses on adjustment, early development and family wellbeing. Best practice is for a health visitor to carry out the 6 to 8 week review in the family home.
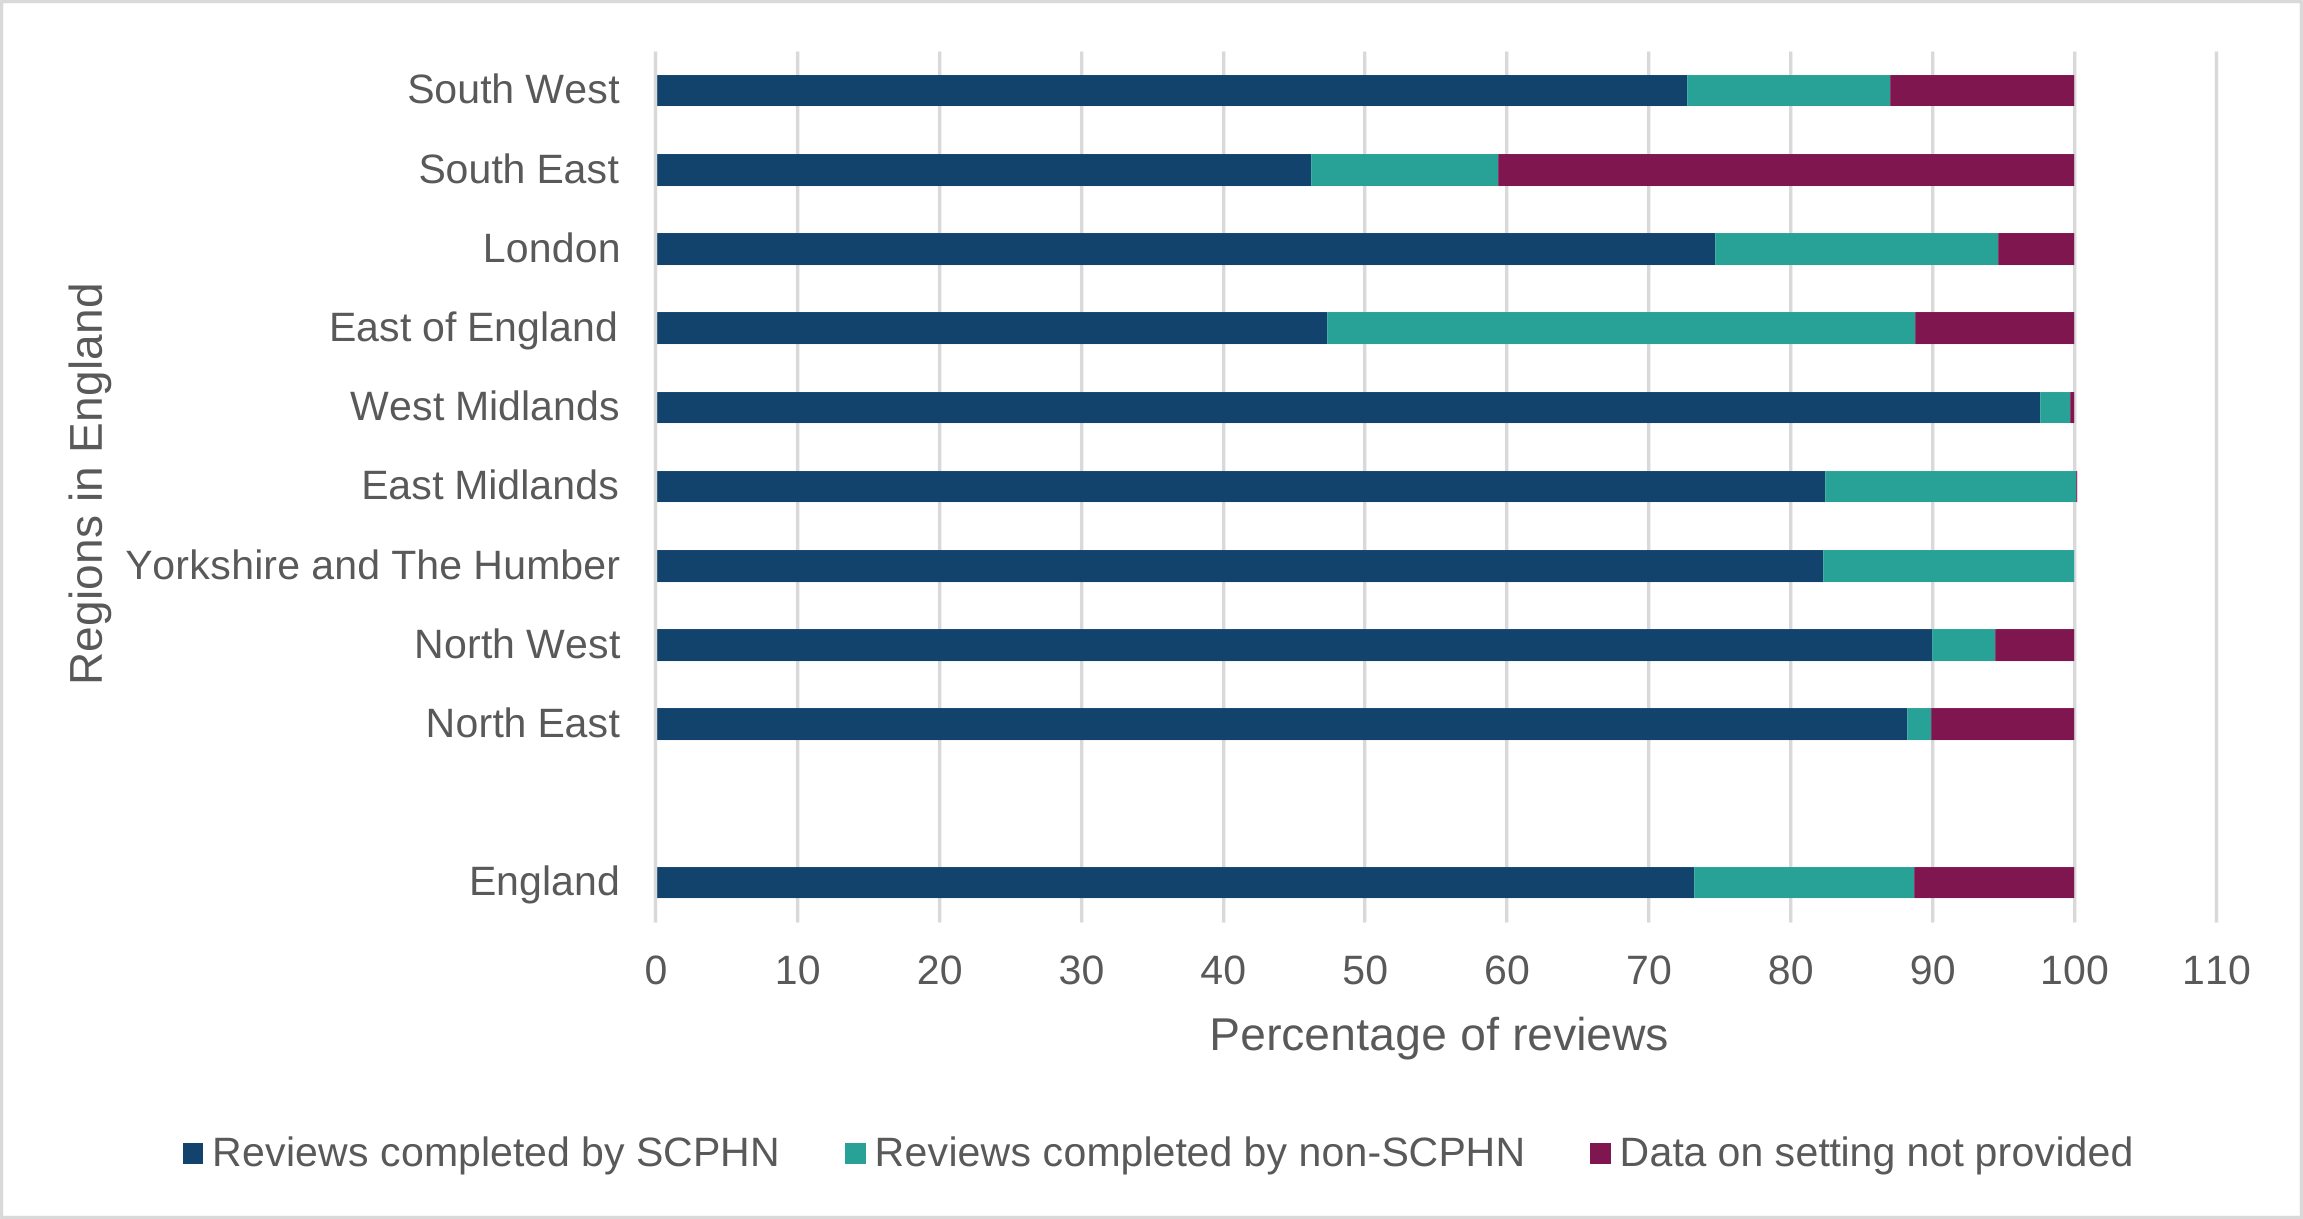
Figure 9: percentage of 6 to 8 week reviews carried out by staff type (SCPHN compared with non-SCPHN) in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 9 shows the percentage of 6 to 8 week reviews carried out by SCPHNs and non-SCPHN staff, and reviews with no staff-type data reported across England and the 9 English regions in 2025. SCPHN staff carried out most reviews nationally, although the proportion varied considerably between regions. Missing staff type data was particularly high in the South East.
This data can be found in table 5 in the data tables published alongside this report.
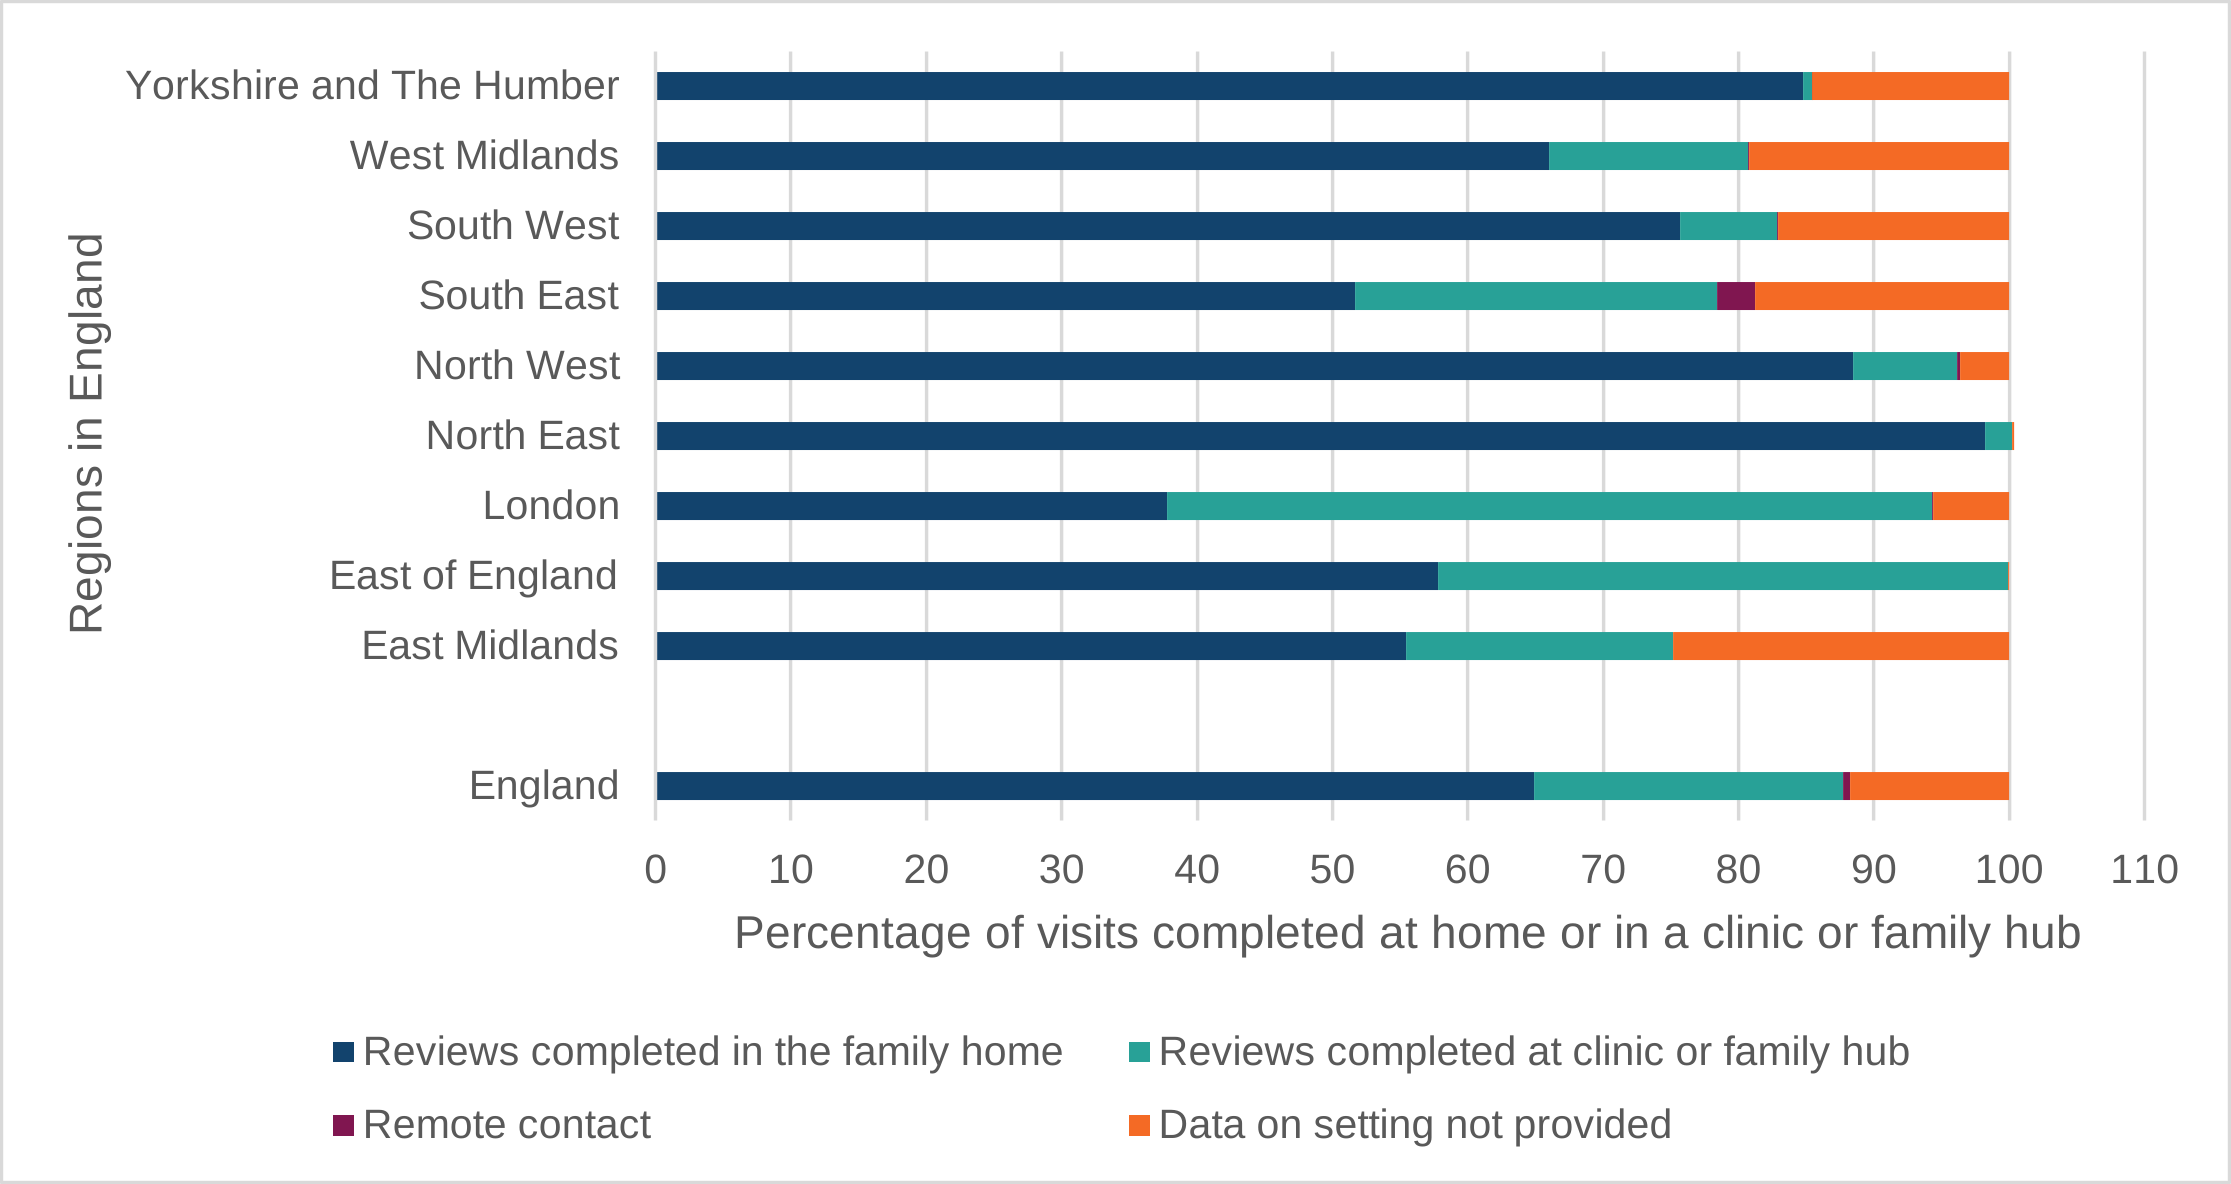
Figure 10: percentage of 6 to 8 week health and development reviews carried out at home or a clinic or family hub in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 10 shows the percentage of 6 to 8 week reviews carried out in the family home, in a clinic or family hub, remotely or with no setting data reported across England and the 9 English regions in 2025. Most reviews took place in the family home nationally, although clinic and family hub delivery also accounted for a substantial proportion of activity. Missing setting data varied considerably across regions and was highest in the East Midlands.
This data can be found in table 5 in the data tables published alongside this report.
9 to 15 month health and development review
The 9 to 15 month review takes place when a baby is between 9 and 15 months old. It focuses on mobility, independence and emerging behaviour. The review may take place in the family home or another suitable setting, such as a clinic, neighbourhood health centre or Best Start family hub. The health visitor and family should agree the location. The healthy child programme guidance states that a health visitor should carry out the review.
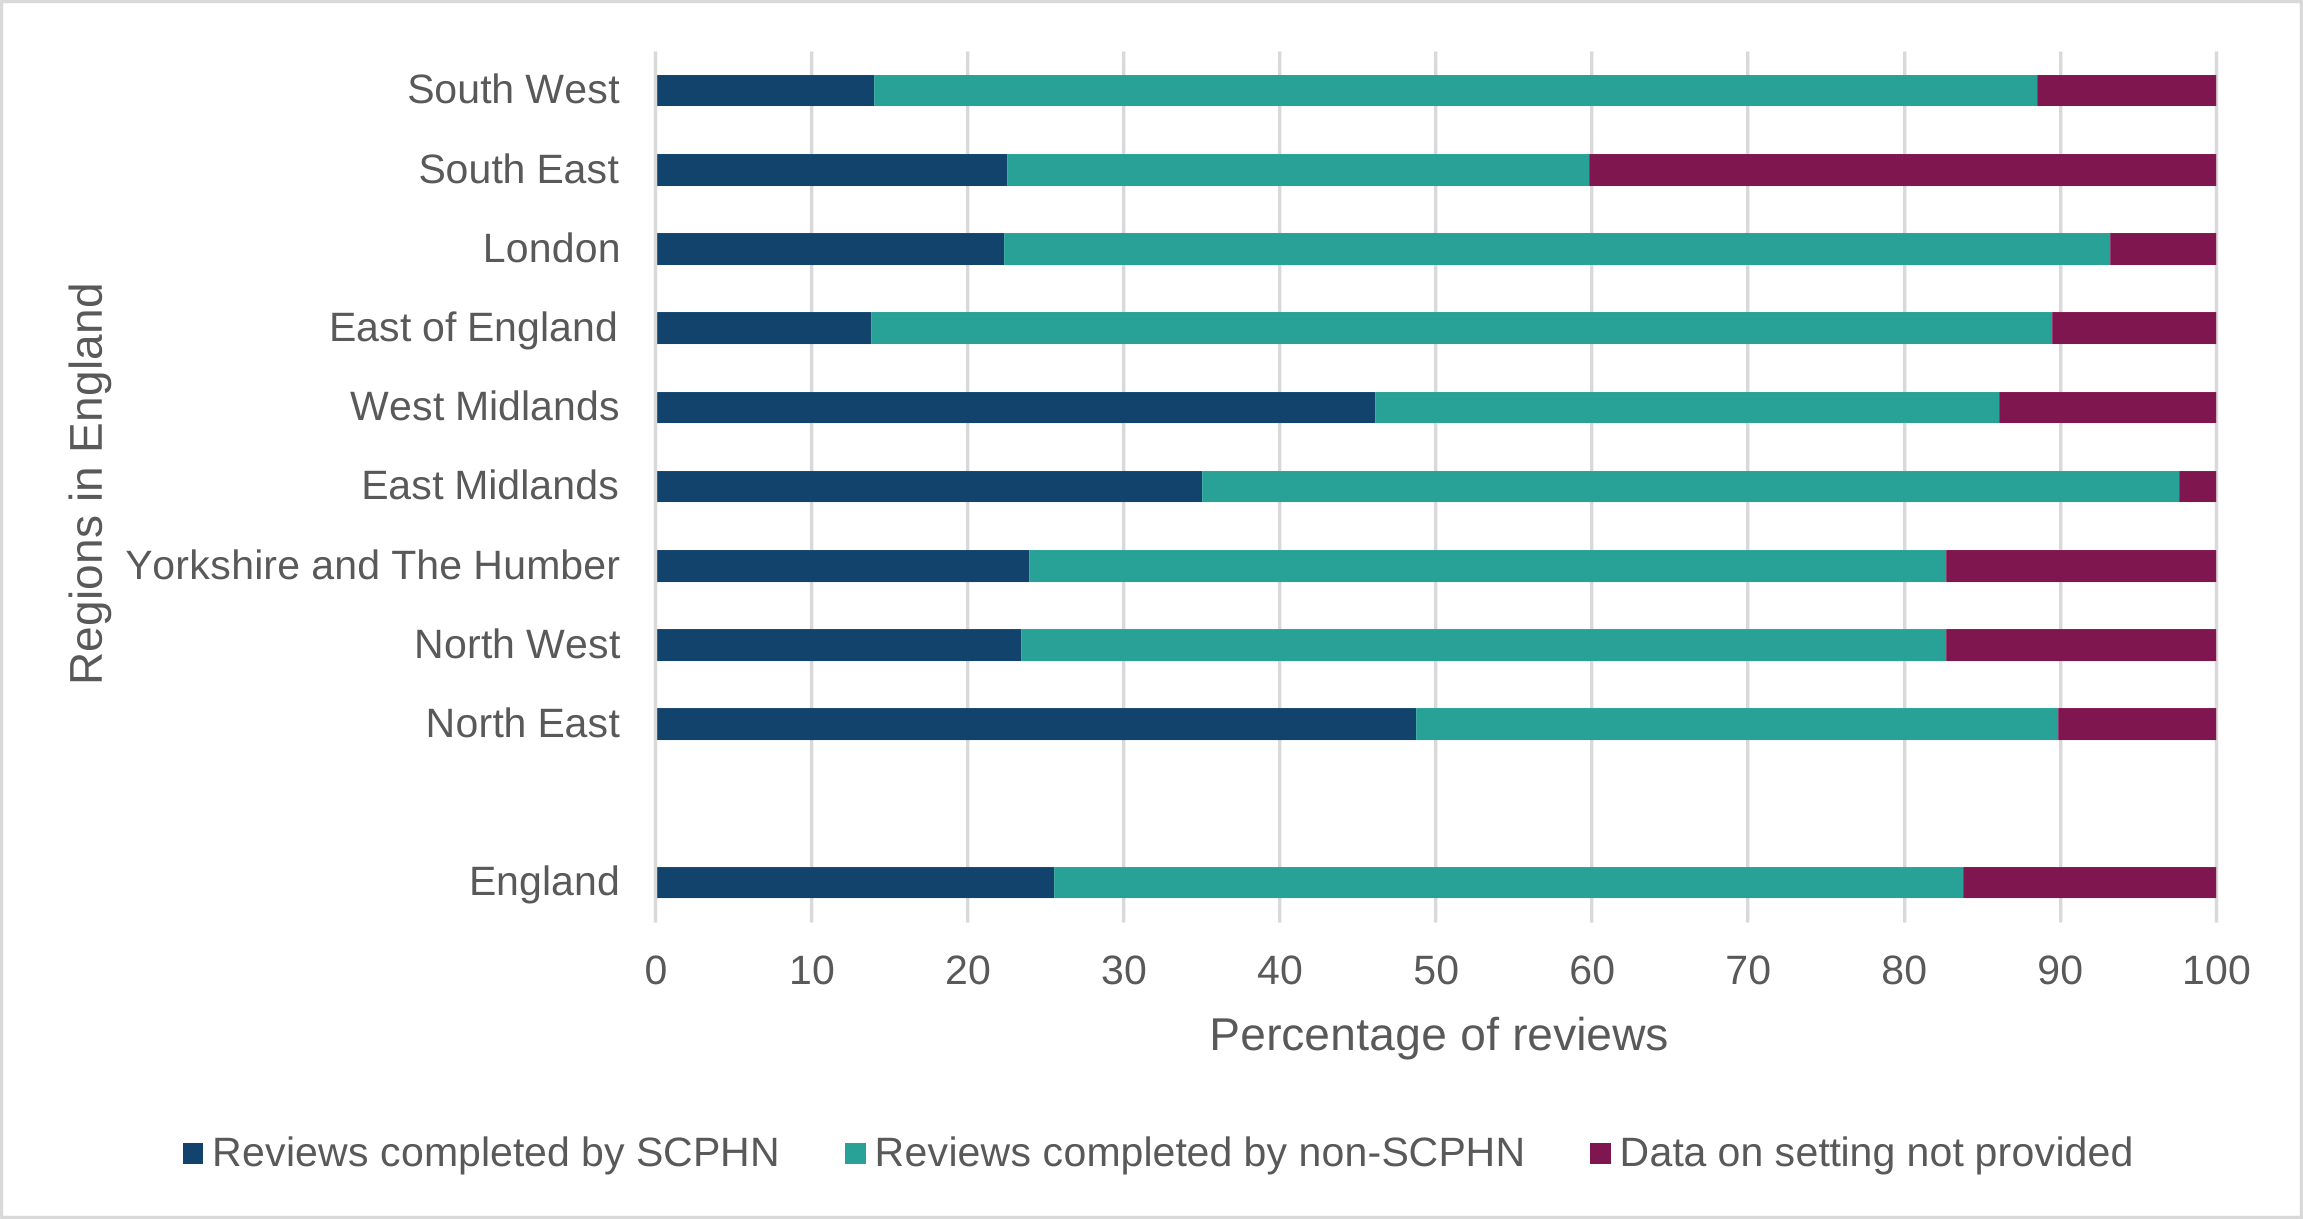
Figure 11: percentage of 9 to 15 month health and development reviews carried out by staff type (SCPHN compared with non-SCPHN) in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 11 shows the percentage of 9 to 15 month reviews carried out by SCPHNs and non-SCPHN staff, and reviews with no staff-type data reported across England and the 9 English regions in 2025. Nationally, non-SCPHN staff carried out most reviews, while SCPHN staff carried out around one-quarter. Missing staff-type data was particularly high in the South East.
This data can be found in table 5 in the data tables published alongside this report.
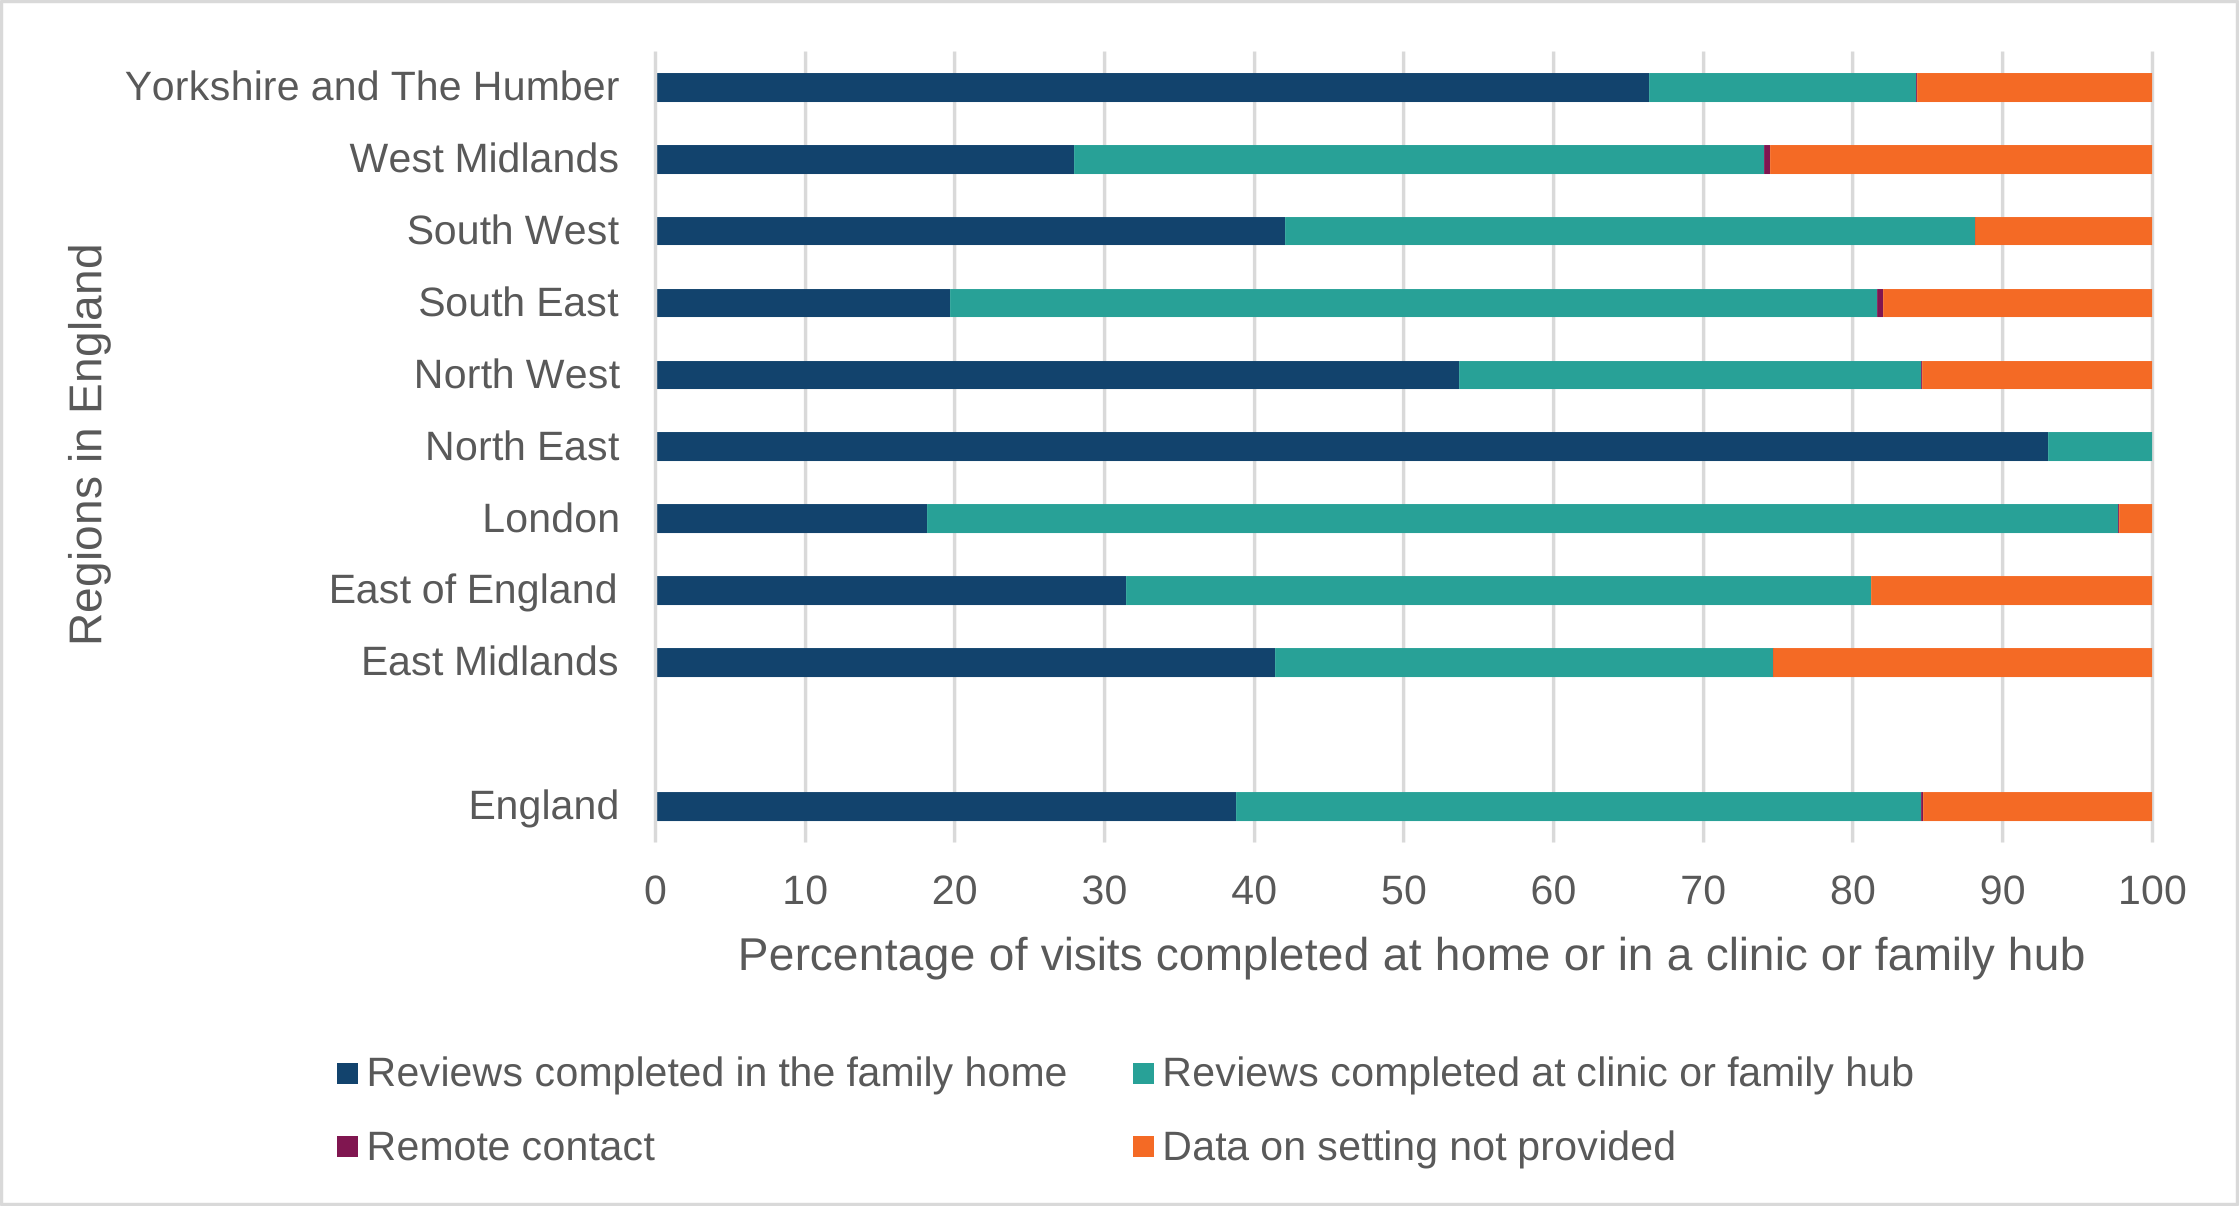
Figure 12: percentage of 9 to 15 month health and development reviews carried out at home or a clinic or family hub in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 12 shows the percentage of 9 to 15 month reviews carried out in the family home, in a clinic or family hub, remotely or with no setting data reported across England and the 9 English regions in 2025. Clinics and family hubs accounted for the largest proportion of reviews nationally, although patterns varied across regions. Missing setting data ranged from none in the North East to around one-quarter of reviews in the East Midlands and West Midlands.
This data can be found in table 5 in the data tables published alongside this report.
2 to 2 and a half year health and development review
The 2 to 2 and a half year review takes place when a child is between 24 and 30 months old. It focuses on readiness for early learning and independence. The review may take place in the family home or another suitable setting, such as a clinic, neighbourhood health centre or Best Start family hub. The health visitor and family should agree the location. The healthy child programme guidance states that a health visitor should carry out the review.
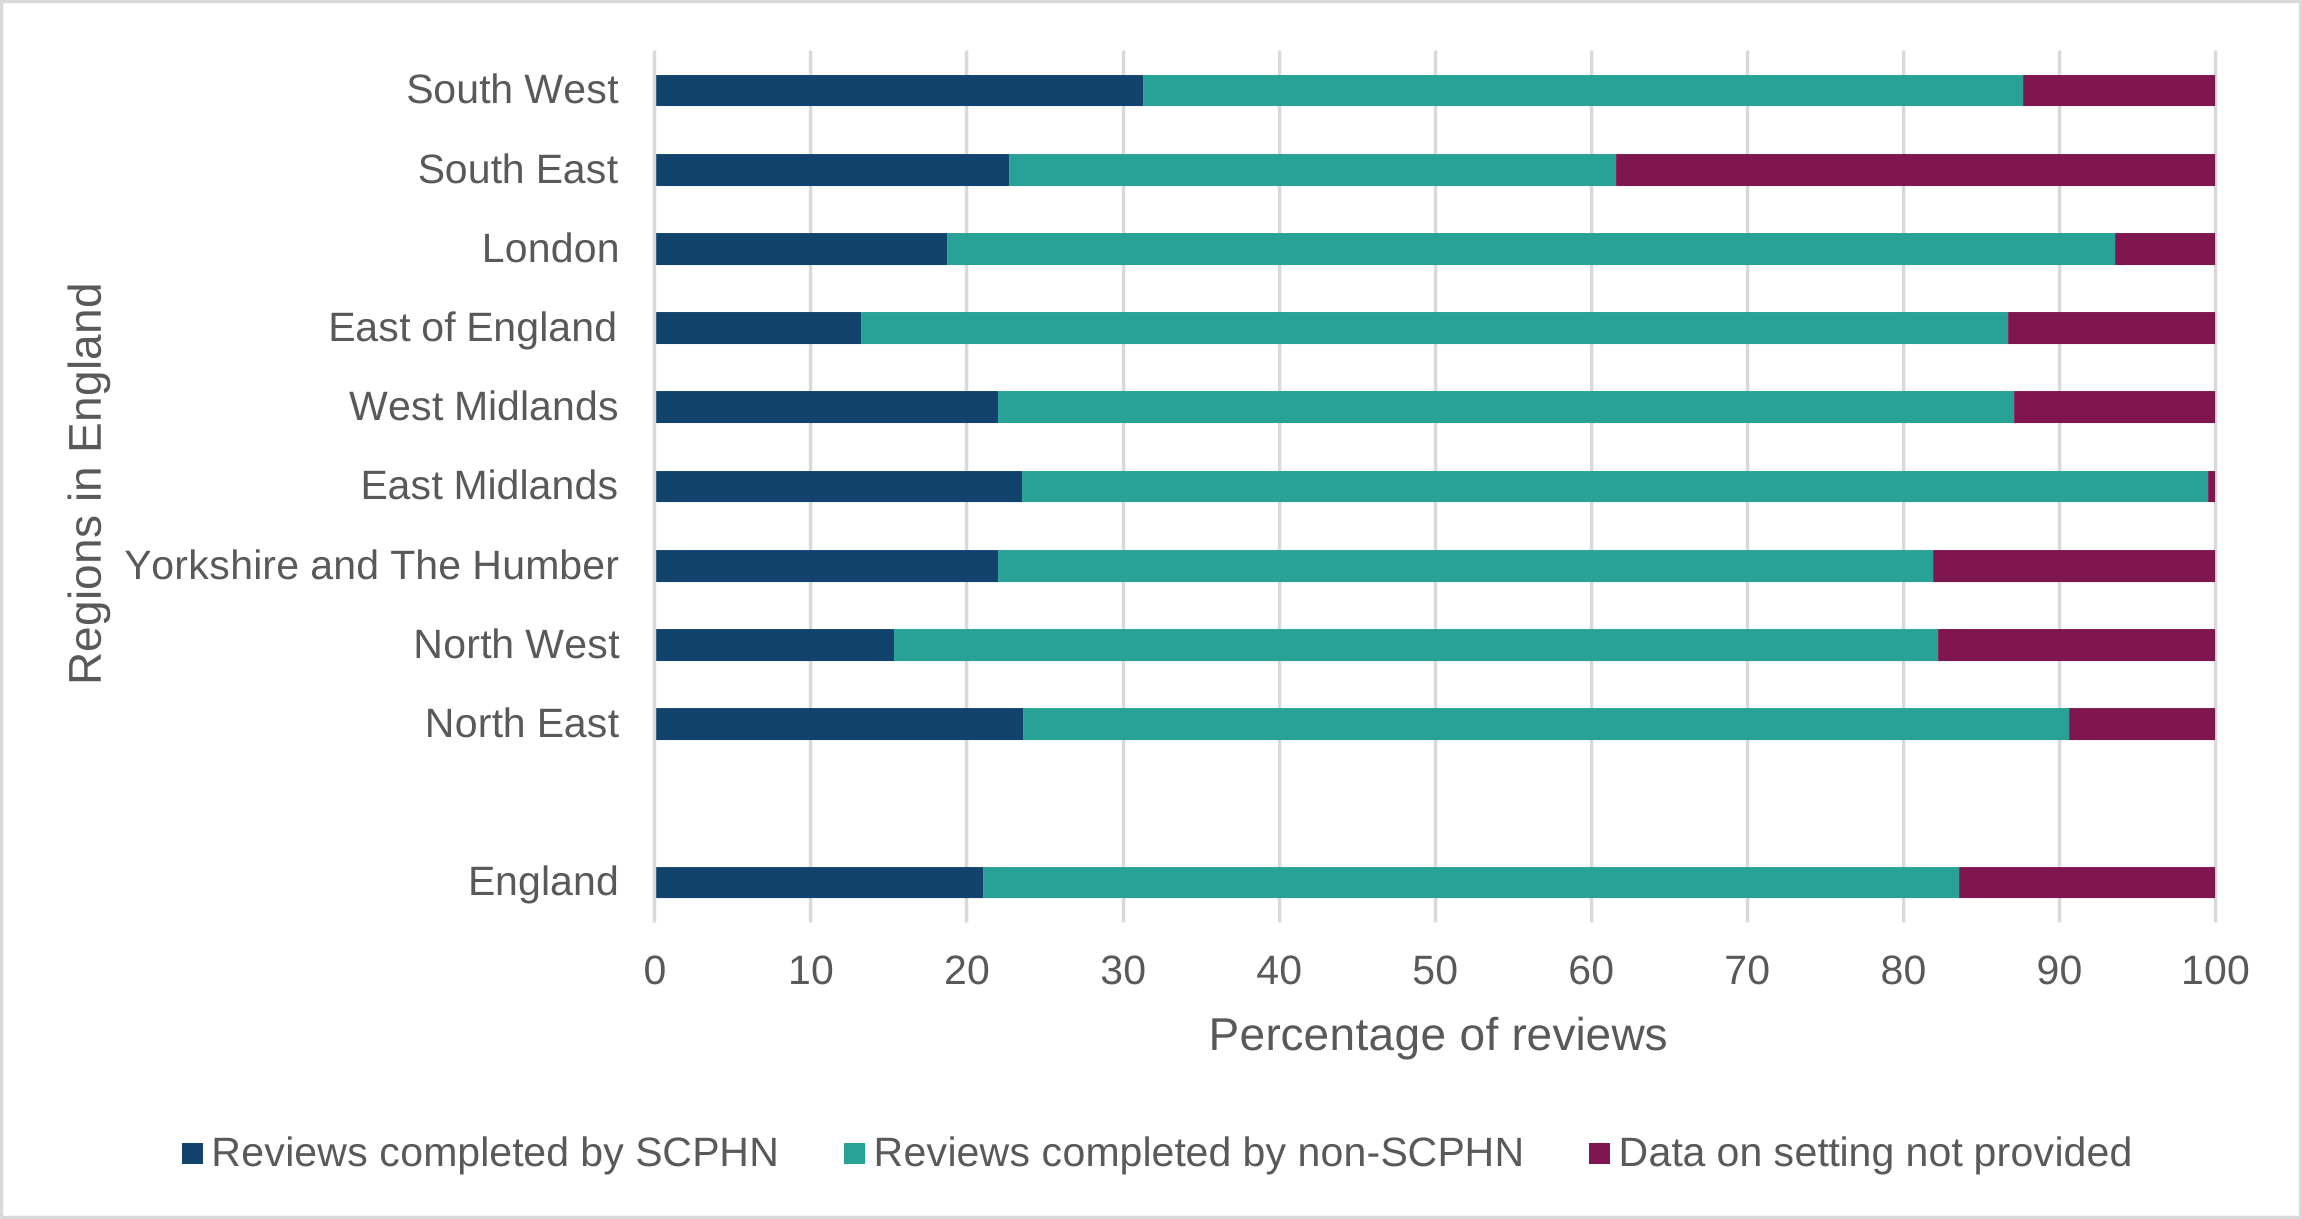
Figure 13: percentage of 2 to 2 and a half year health and development reviews carried out by staff type (SCPHN compared with non-SCPHN) in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 13 shows the percentage of 2 to 2 and a half year reviews carried out by SCPHNs, non-SCPHN staff, and reviews with no staff-type data reported across England and the 9 English regions in 2025. Nationally, non-SCPHN staff carried out most reviews, while SCPHN staff carried out around one-fifth. Missing staff-type data varied across regions and was highest in the South East.
This data can be found in table 5 in the data tables published alongside this report.
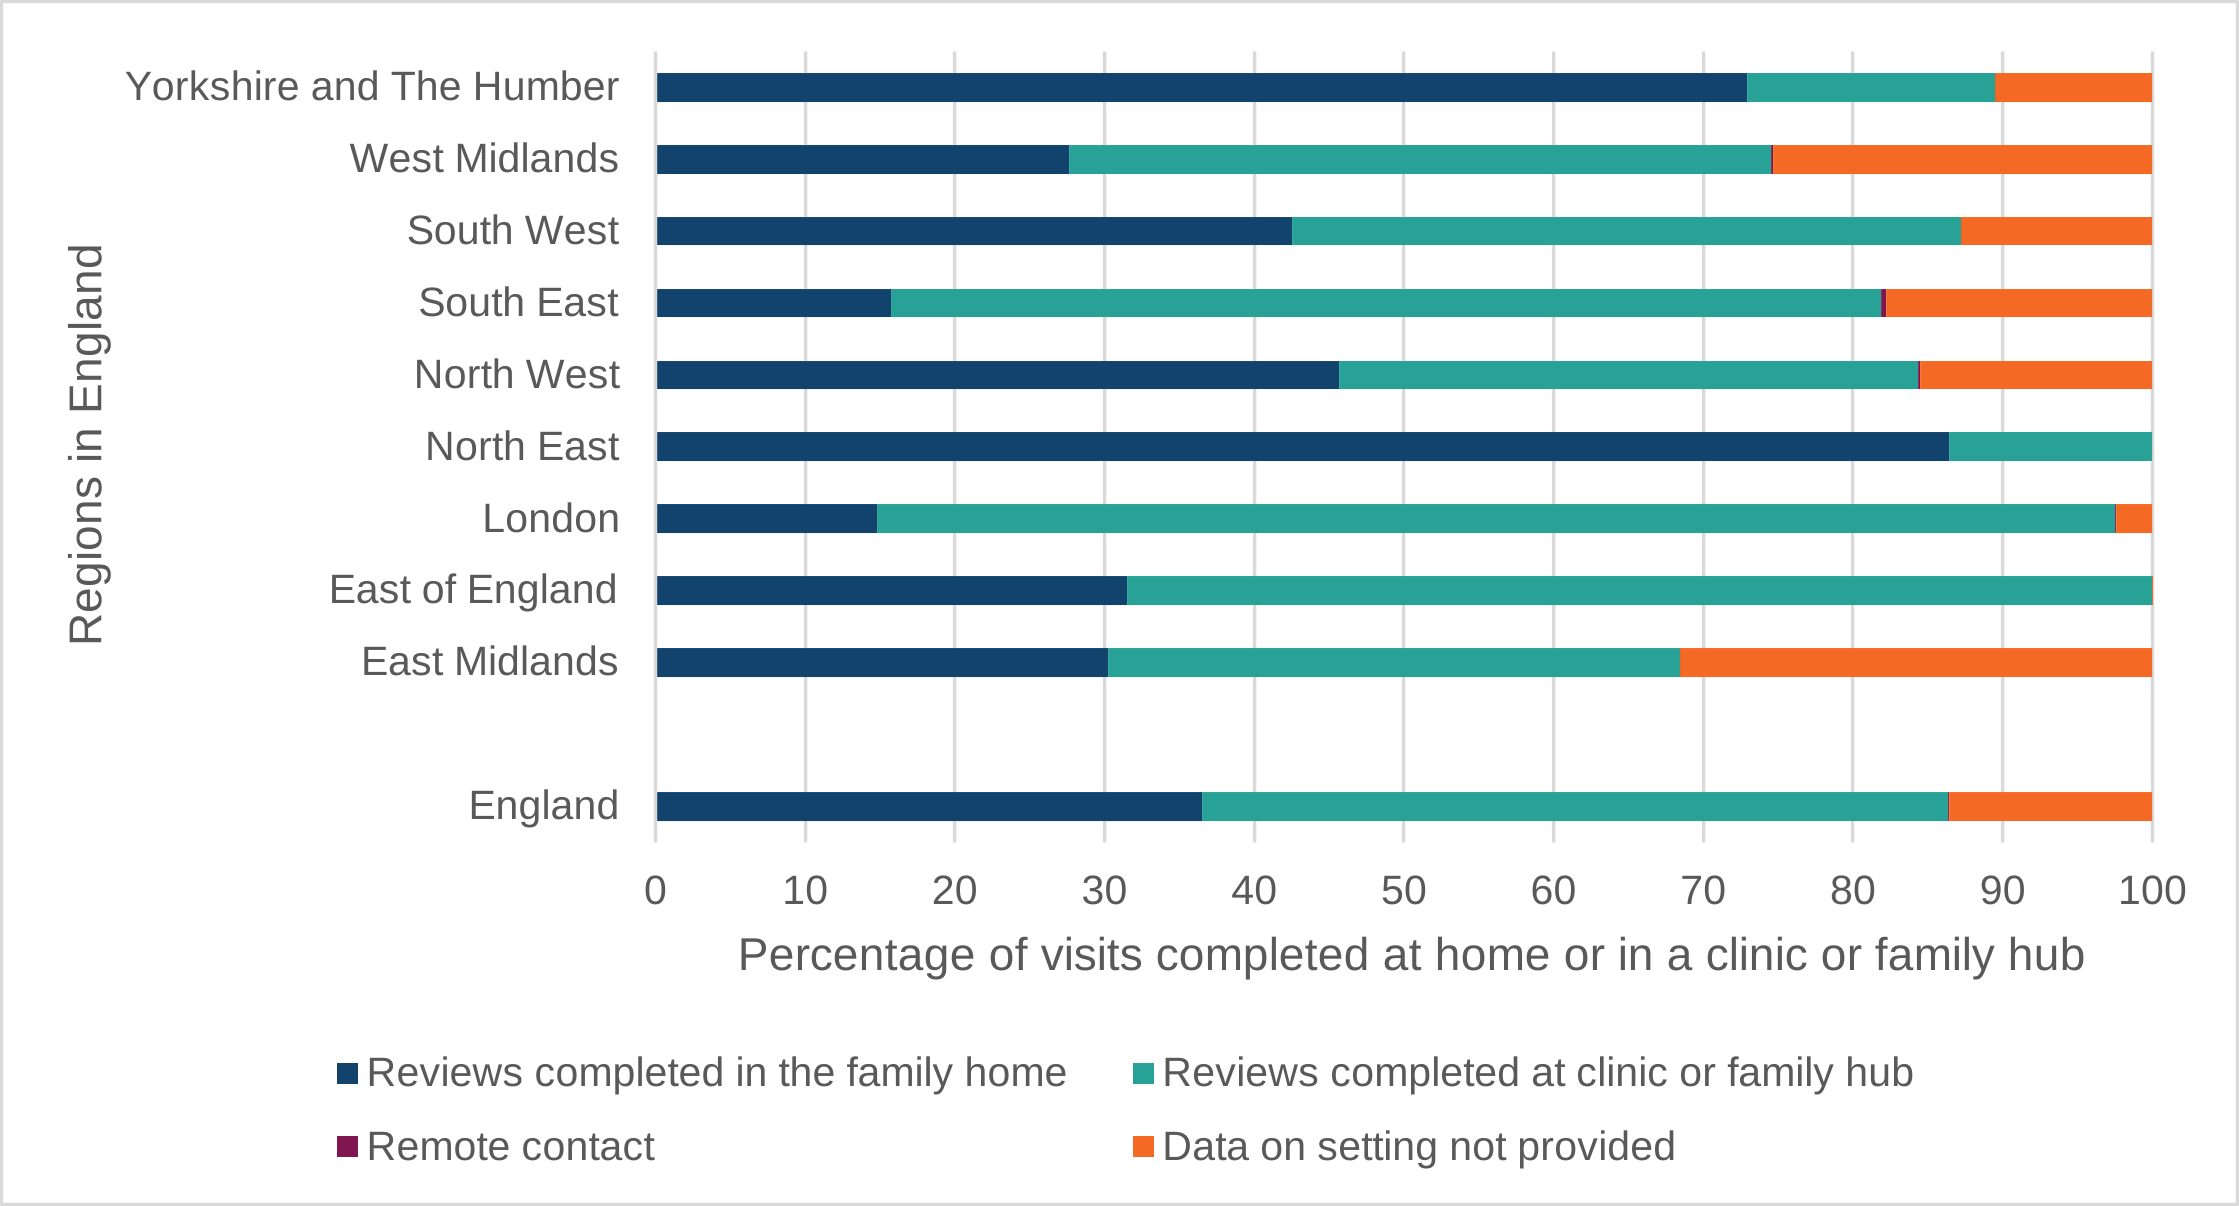
Figure 14: percentage of 2 to 2 and a half year health and development reviews carried out at home or in a clinic or family hub in each region in England, 2025
Source: children’s public health nursing - workforce and activity, 2025 data return
Figure 14 shows the percentage of 2 to 2 and a half year reviews carried out in the family home, in a clinic or family hub, remotely or with no setting data reported across England and the 9 English regions in 2025. Clinics and family hubs accounted for the largest proportion of reviews nationally, followed by home visits. Missing setting data was particularly high in the East Midlands, West Midlands and South East.
This data can be found in table 5 in the data tables published alongside this report.
Non-statutory health and development reviews
Additional targeted health and development reviews can take place at any point from birth to age 5 based on assessed need. While not part of the statutory offer, additional targeted reviews may be particularly valuable at certain time points, at around 3 months, 6 months or 3 and a half years old and are recommended in the healthy child programme for children requiring targeted support. These time points align with known developmental milestones and public health opportunities.
Not all local councils offer these reviews as a standard pathway but those who do are found distributed across the country and not confined to one region. The full data set gives more information.
Table 5: number of local councils delivering non-statutory additional targeted health and development reviews as a standard pathway, 2025
| Non-statutory reviews | Number of local councils that are delivering additional targeted reviews out of the 145 that responded |
|---|---|
| Follow-up antenatal | 4 |
| 3 to 4 months | 43 |
| 18 months | 7 |
| 3 to 3 and a half year | 18 |
| Other | 27 |
5 to 19 school nursing activity
Of the 145 responding local councils, 141 offered at least one school nursing service. Four submitted no data to this question. The total for each row in the table below differs because not all local councils answered yes or no for every service or programme during data collection.
Table 6: school nursing services offered by local councils, 2025
| School nursing offer | Number of local councils that responded to the question | Percentage of local councils that responded ‘yes’ |
|---|---|---|
| ChatHealth or similar digital health advice service | 141 | 62% |
| Community-based drop-ins or activities | 137 | 62% |
| Relationships and sex education (RSE) | 137 | 47% |
| School-based immunisation programmes | 137 | 4% |
| Bedwetting (enuresis) clinics | 140 | 58% |
| Health assessments for vulnerable children | 140 | 94% |
| Other additional service | 76 | 79% |
| Safeguarding contacts or conferences | 144 | 100% |
| School-entry health questionnaires or reviews | 141 | 64% |
| Support for children with specific health needs | 138 | 62% |
| Training for school staff and others | 140 | 68% |
| Universal drop-in clinics in secondary schools | 140 | 74% |
The data shows that:
- the most common school nursing services were health assessments for vulnerable children and universal drop-in clinics in secondary schools. At least 100 local councils offered each service
- safeguarding contacts and conferences were carried out by SCPHNs in all responding local councils as an expected statutory and professional requirement for the SCPHN role
- school-based immunisation programmes were the least commonly reported service - 6 local councils reported offering them through school nurses
- about two-thirds of local councils offered training for school staff and others
- about 60% of local councils offered each of these services:
- ChatHealth or a similar digital health advice service
- community-based drop-ins or activities
- support for children with specific health needs
- bedwetting (enuresis) clinics
About these statistics and future developments
This is the first publication of statistics on the children’s public health nursing: workforce and activity data set. DHSC will publish these statistics every year. Official statistics are produced in accordance with the Statistics and Registration Service Act 2007 and the Office for Statistics Regulation’s Code of Practice for Statistics.
We produce these statistics in line with the code’s 3 pillars: trustworthiness, quality and value.
Any comments about these statistics in development can be sent to:
0-19clinicalprogrammesunit@dhsc.gov.uk
Methodology
Correction factor
We used a population-based scaling factor to estimate national figures. This accounted for the 6 local councils that did not submit workforce data. We divided England’s population aged 0 to 5 (3,072,243) by the population covered by responding councils (2,956,757) using the most up to date Office for National Statistics population data for the year 2025 accessed through the Nomis platform. This produced a correction factor of 1.0391.
We multiplied observed workforce totals from responding councils by this factor to estimate national health visiting and school nursing workforces. This assumes similar relationships between workforce numbers and populations aged 0 to 5 in responding and non-responding councils.
Limitations
The non-responding local councils were:
- Stockton-on-Tees (North East)
- Warwickshire (West Midlands)
- Hillingdon (London)
- Lewisham (London)
- Newham (London)
- Windsor and Maidenhead (South East)
Estimates may be biased if these councils differ in ways not captured by population data from responding councils. Take care when interpreting the data or comparing regional estimates and charts.
The correction factor is unlikely to materially alter national conclusions, even under plausible alternative assumptions. The local councils that responded covered 96% of the target population. The correction factor increased estimates by approximately 4%: by around 531 WTE for health visiting and 166 WTE for school nursing.
Among responding councils, the median was 2.16 WTE health visitors per 1,000 children aged 0 to 5. The interquartile range was 1.76 to 2.95. This shows workforce levels varied across responding councils. The middle 50% of councils fell within this range.
For service activity, the denominator is the total completed health and development reviews reported for each statutory health and development review. Therefore, not all totals add up to 100%. Sometimes, reviews by staff type or location do not equal the total reported. Totals above 100% may reflect overcounting, particularly of remote contacts.
The full methodology explains the data sources, methods, processing, measures, calculations, geographical aggregation, rounding, data quality, interpretation and reproducibility in more detail.