Spotlight on sexually transmitted infections in the West Midlands: 2025 data
Updated 8 October 2026

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/sexually-transmitted-infections-west-midlands-data/spotlight-on-sexually-transmitted-infections-in-the-west-midlands-2025-data
Summary
While this report primarily focuses on the trend between 2024 and 2025, some trends relative to 2019 or earlier are included to provide a comparison to sexual health service provision and sexually transmitted infection (STI) diagnoses prior to the COVID-19 pandemic during 2020 and 2021. For England, the numbers of consultations, sexual health screens and STI diagnoses in 2020 and 2021 are lower than preceding years and any trends during periods which include those years must be interpreted in that context.
STIs represent an important public health problem in the West Midlands. Of all the UK Health Security Agency (UKHSA)’s regions it has the fourth lowest rate of new STIs in England.
27,460 new STIs were diagnosed in the West Midlands population in 2025, a rate of 444 diagnoses per 100,000 population. Rates by upper tier local authority (UTLA) ranged from 230 new STI diagnoses per 100,000 in Herefordshire, County of to 759 new STI diagnoses per 100,000 in Birmingham.
The number of new STIs diagnosed in the West Midlands population increased by less than 0.5% between 2024 and 2025. Changes were seen in the numbers of the 5 main STIs: syphilis decreased by 15%, gonorrhoea decreased by 5%, chlamydia decreased by 1%, genital herpes increased by 24% and genital warts increased by 2%.
UKHSA recommends that local areas should be working towards achieving a chlamydia detection rate no lower than 3,250 per 100,000 among women aged 15 to 24 years and this is an indicator in the Public Health Outcomes Framework. In 2025, the chlamydia detection rate among West Midlands women aged 15 to 24 years was 1,232 per 100,000 compared to 1,264 per 100,000 in 2024.
Rates of new STIs vary slightly between men and women (443 and 422 per 100,000, respectively). Where gender and sexual orientation are known, gay, bisexual and other men who have sex with men (GBMSM) account for 15% of the West Midlands population diagnosed with a new STI excluding chlamydia diagnoses reported via CTAD (50% of those diagnosed with syphilis and 41% of those diagnosed with gonorrhoea).
STIs disproportionately affect young people. The West Midlands population aged between 15 and 24 years accounted for 41% of all new STI diagnoses in 2025. A steep decline has been seen in genital warts diagnosis rates in females aged 15 to 19 following the introduction in 2008 of vaccination against human papillomavirus (HPV), the virus which causes genital warts, for girls. Recent years have seen fluctuating rates though, with a 98% decrease in West Midlands from 2016 to 2025.
The White ethnic group has the highest number of new STI diagnoses: 14,736 (60%). Although 9% of new STIs are in the Black Caribbean ethnic group, they have the highest rate: 2,443 per 100,000, which is 7.6 times the rate seen in the White ethnic group. Where country of birth was known, 81% of the West Midlands population diagnosed with a new STI in 2025 (excluding chlamydia diagnoses reported via CTAD) were UK born. The rate of new STIs among people who lived in the most deprived areas (646 per 100,000) was 2.7 times higher than the rate for people who live in the least deprived areas (243 per 100,000).
Key findings
In 2025, the overall rate of new STI diagnoses in the West Midlands remained below the England average, although substantial inequalities persisted across the region.
Diagnosis rates were highest among young adults, people living in the most deprived communities, Black Caribbean and Black African populations, and residents of urban areas within the West Midlands conurbation, including Birmingham, Wolverhampton and Sandwell.
Trends varied by infection. While diagnoses of some STIs declined compared with previous years, syphilis diagnoses remained substantially higher than before the COVID-19 pandemic. Chlamydia continued to be the most commonly diagnosed STI, although diagnosis rates among young women remained well below the recommended detection threshold. While overall syphilis diagnoses have declined in 2025 compared to 2024, diagnoses among heterosexual men and women continue to increase, highlighting the need for continued prevention, testing and targeted intervention. The introduction of doxyPEP may contribute to further reductions in syphilis diagnoses among eligible populations, including GBMSM; however, continued action is needed to address the differing trends observed across population groups.
Sexual health service delivery continues to evolve, with online consultations accounting for a much greater proportion of activity than before 2020.
The findings highlight the importance of using local intelligence to target prevention activities towards populations and communities experiencing the greatest inequalities and harms associated with STIs along with the highest rates of infection. The observed inequalities by age, ethnicity, deprivation and geography support the use of risk-based approaches described within the STI Prioritisation Framework, ensuring that prevention, testing and treatment efforts are focused where they are most likely to reduce STI-related harms and improve sexual health outcomes.
Continued surveillance, targeted health promotion, equitable access to testing, vaccination, treatment and partner notification remain essential to reducing transmission and addressing sexual health inequalities across the West Midlands.
Prevention messages
Prevention messages include:
Sexual health clinics are free, confidential and available to everyone. They provide testing, post-exposure prophylaxis and treatment for STIs and HIV, as well as vaccination and contraception.
Using condoms consistently and correctly with new or casual partners protects against HIV and other STIs.
Testing is recommended if you have had sex without a condom with a new or casual partner in the last 3 months, or if a partner has tested positive for an STI. In addition:
- women and other people with a womb aged under 25 who are sexually active should have a chlamydia test after sex with a new partner or annually
- gay and bisexual men (GBMSM) with new or casual partners should test for HIV and STIs annually or every 3 months if having sex without condoms with new or casual partners
Prevention medications (known as pre- and post-exposure prophylaxis) can prevent HIV and some STIs:
- doxycycline post-exposure prophylaxis (doxyPEP) is recommended to people at risk of syphilis to reduce their chance of infection – doxyPEP is available at specialist sexual health clinics
- HIV pre-exposure prophylaxis (PrEP) reduces an individual’s risk of getting HIV – PrEP is available from specialist sexual health clinics
- HIV post-exposure prophylaxis (PEP) can be taken after sex to reduce the risk of getting HIV – PEP is available for free from most sexual health clinics and most emergency departments
Vaccination can prevent some STIs and blood-borne viruses:
- GBMSM can get the hepatitis A and hepatitis B vaccines from specialist sexual health clinics – these vaccines are also available for other people with a higher risk of exposure to these viruses
- GBMSM aged 45 years and younger can get the human papillomavirus (HPV) vaccine from specialist sexual health clinics – this protects against genital warts and some forms of cancer
- GBMSM who have recently had multiple sexual partners or an STI, and other people at higher risk, are eligible for a meningococcal B disease vaccine (4CMenB) which can protect against gonorrhoea
- mpox vaccination is available for people at increased risk, including GBMSM who have recently had multiple sexual partners
- hepatitis B and HPV vaccines are also part of the routine childhood vaccination program – catch-up vaccines are available for people who missed them at school
STIs in the West Midlands
Overview
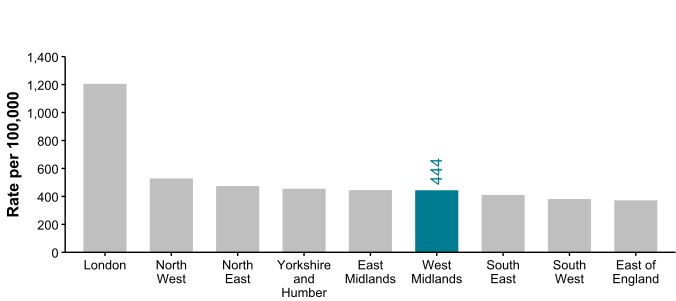
Figure 1. New STI diagnosis rates by UKHSA region of residence, England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
The West Midlands had a new STI diagnosis rate of 444 per 100,000 population in 2025, placing it in the middle of the English regions. The regional rate was substantially lower than that observed in London, which had the highest rate nationally, but higher than the rates recorded in the East Midlands, East of England and South East and South West. Compared with other English regions, the West Midlands had lower diagnosis rates than the North West, North East, Yorkshire and Humber, and East Midlands. Overall, the distribution of new STI diagnosis rates continued to show marked regional variation across England in 2025, with London remaining a clear outlier.
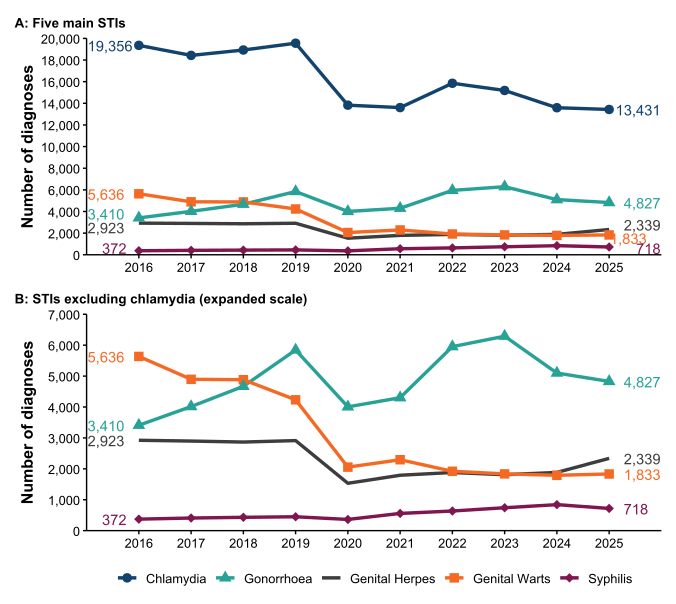
Figure 2. Number of diagnoses of the 5 main STIs (West Midlands, 2016 to 2025): A) all 5 STIs; B) excluding chlamydia (expanded scale)
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
Figure 2 presents trends in diagnoses of the 5 main STIs in the West Midlands between 2016 and 2025. Chlamydia remained the most commonly diagnosed STI throughout the period, although diagnoses declined substantially from 19,356 in 2016 to 13,431 in 2025. Genital warts diagnoses also decreased markedly, while gonorrhoea and syphilis diagnoses increased overall. Genital herpes diagnoses remained below pre-2020 levels despite increasing in 2025.
All 5 STIs showed a decline in diagnoses in 2020, followed by differing post-pandemic trends. Gonorrhoea diagnoses increased to a peak in 2023 before declining in 2024 and 2025, while syphilis diagnoses remained substantially higher than in 2016. In contrast, genital warts experienced a sustained long-term decline and genital herpes diagnoses recovered only partially.
Figure 2B excludes chlamydia and uses an expanded scale, highlighting the contrasting trends more clearly. By 2025, gonorrhoea had become the most commonly diagnosed STI excluding chlamydia, while syphilis diagnoses also increased from 2016 to 2025.
Changes in chlamydia diagnoses should be interpreted alongside changes in testing activity and service delivery. As chlamydia is often asymptomatic and current control activity prioritises detection among young women, diagnosis numbers may reflect changes in testing patterns as well as changes in infection burden.
Table 1. Percentage change in new STI diagnoses, West Midlands
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 19,555 | 13,592 | 13,431 | -31% | -1% |
| Genital herpes | 2,913 | 1,884 | 2,339 | -20% | 24% |
| Genital warts | 4,232 | 1,790 | 1,833 | -57% | 2% |
| Gonorrhoea | 5,844 | 5,098 | 4,827 | -17% | -5% |
| Syphilis | 449 | 841 | 718 | 60% | -15% |
| Other | 5,860 | 4,170 | 4,312 | -26% | 3% |
| All new STIs | 38,853 | 27,375 | 27,460 | -29% | Less than 0.5% change |
Data sources: GUMCAD, CTAD.
See notes for Figure 2. See the New STIs section for a list of diagnoses that are included in the other STIs.
Between 2019 and 2025, the number of new STI diagnoses in the West Midlands decreased overall, although little change was observed between 2024 and 2025. Trends varied considerably by infection.
The overall decline was driven largely by reductions in chlamydia and genital warts diagnoses. In contrast, syphilis was the only STI to increase over the longer term, despite a decline in the most recent year. Genital herpes increased between 2024 and 2025, while gonorrhoea diagnoses declined.
Overall, reductions in chlamydia and genital warts diagnoses were the principal drivers of the long-term decline in STI diagnoses in the West Midlands.
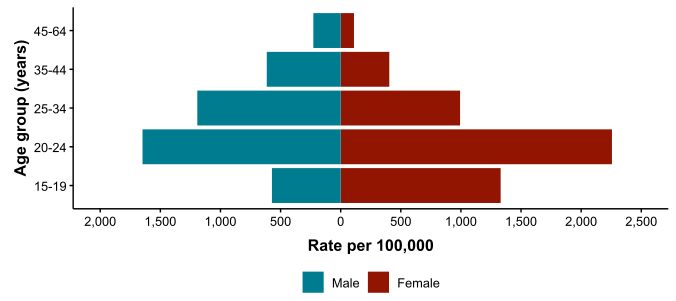
Figure 3. Rates of new STIs per 100,000 by age group (for those aged 15 to 64 years only) and gender, West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Rates of new STIs in the West Midlands in 2025 varied slightly between men and women. In 2025, rates of new STI diagnoses in the West Midlands were highest among people aged 20 to 24 years for both males and females. Females aged 20 to 24 years had the highest diagnosis rate overall, while males in the same age group had the second-highest rate. For both males and females, diagnosis rates declined with age for those aged 25 and over.
The largest difference between the sexes was observed among those aged 25 to 34 years, with males in this age group recording higher rates of new STI diagnoses than females.
Overall, new STI diagnoses were concentrated among younger adults, particularly those aged 20 to 24 years. People aged 15 to 24 years accounted for 41% of all new STI diagnoses in the West Midlands in 2025, highlighting the disproportionate burden of STIs among young people.
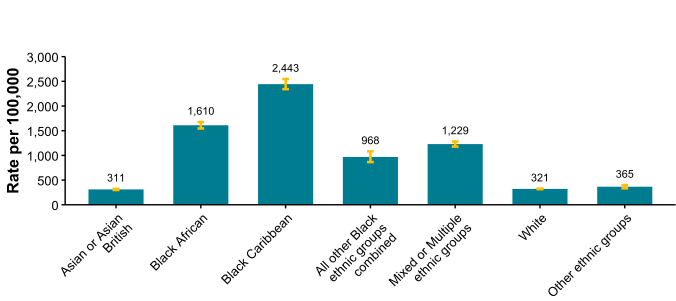
Figure 4. Rates of new STIs per 100,000 by ethnic group, West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021.
Substantial inequalities in rates of new STI diagnoses were observed between ethnic groups in the West Midlands in 2025. People of Black Caribbean ethnicity had the highest diagnosis rate (2,443 per 100,000 population), which is 7.6 times the rate observed among people of White ethnicity (321 per 100,000 population). People of Black African ethnicity (1,610 per 100,000 population) and those of Mixed or Multiple ethnicities (1,229 per 100,000 population) also experienced comparatively high diagnosis rates.
In contrast, the lowest diagnosis rates were observed among people of White ethnicity (321 per 100,000 population) and Asian or Asian British ethnicity (311 per 100,000 population). Rates among all other Black ethnic groups combined (968 per 100,000 population) and people from other ethnic groups (365 per 100,000 population) lay between these extremes.
These findings indicate marked variation in STI diagnosis rates by ethnicity across the West Midlands.
Table 2. Percentage of new STI diagnoses by ethnic group, West Midlands, 2025
| Ethnic group | Number | Percentage (excluding unknown) |
|---|---|---|
| Asian or Asian British | 2,470 | 10% |
| Black African | 2,352 | 10% |
| Black Caribbean | 2,203 | 9% |
| All other Black ethnic groups combined | 317 | 1% |
| Mixed or Multiple ethnic groups | 2,190 | 9% |
| White | 14,736 | 60% |
| Other ethnic groups | 454 | 2% |
| Unknown | 2,738 |
Data sources: GUMCAD, CTAD and ONS Census 2021.
While people of White ethnicity accounted for the greatest number of new STI diagnoses in the West Midlands in 2025 (14,736), important differences were observed between the number of diagnoses and diagnosis rates across ethnic groups.
Excluding diagnoses with unknown ethnicity, over half of all new STI diagnoses occurred among people of White ethnicity. However, as shown in Figure 4, diagnosis rates were substantially higher among Black Caribbean and Black African populations.
These findings indicate a disproportionate burden of STIs among some ethnic minority groups relative to their population size. Although people of White ethnicity accounted for the greatest number of diagnoses, people of Black Caribbean ethnicity experienced the highest diagnosis rate, more than 7 times that observed among people of White ethnicity, highlighting persistent ethnic inequalities in STI burden across the region.
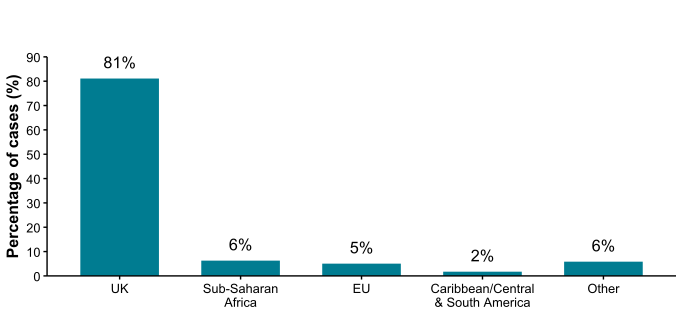
Figure 5. Percentage of new STI diagnoses by world region of birth [note 1], West Midlands, 2025
Data source: GUMCAD data only.
Note 1: data on country of birth is not collected by CTAD. All information about world region of birth is based on diagnoses made in specialist and non-specialist services which report to GUMCAD.
In 2025, most individuals diagnosed with a new STI in the West Midlands were born in the UK, accounting for 81% of diagnoses reported through GUMCAD services.
One in 5 new STI diagnoses occurred among people born outside the UK, although the proportion varied considerably between world regions of birth. Six percent of diagnoses occurred among people born in sub-Saharan Africa, 5% among those born in the European Union, 2% in the Caribbean, Central and South America, and 6% among those born in other world regions.
These findings should be interpreted with caution, as information on country of birth is not collected through CTAD. Estimates by world region of birth are therefore based solely on diagnoses made in specialist and non-specialist sexual health services reporting to GUMCAD.
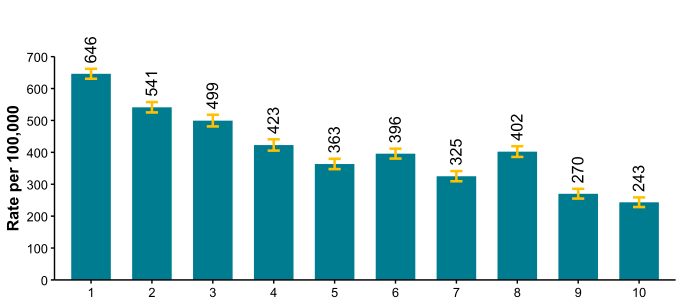
Figure 6. Rates of new STIs per 100,000 by decile of deprivation [note 2], West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Index of Multiple Deprivation and Census 2021 mid-year estimates.
Note 2: deciles run from 1 to 10 in order of decreasing deprivation, with 1 being the decile for the most deprived area. Deprivation is based on 2021 LSOAs – which is available for 96% of GUMCAD data reported in 2025.
A clear deprivation gradient was observed in the West Midlands in 2025, with rates of new STI diagnoses generally decreasing as levels of deprivation decreased. Individuals living in the most deprived areas (decile 1) experienced the highest rate of new STI diagnoses, while those living in the least deprived areas (decile 10) experienced the lowest.
Overall, people living in the most deprived areas experienced nearly 3 times the rate of new STI diagnoses compared with those living in the least deprived areas. Although some variation was observed between adjacent deprivation deciles, these findings demonstrate a strong association between socioeconomic deprivation and STI burden in the West Midlands.
These findings should be interpreted with some caution, as deprivation estimates were available for 95% of GUMCAD records reported in 2025 and are based on 2021 lower layer super output areas (LSOAs).
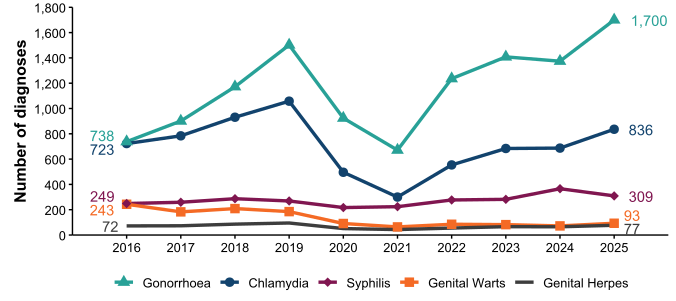
Figure 7. Diagnoses of the 5 main STIs among GBMSM [note 3], West Midlands, 2016 to 2025
Data source: GUMCAD data only.
Note 3: data on sexual orientation is not collected by CTAD. All information about GBMSM is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services.
Where gender and sexual orientation are known, gay, bisexual and other men who have sex with men (GBMSM) accounted for 15% of people diagnosed with a new STI in the West Midlands in 2025 (excluding chlamydia diagnoses reported through CTAD). However, GBMSM accounted for a disproportionate share of some infections, representing 44% of gonorrhoea diagnoses and 52% of syphilis diagnoses.
Among GBMSM in the West Midlands, gonorrhoea remained the most commonly diagnosed STI between 2016 and 2025. Diagnoses of gonorrhoea increased overall during the period and reached their highest level in 2025. Chlamydia diagnoses also increased compared with 2016 but remained below the peak observed prior to the COVID-19 pandemic.
Syphilis diagnoses increased overall during the study period despite fluctuations between years. In contrast, genital warts diagnoses declined substantially, while genital herpes diagnoses remained relatively stable.
All 5 STIs showed reductions in diagnoses during 2020 and 2021, followed by recovery in subsequent years. The increase was most pronounced for gonorrhoea, while genital warts remained well below levels observed at the start of the study period. Overall, gonorrhoea and chlamydia accounted for the greatest burden of STI diagnoses among GBMSM in the West Midlands. Although GBMSM accounted for less than one-fifth of all STI diagnoses, they represented a disproportionate share of gonorrhoea and syphilis diagnoses, highlighting the continued importance of targeted prevention, testing and treatment interventions for this population.
To note, these findings should be interpreted with caution, as data on sexual orientation are not collected by CTAD and analyses are based on GUMCAD diagnoses only.
Table 3. Percentage change in new STI diagnoses among GBMSM, West Midlands
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 1,058 | 687 | 836 | -21% | 22% |
| Genital herpes | 95 | 65 | 77 | -19% | 18% |
| Genital warts | 185 | 72 | 93 | -50% | 29% |
| Gonorrhoea | 1,502 | 1,374 | 1,700 | 13% | 24% |
| Syphilis | 269 | 366 | 309 | 15% | -16% |
| Other | 424 | 275 | 299 | -29% | 9% |
| All new STIs | 3,533 | 2,839 | 3,314 | -6% | 17% |
See notes for Figure 7. See the New STIs section for a list of diagnoses that are included in the other STIs.
Trends in STI diagnoses among GBMSM differed between the longer-term (2019 to 2025) and most recent (2024 to 2025) periods. While the total number of diagnoses was 6% lower in 2025 than in 2019, overall numbers of diagnoses increased compared with 2024.
Gonorrhoea and syphilis were the only STIs to show long-term increases between 2019 and 2025. In contrast, diagnoses of chlamydia, genital herpes and genital warts in 2025 remained below 2019 levels.
The increase in new STI diagnoses among GBMSM observed between 2024 and 2025 was driven primarily by gonorrhoea and chlamydia diagnoses, while syphilis was the only STI to decrease during the most recent year.
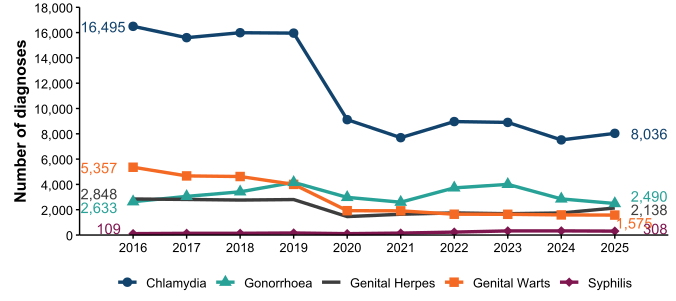
Figure 8. Diagnoses of the 5 main STIs among heterosexual men and all women [note 4], West Midlands, 2016 to 2025
Data source: GUMCAD data only.
Note 4: data on sexual orientation is not collected by CTAD. All information here is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services. Cases are defined here as GUMCAD records where gender is specified as male and sexual orientation is specified as heterosexual, or gender was specified as female, or gender was not specified but orientation was specified as heterosexual. GUMCAD records where sexual orientation was not specified for males or unknown gender individuals are excluded.
Among non-GBMSM in the West Midlands, chlamydia remained the most commonly diagnosed STI throughout 2016 to 2025, despite substantial declines since 2016. Gonorrhoea, genital herpes and genital warts diagnoses were also lower in 2025 than at the start of the study period, with genital warts showing the largest sustained decline. In contrast, syphilis diagnoses increased overall between 2016 and 2025, despite remaining the least commonly diagnosed of the 5 main STIs.
Table 4. Percentage change in new STI diagnoses among heterosexual men and all women, West Midlands
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 15,959 | 7,518 | 8,036 | -50% | 7% |
| Genital herpes | 2,803 | 1,743 | 2,138 | -24% | 23% |
| Genital warts | 4,003 | 1,589 | 1,575 | -61% | -1% |
| Gonorrhoea | 4,160 | 2,855 | 2,490 | -40% | -13% |
| Syphilis | 160 | 327 | 308 | 92% | -6% |
| Other | 5,375 | 3,626 | 3,778 | -30% | 4% |
| All new STIs | 32,460 | 17,658 | 18,325 | -44% | 4% |
Data source: GUMCAD data only.
See notes for Figure 8. See the New STIs section for a list of diagnoses included in the other STIs.
Although the overall number of new STI diagnoses among individuals not identifying as GBMSM remained substantially lower in 2025 than in 2019, diagnoses increased compared with 2024. Trends differed between infections.
Between 2019 and 2025, syphilis was the only STI to show an overall increase, while genital warts experienced the largest decline. Compared with 2024, increases were observed for chlamydia and genital herpes, whereas gonorrhoea, genital warts and syphilis declined.
Overall, the increase in diagnoses between 2024 and 2025 was driven primarily by chlamydia and genital herpes, despite longer-term declines in both infections compared with 2019.
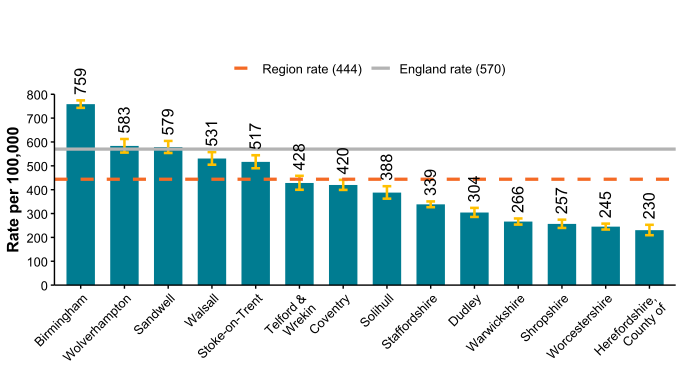
Figure 9. Rate of new STI diagnoses per 100,000 by upper tier local authority, West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
The rate of new STI diagnoses varied considerably across upper tier local authorities in the West Midlands in 2025, ranging from 230 diagnoses per 100,000 population in Herefordshire to 759 per 100,000 population in Birmingham. The regional rate was 444 diagnoses per 100,000 population.
Birmingham reported the highest rate in the region, at 759 diagnoses per 100,000 population, and was the only local authority with a rate substantially above both the regional and national averages. Wolverhampton (583 per 100,000), Sandwell (579 per 100,000) and Walsall (531 per 100,000) also recorded high rates of new STI diagnoses, with Wolverhampton and Sandwell exceeding the England average.
Overall, substantial variation was observed across the region, with diagnosis rates in the highest-rate local authority more than 4 times those in the lowest-rate authority. Rates were generally highest in the metropolitan authorities of the West Midlands conurbation and lower in predominantly rural counties such as Herefordshire, Worcestershire and Shropshire.
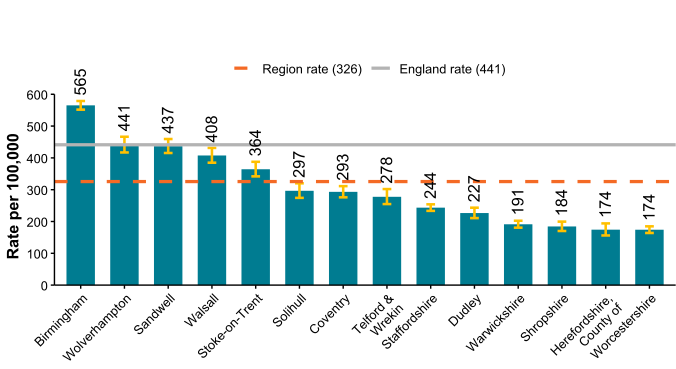
Figure 10. Rate of new STI diagnoses (excluding chlamydia diagnoses among people aged under 25 years [note 5]) per 100,000 by upper tier local authority, West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note 5: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
The rate of new STI diagnoses among people aged under 25 years in the West Midlands varied markedly by upper tier local authority in 2025, ranging from 174 diagnoses per 100,000 population in Worcestershire to 565 per 100,000 population in Birmingham.
Chlamydia diagnoses among those aged 15 to 24 years are excluded from these estimates because variation in local screening practices may influence diagnosis rates. The regional rate was 326 diagnoses per 100,000 population, substantially lower than the England rate of 441 per 100,000 population.
Birmingham reported the highest rate in the region, with 565 diagnoses per 100,000 population, exceeding both the regional and national averages, followed by Wolverhampton (441 per 100,000) and Sandwell (437 per 100,000).
In contrast, Shropshire (184 per 100,000), Herefordshire (174 per 100,000) and Worcestershire (174 per 100,000) recorded some of the lowest diagnosis rates in the region among people under 25.
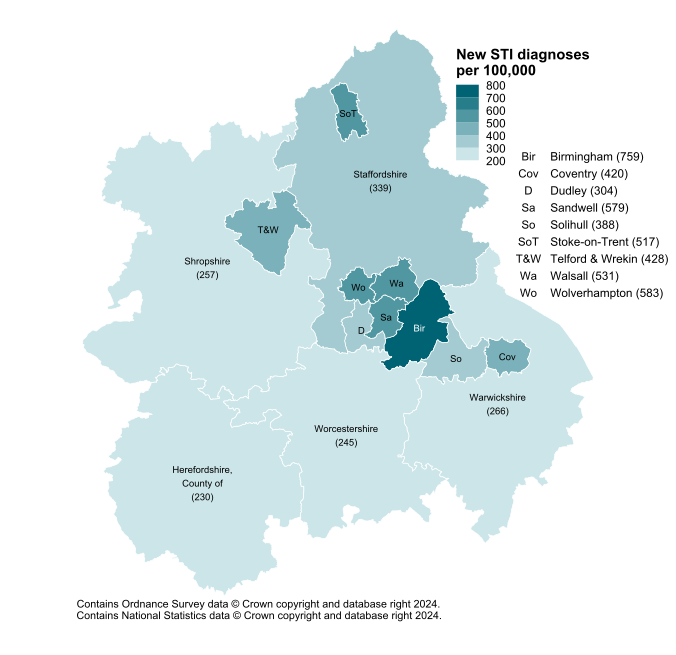
Figure 11. Map of new STI rates per 100,000 by upper tier local authority, West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
The geographical distribution of new STI diagnosis rates across the West Midlands in 2025 shows variation between upper tier local authorities, with higher rates concentrated in the metropolitan areas of the region. Rates were highest in Birmingham (759 per 100,000 population) and neighbouring local authorities within the West Midlands conurbation, forming a distinct cluster of elevated STI burden.
Outside the West Midlands conurbation, diagnosis rates were generally lower, particularly in the predominantly rural counties of Herefordshire, Worcestershire, Shropshire and Warwickshire.
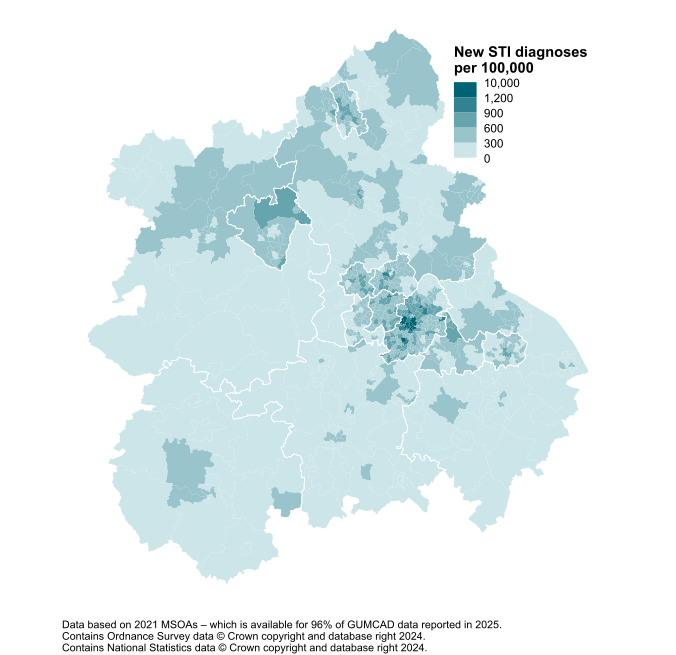
Figure 12. Map of new STI rates per 100,000 by middle super output area (MSOA21), West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Analysis at the MSOA level demonstrates greater geographical variation in new STI diagnosis rates than is apparent from the upper tier local authority summaries shown in Figure 11. Within local authorities, rates varied considerably between neighbourhoods, indicating that STI burden is not distributed evenly across populations.
The highest rates of new STI diagnoses were concentrated within a small number of MSOAs in the metropolitan West Midlands, particularly in parts of Birmingham and neighbouring urban centres. In contrast, most MSOAs across the region, particularly those located in rural and semi-rural areas such as Shropshire, Herefordshire, Worcestershire, Staffordshire and Warwickshire, recorded substantially lower rates.
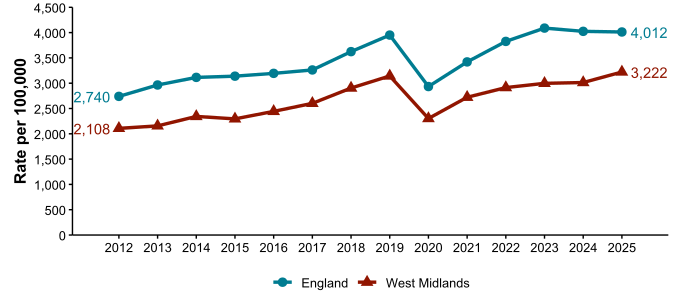
Figure 13. STI testing rate (excluding chlamydia in under-25 year olds [note 6]) per 100,000, West Midlands, 2012 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note 6: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
STI testing rates in the West Midlands increased between 2012 and 2019, before declining sharply in 2020 and subsequently recovering. Following the reduction observed during the COVID-19 pandemic, testing rates increased in each subsequent year, reaching 3,222 tests per 100,000 population in 2025 and exceeding pre-pandemic levels.
Throughout 2016 to 2025, testing rates in the West Midlands remained below those observed nationally. Although both England and the West Midlands experienced similar trends over time, the gap between regional and national testing rates persisted in 2025.
Overall, testing activity has recovered strongly since 2020; however, opportunities remain to increase testing coverage in the West Midlands relative to England.
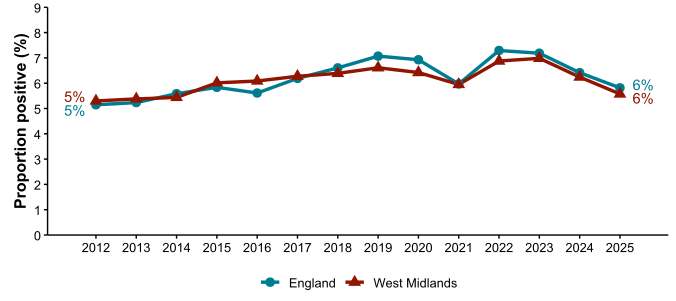
Figure 14. STI testing positivity rate (excluding chlamydia in under 25 year olds [note 7]), West Midlands, 2012 to 2025
Data sources: GUMCAD, CTAD.
Note 7: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
STI testing positivity in the West Midlands remained broadly comparable with England between 2012 and 2025. Positivity increased gradually over the study period, peaked in 2022 and 2023, and subsequently declined to 6% in 2025.
Despite lower testing rates in the West Midlands compared with England (Figure 13), STI positivity remained similar throughout the study period, indicating that the proportion of tests resulting in a diagnosis was comparable in the region and nationally.
Taken together, Figures 13 and 14 suggest that while testing activity in the West Midlands remains below the England average, those who are tested have a similar likelihood of receiving an STI diagnosis.
Table 5. Number of diagnoses of new STIs by UKHSA region of residence, data source and sexual health service type, 2025
| UKHSA region of residence | GUMCAD: specialist SHSs |
GUMCAD: non-specialist SHSs [note 8] |
CTAD | Total |
|---|---|---|---|---|
| East Midlands | 13,724 (61%) |
4,076 (18%) |
4,711 (21%) |
22,511 |
| East of England | 17,420 (68%) |
2,042 (8%) |
6,139 (24%) |
25,601 |
| London | 79,241 (72%) |
10,529 (10%) |
19,826 (18%) |
109,596 |
| North East | 9,111 (70%) |
1,703 (13%) |
2,264 (17%) |
13,078 |
| North West | 31,340 (77%) |
4,738 (12%) |
4,816 (12%) |
40,894 |
| South East | 28,757 (75%) |
1,649 (4%) |
7,914 (21%) |
38,320 |
| South West | 14,333 (64%) |
3,777 (17%) |
4,360 (19%) |
22,470 |
| West Midlands | 20,450 (74%) |
4,133 (15%) |
2,877 (10%) |
27,460 |
| Yorkshire and Humber | 18,720 (72%) |
1,636 (6%) |
5,467 (21%) |
25,823 |
Data sources: GUMCAD, CTAD.
Note 8: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
In 2025, there were 27,460 new STI diagnoses among West Midlands residents. The majority of diagnoses were made in specialist sexual health services (SHSs), which accounted for 20,450 diagnoses (74%). A further 4,133 diagnoses (15%) were reported through non-specialist SHSs, while 2,877 diagnoses (10%) were identified through CTAD services.
The West Midlands had one of the highest percentages of diagnoses made in specialist sexual health services (74%) across England.
Diagnoses made in non-specialist SHSs represented a smaller proportion of all STI diagnoses in the West Midlands (15%), similar to the national pattern.
The contribution of CTAD to overall diagnoses also varied across regions. In the West Midlands, CTAD accounted for 2,877 diagnoses, representing approximately 10% of all STI diagnoses in the region.
Overall, the delivery of sexual health services in the West Midlands was predominantly centred on specialist sexual health services, which accounted for approximately 3 quarters of all STI diagnoses in 2025. Non-specialist services and CTAD contributed a smaller proportion of diagnoses compared with some other regions of England.
Table 6. Number of diagnoses of the 5 main STIs by STI, data source and Sexual Health Service type, West Midlands, 2025
| Five main STIs | GUMCAD: specialist SHSs | GUMCAD: non-specialist SHSs [note 9] | CTAD | Total |
|---|---|---|---|---|
| Chlamydia | 7,579 (56%) |
2,975 (22%) |
2,877 (21%) |
13,431 |
| Genital herpes | 2,338 (100%) |
1 (<1%) |
- | 2,339 |
| Genital warts | 1,833 (100%) |
0 (0%) |
- | 1,833 |
| Gonorrhoea | 3,856 (80%) |
971 (20%) |
- | 4,827 |
| Syphilis | 717 (100%) |
1 (<1%) |
- | 718 |
Data sources: GUMCAD, CTAD.
Note 9: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
The setting in which diagnoses were made varied by STI. Chlamydia diagnoses were identified through both specialist sexual health services and CTAD, while gonorrhoea diagnoses were made through both specialist and non-specialist services. Diagnoses recorded through non-specialist sexual health services accounted for a small proportion of diagnoses overall. Chlamydia had the highest contribution from non-specialist services, with 2,975 diagnoses (22%), followed by gonorrhoea with 971 diagnoses (20%), compared with one syphilis diagnosis (less than 1%) and one genital herpes diagnosis (less than 1%). In contrast, diagnoses of syphilis, genital herpes and genital warts were made almost exclusively in specialist sexual health services.
These findings demonstrate the differing roles of service types in STI diagnosis. While specialist sexual health services remain central to diagnosing and managing a broad range of STIs, community and non-specialist services contribute importantly to the detection of chlamydia and gonorrhoea.
The continued reliance on specialist services for diagnosing infections such as syphilis highlights the importance of maintaining capacity within these services to support timely diagnosis, treatment and partner notification.
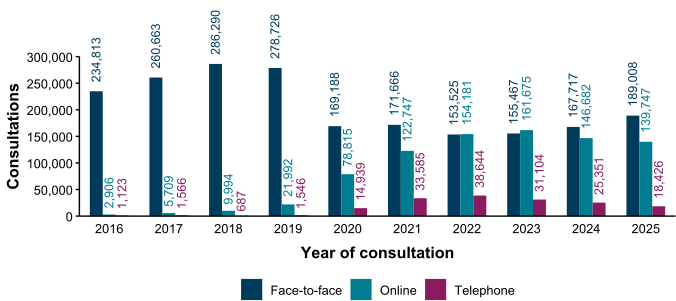
Figure 15. Consultations by service medium, West Midlands, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Patterns of sexual health service use in the West Midlands changed substantially between 2016 and 2025. While face-to-face consultations remained the most common form of contact throughout the study period, online consultations increased markedly following 2020 and accounted for a much larger proportion of activity in 2025 than before the COVID-19 pandemic.
Face-to-face consultations recovered after 2020 but remained below pre-pandemic levels, whereas online consultations remained substantially above those seen prior to 2020. Telephone consultations also increased following the pandemic and continue to represent a greater proportion of activity than before 2020.
Overall, the findings demonstrate a sustained shift towards more diverse models of sexual health service delivery, with online provision now forming an established component of sexual health care alongside traditional face-to-face services.
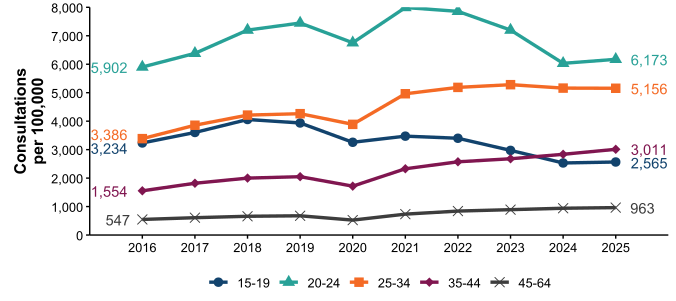
Figure 16. All consultations by age group, West Midlands, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Consultation rates varied by age group between 2016 and 2025, with people aged 20 to 24 years consistently recording the highest rates throughout the study period. Consultation rates declined among those aged 15 to 19 years but increased among adults aged 25 years and over.
By 2025, consultation rates among people aged 25 to 34 years had approached those observed among people aged 20 to 24 years, while rates among adults aged 35 to 44 years and 45 to 64 years had increased substantially compared with 2016.
Overall, although consultation rates remained highest among young adults, the increase in consultation rates among older age groups suggests broader engagement with sexual health services across the population than was observed at the start of the study period.
Implications for prevention and control of sexually transmitted infections in the West Midlands
The findings in this report demonstrate that the burden of STIs in the West Midlands continues to be concentrated within specific populations and communities. Young people, GBMSM, people living in the most deprived communities and some Black ethnic groups experience disproportionately high rates of STI diagnoses. Diagnosis rates among people of Black Caribbean ethnicity were 7.6 times those observed among people of White ethnicity, while people living in the most deprived communities experienced almost 3 times the rate of new STI diagnoses compared with those living in the least deprived communities.
Although overall STI diagnosis rates in the West Midlands remain below the England average, there is variation across the region with diagnoses remaining highest in metropolitan areas and specific neighbourhoods within Birmingham and the Black Country. This variation highlights the need for targeted place-based approaches for those experiencing the highest rates of STIs alongside interventions aimed at populations experiencing the greatest inequalities and harms associated with STIs. Testing activity has recovered following the COVID-19 pandemic and service delivery continues to evolve, with online consultations now accounting for a substantial proportion of sexual health activity. Maintaining equitable access across both digital and face-to-face services will be important to avoid widening existing inequalities.
Reducing inequalities, harms and rates of STIs in the West Midlands will require a combination of behavioural, biomedical and service-based interventions. This includes targeted health promotion, vaccination programmes, partner notification, HIV PrEP, doxyPEP where indicated, and ensuring timely access to testing and treatment. These interventions should be informed by local epidemiology and the STI Prioritisation Framework, with the aim of reducing STI-related harm and narrowing health inequalities across the West Midlands.
The UKHSA STI Prioritisation Framework provides an evidence-based approach to identifying populations experiencing the greatest burden of STI-related harm and directing prevention and control activities accordingly.
The Framework aims to shift the focus of STI control efforts towards reducing adverse health outcomes and addressing inequalities. It provides a clear template for prioritisation, within existing resources and commissioning arrangements. Organisations responsible for planning, commissioning and delivering sexual health services should consider how resources can be targeted to reduce adverse outcomes and address inequalities within existing commissioning arrangements.
For support to use the framework contact your regional Sexual Health Facilitator Danielle.Jayes@ukhsa.gov.uk
Chlamydia
Chlamydia remains the most commonly diagnosed STI in the West Midlands. As infection is frequently asymptomatic, diagnosis trends should be interpreted alongside changes in testing activity and service delivery.
In 2025, the chlamydia detection rate among women aged 15 to 24 years in the West Midlands was 1,232 diagnoses per 100,000 population, substantially below the UKHSA recommended detection rate of at least 3,250 per 100,000 population.
Early diagnosis and treatment remain important in preventing reproductive health complications and reducing onward transmission.
Figure 17. Number of chlamydia diagnoses, West Midlands, 2016 to 2025
Data sources: GUMCAD, CTAD.
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
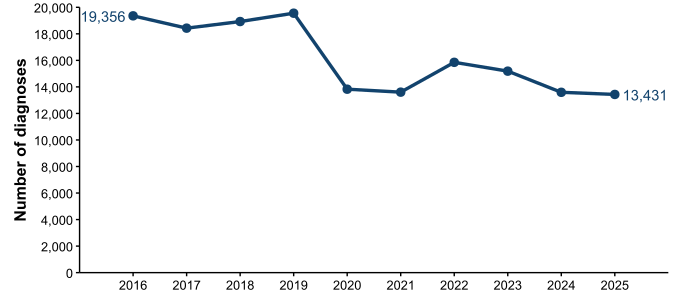
Chlamydia diagnoses in the West Midlands declined substantially between 2016 and 2025. The figure shows that diagnosis numbers remained relatively stable between 2016 and 2019 before declining in 2020. Following this decline, diagnoses increased in 2022 and then fell again in 2024.
The number of diagnoses fell from 19,356 in 2016 to 13,431 in 2025, representing an overall reduction of 30.6% over the study period. Following the marked decline observed in 2020 and 2021, diagnoses increased temporarily in 2022 before declining again in subsequent years.
Between 2023 and 2025, chlamydia diagnoses continued to fall, reaching their lowest level in the time series in 2025. Overall, despite a short-lived increase after the COVID-19 pandemic period, the long-term trend indicates a sustained reduction in chlamydia diagnoses across the West Midlands.
Figure 18. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only), West Midlands, 2016 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimate.
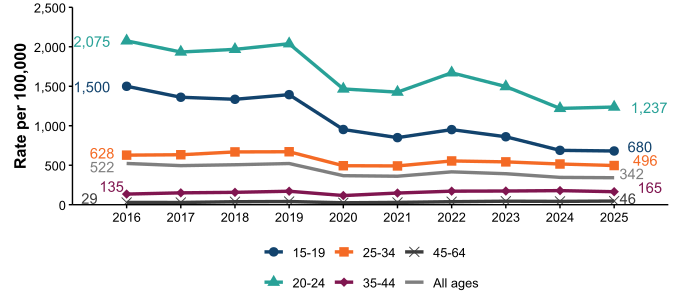
Rates of chlamydia diagnoses in the West Midlands declined across all age groups between 2016 and 2025, although people aged 20 to 24 years consistently recorded the highest rates throughout the study period.
In 2016, the highest rate was observed among people aged 20 to 24 years, at 2,075 diagnoses per 100,000 population. This was followed by those aged 15 to 19 years, at 1,500 per 100,000, people aged 25 to 34 years, at 628 per 100,000, those aged 35 to 44 years, at 135 per 100,000, and people aged 45 to 64 years, at 29 per 100,000.
The figure shows that rates declined across all age groups between 2019 and 2020. Although rates subsequently fluctuated, the ordering of age groups remained broadly unchanged, with higher rates observed among younger age groups throughout the study period.
By 2025, people aged 20 to 24 years continued to have the highest rate of chlamydia diagnoses, at 1,237 diagnoses per 100,000 population. Rates among those aged 15 to 19 years were 680 per 100,000, followed by people aged 25 to 34 years, at 496 per 100,000, those aged 35 to 44 years, at 165 per 100,000, and people aged 45 to 64 years, at 46 per 100,000.
Comparing 2016 and 2025, the largest absolute reduction in the rate of chlamydia diagnoses was observed among people aged 20 to 24 years, whose rate fell from 2,075 to 1,237 diagnoses per 100,000 population. Rates among people aged 15 to 19 years also declined substantially, from 1,500 to 680 per 100,000.
Figure 19. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only) and gender, West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
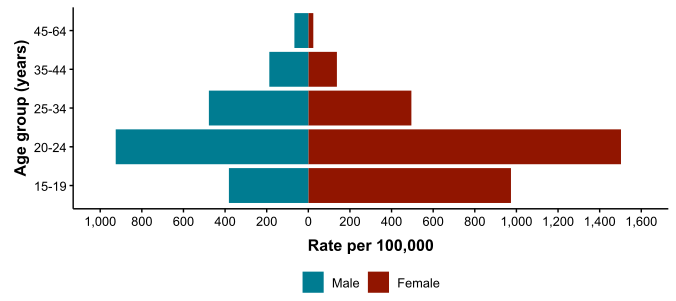
Figure 19 shows that rates of chlamydia diagnoses in the West Midlands in 2025 varied substantially by age group and gender, with the highest rates observed among people aged 20 to 24 years.
Among females, the highest rate was recorded in those aged 20 to 24 years, whose rate exceeded 1,400 diagnoses per 100,000 population. Females aged 15 to 19 years had the second-highest rate. Rates then declined progressively with increasing age, with lower rates observed among women aged 25 to 34, 35 to 44 and 45 to 64 years.
Among males, rates were also highest in the 20 to 24 year age group, exceeding 800 diagnoses per 100,000 population. Males aged 25 to 34 years had the second-highest rate, followed by those aged 15 to 19 years. As with females, rates declined with increasing age.
Females had higher rates than males among those aged 15 to 19 years and 20 to 24 years, with the greatest difference observed in the 20 to 24 year age group. In contrast, among adults aged 25 years and over, rates were generally higher among males than females.
Overall, the burden of chlamydia diagnoses in the West Midlands in 2025 was concentrated among younger age groups, particularly those aged 20 to 24 years. Rates declined substantially with age in both males and females.
Figure 20. Chlamydia detection rate per 100,000, females aged 15 to 24 years by upper tier local authority of residence, West Midlands, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
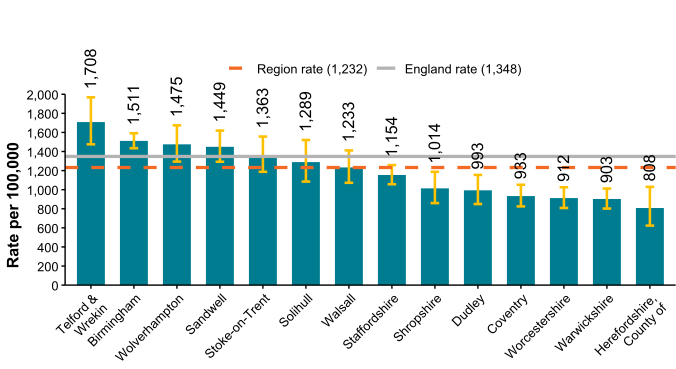
The chlamydia detection rate among females aged 15 to 24 years in the West Midlands varied considerably by upper tier local authority in 2025, ranging from 808 to 1,708 diagnoses per 100,000 population.
The West Midlands regional detection rate was 1,232 diagnoses per 100,000 population, lower than the England rate of 1,348 per 100,000 and below the UKHSA recommended detection rate of at least 3,250 diagnoses per 100,000 population among females aged 15 to 24 years.
Although substantial variation was observed across the region, no upper tier local authority achieved the recommended detection rate. Telford & Wrekin, Birmingham and Wolverhampton reported the highest detection rates, while Herefordshire, Warwickshire and Worcestershire reported the lowest.
Overall, the findings indicate that chlamydia detection among young women remains below recommended levels across all areas of the West Midlands, despite marked geographical variation in detection rates.
Gonorrhoea
Gonorrhoea remains a significant contributor to the burden of STIs in the West Midlands, particularly among younger adults and GBMSM. Ongoing surveillance is important given concerns regarding antimicrobial resistance and continuing transmission.
The introduction of the 4CMenB vaccination programme for people at increased risk of gonorrhoea represents an important addition to the range of interventions available for gonorrhoea prevention.
Figure 21. Number of gonorrhoea diagnoses, West Midlands, 2016 to 2025
Data source: GUMCAD.
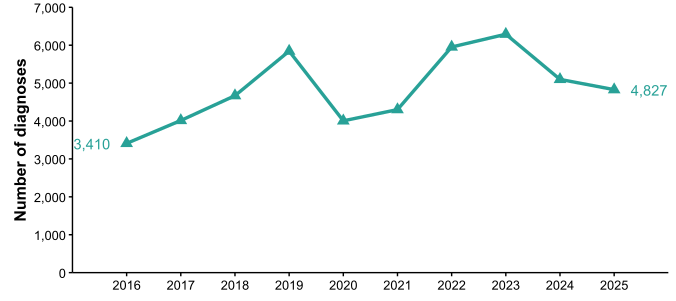
In 2016, there were 3,410 gonorrhoea diagnoses in the West Midlands. The figure shows that diagnoses increased between 2016 and 2019, before declining in 2020. Diagnosis numbers subsequently increased again, reaching their highest level during the study period in 2023, before falling in 2024 and 2025.
By 2025, there were 4,827 gonorrhoea diagnoses in the West Midlands, an increase compared with 2016. The figure indicates that the number of diagnoses recorded in 2025 remained above the level observed at the beginning of the study period.
Overall, gonorrhoea diagnoses in the West Midlands were characterised by an upward trend between 2016 and 2025, despite fluctuations over time.
Figure 22. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only), West Midlands, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
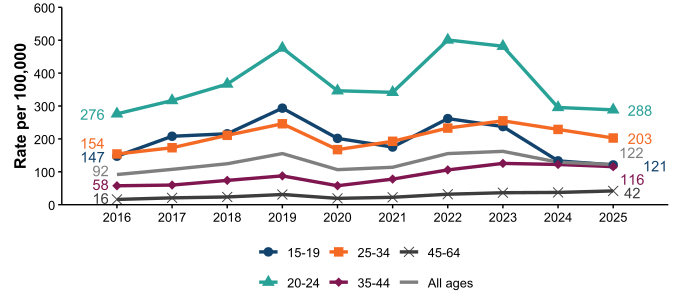
Rates of gonorrhoea varied by age group throughout the study period, with the highest rates consistently observed among people aged 20 to 24 years. The all-ages rate provides an overall measure of gonorrhoea diagnoses across the population aged 15 to 64 years.
In 2016, the rate of gonorrhoea diagnoses was highest among those aged 20 to 24 years, at 276 per 100,000 population, followed by those aged 25 to 34 years (154 per 100,000) and 15 to 19 years (147 per 100,000). Lower rates were recorded among people aged 35 to 44 years (58 per 100,000) and 45 to 64 years (16 per 100,000). The all-ages rate was 92 per 100,000 population.
Rates increased across the younger age groups between 2016 and 2019, before declining in 2020. Rates subsequently increased again, with marked increases among those aged 20 to 24 years and 15 to 19 years between 2021 and 2022. The all-ages rate followed a similar overall pattern, increasing before 2020, declining in 2020 and subsequently rising again.
By 2025, the highest rate remained among people aged 20 to 24 years, at 288 per 100,000 population. Rates were 203 per 100,000 among those aged 25 to 34 years, 122 per 100,000 among those aged 15 to 19 years, 116 per 100,000 among those aged 35 to 44 years, and 42 per 100,000 among those aged 45 to 64 years. The all-ages rate was 121 per 100,000 population.
Overall, gonorrhoea diagnosis rates remained highest among people aged 20 to 24 years throughout 2016 to 2025 and lowest among those aged 45 to 64 years. The all-ages rate increased from 92 per 100,000 in 2016 to 121 per 100,000 in 2025, while the age-specific trends show substantial variation over time, particularly among the younger age groups.
Figure 23. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only) and gender, West Midlands, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
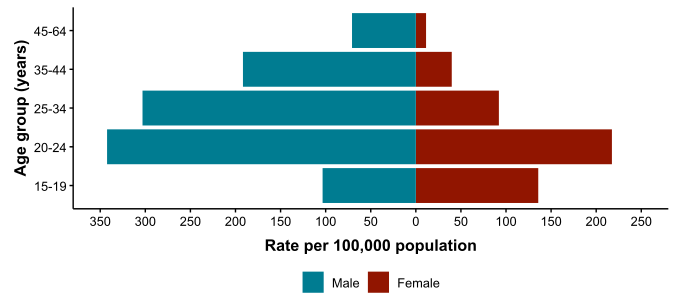
Rates of gonorrhoea diagnoses in 2025 varied by both age group and gender. Among males and females, the highest rates were observed in people aged 20 to 24 years, while the lowest rates were observed among those aged 45 to 64 years.
For males, the rate was highest in the 20 to 24 year age group and declined progressively with increasing age. Rates among males aged 25 to 34 years remained elevated relative to older age groups, while those aged 35 to 44 years and 45 to 64 years experienced substantially lower rates.
A similar age pattern was observed among females, with the highest rate occurring among those aged 20 to 24 years, followed by those aged 15 to 19 years. Rates then decreased across successive age groups.
Comparing genders within age groups, females had higher rates than males among those aged 15 to 19 years and 20 to 24 years. In contrast, males had higher rates than females in the older age groups, with the greatest difference observed among people aged 25 to 34 years.
Overall, gonorrhoea rates in 2025 were concentrated in younger age groups, particularly among people aged 20 to 24 years, with rates declining with increasing age in both males and females.
Figure 24. Rate of gonorrhoea diagnoses per 100,000 by upper tier local authority, West Midlands, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
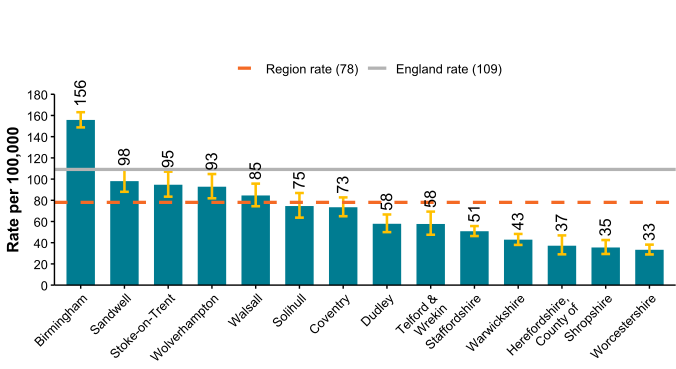
Birmingham had the highest diagnosis rate in the West Midlands, at 156 per 100,000 population, and was the only upper tier local authority with a rate exceeding the England average of 109 per 100,000. Sandwell (98 per 100,000), Stoke-on-Trent (95 per 100,000), Wolverhampton (93 per 100,000) and Walsall (85 per 100,000) also reported rates above the regional average of 78 per 100,000.
Solihull recorded a rate of 75 per 100,000, slightly below the regional average, while Dudley and Telford and Wrekin each had rates of 58 per 100,000. Lower rates were observed in Staffordshire (51 per 100,000), Warwickshire (43 per 100,000), Herefordshire (37 per 100,000), Shropshire (35 per 100,000) and Worcestershire (33 per 100,000).
Overall, rates varied substantially across the West Midlands, with the highest burden concentrated in Birmingham and the Black Country local authorities. Most upper tier local authorities recorded rates below the England average, and approximately half of the authorities had rates below the regional average.
Genital warts
Genital warts diagnoses have declined substantially over the past decade, reflecting the continuing impact of the adolescent HPV vaccination programme. The greatest reductions have occurred among younger age groups, particularly females aged 15 to 19 years, whose diagnosis rate decreased by 98% between 2016 and 2025 in the West Midlands.
These findings demonstrate the population-level benefits of HPV vaccination. Maintaining high vaccination uptake remains important to sustain these public health gains.
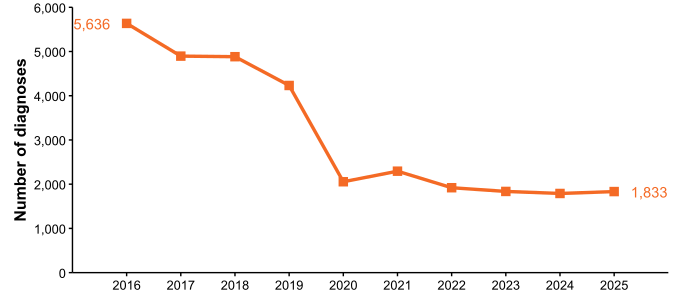
Figure 25. Number of genital warts diagnoses, West Midlands, 2016 to 2025
Data source: GUMCAD.
Diagnoses of genital warts in the West Midlands declined substantially between 2016 and 2025. In 2016, there were 5,636 diagnoses, falling to 4,232 in 2019 before decreasing sharply to 2,055 in 2020.
Following a small increase in 2021 to 2,294 diagnoses, the number of diagnoses remained relatively stable over the subsequent years, with 1,833 diagnoses reported in 2025. This represents a reduction of 67% compared with 2016 and a 57% decrease compared with 2019.
Although diagnoses have stabilised since 2022, levels remain considerably lower than those observed before 2020, indicating a sustained long-term decline in genital wart diagnoses across the West Midlands.
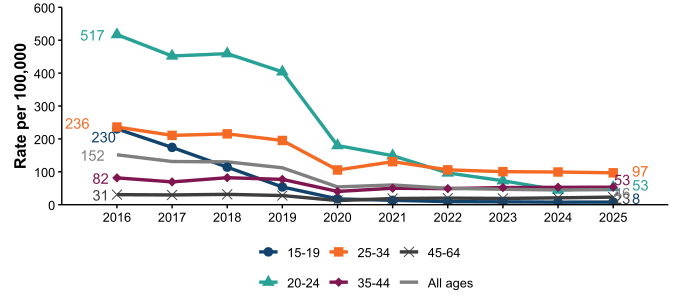
Figure 26. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only), West Midlands, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Rates of genital warts declined across all age groups in the West Midlands between 2016 and 2025, although the magnitude of the decline varied by age. The all-ages rate also declined over the period, from 152 per 100,000 population in 2016 to 46 per 100,000 in 2025.
Throughout most of the period, people aged 20 to 24 years had the highest diagnosis rates. In 2016, the rate in this age group was 517 per 100,000 population. Rates subsequently declined, with a particularly marked reduction between 2019 and 2020, and reached 53 per 100,000 in 2025.
Among people aged 15 to 19 years, the rate decreased from 230 per 100,000 in 2016 to 8 per 100,000 in 2025, with a particularly marked decline between 2018 and 2020, after which rates remained low.
Among residents aged 25 to 34 years, the rate decreased from 236 per 100,000 in 2016 to 97 per 100,000 in 2025. Although rates declined substantially over the period, this age group had the highest genital warts diagnosis rate in 2025.
Rates were lower among the older age groups. Among people aged 35 to 44 years, the rate decreased from 82 per 100,000 in 2016 to 55 per 100,000 in 2025, while among those aged 45 to 64 years, the rate decreased from 31 to 23 per 100,000 over the same period.
Overall, genital warts diagnosis rates declined substantially between 2016 and 2025, with the greatest reductions evident among younger age groups. The all-ages rate fell from 152 to 34 per 100,000 population. By 2025, the age distribution had shifted, with the highest rate recorded among people aged 25 to 34 years (97 per 100,000), followed by those aged 35 to 44 years (55 per 100,000) and 20 to 24 years (53 per 100,000).
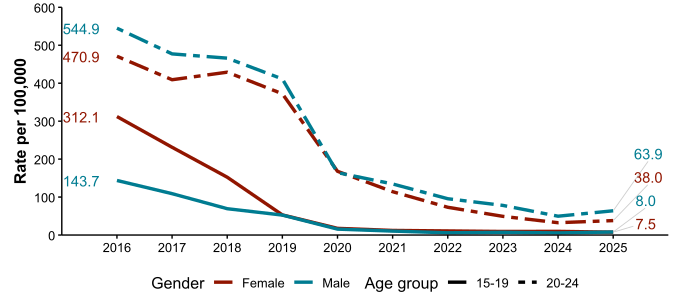
Figure 27. Rates of genital warts per 100,000 aged 15 to 19 and 20 to 24 years by gender, West Midlands, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Among both age groups, rates of genital warts declined substantially between 2016 and 2025, with the largest reductions observed among those aged 15 to 19 years. Throughout the period, rates remained consistently higher among people aged 20 to 24 years than among those aged 15 to 19 years, regardless of gender.
Among individuals aged 20 to 24 years, males had the highest diagnosis rates throughout the study period, decreasing from 544.9 per 100,000 in 2016 to 63.9 per 100,000 in 2025. Rates among females aged 20 to 24 years also fell markedly, from 470.9 to 38.0 per 100,000 over the same period. Both groups experienced a particularly sharp decline between 2019 and 2020, followed by a continued downward trend.
For those aged 15 to 19 years, diagnosis rates were substantially lower and declined to very low levels by 2025. Rates among females fell from 312.1 per 100,000 in 2016 to 7.5 per 100,000 in 2025, while rates among males decreased from 143.7 to 8.0 per 100,000. By 2020, rates in both sexes had fallen to fewer than 20 diagnoses per 100,000 and remained low thereafter.
Overall, genital wart diagnoses decreased markedly across all groups between 2016 and 2025. The greatest reductions occurred among adolescents aged 15 to 19 years, particularly females, among whom diagnosis rates decreased by 97.6% between 2016 and 2025. This substantial decline is consistent with the impact of the HPV vaccination programme introduced for girls in 2008, which provides protection against the HPV types responsible for most genital warts.
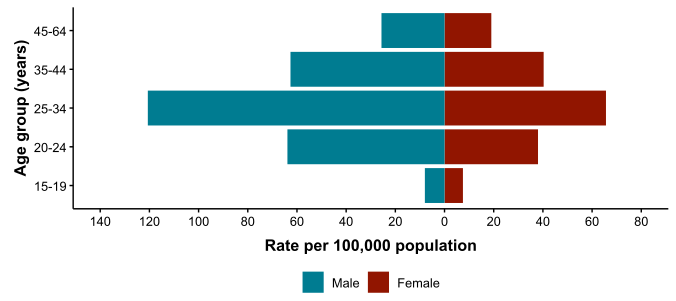
Figure 28. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only) and gender, West Midlands, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Rates of genital warts diagnoses in 2025 varied by both age group and gender. Among males, the highest rate was observed in those aged 25 to 34 years, followed by people aged 20 to 24 years. Rates then declined with increasing age, with the lowest rates recorded among those aged 15 to 19 years and 45 to 64 years.
Among females, the highest rate was also observed in the 25 to 34 year age group. Rates were lower among females aged 20 to 24 years and 35 to 44 years, and lowest among those aged 15 to 19 years and 45 to 64 years.
Comparisons by gender show that males had higher rates than females in every age group. The largest difference between males and females was seen among those aged 25 to 34 years, where the male rate was substantially higher. Smaller differences were observed among people aged 15 to 19 years and 45 to 64 years.
Overall, genital wart diagnosis rates in 2025 were concentrated in adults aged 20 to 34 years, particularly among males aged 25 to 34 years, while rates were comparatively low in the youngest and oldest age groups.
Syphilis
Although less common than other major STIs described in this report, syphilis remains an important public health concern. While early treatment is effective, untreated syphilis can lead to serious neurological, cardiovascular and congenital complications.
Syphilis diagnoses have increased substantially in the West Midlands over the longer term. The regional diagnostic rate increased from 6.4 per 100,000 population in 2016 to 13.6 per 100,000 in 2024, before declining to 11.6 per 100,000 in 2025. Although the West Midlands rate remained below the England rate of 14.1 per 100,000 in 2025, the relative increase since 2016 has been considerably greater in the West Midlands than nationally. This indicates a sustained increase in the regional burden of syphilis despite the reduction observed in the most recent year.
The epidemiology also differs by population group. Among GBMSM, syphilis diagnoses increased from 269 in 2019 to 309 in 2025, a 15% increase, although diagnoses decreased by 16% between 2024 and 2025. Among heterosexual men and all women, diagnoses increased from 160 in 2019 to 308 in 2025, representing a 92% increase, despite a 6% reduction between 2024 and 2025. These findings indicate that, while GBMSM continue to account for a substantial proportion of syphilis diagnoses, the longer-term increase has been particularly pronounced among heterosexual men and women.
Prompt diagnosis, treatment and partner notification therefore remain important components of syphilis control, alongside emerging prevention approaches such as doxycycline post-exposure prophylaxis (doxyPEP) for people at increased risk of infection.
In the West Midlands, enhanced syphilis surveillance has been established to collect more detailed epidemiological information and improve understanding of transmission patterns, risk factors and populations disproportionately affected by infection.
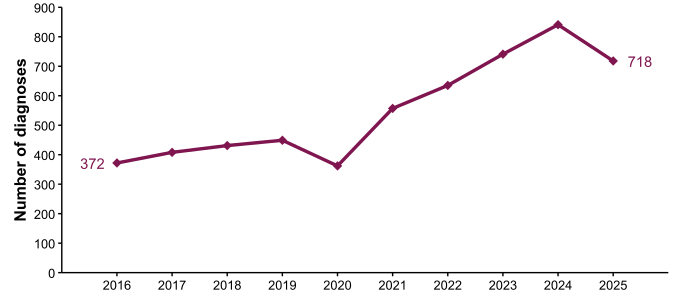
Figure 29. Number of syphilis diagnoses, West Midlands, 2016 to 2025
Data source: GUMCAD.
Syphilis diagnoses in the West Midlands increased overall between 2016 and 2025, despite a temporary decline in 2020.
There were 372 diagnoses in 2016, rising gradually to 449 diagnoses in 2019. Diagnoses then fell to 362 in 2020 before increasing each year between 2021 and 2024, reaching a peak of 841 diagnoses in 2024.
In 2025, the number of syphilis diagnoses declined to 718. Despite this decrease from the previous year, the number of diagnoses remained substantially higher than at the start of the study period.
Overall, the figure shows a long-term upward trend in syphilis diagnoses in the West Midlands between 2016 and 2025, with the largest increases occurring after 2020.
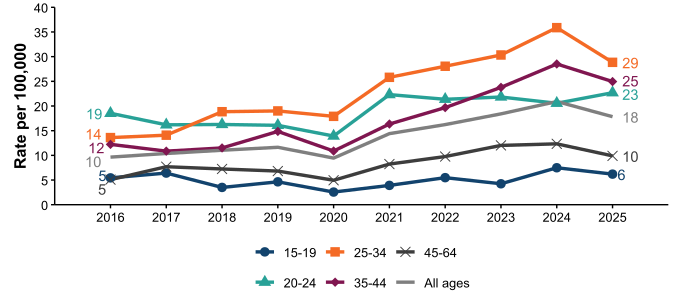
Figure 30. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only), West Midlands, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Rates of syphilis diagnoses increased across all age groups between 2016 and 2025, although the magnitude of increase varied by age.
In 2016, the highest rate was observed among people aged 20 to 24 years, at 19 per 100,000 population. Rates in the remaining age groups were 14 per 100,000 among those aged 25 to 34 years, 12 per 100,000 among those aged 35 to 44 years, and 5 per 100,000 among both the 15 to 19 year and 45 to 64 year age groups.
Following a decline in 2020, rates increased in all age groups between 2021 and 2024. In 2025, the highest rate was observed among people aged 25 to 34 years, at 30 per 100,000 population, followed by those aged 35 to 44 years (26 per 100,000) and those aged 20 to 24 years (23 per 100,000). Lower rates were recorded among people aged 45 to 64 years (10 per 100,000) and those aged 15 to 19 years (6 per 100,000).
The age profile changed over the study period. While the highest rate in 2016 occurred among those aged 20 to 24 years, by 2025 the highest rate was among people aged 25 to 34 years. The largest increases over time were observed in the 25 to 34 year and 35 to 44 year age groups.
Overall, syphilis rates remained lowest among people aged 15 to 19 years throughout the study period, while rates among adults aged 25 to 44 years increased substantially.
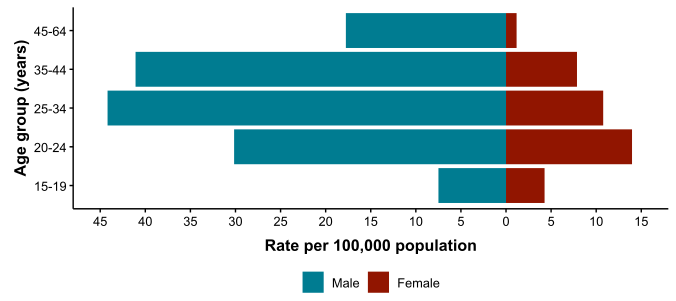
Figure 31. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only) and gender, West Midlands, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Rates of syphilis diagnoses increased overall and across age groups in the West Midlands between 2016 and 2025, although the magnitude and pattern of change varied by age. In 2016, the all-ages rate was 10 per 100,000 population. Among the individual age groups, the highest rate was observed among people aged 20 to 24 years, at 19 per 100,000, followed by those aged 25 to 34 years (14 per 100,000) and 35 to 44 years (12 per 100,000). Rates were lowest among those aged 15 to 19 years and 45 to 64 years, both at 5 per 100,000.
Following a decline in 2020, the all-ages rate increased from 9 per 100,000 in 2020 to 21 per 100,000 in 2024, alongside increases across the individual age groups. In 2025, rates declined from their 2024 levels across all age groups, with the all-ages rate decreasing to 18 per 100,000.
In 2025, the highest age-specific rate was observed among people aged 25 to 34 years, at 29 per 100,000 population, followed by those aged 35 to 44 years (25 per 100,000) and 20 to 24 years (23 per 100,000). Lower rates were recorded among people aged 45 to 64 years (10 per 100,000) and 15 to 19 years (6 per 100,000).
The age profile of syphilis diagnoses changed over the study period. While people aged 20 to 24 years had the highest rate in 2016, by 2025 the highest rate was among those aged 25 to 34 years. The largest sustained increases were observed among adults aged 25 to 44 years.
Overall, despite the decline between 2024 and 2025, the all-ages syphilis diagnosis rate remained substantially higher in 2025 than in 2016 (18 compared with 10 per 100,000). This longer-term increase was particularly evident among adults aged 25 to 44 years, while rates remained lowest among people aged 15 to 19 years throughout the period.
Genital herpes
Genital herpes continues to contribute substantially to sexual health morbidity in the West Midlands.
Effective clinical management, timely diagnosis and access to sexual health services remain important in reducing the impact of infection on affected individuals and limiting onward transmission.
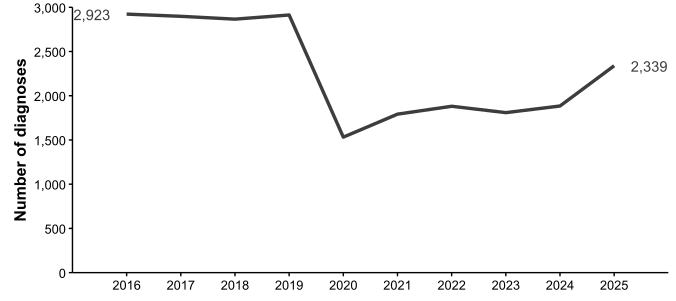
Figure 32. Number of genital herpes diagnoses, West Midlands, 2016 to 2025
Data source: GUMCAD.
Genital herpes diagnoses in the West Midlands declined overall between 2016 and 2025, although diagnoses increased in the years following 2020.
There were 2,923 diagnoses in 2016. Diagnosis numbers remained relatively stable between 2016 and 2019 before falling substantially in 2020. Diagnoses subsequently increased between 2021 and 2025, reaching 2,339 diagnoses in 2025.
Despite the increase observed after 2020, the number of genital herpes diagnoses in 2025 remained lower than at the start of the study period.
Overall, the figure shows a marked reduction in genital herpes diagnoses between 2016 and 2020, followed by a gradual recovery over subsequent years.
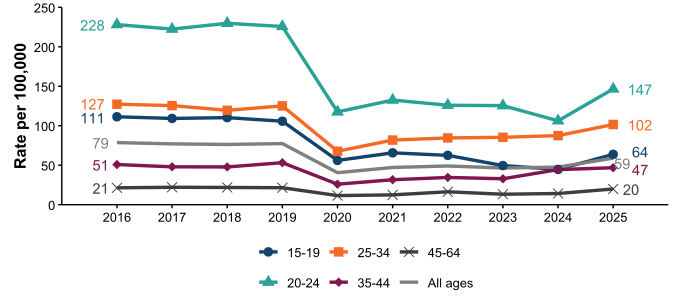
Figure 33. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only), West Midlands, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Rates of genital herpes diagnoses in the West Midlands varied by age group between 2016 and 2025, with the highest rates consistently observed among people aged 20 to 24 years. The all-ages rate declined over the period, although trends differed between age groups.
In 2016, the all-ages genital herpes diagnosis rate was 79 per 100,000 population. The highest age-specific rate was among people aged 20 to 24 years, at 228 per 100,000, followed by those aged 25 to 34 years (127 per 100,000) and 15 to 19 years (111 per 100,000). Lower rates were recorded among those aged 35 to 44 years (51 per 100,000) and 45 to 64 years (21 per 100,000).
Rates remained comparatively stable between 2016 and 2019 before declining markedly in 2020, including a substantial reduction in the all-ages rate. Following 2020, trends diverged by age. Rates among people aged 20 to 24 years and 25 to 34 years generally increased, while rates among those aged 15 to 19 years fluctuated. Rates among people aged 35 to 44 years and 45 to 64 years remained lower than those observed in the younger age groups.
By 2025, the all-ages rate was 59 per 100,000 population. The highest age-specific rate remained among people aged 20 to 24 years, at 147 per 100,000, followed by those aged 25 to 34 years (102 per 100,000), 15 to 19 years (64 per 100,000), 35 to 44 years (47 per 100,000) and 45 to 64 years (20 per 100,000).
Comparing 2016 with 2025, rates were lower across all age groups and overall. The all-ages rate decreased from 79 to 59 per 100,000. The largest absolute reduction among the age groups occurred among people aged 20 to 24 years, decreasing from 228 to 147 per 100,000. Rates also decreased from 127 to 102 per 100,000 among those aged 25 to 34 years and from 111 to 64 per 100,000 among those aged 15 to 19 years. Smaller reductions were observed among those aged 35 to 44 years, from 51 to 47 per 100,000, and those aged 45 to 64 years, from 21 to 20 per 100,000.
Overall, genital herpes diagnosis rates remained concentrated among younger adults, particularly those aged 20 to 24 years. Although the all-ages rate and rates in every age group remained below their 2016 levels in 2025, the increase observed in several younger age groups following the 2020 decline indicates a partial recovery in diagnosis rates in recent years.
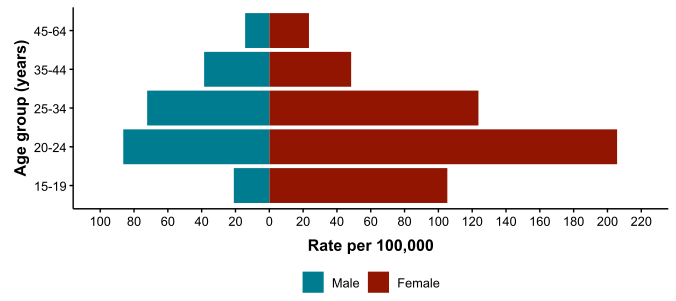
Figure 34. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only) and gender, West Midlands, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
In 2025, genital herpes diagnosis rates varied by both age and gender in the West Midlands. Among females, the highest rate was observed in those aged 20 to 24 years, at just over 200 diagnoses per 100,000 population, followed by those aged 25 to 34 years, over 120 per 100,000.
Among males, the highest diagnosis rate was also recorded in the 20 to 24 year age group, over 80 per 100,000 population. This was followed by males aged 25 to 34 years. Lower rates were observed among older age groups, with males aged 35 to 44 years, while those aged 45 to 64 years had the lowest rate.
Across all age groups, females had higher genital herpes diagnosis rates than males. The largest difference between genders was observed among people aged 20 to 24 years, where the female rate was more than twice that of males. Gender differences were also apparent among those aged 15 to 19 years and 25 to 34 years, whereas rates among males and females aged 35 to 44 years and 45 to 64 years were more similar.
Overall, diagnosis rates were highest among younger adults, particularly females aged 20 to 24 years, while the lowest rates were observed among adults aged 45 to 64 years.
Data sources
Find more information on local sexual health data sources in the UKHSA guide.
The gender and age group chart is restricted to those aged 15 to 64 years as information about STIs in those aged under 15 years is considered highly sensitive. Analyses specific to this group are not provided in routine outputs. Rates for those aged 65 or older are withheld to ensure that no deductive disclosure is possible for the under 15 years age group. The proportion of STIs in those aged under 15 years or older than 64 years is very low.
GUMCAD surveillance system
This disaggregate reporting system collects information about attendances and diagnoses at specialist (Level 3) and non-specialist (Level 2) sexual health services. Information about the patient’s area of residence is collected along with demographic data and other variables. GUMCAD superseded the earlier KC60 system and can provide data from 2009 onwards. GUMCAD is the main source of data for this report.
Due to limits on how much personally identifiable information sexual health clinics are able to share, it is not possible to deduplicate between different clinics. There is a possibility that some patients may be counted more than once if they are diagnosed with the same infection (for infection specific analyses) or a new STI of any type (for new STI analyses) at different clinics during the same calendar year.
CTAD surveillance system
CTAD collects data on all local authority and NHS or NHS-commissioned chlamydia testing carried out in England. CTAD is comprised of all chlamydia (NAATs) tests for all ages (with the exception of conjunctival samples), from all venues and for all reasons. CTAD enables unified, comprehensive reporting of all chlamydia data, to effectively monitor the impact of the NCSP through estimation of the coverage of population screening, proportion of all tests that are positive and detection rates.
For services which report to GUMCAD and for which CTAD does not receive data on the patient’s area of residence (for example, SHSs), information about chlamydia diagnoses is sourced from GUMCAD data.
CTAD does not collect information about sexual orientation or country of birth. Reports from CTAD are excluded from figures in this report which relate to analyses by sexual orientation or world region of birth.
New STIs
New STI diagnoses comprise diagnoses of the following:
- chancroid
- Lymphogranuloma venereum (LGV)
- donovanosis
- chlamydia
- gonorrhoea
- genital herpes (first episode)
- HIV (acute and AIDS defining)
- Molluscum contagiosum
- non-specific genital infection (NSGI)
- non-specific pelvic inflammatory disease (PID) and epididymitis
- chlamydial PID and epididymitis (presented in chlamydia total)
- gonococcal PID and epididymitis (presented in gonorrhoea total)
- scabies
- pediculosis pubis
- syphilis (primary, secondary and early latent)
- trichomoniasis and genital warts (first episode)
- Mycoplasma genitalium
- shigella
Calculations
Confidence intervals were calculated using Byar’s method for numerators >= 10. For small numerators Byar’s method is less accurate and so an exact method based on the Poisson distribution is used.
ONS mid-year population estimates for 2024 were used as a denominator for rates (other than by ethnic group) for 2025. ONS estimates of population by ethnic group for the year 2021 were used as a denominator for rates by ethnic group for 2025. This is the first time that new estimates of population by ethnic group have been available since 2011. This must be considered if comparing rates for 2025 in this report with rates by 2024 in last year’s report, as the rates in the last report used the 2011 estimates.
Interpreting trends
When interpreting trends in the number of STI diagnoses it is important to consider the potential impact of changes to testing, vaccination programmes and the availability of interventions (such as prophylaxis). Specifically, diagnostic testing for gonorrhoea and genital herpes now includes in some areas highly sensitive testing using nucleic acid amplification tests. Additionally, there is some screening of GBMSM at extra-genital sites. Where in place, both will have led to increased case ascertainment of gonorrhoea and genital herpes. Local testing practices for all STIs may vary.
More information
As of 2020, all analyses for this report include data from non-specialist (Level 2) SHSs and enhanced GP services as well as specialist (Level 3) SHSs.
For more information, see the online Sexual and Reproductive Health Profiles.
For more information on HIV data, see the separate HIV Spotlight report.
For more information about local sexual health data sources, see the UKHSA guide.
Local authorities have access to The Summary Profile of Local Authority Sexual Health (SPLASH) Reports (accessible from the Sexual and Reproductive Health Profiles) and the SPLASH supplement reports via the HIV and STI Data exchange.
About the Field Services
The Field Services were established in 2018 as a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Real-time Syndromic Surveillance and Public Health Microbiology to strengthen the surveillance, intelligence and response functions of UKHSA.
You can contact your local FS team at FSMidlands@ukhsa.gov.uk
Acknowledgements
We would like to thank the following:
- local SHSs for supplying the SHS data
- local laboratories for supplying the CTAD data
- UKHSA Blood Safety, Hepatitis, Sexually Transmitted Infections (STI) and HIV Division for collection, analysis and distribution of data