Spotlight on sexually transmitted infections in the South West: 2025 data
Updated 8 October 2026

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/sexually-transmitted-infections-south-west-data/spotlight-on-sexually-transmitted-infections-in-the-south-west-2025-data
Summary
While this report primarily focuses on the trend between 2024 and 2025, some trends relative to 2019 or earlier are included to provide a comparison to sexual health service provision and sexually transmitted infection (STI) diagnoses prior to the 2020-2021 COVID-19 pandemic. Across England, the numbers of consultations, sexual health screens and STI diagnoses in 2020 and 2021 are lower than preceding years and any trends during periods which include those years must be interpreted in that context.
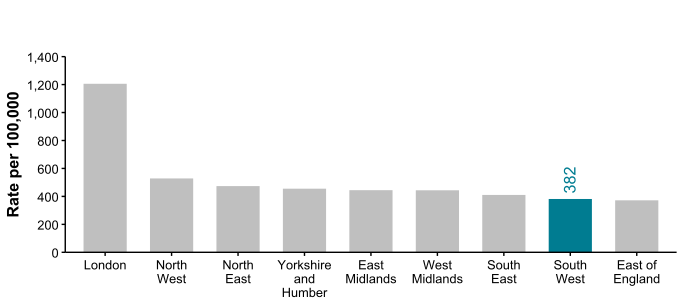
STIs represent an important public health problem in the South West. However, of all UK Health Security Agency (UKHSA) regions in England, the South West has the second lowest rate of new STIs.
A total of 22,470 new STIs were diagnosed among South West residents in 2025, representing an annual rate of 382 diagnoses per 100,000. Rates by upper tier local authority ranged from 281 new STI diagnoses per 100,000 in Somerset to 579 new STI diagnoses per 100,000 in Bournemouth, Christchurch and Poole.
The number of new STIs diagnosed in South West residents decreased by 11% between 2024 and 2025. Changes were seen in the numbers of the 5 main STIs: syphilis increased by 5%, gonorrhoea decreased by 26%, chlamydia decreased by 9%, genital herpes decreased by 3% and genital warts decreased by 6%.
UKHSA recommends that localities should be working towards achieving a chlamydia detection rate no lower than 3,250 per 100,000 among women aged 15 to 24 years and this is an indicator in the Public Health Outcomes Framework. In 2025, the chlamydia detection rate among South West women aged 15 to 24 years was 1,284 per 100,000 compared to 1,410 per 100,000 in 2024 and remaining well below the recommended level.
Rates of new STIs vary slightly between men and women (382 and 351 per 100,000, respectively, where recorded). Excluding chlamydia diagnoses reported via CTAD, and where gender and sexual orientation were known, gay, bisexual and other men who have sex with men (GBMSM) accounted for 17% of the South West population diagnosed with a new STI in 2025, including 66% of those diagnosed with syphilis and 55% of those diagnosed with gonorrhoea.
STIs disproportionately affect young people, and South West residents aged between 15 and 24 years accounted for 44% of all new STI diagnoses in 2025. A steep decline has been seen in genital warts diagnosis rates in females aged 15 to 19 following the introduction in 2008 of vaccination against human papillomavirus (HPV), the virus which causes genital warts, for girls.
The White ethnic group had the highest number of new STI diagnoses in 2025: 17,452 (87% of all diagnoses). Although 1% of new STIs were in the Black Caribbean ethnic group, they had the third highest rate: 1,155 per 100,000, 3.5 times the rate seen in the White ethnic group. Where country of birth was known, 84% of South West residents diagnosed with a new STI in 2025 (excluding chlamydia diagnoses reported via CTAD) were UK-born. The rate of new STIs among people who lived in the most deprived areas (600 per 100,000) was 2.1 times higher than the rate for people who live in the least deprived areas (284 per 100,000).
Chlamydia remained the most commonly diagnosed STI in the South West in 2025. Despite this, there have been substantial declines in chlamydia incidence since 2018, contributing to an overall reduction in STI diagnoses across the South West. In contrast, gonorrhoea and syphilis increased over the longer term, while genital warts showed the largest decline, likely reflecting the impact of HPV vaccination. STI burden remained concentrated among young adults, with gonorrhoea and syphilis disproportionately affecting males and genital herpes more commonly diagnosed among young females.
Among GBMSM, gonorrhoea remained the predominant STI, with diagnoses remaining above pre-pandemic levels despite recent declines. In contrast, STI diagnoses among heterosexual men and all women have fallen substantially since 2019, driven largely by reductions in chlamydia and genital warts, although syphilis continued to increase.
The highest STI diagnosis rates were generally observed in urban local authorities, including Plymouth, Bristol, Torbay and Swindon, while lower rates were seen in more rural areas. Variation was even more pronounced at MSOA level, highlighting localised areas of higher STI burden.
Although STI testing rates increased over time, the South West continued to report lower testing rates and lower positivity than England overall.
Prevention messages
Sexual health clinics are free, confidential and available to everyone. They provide testing, post-exposure prophylaxis and treatment for STIs and HIV, as well as vaccination and contraception.
Using condoms consistently and correctly with new or casual partners protects against HIV and other STIs.
Testing is recommended if you have had sex without a condom with a new or casual partner in the last 3 months or if a partner has tested positive for an STI. In addition:
- women and other people with a womb aged under 25 who are sexually active should have a chlamydia test after sex with a new partner or annually
- gay and bisexual men (GBMSM) with new or casual partners should test for HIV and STIs annually or every 3 months if having sex without condoms with new or casual partners
Prevention medications (known as pre- and post-exposure prophylaxis) can prevent HIV and some STIs:
- doxycycline post-exposure prophylaxis (doxyPEP) is recommended to people at risk of syphilis to reduce their chance of infection – doxyPEP is available at specialist sexual health clinics
- HIV pre-exposure prophylaxis (PrEP) reduces an individual’s risk of getting HIV – PrEP is available from specialist sexual health clinics
- HIV post-exposure prophylaxis (PEP) can be taken after sex to reduce the risk of getting HIV – PEP is available for free from most sexual health clinics and most emergency departments
Vaccination can prevent some STIs and blood-borne viruses:
- GBMSM can get the hepatitis A and hepatitis B vaccines from specialist sexual health clinics – these vaccines are also available for other people with a higher risk of exposure to these viruses
- GBMSM aged 45 years and younger can get the human papillomavirus (HPV) vaccine from specialist sexual health clinics – this protects against genital warts and some forms of cancer
- GBMSM who have recently had multiple sexual partners or an STI and other people at higher risk are eligible for a meningococcal B disease vaccine (4CMenB) which can protect against gonorrhoea
- mpox vaccination is available for people at increased risk, including GBMSM who have recently had multiple sexual partners
- hepatitis B and HPV vaccines are also part of the routine childhood vaccination programme – catch-up vaccines are available for people who missed them at school
STIs in the South West
Overview
Figure 1. New STI diagnosis rates by UKHSA region of residence, England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 1 is a column chart comparing new STI diagnosis rates across UKHSA regions of residence in England in 2025. The South West had the second lowest rate of new STI diagnoses (382 per 100,000 residents), while London had the highest (1,206 per 100,000). Rates in all other regions were broadly comparable. Overall, the rate in London was more than 3 times higher than that in the South West, highlighting substantial regional variation in STI burden across England.
Outside of London, new diagnosis rates were highest among regions in the North of England. STIs in the South West and across England are highly concentrated in urban areas (Figure 9) and among younger age groups (Figure 3); the South West has the lowest population density and the highest median age of all English regions.
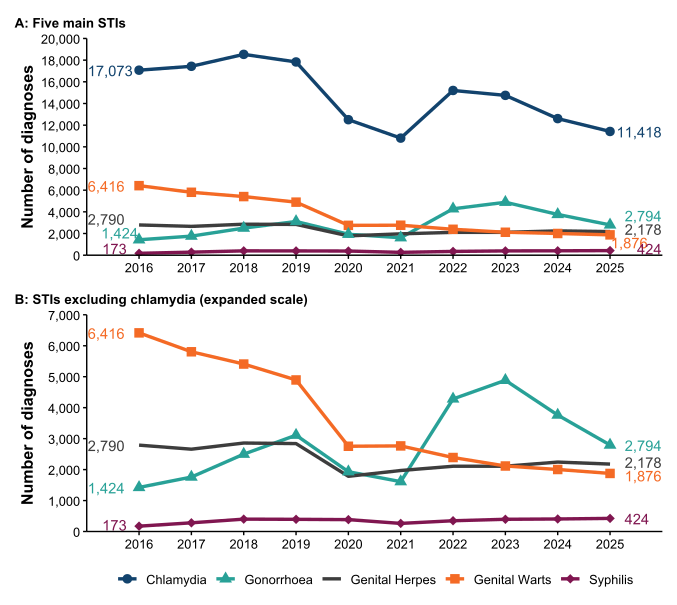
Figure 2. Number of diagnoses of the 5 main STIs (South West, 2016 to 2025): A) all 5 STIs; B) excluding chlamydia (expanded scale)
Data sources: GUMCAD, CTAD.
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
Figure 2 is a line chart showing trends in diagnoses of the 5 main STIs among South West residents between 2016 and 2025. Chlamydia remained the most commonly diagnosed STI throughout the period, despite a substantial decline since 2019. Gonorrhoea diagnoses increased overall, while genital warts and genital herpes declined. Syphilis remained the least commonly diagnosed STI but has increased gradually over time. Most STIs showed a marked decline during the COVID-19 pandemic, followed by varying degrees of recovery.
Chlamydia remained the most frequently diagnosed STI in the South West in 2025, despite decreasing incidence since its peak in 2018. Diagnoses fell sharply between 2019 and 2021, partially recovered in 2022 and 2023, and then declined again in 2025. Between 2024 and 2025, diagnoses decreased by 9%, from 12,604 to 11,418 (Table 1).
Gonorrhoea diagnoses increased between 2016 and 2019 and declined during the COVID-19 pandemic in 2020 and 2021 before a notable increase in 2022. Gonorrhoea declined by 26% between 2024 and 2025, from 3,761 to 2,794, although case counts remain higher than pre-pandemic levels.
Genital herpes diagnoses declined overall, falling by 23% between 2019 and 2025.
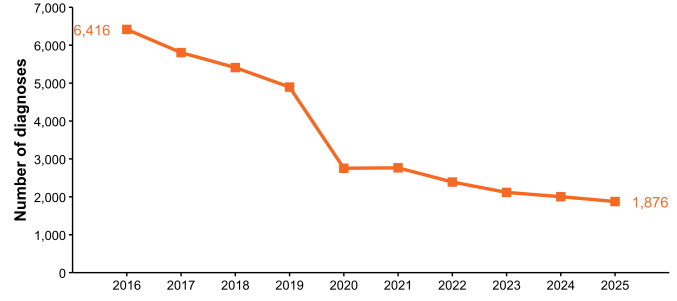
Genital warts diagnoses continued to decline throughout the period, falling by 62% between 2019 and 2025, from 4,895 to 1,876.
Syphilis remained the least commonly diagnosed STI in the South West, although diagnoses have increased by 8% between 2019 and 2025.
Table 1. Percentage change in new STI diagnoses, South West
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 17,831 | 12,604 | 11,418 | −36% | −9% |
| Genital Herpes | 2,840 | 2,243 | 2,178 | −23% | −3% |
| Genital Warts | 4,895 | 2,003 | 1,876 | −62% | −6% |
| Gonorrhoea | 3,111 | 3,761 | 2,794 | −10% | −26% |
| Syphilis | 394 | 405 | 424 | 8% | 5% |
| Other | 6,146 | 4,129 | 3,780 | −38% | −8% |
| All new STIs | 35,217 | 25,145 | 22,470 | −36% | −11% |
Data sources: GUMCAD, CTAD.
Note: see notes for Figure 2. See the New STIs section for a list of diagnoses that are included in the other STIs.
Table 1 summarises changes in new STI diagnoses in the South West between 2019 and 2025 and between 2024 and 2025. Overall, new STI diagnoses decreased by 36% between 2019 and 2025 and by 11% between 2024 and 2025. The largest long-term declines were observed for genital warts (−62%) and other STIs (−38%), while syphilis was the only STI to increase over the period (+8%). Between 2024 and 2025, the overall decrease was driven primarily by reductions in gonorrhoea (−26%) and chlamydia (−9%) diagnoses.
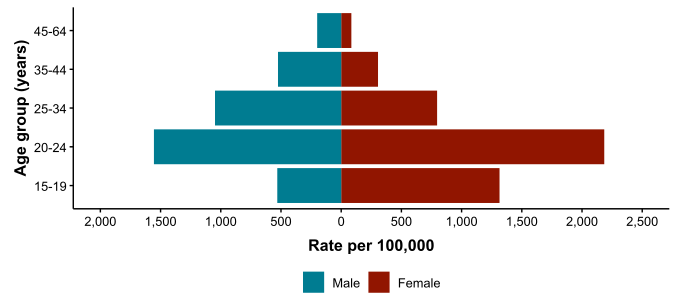
Figure 3. Rates of new STIs per 100,000 by age group (for those aged 15 to 64 years only) and gender, South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 3 is an age-sex pyramid showing the rates of new STIs per 100,000 population in the South West in 2025, by age group and gender, for people aged 15 to 64 years only. Those aged under 15 years and above 64 years have been excluded due to the sensitivity of the data and/or the need to prevent disclosure of small numbers.
Rates of new STI diagnoses in 2025 were highest among young adults, particularly those aged 20 to 24 years. Females had higher diagnosis rates than males in most age groups under 35 years, with the highest rate observed among females aged 20 to 24 years. Rates decreased progressively with age for both genders after 20 to 24 years, with the lowest rates seen among those aged 45 to 64 years. This pattern indicates that the burden of new STI diagnoses is concentrated among younger age groups, especially young women.
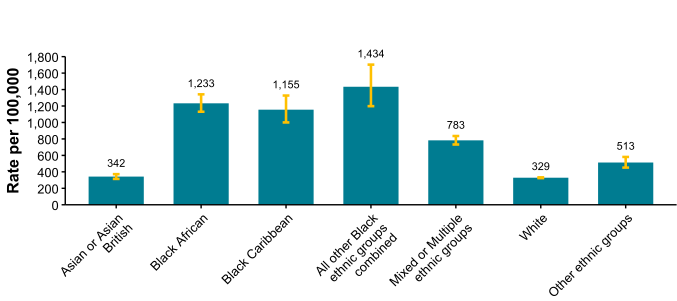
Figure 4. Rates of new STIs per 100,000 by ethnic group, South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021.
Figure 4 shows the rates of new STI diagnoses by ethnic group among South West residents in 2025. 95% confidence intervals are shown in yellow.
Marked ethnic inequalities in new STI diagnosis rates were observed across the South West. Rates were highest among Black Caribbean (1,155 per 100,000 population), Black African (1,233 per 100,000) and all other Black ethnic groups (1,434 per 100,000), and lowest among White (329 per 100,000) and Asian or Asian British groups (342 per 100,000). Rates among Mixed or Multiple (783 per 100,000) and other ethnic groups (513 per 100,000) were intermediate. These findings demonstrate substantial inequalities in STI burden by ethnicity.
Table 2. Percentage of new STI diagnoses by ethnic group, South West, 2025
| Ethnic group | Number | Percentage (excluding unknown) |
|---|---|---|
| Asian or Asian British | 545 | 3% |
| Black African | 534 | 3% |
| Black Caribbean | 199 | 1% |
| All other Black ethnic groups combined | 130 | 1% |
| Mixed or Multiple ethnic groups | 893 | 4% |
| White | 17,452 | 87% |
| Other ethnic groups | 250 | 1% |
| Unknown | 2,467 |
Data sources: GUMCAD, CTAD and ONS Census 2021.
Table 2 presents the numbers and proportions of new STI diagnoses among South West residents by ethnic group in 2025. Percentages were calculated after excluding individuals with unknown ethnicity.
The White ethnic group accounted for the largest proportion of new STI diagnoses (87%), followed by those of Mixed or Multiple ethnic groups (4%). Comparable proportions were observed among the Black African (3%) and Asian or Asian British (3%) ethnic groups. Black Caribbean (1%), other Black (1%), and those of all other ethnic groups (1%) accounted for similar proportions of diagnoses.
Ethnicity data was missing for 11.0% of all new diagnoses. This is lower than in previous years (11.6% in 2024, 11.5% in 2023).
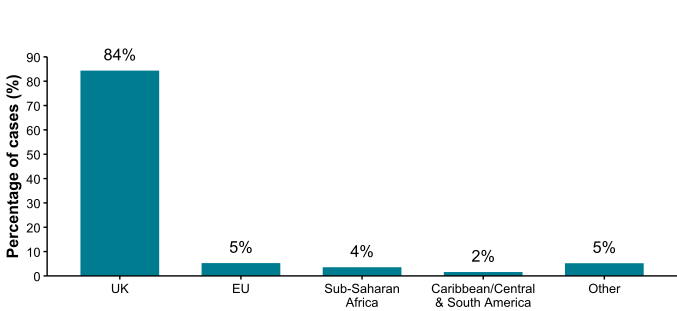
Figure 5. Percentage of new STI diagnoses by world region of birth [note], South West, 2025
Data source: GUMCAD data only.
Note: data on country of birth is not collected by CTAD. All information about world region of birth is based on diagnoses made in specialist and non-specialist services which report to GUMCAD.
Figure 5 is a column chart showing the percentage of South West residents diagnosed with a new STI by world region of birth in 2025, excluding chlamydia diagnoses reported via CTAD.
The majority of new STI diagnoses were among individuals born in the UK (84%). This was followed by those born in the European Union (5%), Sub-Saharan Africa (4%), and the Caribbean, Central and South America (2%). Individuals born in all other world regions combined accounted for the remaining 5% of new STI diagnoses.
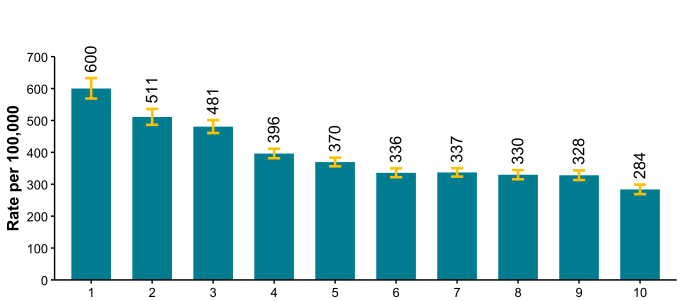
Figure 6. Rates of new STIs per 100,000 by decile of deprivation [note], South West, 2025
Data sources: GUMCAD, CTAD, ONS Index of Multiple Deprivation and Census 2021 mid-year estimates.
Note: deciles run from 1 to 10 in order of decreasing deprivation, with 1 being the decile for the most deprived area. Deprivation is based on 2021 LSOAs – which is available for 96% of GUMCAD data reported in 2025
Figure 6 is a column chart showing rates of new STI diagnoses per 100,000 population among South West residents in 2025, by deprivation decile. 95% confidence intervals are shown in yellow.
Deprivation deciles are based on the 2019 Index of Multiple Deprivation (IMD), which is calculated at the Lower-layer Super Output Area of residence (LSOA) level, a unit of geography containing around 1,500 residents. IMD deciles are calculated by LSOA at the national level for England.
Deciles 1, 2 and 3, reflecting the highest levels of deprivation, had the highest rates of new STI diagnoses, at 600, 511 and 481 per 100,000 respectively. STI diagnosis incidence generally fell with decreasing deprivation, with the lowest rate of 284 per 100,000 population observed in the least deprived decile. This indicates substantial inequalities in STI burden associated with socioeconomic deprivation.
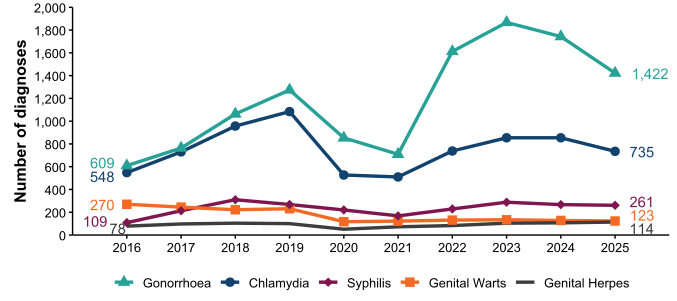
Figure 7. Diagnoses of the 5 main STIs among GBMSM [note], South West, 2016 to 2025
Data source: GUMCAD data only.
Note: data on sexual orientation is not collected by CTAD. All information about GBMSM is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services.
Figure 7 is a line graph showing trends in the number of new diagnoses of the 5 most common STIs among GBMSM in the South West between 2016 and 2025.
Among GBMSM in the South West, gonorrhoea remained the most commonly diagnosed STI throughout the period and showed the greatest overall increase. Diagnoses rose from 609 in 2016 to a pre-pandemic peak in 2019, declined sharply during the COVID-19 pandemic, and then rebounded to a peak of 1,873 in 2023 before falling to 1,422 in 2025. Despite this recent decline, diagnoses remained substantially higher than pre-pandemic levels.
Chlamydia was consistently the second most commonly diagnosed STI. Diagnoses increased from 548 in 2016 to a peak of 1,088 in 2019, before declining markedly during the COVID-19 pandemic. Diagnoses subsequently recovered between 2022 and 2024 but fell slightly to 735 in 2025, below pre-pandemic levels.
Syphilis diagnoses increased overall from 109 in 2016 to 261 in 2025, while genital warts diagnoses declined from 270 to 123. Genital herpes remained the least commonly diagnosed STI, with diagnoses increasing modestly from 78 to 114 over the same period. All 3 infections showed a slight decline during the COVID-19 pandemic, followed by a subsequent recovery.
Table 3. Percentage change in new STI diagnoses among GBMSM [note], South West
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 1,084 | 854 | 735 | −32% | −14% |
| Genital herpes | 100 | 107 | 114 | 14% | 7% |
| Genital warts | 231 | 128 | 123 | −47% | −4% |
| Gonorrhoea | 1,274 | 1,743 | 1,422 | 12% | −18% |
| Syphilis | 268 | 267 | 261 | −3% | −2% |
| Other | 479 | 420 | 376 | −22% | −10% |
| All new STIs | 3,436 | 3,519 | 3,031 | −12% | −14% |
Data source: GUMCAD data only.
See notes for Figure 7. See the New STIs section for a list of diagnoses that are included in the other STIs.
Table 3 summarises counts and trends of STI diagnoses among GBMSM residents of the South West for 2019 and between 2024 and 2025.
A total of 3,031 new STI diagnoses were reported among GBMSM residents in the South West in 2025, representing a 14% decrease compared with 2024. This decline was largely driven by reductions in gonorrhoea and chlamydia diagnoses, the 2 most commonly diagnosed STIs in this population. Between 2024 and 2025, diagnoses fell for gonorrhoea (−18%), chlamydia (-14%), other STIs (−10%), genital warts (−4%) and syphilis (−2%), while genital herpes diagnoses increased by 7%.
Compared with 2019, the largest reductions were observed in genital warts (−47%), chlamydia (−32%) and other STIs (−22%). Syphilis diagnoses changed little over the period (−3%). In contrast, genital herpes (+14%) and gonorrhoea (+12%) were the only STIs to record increases since 2019.
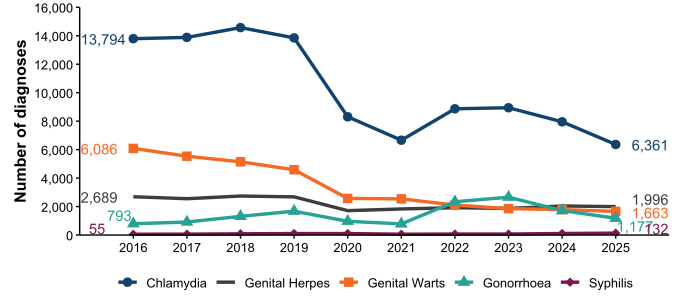
Figure 8. Diagnoses of the 5 main STIs among heterosexual men and all women [note], South West, 2016 to 2025
Data source: GUMCAD data only.
Note: data on sexual orientation is not collected by CTAD. All information here is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services. Cases are defined here as GUMCAD records where gender is specified as male and sexual orientation is specified as heterosexual, or gender was specified as female, or gender was not specified but orientation was specified as heterosexual. GUMCAD records where sexual orientation was not specified for males or unknown gender individuals are excluded.
Among heterosexual men and all women in the South West, chlamydia remained the most commonly diagnosed STI throughout the period (Figure 8). Diagnoses were relatively stable before declining sharply during the COVID-19 pandemic, then partially recovered to a peak in 2023 before falling to 6,361 in 2025.
Genital warts were the second most commonly diagnosed STI until 2022 and showed the largest overall decline, falling by 73% from 6,086 diagnoses in 2016 to 1,663 in 2025.
Gonorrhoea diagnoses increased from 793 in 2016 to a peak in 2023. Although diagnoses subsequently declined to 1,177 in 2025, gonorrhoea became the second most commonly diagnosed STI between 2022 and 2023 before returning to the second least diagnosed STI among this group in 2025.
Genital herpes diagnoses remained relatively stable throughout the period, decreasing from 2,689 in 2016 to 1,996 in 2025. Syphilis remained the least commonly diagnosed STI among heterosexual men and all women, increasing gradually from 55 diagnoses in 2016 to 132 in 2025.
As with GBMSM, diagnoses of most STIs declined during 2020 and 2021, coinciding with the COVID-19 pandemic, followed by varying degrees of recovery in subsequent years.
Table 4. Percentage change in new STI diagnoses among heterosexual men and all women [note], South West
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 13,850 | 7,955 | 6,361 | −54% | −20% |
| Genital herpes | 2,681 | 2,040 | 1,996 | −26% | −2% |
| Genital warts | 4,584 | 1,783 | 1,663 | −64% | −7% |
| Gonorrhoea | 1,675 | 1,718 | 1,177 | −30% | −31% |
| Syphilis | 102 | 107 | 132 | 29% | 23% |
| Other | 5,469 | 3,531 | 3,286 | −40% | −7% |
| All new STIs | 28,361 | 17,134 | 14,615 | −48% | −15% |
Data source: GUMCAD data only.
See notes for Figure 8 (including asterisk). See the New STIs section for a list of diagnoses included in the other STIs.
Table 4 summarises counts and trends of STI diagnoses among heterosexual men and all women in the South West from 2019 to 2025. Data is from GUMCAD only – chlamydia diagnoses from CTAD are excluded.
A total of 14,615 new STI diagnoses were reported among heterosexual men and all women in the South West in 2025, representing a 15% decrease compared with 2024 and a 48% decrease since 2019.
The decline between 2024 and 2025 was driven primarily by reductions in gonorrhoea (−31%) and chlamydia (−20%) diagnoses. Smaller decreases were observed for other STIs (−7%) and genital warts (−7%), while genital herpes diagnoses remained stable (−2%). In contrast, syphilis diagnoses increased by 23% over the same period.
Since 2019, the largest percentage decreases have been observed in genital warts (−64%), chlamydia (−54%) and other STIs (−40%). Gonorrhoea diagnoses also declined substantially (−30%), while genital herpes decreased by 26%. Syphilis was the only STI to increase over this period, rising by 29%.
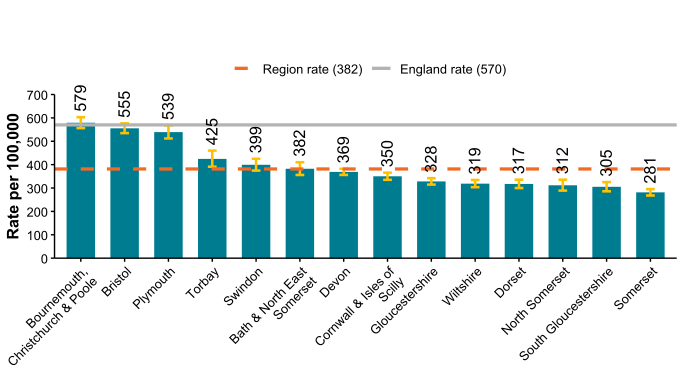
Figure 9. Rate of new STI diagnoses per 100,000 by upper tier local authority, South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 9 is a column chart comparing rates of new STI diagnosis by upper tier local authority (UTLA) in the South West. Yellow bars represent 95% confidence intervals. The overall regional and national rates are represented by the orange and grey lines respectively.
There was considerable variation in rates of new STI diagnoses across UTLAs in the South West in 2025. Bournemouth, Christchurch and Poole had the highest rate (579), followed by Bristol (555) and Plymouth (539). These local authorities reported incidence rates approaching the England value (570). Torbay (425) also reported a rate above the regional average (382). In contrast, Somerset had the lowest rate (281), followed by South Gloucestershire (305), North Somerset (312) and Dorset (317).
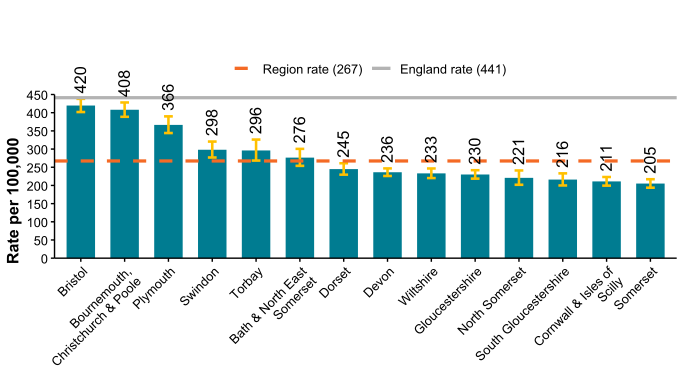
Figure 10. Rate of new STI diagnoses (excluding chlamydia diagnoses among people aged under 25 years [note]) per 100,000 by upper tier local authority, South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 10 is a column chart comparing UTLAs in the South West based on their rate of new STI diagnosis per 100,000 residents. Yellow bars represent 95% confidence intervals. The overall regional and national rates are represented by the orange and grey lines respectively.
Compared to Figure 9, Figure 10 has excluded chlamydia diagnoses in those aged 15 to 24 years, as this population includes all individuals targeted by the National Chlamydia Screening Programme (NCSP).
There was substantial variation in rates of new STI diagnoses across UTLAs in the South West in 2025. Bristol (420) recorded the highest rate, followed by Bournemouth, Christchurch and Poole (408) and Plymouth (366). Swindon (298) and Torbay (296) also reported rates above the regional average of 267 per 100,000. In contrast, Somerset had the lowest rate (205), followed by Cornwall and the Isles of Scilly (211) and South Gloucestershire (216).
All UTLAs in the South West reported rates below the England average (441).
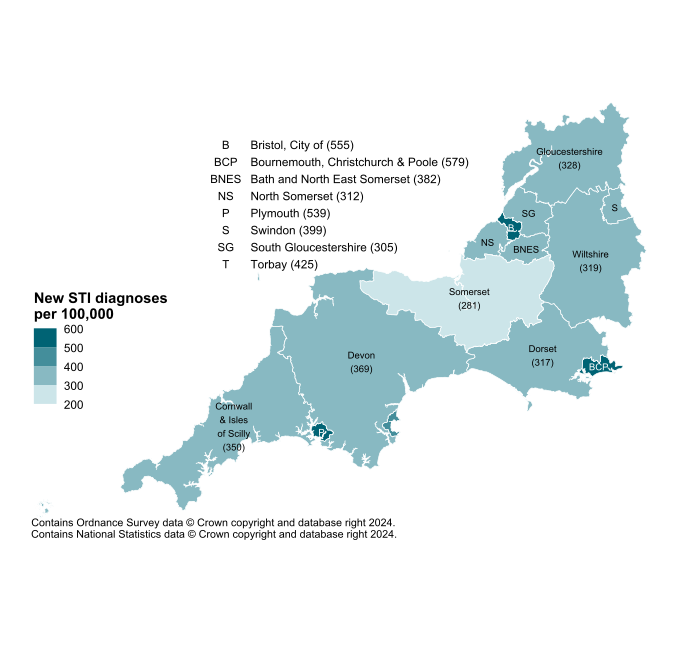
Figure 11. Map of new STI rates per 100,000 by upper tier local authority, South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 11 is a map of UTLAs in the South West showing the geographical distribution of new STI diagnosis rates in 2025. Rates varied considerably across the region, ranging from 281 per 100,000 population in Somerset to 579 per 100,000 in Bournemouth, Christchurch and Poole. Higher rates were concentrated in urban areas, including Plymouth (539), Bristol (555), Torbay (425) and Swindon (399), while lower rates were observed in South Gloucestershire (305), North Somerset (312) and Dorset (317). This pattern highlights substantial geographical variation in STI burden across the South West.
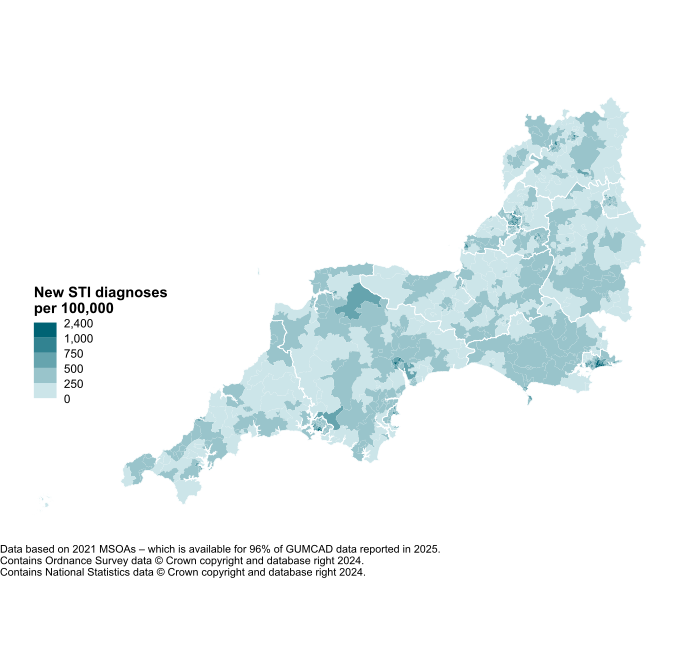
Figure 12. Map of new STI rates per 100,000 by middle super output area (MSOA21), South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 12 shows the distribution of new STI diagnosis rates at MSOA level across the South West in 2025. Considerable variation is evident within local authorities, with higher rates concentrated in urban areas and lower rates generally observed in more rural communities. While most MSOAs recorded relatively low to moderate rates, a small number of areas experienced substantially higher rates, highlighting localised concentrations of STI burden that may not be apparent when examining data at upper-tier local authority level.
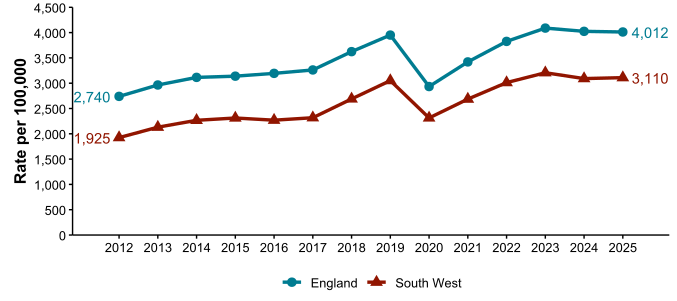
Figure 13. STI testing rate (excluding chlamydia in under-25-year-olds [note]) per 100,000, South West, 2012 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 13 is a line chart showing trends in STI testing rates in the South West between 2012 and 2025, alongside the England average. Chlamydia tests in individuals aged under 25, who are targeted by the NCSP, have been excluded from this figure.
Testing rates increased overall during the period, although a marked decline was observed in 2020. Rates subsequently recovered and remained relatively stable from 2023 onwards. Throughout the period, testing rates in the South West were consistently lower than the England average, although followed a similar trend over time.
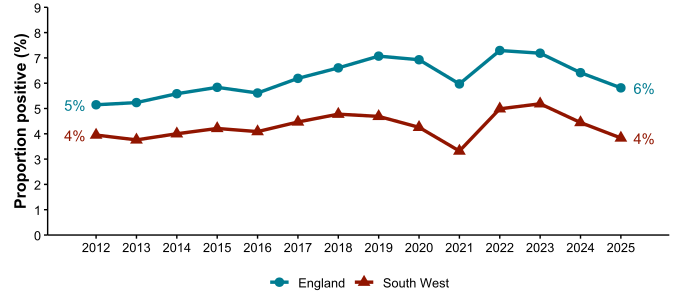
Figure 14. STI testing positivity rate (excluding chlamydia in under-25-year-olds [note]), South West, 2012 to 2025
Data sources: GUMCAD, CTAD.
Note: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 14 is a line chart showing trends in STI testing positivity in the South West between 2012 and 2025, represented as a proportion of tests that were positive, for England and the South West. As with the previous chart, chlamydia tests in individuals aged under 25, who are targeted by the NCSP, have been excluded.
Positivity rates remained consistently lower than the England average, increasing slightly between 2012 and 2019 before decreasing and returning to 4% in 2025. Over the same period, the England positivity rate increased from 5% to 6%.
Table 5. Number of diagnoses of new STIs by UKHSA region of residence, data source and Sexual Health Service Type, 2025
| UKHSA region of residence |
GUMCAD: specialist SHSs |
GUMCAD: non-specialist SHSs [note] |
CTAD | Total |
|---|---|---|---|---|
| East Midlands | 13,724 (61%) |
4,076 (18%) |
4,711 (21%) |
22,511 |
| East of England | 17,420 (68%) |
2,042 (8%) |
6,139 (24%) |
25,601 |
| London | 79,241 (72%) |
10,529 (10%) |
19,826 (18%) |
109,596 |
| North East | 9,111 (70%) |
1,703 (13%) |
2,264 (17%) |
13,078 |
| North West | 31,340 (77%) |
4,738 (12%) |
4,816 (12%) |
40,894 |
| South East | 28,757 (75%) |
1,649 (4%) |
7,914 (21%) |
38,320 |
| South West | 14,333 (64%) |
3,777 (17%) |
4,360 (19%) |
22,470 |
| West Midlands | 20,450 (74%) |
4,133 (15%) |
2,877 (10%) |
27,460 |
| Yorkshire and Humber | 18,720 (72%) |
1,636 (6%) |
5,467 (21%) |
25,823 |
Data sources: GUMCAD, CTAD.
Note: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
Table 5 summarises the number of new STI diagnoses by data source and sexual health service type across UKHSA regions in 2025. In the South West, 22,470 new STI diagnoses were reported, of which 64% were diagnosed in specialist sexual health services, 17% in non-specialist sexual health services, and 19% through CTAD-reported services. This distribution was similar to the national pattern, with specialist sexual health services accounting for the majority of diagnoses in all regions. However, the proportion diagnosed in specialist services varied across regions, ranging from 61% in the East of England to 77% in the North West.
Table 6. Number of diagnoses of the 5 main STIs by STI, data source and Sexual Health Service type, South West, 2025
| Five main STIs |
GUMCAD: specialist SHSs |
GUMCAD: non-specialist SHSs [note] |
CTAD | Total |
|---|---|---|---|---|
| Chlamydia | 4,368 (38%) |
2,690 (24%) |
4,360 (38%) |
11,418 |
| Genital herpes | 2,127 (98%) |
51 (2%) |
- | 2,178 |
| Genital warts | 1,860 (99%) |
16 (1%) |
- | 1,876 |
| Gonorrhoea | 1,878 (67%) |
916 (33%) |
- | 2,794 |
| Syphilis | 422 (100%) |
2 (<1%) |
- | 424 |
Data sources: GUMCAD, CTAD.
Note: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
Table 6 compares the number of diagnoses for the 5 main STIs in the South West across data sources and sexual health service types in 2025. It shows substantial variation in the settings where the 5 main STIs were diagnosed. Specialist sexual health services were the primary setting for diagnosis, accounting for almost all syphilis (99.5%), genital warts (99.1%) and genital herpes (97.7%) diagnoses. Chlamydia diagnoses were split between specialist services (38%), non-specialist services (24%), and CTAD-reported services (38%), while gonorrhoea diagnoses were distributed between specialist (67%) and non-specialist services (33%).
This reflects the fact that diagnoses from non-specialist SHSs largely originate from online screening services that include gonorrhoea and chlamydia testing. Online screening kits do not routinely test for genital herpes and genital warts, and syphilis is largely diagnosed after symptomatic presentation.
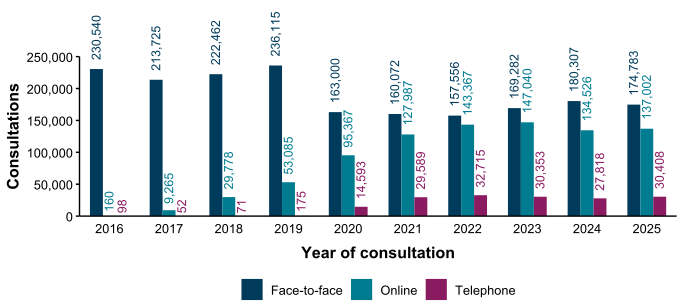
Figure 15. Consultations by service medium, South West, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Figure 15 is a grouped column chart showing the number of sexual health consultations by service medium among South West residents between 2016 and 2025. Face-to-face consultations remained the most common type throughout the period, despite a sharp decline during the COVID-19 pandemic. In contrast, online and telephone consultations increased substantially, particularly after 2020. In 2025, there were 174,783 face-to-face, 137,002 online and 30,408 telephone consultations, indicating a sustained shift towards remote service provision alongside the recovery of in-person care.
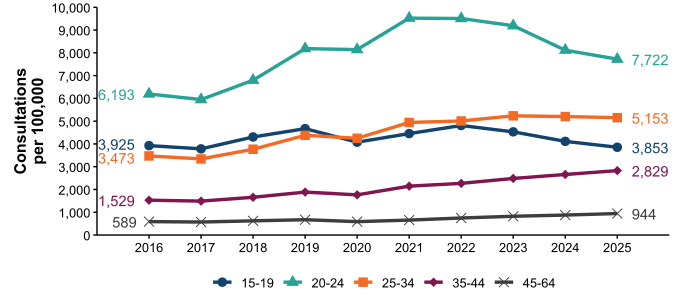
Figure 16. All consultations by age group, South West, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Figure 16 is a line chart showing trends in consultation rates by age group in the South West between 2016 and 2025. Rates were consistently highest among 20- to 24-year-olds, peaking in 2021 and remaining well above all other age groups in 2025 (7,722 per 100,000). Rates among 25 to 34 year olds increased over time and exceeded those among 15 to 19 year olds from 2020 onwards. In contrast, rates among 15 to 19 year olds remained relatively stable overall, despite a decline after 2019. Consultation rates among 45 to 64 year olds were consistently the lowest. Overall, young adults, particularly those aged 20 to 24 years, continued to have the highest levels of sexual health consultations in the South West.
Chlamydia
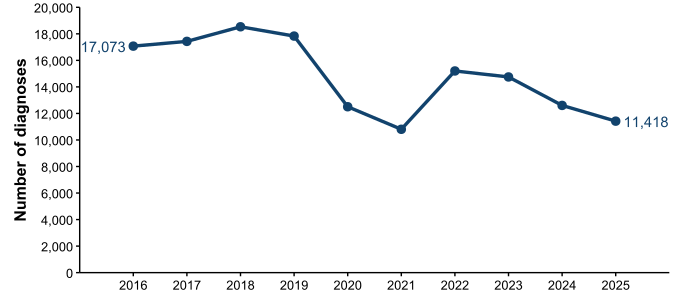
Figure 17. Number of chlamydia diagnoses, South West, 2016 to 2025
Data sources: GUMCAD, CTAD.
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
Figure 17 is a line chart showing trends in the number of chlamydia diagnoses among South West residents between 2016 and 2025. Chlamydia diagnoses declined substantially over the period, falling from 17,073 in 2016 to 11,418 in 2025. Diagnoses peaked in 2018, before declining sharply between 2019 and 2021. Although there was a partial recovery in 2022, diagnoses subsequently fell again. Despite this long-term decline, chlamydia remained the most commonly diagnosed STI in the South West in 2025 (Figure 2).
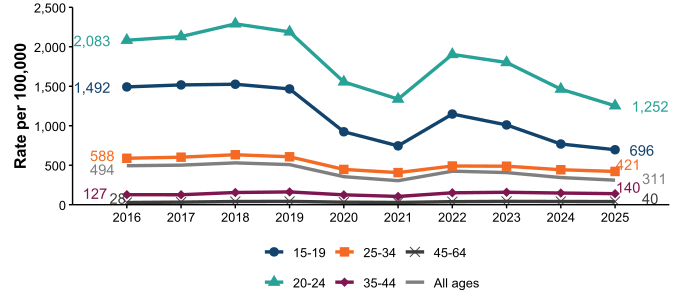
Figure 18. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only), South West, 2016 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 18 is a line chart showing trends in chlamydia diagnosis rates by age group in the South West between 2016 and 2025. Rates were consistently highest among 20 to 24 year olds, followed by 15 to 19 year olds. Rates were lowest among 45 to 64 year olds. All age groups experienced marked declines between 2019 and 2021, followed by a partial recovery and subsequent decrease from 2023 to 2025.
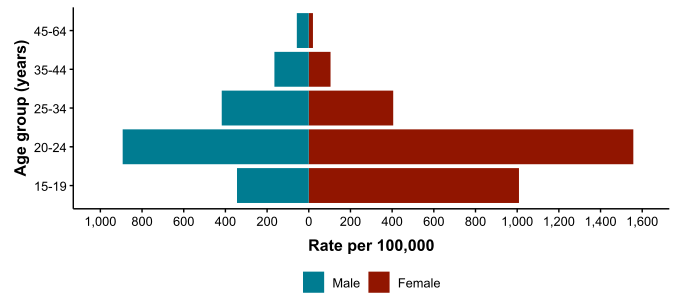
Figure 19. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only) and gender, South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 19 is an age-sex pyramid showing chlamydia diagnosis rates in the South West in 2025. Rates were highest among 20 to 24 year olds, followed by 15 to 19 year olds, for both males and females. Females had higher diagnosis rates than males across all age groups, except those aged 45 to 64 years. Rates declined with increasing age, with the lowest rates observed among 45 to 64 year olds. Overall, the burden of chlamydia was greatest among young adults, particularly females aged 20 to 24 years.
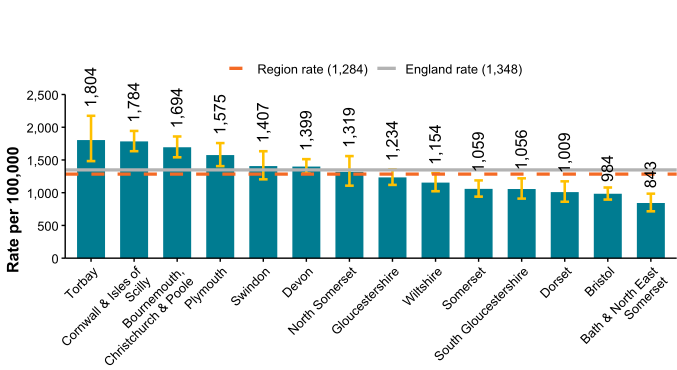
Figure 20. Chlamydia detection rate per 100,000, females aged 15 to 24 years by upper tier local authority of residence, South West, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 20 is a column chart comparing chlamydia detection rates per 100,000 population among females aged 15 to 24 years across UTLAs in the South West in 2025. 95% confidence intervals are indicated in yellow. Rates varied considerably across the region, ranging from 843 in Bath and North East Somerset to 1,804 in Torbay. Four local authorities (Torbay, Cornwall and the Isles of Scilly, Bournemouth, Christchurch and Poole, and Plymouth) reported rates significantly above both the regional (1,284) and England (1,384) averages. In contrast, rates in Bath and North East Somerset, Bristol, Dorset, South Gloucestershire, and Somerset were significantly below both averages. Wiltshire, Gloucestershire, North Somerset, Devon, and Swindon reported rates similar to the regional and/or national averages. These findings highlight substantial geographical inequalities in chlamydia detection among young females across the South West.
Gonorrhoea
Figure 21. Number of gonorrhoea diagnoses, South West, 2016 to 2025
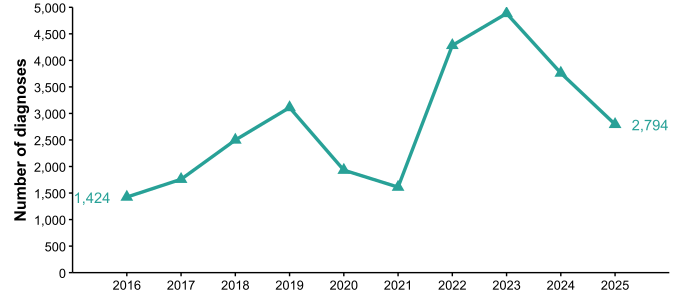
Data source: GUMCAD.
Figure 21 is a line chart showing trends in the number of gonorrhoea diagnoses reported via GUMCAD in the South West from 2016 to 2025. Diagnoses rose steadily between 2016 and 2019, then fell during the pandemic years of 2020 and 2021. Diagnoses with gonorrhoea then increased rapidly in 2022, peaking in 2023, and have subsequently declined in 2024 and 2025. However, diagnoses in 2025 (2,794) remain double those seen in 2016 (1,424).
Figure 22. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only), South West, 2016 to 2025
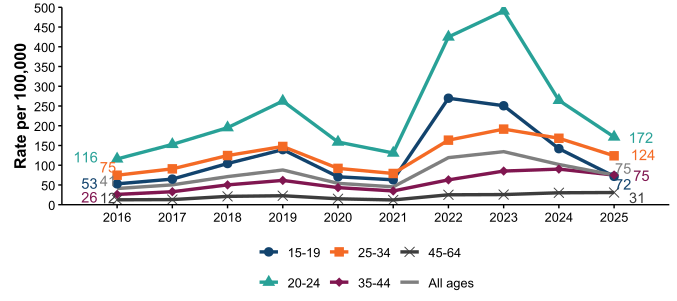
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 22 is a line chart showing trends in rates of gonorrhoea diagnoses by age group (ages 15 to 64 years only) reported via GUMCAD in the South West from 2016 to 2025. Rates are consistently highest among 20 to 24 year-olds, and lowest in those aged 45 to 64 years. Post-pandemic, in 2022, there was a notable increase in the rate of diagnosis among 15 to 19 year olds, taking them above 25 to 34 year olds for 2 years until a subsequent decline in 2024.
Rates among all age groups in 2025 are higher than in 2016.
Figure 23. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only) and gender, South West, 2025
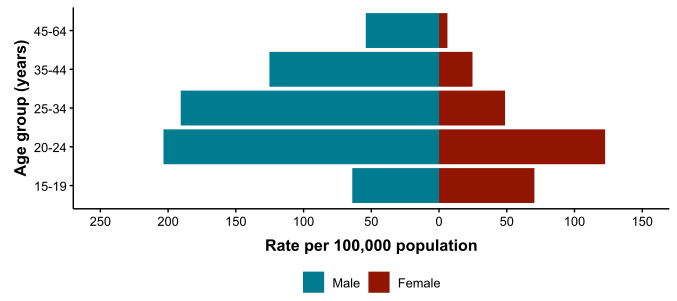
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 23 is an age-sex pyramid showing the rates of gonorrhoea diagnoses reported via GUMCAD in the South West in 2025. Among 15- to 19-year-olds, gonorrhoea rates were marginally higher in females, however across all other ages were greater in males. The highest rates of gonorrhoea were seen in the 20-to-24-year age group in both males and females.
Figure 24. Rates of gonorrhoea diagnoses per 100,000 by upper tier local authority, South West, 2025
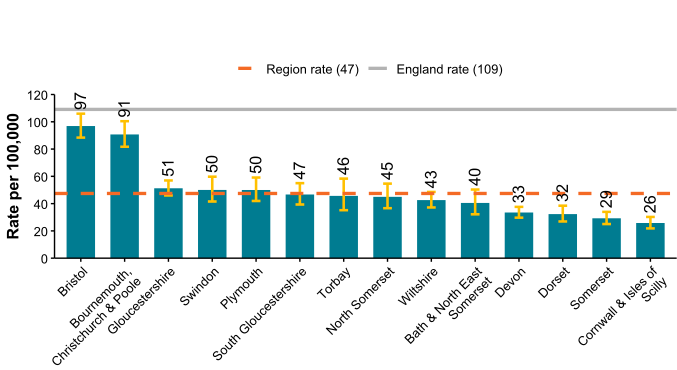
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 24 is a bar chart showing rates of gonorrhoea diagnosis in 2025 by upper tier local authority in the South West. 95% confidence intervals are indicated in yellow. Bristol (97 cases per 100,000 residents) and Bournemouth, Christchurch and Poole (91) had the highest rates in the South West, but were below the England overall rate (109); the overall rate for the South West was 47 cases per 100,000 population.
Devon (33 cases per 100,000 population), Dorset (32), Somerset (29) and Cornwall and the Isles of Scilly (26) were the local authorities with the lowest rates in the South West.
Genital warts
Figure 25. Number of genital warts diagnoses, South West, 2016 to 2025
Data source: GUMCAD.
Figure 25 is a line chart showing the number of diagnoses of genital warts across the South West, reported via GUMCAD from 2016 to 2025. Numbers of diagnoses have decreased consistently from 6,416 in 2016 to 1,876 in 2025.
Figure 26. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only), South West, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
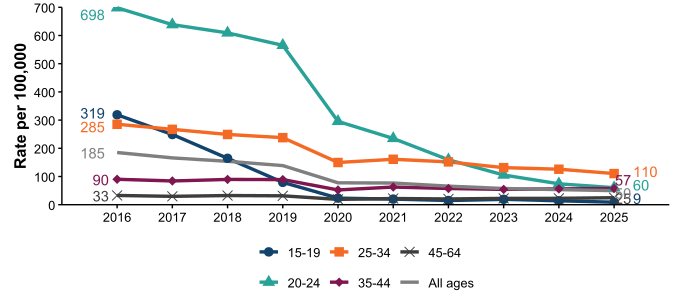
Figure 26 is a line chart showing trends in rates of genital warts diagnoses by age group across the South West, for those aged 15 to 65 years only, reported via GUMCAD from 2016 to 2025. There has been a steady decline in the rates of genital warts across all age groups, most marked among those aged 15 to 19 years and 20 to 24 years, because of the HPV vaccination programme introduced in 2008 for females and 2019 for males.
Figure 27. Rates of genital warts per 100,000 aged 15 to 19 and 20 to 24 years by gender, South West, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
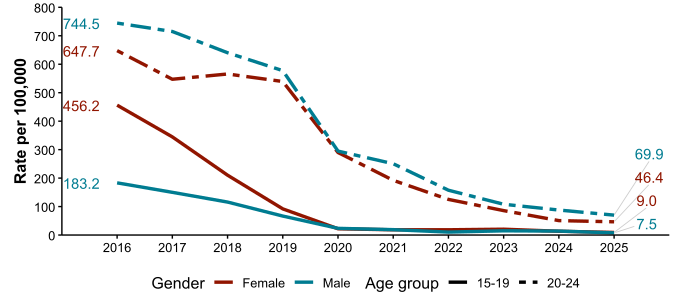
Figure 27 is a line chart showing trends in rates of new diagnoses of genital warts by age group and gender across the South West for those aged 15 to 24 years only, reported via GUMCAD, from 2016 to 2025. A dramatic decline in case rates from 2016 to 2025 is seen among both males and females across both age groups. Among 15 to 19 year old females, case rates have fallen from 456 per 100,000 in 2016 to 9 per 100,000 in 2025, with males falling from 183 to 7.5 per 100,000. The decline in the rate of genital warts can be explained by the introduction of the HPV vaccination programme in 2008 for females and 2019 for males.
Figure 28. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only) and gender, South West, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
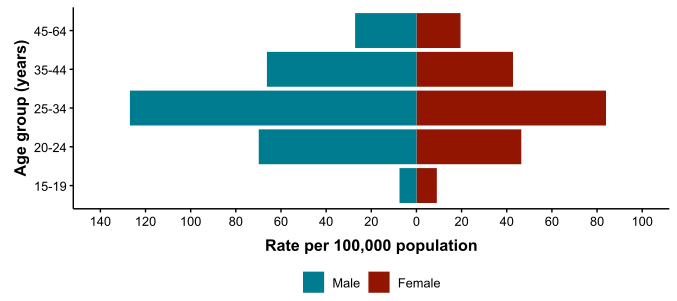
Figure 28 is an age-sex pyramid showing the rates of genital warts reported via GUMCAD for those aged 15 to 64 years only in the South West in 2025. Rates were very low in the 15-19 years age group, and highest in those aged 25 to 34 years. Case rates were higher in males in all age groups from 20 years upwards.
Syphilis
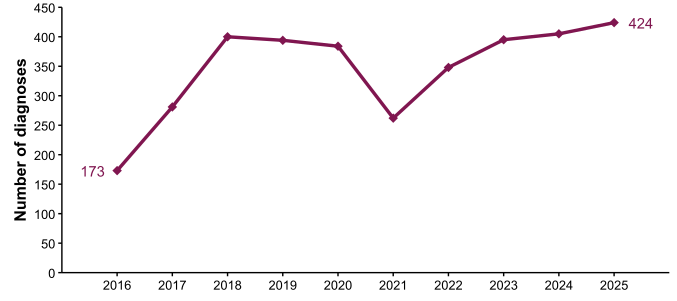
Figure 29. Number of syphilis diagnoses, South West, 2016 to 2025
Data source: GUMCAD.
Figure 29 is a line chart showing the number of syphilis diagnoses reported via GUMCAD across the South West from 2016 to 2025. Overall, case numbers have risen from 173 in 2016 to 424 in 2025. Following a reduction in cases in 2021, diagnoses have increased steadily from 2022 to 2025.
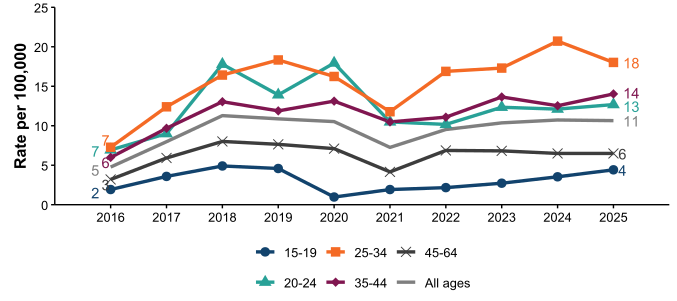
Figure 30. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only), South West, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 30 is a line chart showing trends in rates per 100,000 population of new syphilis diagnoses by age group, for those aged 15 to 64 years only, reported via GUMCAD from the South West from 2016 to 2025. The highest rates of syphilis in the South West in recent years are in those aged 25 to 34, and lowest in those 15 to 19 years. However, all age groups from 15 to 19 up to 45 to 64 years have had a proportionally similar increase in rates between 2016 and 2025.
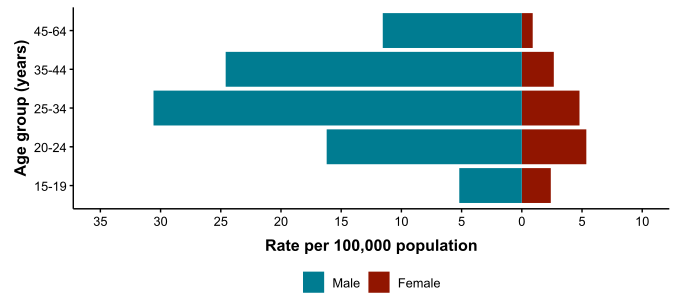
Figure 31. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only) and gender, South West, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 31 is an age-sex pyramid showing rates of syphilis diagnoses reported via GUMCAD in the South West in 2025. Across all age groups syphilis, diagnoses were higher in males, with the highest rates seen in males aged 25 to 34 and 35 to 44 years.
Genital herpes
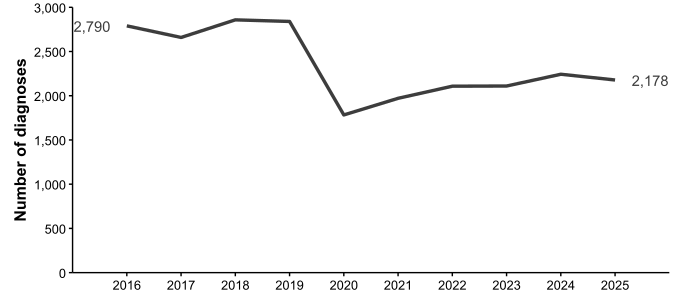
Figure 32. Number of genital herpes diagnoses, South West, 2016 to 2025
Data source: GUMCAD.
Figure 32 is a line chart showing the number of diagnoses of genital herpes reported via GUMCAD across the South West from 2016 to 2025. The number of diagnoses has fallen from 2,790 in 2016 to 2,178 in 2025. In recent years (2022 to 2025) there has been a slight increase in diagnosis numbers following the reduction seen in 2020.
Figure 33. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only), South West, 2016 to 2025
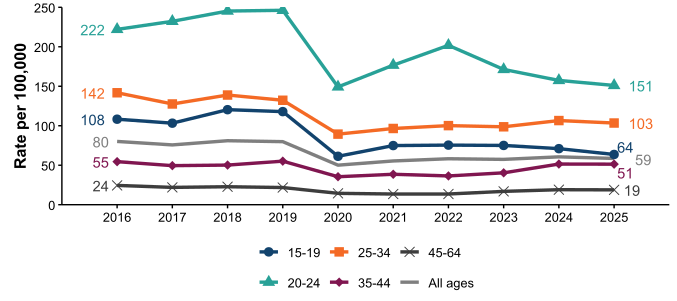
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 33 is a line chart showing trends in rates per 100,000 population of new genital herpes diagnoses by age group for those aged 15 to 64 years only, reported via GUMCAD, across the South West, from 2016 to 2025. Diagnosis rates are highest in those aged 20 to 24 years, and lowest among 45 to 64 year olds. A decline in diagnosis rates of around one-third between 2016 and 2025 is seen across all age groups except for 35 to 44 year olds, where they have remained stable.
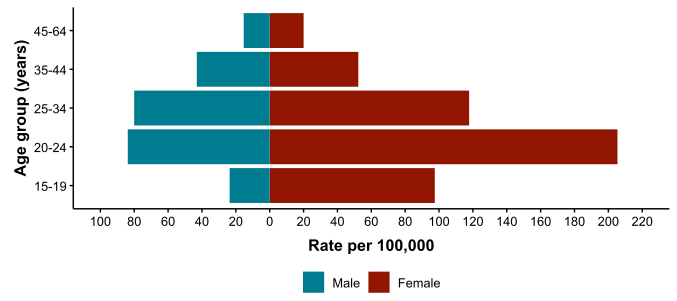
Figure 34. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only) and gender, South West, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 34 is an age-sex pyramid showing rates of genital herpes diagnoses reported via GUMCAD in the South West in 2025. Across all age groups, genital herpes diagnoses were higher in females, with the highest rates seen in females aged 20 to 24 years.
Information on data sources
Find more information on local sexual health data sources in the UKHSA guide.
The gender and age group chart is restricted to those aged 15 to 64 years as information about STIs in those aged under 15 years is considered highly sensitive. Analyses specific to this group are not provided in routine outputs. Rates for those aged 65 or older are withheld to ensure that no deductive disclosure is possible for the under 15 years age group. The proportion of STIs in those aged under 15 years or older than 64 years is very low.
GUMCAD surveillance system
This disaggregate reporting system collects information about attendances and diagnoses at specialist (Level 3) and non-specialist (Level 2) sexual health services. Information about the patient’s area of residence is collected along with demographic data and other variables. GUMCAD superseded the earlier KC60 system and can provide data from 2009 onwards. GUMCAD is the main source of data for this report.
Due to limits on how much personally identifiable information sexual health clinics are able to share, it is not possible to deduplicate between different clinics. There is a possibility that some patients may be counted more than once if they are diagnosed with the same infection (for infection specific analyses) or a new STI of any type (for new STI analyses) at different clinics during the same calendar year.
CTAD surveillance system
CTAD collects data on all local authority and NHS or NHS-commissioned chlamydia testing carried out in England. CTAD is comprised of all chlamydia (NAATs) tests for all ages (with the exception of conjunctival samples), from all venues and for all reasons. CTAD enables unified, comprehensive reporting of all chlamydia data, to effectively monitor the impact of the NCSP through estimation of the coverage of population screening, proportion of all tests that are positive and detection rates.
For services which report to GUMCAD and for which CTAD does not receive data on the patient’s area of residence (for example, SHSs), information about chlamydia diagnoses is sourced from GUMCAD data.
CTAD does not collect information about sexual orientation or country of birth. Reports from CTAD are excluded from figures in this report which relate to analyses by sexual orientation or world region of birth.
New STIs
New STI diagnoses comprise diagnoses of the following:
- chancroid
- Lymphogranuloma venereum (LGV)
- donovanosis
- chlamydia
- gonorrhoea
- genital herpes (first episode)
- HIV (acute and AIDS defining)
- Molluscum contagiosum
- non-specific genital infection (NSGI)
- non-specific pelvic inflammatory disease (PID) and epididymitis
- chlamydial PID and epididymitis (presented in chlamydia total)
- gonococcal PID and epididymitis (presented in gonorrhoea total)
- scabies
- pediculosis pubis
- syphilis (primary, secondary and early latent)
- trichomoniasis and genital warts (first episode)
- Mycoplasma genitalium
- shigella
Calculations
Confidence Intervals were calculated using Byar’s method for numerators >= 10. For small numerators Byar’s method is less accurate and so an exact method based on the Poisson distribution is used.
ONS mid-year population estimates for 2024 were used as a denominator for rates (other than by ethnic group) for 2025. ONS estimates of population by ethnic group for the year 2021 were used as a denominator for rates by ethnic group for 2025. This is the first time that new estimates of population by ethnic group have been available since 2011. This must be considered if comparing rates for 2025 in this report with rates by 2024 in last year’s report, as the rates in the last report used the 2011 estimates.
Interpreting trends
When interpreting trends in the number of STI diagnoses it is important to consider the potential impact of changes to testing, vaccination programmes and the availability of interventions (such as prophylaxis). Specifically, diagnostic testing for gonorrhoea and genital herpes now includes in some areas highly sensitive testing using nucleic acid amplification tests. Additionally, there is some screening of GBMSM at extra-genital sites. Where in place, both will have led to increased case ascertainment of gonorrhoea and genital herpes. Local testing practices for all STIs may vary.
Further information
As of 2020, all analyses for this report include data from non-specialist (Level 2) SHSs and enhanced GP services as well as specialist (Level 3) SHSs.
For further information, see the online Sexual and Reproductive Health Profiles.
For more information on HIV data, see the separate HIV Spotlight report.
For more information on local sexual health data sources, see the UKHSA guide.
Local authorities have access to the Summary Profile of Local Authority Sexual Health (SPLASH) Reports (accessible from the Sexual and Reproductive Health Profiles) and the SPLASH supplement reports via the HIV and STI Data exchange.
About the Field Services
The Field Services was established in 2018 as a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Real-time Syndromic Surveillance and Public Health Microbiology to strengthen the surveillance, intelligence and response functions of UKHSA.
You can contact your local FS team at FES.SouthWest@ukhsa.gov.uk
Acknowledgements
We would like to thank:
- local SHSs for supplying the SHS data
- local laboratories for supplying the CTAD data
- UKHSA Blood Safety, Hepatitis, Sexually Transmitted Infections (STI) and HIV Division for collection, analysis and distribution of data