Spotlight on sexually transmitted infections in the East of England: 2025 data
Updated 8 October 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/sexually-transmitted-infections-east-of-england-data/spotlight-on-sexually-transmitted-infections-in-the-east-of-england-2025-data
Summary
While this report primarily focuses on the trend between 2024 and 2025, some trends relative to 2019 or earlier are included to provide a comparison to sexual health service provision and sexually transmitted infection (STI) diagnoses prior to the COVID-19 pandemic during 2020 and 2021. For England, the numbers of consultations, sexual health screens and STI diagnoses in 2020 and 2021 are lower than preceding years and any trends during periods which include those years must be interpreted in that context. STIs represent an important public health problem in the East of England. Of all the UK Health Security Agency (UKHSA)’s regions it has the lowest rate of new STIs in England. However, it is important to highlight that diagnoses rates of new STIs should be interpreted alongside data on STI testing and positivity rates. For the East of England both are consistently below the England rate.
There was an overall increase in the number of consultations at specialist sexual health services in the East of England between 2024 and 2025 (1.4%, 367,628 to 372,663). Online consultations made up 43% of all consultations in 2025. An appropriate mix of both face to face and online services may facilitate access to SHSs given evidence of inequality of use of online services and some people finding it difficult to be tested for STIs using online services (1).
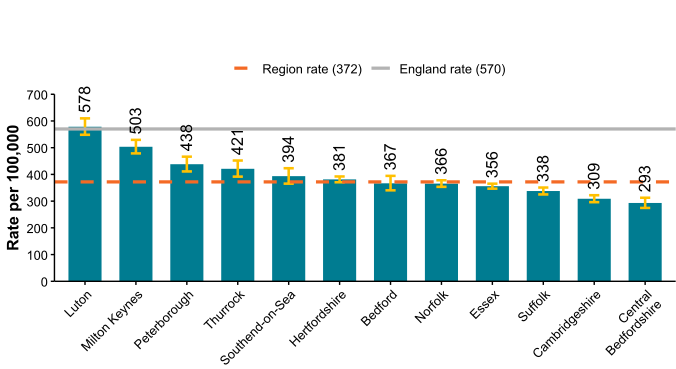
25,601 new STIs were diagnosed in the East of England population in 2025, a rate of 372 diagnoses per 100,000. Rates by upper tier local authority ranged from 293 new STI diagnoses per 100,000 in Central Bedfordshire to 578 new STI diagnoses per 100,000 in Luton.
The number of new STIs diagnosed in the East of England population decreased by 4% between 2024 and 2025. Changes were seen in the numbers of the 5 main STIs: syphilis decreased by 18%, gonorrhoea decreased by 3%, chlamydia decreased by 6%, genital herpes increased by 2% and genital warts increased by 1%. However, the trends varied by age group over time.
UKHSA recommends that local areas should be working towards achieving a chlamydia detection rate no lower than 3,250 per 100,000 among women aged 15 to 24 years and this is an indicator in the Public Health Outcomes Framework. In 2025, the chlamydia detection rate among East of England women aged 15 to 24 years was 1,026 per 100,000 compared to 1,201 per 100,000 in 2024.
Rates of new STIs vary slightly between men and women (380 and 311 per 100,000, respectively). Where gender and sexual orientation are known, gay, bisexual and other men who have sex with men (GBMSM) account for 17% of the East of England population diagnosed with a new STI excluding chlamydia diagnoses reported via CTAD (63% of those diagnosed with syphilis and 55% of those diagnosed with gonorrhoea).
STIs disproportionately affect young people. The East of England population aged between 15 and 24 years accounted for 37% of all new STI diagnoses in 2025. A steep decline has been seen in genital warts diagnosis rates in females aged 15 to 19 following the introduction in 2008 of vaccination against human papillomavirus (HPV), the virus which causes genital warts, for girls. Recent years have seen fluctuating rates though, with a 97% decrease in East of England from 2016 to 2025.
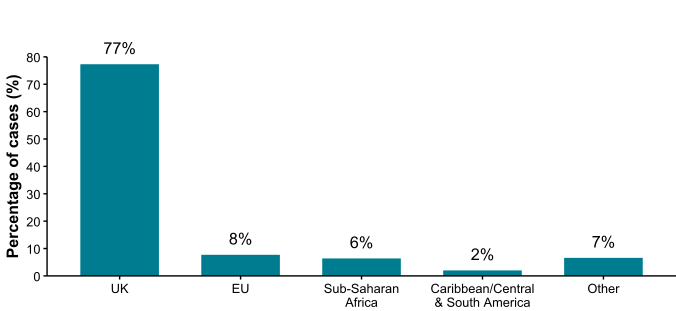
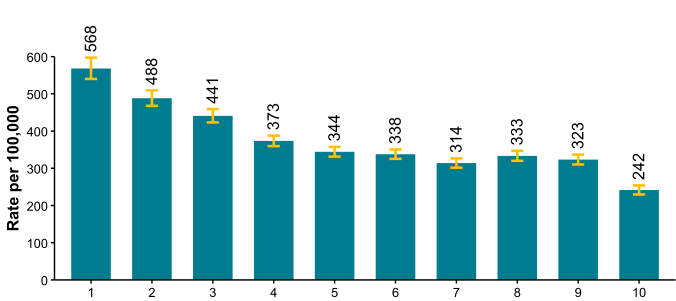
The White ethnic group has the highest number of new STI diagnoses: 15,589 (73%). Although 3% of new STIs are in the Black Caribbean ethnic group, they have the highest rate: 1,585 per 100,000, which is 5.6 times the rate seen in the White ethnic group. Where country of birth was known, 77% of the East of England population diagnosed with a new STI in 2025 (excluding chlamydia diagnoses reported via CTAD) were UK-born. The rate of new STIs among people who lived in the most deprived areas (568 per 100,000) was 2.4 times higher than the rate for people who live in the least deprived areas (242 per 100,000).
Prevention messages
Prevention messages are:
Sexual health clinics are free, confidential and available to everyone. They provide testing, post-exposure prophylaxis and treatment for STIs and HIV, as well as vaccination and contraception.
Using condoms consistently and correctly with new or casual partners protects against HIV and other STIs.
Testing is recommended if you have had sex without a condom with a new or casual partner in the last 3 months, or if a partner has tested positive for an STI. In addition:
- women and other people with a womb aged under 25 who are sexually active should have a chlamydia test after sex with a new partner or annually
- gay and bisexual men (GBMSM) with new or casual partners should test for HIV and STIs annually or every 3 months if having sex without condoms with new or casual partners
Prevention medications (known as pre- and post-exposure prophylaxis) can prevent HIV and some STIs:
- doxycycline post-exposure prophylaxis (doxyPEP) is recommended to people at risk of syphilis to reduce their chance of infection – doxyPEP is available at specialist sexual health clinics
- HIV pre-exposure prophylaxis (PrEP) reduces an individual’s risk of getting HIV – PrEP is available from specialist sexual health clinics
- HIV post-exposure prophylaxis (PEP) can be taken after sex to reduce the risk of getting HIV – PEP is available for free from most sexual health clinics and most emergency departments
Vaccination can prevent some STIs and blood-borne viruses:
- GBMSM can get the hepatitis A and hepatitis B vaccines from specialist sexual health clinics – these vaccines are also available for other people with a higher risk of exposure to these viruses
- GBMSM aged 45 years and younger can get the human papillomavirus (HPV) vaccine from specialist sexual health clinics – this protects against genital warts and some forms of cancer
- GBMSM who have recently had multiple sexual partners or an STI and other people at higher risk are eligible for a meningococcal B disease vaccine (4CMenB) which can protect against gonorrhoea
- mpox vaccination is available for people at increased risk, including GBMSM who have recently had multiple sexual partners
- hepatitis B and HPV vaccines are also part of the routine childhood vaccination programme – catch-up vaccines are available for people who missed them at school
STIs in the East of England
Overview
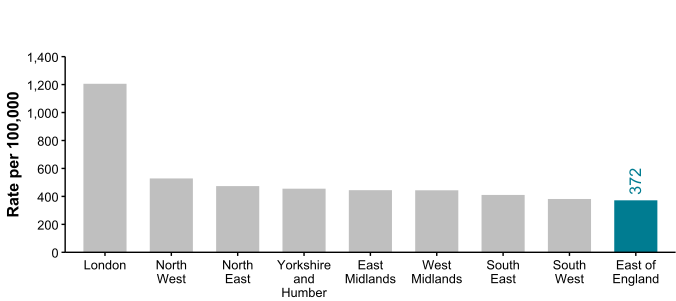
Figure 1. New STI diagnosis rates by UKHSA region of residence, England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 1 is a bar chart showing the rate of new STI diagnoses per 100,000 population by UKHSA region of residence in 2025. The East of England had the lowest rate (372 per 100,000) in England. London had the highest rate.
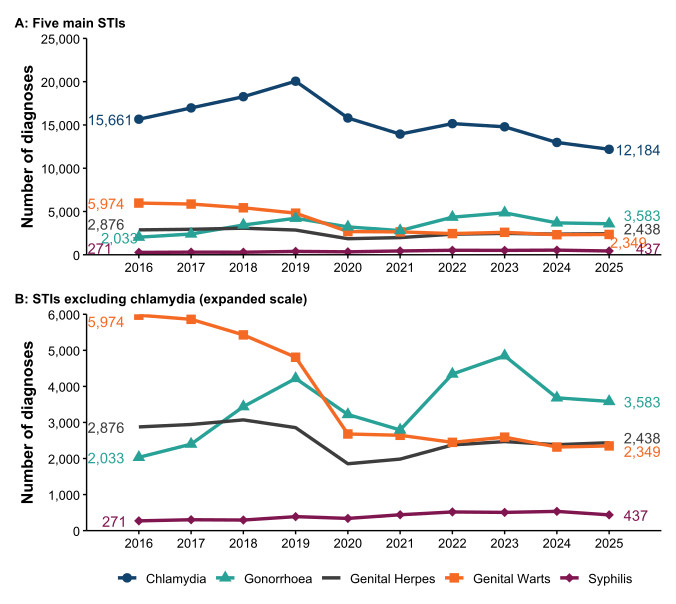
Figure 2. Number of diagnoses of the 5 main STIs (East of England, 2016 to 2025): A) all 5 STIs; B) excluding chlamydia (expanded scale)
Data sources: GUMCAD, CTAD.
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
Figure 2A shows trend lines for the number of diagnoses of the 5 main STIs among East of England residents from 2016 to 2025. Diagnoses of gonorrhoea, and syphilis increased during this time period whereas diagnoses of chlamydia, genital warts and genital herpes decreased.
Figure 2B shows trend lines as in Figure 2A but excluding chlamydia. Between 2024 and 2025 there were slight increases in the number of diagnoses of genital warts and genital herpes.
Table 1. Percentage change in new STI diagnoses, East of England
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 20,053 | 12,978 | 12,184 | -39% | -6% |
| Genital herpes | 2,856 | 2,383 | 2,438 | -15% | 2% |
| Genital warts | 4,808 | 2,318 | 2,349 | -51% | 1% |
| Gonorrhoea | 4,220 | 3,682 | 3,583 | -15% | -3% |
| Syphilis | 388 | 534 | 437 | 13% | -18% |
| Other | 6,211 | 4,756 | 4,610 | -26% | -3% |
| All new STIs | 38,536 | 26,651 | 25,601 | -34% | -4% |
Data sources: GUMCAD, CTAD.
See notes for Figure 2. See section on New STIs for a list of diagnoses that are included in the other STIs.
Table 1 shows the percentage change in new STI diagnoses in East of England residents. In 2025, 25,601 new STI diagnoses were made in the East of England, which was 4% lower than 2024 and 34% lower than in 2019. Syphilis was the only infection that showed an increase between 2019 and 2025, however, there was an 18% decrease in diagnoses of this infection between 2024 and 2025. Genital warts and genital herpes showed a slight increase between 2024 and 2025.
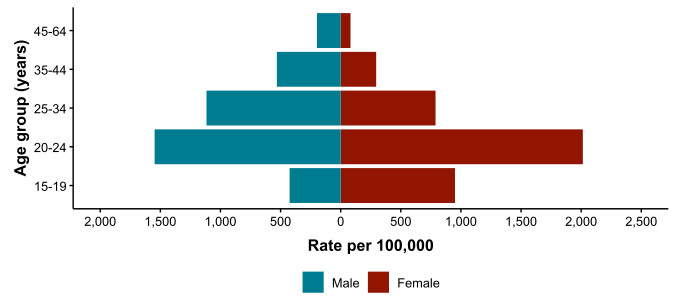
Figure 3. Rates of new STIs per 100,000 by age group (for those aged 15 to 64 years only) and gender, East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 3 is a bar chart showing that the highest rates of new STIs in 2025 were in the group aged 20 to 24 years for both males and females, with a higher rate of diagnosis in females. The lowest rates of new STIs in 2025 were in those aged 45 to 65 years for both males and females.
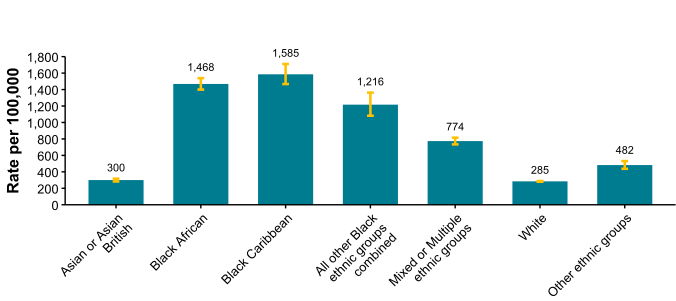
Figure 4. Rates of new STIs per 100,000 by ethnic group, East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021.
Figure 4 is a bar chart showing rates of new STIs by ethnic group per 100,000 in the East of England in 2025. The Black Caribbean ethnic group had the highest rate of STIs in 2025 (1,585 per 100,000) followed by the Black African ethnic group (1,468 per 100,000), All other Black ethnic groups combined (1,216 per 100,000). The White ethnic group had the lowest rate of STIs in 2025 (285 per 100,000).
Table 2. Percentage of new STI diagnoses by ethnic group, East of England, 2025
| Ethnic group | Number | Percentage (excluding unknown) |
|---|---|---|
| Asian or Asian British | 1,218 | 6% |
| Black African | 1,743 | 8% |
| Black Caribbean | 664 | 3% |
| All other Black ethnic groups combined | 296 | 1% |
| Mixed or Multiple ethnic groups | 1,390 | 7% |
| White | 15,589 | 73% |
| Other ethnic groups | 416 | 2% |
| Unknown | 4,285 |
Data sources: GUMCAD, CTAD and ONS Census 2021.
Table 2 shows the proportion of East of England residents diagnosed with a new STI by ethnicity in 2025. The White ethnic group made up the greatest proportion (73%) and the all other Black ethnic groups combined the lowest (1%).
Figure 5. Percentage of new STI diagnoses by world region of birth [note 1], East of England, 2025
Data sources: GUMCAD data only.
Note 1: data on country of birth is not collected by CTAD. All information about world region of birth is based on diagnoses made in specialist and non-specialist services which report to GUMCAD.
Figure 5 is a bar chart showing the proportion of East of England residents diagnosed with a new STI by world region of birth in 2025. The highest proportion was in those who were UK born (77%) followed by the EU excluding UK (8%).
Figure 6. Rates of new STIs per 100,000 by decile of deprivation [note 2], East of England, 2025
Data sources: GUMCAD, CTAD, ONS Index of Multiple Deprivation and Census 2021 mid-year estimates.
Note 2: deciles run from 1 to 10 in order of decreasing deprivation, with 1 being the decile for the most deprived area. Deprivation is based on 2021 LSOAs – which is available for 96% of GUMCAD data reported in 2025
Figure 6 is a bar chart showing rates of new STIs per 100,000 residents by decile of deprivation. The highest rates are in those living in the most deprived areas. Rates increased from the least deprived (Decile 10) to the most deprived areas (Decile 1).
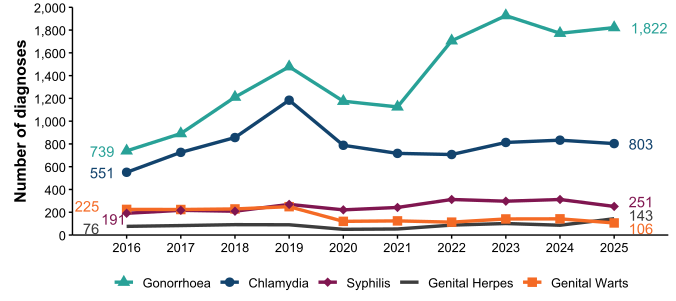
Figure 7. Diagnoses of the 5 main STIs among GBMSM [note 3], East of England, 2016 to 2025
Data sources: GUMCAD data only.
Note 3: data on sexual orientation is not collected by CTAD. All information about GBMSM is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services.
Figure 7 shows trend lines for diagnoses of the 5 main STIs among GBMSM residents in the East of England from 2016 to 2025. Diagnoses of gonorrhoea, chlamydia, syphilis and genital herpes were higher in 2025 than in 2016. Diagnoses of genital warts decreased from 225 in 2016 to 106 in 2025. Gonorrhoea had the highest number of diagnoses in 2025 (1,822) followed by chlamydia (803).
Table 3. Percentage change in new STI diagnoses among GBMSM, East of England
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 1,184 | 833 | 803 | -32% | -4% |
| Genital herpes | 90 | 86 | 143 | 59% | 66% |
| Genital warts | 249 | 142 | 106 | -57% | -25% |
| Gonorrhoea | 1,478 | 1,772 | 1,822 | 23% | 3% |
| Syphilis | 269 | 312 | 251 | -7% | -20% |
| Other | 542 | 500 | 468 | -14% | -6% |
| All new STIs | 3,812 | 3,645 | 3,593 | -6% | -1% |
Data sources: GUMCAD data only.
See notes for Figure 7. See section on New STIs for a list of diagnoses that are included in the other STIs.
Table 3 shows the percentage change in new STI diagnoses in GBMSM residents in the East of England between 2019 and 2025 and 2024 and 2025. In 2025, 3,593 new STI diagnoses were made in GBMSM in the East of England. Diagnoses of genital herpes and gonorrhoea increased between 2019 and 2025 whereas diagnoses of chlamydia, genital warts and syphilis decreased. Between 2024 and 2025 the number of genital herpes diagnoses increased by 66% and the number of gonorrhoea diagnoses increased by 3%.
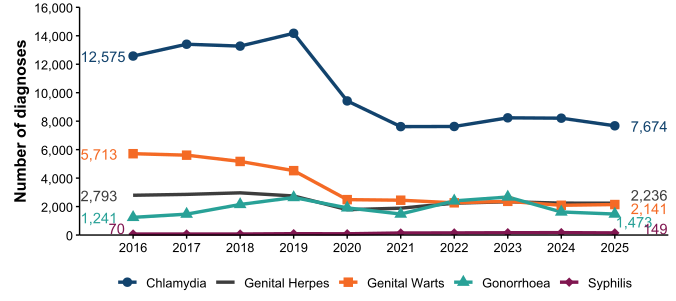
Figure 8. Diagnoses of the 5 main STIs among heterosexual men and all women [note 4], East of England, 2016 to 2025
Data sources: GUMCAD data only.
Note 4: data on sexual orientation is not collected by CTAD. All information here is based on diagnoses made in specialist and non-specialist services which report to GUMCAD and exclude chlamydia diagnoses via online services. Cases are defined here as GUMCAD records where gender is specified as male and sexual orientation is specified as heterosexual, or gender was specified as female, or gender was not specified but orientation was specified as heterosexual. GUMCAD records where sexual orientation was not specified for males or unknown gender individuals are excluded.
Figure 8 shows trend lines for diagnoses of the 5 main STIs among heterosexual men and all women residents in the East of England from 2016 to 2025. Diagnoses of chlamydia, genital warts and genital herpes have decreased during this time period. Diagnoses of syphilis increased from 70 in 2016 to 149 in 2025 and diagnoses of gonorrhoea from 1,241 in 2016 to 1,473 in 2025.
Table 4. Percentage change in new STI diagnoses among heterosexual men and all women, East of England
| Diagnosis | 2019 | 2024 | 2025 | Percentage change 2019 to 2025 | Percentage change 2024 to 2025 |
|---|---|---|---|---|---|
| Chlamydia | 14,174 | 8,209 | 7,674 | -46% | -7% |
| Genital herpes | 2,744 | 2,241 | 2,236 | -19% | <0.5% change |
| Genital warts | 4,522 | 2,089 | 2,141 | -53% | 2% |
| Gonorrhoea | 2,635 | 1,620 | 1,473 | -44% | -9% |
| Syphilis | 94 | 167 | 149 | 59% | -11% |
| Other | 5,569 | 4,089 | 3,988 | -28% | -2% |
| All new STIs | 29,738 | 18,415 | 17,661 | -41% | -4% |
Data sources: GUMCAD data only.
See notes for Figure 8. See section on New STIs for a list of diagnoses included in the other STIs.
Table 4 shows the percentage change in new STI diagnoses among heterosexual men and all women resident in the East of England between 2019 and 2025 and 2024 and 2025. In 2025, 17,661 new STI diagnoses were made in heterosexual men and all women in the East of England. Diagnoses of syphilis increased by 59% between 2019 and 2025 but decreased by 11% between 2024 and 2025. Genital warts had a small (2%) increase between 2024 and 2025.
Figure 9. Rate of new STI diagnoses per 100,000 by upper tier local authority, East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 9 is a bar chart showing the rate of new STI diagnoses per 100,000 population among East of England residents by upper tier local authority of residence in 2025. Luton, Milton Keynes and Peterborough had the highest rates and Central Bedfordshire had the lowest rate.
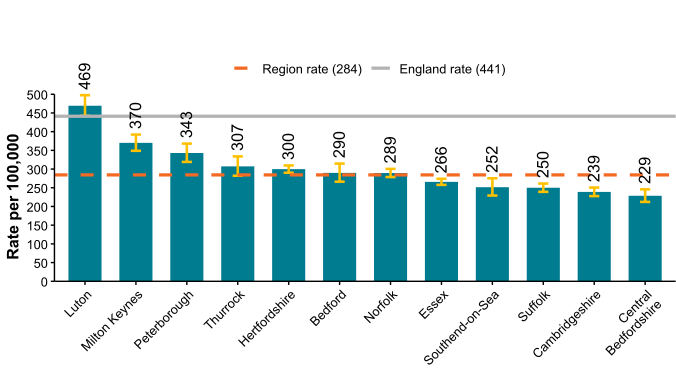
Figure 10. Rate of new STI diagnoses (excluding chlamydia diagnoses among people aged under 25 years [note 5]) per 100,000 by upper tier local authority, East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note 5: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 10 is a bar chart showing the rate of new STI diagnoses per 100,000 population among East of England residents excluding chlamydia diagnoses in residents aged less than 25 years by upper tier local authority of residence in 2025. Luton, Milton Keynes and Peterborough continue to have the highest rates and Central Bedfordshire the lowest rate as in Figure 9.
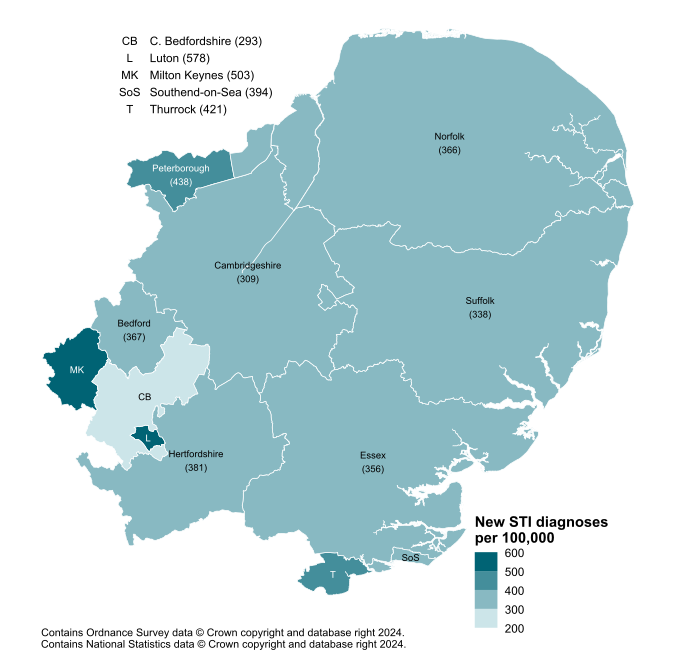
Figure 11. Map of new STI rates per 100,000 by upper tier local authority, East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 11 is a map of all East of England upper tier local authorities showing new STI rates per 100,000 residents in 2025. Two local authorities (Luton and Milton Keynes) had rates higher than 500 per 100,000. All other upper tier local authorities had rates below 500 per 100,000.
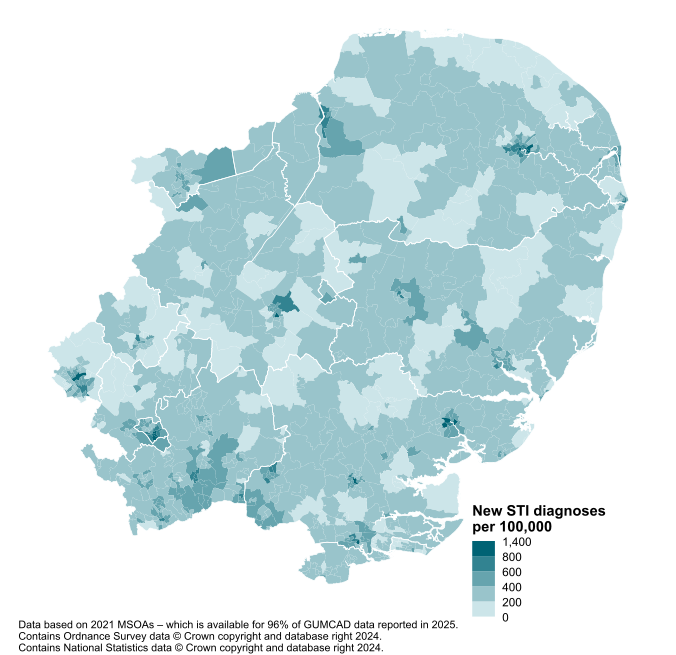
Figure 12. Map of new STI rates per 100,000 by middle super output area (MSOA21), East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 12 is a map of all East of England middle super output areas showing new STI rates per 100,000 residents in 2025. Most areas had rates under 500 per 100,000.
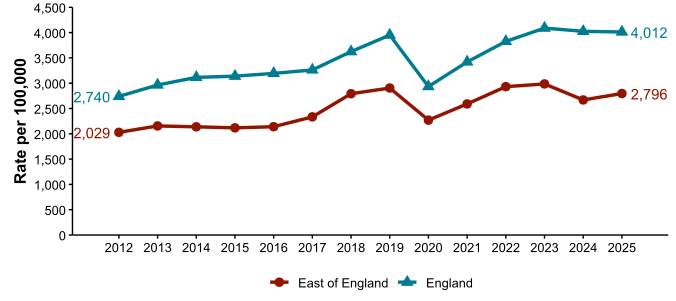
Figure 13. STI testing rate (excluding chlamydia in under 25 year olds [note 6]) per 100,000, East of England, 2012 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Note 6: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 13 shows trend lines for STI testing rate (excluding chlamydia in those aged under 25 years) per 100,000 in East of England residents between 2012 and 2025. The East of England testing rate has been consistently below the England rate. The testing rate in the East of England was higher in 2025 (2,796 per 100,000) compared to 2012 (2,029 per 100,000). After a drop in the testing rate between 2023 and 2024, the rate rose again between 2024 and 2025.
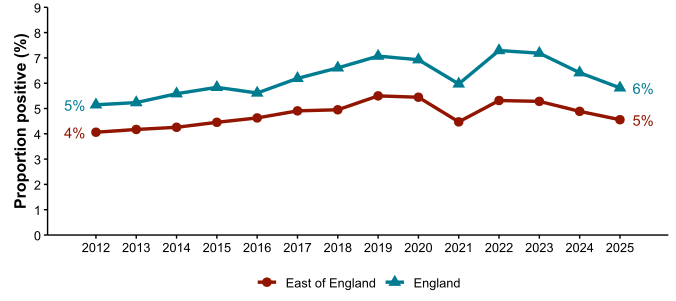
Figure 14. STI testing positivity rate (excluding chlamydia in under-25-year-olds [note 7]), East of England, 2012 to 2025
Data sources: GUMCAD, CTAD.
Note 7: chlamydia diagnoses in the target group for the National Chlamydia Screening Programme (those aged 15 to 24 years) are excluded as these diagnoses may reflect local implementation of screening.
Figure 14 shows trend lines for STI testing positivity rate (excluding chlamydia in those aged under 25 years) in East of England residents between 2012 and 2025. The East of England testing positivity has consistently been below the England rate. The testing positivity was higher in 2025 (5%) compared with 2012 (4%) but has been declining for the past 3 years in line with the England trend.
Table 5. Number of diagnoses of new STIs by UKHSA region of residence, data source and sexual health service type, 2025
| UKHSA region of residence | GUMCAD: specialist SHSs |
GUMCAD: non-specialist SHSs [note 8] |
CTAD | Total |
|---|---|---|---|---|
| East Midlands | 13,724 (61%) |
4,076 (18%) |
4,711 (21%) |
22,511 |
| East of England | 17,420 (68%) |
2,042 (8%) |
6,139 (24%) |
25,601 |
| London | 79,241 (72%) |
10,529 (10%) |
19,826 (18%) |
109,596 |
| North East | 9,111 (70%) |
1,703 (13%) |
2,264 (17%) |
13,078 |
| North West | 31,340 (77%) |
4,738 (12%) |
4,816 (12%) |
40,894 |
| South East | 28,757 (75%) |
1,649 (4%) |
7,914 (21%) |
38,320 |
| South West | 14,333 (64%) |
3,777 (17%) |
4,360 (19%) |
22,470 |
| West Midlands | 20,450 (74%) |
4,133 (15%) |
2,877 (10%) |
27,460 |
| Yorkshire and Humber | 18,720 (72%) |
1,636 (6%) |
5,467 (21%) |
25,823 |
Data sources: GUMCAD, CTAD.
Note 8: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
Table 5 shows the number of diagnoses of new STIs by UKHSA region of residence by source of diagnosis in 2025. Most diagnoses came from specialist sexual health services (17,420 out of 25,601 in the East of England).
Table 6. Number of diagnoses of the 5 main STIs by STI, data source and sexual health service type, East of England, 2025
| 5 main STIs | GUMCAD: specialist SHSs | GUMCAD: non-specialist SHSs [note 9] | CTAD | Total |
|---|---|---|---|---|
| Chlamydia | 5,024 (41%) |
1,021 (8%) |
6,139 (50%) |
12,184 |
| Genital herpes | 2,430 (100%) |
8 (<1%) |
- | 2,438 |
| Genital warts | 2,341 (100%) |
8 (<1%) |
- | 2,349 |
| Gonorrhoea | 2,601 (73%) |
982 (27%) |
- | 3,583 |
| Syphilis | 437 (100%) | 0 (0%) | - | 437 |
Data sources: GUMCAD, CTAD.
Note 9: diagnoses from enhanced GPs reporting to GUMCAD are included in the ‘Non-specialist sexual health services (SHSs)’ total.
Table 6 shows the number of diagnoses of the 5 main STIs in the East of England by source of diagnosis in 2025. Overall, most diagnoses came from specialist sexual health services. CTAD is a surveillance system for chlamydia only and half of diagnoses for chlamydia (6,139) came from this system.
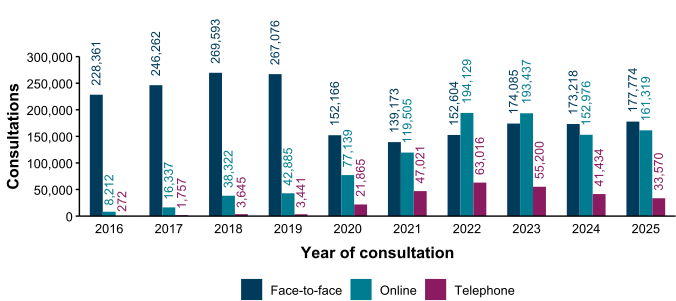
Figure 15. Consultations by service medium, East of England, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Figure 15 is a bar chart showing the number of consultations in East of England residents by type of consultation – either face to face, online or via telephone. Between 2016 and 2019 almost all consultations were face to face. From 2020 there was a shift to more online and telephone consultations. In the most recent year (2025) the highest number of consultations face to face (177,774) closely followed by online (161,319).
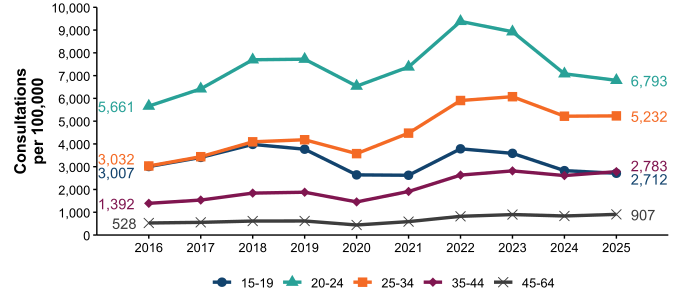
Figure 16. All consultations by age group, East of England, 2016 to 2025
Data sources: GUMCAD, NHS Fingertips.
Figure 16 shows trend lines for all consultations by age group in the East of England between 2016 and 2025. The highest rate per 100,000 of consultations was in the age group 20 to 24 years followed by 25 to 34 years. Between 2016 and 2025 there has been a steady increase in the rate of consultations in those aged 45 to 64 years. The rate of consultations in the youngest age group (15 to 19 years) has declined for 3 years.
Chlamydia
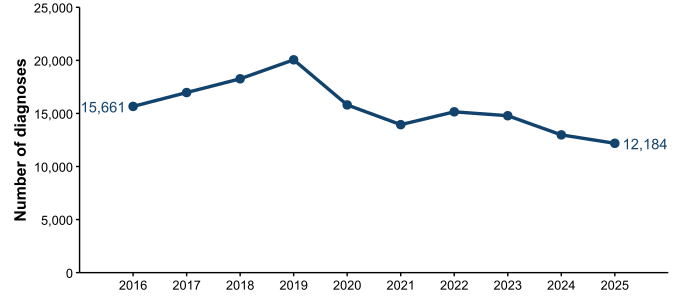
Figure 17. Number of chlamydia diagnoses, East of England, 2016 to 2025
Data sources: GUMCAD, CTAD.
It is important to consider whether there have been any changes to testing practices when interpreting increases or decreases in chlamydia.
Figure 17 shows a trend line of the number of chlamydia diagnoses in the East of England between 2016 and 2025. The number declined over time with 15,661 in 2016 compared to 12,184 in 2025. There was a sharp decline in diagnoses between 2018 and 2020 and a slower decline from 2022 onwards.
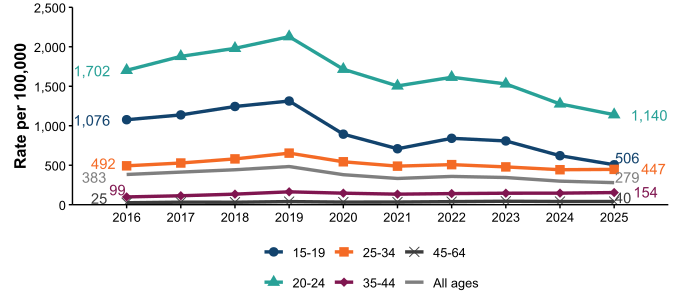
Figure 18. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only), East of England, 2016 to 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 18 shows trend lines for the rate per 100,000 of chlamydia diagnoses by age group in the East of England between 2016 and 2025. Rates decreased during this time in those aged 15 to 19, 20 to 24 and 25 to 34. Rates increased in those aged 35 to 44 and 45 to 64. In 2025, the highest rate of diagnoses was in those aged 20 to 24 (1,140 per 100,000).
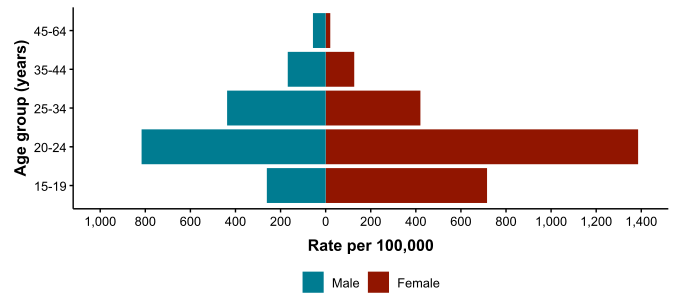
Figure 19. Rates of chlamydia per 100,000 by age group (for those aged 15 to 64 years only) and gender, East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 19 is a bar chart showing that the highest rates of chlamydia in 2025 were in the group aged 20 to 24 years for both males and females, with a higher rate of diagnosis in females. The lowest rates of chlamydia in 2025 were in those aged 45 to 65 years for both males and females.
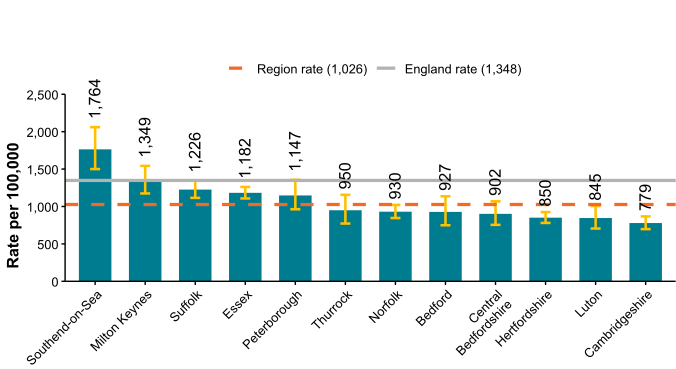
Figure 20. Chlamydia detection rate per 100,000, females aged 15 to 24 years by upper tier local authority of residence, East of England, 2025
Data sources: GUMCAD, CTAD, ONS Census 2021 mid-year estimates.
Figure 20 is a bar chart showing the chlamydia detection rate per 100,000 population aged 15 to 24 years in East of England residents by upper tier local authority of residence in 2025. The highest rate was in Southend-on-Sea (1,764 per 100,000) followed by Milton Keynes (1,349 per 100,000). The lowest rate was in Cambridgeshire (779 per 100,000).
Gonorrhoea
Figure 21. Number of gonorrhoea diagnoses, East of England, 2016 to 2025
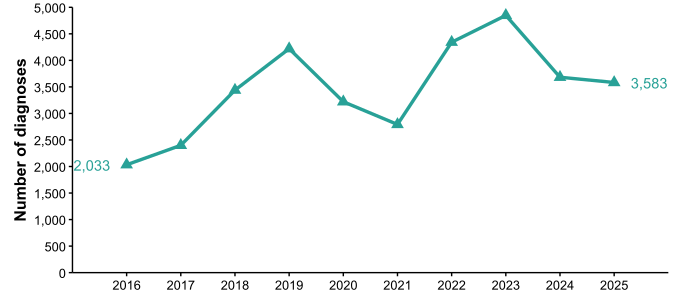
Data source: GUMCAD.
Figure 21 shows a trend line of the number of gonorrhoea diagnoses in the East of England between 2016 and 2025. The number increased over time with 2,033 in 2016 compared to 3,583 in 2025. There has been a decline in diagnoses for the past 2 years.
Figure 22. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only), East of England, 2016 to 2025
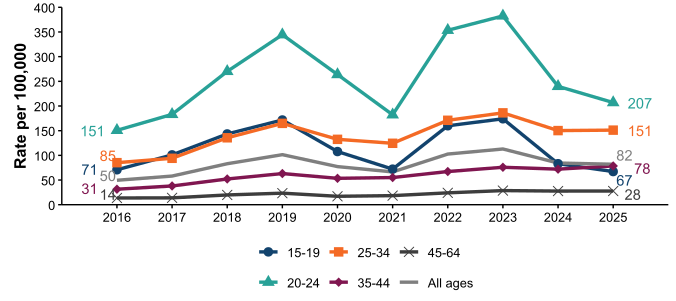
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 22 shows trend lines for the rate per 100,000 of gonorrhoea diagnoses by age group in the East of England between 2016 and 2025. Rates steadily increased between 2016 and 2025 in those aged 45 to 64 years and 35 to 44 years. The highest rate of diagnoses in 2025 was in those aged 20 to 24 years, however this age group has seen a decline in the past 2 years.
Figure 23. Rates of gonorrhoea per 100,000 by age group (for those aged 15 to 64 years only) and gender, East of England, 2025
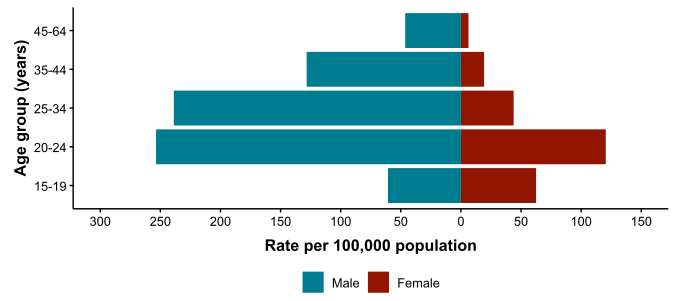
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 23 is a bar chart showing that the highest rates of gonorrhoea in 2025 were in the group aged 20 to 24 years for both males and females. The rates of gonorrhoea are higher in males than females in all age groups apart from those aged 15 to 19 where rates are similar.
Figure 24. Rate of gonorrhoea diagnoses per 100,000 by upper tier local authority, East of England, 2025
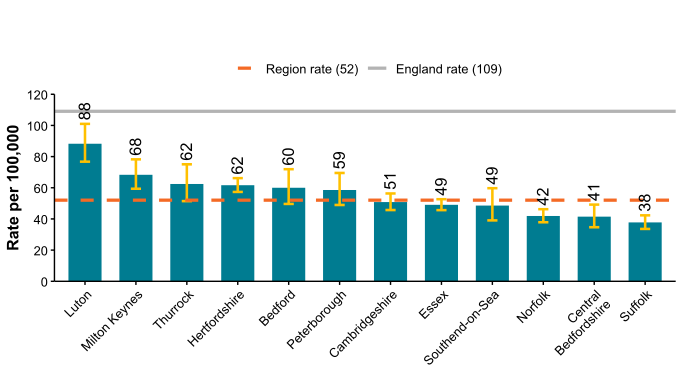
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 24 is a bar chart showing the rate of gonorrhoea diagnoses per 100,000 population in East of England residents by upper tier local authority of residence in 2025. The highest rate was in Luton (88 per 100,000) followed by Milton Keynes (68 per 100,000). The lowest rate was in Suffolk (38 per 100,000).
Genital warts
Figure 25. Number of genital warts diagnoses, East of England, 2016 to 2025
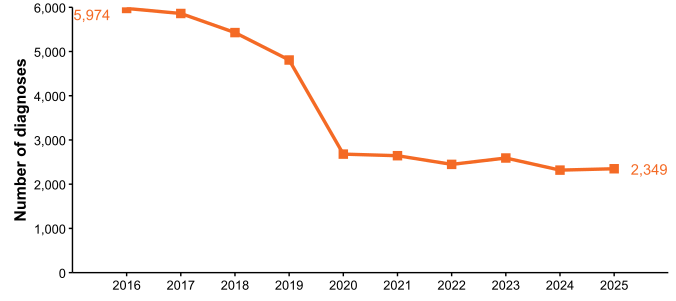
Data sources: GUMCAD.
Figure 25 shows a trend line of the number of genital warts diagnoses in the East of England between 2016 and 2025. The number declined over time with 5,974 in 2016 compared to 2,349 in 2025. There was a steep decline between 2019 and 2020 but since 2020 the decline has been much more gradual.
Figure 26. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only), East of England, 2016 to 2025
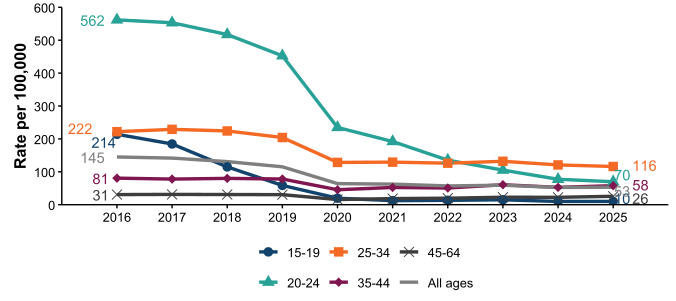
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 26 shows trend lines for the rate per 100,000 genital warts diagnoses by age group in the East of England between 2016 and 2025. Rates decreased during this time across all age groups. The decline in the rate of diagnosis amongst those aged 15 to 19 years and 20 to 24 years was particularly steep. Between 2016 and 2022 the highest rate of diagnoses was in those aged 20 to 24 years, but this changed in the past 2 years to be those aged 25 to 34 years.
Figure 27. Rates of genital warts per 100,000 aged 15 to 19 and 20 to 24 years by gender, East of England, 2016 to 2025
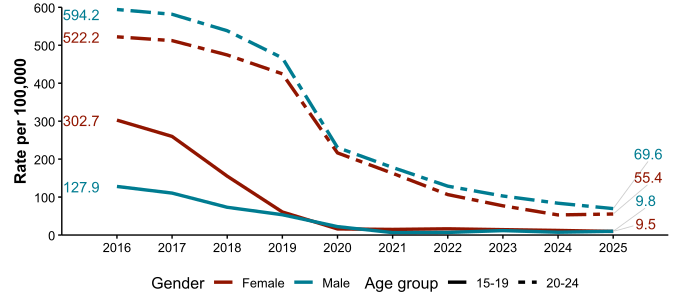
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 27 shows trend lines of the rate per 100,000 genital warts diagnoses in those aged 15 to 19 years and 20 to 24 years by gender in the East of England between 2016 and 2025. The rate of diagnosis decreased during this time across both age groups and genders.
Figure 28. Rates of genital warts per 100,000 by age group (for those aged 15 to 64 years only) and gender, East of England, 2025
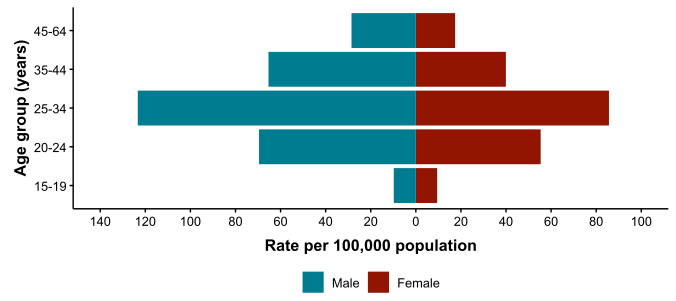
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 28 is a bar chart showing that the highest rates of genital warts in 2025 were in the group aged 25 to 34 years with a higher rate of diagnosis in males. The lowest rates of genital warts in 2025 were in those aged 15 to 19 years for both males and females.
Syphilis
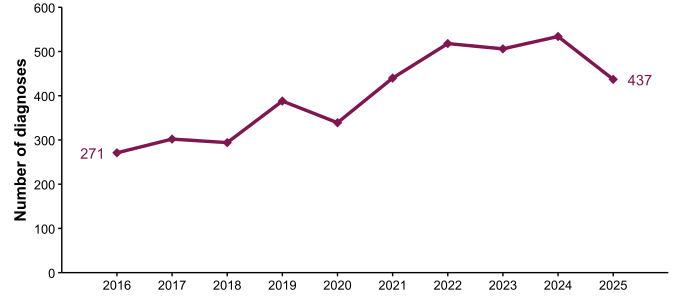
Figure 29. Number of syphilis diagnoses, East of England, 2016 to 2025
Data sources: GUMCAD.
Figure 29 shows a trend line of the number of syphilis diagnoses in the East of England between 2016 and 2025. The number increased over time between 2016 and 2024. However, between 2024 and 2025 there was a decline in diagnoses.
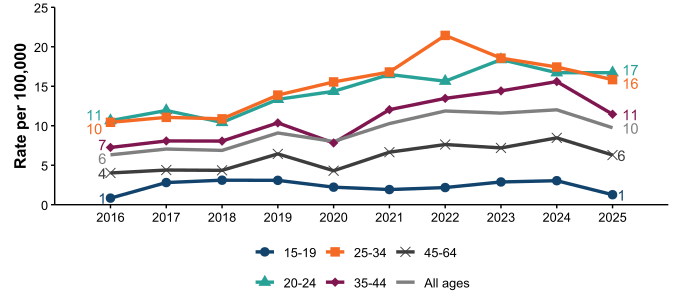
Figure 30. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only), East of England, 2016 to 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 30 shows trend lines for the rate per 100,000 of syphilis diagnoses by age group in the East of England between 2016 and 2025. Rates in all age groups declined between 2024 and 2025 apart from those aged 20 to 24 which were stable. Rates in those aged 15 to 19 years remained very low and stable over time.
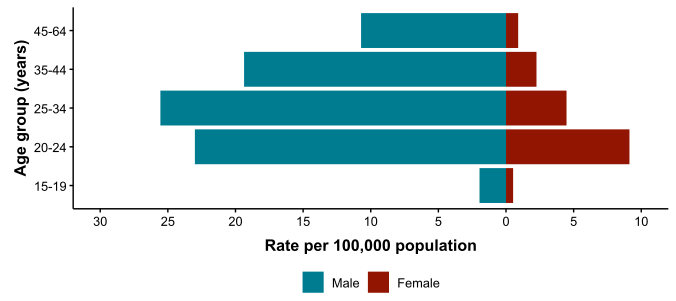
Figure 31. Rates of syphilis per 100,000 by age group (for those aged 15 to 64 years only) and gender, East of England, 2025
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 31 is a bar chart showing that the highest rates of syphilis in 2025 were in the group aged 25 to 34 years for males and 20 to 24 years for females, with a higher rate of diagnosis in males in all age groups. The lowest rates of syphilis in 2025 were in those aged 15 to 19 years for both males and females.
Genital herpes
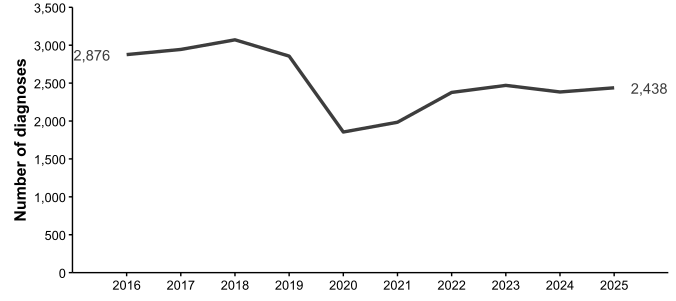
Figure 32. Number of genital herpes diagnoses, East of England, 2016 to 2025
Data source: GUMCAD.
Figure 32 shows a trend line of the number of genital herpes diagnoses in the East of England between 2016 and 2025. The number of diagnoses increased slightly between 2016 and 2018 and then declined to 2020. Since 2020 there has been a steady increase. The number of diagnoses is still lower in 2025 (2,438) than it was in 2016 (2,876).
Figure 33. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only), East of England, 2016 to 2025
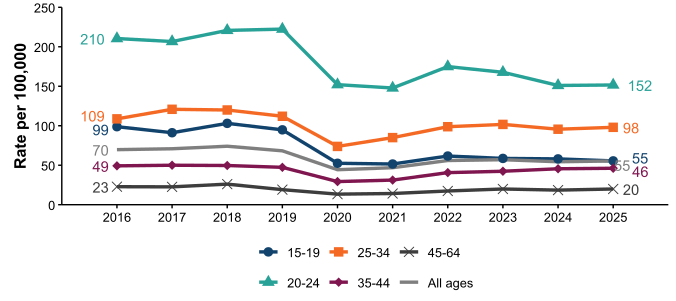
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 33 shows trend lines for the rate per 100,000 of genital herpes diagnoses by age group in the East of England between 2016 and 2025. Between 2024 and 2025, rates increased in those aged 25 to 34 years, 35 to 44 years and 45 to 65 years. The highest rate of diagnoses in 2025 was in those aged 20 to 24 years.
Figure 34. Rates of genital herpes per 100,000 by age group (for those aged 15 to 64 years only) and gender, East of England, 2025
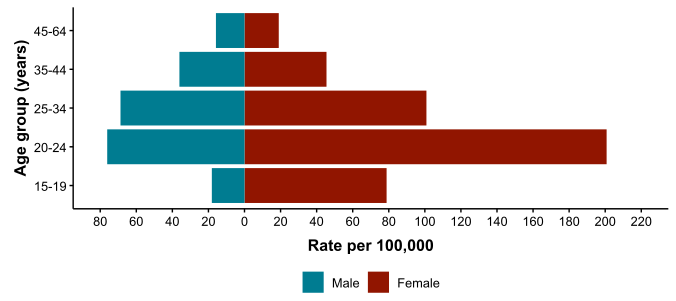
Data sources: GUMCAD, ONS Census 2021 mid-year estimates.
Figure 34 is a bar chart showing that the highest rates of genital herpes in 2025 were in the group aged 20 to 24 years for both males and females, with a higher rate of diagnosis in females. The lowest rates of genital herpes in 2025 were in those aged 45 to 64 years for both males and females.
Data sources
Find more information on local sexual health data sources in the UKHSA guide.
The gender and age group chart is restricted to those aged 15 to 64 years as information about STIs in those aged less than 15 years is considered highly sensitive. Analyses specific to this group are not provided in routine outputs. Rates for those aged 65 or older are withheld to ensure that no deductive disclosure is possible for the under 15 years age group. The proportion of STIs in those aged less than 15 years or older than 64 years is very low.
GUMCAD surveillance system
This disaggregate reporting system collects information about attendances and diagnoses at specialist (Level 3) and non-specialist (Level 2) sexual health services. Information about the patient’s area of residence is collected along with demographic data and other variables. GUMCAD superseded the earlier KC60 system and can provide data from 2009 onwards. GUMCAD is the main source of data for this report.
Due to limits on how much personally identifiable information sexual health clinics are able to share, it is not possible to deduplicate between different clinics. There is a possibility that some patients may be counted more than once if they are diagnosed with the same infection (for infection specific analyses) or a new STI of any type (for new STI analyses) at different clinics during the same calendar year.
CTAD surveillance system
CTAD collects data on all local authority and NHS or NHS-commissioned chlamydia testing carried out in England. CTAD is comprised of all chlamydia (NAATs) tests for all ages (with the exception of conjunctival samples), from all venues and for all reasons. CTAD enables unified, comprehensive reporting of all chlamydia data, to effectively monitor the impact of the NCSP through estimation of the coverage of population screening, proportion of all tests that are positive and detection rates.
For services which report to GUMCAD and for which CTAD does not receive data on the patient’s area of residence (for example, SHSs), information about chlamydia diagnoses is sourced from GUMCAD data.
CTAD does not collect information about sexual orientation or country of birth. Reports from CTAD are excluded from figures in this report which relate to analyses by sexual orientation or world region of birth.
New STIs
New STI diagnoses comprise diagnoses of the following:
- chancroid
- Lymphogranuloma venereum (LGV)
- donovanosis
- chlamydia
- gonorrhoea
- genital herpes (first episode)
- HIV (acute and AIDS defining)
- Molluscum contagiosum
- non-specific genital infection (NSGI)
- non-specific pelvic inflammatory disease (PID) and epididymitis
- chlamydial PID and epididymitis (presented in chlamydia total)
- gonococcal PID and epididymitis (presented in gonorrhoea total)
- scabies
- pediculosis pubis
- syphilis (primary, secondary and early latent)
- trichomoniasis and genital warts (first episode)
- Mycoplasma genitalium
- shigella
Calculations
Confidence intervals were calculated using Byar’s method for numerators >= 10. For small numerators Byar’s method is less accurate and so an exact method based on the Poisson distribution is used.
ONS mid-year population estimates for 2024 were used as a denominator for rates (other than by ethnic group) for 2025. ONS estimates of population by ethnic group for the year 2021 were used as a denominator for rates by ethnic group for 2025. This is the first time that new estimates of population by ethnic group have been available since 2011. This must be considered if comparing rates for 2025 in this report with rates by 2024 in last year’s report, as the rates in the last report used the 2011 estimates.
Interpreting trends
When interpreting trends in the number of STI diagnoses it is important to consider the potential impact of changes to testing, vaccination programmes and the availability of interventions (such as prophylaxis). Specifically, diagnostic testing for gonorrhoea and genital herpes now includes in some areas highly sensitive testing using nucleic acid amplification tests. Additionally, there is some screening of GBMSM at extra-genital sites. Where in place, both will have led to increased case ascertainment of gonorrhoea and genital herpes. Local testing practices for all STIs may vary.
More information
As of 2020, all analyses for this report include data from non-specialist (Level 2) SHSs and enhanced GP services as well as specialist (Level 3) SHSs.
For more information, access the online Sexual and Reproductive Health Profiles.
For more information on HIV data, see the separate HIV Spotlight report.
For more information on local sexual health data sources, see the UKHSA guide.
Local authorities have access to The Summary Profile of Local Authority Sexual Health (SPLASH) Reports (accessible from the Sexual and Reproductive Health Profiles) and the SPLASH supplement reports via the HIV and STI Data exchange.
About the Field Services
The Field Services were established in 2018 as a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Real-time Syndromic Surveillance and Public Health Microbiology to strengthen the surveillance, intelligence and response functions of UKHSA.
You can contact your local FS team at eoe.stihiv@ukhsa.gov.uk
Acknowledgements
We would like to thank the following:
- local SHSs for supplying the SHS data
- local laboratories for supplying the CTAD data
- UKHSA Blood Safety, Hepatitis, Sexually Transmitted Infections (STI) and HIV Division for collection, analysis and distribution of data
Reference
- Sonubi T, Sheik-Mohamud D, Ratna N and others. ‘STI testing, diagnoses and online chlamydia self-sampling among young people during the first year of the COVID-19 pandemic in England’ International Journal of STD & AIDS 2023: volume 34, issue 12, pages 841 to 853