Lead Exposure in Children Surveillance System (LEICSS) annual report, 2026
Updated 22 October 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/lead-exposure-in-children-surveillance-reports-from-2021/lead-exposure-in-children-surveillance-system-leicss-annual-report-2026
Executive summary
Lead Exposure in Children Surveillance System (LEICSS) is a national surveillance system coordinated by the UK Health Security Agency (UKHSA). The system notifies health protection teams (HPTs) of incident cases of elevated blood lead concentration (BLC) in children aged 0 to 15 years in England. These notifications initiate health protection case management and public health interventions aimed at identifying and removing sources of lead exposure.
Following a review of the evidence on the harmful effects of lead exposure in children (1, 2), a UKHSA task and finish group recommended to lower the blood lead public health intervention threshold for England. From 5 July 2021, the case definition for surveillance changed to half the original concentration, from 0.48 μmol/L (equivalent to ≥10 μg/dL) to 0.24 μmol/L (equivalent to ≥5 μg/dL). As expected, this change led to a substantial increase in the number of cases reported to LEICSS.
This report summarises the surveillance of cases from 1 January to 31 December 2025. It also provides an update on surveillance activities, including data collected through Enhanced Surveillance Questionnaires (ESQs) completed by HPTs during case management to gather information on potential risk factors and sources of lead exposure.
Main findings
The main findings of this report are that:
- in 2025, a total of 324 cases were reported to UKHSA, reflecting a 31% increase from the 247 cases recorded in 2024; most cases (296, 91%) were directly notified to LEICSS by participating laboratories, while 28 cases (9%) were notified through other routes, similar to last year
- the median delay between the specimen collection date and the date cases which were entered into the UKHSA Case Incident Management System (CIMS) was 7 days (interquartile range (IQR) 4 to 11 days), slightly shorter than in 2024 (median 10 days, IQR 7 to 15 days); this was an improvement in the timeliness of case reporting and processing
- cases were primarily 5 to 11 years of age (48%), followed closely by children aged 1 to 4 years (46%); nearly half of the cases (48%) reside in the most deprived areas (IMD quintile 5). The median blood lead concentration of laboratory-detected cases was 0.37 μmol/L (7.66 µg/dL), similar to that reported in 2024
- according to statistics from several international population surveys, we believe that the number of cases reported to LEICSS is significantly lower than the estimated incidence of lead exposure in children in England (3 to 6)
- in 2025, the detection rate for children aged 0 to 15 in England was 30 cases per million, although there were large regional variations; the highest reporting rates were from Yorkshire and the Humber region (94 cases per million), and the lowest in the North East region (6 cases per million)
- in 2025, the most commonly reported lead exposures (based on ESQ 183 cases) were from soil (53%), paint (36%) and drinking water pipes (11%); other reported sources of exposure included: a parent or guardian’s occupation (6%); imported utensils, ceramic pottery and pewter (5%); imported spices and food (5%); and traditional medicines and herbal remedies (1%)
- in 2025, of the 183 cases with completed ESQs, 86% (158) reported pica behaviours and 78% (142) reported learning difficulties
Main messages and recommendations
Lead is a heavy metal contaminant that persists in the environment and can be harmful to the body, even at low concentrations in the blood. There is no known safe level of lead exposure. Children who exhibit pica (see note 1) or engage in hand-to-mouth behaviours in environments containing lead hazards are at the greatest risk of exposure.
Clinicians must be aware of the risk associated with lead exposure in children. It is important that they understand the main sources of lead exposure, identify children at increased risk, and recognise the signs and symptoms of exposure. For additional information on resources for public health professionals and clinicians, see the Resources section of this report.
Cases that meet the case definition (children aged under 16 years with a BLC ≥5 µg/dL equivalent to ≥0.24 µmol/L) must be notified to UKHSA Health Protection Teams for public health case management. Additional notification requirements are detailed in the Case Reporting to LEICSS section of this report.
Background
Lead exposure has been recognised as a public health concern for centuries. A recent study discussed the mining and smelting activities that occurred during the Roman era, which released substantial quantities of lead into the atmosphere, resulting in widespread environmental contamination across Europe. These emissions are thought to have increased blood lead concentrations in exposed populations and may have contributed to cognitive decline and broader public health impacts throughout the Roman Empire (7).
There is no defined safe threshold for the harmful effects of lead in children. Environmental lead exposure remains a significant public health challenge globally (8, 9) and can result in severe multi-system toxicity (1). The manifestation of this toxicity depends on both the BLCs and the rate at which lead accumulates in the body. Overt manifestations of toxicity (that is, lead poisoning), such as anaemia or abdominal pain, are often associated with higher BLC (for instance >1.93 μmol/L (>30 µg/dL) (see note 3) (2, 10). However, adverse health effects can occur at much lower BLCs, even in the absence of obvious clinical symptoms. Low BLCs have been associated with decreased intelligence in children, behavioural difficulties, and learning problems (11). Recent evidence continues to demonstrate adverse impacts on cognitive development, attention, behaviour and educational attainment as well as effects on the central nervous and cardiovascular systems at below historical intervention thresholds (12 to 15). A recent global modelling study estimated that lead exposure results in the loss of approximately 765 million IQ points among children younger than five years globally, highlighting the substantial public health burden associated with lead exposure (16). The Global Burden of Disease Study estimated that lead exposure was responsible for 3.5 million deaths and 71.6 million disability-adjusted life years (DALYs) globally in 2023, primarily through cardiovascular disease. Lead was estimated to be the eighth leading risk factor for global mortality and the second leading environmental risk factor, highlighting its substantial contribution to the global burden of disease (17).
An estimated 1 in 3 children (up to 800 million globally) have a BLC at or above 0.24 µmol/L (5 µg/dL), the threshold at which many nations recommend clinical or public health action (5). Lead remains one of the most significant environmental toxicants worldwide, particularly affecting children in low- and middle-income countries (18). However, there is currently no data available regarding the number of children in England who are exposed to lead resulting in concentrations above this threshold. In comparable high-income countries, such as the United States of America and France, national screening programmes have been established to screen children aged 1 to 5 years (commonly targeting children identified as being at higher risk of lead exposure) and identify those with elevated BLCs (19, 20). In 2018, the UK National Screening Committee reviewed the evidence to assess the need for population screening (21). They did not recommend the introduction of a systematic population screening programme due to concerns about testing and treatment, as well as the lack of population prevalence data demonstrating that lead exposure is a significant public health concern in the UK.
Survey data from comparable high-income countries can be used (after considering population differences) to estimate the prevalence of elevated BLC in England. A survey conducted in France from 2008 to 2009 (see note 2) estimated that 1.5% of children aged 1 to 6 years had a BLC ≥ 0.24 µmol/L (≥5 µg/dL). In the USA, according to the National Surveillance Data, 1.1% of the children aged 1 to 5 years had a BLC ≥0.24 µmol/L (≥5 µg/dL). Applying this to the population of children aged under 6 years in England in 2025 (based on ONS 2024 Census data) (22, 23), it is estimated that approximately 48,388 children may have BLCs above the intervention threshold. Estimates from the Institute of Health Metrics and Evaluation (IHME) (5), using the Global Burden of Disease tools, suggest that in the UK there may be as many as 213,702 (95% CI 186,000 to 281,500) children aged 0 to 19 years with a BLC of ≥0.24 µmol/L (≥5 µg/dL), and 29,036 (95% CI 25,000 to 42,500) children with a BLC ≥0.48 µmol/L (≥10 µg/dL). Most recent IHME Global Burden of Disease 2023 estimates indicate that 168,378 children aged 0 to 19 years in the United Kingdom might have blood lead concentrations above 5 µg/dL (24).
Globally, primary prevention measures such as reducing the use of lead in paints and fuels, programmes and advice for the removal of leaded drinking water pipes, remediating lead in soil, and controlling industrial emissions have successfully reduced lead in the environment. As a result, exposure to lead has lowered, which has contributed to a demonstrated reduction in BLCs in children, for instance in the United States of America (4, 25). However, lead remains a persistent contaminant, and children continue to be exposed to lead in the environment through historical remnants. Since the removal of lead from road vehicle petrol, ingestion rather than inhalation has become the most common route of exposure in high-income countries, particularly through dust, soil and flakes of leaded paint (10). Lead-based paint was widely used in the UK before its gradual withdrawal from the 1960s (26) and was mostly banned from sale in 1992.
Cases of lead exposure are identified through blood testing. As the signs and symptoms of lead exposure are often non-specific, they can often be overlooked or misdiagnosed in clinical settings. Effective case detection therefore depends on clinicians maintaining a high level of clinical suspicion for lead poisoning symptoms as well as following clinical guidance for the management of pica and other risk factors of lead exposure. This requires a broad understanding of the child’s physical and behavioural development, socioeconomic background, and home and housing conditions to identify factors that may increase the risk of lead exposure. Surveillance of cases identified by clinicians provides valuable information to support public health case management and inform preventive action. Blood lead concentrations primarily reflect recent exposure, with a half-life of approximately 20 to 40 days, while around 70% of the lead body burden in children is stored in bone, where it may persist for 10 to 30 years. Lead stored in bone can be remobilised into the bloodstream over time, meaning that elevated BLC may persist after exposure has ceased and may complicate interpretation of the interval between exposure, testing and follow-up measurements (27).
In 2021, the United States Centers for Disease Control and Prevention (CDC) lowered their intervention level for BLC from 0.24 µmol/L (5 µg/dL) to 0.17 µmol/L (3.5 µg/dL) (28). In England, the case definition for elevated BLC in children under 16 years was also halved from 0.48 µmol/L (10 µg/dL) to 0.24 µmol/L (5 µg/dL) in July 2021. This change allows more children with elevated BLCs to receive the necessary public health case management and intervention. While there is no defined UK threshold for the harmful effects of lead in children, a BLC of ≥0.1 μmol/L (≥2 μg/dL) to <0.24 μmol/L (<5 μg/dL) is now widely accepted as the clinical threshold above which investigation should occur and a source should be identified. At ≥0.24 μmol/L (≥5 μg/dL) UKHSA should be informed, and clinical and environmental monitoring should be initiated with systematic identification of potential sources, identification of other vulnerable individuals, and further monitoring (29).
The primary approach to managing lead exposure is the timely removal, reduction or access to the source of exposure. Additionally, symptomatic children and those with a BLC greater than 2.4 μmol/L (> 50 µg/dL) may require chelation therapy (10). Evidence from LEICSS indicates that in England, lead exposure can occur through a range of sources and pathways. These include lead-contaminated paint, water, soil or dust, herbal medicine preparations, contaminated food and spices, and consumer products that fail to meet safety regulations, such as painted toys, makeup, and lead crystal glassware. Between 2014 and 2022, paint and soil were the most frequently reported sources of lead exposure for children in England (30). Children may have experienced secondary exposure from parental occupations or hobbies involving lead, where contaminated dust is brought into the home on their clothes, shoes and vehicles (10, 31). A recent study (32) found that living in terraced houses and in properties built before the 1970s were key risk factors for elevated BLCs among children in England.
Children with learning and developmental disorders are at increased risk of lead exposure because they are more likely to engage in hand-to-mouth behaviours or exhibit pica, resulting in the ingestion of non-food items that may contain lead, such as paint flakes or soil (33). Additionally, children already exposed to lead, even at very low concentrations, have reduced learning capacity and increased prevalence of developmental disorders (12, 13, 34, 35). Iron deficiency may further increase susceptibility to lead toxicity and is also associated with pica behaviour (36).
The Lead Exposure in Children Surveillance System (LEICSS)
UKHSA coordinates LEICSS, a national surveillance system for children residing in England. Formal surveillance of lead exposure in children in England began in 2010 with the Surveillance of elevated blood Lead in Children (SLiC) study, a collaborative research project involving the British Paediatric Surveillance Unit and the Health Protection Agency (the forebear to PHE, now UKHSA). The authors of the SLiC study recommended the establishment of a laboratory-based surveillance system to facilitate timely public health management of cases of lead poisoning in children (37). Therefore, a pilot system, known as the Lead Poisoning in Children (LPIC) surveillance system, was instigated in 2014. Following a successful evaluation, the system was permanently implemented as LEICSS in 2016. In December 2021, LEICSS was integrated into a UKHSA Lead Exposure, Public Health Intervention and Surveillance group (LEPHIS) to recognise the broader aims of preventing lead exposure in children, in addition to the rapid recognition of cases of lead poisoning.
LEICSS aims are:
- To facilitate timely public health action for individual cases, as the mainstay of treatment for cases of lead exposure is rapid removal of the putative source of exposure.
- To meet population level surveillance objectives, to inform public health action that reduces the incidence of lead exposure in children in England, such as identification of geographic areas or populations at risk, and identification of current and emerging sources of exposure.
The aims and development of LEPHIS are overseen by a cross-departmental working group within UKHSA and an external steering group with additional representatives from participating laboratories, academia, NHS clinical toxicology, and patient representative groups (for example, the Lead Exposure and Poisoning Prevention Alliance). For the complete list of members, please refer to the Steering and Working Group Members section at the end of this report.
The data collected from LEICSS feeds into the Environmental Public Health Surveillance System (EPHSS) for England, operated by UKHSA as part of the Environmental Public Health Tracking programme (EPHSS) and the steering group and working group report to the UKHSA Environmental Public Health Tracking Board. LEICSS data are also available through the UKHSA data dashboard: lead exposure in children.
Case reporting to LEICSS
LEICSS is a passive surveillance system that integrates reports of incident (newly detected) cases of lead exposure notified to UKHSA from a variety of sources.
Since 5 July 2021, a case is defined as a child:
- with a blood lead concentration ≥0.24 μmol/L (equivalent to ≥5 μg/dL), as detected in a UK Accreditation Service (UKAS) accredited biochemistry or toxicology laboratory
- reported to UKHSA for public health intervention
- aged under 16 years at the time of first reporting of elevated blood lead concentration
- resident in England
The surveillance system collates cases reported through the following routes:
- Direct notification to LEICSS from a UK Accreditation Service (UKAS) accredited testing biochemistry or toxicology laboratory.
- Notification to a local UKHSA Health Protection Team (HPT) from a non-UKHSA source (for example, the managing clinician or an environmental health officer) (see note 4) and recorded on the Case Incident Management System (CIMS).
- Notification to another UKHSA Directorate (for example, the Radiation, Chemical, Climate and Environmental Hazards (RCCE) Directorate) and then referred to an HPT for investigation and management.
Case notification to UKHSA is voluntary but encouraged for efficient case management and surveillance purposes.
Direct reporting to LEICSS from biochemistry and toxicology laboratories
A group of highly specialised diagnostic laboratories, known as the Supra- Regional Assay Service (SAS) Trace Elements network, serve as a referral network for specialised laboratory investigations in the UK. BLC is measured at six SAS Trace Elements laboratories in England, which are estimated to conduct most testing nationwide. All six SAS laboratories participate in the LEICSS program, and a partnership has been established with the SAS-associate laboratory in Wales (Cardiff Toxicology Laboratory) to notify LEICSS of England residents whose BLC may be determined in Cardiff. Additionally, other non-SAS laboratories that are UKAS accredited have also agreed to report cases to LEICSS; these laboratories are typically located in larger NHS Trusts or operate as private entities. A list of all contributing laboratories is included in the Acknowledgements section of this report.
Cases reported through a laboratory that meet the case definition are referred to as ‘laboratory-detected’ cases. LEICSS surveillance staff enter case details into the CIMS upon receiving a notification and alert the relevant local HPT to initiate investigation and case management. This route of notification to the investigating HPT is more timely than waiting for notification from other sources involved in treating the case, for example, the managing clinician.
Health protection team notified cases
HPT cases are those that are or were:
- notified directly to a health protection team in England for public health management and classified on the HPT case management system as ‘toxic exposure to lead’
- aged under 16 years at the time of notification to the health protection team
- resident in England
- not initially notified to LEICSS by a participating biochemistry/toxicology laboratory
Blood lead concentration data for cases notified by non-laboratory sources is not routinely recorded in the HPT CIMS in a way that facilitates easy extraction for analysis by LEICSS. Thus, an HPT notified case may potentially have a BLC <5µg/dL (<0.24 µmol/L) or may have missing BLC data.
UKHSA notified cases
Occasionally, cases are initially identified by other departments (such as RCCE) before notification to the HPT. For example, this may occur as a result of a wider exposure incident with the investigation led by RCCE. These cases are also entered into the HPT case management system and can be extracted in the same way as HPT notified cases.
Public health management of cases
Once notified to a local HPT, lead exposure cases are assigned to a lead clinician who uses UKHSA national guidance to manage the case(s) (38). The actions undertaken depend on the initial BLC reported. In general, public health management is aimed at identifying the source of the lead and mitigating it effectively. This is done by supporting the family of the case, in collaboration with their clinical team, and other relevant stakeholders like UKHSA’s Environmental Hazards and Emergencies department, local authority Environmental Health and Public Health and Housing departments.
Surveillance data for 2025
This section provides a summary of cases of lead exposure in children residing in England that were reported to HPTs between 1 January and 31 December 2025. Where relevant, 2025 metrics are compared with 2015 to 2024 data and the corresponding 10-year average, based on cases reported in each of those years.
Figures are correct at the time of publication but may be subject to change as new information about cases becomes available.
This report, and previous years’ annual reports since 2021 are available at Lead exposure in children: surveillance reports.
For reports published before 2021 Lead Exposure in Children Surveillance System: Surveillance Reports published before 2021
Number of incident cases
In 2025, a total of 364 reports of elevated BLC in children were notified to LEICSS. Of these, 324 (89%) met the case definition (reports of BLC <0.24 μmol/L are not included) (see note 5). Figure 1 shows the number of cases reported each year since 2015. In 2025, the number of cases increased by 31% compared with 2024. It should be noted that a small number of cases may represent repeat notifications of children previously reported to LEICSS. If a case has been closed and a further notification is received more than one year later, it may be recorded as a new case, as this may be indicative of a new lead exposure.
Ninety-one percent of cases were direct laboratory reports to LEICSS, with 9% through other reporting routes (for instance direct to HPTs) (Table 1). This is higher compared to previous years, where 82% of cases were directly reported by laboratories, but it was similar to that observed in 2024.
Table 1. Count and percentage of LEICSS cases, England 2025, compared to 2015 to 2024
| Route of detection by LEICSS | Count of cases 2025 (% of total) | Count of cases 2015 to 2024 (% of total) |
|---|---|---|
| Direct laboratory reports | 296 (91) | 832 (82) |
| Other Routes | 28 (9) | 184 (18) |
| Total | 324 | 1,016 |
Figure 1. Count of LEICSS cases per year (England): 2015 to 2025
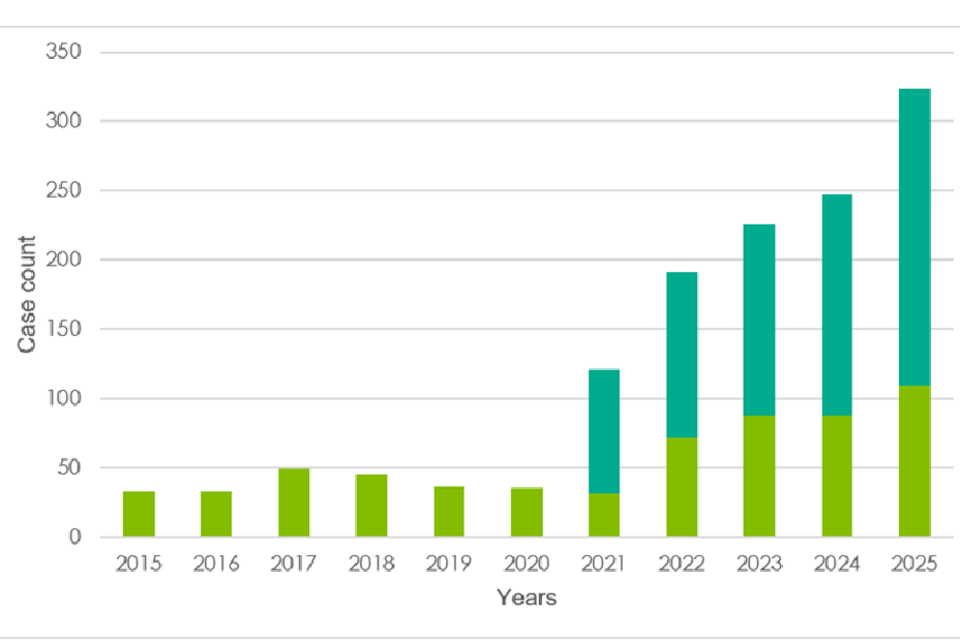
Note 1: dark green represents cases with BLCs ≥0.24 to <0.48 µmol/L, and light green represents cases with BLCs ≥0.48 µmol/L.
Note 2: data for 2015 to 2021 include some cases that do not meet the case definition criteria.
Timeliness of reporting of laboratory-detected cases to LEICSS and notification to Health Protection Teams
For laboratory-reported cases, the median delay between the date of specimen collection and the case reporting data entered onto CIMS (as a proxy for the date of report to HPTs) was 7 days, with a wide interquartile range (IQR) of 4 to 11 days. This is slightly lower than the reported average for previous years (11 days; IQR 8 to 18). These findings indicate a modest improvement in the timeliness of case reporting and processing (Table 2).
Table 2. Time between specimen collection to case entry on to CIMS (for case management) for laboratory-detected LEICSS cases (England): 2015 to 2025
| Year | Direct lab-detected cases | Cases with valid data [note 1] (%) | Median days delay | IQR [note 2] |
|---|---|---|---|---|
| 2025 | 296 | 286 (97) | 7 | 4 to 11 |
| 2024 | 223 | 221 (99) | 10 | 7 to 15 |
| 2023 | 177 | 166 (94) | 11 | 6 to 17 |
| 2022 | 160 | 159 (99) | 17 | 10 to 32 |
| 2021 [note 3] | 86 | 80 (93) | 11 | 8 to 15 |
| 2020 [note 4] | 21 | 20 (99) | 17.5 | 10 to 30 |
| 2019 | 30 | 28 (93) | 8 | 7 to 14 |
| 2018 | 34 | 31 (91) | 8 | 6 to 13 |
| 2015 to 2017 | 91 | 82 (90) | 9 | 7 to 14 |
Note 1: cases where both a valid specimen date and a valid date of entry onto CIMS were extracted from CIMS.
Note 2: IQR = Interquartile range.
Note 3: case definition changed.
Note 4: during the COVID-19 year, HPTs experienced significantly reduced capacity due to their involvement in responding to Covid related incidents.
Occurrence and trends of cases of lead exposure in children
Count and detection rate (by LEICSS) of cases by regions and year
Similar to recent years, in 2025 there was a further increase in LEICSS cases reported compared to the previous year. Since the change in case definition in 2021, the annual number of reported cases increased by 58% in 2022 compared with 2021,18% in 2023 compared with 2022, 9% increase in 2024 compared to 2023 and 31% in 2025 compared with 2024 (Figure 2 and Table 3).
The detection rate of LEICSS cases increased from 23 per million children in 2024 to 29 per million in 2025. The highest reporting rate continued to be in the Yorkshire and the Humber region (94 per million children), remaining substantially higher than all other regions, but no increase in cases compared to 2024 was noted. The North West experienced the largest absolute increase in case reporting, with the detection rate rising from 19 cases per million in 2024 to 48 cases per million in 2025 (Figure 2). The percentage increases from 2024 to 2025 were noticeably high in East Midlands (9 to 25 per million (187%)) and East of England (7 to 18 per million (175%)), where reporting rates more than doubled (Table 3). The lowest detection rates in 2025 were observed in the North East (6 per million) and South East (14 per million). Overall, detection rates increased across most regions in 2025, despite substantial geographical variations. (Table 3).
Figure 2. Detection rate of LEICSS cases (per million) per regional population of 0 to 15 year old children, 2015 to 2025, England
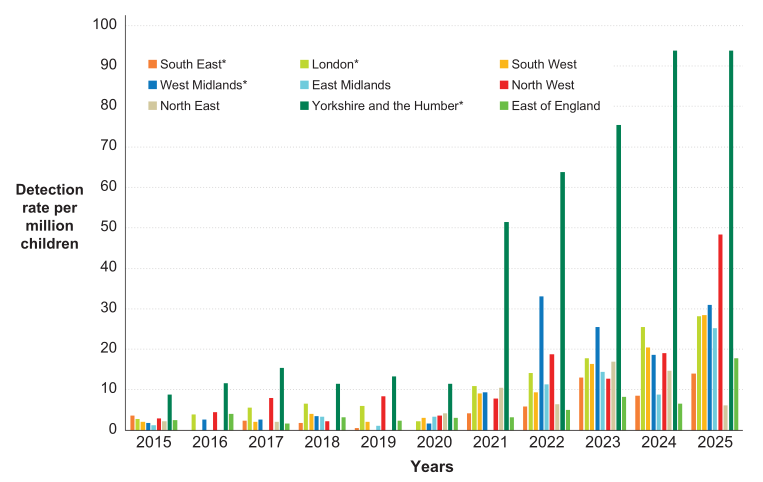
The asterisk (*) denotes centres where an SAS laboratory that participates in the surveillance system is situated; 2024 mid-year population estimate (MYE) was used as the denominator for 2025 cases (23).
Table 3. Count (and % of total) of LEICSS cases, percentage change from 2024 to 2025, and average detection rate [note 2] of cases (per million of 0 to 15-year-old children) by region and year of notification, England 2015 to 2025
| Region | Cases 2015 to 2020 (%) | Cases 2021 (%) | Cases 2022 (%) | Cases 2023 (%) | Cases 2024 (%) | Cases 2025 (%) | Cases 2015 to 2025 (%) | % change in cases from 2024 to 2025 | Average detection rate [note 3] of cases (per million per year) 2015 to 2025 |
|---|---|---|---|---|---|---|---|---|---|
| South East [note 1] | 14 (6) | 7 (6) |
10 (5) | 23 (10) | 15 (6) | 25 (8) | 94 (7) | 67% | 4.9 |
| London [note 1] | 49 (21) | 20 (17) | 24 (12) | 30 (13) | 43 (18) | 48 (15) | 214 (16) | 12% | 11.0 |
| South West | 13 (6) | 9 (7) | 9 (5) | 16 (7) | 20 (8) | 28 (9) | 95 (7) | 40% | 8.8 |
| West Midlands [note 1] | 14 (6) | 11 (9) | 38 (20) | 30 (13) | 22 (9) | 37 (11) | 152 (11) | 68% | 11.9 |
| East Midlands | 8 (3) | 0 (0) | 10 (5) | 13 (6) | 8 (3) | 23 (7) | 62 (5) | 187% | 6.3 |
| North West | 33 (14) | 11 (9) | 26 (14) | 18 (8) | 27 (11) | 34 (10) | 149 (11) | 26% | 10.1 |
| North East | Fewer than 5 | Fewer than 5 | Fewer than 5 | 8 (4) | 7 (3) |
9 (3) | 36 (3) | 29% | 5.8 |
| Yorkshire and the Humber [note 1] | 75 (33) | 54 (45) | 65 (34) | 78 (35) | 97 (39) | 98 (30) | 467 (35) | 1% | 41.0 |
| East of England | 21 (9) | Fewer than 5 | 6 (3) | 10 (4) | 8 (3) | 22 (7) | 71 (5) | 175% | 5.2 |
| England | 231 | 121 | 191 | 226 | 247 | 324 | 1,340 | 31% | 11.4 |
Note 1: centres where participating SAS laboratories are situated.
Note 2: should not be interpreted as an estimate of incidence – see the ‘Case detection rate and ascertainment’ section of this report.
Note 3: the numerator for this indicator is incident cases from 2015 to 2025, and the denominator is the ONS mid-year estimate of the 0 to 15 year old population from 2015 to 2025. Cases allocated to UK region according to postcode of residence.
Figure 3. Average detection rate [note 1] of LEICSS cases (per million 0 to 15 year-old children) by region, England 2015 to 2025 [note2]
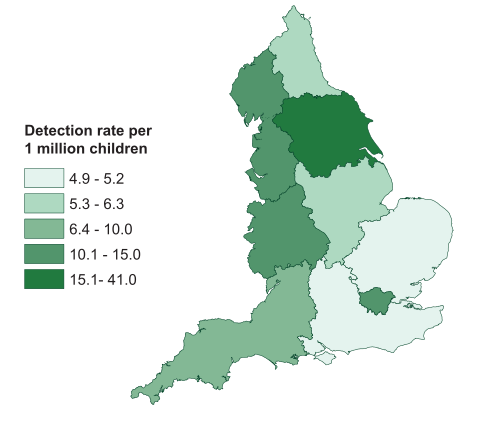
Note 1: should not be interpreted as an estimate of incidence – see ‘The case detection rate and ascertainment’ section below.
Note 2: from 2025 onwards, the England map uses ONS regional boundaries rather than UKHSA regional boundaries. This does not affect the regional assignment of LEICSS cases.
Case detection rate and ascertainment
Due to the lack of overt clinical symptoms at lower BLCs (gastrointestinal symptoms are more common above 20 μg/dL and increased risks of neuropathy and renal failure are associated with levels above 40 μg/dL) (10), surveillance of clinically reported cases will underestimate the total number of affected children. International population biomonitoring surveys, which provide a direct measure of lead exposure in children, suggest that the actual cases of paediatric lead exposure are considerably higher than those identified by the LEICSS (3 to 5, 39). Therefore, the figures above should not be considered representative of the incidence of child lead exposure in England.
The marked regional variation observed in LEICSS data is likely due to bias in case ascertainment rather than a true reflection of regional differences in incidence or prevalence rates. The Leeds SAS laboratory (located in Yorkshire and Humber) actively encourages clinicians to test children for lead exposure when they are assessed for iron deficiency and when the child is also known to have pica behaviours (40). This practice has contributed to a 90% increase in testing and case reporting in the year following its implementation and reporting rates have remained significantly higher than other regions since then. This laboratory also actively involves local clinicians, demonstrating that raising awareness and testing frequency have a significant impact on case detection by the surveillance system. Although it is expected that SAS laboratories carry out the majority of BLC tests in children in England, other laboratories also carry out blood lead testing and may not report directly to LEICSS. This contributes to variable case ascertainment, although these cases may be reported to UKHSA via other routes.
Use of ONS regional boundaries
From 2025 onwards, regional map of England (Figure 3) is presented using ONS regional boundaries rather than UKHSA regional boundaries. This change relates only to the geographical boundaries displayed and does not affect the UKHSA region assignment of cases reported to LEICSS.
Count and detection rate of cases by gender and age
In 2025, Table 4 shows that a higher proportion of cases were male (n=212, 66%), than in 2024 (n=143, 58%) and this was observed across all age groups (Figure 5). This gender disparity is reflected in the literature and may indicate a predisposition to specific high-risk behaviours in males or a higher risk/prevalence of comorbidities in young males. This heightened risk of lead exposure may be linked to conditions like autism (associated with pica) (41) being more prevalent in males than females, with a ratio of 3:1 (42).
The age distribution of cases in 2025 differed from that observed during 2015 to 2024. Children aged 5 to 11 years accounted for the largest proportion of cases (48%, n=157) followed closely by children aged 1 to 4 years (46%, n=148) (Table 4 and Figure 4). This represents a change from 2024, when children aged 1 to 4 years accounted for most cases (64%), while children aged 5 to 11 years accounted for 29%. Historically, most cases were among children aged 1 to 4 years, who accounted for 66% (673) of cases reported between 2015 and 2024. Additionally, fewer cases were reported between 5 and 11 years (26%), while only 4% were reported in each of the youngest, and the oldest, age groups.
Lead exposure in children primarily occurs through the ingestion of substances containing lead, particularly from deteriorating lead paint. The high percentage of cases in preschool-aged children may reflect their increased vulnerability to lead exposure due to mouthing behaviours (4). Additionally, developmental delays and learning difficulties are often more noticeable in this age group, and symptoms of autism may be more apparent, which could result in more clinical investigations for these children. The increase of cases among children aged 5 to 11 years in 2025 may indicate changes in exposure patterns or case ascertainment.
Table 4. Count and percentage of LEICSS cases by age group and sex in England, 2025, and 2015 to 2024
| Age group [note 1] | Male (n,%) 2025 | Female (n,%) 2025 | Unknown [note 2] (n,%) 2025 |
Male (n,%) 2015 to 2024 | Female (n,%) 2015 to 2024 |
Unknown [note 2] (n,%) 2015 to 2024 |
Cases (n,%) 2025 | Cases (n,%) 2015 to 2024 |
|---|---|---|---|---|---|---|---|---|
| Under 1 year | Fewer than 5 | 0 (0) |
0 (0) |
20 (3) |
22 (6) |
Fewer than 5 | Fewer than 5 | 43 (4) |
| 1 to 4 years | 89 (42) |
59 (54) |
0 (0) |
408 (64) |
251 (72) |
14 (59) |
148 (46) |
673 (66) |
| 5 to 11 years | 110 (51) |
46 (41) |
Fewer than 5 | 187 (29) |
67 (19) |
8 (33) |
157 (48) |
262 (26) |
| 12 to 15 years | 12 (6) |
6 (5) |
0 (0) |
25 (4) |
11 (3) |
Fewer than 5 | 18 (5) |
37 (4) |
| Total | 212 | 111 | 1 | 640 | 351 | 24 | 324 | 1,015 |
Note 1: age of child at date of entry onto CIMS.
Note 2: the extracted data had missing gender details.
Figure 4. Age distribution of LEICSS cases in 2025 compared with the age distribution of cases reported during 2015 to 2024
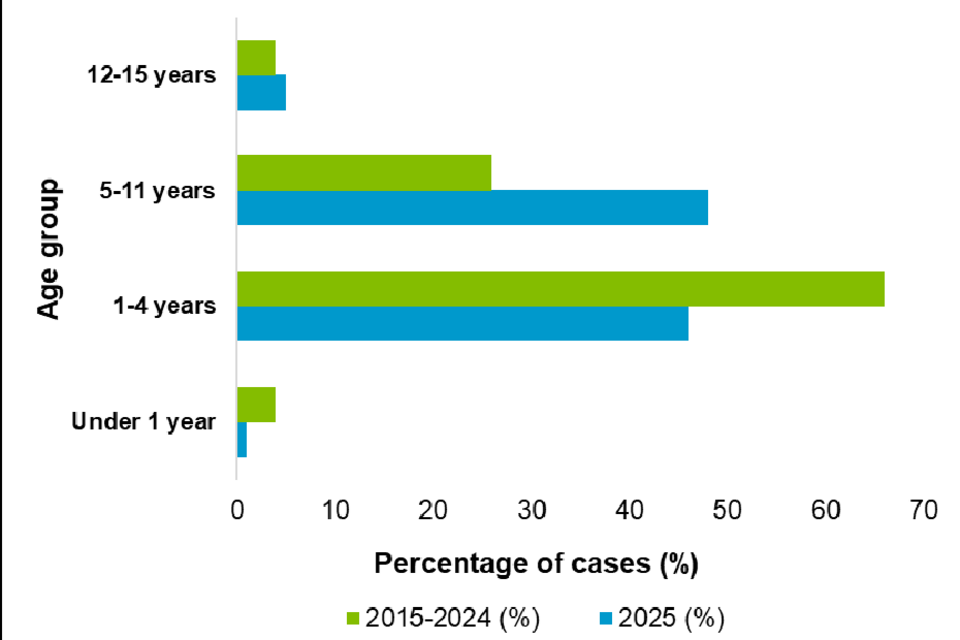
Figure 5. Average case age and gender-specific detection rate† per million of 0 to 15 year old children per year, England 2015 to 2025
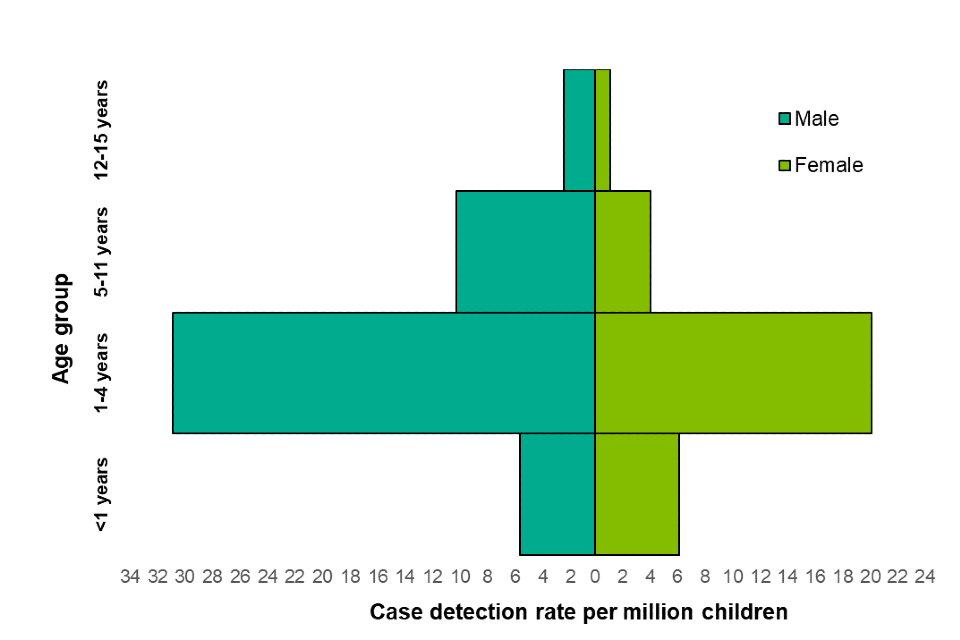
Figure 5 should not be interpreted as an estimate of incidence – see the ‘Case detection rate and ascertainment’ section, above.
Percentage of cases by index of multiple deprivation (IMD) quintile
The IMD provides a measure of deprivation across seven domains (see note 6), summarised at the area level. In 2025, 67% of the cases with residential postcode were from areas classified within the two most deprived IMD quintiles, similar to the average observed over the previous 10-year period (70%) (Figure 6). This proportion is higher than expected, given that only 45% of the population aged under 16 in England lives in areas within these two quintiles (Figure 6). Nearly half (48%) of the cases in 2025 lived in the most deprived quintile (Q5). The distribution of cases across deprivation quintiles in 2025 was broadly similar to that observed in 2024. Compared to 2015 to 24 cases, the percentage of cases in least deprived areas (Q1 and Q2) has slightly increased, and the percentage of cases in most deprived areas slightly decreased in 2025.
These findings are consistent with trends observed in United States national survey data on lead exposure and socioeconomic status (16). Possible explanations include increased exposure to lead-containing hazards, such as older housing (13,17), or a greater frequency of co-morbidity conditions such as iron deficiency anaemia, autism and learning difficulties (43). Children from ethnic minority heritages are more likely to be housed in deprived areas (44); they may therefore be disproportionately exposed to lead hazards. However, this relationship cannot be explored using LEICSS data due to insufficient completeness of ethnicity data (31,45).
Figure 6. Percentage of LEICSS cases in each quintile of index of multiple deprivation [note 1], England 2025 and 2015 to 2024, for 0 to 15 year-old children
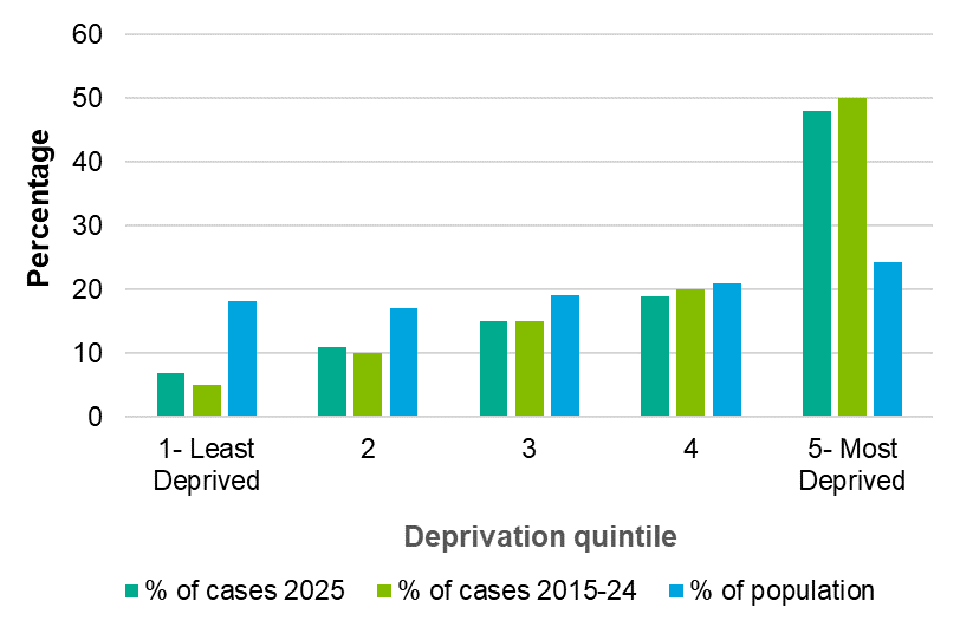
Note 1. Index of multiple deprivation (IMD) assigned to the Lower-layer Super Output Area of the cases’ postcode, using IMD scores from 2019.
Blood lead concentrations of laboratory-detected cases
Table (5) shows the distribution of BLC recorded for the cases in 2025, compared to previous years. The mean and median BLC in 2025 were 0.55 μmol/L (11.3 µg/dL) and 0.37 μmol/L (7.66 µg/dL), respectively. These values are similar to those reported during the previous three years but lower than the mean and median of 1.01 μmol/L (20.91 µg/dL) and 0.71 μmol/L (14.6 µg/dL), respectively, from 2015-2020 (Table 5). This reduction in mean and median BLC observed since 2021 is expected as a result of lowering the blood lead public health intervention threshold in 2021.
In 2025, most reported cases (n=215, 60%) were in the 0.24 to <0.48 µmol/L range. However, the number of children reported with BLC at or above 0.48 µmol/L (n=109) was still higher than the cases in 2024 (n=88). This suggests that factors other than the lowering of the public health intervention concentration from 10 µg/dL to 5 µg/dL (0.48 μmol/L to 0.24 μmol/L), such as increased clinical awareness, may have contributed to the increase in reported cases.
Between 2015 and 2025, 92% (data not shown) of BLC were below 1.45 μmol/L (<30 µg/dL). At these concentrations, children are likely to be asymptomatic or may exhibit non-specific neurobehavioural clinical manifestations (28), demonstrating that these cases were identified based on a high degree of clinical suspicion and not symptomology.
Table 5. Blood lead concentration (μmol/L) from laboratory detected LEICSS cases, England, 2025, compared to previous years [note 5]
| Year | Lab detected cases (total cases) | Minimum | Maximum | Median | Lower Quartile | Upper Quartile | Mean |
|---|---|---|---|---|---|---|---|
| 2025 [note 1] | 296 (234) | 0.24 | 5.1 | 0.37 | 0.29 | 0.6 | 0.55 |
| 2024 [note 1] | 223 (247) | 0.24 | 9.74 [note 3] | 0.37 | 0.28 | 0.6 | 0.62 |
| 2023 [note 1] | 177 (226) | 0.24 | 5.1 | 0.39 | 0.28 | 0.53 | 0.55 |
| 2022 [note 1] | 160 (191) | 0.24 | 4.03 | 0.37 | 0.29 | 0.66 | 0.61 |
| 2021 [note 1] | 80 (121) | 0.24 | 4.49 | 0.48 | 0.33 | 0.78 | 0.67 |
| 2015 to 2020 [note 2] | 160 (231) | 0.48 | 17.59 [note 4] | 0.71 | 0.55 | 1.13 | 1.01 |
Note 1: only children with a BLC≥0.24 μmol/L were eligible for notification to LEICSS.
Note 2: only children with a BLC≥0.48 μmol/L were eligible for notification to LEICSS.
Note 3: the highest BLC (2024):9.74 μmol/L; excluding this single case, the maximum reported was 5.8 μmol/L.
Note 4: the highest BLC (2015 to 2021): 17.59 μmol/L; excluding this single case, the maximum reported was 3.30 μmol/L.
Note 5: in previous reports, values below the intervention concentration were included. In this year’s report, only direct lab-detected cases meeting the case definition are included.
Table 5 looks at individual years post 2021 rather than summarising 2015 to 2023 because 2021 is when the public health intervention concentration was lowered and the impact on mean and median BLC in reported cases is expected to be significant.
Table 6. Distribution of blood lead concentrations reported to LEICSS in England for 2015 to 2025 [note 1]
| Year | BLC <0.24 µmol/L (%) [note 2] | BLC 0.24 to <0.48 µmol/L (%) | BLC ≥0.48 µmol/L(%) |
|---|---|---|---|
| 2025 [note 1] | 32 (9) | 215 (60) | 109 (31) |
| 2024 [note 1] | 28 (10) | 159 (58) | 88 (32) |
| 2023 [note 1] | 35 (13) | 138 (53) | 88 (34) |
| 2022 [note 1] | 21 (10) | 119 (56) | 72 (34) |
| 2015 to 2021 | 18 (6) [note 2] | 60 (19) | 242 (75) |
Note 1: only children with a BLC ≥0.24 μmol/L (equivalent to ≥5 μg/dL) were eligible.
Note 2: there are often reports of children with BLC below the reporting threshold from labs and other sources.
Duration of case investigation
Of the cases for which the investigation had been concluded by the time of data extraction (52%), the median duration of the investigation in 2025 was 13 weeks, excluding cases managed by the Yorkshire and Humber HPT, which has implemented a new case management system. This was longer than the median duration in 2024, which was 11 weeks, and broadly similar to the median duration reported during 2015 to 2023 (10 weeks, see Table 7).
Table 7. Duration, in weeks, of the public health investigation of LEICSS cases [note 1] reported to the surveillance system, England, 2025, 2024 and 2015 to 2023
| Year | Closed cases/total cases (%) | Median duration (weeks) [note 1] (LQ-UQ) [note 2] |
|---|---|---|
| 2025 [note 3] | 117 out of 226 (52) | 13 (6 to 23) |
| 2024 [note 3] | 76 out of 150 (51) | 11 (3 to 20) |
| 2015 to 2023 | 691 out of 769 (90) | 10 (3 to 22) |
Note 1: period between date entered onto CIMS and date case closed on CIMS; cases must have been closed at date of data extraction from CIMS in January 2026.
Note 2: LQ = lower quartile; UQ = upper quartile.
Note 3: these includes all HPTs, excluding Yorkshire and Humber, which has instituted a new case management system.
Children whose death was attributed to lead exposure
In 2015, a case report was published concerning the death of a 2-year-old child who had pica and iron deficiency and who developed acute lead toxicity following the ingestion of lead-containing paint. Delays in diagnosis and the subsequent death of the child were attributed to clinicians’ lack of awareness regarding the connection between lead exposure and pica (40). Historical data has shown deaths attributable to lead exposure in children are rare in England (42, 46).
System developments
Progress in the development of lead surveillance continued in 2025. The Lead Exposure Public Health Interventions and Surveillance (LEPHIS) Working Group meets regularly to coordinate surveillance efforts and intervention initiatives and to raise awareness of lead hazards.
Invitation of further laboratories to participate in surveillance
We continue to invite laboratories participating in the UK National External Quality Assessment Scheme (UK NEQAS) for Trace Elements (which includes measurement of BLC to participate in case reporting to LEICSS). Presentations to the Association for Clinical Biochemistry and Laboratory Medicine (ACBLM) and other interested parties on the work of LEICSS have raised awareness of reporting by laboratories and resulted in the recruitment of more laboratories participating in surveillance. Contact epht@ukhsa.gov.uk for more information.
Alerts for testing for blood lead concentrations in children
The introduction of an electronic alert within the Leeds SAS laboratory test request system encourages clinicians to consider testing for blood lead (for those children suspected of pica/iron deficiency) which led to increased test requests by 90% in 2017. The LEPHIS Working Group and Steering Group have supported laboratories in exploring the feasibility of implementing a similar model across the SAS laboratory network. However, due to the diversity of laboratory information systems in use, implementation of a standardised alerting system is not currently feasible. Discussions with laboratories are underway to amend the text on blood lead reporting to include more detailed information on expected BLC, in line with the reporting approach used by Leeds SAS laboratory.
Enhanced surveillance questionnaire (ESQ)
The ESQ is an e-questionnaire used to support the HPT risk assessment by collecting information on potential sources of lead exposures, such as a history of pica, learning difficulties, the occupational status of guardian(s), housing age and ownership, and other relevant factors. The ESQ was introduced in July 2021 to support HPTs in managing the increase in case numbers after the lowering of the intervention concentration. It also supports case management by helping to identify and exclude potential sources of lead exposure. Findings from the ESQ have been summarised to describe the frequency of potential lead exposure sources among reported cases.
A paper published in 2023 examined the sources of lead exposure in reported cases (12). This analysis was based on an audit of cases through a look-back questionnaire distributed to all HPTs that had reported LEICSS cases between 2014 and 2021.
Table 8 summarises ESQ data for cases reported in 2025, compared with ESQ from 2021 to 2024 inclusive, as well as the findings from the previously published study (31). In 2025, out of 324 LEICSS cases, 183 ESQs were concluded (56%). Among cases with a completed ESQ, soil (53%) was the most frequently identified potential source of lead exposure, followed by paint (36%). Other commonly reported potential sources include drinking water and lead pipes, workplace of parents and guardians, imported spices, imported utensils, ceramic pottery, and pewter products. Compared with 2024, the proportion of completed ESQs identifying soil and paint as potential exposure sources increased substantially, from 24% to 53% and from 17% to 36%, respectively. Other potential exposure sources were broadly similar to those reported in 2024.
The ESQ also records any history of pica behaviour and diagnosed learning difficulties. In 2025, 158 cases (86% of those with an ESQ) reported pica behaviour. Learning difficulties were reported in 142 cases (78%), which is nearly the same rate as that reported in the previous year (74%). Of those with a completed ESQ, 134 cases (73%) were reported to have both learning difficulty and pica behaviour. These findings may suggest that clinicians recognise that children are at increased risk of exposure, including those who exhibit pica or hand-to-mouth behaviour, and those with learning difficulties. However, without more complete data and reliable population estimates for the prevalence of pica and elevated blood lead levels in children, these findings should be interpreted with caution.
Table 8. Reported exposure sources for cases with an ESQ (which is completed during active case management by HPTs)
| Years in which cases were reported | Number of cases with a completed ESQ or look-back questionnaire, out of total cases [note 1] (%) | Paint source (%) | Soil source (%) | Imported spices or food (%) | Traditional medicines (%) | Imported utensils; ceramic pottery/pewter (%) | Workplace exposure from parents and guardians (%) | Drinking water and/or leaded pipe sources (%) |
|---|---|---|---|---|---|---|---|---|
| 2025 [note 1] | 183 out of 324 (56%) |
66 (36%) |
97 (53%) |
9 (5%) |
2 (1%) |
10 (5%) |
11 (6%) |
21 (11%) |
| 2021 to 2024 [note 2] | 337 out of 754 (45%) |
120 (36%) |
181 (54%) |
34 (10%) |
20 (6%) |
19 (6%) |
14 (4%) |
25 (7%) |
| 2015 to 2022 [note 3] | 347 out of 542 (64%) |
150 (43%) |
103 (29%) |
20 (6%) |
14 (4%) |
7 (2%) |
3 (1%) |
19 (5%) |
Note 1: case management requires cases with a BLC ≥0.48 μmol/L (equivalent to ≥10 μg/dL) to complete an ESQ; therefore, not all cases are expected to have an ESQ completed.
Note 2: data obtained from the ESQ; this includes cases reported from July 2021 to December 2024.
Note 3: data obtained from an audit of historical cases, via both a look back questionnaire and the ESQ (31).
UKHSA’s Environmental Public Health Surveillance System
The Environmental Public Health Surveillance System (EPHSS) collates and integrates data from selected databases on environmental hazards, exposures, and health outcome data. Further details of the system are available at: Environmental public health surveillance system (EPHSS).
A LEICSS module incorporated within EPHSS enables anonymised and aggregated LEICSS data to be interrogated and analysed, generating user-defined outputs for surveillance and reporting purposes. At present, the EPHSS platform is accessible only to UKHSA staff; however, plans are underway to extend access to external users in the future. The LEICSS case data within EPHSS are updated on a quarterly basis.
To gain access to LEICSS outputs via EPHSS, email: ephss@ukhsa.gov.uk
Current and future activities
-
Analysis of LEICSS and ESQ data is ongoing with plans to publish the results.
-
The UKHSA Dashboard which is public facing (UKHSA data dashboard: lead exposure in children includes LEICSS data as part of its modules.
-
The University of Northumbria, together with members of the LEPHIS Steering Group are leading the Elevated Child Lead Interagency Prevalence Study (ECLIPS Lead-safe Futures) and have secured funding from UK Research and Innovation (UKRI) for a feasibility study focused on protocol development. The pilot study initiated in January 2025, is evaluating the feasibility and acceptability of a child friendly, home based finger prick blood sampling method for measuring blood lead concentrations, alongside the collection of environmental samples and questionnaire data. The study protocol manuscript has been submitted to BMJ Open for publication.
-
The Environmental Hazards and Emergencies Department of UKHSA partnered with members of UKHSA’s Health Protection Teams to develop a set of guidance documents and standardised letters to support child-lead case management. These resources are available to practitioners through the UKHSA internal duty doctors’ pack (47). In addition, a public-facing webpage on GOV.UK that summarises this guidance has been published: Lead poisoning: advice for the public and healthcare professionals. UKHSA is also developing a new public facing website on GOV.UK that will provide information on chemicals and products that members of the public may encounter in their everyday lives, this will include a page on lead.
-
UKHSA has completed a research project with the Georgian National Center for Disease Control to identify sources of lead exposure in children in Georgia (48 to 50). Publications from the project are currently in preparation.
Notes
Note 1: pica is the persistent ingestion of non-nutritive substances at an age where this is developmentally inappropriate.
Note 2: France banned white lead-based interior paint in 1909 (earlier than England); thus, exposures from this source would be expected to be lower than in the UK.
Note 3: both µmol/L and µg/dL units are commonly used internationally to express blood lead concentrations, where 1 µg/dL = 0.0483 µmol/L. Divide the concentration in µg/dL by 20.7 to obtain the concentration in µmol/L.
Note 4: HPTs are frontline units responsible for investigating and managing public health threats to their populations.
Note 5: eight cases from 2023 were reported in 2022 and were excluded from the 2023 report.
Note 6: see English indices of deprivation 2019.
References
1. UKHSA. Lead: toxicological overview
2. Public Health England (2021). ‘Evaluation of whether to lower the public health intervention concentration for lead exposure in children’
3. Etchevers A, and others (2014). ‘Blood lead levels and risk factors in young children in France, 2008 to 2009’ International Journal of Hygiene and Environmental Health: volume 217, pages 528 to 537.
4. American Academy of Pediatrics Committee on Environmental Health (2005). ’Lead exposure in children: prevention, detection, and management’ Pediatrics: volume 116 number 4, pages 1,036 to 1,046.
5. Rees N and Fuller R (2020). ‘The Toxic Truth: Children’s exposure to lead pollution undermines a generation of future potential. Unicef and Pure Earth’
6. Larsen B, Sanchez-Triana E (2023). ‘Global health burden and cost of lead exposure in children and adults: a health impact and economic modelling analysis’ The Lancet Planetary Health: volume 7, issue 10.
7. McConnell JR, and others (2024). ‘Pan-European atmospheric lead pollution, enhanced blood lead levels and cognitive decline from Roman-era mining and smelting’ Environmental Sciences: volume 122.
8. Yu D (2025). ‘Lead exposure in the 21st century: modelling a path from crisis to prevention’ Eco-Environment and Health: volume 4 number 3, article100159
9. Chen M, and others (2025). ‘Environmental lead risk in the 21st century’ Communications Earth and Environment. Volume 6, number 776
10. WHO (2010). Childhood lead poisoning: pages 1 to 72
11. US Centers for Disease Control and Prevention (2024). ’CDC Updates Blood Lead Reference Value’
12. Shadbegian R and others (2024). ‘Low-level, early life lead exposure and school behavior’ Pediatrics: volume 154
13. Crawfurd L, and others (2025). ‘The effect of lead exposure on children’s learning in the developing world: a meta-analysis’ World Bank Research Observer: volume 40 number 2, pages 229 to 260
14. WHO (2024). Lead poisoning and health.
15. Agency for Toxic Substances and Disease Registry (2020). ’ATSDR Lead Tox Profile’
16. Larsen B, Sánchez-Triana E (2023). ‘Global health burden and cost of lead exposure in children and adults: a health impact and economic modelling analysis’ Lancet Planetary Health: volume 7 number 10, pages e831 to e840
17. GBD 2023 Lead Collaborators, Stanaway J D, Spearman S, and others (2026). ‘Lead-attributable cardiovascular disease burden: Global Burden of Disease Study 2023’ Journal of the American Medical Association: volume 335, number 16, pages 1,418 to 1,427
18. Pure Earth. ‘Annual Report 2024/25 Pure-Earth-Annual-Report-2024-25.pdf’
19. Etchevers A, and others (2015). ’Screening for elevated blood lead levels in children: assessment of criteria and a proposal for new ones in France’ International Journal of Environmental Research and Public Health: volume 12, issue 12, pages 15,366 to 15,378
20. US Centers for Disease Control and Prevention (2021). ’CDC updates blood lead reference value for children’
21. Bazian Ltd (2018). ‘Screening for elevated blood lead levels in asymptomatic children aged 1 to 5 years’. In: External review against programme appraisal criteria for the UK National Screening Committee
22. US Centers for Disease Control and Prevention (2025). ’Childhood Blood Lead Surveillance: National Data’
23. Office for National Statistics (2025). Population estimates for England and Wales: mid 2024
24. Pure Earth. ‘Lead Pollution in United Kingdom of Great Britain and Northern Ireland’
25. Kaysi I, Mahmassani H, Arnaout S, and Kattan L (2000). ‘Phasing out lead in automotive fuels: conversion considerations, policy formulation and application to Lebanon’ Journal of Environmental Assessment Policy and Management
26. Johnson L, Barlow PJ and Barratt RS (1984). ‘Lead in paint: brushed aside?’ Journal of the Royal Society of Health: volume 104 number 2, pages 64 to 67
27. UKHSA (2022). Lead: toxicological overview
28. Ruckart PZ and others (2021). ‘Update of the blood lead reference value: United States, 2021’ Morbidity and Mortality Weekly Report: volume 70 number 43, pages 1,509 to 1,512
29. UKHSA (2024). Lead: clinical intervention
30. UK Health Security Agency. (2024). Lead Exposure in Children Surveillance System (LEICSS) annual report, 2024
31. Dave M and others (2023). ‘Lead exposure sources and public health investigations for children with elevated blood lead in England, 2014 to 2022’ PLOS One: volume 19, number 7
32. Crabbe H, and others (2022). ‘As safe as houses; the risk of childhood lead exposure from housing in England and implications for public health’ BMC Public Health: volume 22 number 1, page 2,052
33. US Centers for Disease Control and Prevention (1991). ’Preventing lead poisoning in young children’
34. Lewendon G, and others (2001). ‘Should children with developmental and behavioural problems be routinely screened for lead?’ Archives of Disease in Childhood: volume 85, number 4, pages 286 to 288
35. US Centers for Disease Control and Prevention (2024). ’CDC Updates Blood Lead Reference Value’
36. Kwong WT, Friello P and Semba RD. ‘Interactions between iron deficiency and lead poisoning: epidemiology and pathogenesis’ Science of the Total Environment 2004: volume 330, number 1 to 3, pages 21 to 37
37. Public Health England (2018). ‘Surveillance of elevated blood lead in children (SLiC): a British Paediatric Surveillance Unit analysis’
38. UKHSA (2024). ‘Lead standard operating procedure for HPTs’ [internal document]
39. Tsoi MF and others (2021). ‘Continual decrease in blood lead level in Americans: United States National Health Nutrition and Examination Survey 1999 to 2014’ American Journal of Medicine: volume 129 number 11, pages 1,213 to 1,218
40. Talbot A, Lippiatt C and Tantry A (2018). ‘Lead in a case of encephalopathy’ BMJ Case Reports
41. Matson JL and others (2011). ‘Pica in persons with developmental disabilities: characteristics, diagnosis, and assessment’ Research in Autism Spectrum Disorders: volume 5, number 4, pages 1,459 to 1,464
42. Loomes R, Hull L and Mandy WPL (2017). ‘What is the male-to-female ratio in autism spectrum disorder? A systematic review and meta-analysis’ Journal of the American Academy of Child and Adolescent Psychiatry: volume 56 number 6, pages 466 to 474
43. Hauptman M, Stierman B, and Woolf AD (2019). ‘Children with autism spectrum disorder and lead poisoning: diagnostic challenges and management complexities’ Clinical Paediatrics: volume 58, issue 6, pages 605 to 612
44. Jivraj S and others (2022). ‘How likely are people from minority ethnic groups to live in deprived neighbourhoods?’ Cambridge University Press
45. Perry MJ, and others (2021). ‘Pervasive structural racism in environmental epidemiology’ Environmental Health: volume 20 number 1, page 119
46. Elliott P, and others (1999). ‘Clinical lead poisoning in England: an analysis of routine sources of data’ Occupational and Environmental Medicine: volume 56, number 12, pages 820 to 824
47. Roberts DJ, and others (2022). ‘Lead exposure in children’ British Medical Journal: volume 377
48. Ruadze E, and others (2021). ‘Reduction in blood lead concentration in children across the Republic of Georgia following interventions to address widespread exceedance of reference value in 2019’ International Journal of Environmental Research and Public Health: volume 18 number 22
49. Laycock A, and others (2022). ‘The Use of Pb isotope ratios to determine environmental sources of high blood Pb concentrations in children: a feasibility study in Georgia’ International Journal of Environmental Research and Public Health: volume 19 number 22
50. Bainduri M and others (2024). ’Assessment of blood lead levels in 2 to 7-year-old children in Poti, Georgia, 2023: a pilot study of environmental lead exposure sources’ Environmental Research: volume 278
Resources
UKHSA launched a free online training course, ‘Tackling lead poisoning in public health’, in July 2021, designed for professionals involved in responding to lead incidents to develop their understanding of lead poisoning and public health policy.
A webinar on the importance of lead exposure, held in 2021 by the Royal College of Paediatrics and Child Health (RCPCH) for training of physicians and paediatrics, is available on YouTube (See ‘RCPCH-BPSU webinar series: Toxicity in children – a continuing problem’).
To stay updated with the work of UKHSA’s Environmental Public Health Tracking (EPHT) group and EPHSS, email: epht@ukhsa.gov.uk
To find out more about gaining access to LEICSS outputs via EPHSS, email: ephss@ukhsa.gov.uk
More resources for the public health management of cases of lead exposure
The LEPHIS Steering group, with the British Paediatric Surveillance Unit (BPSU) and Royal College of Paediatrics and Child Health presented a webinar on lead as part of their series on rare diseases (to raise awareness of LEICSS amongst clinicians).
Lead toxicology and incident management advice (UKHSA Chemicals Compendium): Lead: health effects, incident management and toxicology
Public Health Incidents Involving Lead : an online public health course
Lead pages in the UKHSA chemicals compendium
Lead Exposure in Children Surveillance System: Surveillance Reports from 2021
Lead exposure in children: surveillance reports before 2021
Health and Safety Executive report: ‘Exposure to Lead’
Advice and guidance on lead and the prevention, diagnosis and treatment of lead poisoning: Lead poisoning: advice for the public and healthcare professionals
Resources for clinicians
Clinicians with clinical lead exposure queries should consult TOXBASE, the online information database produced by the National Poisons Information Service (NPIS) or telephone the NPIS directly on 0344 892 0111. This telephone helpline is only available to healthcare professionals and cannot take calls from members of the public.
Procedures for reporting lead cases to UKHSA
For adult cases with a BLC of ≥0.48 μmol/L (equivalent to ≥10μg/dL): contact the local HPT of the case. The relevant HPT can be identified by entering the residential postcode of the case into GOV.UK.
For pregnant women with a BLC of ≥0.24 μmol/L (equivalent to ≥5μg/dL): contact the local HPT of the case. The relevant HPT can be identified by entering the residential postcode of the case into GOV.UK.
Sources and presentations of lead exposure in children
Important sources of lead exposure in children are as follows:
- deteriorating leaded paint (particularly houses built prior to early 1970s)
- herbal medicinal preparations
- consumer products (if unregulated): medicines, food, spices, ceramic cookware, lead crystal, toys, make-up
- parental hobbies or occupations (including dust on clothing)
- lead water pipes, and lead from drinking water pipe fittings (namely, solder) (particularly houses built prior to early 1970s)
- contaminated soil or land
Children at most risk of lead exposure are as follows:
- children with pica or increased hand to mouth behaviour (for example, children with autism or global developmental delay), particularly with iron deficiency
- children who have recently migrated from countries with less regulation to prevent lead exposure
- children living in older homes and attending older schools containing leaded paint
- children living in more urban or industrial environments
Presentations of lead exposure in children are as follows:
- acute exposure resulting in high BLC: anorexia, abdominal pain, constipation, irritability and reduced concentration, encephalopathy
- chronic exposure
- lower BLCs: mild cognitive and behavioural impairments, may contribute to global developmental delay, decreased academic achievement, IQ, and specific cognitive measures (S); increased incidence of attention-related behaviours and problem behaviours (S), and delayed puberty and decreased kidney function in children ≥12 years of age (L)
- higher BLCs: reduced appetite, abdominal pain, constipation, anaemia, delayed puberty, reduced postnatal growth, decreased IQ, and decreased hearing (S); and increased hypersensitivity or allergy by skin prick test to allergens and increased IgE (L)
Where (S) = sufficient evidence and (L) = limited evidence
Contacts
To notify cases, contact: phe.leicss@nhs.net
For general enquiries, contact: epht@ukhsa.gov.uk
For lead surveillance module in UKHSA’s Environmental Public Health Surveillance System, contact: ephss@ukhsa.gov.uk
Interpretation of Blood Lead Concentration Units
Blood lead concentrations (BLCs) in this report are presented in µmol/L, the standard unit used by UK laboratories. For international comparison, equivalent concentrations in µg/dL are also provided. It is to note that some international publications may report blood lead concentrations in µg/L, and care should be taken when comparing values reported using different units.
| BLC Unit conversion | ||
|---|---|---|
| µmol/L | µg/dL | µg/L |
| 0.1 | 2 | 21 |
| 0.2 | 4 | 42 |
| 0.24 | 5 | 50 |
| 0.48 | 10 | 100 |
| 1.44 | 30 | 300 |
| 2 | 42 | 414 |
| 2.4 | 50 | 500 |
Steering and working group members (UKHSA unless otherwise indicated)
LEICSS surveillance team: Araceli Busby (surveillance lead and Chair); Neena George; Priya Mondal; Elena DeCandia; Rebecca Close and Neelam Iqbal.
LEPHIS Working Group (as above plus the following members): Alec Dobney; Sarah Dack; Tim Marczylo; Naomi Earl; Lorraine Stewart; Tess Tigere; Vince Cassidy; Kerry Foxall; Richard Dunn; Lee Grayson; Mercy Vergis; Helen Crabbe; Ovnair Sepai; Emily Bird and Bernd Eggen.
LEPHIS Steering Group (includes the above working group plus the following members): Alan Emond (University of Bristol/British Paediatric Surveillance Unit); Louise Ander (British Geological Survey); Sally Bradberry/Mark Pucci (National Poisons Information Service, City Hospital, Birmingham); Kishor Raja and Carys Lippiatt (Supra-regional Assay Service Trace Elements laboratories); Andrew Kibble (RCCE Wales); Tim Pye (LEAPP Alliance); Geoffrey Mullings (UKHSA CIMS team); Priyanka Chaurasia (Ulster University); Luke Week and Jack Gordon-Brown (Comms, UKHSA).
Acknowledgement to laboratories
NHS Supra-regional Assay Services Trace Elements laboratories: Birmingham; Leeds; Southampton; Guildford; London Charing Cross; London Kings College.
Other laboratories notifying cases included in this report: Cardiff Toxicology Laboratories; Southmead Hospital, Bristol; Alder Hey Children’s Hospital, Liverpool; Royal Liverpool University Hospital; Northern General Hospital, Sheffield; Nottingham University NHS Trust Hospital.