Hepatitis C in the West Midlands annual report 2025
Updated 8 October 2026

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/hepatitis-c-in-the-west-midlands-annual-reports/hepatitis-c-in-the-west-midlands-annual-report-2025
Introduction
Hepatitis C virus (HCV) is a bloodborne virus. Chronic infection can lead to liver cirrhosis, end stage liver disease and liver cancer. Prevention and treatment efforts have been combined to combat HCV infection and progress towards elimination of HCV as a public health threat by 2030 (set out in the World Health Organization Global Health Sector Strategy on Viral Hepatitis). The National Strategic Group on Viral Hepatitis, a cross-agency expert advisory body supported by the UK Health Security Agency (UKHSA) provides strategic guidance on viral hepatitis in England, and supports progress toward achieving the World Health Organization (WHO) goal of HCV elimination.
UKHSA publishes a national Hepatitis C in England report which summarises England’s progress towards the WHO elimination targets for HCV infection. This regional spotlight report complements the ‘Hepatitis C in England’ report and presents further information on HCV disease surveillance, and trends in HCV diagnosis, testing and treatment in West Midlands UKHSA region with data up to end of 2024.
For more about data sources, see Information on data sources.
Summary
Key findings for hepatitis C testing:
- there were 1,161 new laboratory reports of hepatitis C in residents of the West Midlands UKHSA region, representing a rate of 18.8 reports per 100,000 population in 2024
- the number of new laboratory reports has increased by 46.2% since 2023 and increased by 6.5% over the past 10 years
- in 2024, the number of positive laboratory reports by upper tier local authority of residence ranged from 5 in Solihull to 286 in Worcestershire. Rates were highest in Sandwell at 73.2 and lowest in Solihull with 2.3
- in 2024, the number of laboratory reports in males was 589 (50.7%) and in females was 255 (22.0%). Sex was unknown in 27.3% of cases
- in 2024, the highest number of laboratory reports was in males aged 35 to 44 and females aged 35 to 44
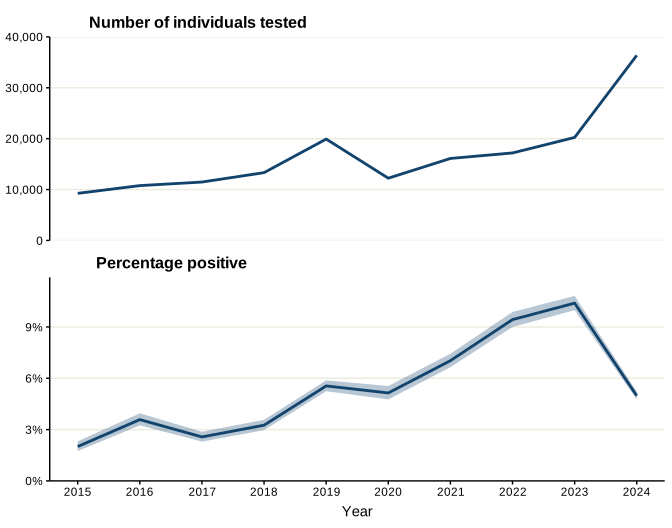
- there have been 36,371 individuals tested for anti-HCV in sentinel laboratories in West Midlands UKHSA region in 2024, of which 5.0% tested positive. The proportion positive was lower for tests referred from general practitioner (GP) surgeries, and higher for tests from drug services; the total number of tests conducted has likely increased since 2022 as a result of a new ‘opt-out’ bloodborne virus testing programme at selected emergency departments
Key findings for hepatitis C treatment pathway:
- of 5,511 individuals with chronic hepatitis C linked to specialist treatment services (using a recorded NHS number or name and date of birth via the NHSE Hepatitis C Patient Registry and Treatment Outcome System and/or NHSE’s Blueteq System), 5,350 started treatment within 90 days and 4,092 achieved a sustained viral response (SVR), in the West Midlands UKHSA region between 2015 and 2024
Key findings for HCV-related morbidity and mortality:
- the number of first hospital admissions for individuals with a diagnosis code for hepatitis C-related end-stage liver disease or hepatitis C-related hepatocellular carcinoma is estimated to be between 59 and 79 in the West Midlands UKHSA region in 2024. This was lower than in 2023 (first hospital admissions: 85 to 110)
- the number of registered deaths from hepatitis C-related and end-stage liver disease and/ or hepatocellular carcinoma was estimated to be between 17 and 40 in the West Midlands UKHSA region in 2024. The lower and upper bound estimates were lower than their corresponding values for 2023, (estimated deaths: 20 to 43)
Trends in HCV testing and diagnosis in the general population and risk groups
New laboratory-confirmed diagnoses of HCV
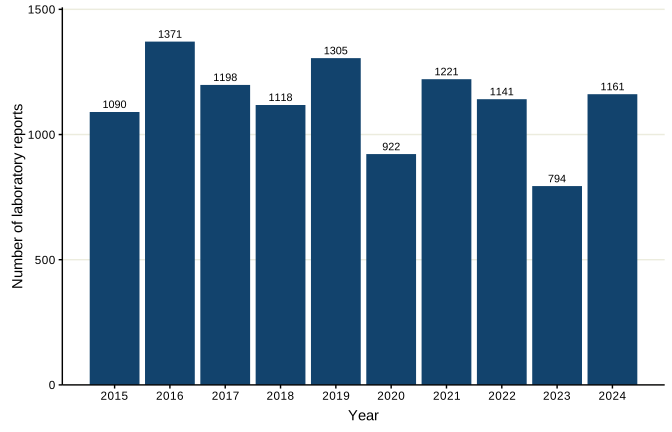
Figure 1. Number of new laboratory reports of hepatitis C, residents of West Midlands UKHSA region, 2015 to 2024
Data source: Second Generation Surveillance System (SGSS). For more information, see Information on data sources.
Note 1: in 2022, a new bloodborne virus (BBV) testing programme was introduced in selected emergency department (ED) sites in areas of very high and high human immunodeficiency virus (HIV) diagnosed prevalence across England, which included sites in London, Manchester, Salford, Brighton and Blackpool. This programme expanded to other areas of high HIV prevalence in the second phase of the implementation of this programme, starting in 2024, however, not all UKHSA regions had participating ED sites within their areas. Sites within the West Midlands were part of the second phase of this programme.
The number of new laboratory reports of hepatitis C in the West Midlands fluctuated between 2015 and 2024, with a marked decline in 2020 and 2023, the decline in 2020 most likely reflecting reduced testing during the COVID-19 pandemic. The reason for the dip in numbers in 2023 is not clear, however, may be a result of a number of reasons such as data quality issues, or testing practices which include use of oral swab testing. Reports recovered in subsequent years and increased substantially in 2024 to 1,161 cases, representing a 46.2% increase compared with 2023. This may partly reflect the expansion of bloodborne virus testing in emergency departments (ED), which began for 3 out of the 9 sites signed up to the programme in 2024 in the West Midlands.
It is important to note that these laboratory results include both antibody and RNA positive results which means that not all new laboratory reports are new infections.
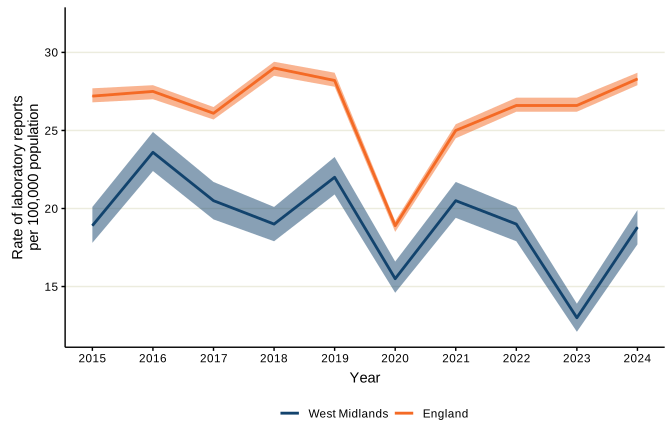
Figure 2. Rate per 100,000 population of new laboratory reports of hepatitis C, residents of West Midlands UKHSA region and England, 2015 to 2024
Data sources: SGSS and Office for National Statistics (ONS) mid-year population estimates (MYE). For more information, see Information on data sources.
Note 2: the error bands represent 95% confidence intervals.
Rates of new laboratory reports in the West Midlands broadly followed the national trend from 2016 to 2021 but remained consistently below the England rate. Following a decline in 2020, rates subsequently increased in 2021 to 20.5 per 100,000, then showed a general decrease and reached 18.8 per 100,000 population in 2024. A sharp dip seen in 2023 does not follow the pattern seen for England, this may have been due to a decline in testing during that year or data quality issues, though further investigation would be needed to fully understand this.
The overall trend appears to be downward since 2016, which may show the progress being made by the Birmingham Operational Delivery Network (ODN). Up to 2024, micro-elimination had been achieved in some rural drug services and some prisons in areas of low prevalence, which may not completely reflect in the numbers but shows good progress towards elimination.
Table 1. Number and rate per 100,000 population of new laboratory reports of hepatitis C by UKHSA region of residence and England, 2015 to 2024
| Area | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | 2023 | 2024 | |
|---|---|---|---|---|---|---|---|---|---|---|---|
| East Midlands | Count | 963 | 1,079 | 1,124 | 1,341 | 1,345 | 709 | 971 | 1,027 | 870 | 1,345 |
| East Midlands | Rate | 20.6 | 22.8 | 23.5 | 27.8 | 27.8 | 14.6 | 19.9 | 20.8 | 17.4 | 26.6 |
| East of England | Count | 1,105 | 1,291 | 1,131 | 1,039 | 1,072 | 773 | 1,092 | 997 | 815 | 929 |
| East of England | Rate | 16.6 | 19.2 | 16.7 | 15.3 | 15.7 | 11.3 | 15.8 | 14.3 | 11.5 | 12.9 |
| London | Count | 4,026 | 4,177 | 3,432 | 3,146 | 2,634 | 2,438 | 2,702 | 3,533 | 4,093 | 4,552 |
| London | Rate | 46.5 | 47.8 | 39.1 | 35.6 | 29.6 | 27.5 | 30.7 | 39.8 | 45.5 | 50.1 |
| North East | Count | 216 | 228 | 390 | 750 | 967 | 700 | 903 | 1,071 | 777 | 888 |
| North East | Rate | 8.3 | 8.7 | 14.9 | 28.5 | 36.7 | 26.5 | 34.1 | 39.9 | 28.5 | 32.2 |
| North West | Count | 2,935 | 2,625 | 2,485 | 3,467 | 2,964 | 1,462 | 2,782 | 2,693 | 2,826 | 2,767 |
| North West | Rate | 40.9 | 36.3 | 34.2 | 47.4 | 40.3 | 19.8 | 37.5 | 35.8 | 37.0 | 35.8 |
| South East | Count | 1,581 | 1,818 | 1,436 | 1,445 | 1,491 | 1,216 | 1,749 | 2,140 | 2,277 | 1,781 |
| South East | Rate | 18.8 | 21.4 | 16.8 | 16.8 | 17.3 | 14.0 | 20.1 | 24.3 | 25.5 | 19.7 |
| South West | Count | 1,147 | 1,065 | 1,105 | 994 | 957 | 913 | 842 | 947 | 1,035 | 1,400 |
| South West | Rate | 21.0 | 19.3 | 19.8 | 17.7 | 17.0 | 16.1 | 14.7 | 16.4 | 17.8 | 23.8 |
| West Midlands | Count | 1,090 | 1,371 | 1,198 | 1,118 | 1,305 | 922 | 1,221 | 1,141 | 794 | 1,161 |
| West Midlands | Rate | 18.9 | 23.6 | 20.5 | 19.0 | 22.0 | 15.5 | 20.5 | 19.0 | 13.0 | 18.8 |
| Yorkshire and Humber | Count | 1,812 | 1,483 | 1,423 | 1,608 | 1,665 | 1,035 | 1,314 | 1,258 | 1,243 | 1,514 |
| Yorkshire and Humber | Rate | 33.7 | 27.4 | 26.2 | 29.5 | 30.5 | 18.9 | 24.0 | 22.7 | 22.2 | 26.7 |
| England | Count | 14,916 | 15,182 | 14,517 | 16,195 | 15,864 | 10,630 | 14,116 | 15,217 | 15,432 | 16,590 |
| England | Rate | 27.2 | 27.5 | 26.1 | 29.0 | 28.2 | 18.9 | 25.0 | 26.6 | 26.6 | 28.3 |
Data sources: SGSS and Office for National Statistics (ONS) mid-year population estimates (MYE). For more information, see Information on data sources.
Note 3: data was not available to assign a case to a UKHSA region in 253 cases, meaning that the sum of all regional cases may not equal the number of England cases.
In 2024, the West Midlands reported 1,161 new laboratory reports of hepatitis C, equivalent to a rate of 18.8 per 100,000 population. Regional rates varied considerably across England, with the highest rates observed in London (50.1 per 100,000) and the North West (35.8 per 100,000). The West Midlands rate was lower than the England average of 28.3 per 100,000 population.
Table 2. Number and rate per 100,000 population of new laboratory reports of hepatitis C by upper tier local authority (UTLA) of residence, 2015 to 2024
| Area | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | 2023 | 2024 | |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Birmingham | Count | 253 | 391 | 364 | 317 | 405 | 253 | 427 | 330 | 89 | 203 |
| Birmingham | Rate | 22.7 | 34.6 | 31.9 | 27.7 | 35.2 | 22.0 | 37.3 | 28.6 | 7.6 | 17.2 |
| Coventry | Count | 171 | 131 | 179 | 129 | 184 | 148 | 183 | 200 | 111 | 72 |
| Coventry | Rate | 51.6 | 38.9 | 52.6 | 37.6 | 53.5 | 42.9 | 53.2 | 56.9 | 30.9 | 19.5 |
| Dudley | Count | 60 | 52 | 52 | 46 | 33 | 26 | 31 | 36 | 10 | 29 |
| Dudley | Rate | 19.0 | 16.4 | 16.3 | 14.3 | 10.2 | 8.1 | 9.6 | 11.1 | 3.0 | 8.7 |
| Herefordshire | Count | 28 | 18 | 12 | 21 | 41 | 68 | 14 | 14 | 40 | 24 |
| Herefordshire | Rate | 15.1 | 9.7 | 6.4 | 11.3 | 22.0 | 36.6 | 7.5 | 7.4 | 21.0 | 12.6 |
| Sandwell | Count | 27 | 42 | 42 | 68 | 66 | 40 | 25 | 32 | 87 | 259 |
| Sandwell | Rate | 8.3 | 12.7 | 12.6 | 20.2 | 19.4 | 11.7 | 7.3 | 9.3 | 24.9 | 73.2 |
| Shropshire | Count | 67 | 111 | 58 | 28 | 48 | 23 | 28 | 37 | 38 | 23 |
| Shropshire | Rate | 21.6 | 35.5 | 18.4 | 8.8 | 15.0 | 7.2 | 8.6 | 11.3 | 11.5 | 6.9 |
| Solihull | Count | 8 | 52 | 27 | 6 | 5 | 6 | 6 | 5 | 5 | 5 |
| Solihull | Rate | 3.8 | 24.4 | 12.6 | 2.8 | 2.3 | 2.8 | 2.8 | 2.3 | 2.3 | 2.3 |
| Staffordshire | Count | 131 | 117 | 116 | 77 | 100 | 112 | 152 | 95 | 75 | 79 |
| Staffordshire | Rate | 15.3 | 13.6 | 13.4 | 8.9 | 11.5 | 12.8 | 17.3 | 10.7 | 8.4 | 8.7 |
| Stoke-on-Trent | Count | 64 | 74 | 43 | 57 | 104 | 57 | 91 | 101 | 84 | 88 |
| Stoke-on-Trent | Rate | 25.2 | 28.9 | 16.7 | 22.0 | 40.1 | 22.0 | 35.3 | 38.8 | 31.6 | 32.5 |
| Telford and Wrekin | Count | 16 | 22 | 27 | 42 | 34 | 8 | 12 | 15 | 14 | 19 |
| Telford and Wrekin | Rate | 9.3 | 12.5 | 15.2 | 23.4 | 18.7 | 4.4 | 6.5 | 7.9 | 7.3 | 9.7 |
| Walsall | Count | 56 | 72 | 72 | 71 | 69 | 15 | 18 | 19 | 9 | 10 |
| Walsall | Rate | 20.3 | 25.9 | 25.6 | 25.1 | 24.2 | 5.3 | 6.3 | 6.6 | 3.1 | 3.4 |
| Warwickshire | Count | 65 | 75 | 60 | 77 | 89 | 70 | 129 | 115 | 58 | 48 |
| Warwickshire | Rate | 11.6 | 13.2 | 10.5 | 13.3 | 15.2 | 11.9 | 21.5 | 18.9 | 9.3 | 7.6 |
| Wolverhampton | Count | 33 | 41 | 41 | 21 | 6 | 24 | 24 | 26 | 17 | 14 |
| Wolverhampton | Rate | 12.9 | 15.9 | 15.7 | 8.0 | 2.3 | 9.1 | 9.1 | 9.7 | 6.2 | 5.0 |
| Worcestershire | Count | 109 | 164 | 97 | 114 | 121 | 72 | 79 | 116 | 157 | 286 |
| Worcestershire | Rate | 18.7 | 27.9 | 16.4 | 19.2 | 20.2 | 12.0 | 13.1 | 19.0 | 25.5 | 46.0 |
| No UTLA data available | Count | 2 | 9 | 8 | 44 | 0 | 0 | 2 | 0 | 0 | 2 |
| No UTLA data available | Rate | NA | NA | NA | NA | NA | NA | NA | NA | NA | NA |
| England | Count | 14,916 | 15,182 | 14,517 | 16,195 | 15,864 | 10,630 | 14,116 | 15,217 | 15,432 | 16,590 |
| England | Rate | 27.2 | 27.5 | 26.1 | 29.0 | 28.2 | 18.9 | 25.0 | 26.6 | 26.6 | 28.3 |
Data sources: SGSS and Office for National Statistics (ONS) mid-year population estimates (MYE). For more information, see Information on data sources.
Note 4: data was not available to assign a case to a UKHSA region in 253 cases, meaning that the sum of all regional cases may not equal the number of England cases. UTLA data was available for 99% of cases where region data was available.
There was considerable variation in hepatitis C diagnosis rates across upper tier local authorities in the West Midlands in 2024. Sandwell reported the highest rate (73.2 per 100,000 population), followed by Worcestershire (46.0) and Stoke-on-Trent (32.5). In contrast, Solihull had the lowest rate at 2.3 per 100,000 population. Although Worcestershire reported the highest number of cases (286), Sandwell had the highest rate after accounting for population size.
Although it is not clear why there have been large increases between 2023 and 2024 in both Sandwell and Worcestershire which could be a result of various issues. For Sandwell an initiative to find and treat attendees of a large drug and alcohol service within that local authority in 2024 could have contributed to some of these new positive laboratory reports. For Worcestershire, the work around prison testing had increased, so may have also contributed to some of this increase, however, in both cases further work would be needed to explore the reasons for these fluctuations in the data at UTLA level.
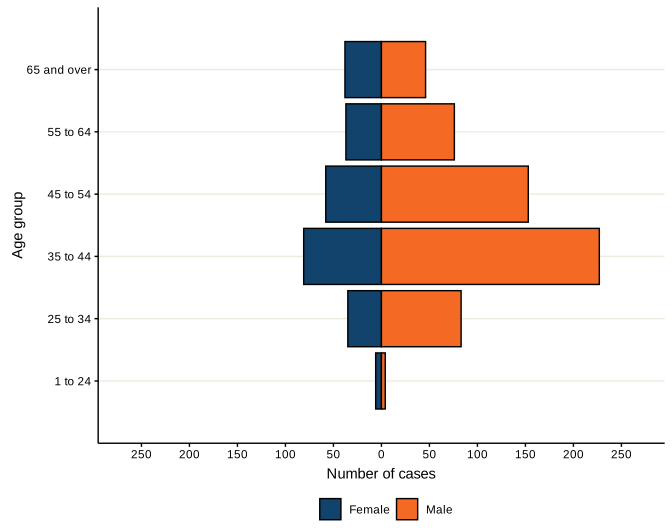
Figure 3. Age group and sex of new laboratory reports of hepatitis C, residents of West Midlands UKHSA region, 2024
Data source: Second Generation Surveillance System (SGSS). For more information, see Information on data sources.
The age and sex distribution of laboratory reports shows that most reports were among males. In 2024, 50.7% of reports were in males compared with 22.0% in females, while sex was unknown for 27.3% of reports. The highest number of reports was observed among males aged 35 to 44 years; for females the highest number of reports was also amongst those aged 35 to 44 years. A substantial proportion of reports had unknown age and/or sex recorded, and these findings should therefore be interpreted with caution.
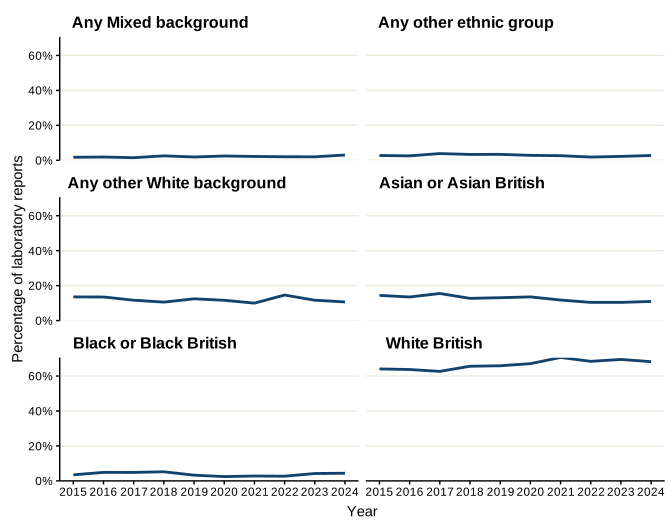
Figure 4. Ethnicity distribution of new laboratory reports of hepatitis C, residents of West Midlands UKHSA region, 2015 to 2024
Data source: SGSS. For more information, see Information on data sources.
Note 5: this figure excludes cases of unknown ethnicity. (42.1% of reports had no ethnicity recorded).
Note 6: where the number of cases in an ethnic group in a given year is between 1 and 4 (inclusive), data has been suppressed for disclosure control. Suppressed values are shown as an asterisk (*) on the chart.
Among reports with ethnicity recorded, the greatest percentage of hepatitis C diagnoses occurred among individuals recorded as White British throughout the reporting period. The distribution of diagnoses by ethnicity has remained broadly stable over time, although some variation between ethnic groups was observed. Interpretation should be made with caution as 42.1% of laboratory reports had no ethnicity recorded.
HCV testing in the wider population
Figure 5. Number of individuals tested for anti-HCV by year and percentage positive in sentinel laboratories in West Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 7: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 8: in 2022, a new bloodborne virus (BBV) testing programme was introduced in selected emergency department (ED) sites in areas of very high and high human immunodeficiency virus (HIV) diagnosed prevalence across England. This programme expanded to other areas of high HIV prevalence in the second phase of the implementation of this programme, starting in 2024, however, not all UKHSA regions had participating ED sites within their areas.
Note 9: the error bands represent 95% confidence intervals.
The number of individuals tested for anti-HCV increased substantially over time and reached 36,371 in 2024 from 9,257 in 2015. Testing activity increased, particularly in 2024 compared to 2023 (20,243 tests), following the implementation and expansion of the emergency department opt-out bloodborne virus testing programme. While there was increased testing, the proportion testing positive remained relatively low at 4.98% in 2024 compared to 10.39% in 2023, which may suggest that testing is reaching a broader population.
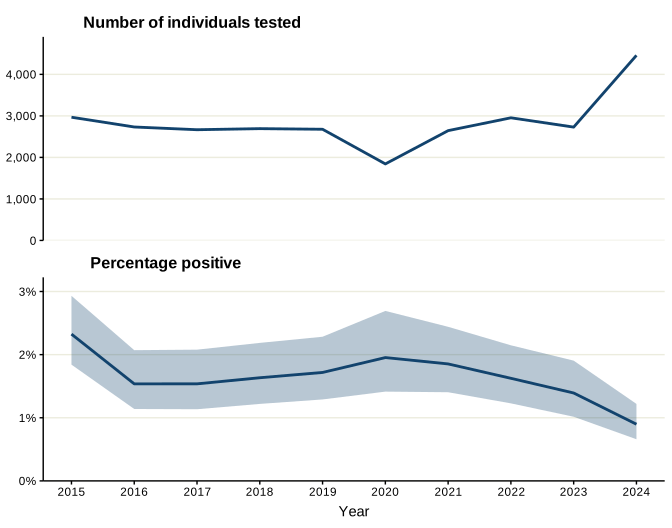
Figure 6. Number of individuals tested for anti-HCV by year and percentage positive, through GP surgeries, in sentinel laboratories in West Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 10: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 11: the error bands represent 95% confidence intervals.
The number of individuals tested for anti-HCV through GP surgeries showed little variation between 2015 and 2023, remaining just below 3000 tests, except in 2020 where it dropped likely due to the effect of the pandemic. In 2024 the testing level increased to 4,458 which may be due to initiatives taking place to expand testing in primary care. The proportion testing positive for anti-HCV through GP surgeries was consistently lower than that observed across all testing settings combined and showed an overall decline over time. This may reflect changes in testing practices, risk profiles of those tested, and increasing testing coverage.
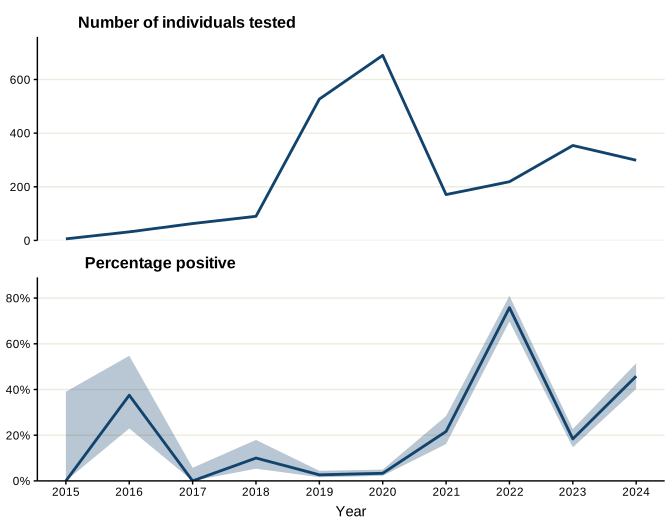
Figure 7. Number of individuals tested for anti-HCV by year and percentage positive, through sexual health services, in sentinel laboratories in West Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 12: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 13: the error bands represent 95% confidence intervals.
Testing volumes through sexual health services fluctuated over time from 2015 to 2024, as did positivity. This pattern of testing and positivity may be due to changes in testing practices, such as more targeted testing during certain periods, or issues with data quality, reporting or processing, however, further investigation would be needed to understand these patterns.
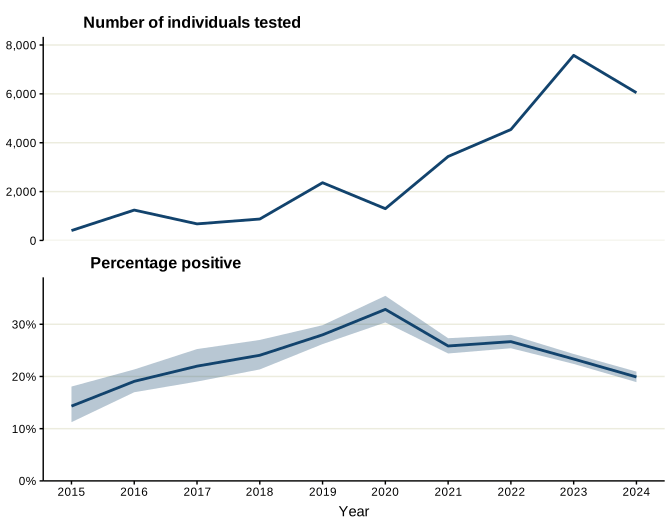
Figure 8. Number of individuals tested for anti-HCV by year and percentage positive, through drug services, in sentinel laboratories in West Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 14: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 15: the error bands represent 95% confidence intervals.
Drug services consistently reported high positivity among the testing settings presented, reflecting the increased risk of hepatitis C infection among people who inject drugs. Testing activity fluctuated over the reporting period but showed an overall increase starting from 405 tests in 2015 to 6,046 in 2024, while positivity remained high compared with most other testing settings. Although there is a decline in positivity since 2020, the number of positive results has increased overall. Drug services therefore continue to be an important route for identifying infections and supporting access to treatment.
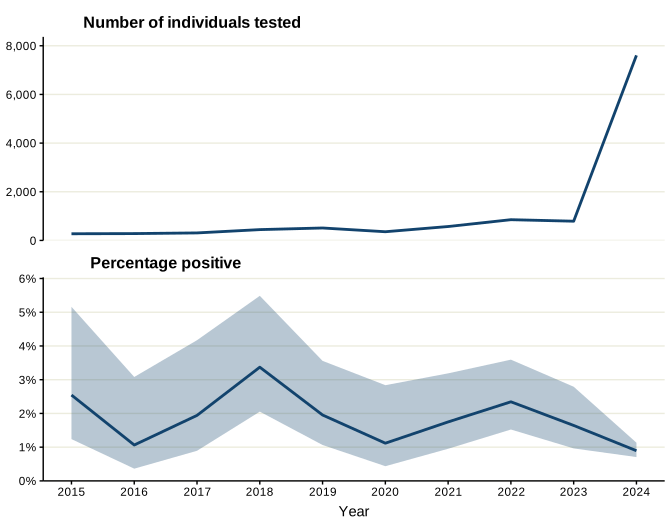
Figure 9. Number of individuals tested for anti-HCV by year and percentage positive, through emergency departments, in sentinel laboratories in West Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 16: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 17: in 2022, a new bloodborne virus (BBV) testing programme was introduced in selected emergency department (ED) sites in areas of very high and high human immunodeficiency virus (HIV) diagnosed prevalence across England. This programme expanded to other areas of high HIV prevalence in the second phase of the implementation of this programme, starting in 2024, however, not all UKHSA regions had participating ED sites within their areas.
Note 18: the error bands represent 95% confidence intervals.
Testing volumes in EDs increased substantially following the introduction and expansion of opt-out bloodborne virus testing programmes, with positivity remaining low in testing within this setting. This increase in testing is likely to have provided opportunities to identify hepatitis C infections among individuals who may not otherwise engage with healthcare services or conventional testing pathways for hepatitis C.
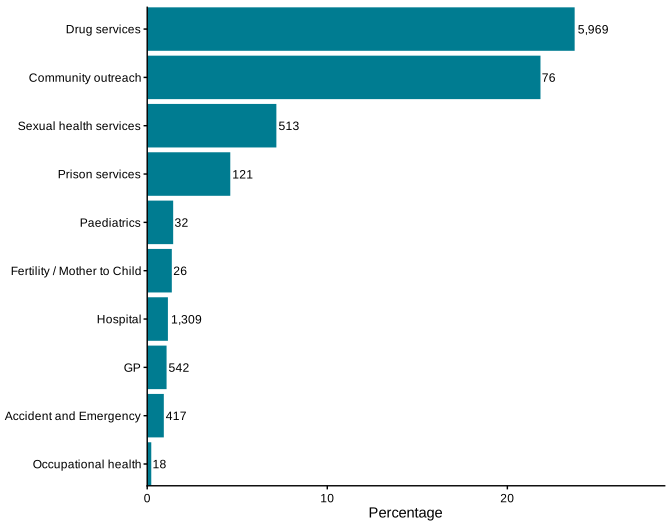
Figure 10. Percentage positivity for anti-HCV tests by setting or reason for test in sentinel laboratories 2020 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Numbers next to bars indicate the number of positive cases in 2020 to 2024.
Note 19: percentage positive is calculated using the number of individuals tested per year per speciality. If an individual has multiple tests in a year across multiple specialities, then they will be counted once per speciality.
For the period of 2020 to 2024, the highest positivity and highest number of positive results identified was observed among people tested through drug services, with 23.7% positivity for tests in drug services and 5,969 positive results. Community outreach testing had the second highest positivity of 21.8%, although this estimate was based on a relatively small number of tests (348).
The highest volume of testing took place in hospital settings, comprising 113,899 tests, with a comparatively lower level of positivity.
Positivity for anti-HCV tests was highest through targeted pathways associated with higher hepatitis C risk. These findings highlight the importance of maintaining testing among populations at increased risk of hepatitis C infection.
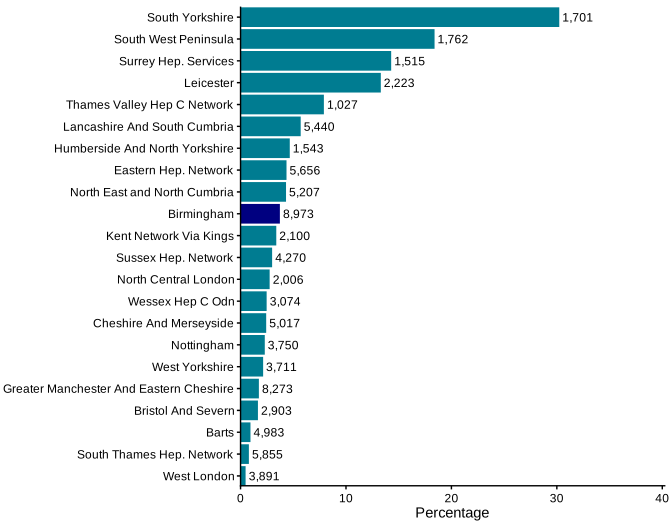
Figure 11. Percentage of individuals testing anti-HCV positive among those tested in sentinel laboratories, by operational delivery network (ODN), 2020 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Numbers next to bars indicate the number of positive cases.
Note 20: ODN boundaries do not fully align with UKHSA regional boundaries, so not all West Midlands residents may be captured within the highlighted bars in the figure above. Bars are highlighted in the above chart based on the region containing the majority of their residents. Consequently, the highlighted bars may include cases from outside the region, and some residents of the West Midlands region may fall into ODNs / highlighted bars associated with other regions.
The percentage of individuals testing anti-HCV positive for Birmingham ODN (3.7%) was the tenth highest amongst all ODNs in England. Birmingham ODN had the fifth highest amount of testing, with 240,535 tests, but had the highest number of positive results, 8,973 in total over this period.
Differences in positivity amongst ODNs are likely to reflect variation in local population characteristics, risk profiles, service provision and testing pathways. These findings demonstrate the importance of developing and implementing local approaches to hepatitis C testing and case finding.
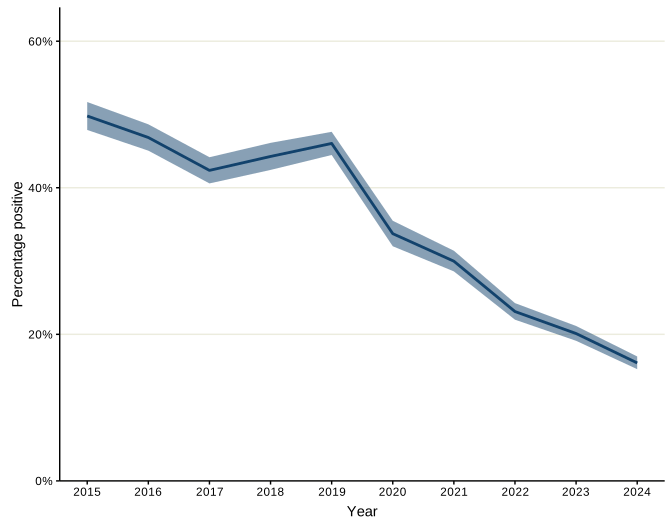
Figure 12. Percentage of individuals tested positive for HCV RNA in sentinel laboratories in West Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
The proportion of individuals testing positive for HCV RNA provides an indication of current hepatitis C infection among those tested. The overall trend suggests a decline in positivity over time, while testing volumes have increased. This pattern is consistent with testing reaching a wider population and with progress in diagnosis and treatment of chronic hepatitis C infection, although changes in the populations tested over time should also be considered.
Figure 13. Percentage of individuals testing HCV RNA positive among those tested in sentinel laboratories, by operational delivery network (ODN), 2020 to 2024
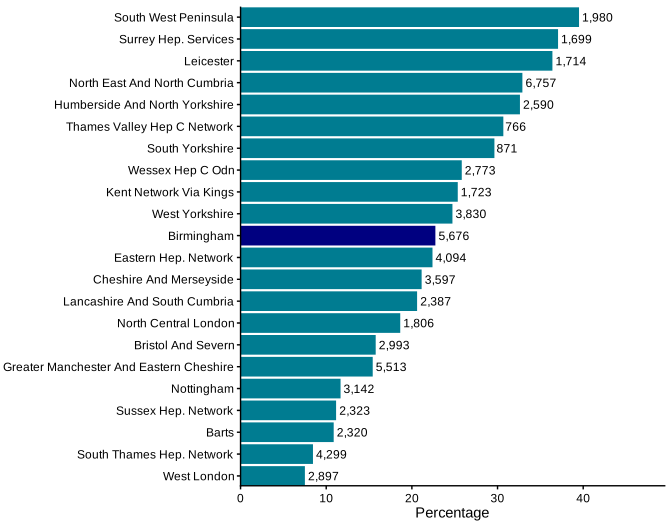
Data source: SSBBV. For more information, see Information on data sources.
Numbers next to bars indicate the number of positive cases.
See note 20.
Birmingham ODN had the 11th highest positivity, 22.7%, identifying the second highest number of RNA positive results, 5,676 during 2020 to 2024 compared to the other ODNs across the country.
Differences in positivity are likely to reflect variation in local testing pathways, case mix and the underlying burden of chronic hepatitis C infection. Results should therefore be interpreted within the context of local service provision and testing coverage.
Testing and diagnosis in people who inject drugs (PWID)
Figure 14. Percentage of Unlinked Anonymous Monitoring (UAM) Survey participants with evidence of ever being infected with HCV (anti-HCV), West Midlands UKHSA region and England, 2015 to 2024
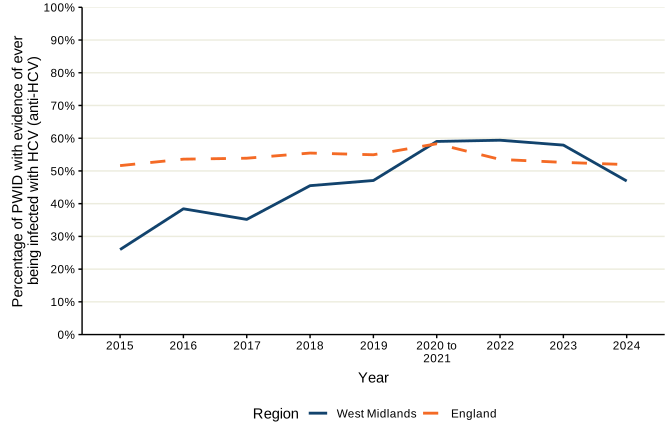
Data sources: UAM Survey. For more information see Information on data sources.
Note 21: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
The proportion of people who inject drugs with evidence of ever having been infected with hepatitis C remained above 50% in England throughout the reporting period. However, in the West Midlands, the percentage rose from 26% in 2015, to 59% in 2020 to 2021, remaining at around this level until 2023, during which time this was higher than the England average, showing a small decline in 2024, 46.9%. This reflects the continuing burden of hepatitis C among people who inject drugs and the need for continued testing and support through treatment where current cases are identified.
Figure 15. Percentage of Unlinked Anonymous Monitoring (UAM) Survey participants ever infected with HCV who have chronic HCV infection, West Midlands UKHSA region and England, 2015 to 2024
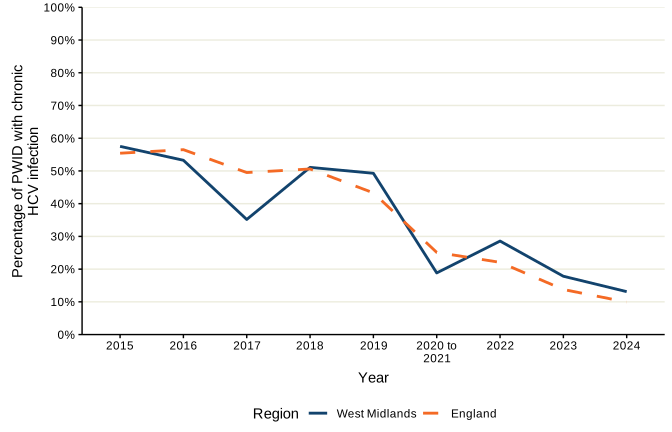
Data sources: UAM Survey. For more information see Information on data sources.
Note 22: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
The prevalence of chronic hepatitis C infection among people who inject drugs provides an indicator influenced by both ongoing transmission and treatment coverage within this population. Overall prevalence has declined over time in the West Midlands, from 57.5% in 2015 to 13.1% in 2024, mirroring national trends (55.4% and 9.9%). This reduction is consistent with increased treatment uptake and progress towards hepatitis C elimination.
Figure 16. Percentage of Unlinked Anonymous Monitoring (UAM) Survey participants who self-reported being recently (current or previous year) tested for HCV, West Midlands UKHSA region and England, 2015 to 2024
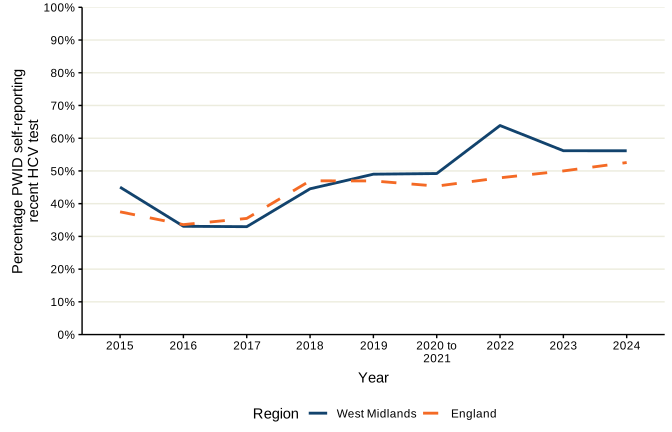
Data sources: UAM Survey. For more information, see Information on data sources.
Note 23: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
Following a small decline in self-reported testing between 2015, 45%, and 2017, 33%, the proportion of people who inject drugs reporting a recent hepatitis C test increased to 56.2% in 2024, and generally followed the pattern observed nationally (37.5% in 2015 and 52.6% in 2024). Maintaining high testing coverage within this population remains important to support timely diagnosis, treatment initiation and prevention of onward transmission.
Hepatitis C treatment pathway
Figure 17. Treatment pathway in West Midlands UKHSA region, 2015 to 2024
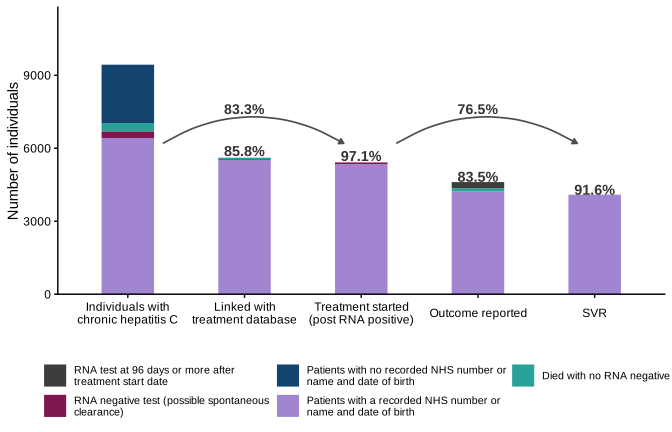
Data source: SSBBV, NHS England (NHSE) Hepatitis C Patient Registry and Treatment Outcome System, NHSE Blueteq System. For more information, see Information on data sources.
Between 2015 and 2024:
- 85.0% of individuals with chronic hepatitis C were linked to treatment
- 97.5% of those linked to treatment had started treatment
- 82.9% of all individuals with chronic hepatitis C had started treatment, meeting the WHO elimination target for treatment coverage (≥80%)
- 93.7% of those who started treatment had a recorded outcome
- 94.1% of those with an outcome recorded achieved sustained virological response (SVR)
Definitions of the numerator and denominator for each metric shown in the treatment pathway are provided in Table 3 of the Technical Notes.
Note 24: in individuals testing hepatitis C virus RNA or core antigen positive with no linkage to the Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System, there are no time restrictions on a subsequent RNA or core antigen negative test after the initial RNA or core antigen positive test. Therefore, these individuals may include those that have spontaneous clearance of their infection or individuals who have cleared infection as a result of treatment but were not linked to the NHSE Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System.
Note 25: in the absence of a reported SVR as a treatment outcome in the NHSE Hepatitis C Patient Registry and Treatment Outcome System, an RNA or core antigen negative test recorded at 96 days or more after the treatment start date in SSBBV was used.
Definitions of the numerator and denominator for each metric shown in the treatment pathway are provided in Table 3 of the Technical Notes.
Treatment pathway by operational delivery network (ODN)
Birmingham ODN
Figure 18. Treatment pathway by operational delivery network (ODN) in Birmingham ODN, 2015 to 2024
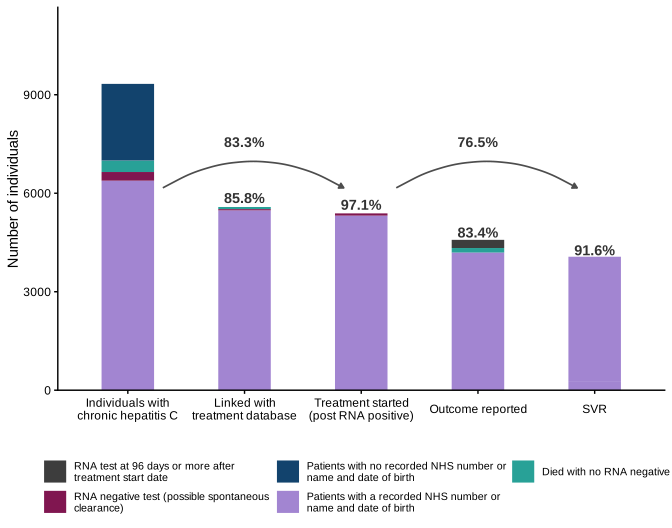
Data source: SSBBV, NHSE Hepatitis C Patient Registry and Treatment Outcome System, NHSE Blueteq System. For more information, see Information on data sources.
See notes 24 and 25.
Note 26: ODN boundaries do not fully align with UKHSA regional boundaries, so not all West Midlands residents may be captured in this chart. ODN charts are presented within this report for the region containing the majority of their residents. Consequently, these charts may include cases from outside the region, and some residents of this region may be in ODNs falling in other regions, and so included in other regions’ reports.
Between 2015 and 2024:
- 85.8% of individuals with chronic hepatitis C were linked to treatment
- 97.1% of those linked to treatment had started treatment
- 83.3% of individuals with chronic hepatitis C had started treatment, meeting the WHO elimination target for treatment coverage (≥80%)
- 83.4% of those who started treatment had a recorded outcome. 91.6% of those with an outcome recorded achieved SVR
- 76.5% of those who started treatment achieved SVR
Definitions of the numerator and denominator for each metric shown in the treatment pathway are provided in Table 3 of the Technical Notes.
West Midlands accounted for 6,423 individuals who tested positive for hepatitis C virus RNA or core antigen with NHS number or name and date of birth reported through SSBBV who had not died before linkage to treatment and where there was no evidence of possible spontaneous clearance. There is one main ODN in the West Midlands, Birmingham ODN, which accounted for 6,383 individuals who tested positive for hepatitis C virus RNA or core antigen with NHS number or name and date of birth reported through SSBBV who had not died before linkage to treatment and where there was no evidence of possible spontaneous clearance.
Achievement of the WHO elimination target for treatment coverage would mean a value equal to or greater than 80% of individuals with chronic hepatitis C starting treatment during a specified time frame. For the West Midlands and Birmingham ODN this was 83.3% meaning the WHO elimination target was achieved between 2015 and 2024, showing good progress is being made in the region.
Birmingham ODN had high proportions of individuals achieving SVR out of those who had started treatment, 76.5%.
There are limitations to this data, as it is not possible to capture where individuals may have restarted treatments, and measure how this affects these data. However, overall, these findings demonstrate high treatment uptake and effectiveness within the West Midlands treatment pathway.
Reinfections in individuals initiating treatment
For people who initiated treatment between 2015 and 2024 in West Midlands, the reinfection rate was 7.7 per 100 person-years (95% CI 7.0 to 8.5), which was higher than the England estimate (6.5 per 100 person-years, 95% CI 6.3 to 6.7). Among those who had injected drugs within the 3 years prior to treatment initiation, the reinfection rate was 9.9 per 100 person-years (95% CI 9.0 to 10.8), which was slightly higher than the England estimate (8.8 per 100 person-years, 95% CI 8.5 to 9.0). For individuals whose last injection was more than 3 years earlier, the rate was 3.2 per 100 person-years (95% CI 2.3 to 4.2), which was slightly lower than the England estimate (4.0 per 100 person-years, 95% CI 3.8 to 4.2). Among people with any history of imprisonment before starting treatment, the reinfection rate was 9.4 per 100 person-years (95% CI 8.1 to 10.9), which was slightly higher than the England estimate (9.4 per 100 person-years, 95% CI 9.0 to 9.7).
Monitoring HCV-related morbidity
Hospital admissions from HCV
Figure 19. Number of first hospital admissions for hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC), West Midlands UKHSA region and England
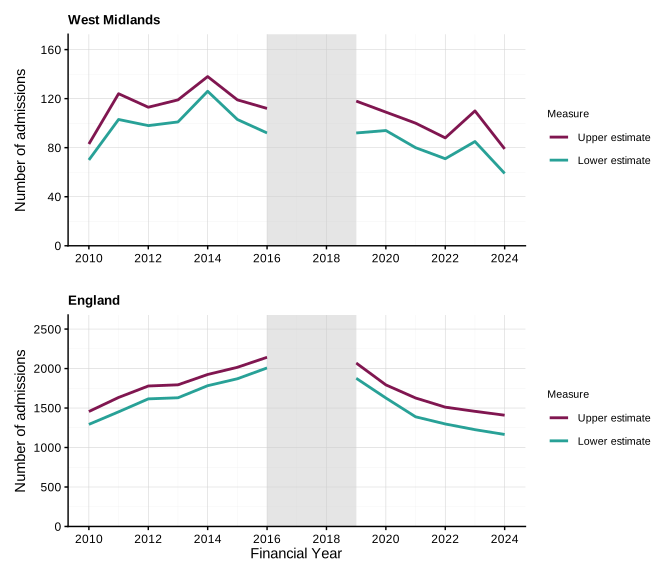
Data source: Hospital Episode Statistics (HES), NHS England. Produced by the UK Health Security Agency. Copyright © 2025, reused with the permission of NHS England. All rights reserved. For more information, see Information on data sources.
Note 27: estimates of incidence of hepatitis C-related ESLD and/or HCC are not available for 2017 and 2018. This is due to an interruption in the supply of identifiers by NHS Trusts in tax year April 2017 to March 2018.
Note 28: data for 2024 is provisional and figures for previous years are subject to change as a result of late reporting and the associated de-duplication procedure.
Note 29: defined by codes or text entries for ascites, bleeding oesophageal varices, hepato-renal syndrome, hepatic encephalopathy, or hepatic failure.
Note 30: data based on HES as of December 2025.
Figure 20. Rate per 100,000 of first hospital admissions for hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC), West Midlands UKHSA region and England
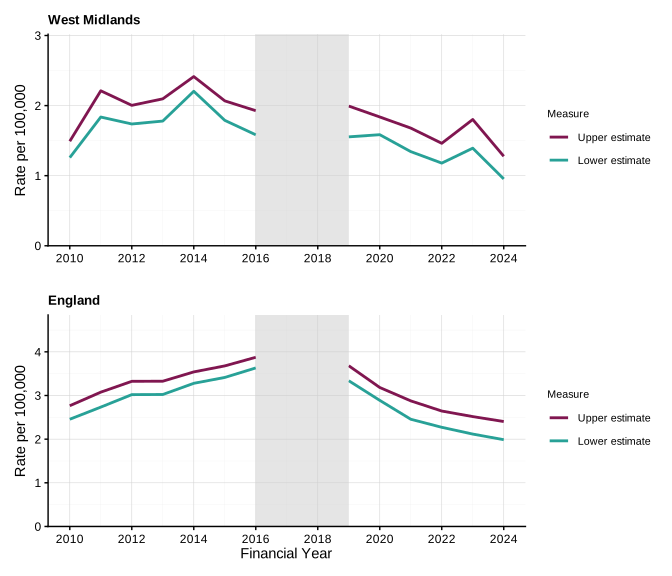
Data source: Hospital Episode Statistics (HES), NHS England. Produced by the UK Health Security Agency. Copyright © 2025, reused with the permission of NHS England. All rights reserved. For more information, see Information on data sources.
Note 31: estimates of incidence of hepatitis C-related ESLD and/or HCC are not available for 2017 and 2018. This is due to an interruption in the supply of identifiers by NHS Trusts in tax year April 2017 to March 2018.
Note 32: data for 2024 is provisional and figures for previous years are subject to change as a result of late reporting and the associated de-duplication procedure.
Note 33: defined by codes or text entries for ascites, bleeding oesophageal varices, hepato-renal syndrome, hepatic encephalopathy, or hepatic failure.
Note 34: data based on HES as of December 2025.
Figure 19 shows the number of first hospital admissions for hepatitis C-related end-stage liver disease and/or hepatocellular carcinoma, which provide a measure of severe disease burden. Generally, in the West Midlands, since 2014 there appears to be a downward trend, from 126 hospital admissions lower bound value and 138 upper bound value in 2014, compared to 2024 where there were 59 and 79 admissions respectively, suggesting a reduction in severe hepatitis C-related morbidity. Trends over time help assess the impact of prevention and treatment programmes.
Figure 20 shows rates of first hospital admissions in the West Midlands and England, with the West Midlands being consistently lower than rates for England. Generally, since 2019 both the West Midlands and England have seen a decrease in rates of first hospital admissions.
HCV-related mortality
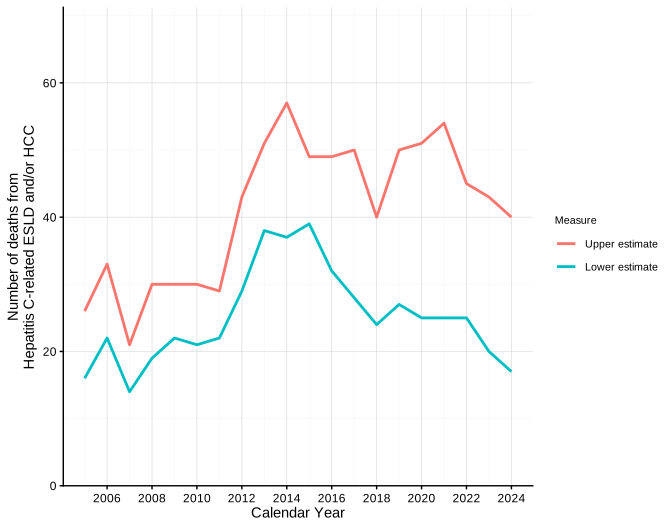
Figure 21. Number of deaths from hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC), West Midlands UKHSA region, 2005 to 2024
Data source: ONS Mortality and ONS MYE. For more information, see Information on data sources.
The number of deaths attributable to hepatitis C-related end-stage liver disease and/or hepatocellular carcinoma in the West Midlands has fluctuated over time, with differences between the lower and upper estimates reflecting uncertainty in attribution. Mortality increased during the early part of the reporting period before declining in more recent years. In 2024, the lower-bound estimate was 17 deaths and the upper-bound estimate was 40 deaths, compared with 39 and 45 deaths respectively in 2015.
The updated methodology provides a more comprehensive assessment of hepatitis C-related mortality through linkage of mortality, hospital admission and laboratory surveillance datasets. Continued monitoring of mortality trends remains important for assessing progress towards reducing the severe consequences of chronic hepatitis C infection.
Figure 22. Mortality rate per 100,000 population for hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC) by UKHSA region, 2020 to 2024

Data source: ONS Mortality and ONS MYE. For more information, see Information on data sources.
The West Midlands had a lower mortality rate (1.1 per 100,000 population) for hepatitis C-related end-stage liver disease and/or hepatocellular carcinoma than England (1.3 per 100,000 population), and below the WHO target of less than or equal to 2 per 100,000 (however, this target is a combined target with hepatitis B).
Regional variation in mortality rates may reflect differences in hepatitis C prevalence, access to healthcare, treatment uptake and demographic factors. The updated upper-estimate methodology provides a more comprehensive assessment of hepatitis C-related mortality than previous approaches.
Prevention of infection by harm reduction
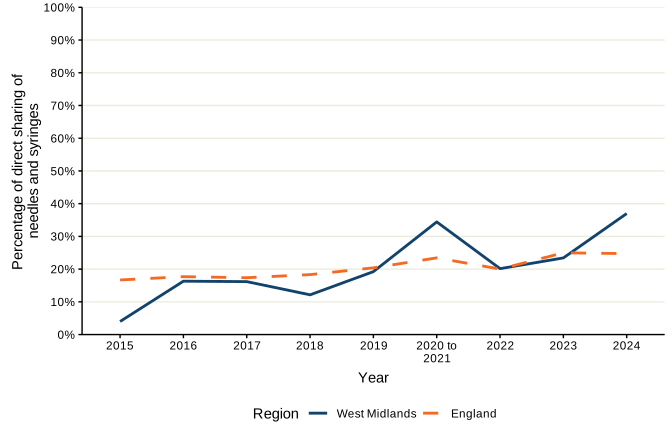
Figure 23. Reported level of direct sharing of needles/syringes among people who inject drugs (PWID), in the preceding 4 weeks, West Midlands UKHSA region and England, 2015 to 2024
Data sources: UAM Survey. For more information, see Information on data sources.
Note 35: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
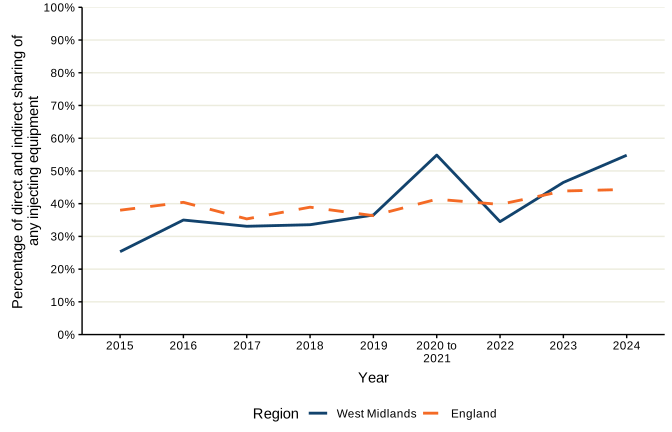
Figure 24. Reported level of direct and indirect sharing of injecting equipment among people who inject drugs (PWID), in the preceding 4 weeks, West Midlands UKHSA region and England, 2015 to 2024
Data sources: UAM Survey. For more information, see Information on data sources.
Note 36: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
Figure 23 shows self-reported levels of direct sharing of needles or syringes amongst PWID, and figure 24 shows levels of both direct and indirect sharing of injecting equipment among PWID. Both graphs are comparing the West Midlands to England. Sharing of injecting equipment remains a key risk factor for hepatitis C transmission, and reducing these behaviours over time continues to be a challenge amongst this risk group.
The levels in the West Midlands have remained similar to those for England from 2015 to 2024, showing a substantial increase over time from 25.3% to 54.8% compared to 38% to 44.4% in England which is of continued concern.
The reported level of direct and indirect sharing of injecting equipment in the West Midlands increased in 2024, increasing above the England level, suggesting further work will be needed to understand the possible reasons for this such as changes in the number of pharmacies providing Needle and Syringe Programmes (NSP).
Information on data sources
Second Generation Surveillance System (SGSS)
Brief description
SGSS captures routine laboratory surveillance data on infectious diseases and antimicrobial resistance from laboratories within England. Along with a number of other organisms, hepatitis C is notifiable under the Health Protection (Notifications) Regulations (2010).
Technical notes
Laboratory reports of new diagnoses of HCV include positive test results for anti-HCV and HCV-RNA tests and are submitted to UKHSA or predecessor organisations via SGSS/CoSurv.
Data is assigned to local authority and UKHSA region by patient postcode where present, if patient postcode is unknown, data is assigned to local authority and UKHSA region of registered general practice; where both patient postcode and registered general practice are unknown data is assigned to local authority and UKHSA region of laboratory.
Dates are assigned based on earliest positive specimen date. Patient identifiable data submitted by NHS laboratories is variable, particularly from sexual health and drug and alcohol services, which limits the ability to deduplicate.
Laboratory reports for children under 1 year of age are excluded from the analyses to rule out detecting maternal antibody. Rates per 100,000 have been calculated using mid-year population estimates (MYE) supplied by the Office for National Statistics (ONS).
Caveat: SGSS data in this report may differ from data shown in the Hepatitis C in England report and from data reported in other surveillance outputs at a different point in time. This is due to the SGSS dataset being a live system and a number of cleaning, deduplication, remapping and other operational processes being routinely applied to the data to improve data quality.
Data extracted from Sentinel Surveillance of bloodborne virus testing (SSBBV) and SGSS will vary for several reasons and should not be compared: the 2 systems have collected data over different historical periods, with data reported to SGSS and predecessor systems since 1995, whereas SSBBV has been running since 2002. Data reported to SSBBV reflects the timeframe from when the laboratory joined the surveillance system, with laboratories joining more recently having less data available than laboratories who have been reporting since 2002. Furthermore, whilst SGSS collects national level data, SSBBV collects data from a subset of laboratories. Currently, 35 laboratories report to SSBBV with an estimated 45% coverage testing in the GP registered population in England.
Finally, it is not possible to differentiate a previous or current infection in SGSS with limited HCV RNA or HCV Ag data available, therefore numbers presented will be a mixture of previous and current infections. However, SSBBV allows for the collection of all HCV markers enabling HCV antibody and HCV RNA or HCV Ag to be presented separately.
Sentinel Surveillance of Bloodborne Viruses (SSBBV)
Brief description
SSBBV is a sub-national surveillance system for BBV testing activity and results in England, managed by UKHSA. Established in 2002, it includes data on all positive and negative BBV tests processed by the sentinel laboratories that participate in SSBBV. Laboratory participation in SSBBV is voluntary and currently represents approximately 45% of the GP registered population in England. SSBBV includes the 2 laboratories that process DBS tests for the major drug services in England. Therefore, it is likely that the data covers most tests coming from drug services, where DBS is the main method of testing.
Technical notes
Patient identifiable data submitted by laboratories is variable, particularly from sexual health and drug and alcohol services, which limits the ability to de-duplicate. Data is de-duplicated subject to availability of date of birth, Soundex, NHS number and first initial. The proportion positive is calculated using the number of people tested.
For trends in hepatitis C antibody testing, SSBBV data is from 35 laboratories and is based on complete and consistent reporting since 2015 to remove any artificial increases or decreases in testing due to changes in reporting. This
means that the numbers of laboratories included for trend data may change each year depending on their reporting history. A positive test result first reported by participating laboratories may not reflect an individual’s first diagnosis.
Antibody testing excludes samples collected outside routine testing such as look back studies, reference testing, and children aged one year and under, whereas RNA or core antigen testing includes reference testing.
Reinfection
In England, 2 criteria have been used to identify hepatitis C virus reinfection, either of which would establish a person as experiencing reinfection:
- individuals with a positive hepatitis C virus RNA test at least 196 days (28 weeks) after treatment start date among those with a SVR during their first treatment period
- individuals who have a subsequent period of treatment after an initial SVR, and where this subsequent treatment period was at least 196 days after first treatment start date
For both definitions SVR is defined as either a recorded SVR or proxy SVR from a negative RNA or core antigen result after treatment. A period of 196 days between first treatment and reinfection diagnosis is used to define reinfection as the majority of individuals receiving treatment will have cleared hepatitis C virus within 6 months (182 days). A further 2 weeks (14 days) is added to account for any delays in treatment initiations. Reinfection after spontaneous clearance is not included.
The estimate now includes multiple reinfections, whereby someone is treated after experiencing their first reinfection and achieves an SVR but then has a subsequent hepatitis C virus RNA or core antigen positive result. The data is reliant upon persons initiating treatment being added to the NHSE Blueteq System or NHSE Hepatitis C Patient Registry and Treatment Outcome System, sufficient identifiers being available to link between the treatment and SSBBV databases and on people being tested post treatment. It should be noted that there is no internationally agreed definition for defining hepatitis C reinfection and a different window period may be used to confirm SVR post treatment. For example, Scotland uses a negative test between 10 weeks and 12 months post treatment to confirm SVR. As we progress towards elimination of hepatitis C virus as a public health threat, ongoing work across the UK will aim to harmonise definitions of reinfection where possible and utilise multiple methods, including the use of whole genome sequencing, to better understand reinfection.
Hospital Episode Statistics (HES)
Brief description
New cases of hepatitis C-related ESLD and/or HCC are monitored using HES for incidence of ESLD and HCC, and HES and SGSS for hepatitis C diagnoses. This is a new method in 2025 which presents data as a sensitivity analysis with upper and lower bounds, mirroring the updated methodology for deaths from hepatitis C-related ESLD and/or HCC. New cases are identified by first linking all episodes of ESLD and/or HCC in HES for an individual using their unique patient identifier. These are classified as ‘new’ if no previous episodes of ESLD and/or HCC for that individual are found in at least the previous 5 years (less than 1% of HCC and/or ESLD episodes are estimated to have had a previous episode more than 5 years earlier).
Linkage to hepatitis C diagnoses uses the following 2 methods:
- Lower bound: linkage to episode of hepatitis C in HES for all years: first diagnosis of ESLD and/or HCC linked to hepatitis C diagnosis in HES for any year. First diagnosis of ESLD and/or HCC used data from 2003 to 2024 to give minimum 5-year window for first episode starting at 2010. Hepatitis C diagnosis started from 1 April 2000 onwards. Hepatitis C includes both acute and chronic cases.
- Upper bound: linkage to diagnoses of hepatitis C in HES or surveillance data for all years: first diagnosis of ESLD and/or HCC linked to earliest diagnosis of hepatitis C in any of HES or SGSS.
Due to the loss of identifiers in HES data for 2017, data for 2017 and 2018 is omitted.
More information is available in the Appendix 3 of Hepatitis C in England 2022.
Hepatitis C Treatment Pathway data
Brief description
Hepatitis C treatment initiation data is used to monitor access to hepatitis C treatment. Treatment coverage is defined as the proportion of individuals diagnosed with chronic hepatitis C (hepatitis C virus RNA or hepatitis C core antigen test positive) and who initiated treatment during a specified time frame over the number of individuals diagnosed with chronic hepatitis C for the specified time period.
Technical notes
Records from individuals with a diagnosis of chronic hepatitis C reported through SSBBV (positive hepatitis C virus RNA or antigen tests) are linked to the NHSE Hepatitis C Patient Registry and Treatment Outcome System using NHS number, name, DOB, hospital number and NHSE’s Blueteq System using NHS number, DOB, Blueteq number and excludes children aged under one year.
Patient identifiable data submitted by SSBBV laboratories is variable, particularly from sexual health and drug and alcohol services, which limits the ability to link data sets or de-duplicate. Data is de-duplicated subject to availability of DOB, Soundex, NHS number and first initial. Data quality is assessed on an ongoing basis to verify the number of people who tested positive for hepatitis C virus RNA or core antigen. As individuals are followed through the care pathway, the denominator is updated to exclude people who have died or who have evidence of spontaneous clearance.
In individuals testing hepatitis C virus RNA or core antigen positive with no linkage to the Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System, there are no time restrictions on a subsequent hepatitis C virus RNA or core antigen negative test after the initial RNA or core antigen positive test. Therefore, these individuals may include those that have spontaneous clearance of their hepatitis C virus infection or individuals who have cleared their hepatitis C virus infection as a result of treatment but were not linked to the NHSE Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System.
The NHSE Hepatitis C Patient Registry and Treatment Outcome System was commissioned by NHSE in 2017 from the Arden and Greater East Midlands Commissioning Support Unit to capture more detailed information for patients. The hepatitis C virus treatment monitoring in England report summarises the data held within the registry and Treatment Outcome System up to the end of April 2018.
Table 3. Definitions of the numerator and denominator for metrics reported in the hepatitis C treatment pathway
| Metric | Numerator | Denominator |
|---|---|---|
| Proportion of individuals diagnosed with chronic hepatitis C who were linked to specialist treatment services | Number of individuals linked to specialist hepatitis C treatment services via ODNs (identified through successful linkage to the NHSE Hepatitis C Patient Registry and Treatment Outcome System and/or NHSE’s Blueteq System). | Number of individuals who tested positive for hepatitis C virus RNA or core antigen with NHS number or name and date of birth (DOB) reported through SSBBV who had not died before linkage to treatment and where there was no evidence of possible spontaneous clearance. |
| Proportion of individuals linked to specialist treatment services who initiated treatment | Number starting treatment. | Number of individuals linked to specialist hepatitis C treatment services via ODNs. |
| Proportion of individuals diagnosed with chronic hepatitis C who initiated treatment (WHO target) | Number starting treatment. | Number of individuals who tested positive for hepatitis C virus RNA or core antigen with NHS number or name and DOB reported through SSBBV who had not died before linkage to treatment and where there was no evidence of possible spontaneous clearance. |
| Proportion of individuals who initiated treatment who had an outcome reported or had an RNA or core antigen test reported through SSBBV | Number of individuals who had a treatment outcome reported via the NHSE Hepatitis C Patient Registry and Treatment Outcome System, or in the absence of a recorded outcome, an RNA or core antigen test (positive or negative) recorded at 96 days or more after the treatment start date in SSBBV. | Number of individuals who started treatment. |
| Proportion of individuals who initiated treatment and were reported to have achieved SVR either as a treatment outcome or had an RNA or core antigen negative result reported through SSBBV | Number clearing hepatitis C virus as a treatment outcome, or in the absence of a reported SVR, an RNA or core antigen negative test recorded at 96 days or more after the treatment start date in SSBBV. The proportion reported as clearing hepatitis C virus is likely to be lower than the true proportion. | Number starting treatment. |
| Proportion of individuals who initiated treatment and had an outcome reported or an RNA or core antigen test reported through SSBBV who were reported to have achieved SVR or had an RNA or core antigen negative test result | Number clearing hepatitis C virus as a treatment outcome, or in the absence of a reported SVR, an RNA or core antigen negative test recorded at 96 days or more after the treatment start date in SSBBV. | Number of individuals with a treatment outcome recorded or with an RNA or core antigen test (positive or negative) recorded at 96 days or more after the treatment start date in SSBBV. |
Office for National Statistics (ONS) Mortality data
Brief description
The number of hepatitis C virus-related deaths are used to measure mortality. Deaths are based on the year of death. International classification of diseases (ICD) tenth revision (ICD-10) codes for ESLD and HCC are used to identify deaths with ESLD or HCC as a cause or associated with hospital admissions for these conditions. The number of deaths was estimated using slightly different ICD-10 codes from those used by WHO. A comparison of the codes used can be found in the Hepatitis C in England 2022 report.
Technical notes
An updated method for estimating deaths from hepatitis C-related ESLD and/or HCC has been used for this report. The previous method of reporting that solely used death data from the Office for National Statistics (ONS) was shown to underestimate mortality rates from hepatitis C-related liver disease by up to 60%. To address this, an updated method is used that presents the estimated mortality attributable to hepatitis C as a range. The lower bound of this range is similar to the previous methodology using only ONS death registration data, while the upper bound uses ONS death registration data linked to data on hospital episode statistics (HES) data on viral hepatitis, ESLD and/or HCC and laboratory data on viral hepatitis diagnoses. The updated methodology has been applied to all previous years and includes deaths by year of death rather than by year the death was registered as was previously used.
Lower bound represents deaths where ESLD and/or HCC and hepatitis C were reported in ONS death registration data (as year of death is now used this is not comparable with previously published estimates which used year the death was registered). Upper bound represents deaths where ESLD and/or HCC were reported in ONS death registrations or identified in HES hospital admissions data linked to deaths data, and hepatitis C diagnoses were identified by linking between ONS deaths, HES hospital admissions data and laboratory diagnosis data to yield a maximum number of deaths attributable to hepatitis C-related ESLD and/or HCC. Excluding deaths of people aged under 16 and deaths registered in England where the deceased’s usual residence is outside England. ESLD is defined by codes or text entries for ascites, bleeding oesophageal varices, hepato-renal syndrome, hepatic encephalopathy, or hepatic failure.
Unlinked Anonymous Monitoring (UAM)
Brief description
The voluntary UAM Survey recruits people who have ever injected psychoactive drugs through specialist services (such as needle and syringe programmes and addiction treatment centres) across England, Wales and Northern Ireland. Those who agree to take part self-complete a questionnaire and provide a biological specimen that is tested anonymously for HIV, hepatitis B and hepatitis C.
Technical notes
Regional level data from the UAM Survey should be interpreted cautiously as the survey recruits participants through a nationally reflective sample of the services provided to people who inject drugs.
The COVID-19 pandemic, and associated changes in service delivery, impacted on recruitment to the survey in 2020 and 2021. By 2022, the number of services taking part in the survey, and the number of participants was comparable to pre-pandemic levels.
Published regional-level data and more information can be found at People who inject drugs: HIV and viral hepatitis monitoring.
Acknowledgements
We would like to thank the following:
- local laboratories for supplying the hepatitis data
- the UKHSA Blood Safety, Hepatitis, STI and HIV Division for collection, analysis and distribution of data
- the UKHSA Epidemiology Data Science unit (part of the Epidemiology Data Science team) for producing the charts and figures contained in this report
- the Office for National Statistics (ONS), which carried out the original collection and collation of the mid-year population estimates, death registration data and geographic boundary data but bears no responsibility for their future analysis or interpretation)
- the Hospital Episode Statistics (HES), NHS England, produced by UKHSA
About Field Services
Field Services is a division within UKHSA that provides a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Public Health Microbiology, Rapid Investigation, Real-time Syndromic Surveillance, Field Epidemiology Training, and Data Science to strengthen the surveillance, epidemiological intelligence and response functions of UKHSA.
You can contact your local Field Services team at FSMidlands@ukhsa.gov.uk
If you have any comments or feedback regarding this report or the Field Services, please contact FS.Central@ukhsa.gov.uk