Chapter 4. Tuberculosis treatment and outcomes, England, 2025
Published 29 October 2026
Applies to England

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/tuberculosis-in-england-2026-report/chapter-4-tuberculosis-treatment-and-outcomes-england-2025
Main messages
In 2025:
- the time between onset of symptoms and start of treatment has remained static over the past five years, with approximately a third of individuals with infectious TB experiencing a delay of more than 4 months before starting treatment and just under a third a delay of between 2 to 4 months
- observed therapy, which includes either directly observed therapy (DOT) or video observed therapy (VOT), supporting treatment completion in individuals with more complex needs, was offered to 13.1% and 8.0% of people, respectively, with uptake of just over 50% for both
- there were regional differences in the proportions of people offered DOT or VOT and in their uptake which may reflect inequalities in access and funding
- treatment outcomes at 12 months for individuals notified in 2024, expected to have completed treatment by the end of 2025, were consistent with previous years, with 84.8% completing treatment and 2.9% having died, the remainder being lost to follow up, no outcome recorded or treatment stopped
- treatment completion was lower for individuals with social risk factors (78.3%) compared with those without (86.0%), consistent with previous years
- in people treated for non-MDR (multi-drug resistant) or RR (rifampicin resistant) TB with an expected standard treatment duration of 6 months, only 41.4% completed within 6 months, unchanged from previous years
- in people treated for MDR-TB, the proportion who completed treatment within the expected 24 months has increased to 80.4% for people notified in 2023 from 50.7% for people notified in 2014, likely due to the introduction of shorter MDR treatment regimens
- a total of 212 deaths were recorded for people notified in 2024 in the entire non drug-resistant treatment cohort (3.9%); 16.5% of these were diagnosed with TB after death, whilst a further 9.4% died before TB treatment was started, both of which were increased compared with people notified over the period 2020 to 2023.
Supplementary tables
The data behind the charts in this chapter can be found in the accompanying spreadsheet, which is available to download.
Treatment delay in people notified with pulmonary TB
Treatment delay is defined as the period from the start of symptoms (as reported by the patient) and the start of TB treatment. Diagnostic delay is the period from the start of symptoms to diagnosis. In 2025 the median period between diagnosis and starting treatment was one day (interquartile range 0 to 3 days). This has remained stable over recent years (see Supplementary Table 1 in the accompanying spreadsheet).
In this chapter we report overall treatment delay and risk factors for treatment delay.
Table 1 presents data on the proportion of people notified with pulmonary TB with delay from symptom onset to treatment start of between 2 to 4 months and more than 4 months from 2021 to 2025.
Treatment delays have not reduced in the last five years, with nearly a third of individuals with infectious TB still experiencing a delay of more than 4 months and just under a third a delay of between 2 to 4 months in 2025.However, the proportion of people with very long delays of more than 6 months has decreased to 16.7% in 2025 from a peak of 19.4% in 2021 (Supplementary Table 2 in the accompanying spreadsheet)
Table 1. Number and proportion of people with treatment delay notified with pulmonary TB in 2021 to 2025, England, 2025
| Year | 0 to 2 months (number) | 0 to 2 months (percentage) | 2 to 4 months (number) | 2 to 4 months (percentage) | Over 4 months (number) | Over 4 months (percentage) | Total included (number) |
|---|---|---|---|---|---|---|---|
| 2021 | 742 | 37.6 | 601 | 30.4 | 633 | 32.0 | 1,976 |
| 2022 | 738 | 37.8 | 620 | 31.7 | 596 | 30.5 | 1,954 |
| 2023 | 854 | 39.8 | 650 | 30.3 | 644 | 30.0 | 2,148 |
| 2024 | 961 | 40.4 | 737 | 31.0 | 683 | 28.7 | 2,381 |
| 2025 | 868 | 39.0 | 685 | 30.8 | 673 | 30.2 | 2,226 |
Notes to Table 1
1. Delays of ‘2 to 4 months’ includes delays between 61 to 121 days, and ‘over 4 months’ includes delays from 122 to 730 days.
2. Excludes people diagnosed with TB at post-mortem (132), those with delays over 2 years (154), and those with missing data for either start of symptoms (1,974) or treatment start date (353) or negative values (3).
3. The total includes the number of people with pulmonary TB for whom time between symptom onset to treatment start was known.
Factors associated with treatment delay in pulmonary TB
Further data for the proportion of people notified with pulmonary TB experiencing treatment delay is presented in the accompanying spreadsheet:
- by UKHSA region from 2016 to 2025 in Supplementary Table 2 in the accompanying spreadsheet
- by upper-tier level local authority averaged from 2023 to 2025 in Supplementary Table 3 in the accompanying spreadsheet
- by place of birth (UK or non-UK born) from 2016 to 2025 in Supplementary Table 4 in the accompanying spreadsheet
There is considerable variation by upper-tier local authority in treatment delay. Averaged over the period 2023 to 2025, and excluding those with fewer than 5 notifications, 22 out of 143 (15.4%) upper tier local authorities had more than 45% patients experiencing treatment delay (4 months or more) and 8 (5.6%) had less than 15% of patients experiencing treatment delay. Treatment delays were higher in the UK born population in 2025 (35.0% with delay over 4 months) than those born outside the UK (28.9%).
As shown in Figure 1 below, people aged over 65 had approximately a 30% increased risk of treatment delay compared with people aged 15 to 44 years and those born in the UK had a 26% increased risk. Males likely had a small decreased risk of treatment delay compared with females.
Figure 1. Predictors of treatment delays of over 4 months in people notified with pulmonary TB, England 2023 to 2025 (aggregated data, univariable analysis)
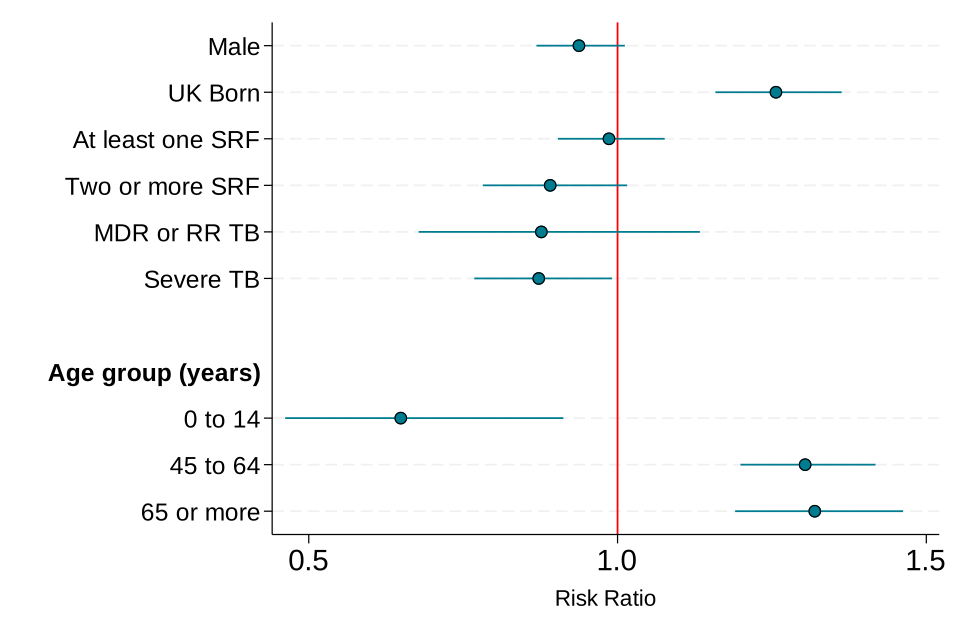
Note: reference groups for RRs in the order presented in the above figure are: female, born outside of the UK, no SRFs recorded, not treated for MDR or RR TB, non-severe (TB with no known or potential central nervous system involvement) and aged 15 to 44 years old.
Data for all potential predictors tested for an association with treatment delay of 4 months or more are shown in Supplementary Table 5 in the accompanying spreadsheet.
Enhanced support including directly observed therapy (DOT) and video observed therapy (VOT) for people undergoing TB treatment
Enhanced case management (ECM)
The 2022 joint case management tool provides standardised recommendations for enhanced case management (ECM) in individuals receiving anti-TB treatment with clinical and/or social complexities. Where there are social risk factors (SRF) or multidrug or rifampicin-resistant TB (MDR or RR TB), the case may be deemed ECM level 3 and require DOT/VOT, following National Institute of Health and Care Excellence (NICE) guidelines:
- ECM level 1: people with clinical and/or social issues which impact on treatment, for example, children with TB, or those taking antiretrovirals
- ECM level 2: people with complex clinical and/or social issues which impact on treatment, for example, complex side effects or single drug resistance, which may necessitate weekly visits
- ECM level 3: people with very complex clinical and or social issues which impact on treatment, for example, social risk factors (SRFs) or MDR or RR TB which necessitates DOT/VOT
Table 2 shows levels of ECM by year. In 2025, 2,444 people notified with TB (45.1%) were assessed as needing some level of ECM, similar to the previous 2 years.
Table 2. Enhanced case management (ECM) by year, England, 2021 to 2025
| Year | Total (number) | Any ECM (number) | Any ECM (percentage) | Level 1 (number) | Level 1 (percentage) | Level 2 (number) | Level 2 (percentage) | Level 3 (number) | Level 3 (percentage) | Unknown level (number) | Unknown level (percentage) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| 2021 | 4,356 | 1,600 | 36.7 | 440 | 10.1 | 390 | 9.0 | 638 | 14.6 | 132 | 3.0 |
| 2022 | 4,332 | 1,947 | 44.9 | 688 | 15.9 | 539 | 12.4 | 706 | 16.3 | 14 | 0.3 |
| 2023 | 4,796 | 2,243 | 46.8 | 743 | 15.5 | 641 | 13.4 | 850 | 17.7 | 9 | 0.2 |
| 2024 | 5,450 | 2,766 | 50.8 | 925 | 17.0 | 790 | 14.5 | 1,039 | 19.1 | 12 | 0.2 |
| 2025 | 5,415 | 2,444 | 45.1 | 872 | 16.1 | 663 | 12.2 | 892 | 16.5 | 17 | 0.3 |
Note: people diagnosed with TB post-mortem are excluded from this analysis.
Proportions needing ECM are reported in the accompanying spreadsheet:
- by UKHSA region in 2025 in Supplementary Table 6 in the accompanying spreadsheet
- by demographic characteristics in 2025 in Supplementary Table 7 in the accompanying spreadsheet
As shown in Figure 2 below, people with social risk factors were nearly twice as likely to be identified as needing ECM (any level). Compared with the recommendation that all children should receive some level of ECM, from 2023 to 2025 only 94.2% of children aged 14 years or less were recorded as needing ECM.
Figure 2. Predictors of identified need of enhanced case management (ECM), of any level, England, notified in 2023 to 2025 (aggregated data, univariable analysis)
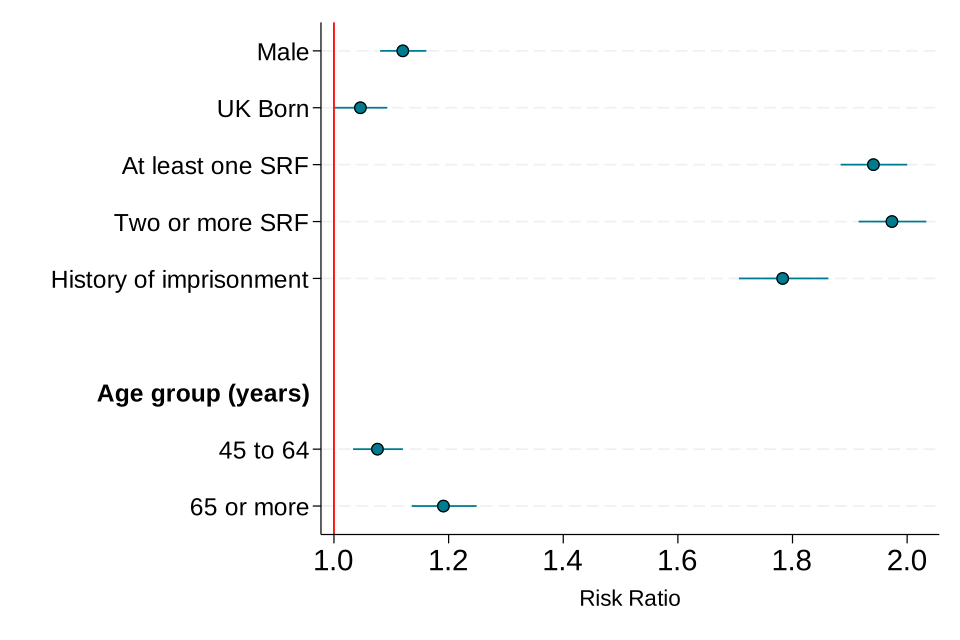
Note: reference groups for RRs in the order presented in Figure 2 are: female; not born in the UK; no SRFs recorded; less than 2 SRF factors recorded; no history of imprisonment in those with data recorded; and aged 15 to 44 years old.
Data for all potential predictors tested for an association with an identified need for ECM is shown in Supplementary Table 8 in the accompanying spreadsheet.
Directly observed and video observed therapy (DOT/VOT)
NTBS records if people are thought to need ECM, but not if they received that care. In contrast, the recording of whether DOT (or more recently also VOT) includes if it was offered and if was received. VOT was introduced as a category to NTBS in 2025.
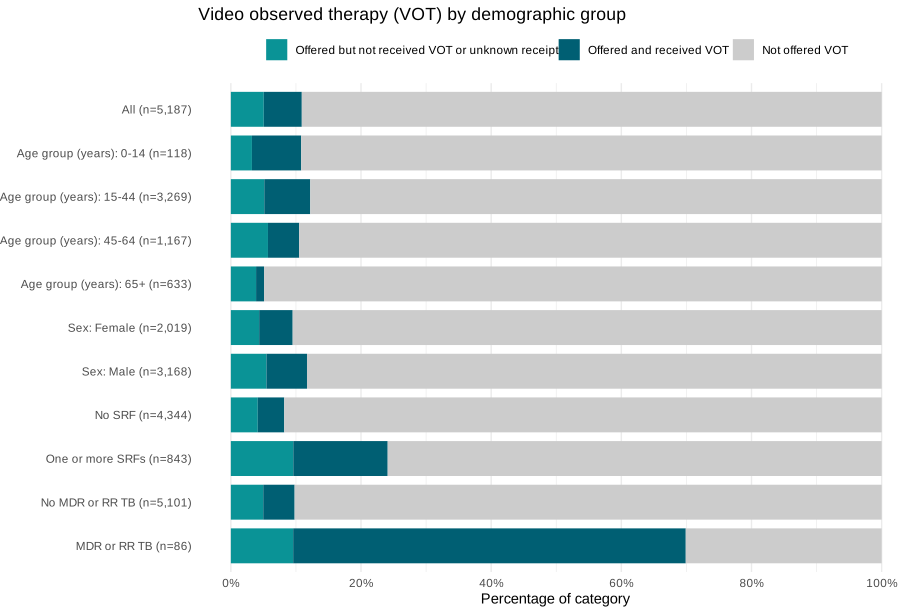
In 2025 data regarding if DOT or VOT was offered or not was complete for 96.1% of all TB notifications that were not diagnosed post-mortem (5,202 out of 5,415), DOT was recorded as being offered to 13.7% of people (711 out of 5,187), of whom 52.3% were recorded as having received it (Figure 3A). VOT was recorded as being offered to 10.8% (431 out of 3,960) of whom 53.6% were recorded as having received it (Figure 3B).
Figure 3A. Proportion of people offered and received DOT, England, 2025
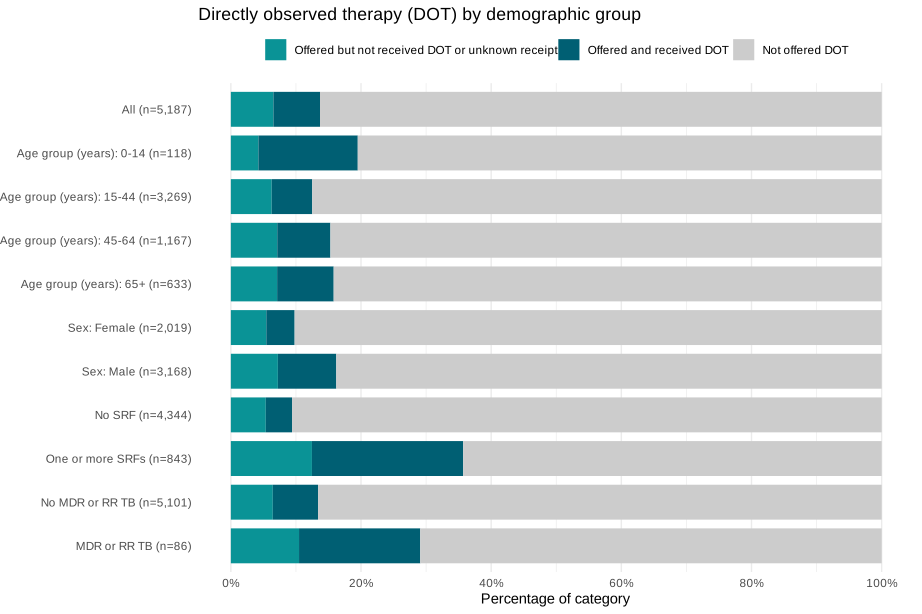
Figure 3B. Proportion of people offered and received VOT, England, 2025
Data used in these figures can be seen in Supplementary Table 9 in the accompanying spreadsheet.
Notes:
- people with unknown information if DOT or VOT was offered were excluded (228 and 1,455 respectively)
- people who were diagnosed postmortem were excluded (34)
Data on DOT and VOT is presented for 2021 to 2025 in Supplementary Table 10 in the accompanying spreadsheet.
In 2025, DOT and VOT were offered more frequently to people with one or more social risk factors (35.6% & 24.0%) or treated with a drug-resistant TB regimen (29.1% and 59.3%) and DOT to children aged 14 or less (19.5%) (Figure 3A& B). Uptake of DOT ranged from 78% in children to 42.9% in girls and women, whilst uptake of VOT ranged from 86.3% in people treated with a drug-resistant TB regimen to 24.0% in older people (Figure 3A and 3B and Supplementary Table 9 in the accompanying spreadsheet).
There was also regional variation in the proportion of people who were offered DOT with the highest proportions in West Midlands (22.4%) and London (20.3%) and lowest in the South West (3.8%). Uptake of DOT was over 80% in 2 regions (South East, and North East) and less than 40% in the West Midlands and North West (see Supplementary Table 9 in in the accompanying spreadsheet). Similarly, VOT was offered most frequently in London (13.5%) and the West Midlands (11.2%), and least in the North East (1.8%) and Yorkshire and the Humber (1.9%) (see Supplementary Table 9).
TB treatment outcomes in the non-MDR or non-RR TB cohort (without central nervous system (CNS) disease)
Treatment outcomes at 12 months and last recorded treatment outcome for people notified in 2024
Treatment outcomes are reported according to the year of notification. For people treated for non-MDR or non-RR TB, outcomes are reported for those notified up to and including 2024 as that is the latest year of notifications for whom treatment completion is expected within the 2025 data. For people treated for MDR or RR TB, outcomes are reported for those notified up to and including 2023. For further definitions of TB treatment cohorts please see the Methodology and definitions chapter
Mutually exclusive treatment outcome categories are shown in Table 3 below for people treated for non-MDR or non-RR TB without CNS disease notified in 2024, by 12 months since start of treatment:
- 84.8% had completed treatment
- 2.9% had died
- 4.8% were lost to follow up
- 2.6% were still on treatment
- 1.7% had stopped treatment
Table 3. Treatment outcome at 12 months and last recorded outcome for people notified in 2024 treated for non-MDR or non-RR TB with expected treatment duration less than 12 months, England, 2025
| TB treatment outcomes | TB treatment outcome at 12 months (number) | TB treatment outcome at 12 months (percentage) | Last recorded TB treatment outcome (number) | Last recorded TB treatment outcome (percentage) |
|---|---|---|---|---|
| Treatment completed | 4,068 | 84.8 | 4,216 | 87.9 |
| Died | 138 | 2.9 | 138 | 2.9 |
| Lost to follow-up | 228 | 4.8 | 234 | 4.9 |
| Still on treatment | 123 | 2.6 | 23 | 0.5 |
| Stopped | 83 | 1.7 | 85 | 1.8 |
| Not evaluated | 158 | 3.3 | 102 | 2.1 |
| Total | 4,798 | 100.0 | 4,798 | 100.0 |
Note: excludes those with post-mortem diagnosis, those with CNS TB and those treated with an MDR or RR TB regimen.
Treatment completion increased to 87.9% for last recorded treatment outcome. Twelve-month TB treatment outcomes for this cohort for notifications from 2015 to 2024 are shown in Supplementary Table 11 in the accompanying spreadsheet.
Of those notified in 2024 and reported to still be on treatment at 12 months (123 people, Table 3), 97 (78.9%) subsequently completed treatment as their last recorded outcome. At the time of data close, 22 (17.9%) were still on treatment, 2 (1.6%) were lost to follow-up, and 2 (1.63%) of people had had their treatment stopped. Of those notified in 2024 and reported as not evaluated at 12 months (158), 51 (32.3%) were subsequently reported as treatment completed, 4 (2.5%) were lost to follow-up, 1 (0.6%) was still on treatment and the rest remained as non-evaluated (102, 64.6%). Last recorded treatment outcomes for this cohort notified from 2015 to 2024 are shown in Supplementary Table 12 in the accompanying spreadsheet.
For the above cohort notified in 2024 the 12-month TB treatment completion rate is similar to the previous ten years at 84.8% (range 84.9% to 86.4%). Treatment completion at the last recorded outcome was lower at 87.9% compared with previous ten years (range of 89.6% to 90.8%), but this is expected to increase after more months of follow-up (see Supplementary Table 12).
Treatment completion in those with and without a social risk factor
In 2025, 12-month TB treatment completion in people notified in 2024 treated for non-MDR or RR TB and expected to complete within 12 months with one or more SRFs was 78.3%, significantly lower than in those without a SRF (86.0%, p less than 0.001) and was also lower at last recorded treatment outcome. There have been no improvements in treatment completion in people with SRFs over the last 5 years (Figure 4)
Figure 4. Proportion of people treated for non-MDR or non-RR TB notified in 2020 to 2024 with treatment completion at 12 months or last recorded outcome, England 2025
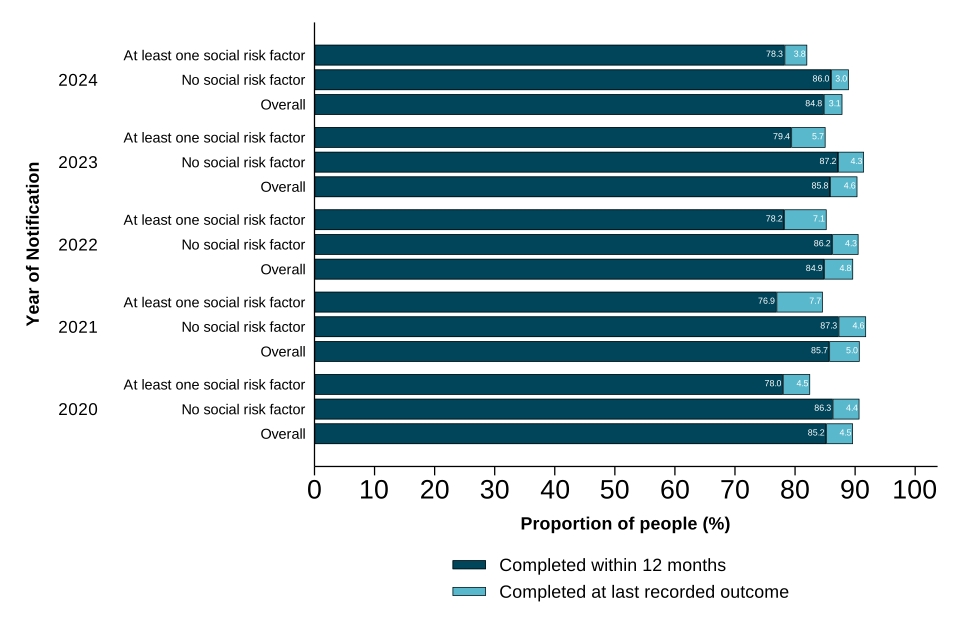
Data used in this figure can be seen in Supplementary Tables 11 and 12 in the accompanying spreadsheet.
Treatment outcomes in those who did not complete treatment within 12 months
Treatment outcomes at 12 months in people notified from 2015 to 2024 who did not complete their treatment within the expected 12 months are shown in Figure 5 and in Supplementary Table 11 in in the accompanying spreadsheet. The proportion of those not evaluated for the 2024 cohort is expected to decrease slightly as more missing values are entered over time. The proportion of those who died within 12 months (measured from start of treatment, diagnosis or notification depending on which is the latest data point available) was 2.9%, lower than the previous high of 5.1% in those notified in 2020 (p = 0.003) and similar to most other years. This year there were no further deaths reported in the last recorded outcome (Table 3). The proportion of people lost to follow-up slightly increased to 4.8% in the 2024 cohort compared with 3.0% in the 2023 cohort. The proportion recorded as not evaluated increased in 2024 to 3.3% from 2.9% seen in 2023. However, as has occurred in previous years, the proportion recorded as not evaluated is expected to decrease in later reporting years with increased follow-up.
Figure 5. Breakdown of outcomes of people treated for non-MDR or non-RR TB, notified in 2015 to 2024 who did not complete treatment within 12 months and with expected treatment duration less than 12 months, England, 2025
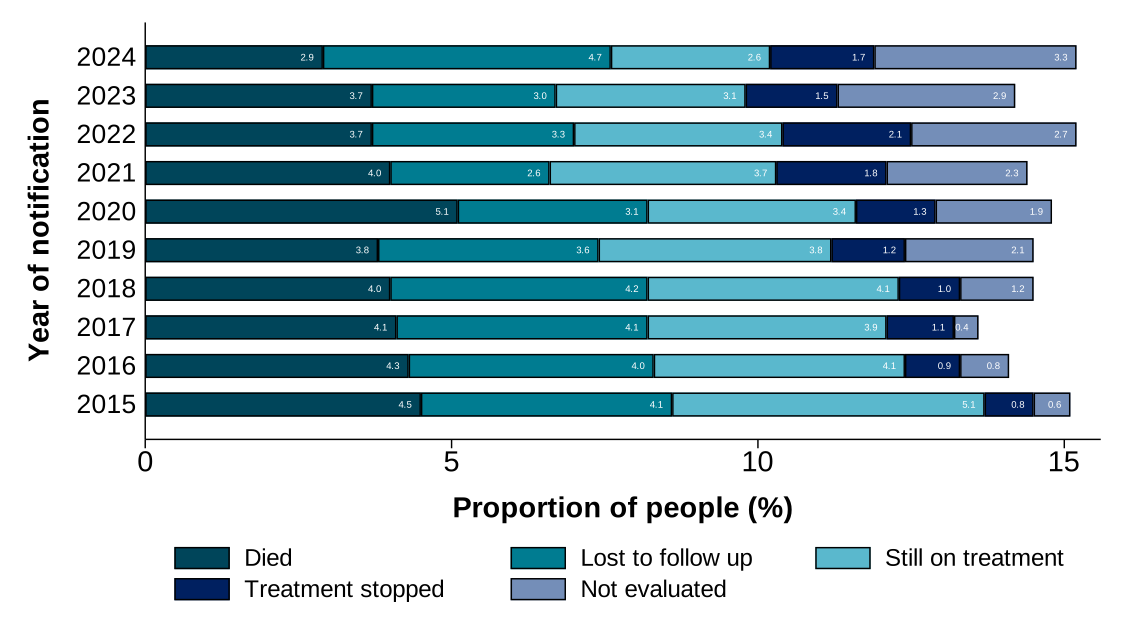
Data underlying this figure is available in Supplementary Table 11 in in the accompanying spreadsheet.
Treatment outcomes by 12 months by age, sex and region
Treatment outcomes by 12 months are reported for the cohort of people treated for non-MDR or non-RR TB and without severe disease by:
- treatment completion by age group for notifications in 2015 to 2024 in Supplementary Table 13
- treatment outcomes by age and sex for notifications in 2024 in Supplementary Table 14
- treatment outcomes by UKHSA region for notifications in 2024 in Supplementary Table 15
- proportion completed treatment by UKHSA region from 2015 to 2024 in Supplementary Table 16
Treatment completion was consistently lower in older age groups. For people notified in 2024 treatment completion was 88.1% in children aged 14 years or less compared with 72.1% in adults aged 65 years or more (p<0.001 for trend). When further disaggregated by sex, a higher proportion of males notified in 2024 died before 12 months for all ages except children, with the greatest difference in adults aged more than 65 years (17.5% of males over 65 with TB died, compared with 9.3% of females aged over 65).
Treatment duration
Treatment duration was recorded for 97.8% (4,123 out of 4,216) of people notified in 2024 who completed treatment in the cohort expected to complete within 12 months; of these 41.4% completed within the standard 6 months and a further 30.5% in 6 to 8 months and 3.5% took more than 12 months to complete treatment. These proportions have changed little over the previous 10 years (see Supplementary Table 17).
Figure 6 below shows that the proportions of people who completed treatment within 6 months varied little by age group, but was slightly lower in people born in the UK. The proportions of people who completed in 10 months or more was greatest in children aged 14 years or less.
Figure 6. Treatment duration by age and place of birth for the non-MDR or non-RR TB cohort expected to complete in 12 months notified in 2020 to 2024 (aggregate data), England, 2025
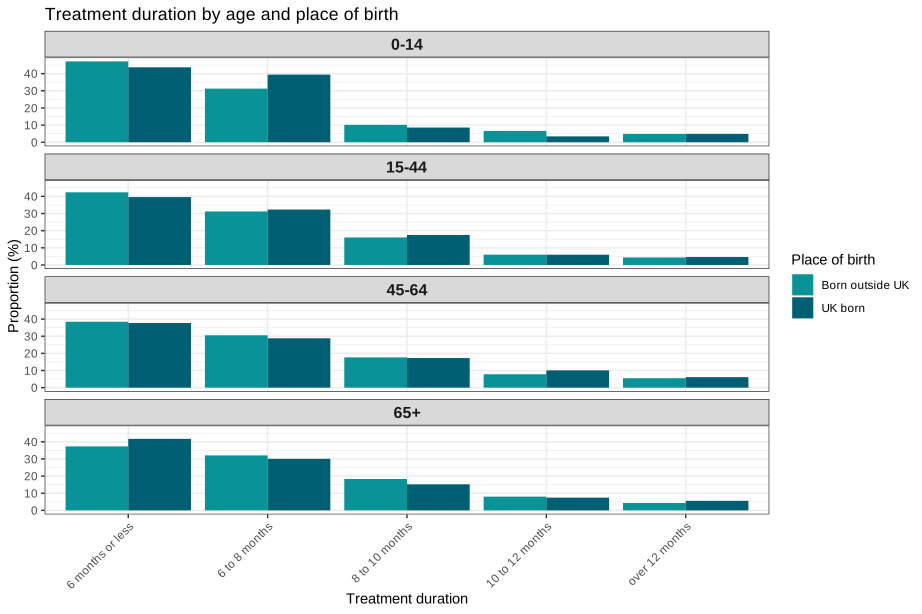
Data used in this figure can be found in Supplementary Table 18 in in the accompanying spreadsheet.
TB treatment outcomes for the non-MDR or non-RR TB cohort with CNS disease
Last recorded treatment outcomes in this cohort for those notified in 2024 are shown in Table 4 and for notification years from 2015 to 2024 in Supplementary Table 19. At the last recorded outcome, 78.8% of people notified in 2024 had completed treatment, while 3.5% were still on treatment. The proportion of people with CNS TB who had died at the last recorded outcome was more than double that of those without CNS disease (7.2% compared with 3.3%).
Table 4. Last recorded treatment outcome for people notified in 2024 with non-MDR or non-RR TB with CNS disease, England, 2025
| TB treatment outcomes | Last recorded TB treatment outcome (number) | Last recorded TB treatment outcome (percentage) |
|---|---|---|
| Treatment completed | 427 | 78.8 |
| Died | 39 | 7.2 |
| Lost to follow-up | 24 | 4.4 |
| Still on treatment | 19 | 3.5 |
| Stopped | 14 | 2.6 |
| Not evaluated | 19 | 3.5 |
| Total | 542 | 100.0 |
Note: excludes those with post-mortem diagnosis and those treated for MDR or RR TB.
Last recorded treatment outcome for the entire non-MDR or non-RR TB cohort
Last recorded treatment outcome for the entire non-MDR or non-RR TB cohort are shown in the accompanying spreadsheet:
- by year of notification, 2015 to 2024 in Supplementary Table 20
- by site of disease in 2024 notification year Supplementary Table 21
- by UKHSA region in 2024 notification year Supplementary Table 22
Treatment completion as the last recorded outcome for the entire non-MDR or non-RR TB cohort has not notably changed over time, with a 10-year average of 89.0%. The proportion of people who had died at their last reported outcome was 3.3% for those notified in 2024, less than the previous high of 6.0% for people notified in the peak pandemic year of 2020 and less than the 10-year average (4.7%).
For people notified in 2024, the proportion of people who had died was greater in those who were notified with pulmonary disease, both with other sites of disease as well (2,450 completed treatment; 4.8% died) or with only pulmonary disease (1,655 completed treatment; 4.4% died). People notified with miliary (disseminated disease and therefore included in pulmonary) had worse outcomes (119 completed treatment,11.6% died). There were fewer deaths in people notified with extrapulmonary disease only (2,193 completed treatment; 1.6% died). However, within subgroups of extrapulmonary disease only, CNS – meningitis and genitourinary, a high proportion died (65 completed treatment, 11.3% died, 78 completed treatment, 7.9% died respectively). People notified with extrapulmonary extra-thoracic lymph node TB had the highest treatment completion and low mortality (1,151 completed treatment, 0.8% died).
There were variations in treatment outcomes between UKHSA regions with the lowest treatment completion in the South West at 81.0% compared with the highest in the Yorkshire and Humber of 88.8.%. Of people notified in 2024, the proportion of people who died at their last recorded treatment outcome ranged from 2.3% in the East of England to 5.2% in the West Midlands, but due to small numbers these differences should be interpreted with caution.
Factors affecting treatment completion at last recorded outcome in the entire non-MDR or non-RR cohort
Figure 7 presents factors associated with treatment completion at the last recorded treatment outcome for the entire non-MDR or RR cohort for people notified in 2022 to 2024 combined. In univariable analysis, males, those with pulmonary disease, those born in the UK or with social risk factors, those with prison history, previous TB or CNS disease were less likely to complete treatment. The group least likely to complete treatment were older people aged 65 years or more compared with people aged 15 to 44 years, whilst children and people whose treatment had been delayed beyond 2 months from symptom onset were more likely to complete treatment.
Figure 7. Predictors of treatment completion (last recorded outcome) for people treated for non-MDR or non-RR TB, England, notified in 2022 to 2024 (aggregated data, univariable analysis)
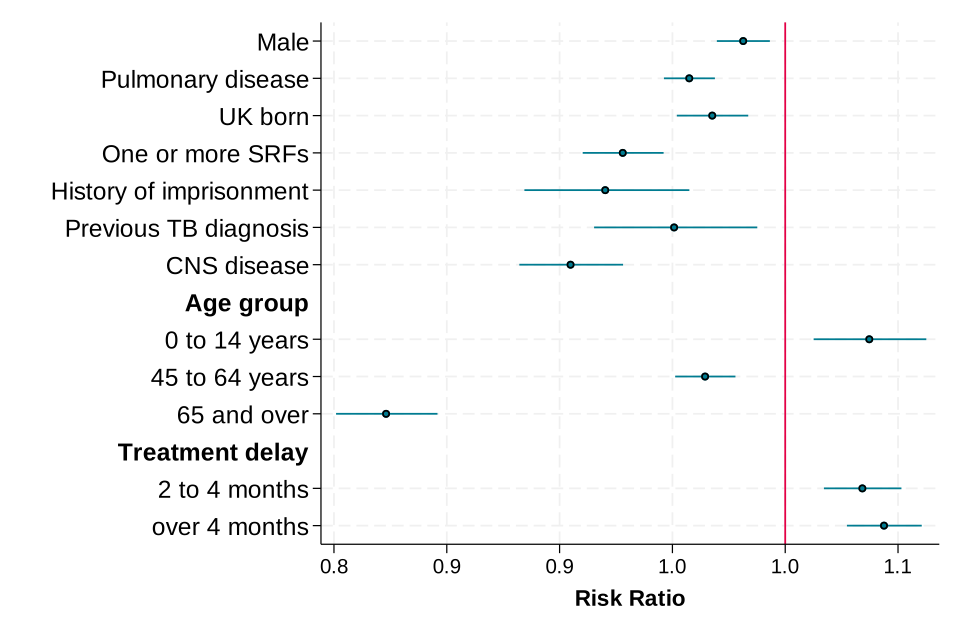
Notes
1. Comparison groups for RRs are as follows: males; pulmonary TB with or without extra-pulmonary TB compared with non-pulmonary TB only; no SRFs recorded; no history of imprisonment in those with data recorded; no previous diagnosis in those with data recorded; CNS disease includes those with TB meningitis, spinal, miliary or cryptic TB in which CNS involvement cannot be excluded compared with all other sites of disease; people aged 15 to 44 years, less than 2 months’ treatment delay in those with treatment start date recorded.
2. People treated for MDR TB or RR TB and post-mortem diagnosis are excluded.
Data underlying this analysis can be seen in Supplementary Table 23 in in the accompanying spreadsheet.
All deaths for the entire non-MDR or non-RR TB cohort
For people notified in 2024 in the non-MDR or non-RR TB cohort there were an additional 35 deaths in people who were diagnosed with TB post-mortem and are not included in the treatment outcome figures above. When these people are included, there was a total of 212 deaths and the proportion of all people notified with TB that died increased to 3.9% out of 5,375 people.
Out of 177 deaths of people in this cohort diagnosed before death and notified in 2024, TB was reported to have caused or contributed to death for 43.5%, was incidental to death for 26.0%, was unknown in 20.3% and record of the contribution of TB to the death was missing in the remaining 10.2%. These proportions have not notably changed over time (see Supplementary Table 24). For the 35 deaths that were in people diagnosed post-mortem, it was missing for all if TB was the cause of death.
Time to death in the entire non-MDR or non-RR TB cohort
Out of 212 people who were notified with TB in 2024 and died, 16.5% were diagnosed with TB after death (postmortem) and a further 9.4% died before starting TB treatment. Of the 156 people who died after a known treatment start date 86 (40.6%) died within 60 days of starting treatment compared with 32.1% after 60 days (Figure 8). This pattern has been consistent over the last 5 years but the proportion of deaths before starting treatment was highest for people notified in 2024.
Figure 8: Categorisation of time to death in entire non-MDR or non-RR TB, England, 2020 to 2024
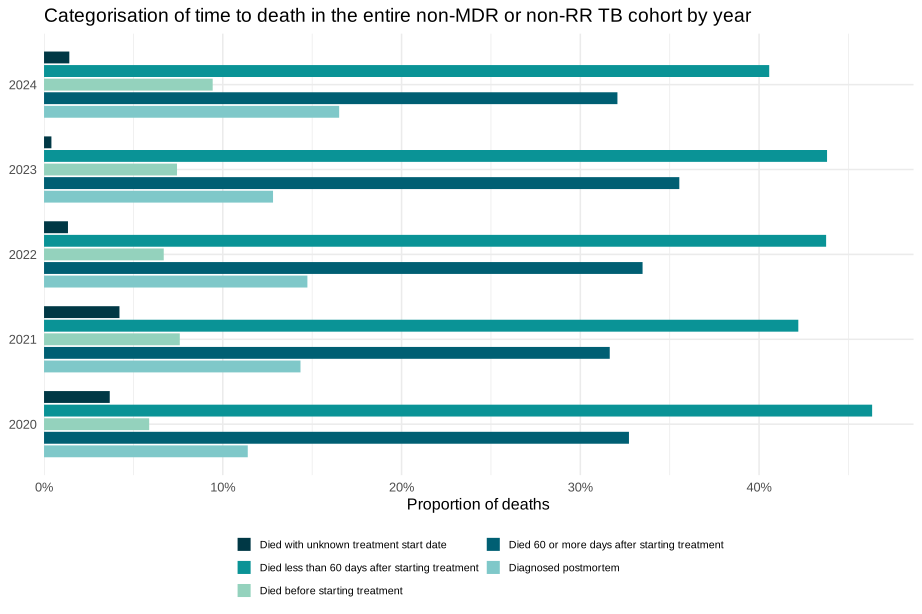
Data underlying this figure can be seen in Supplementary Table 25 in in the accompanying spreadsheet.
Note: people treated for MDR TB or RR TB were excluded.
Factors affecting risk of death at last recorded outcome in the entire non-MDR or non-RR cohort
Figure 9 shows factors associated with death as the last reported TB treatment outcome adjusted for the effect of age for people notified in 2022 to 2024. Independent of age, males, and people with pulmonary disease, those with SRFs and comorbidities had an increased risk of dying. The largest effects were for the relatively rare conditions of current alcohol misuse (affecting 4.5% of this cohort; adjusted RR 3.47, 95% CI 2.76 to 4.36) and those with comorbid chronic liver disease (affecting 1.3% of this cohort; adjusted RR 3.78, 95% CI 2.97 to 4.81). Pulmonary TB, affecting 54.5%, was associated with a doubled risk of death (adjusted RR 2.12; 95% CI 1.80 to 2.51) and of similar magnitude to risk associated with having severe CNS TB disease (see Supplementary Table 26).
Figure 9. Factors associated death for entire non-MDR or RR cohort, England, 2022 to 2024 (aggregated data) adjusted for age
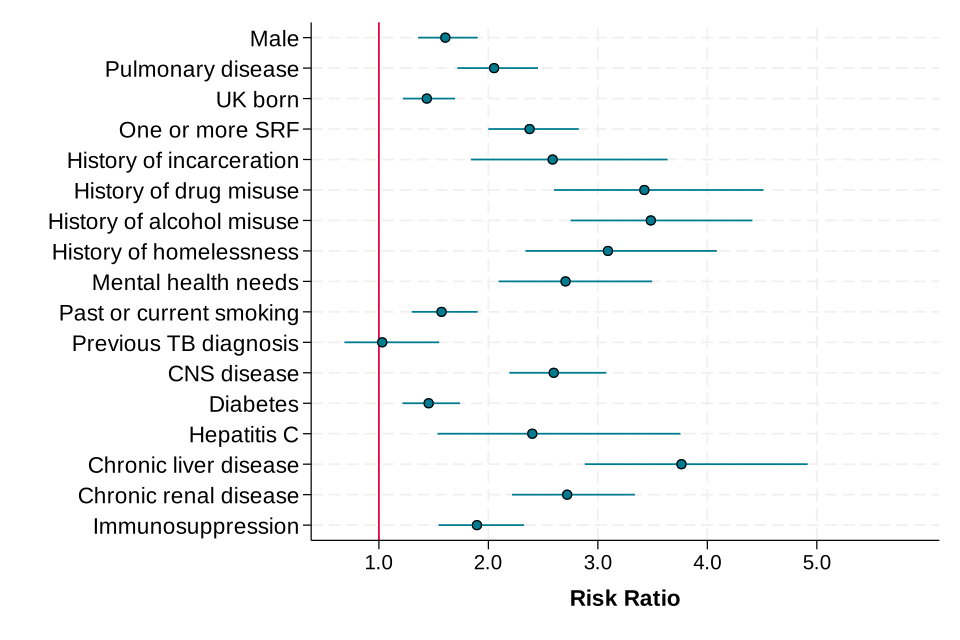
Notes
1. Comparison groups for RRs in the order presented as follows: females; non-pulmonary TB; born outside of the UK; no SRFs recorded, prison, drug, alcohol, homelessness or mental health needs identified in those with data recorded; no history of smoking in those with data recorded; no previous TB diagnosis; CNS disease includes those with meningitis, spinal, miliary or cryptic TB in which CNS involvement cannot be excluded compared with all other sites of disease; no diabetes, hepatitis, chronic liver or chronic renal disease or immunosuppression in those with data recorded.
2. People treated for MDR and RR TB and TB diagnosed at post-mortem are excluded.
Data underlying this analysis, including factors not shown here are presented in Supplementary Table 26 in the accompanying spreadsheet.
TB treatment outcomes in the drug resistant (MDR or RR TB) cohort
TB outcomes for the MDR or RR cohort are reported at 24 months, so the most recent complete data is for people notified in 2023. The 2023 cohort comprised 112 people treated for MDR or RR TB. 101 of these had culture -confirmed MDR or RR TB at diagnosis, of whom 16 had pre-extensively drug resistant (pre-XDR) TB and 1 had extensively drug resistant (XDR) (see Table 13 in the ‘TB Diagnosis, microbiology and drug resistance in England’ data set).
Treatment outcome at 24 months and last recorded outcome for persons treated for drug-resistant TB notified in 2023 are shown in Table 5 and for notification years 2014 to 2023 in Figures 10 and 11 and Supplementary Tables 27 and Supplementary Table 28 in the accompanying spreadsheet. A total of 90 people notified in 2023 completed treatment within 24 months. A further 3 people completed treatment after 24 months, bringing overall treatment completion for people notified in 2023 to 83.0%. Although overall treatment completion for people with MDR or RR TB has remained similar from 2014 to 2023, there has been an increase in treatment completion within 24 months, from 50.7% in 2014 to 80.4% in 2023 reflecting improved and shorter drug regimens (Figure 10).
Table 5. Treatment outcome at 24 months and last recorded outcome for people treated for MDR or RR TB notified in 2023, England, 2025
| TB treatment outcomes | TB treatment outcome at 24 months (number) | TB treatment outcome at 24 months (percentage) | Last recorded TB treatment outcome (number) | Last recorded TB treatment outcome (percentage) |
|---|---|---|---|---|
| Treatment completed | 90 | 80.4 | 93 | 83.0 |
| Died | 6 | 5.4 | 6 | 5.4 |
| Lost to follow-up | 4 | 3.6 | 4 | 3.6 |
| Still on treatment | 2 | 1.8 | 1 | 0.9 |
| Stopped | 1 | 0.9 | 1 | 0.9 |
| Not evaluated | 9 | 8.0 | 7 | 6.2 |
| Total | 112 | 100.0 | 112 | 100.0 |
Note. Table excludes people diagnosed post-mortem.
Figure 10. Proportion of people treated for MDR or RR TB with treatment completion at 24 months or last recorded outcome notified in 2014 to 2023, England 2025
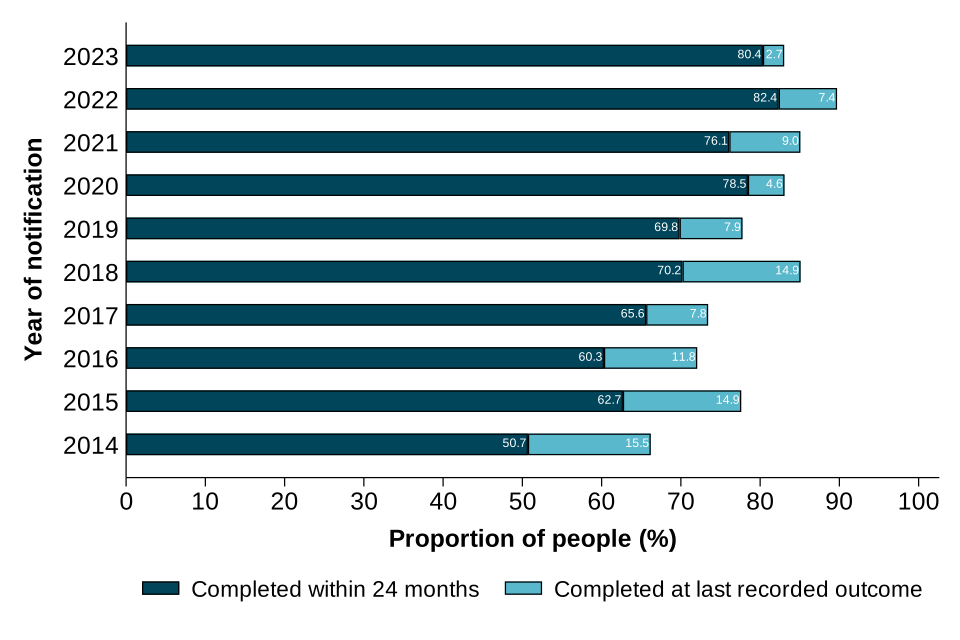
Data underlying this figure is shown in Supplementary Tables 27 and 28 in the accompanying spreadsheet.
Treatment outcomes at 24 months for people with MDR or RR TB notified from 2014 to 2023 and who did not complete treatment are shown in Figure 11 below.
Figure 11. Breakdown of outcomes of people treated for MDR or RR TB, notified in 2014 to 2023 who did not complete treatment within 24 months, England, 2025
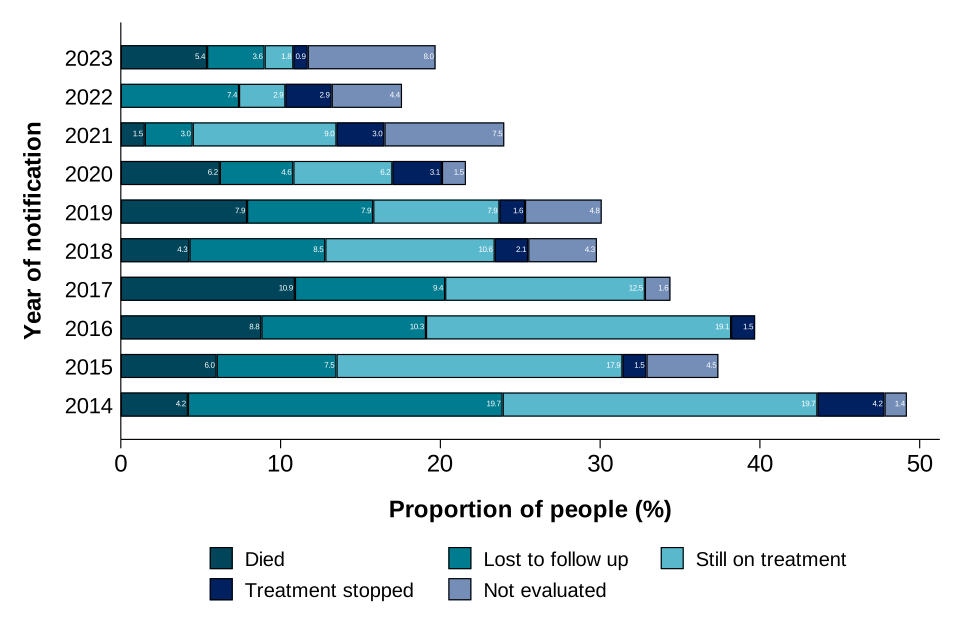
Data underlying this figure is available in Supplementary Table 28 in the accompanying spreadsheet.
Treatment duration
For people notified in 2023 who completed treatment, time to completion was known for 94.6% (88 out of 93) in the cohort. The proportion of people who completed treatment within 12 months was 25.0% for people notified in 2023 compared with 11.5% for people notified in 2022 (see Supplementary Table 28).
Deaths in the MDR or RR TB cohort
For people notified in 2023, no one was diagnosed after death. For the 6 deaths in this cohort, 1 death was recorded as having been caused by TB, 4 as TB incidental to death and 2 with unknown or missing contribution of TB to death. All started treatment with 2 people dying within 60 days of starting treatment and 4 people after more than 60 days.