Hepatitis C in the East Midlands annual report 2025
Updated 21 October 2026

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/hepatitis-c-in-the-east-midlands-annual-reports/hepatitis-c-in-the-east-midlands-annual-report-2025
Introduction
Hepatitis C virus (HCV) is a bloodborne virus. Chronic infection can lead to liver cirrhosis, end-stage liver disease and liver cancer. Prevention and treatment efforts have been combined to combat HCV infection and progress towards elimination of HCV as a public health threat by 2030 (set out in the World Health Organization Global Health Sector Strategy on Viral Hepatitis). The National Strategic Group on Viral Hepatitis, a cross-agency expert advisory body supported by the UK Health Security Agency (UKHSA) provides strategic guidance on viral hepatitis in England, and supports progress toward achieving the World Health Organization (WHO) goal of HCV elimination.
UKHSA publishes a national Hepatitis C in England report which summarises England’s progress towards the WHO elimination targets for HCV infection. This regional spotlight report complements the ‘Hepatitis C in England’ report and presents further information on HCV disease surveillance, and trends in HCV diagnosis, testing and treatment in East Midlands UKHSA region with data up to end of 2024.
For more details, see Information on data sources.
Summary
Key findings for hepatitis C testing:
- there were 1,345 new laboratory reports of hepatitis C in residents of the East Midlands UKHSA region, representing a rate of 26.6 reports per 100,000 population in 2024
- the number of new laboratory reports has increased by 54.6% since 2023 and increased by 39.7% over the past 10 years
- in 2024, the number of positive laboratory reports by upper tier local authority of residence ranged from 52 in North Northamptonshire to 301 in Leicester. Rates were highest in Derby at 107.6 and lowest in Derbyshire with 8.5
- in 2024, the number of laboratory reports in males was 590 (43.9%) and in females was 303 (22.5%). Sex was unknown in 33.6% of cases
- in 2024, the highest number of laboratory reports was in males aged 35 to 44 and females aged 35 to 44
- there have been 54,948 individuals tested for anti-HCV in sentinel laboratories in East Midlands UKHSA region in 2024, of which 2.1% tested positive. The proportion positive was lower for tests referred from general practitioner (GP) surgeries, lower for tests from sexual health services, and higher for tests from drug services; the total number of tests conducted has likely increased since 2022 nationally and since 2024 in the East Midlands as a result of a new ‘opt-out’ bloodborne virus testing programme at selected emergency departments (73% increase in testing in the East Midlands between 2023 and 2024)
Key findings for hepatitis C treatment pathway:
- of 4,558 individuals with chronic hepatitis C linked to specialist treatment services (using a recorded NHS number or name and date of birth via the NHSE Hepatitis C Patient Registry and Treatment Outcome System and/or NHSE’s Blueteq System), 4,444 started treatment within 90 days and 3,919 achieved a sustained viral response (SVR), in East Midlands UKHSA region between 2015 and 2024
Key findings for HCV-related morbidity and mortality:
- the number of first hospital admissions for individuals with a diagnosis code for hepatitis C-related end-stage liver disease or hepatitis C-related hepatocellular carcinoma is estimated to be between 59 and 79 in the East Midlands UKHSA region in 2024. This was lower than in 2023 (first hospital admissions: 71 to 93)
- the number of registered deaths from hepatitis C-related and end-stage liver disease and/or hepatocellular carcinoma was estimated to be between 21 and 25 in East Midlands UKHSA region in 2024. Both values were higher than the lower bound estimate of 18 in 2023, but below the upper bound estimate of 32
Trends in HCV testing and diagnosis in the general population and risk groups
New laboratory-confirmed diagnoses of HCV
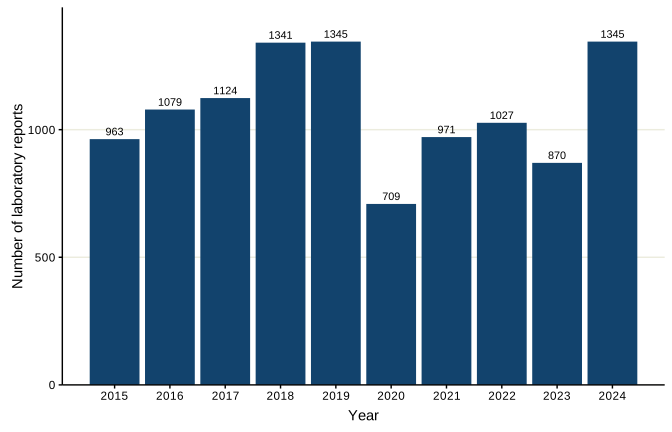
Figure 1. Number of new laboratory reports of hepatitis C, residents of East Midlands UKHSA region, 2015 to 2024
Data source: Second Generation Surveillance System (SGSS). For more information, see Information on data sources.
Note 1: in 2022, a new bloodborne virus (BBV) testing programme was introduced in selected emergency department (ED) sites in areas of very high and high human immunodeficiency virus (HIV) diagnosed prevalence across England, which included sites in London, Manchester, Salford, Brighton and Blackpool. This programme expanded to other areas of high HIV prevalence in the second phase of the implementation of this programme, starting in 2024, however, not all UKHSA regions had participating ED sites within their areas. Sites within the East Midlands were part of the second phase of this programme.
The number of new laboratory reports of hepatitis C in East Midlands fluctuated between 2015 and 2024, with a marked decline in 2020; this was most likely due to reduced testing during the pandemic. This was followed by recovery in subsequent years. Reports increased substantially in 2024, reaching 1,345, the highest number reported since 2019. This increase is likely to have been influenced by the introduction of opt-out bloodborne virus testing in 4 out of the 6 emergency departments signed up to the programme in the East Midlands during 2024, which expanded testing coverage and opportunities for case finding.
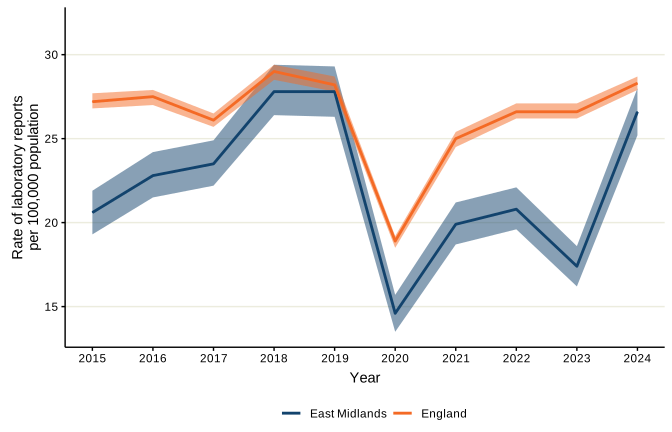
Figure 2. Rate per 100,000 population of new laboratory reports of hepatitis C, residents of East Midlands UKHSA region and England, 2015 to 2024
Data sources: SGSS and Office for National Statistics (ONS) mid-year population estimates (MYE). For more information, see Information on data sources.
Note 2: the error bands represent 95% confidence intervals.
Rates of new laboratory reports in East Midlands broadly followed the national trend over the period but remained lower. Rates fell during 2020 and subsequently increased, reaching 26.6 per 100,000 population in 2024. In 2024, the East Midlands rate was similar to the England rate of 28.3 per 100,000 population.
Table 1. Number and rate per 100,000 population of new laboratory reports of hepatitis C by UKHSA region of residence and England, 2015 to 2024
| Area | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | 2023 | 2024 | |
|---|---|---|---|---|---|---|---|---|---|---|---|
| East Midlands | Count | 963 | 1,079 | 1,124 | 1,341 | 1,345 | 709 | 971 | 1,027 | 870 | 1,345 |
| East Midlands | Rate | 20.6 | 22.8 | 23.5 | 27.8 | 27.8 | 14.6 | 19.9 | 20.8 | 17.4 | 26.6 |
| East of England | Count | 1,105 | 1,291 | 1,131 | 1,039 | 1,072 | 773 | 1,092 | 997 | 815 | 929 |
| East of England | Rate | 16.6 | 19.2 | 16.7 | 15.3 | 15.7 | 11.3 | 15.8 | 14.3 | 11.5 | 12.9 |
| London | Count | 4,026 | 4,177 | 3,432 | 3,146 | 2,634 | 2,438 | 2,702 | 3,533 | 4,093 | 4,552 |
| London | Rate | 46.5 | 47.8 | 39.1 | 35.6 | 29.6 | 27.5 | 30.7 | 39.8 | 45.5 | 50.1 |
| North East | Count | 216 | 228 | 390 | 750 | 967 | 700 | 903 | 1,071 | 777 | 888 |
| North East | Rate | 8.3 | 8.7 | 14.9 | 28.5 | 36.7 | 26.5 | 34.1 | 39.9 | 28.5 | 32.2 |
| North West | Count | 2,935 | 2,625 | 2,485 | 3,467 | 2,964 | 1,462 | 2,782 | 2,693 | 2,826 | 2,767 |
| North West | Rate | 40.9 | 36.3 | 34.2 | 47.4 | 40.3 | 19.8 | 37.5 | 35.8 | 37.0 | 35.8 |
| South East | Count | 1,581 | 1,818 | 1,436 | 1,445 | 1,491 | 1,216 | 1,749 | 2,140 | 2,277 | 1,781 |
| South East | Rate | 18.8 | 21.4 | 16.8 | 16.8 | 17.3 | 14.0 | 20.1 | 24.3 | 25.5 | 19.7 |
| South West | Count | 1,147 | 1,065 | 1,105 | 994 | 957 | 913 | 842 | 947 | 1,035 | 1,400 |
| South West | Rate | 21.0 | 19.3 | 19.8 | 17.7 | 17.0 | 16.1 | 14.7 | 16.4 | 17.8 | 23.8 |
| West Midlands | Count | 1,090 | 1,371 | 1,198 | 1,118 | 1,305 | 922 | 1,221 | 1,141 | 794 | 1,161 |
| West Midlands | Rate | 18.9 | 23.6 | 20.5 | 19.0 | 22.0 | 15.5 | 20.5 | 19.0 | 13.0 | 18.8 |
| Yorkshire and Humber | Count | 1,812 | 1,483 | 1,423 | 1,608 | 1,665 | 1,035 | 1,314 | 1,258 | 1,243 | 1,514 |
| Yorkshire and Humber | Rate | 33.7 | 27.4 | 26.2 | 29.5 | 30.5 | 18.9 | 24.0 | 22.7 | 22.2 | 26.7 |
| England | Count | 14,916 | 15,182 | 14,517 | 16,195 | 15,864 | 10,630 | 14,116 | 15,217 | 15,432 | 16,590 |
| England | Rate | 27.2 | 27.5 | 26.1 | 29.0 | 28.2 | 18.9 | 25.0 | 26.6 | 26.6 | 28.3 |
Data sources: SGSS and Office for National Statistics (ONS) mid-year population estimates (MYE). For more information, see Information on data sources.
Note 3: data was not available to assign a case to a UKHSA region in 253 cases, meaning that the sum of all regional cases may not equal the number of England cases.
In 2024, East Midlands reported 1,345 new laboratory-confirmed hepatitis C cases, equivalent to a rate of 26.6 per 100,000 population. Regional rates varied across England, with the highest rates observed in London and the North West, while East Midlands remained close to the national average.
Table 2. Number and rate per 100,000 population of new laboratory reports of hepatitis C by upper tier local authority (UTLA) of residence, 2015 to 2024
| Area | 2015 | 2016 | 2017 | 2018 | 2019 | 2020 | 2021 | 2022 | 2023 | 2024 | |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Derby | Count | 211 | 170 | 219 | 293 | 193 | 42 | 25 | 149 | 153 | 295 |
| Derby | Rate | 82.0 | 65.4 | 83.9 | 111.7 | 73.4 | 16.0 | 9.6 | 56.4 | 56.7 | 107.6 |
| Derbyshire | Count | 53 | 74 | 84 | 86 | 96 | 54 | 74 | 57 | 70 | 70 |
| Derbyshire | Rate | 6.8 | 9.5 | 10.7 | 11.0 | 12.2 | 6.8 | 9.3 | 7.1 | 8.6 | 8.5 |
| Leicester | Count | 78 | 105 | 150 | 176 | 275 | 131 | 142 | 101 | 184 | 301 |
| Leicester | Rate | 22.3 | 29.4 | 41.4 | 47.9 | 74.4 | 35.5 | 38.7 | 27.1 | 48.1 | 77.5 |
| Leicestershire and Rutland | Count | 55 | 52 | 56 | 67 | 85 | 34 | 34 | 53 | 97 | 130 |
| Leicestershire and Rutland | Rate | 7.8 | 7.3 | 7.7 | 9.1 | 11.5 | 4.6 | 4.5 | 6.9 | 12.5 | 16.5 |
| Lincolnshire | Count | 203 | 220 | 267 | 197 | 191 | 96 | 124 | 118 | 96 | 101 |
| Lincolnshire | Rate | 27.5 | 29.5 | 35.5 | 26.0 | 25.1 | 12.6 | 16.1 | 15.2 | 12.2 | 12.8 |
| North Northamptonshire | Count | 28 | 54 | 100 | 209 | 78 | 55 | 96 | 101 | 37 | 52 |
| North Northamptonshire | Rate | 8.4 | 15.8 | 28.8 | 59.4 | 22.0 | 15.4 | 26.6 | 27.8 | 10.0 | 13.9 |
| Nottingham | Count | 80 | 111 | 102 | 110 | 122 | 66 | 72 | 82 | 80 | 178 |
| Nottingham | Rate | 25.5 | 34.9 | 31.8 | 34.1 | 37.8 | 20.4 | 22.5 | 25.1 | 24.5 | 53.8 |
| Nottinghamshire | Count | 167 | 213 | 113 | 78 | 169 | 135 | 248 | 181 | 102 | 163 |
| Nottinghamshire | Rate | 20.8 | 26.4 | 13.9 | 9.6 | 20.6 | 16.4 | 30.0 | 21.7 | 12.0 | 19.0 |
| West Northamptonshire | Count | 86 | 79 | 30 | 104 | 134 | 93 | 156 | 185 | 51 | 54 |
| West Northamptonshire | Rate | 21.6 | 19.5 | 7.3 | 24.9 | 31.7 | 22.0 | 36.6 | 43.1 | 11.7 | 12.3 |
| No UTLA data available | Count | 2 | 1 | 3 | 21 | 2 | 3 | 0 | 0 | 0 | 1 |
| No UTLA data available | Rate | NA | NA | NA | NA | NA | NA | NA | NA | NA | NA |
| England | Count | 14,916 | 15,182 | 14,517 | 16,195 | 15,864 | 10,630 | 14,116 | 15,217 | 15,432 | 16,590 |
| England | Rate | 27.2 | 27.5 | 26.1 | 29.0 | 28.2 | 18.9 | 25.0 | 26.6 | 26.6 | 28.3 |
Data sources: SGSS and Office for National Statistics (ONS) mid-year population estimates (MYE). For more information, see Information on data sources.
Note 4: data was not available to assign a case to a UKHSA region in 253 cases, meaning that the sum of all regional cases may not equal the number of England cases. UTLA data was available for 100% of cases where region data was available.
There was considerable variation in hepatitis C diagnosis rates across local authorities within East Midlands in 2024. Derby, Leicester and Nottingham, all major urban centres within the region, reported rates above both the regional and national averages. Derby reported the highest rate (107.6 per 100,000 population), followed by Leicester (77.5) and Nottingham (53.8), which were all above the regional and national rates. All the other local authorities had rates below the regional and national rates with Derbyshire having the lowest rate (8.5 per 100,000 population).
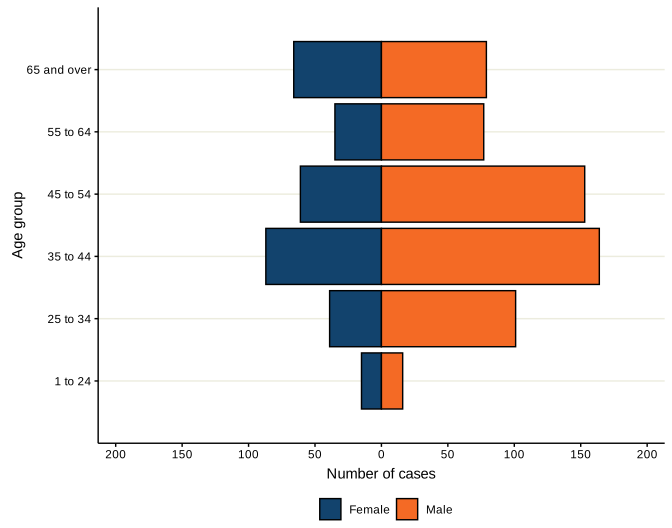
Figure 3. Age group and sex of new laboratory reports of hepatitis C, residents of East Midlands UKHSA region, 2024
Data source: Second Generation Surveillance System (SGSS). For more information, see Information on data sources.
The age and sex distribution of laboratory reports shows that most reports occurred among males. Among both males and females, the highest number of reports was recorded in those aged 35 to 44 years. Among males, the second highest number of reports was observed in those aged 45 to 54 years, while among females the second highest number was observed in those aged 65 years and over. Interpretation should be made with caution as approximately one-third of reports had incomplete age and/or sex information recorded.
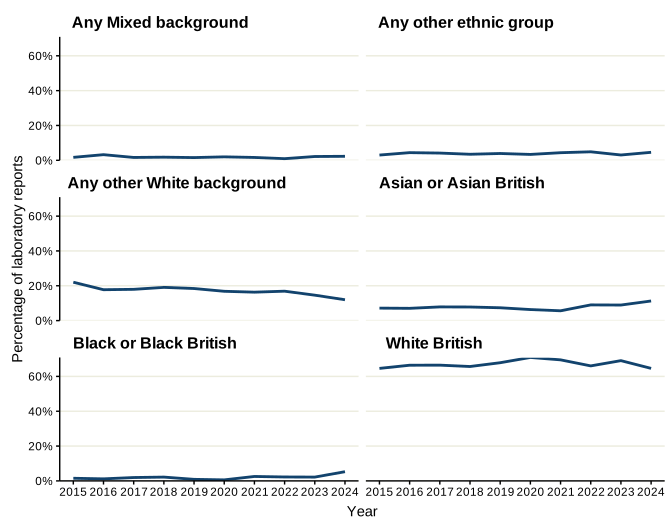
Figure 4. Ethnicity distribution of new laboratory reports of hepatitis C, residents of East Midlands UKHSA region, 2015 to 2024
Data source: SGSS. For more information, see Information on data sources.
Note 5: this figure excludes cases of unknown ethnicity. (42.6% of reports had no ethnicity recorded).
Note 6: where the number of cases in an ethnic group in a given year is between 1 and 4 (inclusive), data has been suppressed for disclosure control. Suppressed values are shown as an asterisk (*) on the chart.
Among reports with ethnicity recorded, the distribution of hepatitis C diagnoses varied by ethnic group across the period, the greatest percentage of cases was among those reported to be white British for the whole period. Those of any other white background had the second highest percentage of new laboratory reports and have shown a steady decline over the 10-year period, while Asian or Asian British and Black or Black British individuals have seen a small increase in percentages since 2021. Interpretation should be made with caution as over 40% of laboratory reports had no ethnicity recorded.
HCV testing in the wider population
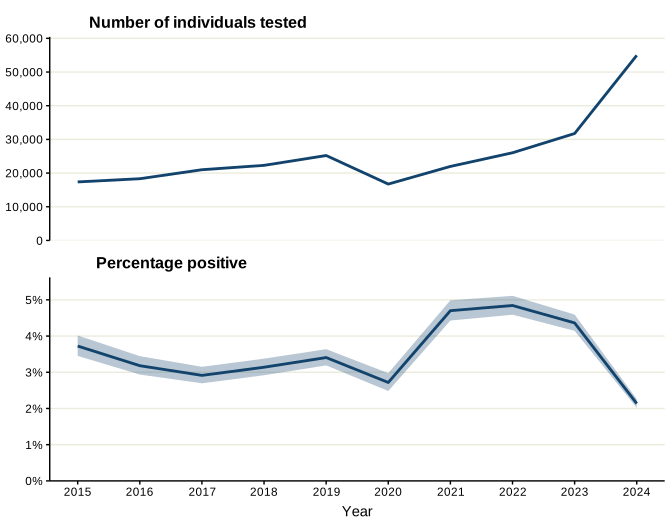
Figure 5. Number of individuals tested for anti-HCV by year and percentage positive in sentinel laboratories in East Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 7: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 8: in 2022, a new bloodborne virus (BBV) testing programme was introduced in selected emergency department (ED) sites in areas of very high and high human immunodeficiency virus (HIV) diagnosed prevalence across England. This programme expanded to other areas of high HIV prevalence in the second phase of the implementation of this programme, starting in 2024, however, not all UKHSA regions had participating ED sites within their areas.
Note 9: the error bands represent 95% confidence intervals.
The number of individuals tested for anti-HCV increased over time (17,376 in 2015 to 54,948 in 2024), with a rise from 2020 onwards showing a recovery in testing after the pandemic. There was a sharper rise seen in 2024 following the implementation of the ED opt-out BBV testing programme in the East Midlands. Positivity remained low, with a sharp increase between 2020 and 2021, remaining stable (between 4.5% and 5%) between 2021 and 2023, then showing a sharp fall in 2024, likely to be influenced by the increased testing seen in the same year. This pattern may reflect expansion of testing into a broader population through non-targeted emergency department testing, although changes in the characteristics of those tested may also have contributed. This is because ED testing is opt-out on a non-targeted basis, with the aim of identifying cases that may not be captured through other testing streams. As a result, it can detect infections among individuals who do not fall within identified risk groups or exhibit recognised risk factors.
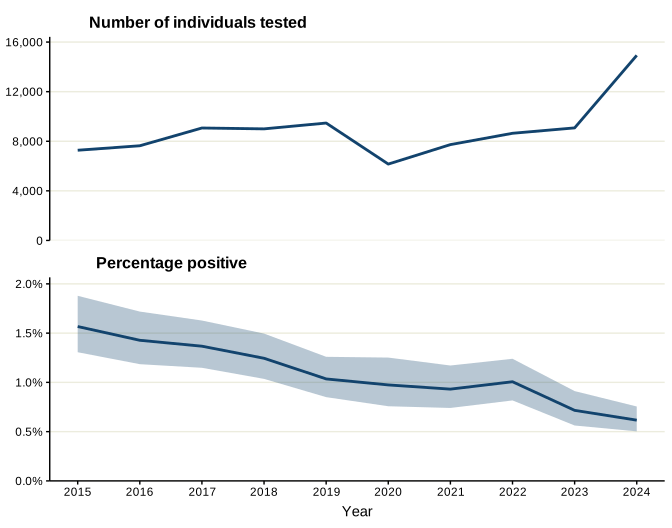
Figure 6. Number of individuals tested for anti-HCV by year and percentage positive, through GP surgeries, in sentinel laboratories in East Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 10: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 11: the error bands represent 95% confidence intervals.
The number of individuals tested for anti-HCV through GP surgeries varied over the period but remained substantial. The proportion testing positive was consistently lower than that seen overall (see Figure 5), declining steadily over time. This may reflect changes in testing practices, increasing testing coverage and differences in the populations being tested.
Note: the increase in people being tested in 2023 through GP surgeries coincides with the implementation of case-finding HCV through the use of the Primary Care Search Tool across primary care networks or individual GP surgeries who participated in this project.
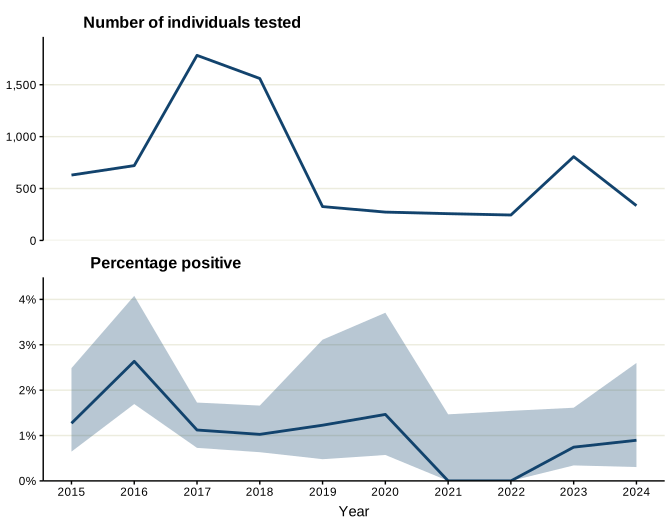
Figure 7. Number of individuals tested for anti-HCV by year and percentage positive, through sexual health services, in sentinel laboratories in East Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 12: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 13: the error bands represent 95% confidence intervals.
Testing volumes in sexual health services changed over time, with increases in the number of tests undertaken between 2016 and 2019. Across the period 2015 to 2024, the proportion of individuals testing positive through sexual health services remained consistently low relative to several other testing settings. This suggests a relatively low burden of hepatitis C infection among individuals tested through these services compared with other settings.
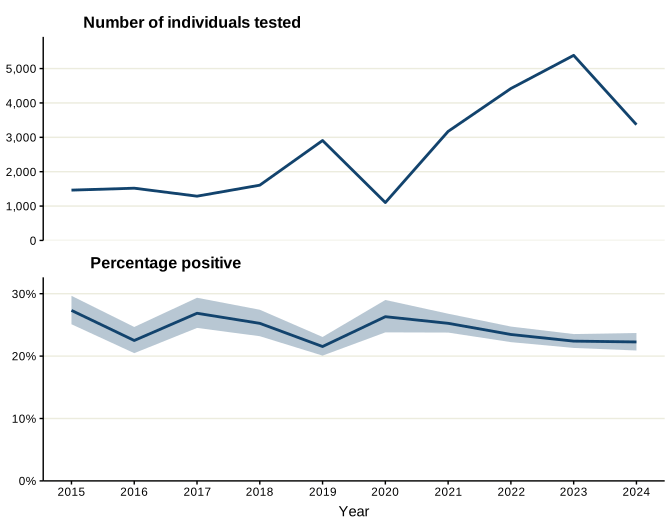
Figure 8. Number of individuals tested for anti-HCV by year and percentage positive, through drug services, in sentinel laboratories in East Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 14: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 15: the error bands represent 95% confidence intervals.
Drug services had the highest positivity among the testing settings presented, consistent with the elevated risk of hepatitis C infection among people who inject drugs. Testing activity fluctuated over time, particularly showing a large increase in testing from 2020 to 2023, dropping in 2024 but remaining above pre-pandemic levels of testing. The decline in testing seen in 2024 may reflect a combination of factors, including saturation of testing within established services, changes in service engagement, and modifications to testing pathways, for example, increasing use of point-of-care tests or changes in laboratory providers may reduce the number of anti-HCV tests recorded through sentinel laboratory surveillance, even where overall testing activity remains stable. This testing remains an important source of case identification.
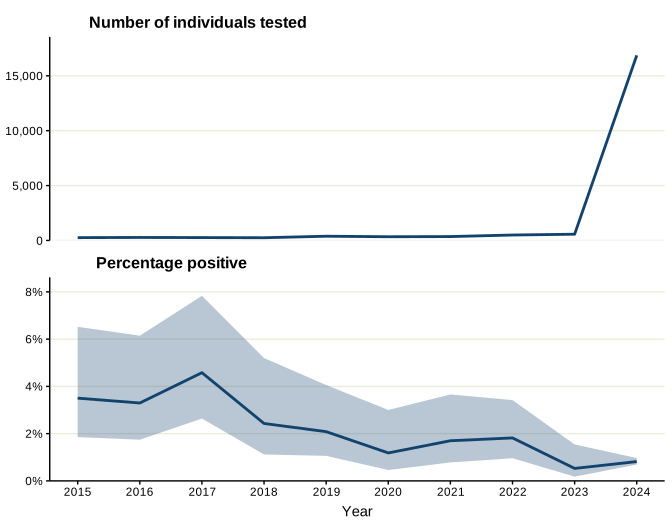
Figure 9. Number of individuals tested for anti-HCV by year and percentage positive, through emergency departments, in sentinel laboratories in East Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Note 16: trend data only includes testing laboratories that have consistently reported over time. Results from laboratories that report results on an inconsistent or temporary basis are excluded so as not to skew trends.
Note 17: in 2022, a new bloodborne virus (BBV) testing programme was introduced in selected emergency department (ED) sites in areas of very high and high human immunodeficiency virus (HIV) diagnosed prevalence across England. This programme expanded to other areas of high HIV prevalence in the second phase of the implementation of this programme, starting in 2024, however, not all UKHSA regions had participating ED sites within their areas.
Note 18: the error bands represent 95% confidence intervals.
Testing volumes in emergency departments increased substantially following the introduction and expansion of opt-out BBV testing (568 tests in 2023 compared to 16,862 tests in 2024). This programme is likely to have increased opportunities to identify hepatitis C infections among individuals who may not otherwise access testing services.
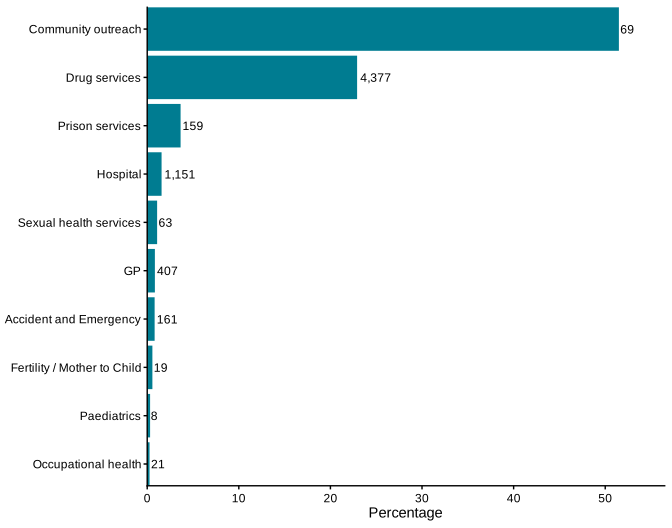
Figure 10. Percentage positivity for anti-HCV tests by setting or reason for test in sentinel laboratories 2020 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Numbers next to bars indicate the number of positive cases.
Note 19: figure shows number of individuals tested per year per speciality. If an individual has multiple tests in a year across multiple specialities then they will be counted once per speciality.
The highest percentage positive tests were seen from community outreach testing (51%). It suggests a) that testing by outreach workers in these settings is well targeted, and b) the importance of their work in the identification of cases who may not normally present to services – though this estimate should be interpreted cautiously in the context of the number of tests undertaken (69). The highest number of cases were identified in Drug services (4,377), reflecting the greater volume of testing taking place among this high-risk population.
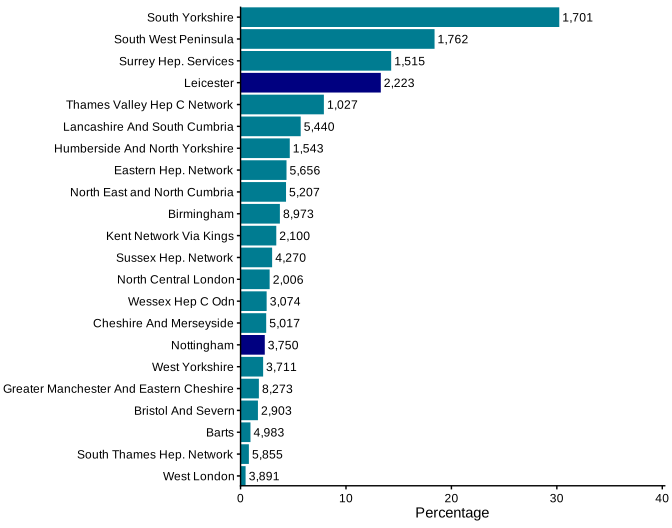
Figure 11. Percentage of individuals testing anti-HCV positive among those tested in sentinel laboratories, by operational delivery network (ODN), 2020 to 2024
Data source: SSBBV. For more information, see Information on data sources.
Numbers next to bars indicate the number of positive cases.
Note 20: ODN boundaries do not fully align with UKHSA regional boundaries, so not all East Midlands residents may be captured within the highlighted bars. Bars are highlighted in the above chart based on the region containing the majority of their residents. Consequently, the highlighted bars may include cases from outside the region, and some residents of this region may fall into ODNs / highlighted bars associated with other regions.
Testing activity and positivity differed between operational delivery networks with the highest positivity seen in South Yorkshire at 30% from 5,627 people tested, which was the lowest amount of people tested via sentinel laboratories; and the lowest positivity – seen in West London at 0.5% from 813,600 people tested – which was the highest number of people tested. These variations may reflect differences in local population characteristics, service provision and the prevalence of hepatitis C infection as well as changes in testing patterns over this period in the different areas; ED opt-out testing was introduced first in 2022 in London ODN areas, as they were areas of highest HIV prevalence. Positivity estimates should also be interpreted alongside testing volume, as ODNs with smaller numbers tested may show greater variation in positivity estimates.
For the East Midlands Leicester had a higher positivity at 13.3% with 16,709 individuals tested, and Nottingham had a positivity of 2.2% with 163,124 individuals tested over this period. Because these data are taken from sentinel surveillance it is important to note that for the East Midlands, Nottingham lab has been submitting data to the system longer than Leicester, which only started submitting data in 2024, giving Leicester fewer years of data to contribute to this analysis.
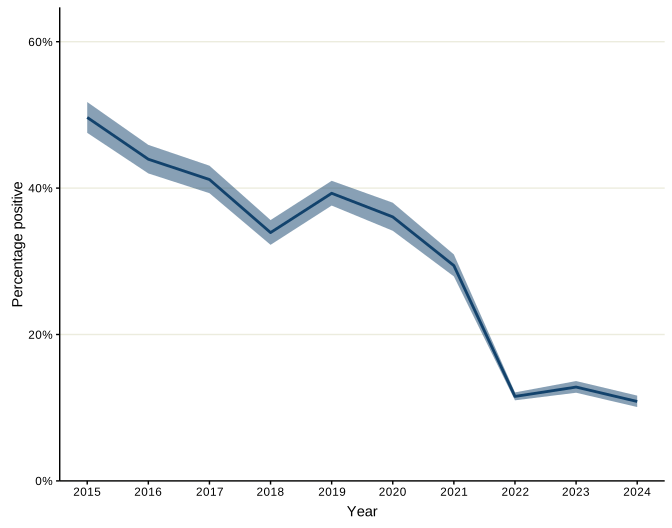
Figure 12. Percentage of individuals tested positive for HCV RNA in sentinel laboratories in East Midlands UKHSA region, 2015 to 2024
Data source: SSBBV. For more information, see Information on data sources.
The proportion of individuals testing positive for HCV RNA provides an indication of detection of current infection among those tested. The overall trend for the East Midlands shows a decline from 50% to below 20%. Although there has been a decline in positivity, the volume of testing has broadly increased, from 2,161 to 5,458, showing testing is reaching a wider population over this period.
Figure 13. Percentage of individuals testing HCV RNA positive among those tested in sentinel laboratories, by operational delivery network (ODN), 2020 to 2024
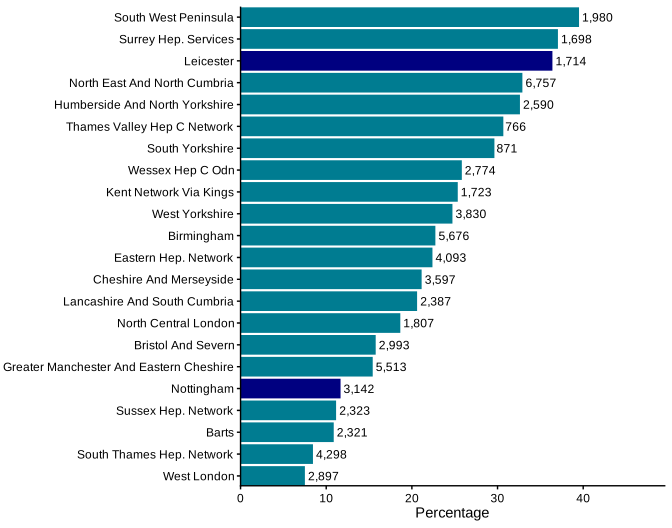
Data source: SSBBV. For more information, see Information on data sources.
Numbers next to bars indicate the number of positive cases.
Positivity in Leicester was 30.8% from 6,341 tests, compared to Nottingham where the positivity was 12.7% from 30,549 tests. Although differences are likely to reflect local testing pathways and the underlying burden of chronic hepatitis C infection within each network, for this data it is important to bear in mind the comments made about Figure 11 regarding the difference in submitted data from Nottingham and Leicester ODN.
Testing and diagnosis in people who inject drugs (PWID)
Figure 14. Percentage of Unlinked Anonymous Monitoring (UAM) Survey participants with evidence of ever being infected with HCV (anti-HCV), East Midlands UKHSA region and England, 2015 to 2024
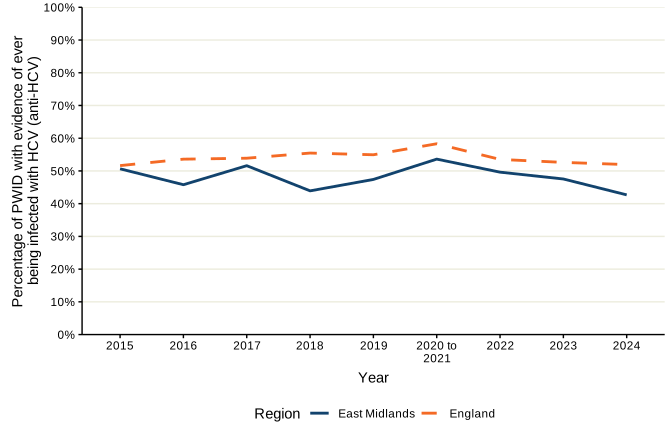
Data sources: UAM Survey. For more information, see Information on data sources.
Note 21: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
The proportion of people who inject drugs with evidence of ever having been infected with hepatitis C remained lower in the East Midlands compared to England throughout most of the reporting period. Estimates fluctuated over time, including a decline in 2024. Regional estimates should be interpreted cautiously because of relatively small sample sizes.
Figure 15. Percentage of Unlinked Anonymous Monitoring (UAM) Survey participants ever infected with HCV who have chronic HCV infection, East Midlands UKHSA region and England, 2015 to 2024
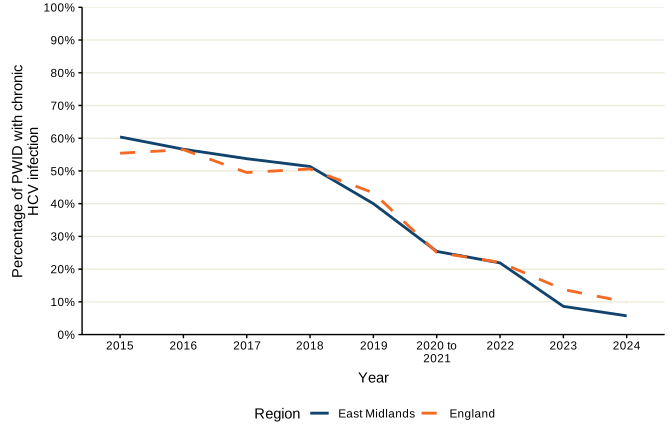
Data sources: UAM Survey. For more information, see Information on data sources.
Note 22: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
The prevalence of chronic hepatitis C infection among PWID provides an indicator of ongoing transmission and treatment coverage within this population. Overall, the East Midlands has shown a decline in prevalence, from 60.4% in 2015 to 5.7% in 2024, similar to the England pattern of prevalence of 55.4% in 2015 to 9.9% in 2024. This reduction is consistent with increased treatment uptake and progress towards hepatitis C elimination, although UAM Survey sampling variation should also be taken into consideration.
Figure 16. Percentage of Unlinked Anonymous Monitoring (UAM) Survey participants who self-reported being recently (current or previous year) tested for HCV, East Midlands UKHSA region and England, 2015 to 2024
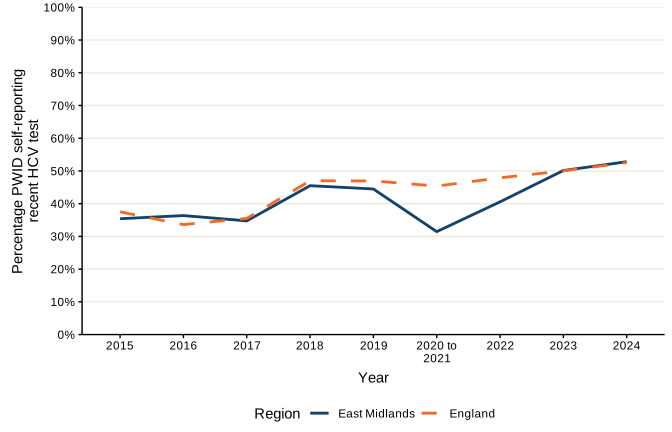
Data sources: UAM Survey. For more information, see Information on data sources.
Note 23: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
The proportion of PWID reporting a recent hepatitis C test reflects engagement with testing services. The pattern for the East Midlands is similar to England of a steady increase in proportion, with the East Midlands showing a sharper increase between 2021(31.5%) and 2024 (52.8%). Maintaining high testing coverage is essential for timely diagnosis, treatment initiation and prevention of onward transmission.
Hepatitis C treatment pathway
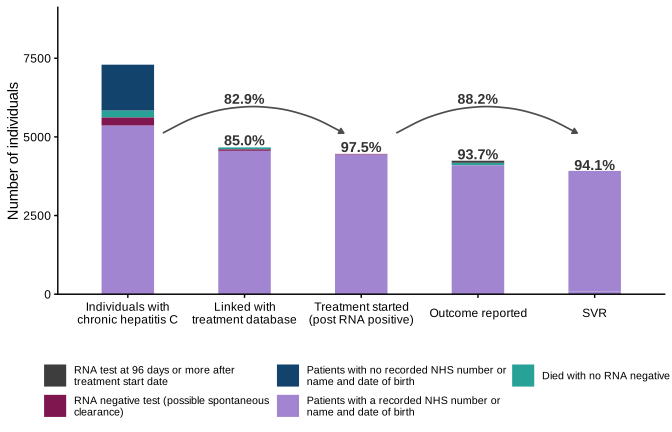
Figure 17. Treatment pathway in East Midlands UKHSA region, 2015 to 2024
Data source: SSBBV, NHS England (NHSE) Hepatitis C Patient Registry and Treatment Outcome System, NHSE Blueteq System. For more information, see Information on data sources.
Between 2015 and 2024:
- 85.0% of individuals with chronic hepatitis C were linked to treatment
- 97.5% of those linked to treatment had started treatment
- 82.9% of all individuals with chronic hepatitis C had started treatment, meeting the WHO elimination target for treatment coverage (≥80%)
- 93.7% of those who started treatment had a recorded outcome
- 94.1% of those with an outcome recorded achieved sustained virological response (SVR)
Definitions of the numerator and denominator for each metric shown in the treatment pathway are provided in Table 3 of the Technical Notes.
Note 24: in individuals testing hepatitis C virus RNA or core antigen positive with no linkage to the Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System, there are no time restrictions on a subsequent RNA or core antigen negative test after the initial RNA or core antigen positive test. Therefore, these individuals may include those that have spontaneous clearance of their infection or individuals who have cleared infection as a result of treatment but were not linked to the NHSE Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System.
Note 25: in the absence of a reported SVR as a treatment outcome in the NHSE Hepatitis C Patient Registry and Treatment Outcome System, an RNA or core antigen negative test recorded at 96 days or more after the treatment start date in SSBBV was used.
Definitions of the numerator and denominator for each metric shown in the treatment pathway are provided in Table 3 of the Technical Notes.
Treatment pathway by operational delivery network (ODN)
1) Leicester ODN
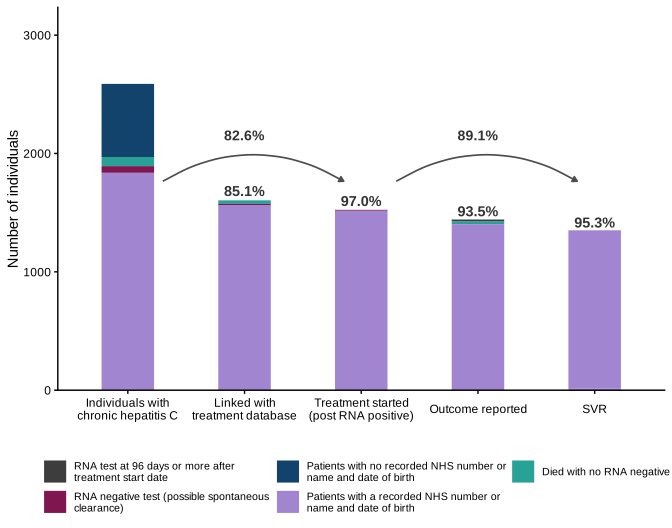
Figure 18. Treatment pathway by operational delivery network (ODN) in Leicester ODN, 2015 to 2024
Data source: SSBBV, NHSE Hepatitis C Patient Registry and Treatment Outcome System, NHSE Blueteq System. For more information, see Information on data sources.
See notes 24 and 25.
Note 26: ODN boundaries do not fully align with UKHSA regional boundaries, so not all East Midlands residents may be captured in these ODN charts. ODN charts are presented within this report for the region containing the majority of their residents. Consequently, these charts may include cases from outside the region, and some East Midlands residents may be in ODNs falling in other regions and so included in other regions’ reports.
Between 2015 and 2024:
- 85.1% of individuals with chronic hepatitis C were linked to treatment
- 97.0% of those linked to treatment had started treatment
- 82.6% of individuals with chronic hepatitis C had started treatment, meeting the WHO elimination target for treatment coverage (≥80%)
- 93.5% of those who started treatment had a recorded outcome
- 95.3% of those with an outcome recorded achieved SVR; 89.1% of those who started treatment achieved SVR
A total of 3.9% of cases resident in the East Midlands fall into the South Yorkshire ODN; data for this ODN is captured in the ‘Spotlight on Hepatitis C in the Yorkshire and Humber Region’ report.
2) Nottingham ODN
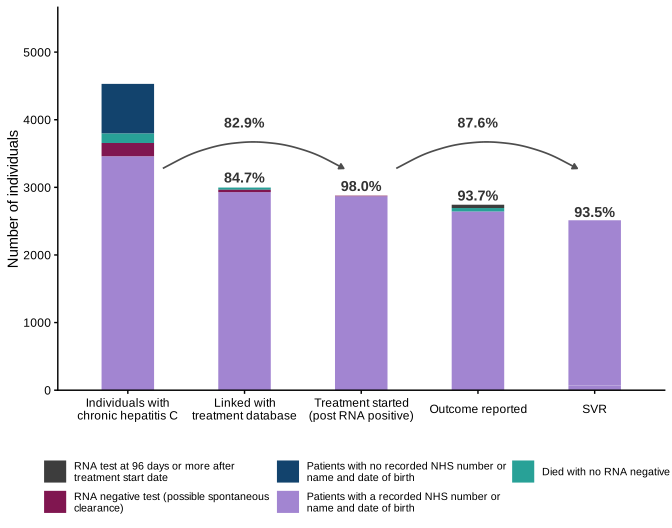
Figure 19. Treatment pathway by operational delivery network (ODN) in Nottingham ODN, 2015 to 2024
Data source: SSBBV, NHSE Hepatitis C Patient Registry and Treatment Outcome System, NHSE Blueteq System. For more information, see Information on data sources.
See notes 24, 25 and 26.
Between 2015 and 2024:
- 84.7% of individuals with chronic hepatitis C were linked to treatment
- 98.0% of those linked to treatment had started treatment
- 82.9% of individuals with chronic hepatitis C had started treatment, meeting the WHO elimination target for treatment coverage (≥80%)
- 93.7% of those who started treatment had a recorded outcome
- 93.5% of those with an outcome recorded achieved SVR
- 87.6% of those who started treatment achieved SVR
3.9% of cases resident in the East Midlands fall into the South Yorkshire ODN; data for this ODN is captured in the ‘Spotlight on Hepatitis C in the Yorkshire and Humber Region’ report.
Definitions of the numerator and denominator for each metric shown in the treatment pathway are provided in Table 3 of the Technical Notes.
East Midlands accounted for 5,363 individuals who tested positive for hepatitis C virus RNA or core antigen and had a recorded NHS number or name and date of birth (DOB) reported through SSBBV who had not died before linkage to treatment and where there was no evidence of possible spontaneous clearance. Treatment pathways were broadly similar across the region’s ODNs with high levels of linkage to care, treatment initiation and sustained viral response among those with treatment outcomes available. Variations between ODNs should be interpreted in the context of local population size and case mix, along with any data caveats.
Achievement of the WHO elimination target for treatment coverage would mean a value equal to or greater than 80% of individuals with chronic hepatitis C starting treatment during a specified time frame. For the East Midlands this was 82.9% meaning this target was achieved. The WHO elimination target was achieved by both ODNs in the East Midlands, with Leicester achieving 82.6% and Nottingham 82.9% for this target between 2015 and 2024, meaning good progress is being made across the region.
Both ODNs had high proportions of individuals achieving SVR out of those who had started treatment, 89.1% and 87.6% in Leicester (Leicester, Leicestershire, Northampton, Kettering and Rutland) and Nottingham (Nottingham, Nottinghamshire, Derby, Derbyshire & Lincolnshire) respectively.
These findings demonstrate high treatment uptake and effectiveness within the East Midlands treatment pathway.
Reinfections in individuals initiating treatment
For people who initiated treatment between 2015 and 2024 in East Midlands, the reinfection rate was 7.6 per 100 person-years (95% CI 6.9 to 8.4), which was higher than the England estimate (6.5 per 100 person-years, 95% CI 6.3 to 6.7). Among those who had injected drugs within the 3 years prior to treatment initiation, the reinfection rate was 9.7 per 100 person-years (95% CI 8.7 to 10.9), which was slightly higher than the England estimate (8.8 per 100 person-years, 95% CI 8.5 to 9.0). For individuals whose last injection was more than 3 years earlier, the rate was 7.0 per 100 person-years (95% CI 6.0 to 8.2), which was higher than the England estimate (4.0 per 100 person-years, 95% CI 3.8 to 4.2). Among people with any history of imprisonment before starting treatment, the reinfection rate was 7.7 per 100 person-years (95% CI 6.6 to 9.0), which was lower than the England estimate (9.4 per 100 person-years, 95% CI 9.0 to 9.7).
Monitoring HCV-related morbidity
Hospital admissions from HCV
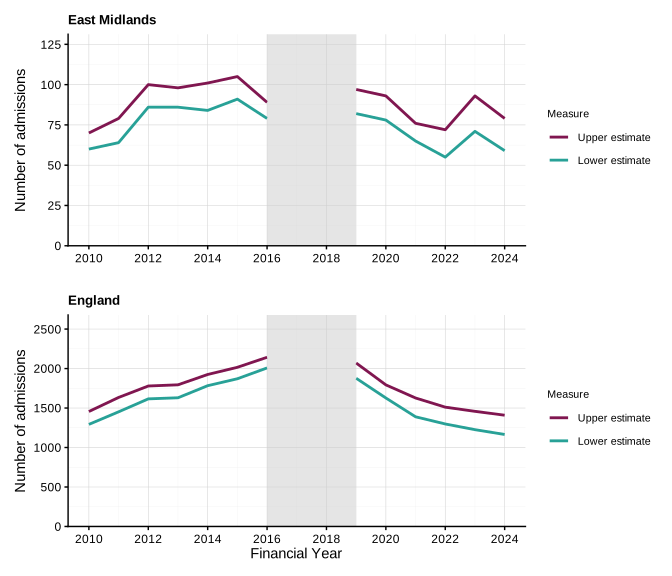
Figure 20. Number of first hospital admissions for hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC), East Midlands UKHSA region and England
Data source: Hospital Episode Statistics (HES), NHS England. Produced by the UK Health Security Agency. Copyright © 2025, reused with the permission of NHS England. All rights reserved. For more information, see Information on data sources.
Note 27: estimates of incidence of hepatitis C-related ESLD and/or HCC are not available for 2017 and 2018. This is due to an interruption in the supply of identifiers by NHS Trusts in tax year April 2017 to March 2018.
Note 28: data for 2024 is provisional and figures for previous years are subject to change as a result of late reporting and the associated de-duplication procedure.
Note 29: defined by codes or text entries for ascites, bleeding oesophageal varices, hepato-renal syndrome, hepatic encephalopathy, or hepatic failure.
Note 30: data based on HES as of December 2025.
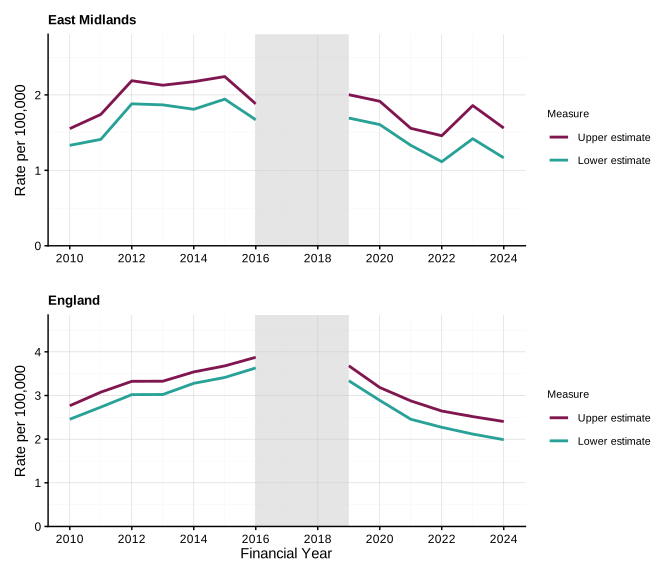
Figure 21. Rate per 100,000 of first hospital admissions for hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC), East Midlands UKHSA region and England
Data source: Hospital Episode Statistics (HES), NHS England. Produced by the UK Health Security Agency. Copyright © 2025, reused with the permission of NHS England. All rights reserved. For more information, see Information on data sources.
Note 31: estimates of incidence of hepatitis C-related ESLD and/or HCC are not available for 2017 and 2018. This is due to an interruption in the supply of identifiers by NHS Trusts in tax year April 2017 to March 2018.
Note 32: data for 2024 is provisional and figures for previous years are subject to change as a result of late reporting and the associated de-duplication procedure.
Note 33: defined by codes or text entries for ascites, bleeding oesophageal varices, hepato-renal syndrome, hepatic encephalopathy, or hepatic failure.
Note 34: data based on HES as of December 2025.
Figure 20 shows the number of first hospital admissions for hepatitis C-related end-stage liver disease and/or hepatocellular carcinoma, which provide a measure of severe disease burden. In the East Midlands, since 2015 there appears to be a downward trend, from 91 hospital admissions lower bound value and 105 upper bound value in 2015, compared to 2024 where there were 59 and 79 admissions respectively, suggesting a reduction in severe hepatitis C-related morbidity. Trends over time help assess the impact of prevention and treatment programmes.
Figure 21 shows rates of first hospital admissions in the East Midlands and England, with the East Midlands being consistently lower than rates for England. Since 2019 England has seen a decrease in rates of first hospital admissions. For the East Midlands, although the trend is generally the same, it is not as smooth, but rates remain small, being 1.7 and 2.0 lower and upper estimate rates per 100,000 respectively in 2019 compared to 1.2 and 1.6 for the corresponding rates in 2024.
HCV-related mortality
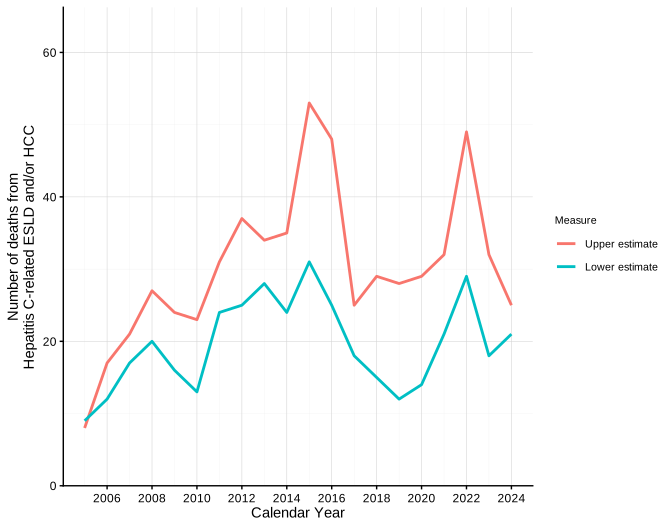
Figure 22. Number of deaths from hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC), East Midlands UKHSA region, 2005 to 2024
Data source: ONS Mortality and ONS MYE. For more information, see Information on data sources.
The number of deaths attributable to hepatitis C-related liver disease has fluctuated over time. Due to new methodologies being used to derive better estimates for mortality data there are 2 estimates giving the 2 trend lines in the figure above, a lower and upper estimate. The lower estimate of this range is similar to the previous methodology using only ONS death registration data, while the upper bound uses ONS death registration data linked to data on hospital episode statistics (HES) data on viral hepatitis, ESLD and/or HCC and laboratory data on viral hepatitis diagnoses.
For the East Midlands both upper and lower estimates suggest mortality increased during the early years of the reporting period before fluctuating in more recent years. In 2024, the lower-bound estimate was 21 deaths and the upper-bound estimate was 25 deaths.
Monitoring mortality trends remains an important measure for assessing progress towards reducing the severe consequences of chronic hepatitis C infection.
Figure 23. Mortality rate per 100,000 population for hepatitis C-related end-stage liver disease (ESLD) and/or hepatocellular carcinoma (HCC) by UKHSA region, 2020 to 2024

Data source: ONS Mortality and ONS MYE. For more information, see Information on data sources.
Of the 9 UKHSA regions, the East Midlands had the third lowest mortality rate (0.99 per 100,000 population) for hepatitis C-related ESLD and/or HCC between 2020 and 2024, and has a lower rate than the rate for England (1.3 per 100,000 population). To note, the updated ‘upper estimate’ methodology provides a more complete assessment of HCV‑related mortality but may produce values that differ from previous surveillance outputs.
Prevention of infection by harm reduction
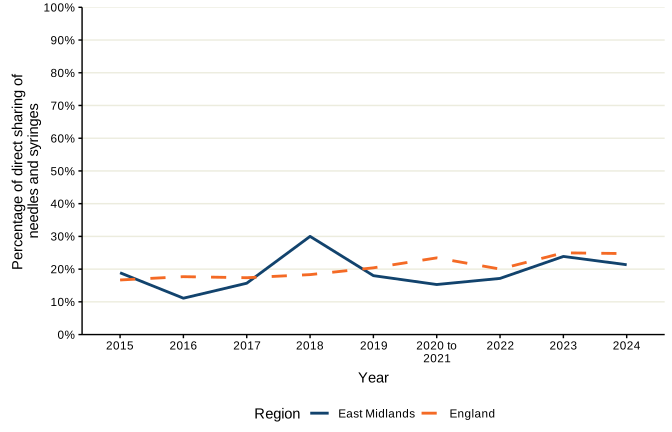
Figure 24. Reported level of direct sharing of needles/syringes among people who inject drugs (PWID), in the preceding 4 weeks, East Midlands UKHSA region and England, 2015 to 2024
Data sources: UAM Survey. For more information, see Information on data sources.
Note 35: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined.
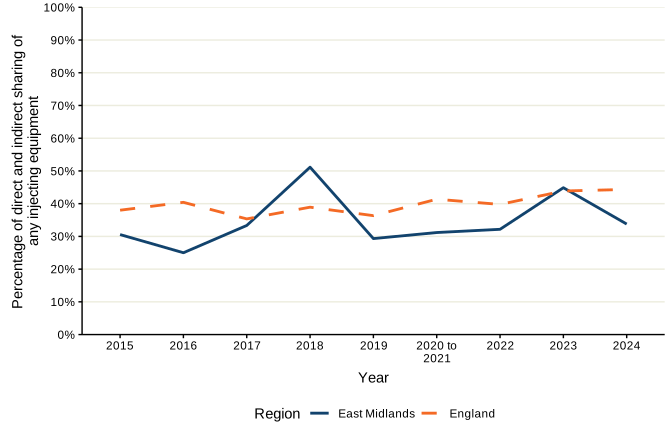
Figure 25. Reported level of direct and indirect sharing of injecting equipment among people who inject drugs (PWID), in the preceding 4 weeks, East Midlands UKHSA region and England, 2015 to 2024
Data sources: UAM Survey. For more information, see Information on data sources.
Note 36: during 2020 and 2021, recruitment to the UAM Survey was impacted by the COVID-19 pandemic. As a result, there were changes in the geographic and demographic profile of people taking part. This should be considered when interpreting data for these years. Due to small numbers, data for 2020 and 2021 is combined. See Technical Notes for more details.
Figure 24 shows self-reported levels of direct sharing of needles or syringes among PWID, and figure 25 shows levels of both direct and indirect sharing of injecting equipment among PWID both graphs are comparing the East Midlands to England. Sharing of injecting equipment remains a key risk factor for hepatitis C transmission, and reducing these behaviours over time continues to be a challenge among this risk group.
The levels in the East Midlands have remained similar to those for England from 2015 to 2024, showing a small increase over time 30.6% to 33.8% compared to 38% to 44.4% in England which is of continued concern. The East Midlands has levelled out since 2019 (29.3%), showing a small peak in activity in 2023 where it increased to 44.9%. In the latest year of data, 2024, there was a small decrease to 33.8% of reported direct sharing of injecting equipment, compared to 44.4% seen in England. Year-to-year variation may reflect changes in participant characteristics, service engagement or sampling variability, particularly at regional level.
Information on data sources
Second Generation Surveillance System (SGSS)
Brief description
SGSS captures routine laboratory surveillance data on infectious diseases and antimicrobial resistance from laboratories within England. Along with a number of other organisms, hepatitis C is notifiable under the Health Protection (Notifications) Regulations (2010).
Technical notes
Laboratory reports of new diagnoses of HCV include positive test results for anti-HCV and HCV-RNA tests and are submitted to UKHSA or predecessor organisations via SGSS/CoSurv.
Data is assigned to local authority and UKHSA region by patient postcode where present, if patient postcode is unknown, data is assigned to local authority and UKHSA region of registered general practice; where both patient postcode and registered general practice are unknown data is assigned to local authority and UKHSA region of laboratory.
Dates are assigned based on earliest positive specimen date. Patient identifiable data submitted by NHS laboratories is variable, particularly from sexual health and drug and alcohol services, which limits the ability to de-duplicate.
Laboratory reports for children under 1 year of age are excluded from the analyses to rule out detecting maternal antibody. Rates per 100,000 have been calculated using mid-year population estimates (MYE) supplied by the Office for National Statistics (ONS).
Caveat: SGSS data in this report may differ from data shown in the Hepatitis C in England report and from data reported in other surveillance outputs at a different point in time. This is due to the SGSS dataset being a live system and a number of cleaning, de-duplication, remapping and other operational processes being routinely applied to the data to improve data quality.
Data extracted from Sentinel Surveillance of bloodborne virus testing (SSBBV) and SGSS will vary for several reasons and should not be compared: the 2 systems have collected data over different historical periods, with data reported to SGSS and predecessor systems since 1995, whereas SSBBV has been running since 2002. Data reported to SSBBV reflects the timeframe from when the laboratory joined the surveillance system, with laboratories joining more recently having less data available than laboratories who have been reporting since 2002. Furthermore, whilst SGSS collects national level data, SSBBV collects data from a subset of laboratories. Currently, 35 laboratories report to SSBBV with an estimated 45% coverage testing in the GP registered population in England.
Finally, it is not possible to differentiate a previous or current infection in SGSS with limited HCV RNA or HCV Ag data available, therefore numbers presented will be a mixture of previous and current infections. However, SSBBV allows for the collection of all HCV markers enabling HCV antibody and HCV RNA or HCV Ag to be presented separately.
Sentinel Surveillance of Bloodborne Viruses (SSBBV)
Brief description
SSBBV is a sub-national surveillance system for BBV testing activity and results in England, managed by UKHSA. Established in 2002, it includes data on all positive and negative BBV tests processed by the sentinel laboratories that participate in SSBBV. Laboratory participation in SSBBV is voluntary and currently represents approximately 45% of the GP registered population in England. SSBBV includes the 2 laboratories that process DBS tests for the major drug services in England. Therefore, it is likely that the data covers most tests coming from drug services, where DBS is the main method of testing.
Technical notes
Patient identifiable data submitted by laboratories is variable, particularly from sexual health and drug and alcohol services, which limits the ability to de-duplicate. Data is de-duplicated subject to availability of date of birth, Soundex, NHS number and first initial. The proportion positive is calculated using the number of people tested.
For trends in hepatitis C antibody testing, SSBBV data is from 35 laboratories and is based on complete and consistent reporting since 2015 to remove any artificial increases or decreases in testing due to changes in reporting. This
means that the numbers of laboratories included for trend data may change each year depending on their reporting history. A positive test result first reported by participating laboratories may not reflect an individual’s first diagnosis.
Antibody testing excludes samples collected outside routine testing such as look back studies, reference testing, and children aged one year and under, whereas RNA or core antigen testing includes reference testing.
Reinfection
In England, 2 criteria have been used to identify hepatitis C virus reinfection, either of which would establish a person as experiencing reinfection:
- individuals with a positive hepatitis C virus RNA test at least 196 days (28 weeks) after treatment start date among those with a SVR during their first treatment period
- individuals who have a subsequent period of treatment after an initial SVR, and where this subsequent treatment period was at least 196 days after first treatment start date
For both definitions SVR is defined as either a recorded SVR or proxy SVR from a negative RNA or core antigen result after treatment. A period of 196 days between first treatment and reinfection diagnosis is used to define reinfection as the majority of individuals receiving treatment will have cleared hepatitis C virus within 6 months (182 days). A further 2 weeks (14 days) is added to account for any delays in treatment initiations. Reinfection after spontaneous clearance is not included.
The estimate now includes multiple reinfections, whereby someone is treated after experiencing their first reinfection and achieves an SVR but then has a subsequent hepatitis C virus RNA or core antigen positive result. The data is reliant upon persons initiating treatment being added to the NHSE Blueteq System or NHSE Hepatitis C Patient Registry and Treatment Outcome System, sufficient identifiers being available to link between the treatment and SSBBV databases and on people being tested post treatment. It should be noted that there is no internationally agreed definition for defining hepatitis C reinfection and a different window period may be used to confirm SVR post treatment. For example, Scotland uses a negative test between 10 weeks and 12 months post treatment to confirm SVR. As we progress towards elimination of hepatitis C virus as a public health threat, ongoing work across the UK will aim to harmonise definitions of reinfection where possible and utilise multiple methods, including the use of whole genome sequencing, to better understand reinfection.
Hospital Episode Statistics (HES)
Brief description
New cases of hepatitis C-related ESLD and/or HCC are monitored using HES for incidence of ESLD and HCC, and HES and SGSS for hepatitis C diagnoses. This is a new method in 2025 which presents data as a sensitivity analysis with upper and lower bounds, mirroring the updated methodology for deaths from hepatitis C-related ESLD and/or HCC. New cases are identified by first linking all episodes of ESLD and/or HCC in HES for an individual using their unique patient identifier. These are classified as ‘new’ if no previous episodes of ESLD and/or HCC for that individual are found in at least the previous 5 years (less than 1% of HCC and/or ESLD episodes are estimated to have had a previous episode more than 5 years earlier).
Linkage to hepatitis C diagnoses uses the following 2 methods:
- Lower bound: linkage to episode of hepatitis C in HES for all years: first diagnosis of ESLD and/or HCC linked to hepatitis C diagnosis in HES for any year. First diagnosis of ESLD and/or HCC used data from 2003 to 2024 to give minimum 5-year window for first episode starting at 2010. Hepatitis C diagnosis started from 1 April 2000 onwards. Hepatitis C includes both acute and chronic cases.
- Upper bound: linkage to diagnoses of hepatitis C in HES or surveillance data for all years: first diagnosis of ESLD and/or HCC linked to earliest diagnosis of hepatitis C in any of HES or SGSS.
Due to the loss of identifiers in HES data for 2017, data for 2017 and 2018 is omitted.
More information is available in the Appendix 3 of Hepatitis C in England 2022.
Hepatitis C Treatment Pathway data
Brief description
Hepatitis C treatment initiation data is used to monitor access to hepatitis C treatment. Treatment coverage is defined as the proportion of individuals diagnosed with chronic hepatitis C (hepatitis C virus RNA or hepatitis C core antigen test positive) and who initiated treatment during a specified time frame over the number of individuals diagnosed with chronic hepatitis C for the specified time period.
Technical notes
Records from individuals with a diagnosis of chronic hepatitis C reported through SSBBV (positive hepatitis C virus RNA or antigen tests) are linked to the NHSE Hepatitis C Patient Registry and Treatment Outcome System using NHS number, name, DOB, hospital number and NHSE’s Blueteq System using NHS number, DOB, Blueteq number and excludes children aged under one year.
Patient identifiable data submitted by SSBBV laboratories is variable, particularly from sexual health and drug and alcohol services, which limits the ability to link data sets or de-duplicate. Data is de-duplicated subject to availability of DOB, Soundex, NHS number and first initial. Data quality is assessed on an ongoing basis to verify the number of people who tested positive for hepatitis C virus RNA or core antigen. As individuals are followed through the care pathway, the denominator is updated to exclude people who have died or who have evidence of spontaneous clearance.
In individuals testing hepatitis C virus RNA or core antigen positive with no linkage to the Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System, there are no time restrictions on a subsequent hepatitis C virus RNA or core antigen negative test after the initial RNA or core antigen positive test. Therefore, these individuals may include those that have spontaneous clearance of their hepatitis C virus infection or individuals who have cleared their hepatitis C virus infection as a result of treatment but were not linked to the NHSE Hepatitis C Patient Registry and Treatment Outcome System or NHSE’s Blueteq System.
The NHSE Hepatitis C Patient Registry and Treatment Outcome System was commissioned by NHSE in 2017 from the Arden and Greater East Midlands Commissioning Support Unit to capture more detailed information for patients. The hepatitis C virus treatment monitoring in England report summarises the data held within the registry and Treatment Outcome System up to the end of April 2018.
Table 3. Definitions of the numerator and denominator for metrics reported in the hepatitis C treatment pathway
| Metric | Numerator | Denominator |
|---|---|---|
| Proportion of individuals diagnosed with chronic hepatitis C who were linked to specialist treatment services | Number of individuals linked to specialist hepatitis C treatment services via ODNs (identified through successful linkage to the NHSE Hepatitis C Patient Registry and Treatment Outcome System and/or NHSE’s Blueteq System). | Number of individuals who tested positive for hepatitis C virus RNA or core antigen with NHS number or name and date of birth (DOB) reported through SSBBV who had not died before linkage to treatment and where there was no evidence of possible spontaneous clearance. |
| Proportion of individuals linked to specialist treatment services who initiated treatment | Number starting treatment. | Number of individuals linked to specialist hepatitis C treatment services via ODNs. |
| Proportion of individuals diagnosed with chronic hepatitis C who initiated treatment (WHO target) | Number starting treatment. | Number of individuals who tested positive for hepatitis C virus RNA or core antigen with NHS number or name and DOB reported through SSBBV who had not died before linkage to treatment and where there was no evidence of possible spontaneous clearance. |
| Proportion of individuals who initiated treatment who had an outcome reported or had an RNA or core antigen test reported through SSBBV | Number of individuals who had a treatment outcome reported via the NHSE Hepatitis C Patient Registry and Treatment Outcome System, or in the absence of a recorded outcome, an RNA or core antigen test (positive or negative) recorded at 96 days or more after the treatment start date in SSBBV. | Number of individuals who started treatment. |
| Proportion of individuals who initiated treatment and were reported to have achieved SVR either as a treatment outcome or had an RNA or core antigen negative result reported through SSBBV | Number clearing hepatitis C virus as a treatment outcome, or in the absence of a reported SVR, an RNA or core antigen negative test recorded at 96 days or more after the treatment start date in SSBBV. The proportion reported as clearing hepatitis C virus is likely to be lower than the true proportion. | Number starting treatment. |
| Proportion of individuals who initiated treatment and had an outcome reported or an RNA or core antigen test reported through SSBBV who were reported to have achieved SVR or had an RNA or core antigen negative test result | Number clearing hepatitis C virus as a treatment outcome, or in the absence of a reported SVR, an RNA or core antigen negative test recorded at 96 days or more after the treatment start date in SSBBV. | Number of individuals with a treatment outcome recorded or with an RNA or core antigen test (positive or negative) recorded at 96 days or more after the treatment start date in SSBBV. |
Office for National Statistics (ONS) Mortality data
Brief description
The number of hepatitis C virus-related deaths are used to measure mortality. Deaths are based on the year of death. International classification of diseases (ICD) tenth revision (ICD-10) codes for ESLD and HCC are used to identify deaths with ESLD or HCC as a cause or associated with hospital admissions for these conditions. The number of deaths was estimated using slightly different ICD-10 codes from those used by WHO. A comparison of the codes used can be found in the Hepatitis C in England 2022 report.
Technical notes
An updated method for estimating deaths from hepatitis C-related ESLD and/or HCC has been used for this report. The previous method of reporting that solely used death data from the Office for National Statistics (ONS) was shown to underestimate mortality rates from hepatitis C-related liver disease by up to 60%. To address this, an updated method is used that presents the estimated mortality attributable to hepatitis C as a range. The lower bound of this range is similar to the previous methodology using only ONS death registration data, while the upper bound uses ONS death registration data linked to data on hospital episode statistics (HES) data on viral hepatitis, ESLD and/or HCC and laboratory data on viral hepatitis diagnoses. The updated methodology has been applied to all previous years and includes deaths by year of death rather than by year the death was registered as was previously used.
Lower bound represents deaths where ESLD and/or HCC and hepatitis C were reported in ONS death registration data (as year of death is now used this is not comparable with previously published estimates which used year the death was registered). Upper bound represents deaths where ESLD and/or HCC were reported in ONS death registrations or identified in HES hospital admissions data linked to deaths data, and hepatitis C diagnoses were identified by linking between ONS deaths, HES hospital admissions data and laboratory diagnosis data to yield a maximum number of deaths attributable to hepatitis C-related ESLD and/or HCC. Excluding deaths of people aged under 16 and deaths registered in England where the deceased’s usual residence is outside England. ESLD is defined by codes or text entries for ascites, bleeding oesophageal varices, hepato-renal syndrome, hepatic encephalopathy, or hepatic failure.
Unlinked Anonymous Monitoring (UAM)
Brief description
The voluntary UAM survey recruits people who have ever injected psychoactive drugs through specialist services (such as needle and syringe programmes and addiction treatment centres) across England, Wales and Northern Ireland. Those who agree to take part self-complete a questionnaire and provide a biological specimen that is tested anonymously for HIV, hepatitis B and hepatitis C.
Technical notes
Regional level data from the UAM survey should be interpreted cautiously as the survey recruits participants through a nationally reflective sample of the services provided to people who inject drugs.
The COVID-19 pandemic, and associated changes in service delivery, impacted on recruitment to the survey in 2020 and 2021. By 2022, the number of services taking part in the survey, and the number of participants was comparable to pre-pandemic levels.
Published regional-level data and more information can be found at People who inject drugs: HIV and viral hepatitis monitoring.
Acknowledgements
We would like to thank the following:
- local laboratories for supplying the hepatitis data
- the UKHSA Blood Safety, Hepatitis, STI and HIV Division for collection, analysis and distribution of data
- the UKHSA Epidemiology Data Science unit (part of the Epidemiology Data Science team) for producing the charts and figures contained in this report
- the Office for National Statistics (ONS), which carried out the original collection and collation of the mid-year population estimates, death registration data and geographic boundary data but bears no responsibility for their future analysis or interpretation)
- the Hospital Episode Statistics (HES), NHS England, produced by UKHSA
About Field Services
Field Services is a division within UKHSA that provides a national service comprising geographically dispersed multi-disciplinary teams integrating expertise in Field Epidemiology, Public Health Microbiology, Rapid Investigation, Real-time Syndromic Surveillance, Field Epidemiology Training, and Data Science to strengthen the surveillance, epidemiological intelligence and response functions of UKHSA.
You can contact your local Field Services team at FSMidlands@ukhsa.gov.uk
If you have any comments or feedback regarding this report or the Field Services, please contact FS.Central@ukhsa.gov.uk