Surveillance of respiratory syncytial virus: winter 2025 to 2026
Published 13 August 2026

© Crown copyright 2026
This publication is licensed under the terms of the Open Government Licence v3.0 except where otherwise stated. To view this licence, visit nationalarchives.gov.uk/doc/open-government-licence/version/3 or write to the Information Policy Team, The National Archives, Kew, London TW9 4DU, or email: psi@nationalarchives.gov.uk.
Where we have identified any third party copyright information you will need to obtain permission from the copyright holders concerned.
This publication is available at https://www.gov.uk/government/publications/surveillance-of-respiratory-syncytial-virus-winter-2025-to-2026/surveillance-of-respiratory-syncytial-virus-winter-2025-to-2026
Main points
Disease patterns
In the 2025 to 2026 season:
-
overall RSV activity across all nations and surveillance systems started around weeks 44 and 45 2025 (start of November), and peaked across nations during weeks 49 to 52 (December) 2025, with some indicators (particularly for older adults), peaking in January 2026. Activity then steadily declined and reached low levels across most nations and surveillance systems in weeks 9 and 10 2026 (ending 2 and 9 March 2026)
-
across nations and systems the epidemic wave including peak activity appeared to occur later than in previous seasons
-
in multiple indicators across the nations, lower RSV activity was observed as the vaccination programmes took fuller effect. Increased testing and therefore case ascertainment may have offset vaccination-associated admission reductions in some surveillance systems
Vaccine uptake
Vaccination programmes to protect against RSV began on 1 September 2024 in England, Wales, and Northern Ireland, and on 1 August 2024 in Scotland. Data from Northern Ireland during the 2025 to 2026 season was not available for this report.
In England:
- 65.0% of eligible older adults had received an RSV vaccine by the end of May (50.1% of older adults in the routine cohort, 70.4% of older adults in the catch-up cohorts)
- 55.6% of women giving birth between the start of the programme and February 2026 had received an RSV vaccine prior to birth. In the last 12 months with complete data (between March 2025 and February 2026) 61.7% of women giving birth had received an RSV vaccine
In Scotland:
- during the 2025 to 2026 season, 68.8% of adults turning 75 had received an RSV vaccination. In the 2024 to 2025 season, 70.0% of older adults in the routine cohort and 70.7% of older adults in the catch-up cohorts had received an RSV vaccine
- 53.7% of pregnant women who reached 28 weeks of pregnancy had received an RSV vaccine since the start of the programme
In Wales:
- 64.9% of eligible older adults had received an RSV vaccine by the end of May 2026 (50.4% of older adults in the routine cohort, 71.4% of older adults in the catch-up cohorts)
- 50.0% of women giving birth between the start of the programme and May 2026 had received an RSV vaccine prior to birth. In the last 12 months with complete data available (June 2025 to May 2026), 56.2% of women giving birth had received an RSV vaccine
Vaccination impact
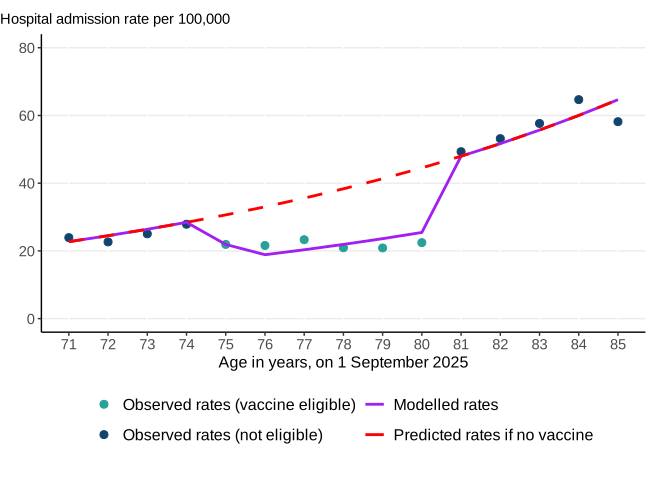
Vaccine impact analysis in England indicated a sustained reduction in expected RSV-related hospitalisation rates among eligible adults 75 to 80 years of age.
Community surveillance
Acute respiratory infection incidents
Health protection professionals in the national agencies are notified of potential public health incidents, including outbreaks affecting different institutions, which are investigated, risk assessed and managed. There is some variation in reporting and recording practices between settings and caution is advised in comparisons.
England
Information on acute respiratory infection (ARI) incidents is based on situations reported to UK Health Security Agency (UKHSA) health protection teams (HPTs) and entered onto the Case and Incident Management System (CIMS).
These include confirmed outbreaks of ARI (2 or more laboratory-confirmed cases of SARS-CoV-2, influenza, RSV or other respiratory pathogens) linked to a particular setting, as well as situations where an outbreak is suspected. All suspected outbreaks are further investigated by the HPT in liaison with local partners. Respiratory sampling to identify the virus involved is encouraged, however where clinical-epidemiological risk assessment suggests a high probability of influenza this may not be done. Incident reports are manually reviewed during the data cleaning process and assigned to a specific pathogen only if confirmation of a positive virological test can be identified.
Reporting practices are known to vary between seasons and between regions. Any interpretation of temporal and regional trends should consider the likelihood of differences in reporting of ARI incidents over time and between regions.
In England, there were a total of 3,866 ARI incidents in closed settings reported between week 40 (ending 5 October) 2025 and week 14 (ending 5 April) 2026. Virological testing information was available for 2,091 (54.1%) incidents, of which 274 (13.1%) were due to RSV, 84 (4.0%) were due to multiple pathogens (at least one of which was RSV) and 1,733 incidents (82.9%) were due to other pathogens, including 1,159 influenza and 360 SARS-CoV-2. In 1,775 (45.9%) incidents, virological testing results were not available.
Of the incidents in which RSV was virologically confirmed, 287 (80.2%) were reported from care homes, 59 (16.5%) from educational settings, 10 (2.8%) from hospital settings, 1 (0.3%) from prisons and 1 (0.3%) from other settings (Table 1).
Table 1. The number of incidents in England by institution and pathogen between week 40 2025 and week 14 2026
| Setting | RSV | Mixed outbreak (with RSV present) | Other pathogens | Not available/tested | Total |
|---|---|---|---|---|---|
| Care home | 208 | 79 | 1,449 | 1,454 | 3,190 |
| Educational setting | 56 | 3 | 111 | 284 | 454 |
| Hospital | 8 | 2 | 139 | 8 | 157 |
| Prison | 1 | 0 | 5 | 7 | 13 |
| Other | 1 | 0 | 29 | 22 | 52 |
| Total | 274 | 84 | 1,733 | 1,775 | 3,866 |
Reported RSV outbreaks peaked in week 3 2026 (week ending 18 January 2026), with the majority of RSV outbreaks occurring in care home settings. The majority of RSV outbreaks reported in educational settings occurred between week 46 (ending 16 November) and week 51 (ending 21 December) 2025 (Figure 1).
Figure 1. Number of RSV outbreaks by week and setting, 2025 to 2026 season, England [note 1]
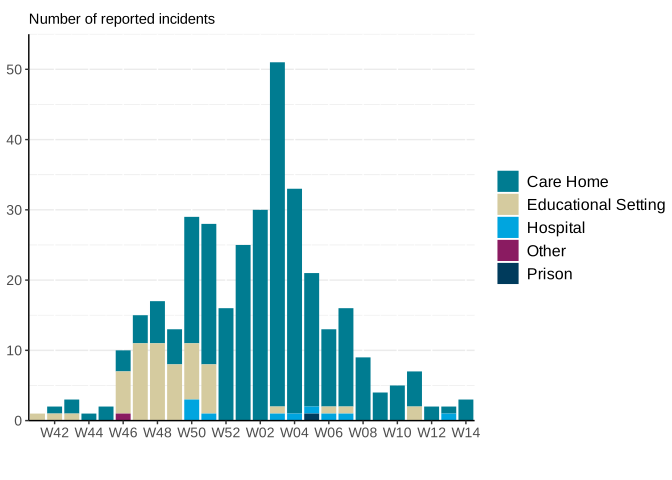
Note 1: includes outbreaks of RSV as well as mixed outbreaks where at least one of the pathogens identified was RSV.
Scotland
In Scotland, outbreaks are defined where at least 2 cases (laboratory confirmed and/or suspected) of any ARI are detected within 48 hours in any setting. To be defined as an ARI outbreak, either the pathogen or the scenario entered onto HPZone must be clearly indicative of ARI as the type of outbreak. Where a pathogen is listed but the outbreak is not laboratory confirmed, or where the pathogen is unknown, these have been labelled ‘Not available/tested’.
Between week 40 2025 (week ending 5 October) and week 14 2026 (week ending 5 April) there were 37 confirmed RSV outbreaks, of which 32 occurred within care homes, 3 in hospital settings, one in an educational setting and one in another setting (Table 2).
Table 2. Number of ARI incidents by institution and pathogen, Scotland, 2025 to 2026 season
| Setting | Respiratory syncytial virus (RSV) | Other pathogens | Not available/tested | Total |
|---|---|---|---|---|
| Prison | 0 | 1 | 0 | 1 |
| Other | 1 | 5 | 5 | 11 |
| Hospital | 3 | 13 | 2 | 18 |
| Educational setting | 1 | 1 | 63 | 65 |
| Care home | 32 | 166 | 136 | 334 |
| Total | 37 | 186 | 206 | 429 |
Wales
In Wales, outbreaks are reported on the Tarian case and incident management system.
There were a total of 148 ARI outbreaks reported between week 40 (ending 5 October) 2025 and week 12 (ending 22 March) 2026. Virological results indicated that 6 outbreaks were due to RSV, of which all were in residential homes. Of the 6 confirmed RSV outbreaks, 2 also involved confirmed influenza, one involved rhinovirus, and another involved streptococcal infection.
Northern Ireland
Suspected ARI incidents in different settings are notified to the Public Health Agency (PHA) Acute Response Duty Room and recorded in HPZone, a case and incident management system. A confirmed ARI outbreak can be defined as where there are 2 or more laboratory confirmed cases with onset within a 14 day period, where transmission within the same setting is considered the likely cause.
In Northern Ireland, there were a total of 211 confirmed ARI outbreaks reported to the PHA Acute Response Duty Room from week 40, 2025 (week commencing 29 September) to week 16, 2026 (week commencing 13 April). Of these, 112 (53.1%) were reported in hospital settings, 93 (44.1%) in care home settings and 6 (2.8%) in other settings. Of the 211 ARI outbreaks, 11 (5.2%) were confirmed RSV outbreaks, the vast majority being reported in care home settings (81.8%; 9 out of 11).
Table 3. Number of ARI incidents by institution and pathogen, Northern Ireland, 2025 to 2026 season
| Setting | RSV | Other pathogens | Total |
|---|---|---|---|
| Care home | 9 | 84 | 93 |
| Hospital | 2 | 110 | 112 |
| Other | 0 | 6 | 6 |
| Total | 11 | 200 | 211 |
Primary care surveillance
General practice sentinel swabbing
RCGP sentinel swabbing scheme in England
Primary care surveillance is undertaken in collaboration with the Royal College of General Practitioners (RCGP) Research and Surveillance Centre (RSC). More information on the methodology can be found in the data quality report.
A subset of the RCGP RSC network (around 300 GP practices) take part in weekly virology surveillance. Practices collect nasopharyngeal samples from patients presenting to their GP with symptoms of any ARI with an onset date within the last 7 days. The ARI diagnosis definition is subclassified into influenza-like illness (ILI), lower respiratory tract infections (LRTI), upper respiratory tract infections (URTI) and exacerbation of chronic lung disease (ECLD).
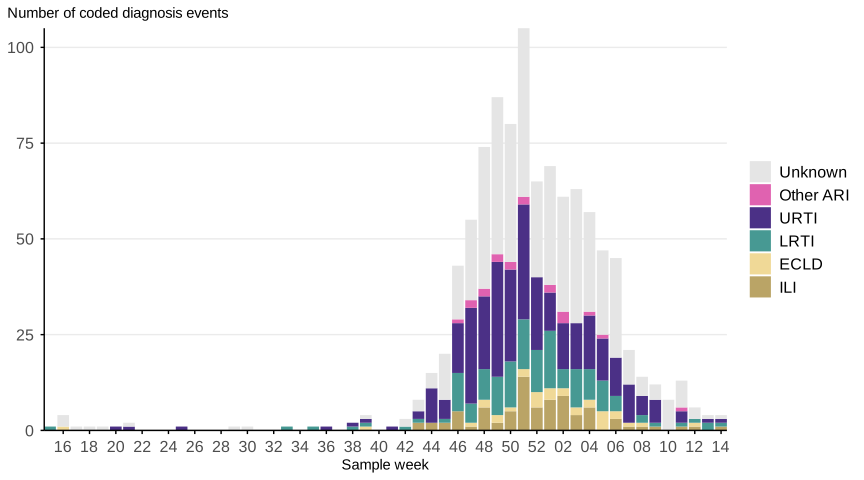
From week 15 (ending 13 April) 2025 to week 14 (ending 5 April) 2026, among all-age individuals with RSV infection, the most frequent coded ARI diagnosis was URTI, followed by LRTI and ILI (Figure 2).
Figure 2. Weekly number of RSV attendances by coded ARI in England, GP sentinel swabbing, 2025 to 2026 season
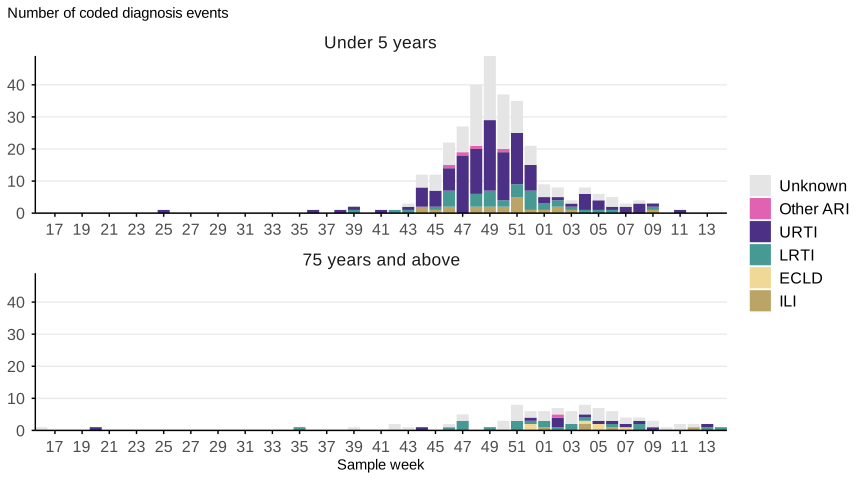
By age group, in those aged under 5 years with RSV, the most frequent coded ARI diagnosis was URTI, followed by LRTI and ILI. In those aged 75 years and over with RSV, the most frequent coded ARI was LRTI, followed by URTI and ILI (Figure 3).
Figure 3. Weekly number of RSV attendances by coded ARI in those aged under 5 years and 75 and over in England, GP sentinel swabbing, 2025 to 2026 season
Between week 15 (ending 13 April) 2025 and week 14 (ending 5 April) 2026, a total of 17,199 samples were tested for RSV and 1,004 were positive for RSV (Figure 4). Among the positive samples for RSV, 24.2% were positive for RSV A and 45.8% were positive for RSV B. 11 samples tested positive for both RSV A and RSV B. Starting from week 40 (ending 5 October) 2025, samples with more than 7 days between the sample collection date and the symptom onset date were excluded.
RSV positivity began to increase in week 42 (ending 19 October) 2025, peaked at week 1 (ending 4 January) 2026, and decreased thereafter (Figure 5). RSV B was predominant for most of the season.
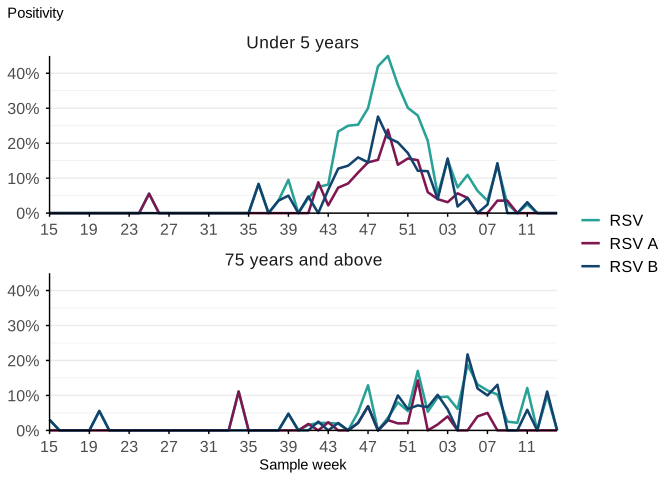
By age group, the highest RSV positivity was observed in children under 5 years; positivity peaked at 45.0% in week 49 (week ending 7 December) 2025. Among those aged 75 years and above, the highest RSV positivity rate was 18.8% reported in week 5 (week ending 1 February) 2026. During the peak season, RSV B was predominant in those aged under 5 years, and RSV B was also more commonly detected among those aged 75 years and above (Figure 6).
Figure 4. Weekly number of samples testing positive for RSV in England, GP sentinel swabbing scheme, 2025 to 2026 season
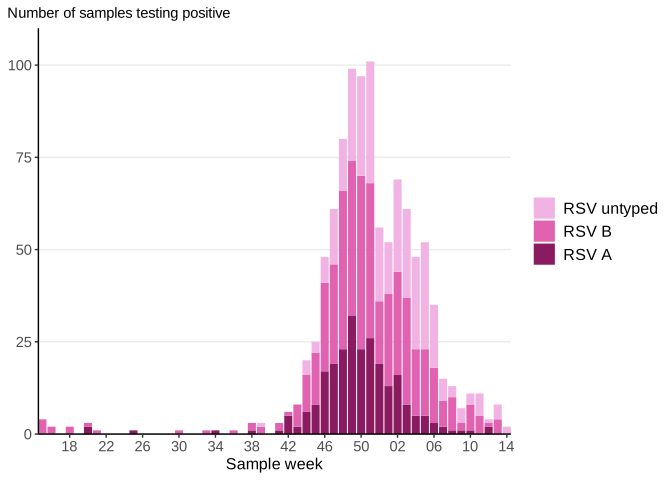
Figure 5. Weekly positivity for RSV, RSV A and RSV B in England, GP sentinel swabbing scheme, 2025 to 2026 season
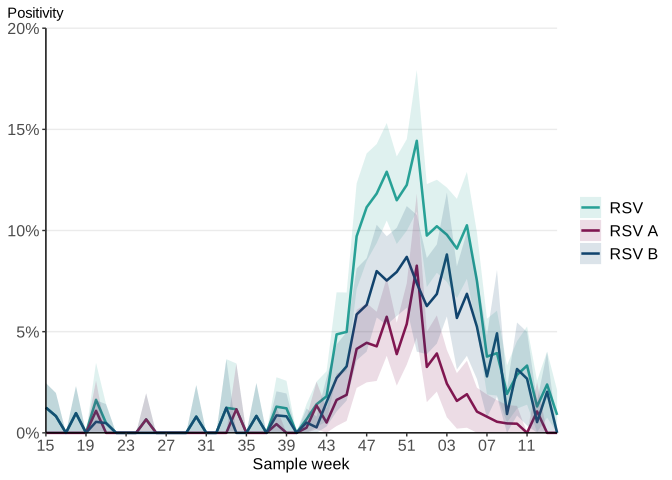
Figure 6. Weekly positivity for RSV, RSV A and RSV B in those aged under 5 years and aged 75 years and above, GP sentinel swabbing scheme, 2025 to 2026 season
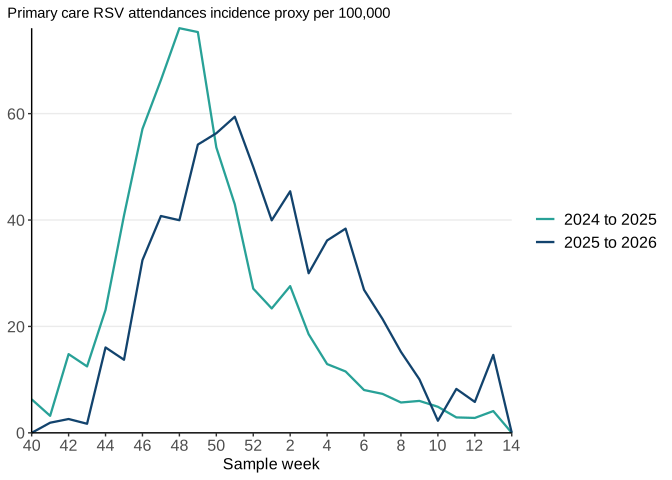
In the 2025 to 2026 season, the all-age primary care RSV attendances incidence proxy was higher than that observed in the 2024 to 2025 season (Figure 7) from week 50 (week ending 14 December) 2025. This is an experimental metric used as a proxy for the incidence of primary care RSV attendances per 100,000 population. This is a composite indicator calculated using the weekly ARI rate per 100,000 population multiplied by the weekly RSV positivity among the ARI presentations. The ARI rate is calculated within the wider RCGP RSC network of around 2,000 GP practices covering over 20 million registered patients of all ages across England. The RSV positivity is from a subset of the GP practices participating in the virology swabbing surveillance. This approach is described in the WHO pandemic influenza severity assessment (PISA) framework.
Figure 7. Primary care RSV attendances incidence rate per 100,000 all-age population (proxy) in England, GP sentinel swabbing
Scotland
Community Acute Respiratory Infection (CARI) surveillance is a sentinel community surveillance programme for a range of respiratory pathogens: SARS-CoV-2, influenza A and B, RSV, adenovirus, coronavirus (non-SARS CoV-2), human metapneumovirus, rhinovirus, parainfluenza and Mycoplasma pneumoniae. The programme is open to GP practices across all NHS Boards in Scotland. To become a sentinel site, GP practices voluntarily opt into the CARI programme. The number of participating practices and the number of practices returning samples each week can vary but is within a range of 100 to 150 practices typically covering approximately 15% of the total population. Patients in the community who consult a sentinel GP practice with respiratory symptoms and who meet the case definition for ARI are recruited, consented, and tested for the CARI programme. Clinicians also complete a symptoms checklist. More information on the methodology can be found in the overview of the CARI surveillance system.
Between week 15 (ending 13 April) 2025 to week 14 (ending 5 April) 2026, a total of 18,471 CARI samples were tested for RSV, of which 975 (5.3%) were positive for RSV.
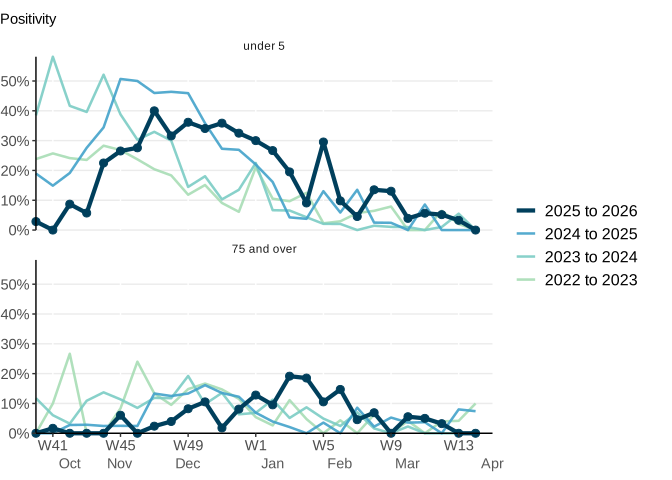
RSV test positivity increased exponentially from week 43 (ending 26 October) 2025, peaked in week 1 (commencing 29 December 2025) 2026 at 16.8% and declined thereafter (Figure 8). The highest RSV positivity was observed in children under 5 years, peaking at 40.0% in week 47 (week ending 23 November). The highest test positivity observed for those aged 75 years and over was in week 3 (ending 18 January) 2026 at 19.1% (Figure 9).
Figure 8. Weekly percentage of tests positive for RSV through CARI by season, Scotland, 2022 to 2026
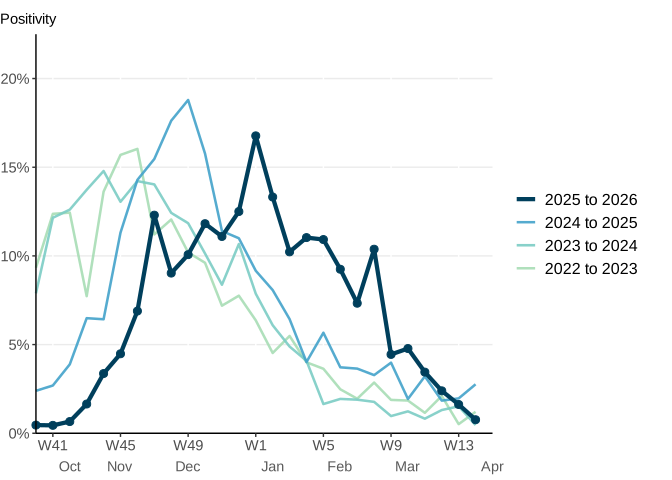
Figure 9. Weekly percentage of tests positive for RSV through CARI by age group and season, Scotland, 2022 to 2026
Wales
Virological surveillance samples are collected from individuals presenting with ILI, ARI, acute bronchitis or bronchiolitis symptoms at a network of 75 sentinel GPs across Wales. Surveillance samples are routinely tested for: influenza, SARS-CoV2, RSV, adenovirus, Mycoplasma pneumoniae, rhinovirus, parainfluenza, human metapneumovirus, human bocavirus, seasonal coronaviruses, enterovirus D-68 and other enteroviruses.
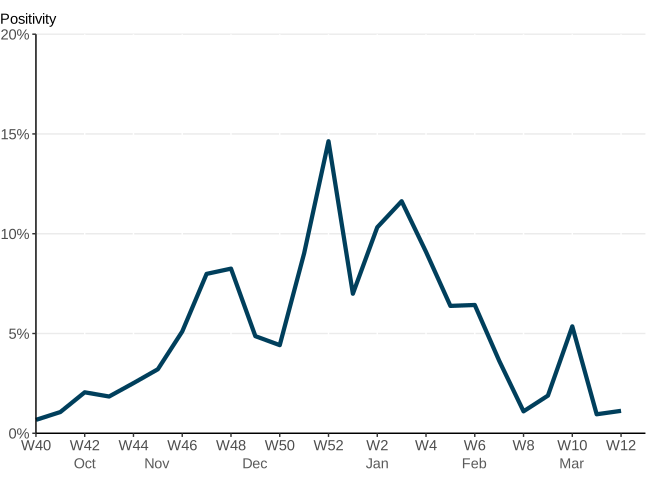
In Wales, 5,690 samples were received for testing from sentinel GP practices between week 40 (ending 5 October) 2025 and week 12 (ending 22 March) 2026. Of these, 281 specimens tested positive for RSV. Positivity began to increase in week 42 (ending 19 October) 2025 and peaked in week 52 (ending 28 December) 2026 at 14.6%, after which RSV positivity gradually declined.
Figure 10. Weekly percentage of tests positive for RSV, Wales, 2025 to 2026
Northern Ireland
Community sentinel GP practices cover approximately 15% of the population of Northern Ireland. The programme tests for influenza A and B, RSV and SARS-CoV-2 through the opportunistic swabbing of patients who provide consent, and who attend (in person) with ILI, ARI or suspected COVID-19 symptoms. All testing is undertaken at the Regional Virus Laboratory (RVL).
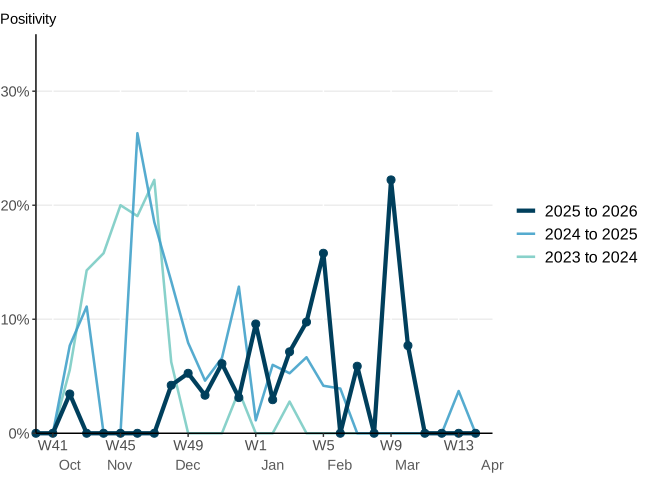
1,107 RSV swabs were received from week 40 (ending 5 October) 2025 to week 16 (ending 19 April) 2026, of which 47 were positive (4.2% positivity). The highest amount of positive RSV samples were in week 51 (ending 21 December) 2025 (eight out of 131; 6.1%). The highest positivity was in week 9 (ending 1 March) 2026, with 2 positives from 9 received samples (22.2%)
Figure 11. Weekly percentage of tests positive for RSV by season, Northern Ireland, 2023 to 2026
Secondary care surveillance
Syndromic surveillance
England
In England, national UKHSA real-time syndromic surveillance systems include emergency department (ED) attendances via the Emergency Department Syndromic Surveillance System (EDSSS).
Acute bronchiolitis is the main clinical presentation of infant RSV. In ED syndromic surveillance bronchiolitis attendances are grouped with bronchitis attendances.
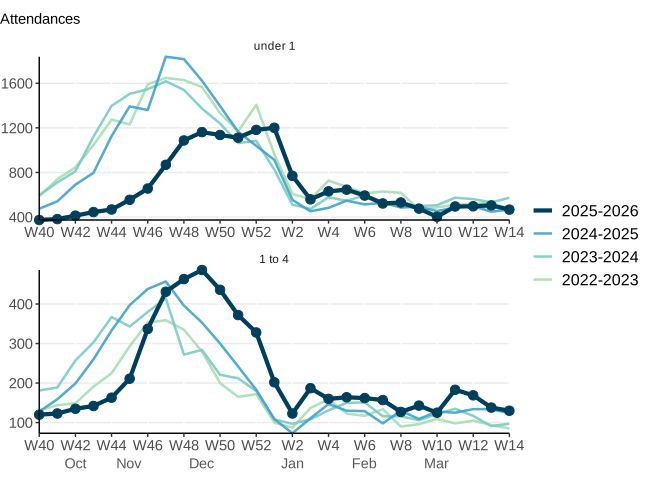
Overall, ED attendances gradually increased from week 40 (ending 5 October) 2025 onwards, with an acceleration in attendances starting week 44 (ending 2 November) 2025, peaking in week 49 (ending 7 December) 2025 at 1,669 weekly attendances and declined at an irregular rate thereafter. Overall attendances started increasing later and the peak was lower in the 2025 to 2026 season compared to previous seasons (Figure 12).
By age, attendances in children younger than one year of age increased from week 44 (ending 2 November), and peaked at similar levels from week 48 (ending 30 November) to week 1 (ending 4 January) 2026 at approximately 1,100 to 1,200 weekly attendances and then declined to low levels from week 3 (ending 18 January) 2026 onwards. In children aged 1 to 4 years of age, attendances increased from week 44 (ending 2 November), peaked in week 49 (ending 7 December onwards) at 486 weekly attendances and declined to low levels by week 2 (ending 11 January) onwards. In this age group, attendances appeared to peak 2 weeks later, but at similar levels to previous seasons (Figure 13).
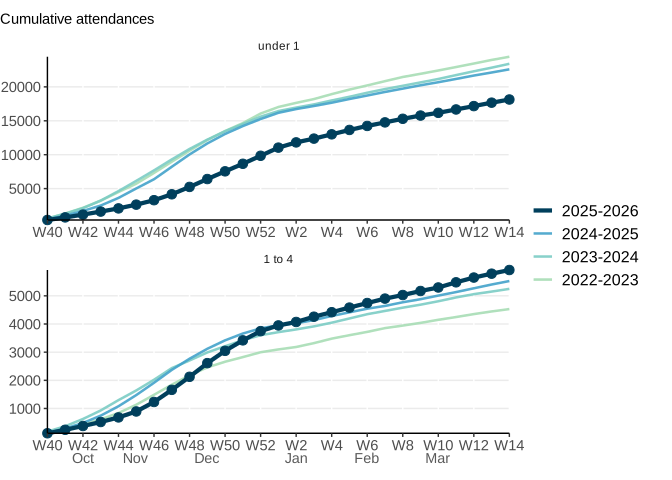
Looking at cumulative attendances across the past 4 winter seasons (weeks 40 to 14), children aged under one year recorded 18,137 attendances in 2025 to 2026 which was lower compared with 22,585 in 2024 to 2025, 23,403 in 2023 to 2024 and 24,442 in 2022 to 2023. Among children aged 1 to 4 years, cumulative attendances were 5,917 in 2025 to 2026 which was slightly higher than 5,526 in 2024 to 2025, 5,248 in 2023 to 2024 and 4,531 in 2022 to 2023 (Figure 14).
Figure 12. Weekly ED attendances for acute bronchiolitis or bronchitis in all ages, England, 2025 to 2026 season
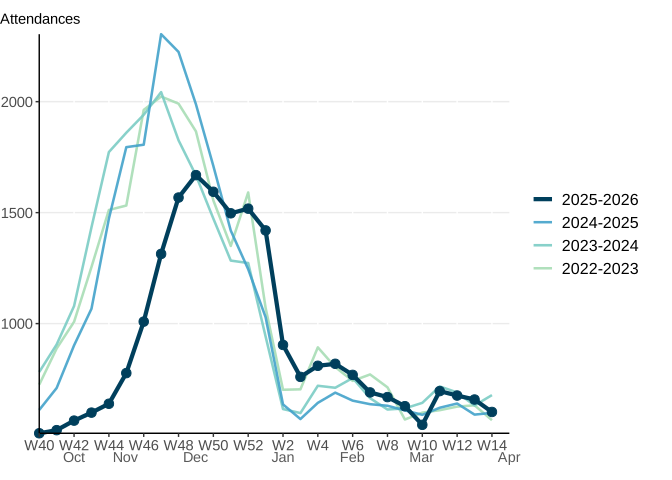
Figure 13. Weekly ED attendances for acute bronchiolitis or bronchitis by age group in children aged under 5 years, England, 2022 to 2026 [note 2]
Note 2: scales vary in each graph to enable trend comparisons.
Figure 14. Weekly cumulative ED attendances starting in week 40 for acute bronchiolitis or bronchitis by age group in children aged under 5 years, England, 2022 to 2026 [note 2]
Note 2: scales vary in each graph to enable trend comparisons.
Scotland
The General / Acute and Inpatient Day Case dataset (SMR01) collects episode level data on hospital inpatient and day case discharges from acute specialities from hospitals in Scotland. Figure 15 presents the weekly number of patients admitted as an emergency to a hospital in Scotland with an International Classification of Diseases, Tenth Revision (ICD-10) code related to acute bronchiolitis in any of the condition fields, by season between 2022 and 2026.
Weekly admissions for acute bronchiolitis increased from week 42 (ending 19 October) 2025, peaked between week 48 (ending 30 November) 2025 and 51 (ending 21 December) 2025 at 180 to 190 weekly admissions and then gradually declined. Admissions appeared overall lower than in previous seasons (Figure 15).
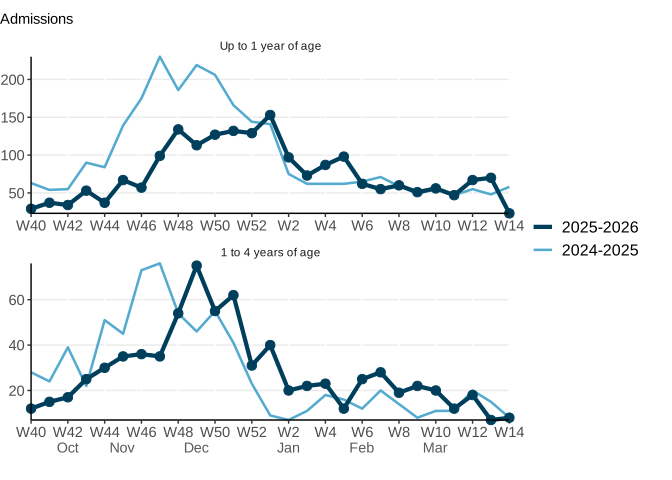
By age, attendances in children younger than one year of age increased from week 45 (ending 9 November), and peaked in week 1 (ending 4 January) 2026 at approximately 150 weekly attendances and then declined to low levels from week 6 (ending 8 February) 2026 onwards. ED attendances appeared lower than in the 2024 to 2025 season. In children aged 1 to 4 years of age, attendances increased from week 43 (ending 26 October), peaked in week 49 (ending 7 December) at 75 weekly attendances and declined to low levels by week 2 (ending 11 January) onwards. In this age group, attendances appeared similar to the previous season.
Figure 15. Weekly admissions for acute bronchiolitis by season, Scotland, 2022 to 2026
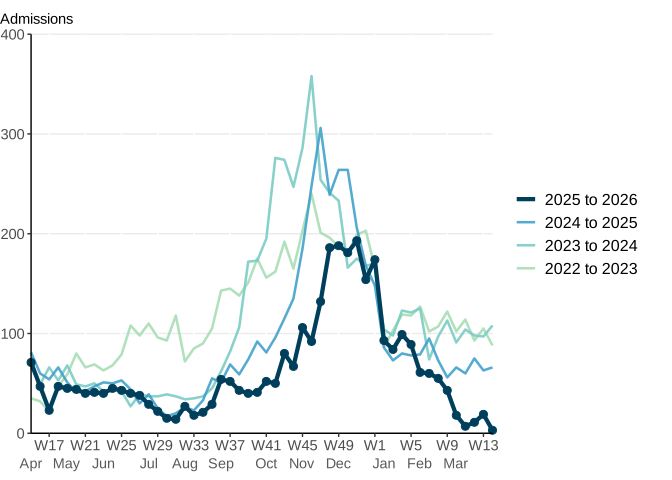
Figure 16. Weekly admissions for acute bronchiolitis by season, Scotland, 2022 to 2026 [note 2]
Note 2: scales vary in each graph to enable trend comparisons.
RSV hospital admissions
England
UKHSA collates data on test-confirmed hospitalised RSV cases in England by level of care (admissions excluding Intensive Care or High Dependency Unit (ICU or HDU) and admissions to ICU or HDU) through the SARI Watch surveillance system. This is a sentinel system, with data collected by a small network of acute NHS trusts reporting voluntarily. Trusts submit weekly aggregate counts of new RSV admissions and these are summed and converted to rates per 100,000 by linking to catchment populations of participating trusts in that week. Please see the data quality report for additional details on SARI-Watch data collections including RSV.
From the 2024 to 2025 season, surveillance of RSV commenced earlier (starting week 36) to routinely capture earlier activity, pausing earlier at week 14 due to substantial decreases in activity that typically occur by this time. In prior seasons, RSV surveillance operated routinely between week 40 and week 20 in the following year (except in 2023 to 2024 where surveillance paused at week 16). Analyses for the 2025 to 2026 season include data from the full reporting period (week 36 2025 to week 14 2026 inclusive). Where comparisons to previous seasons are presented, data from week 40 to week 14 inclusive are used.
Overall activity, hospital admissions excluding ICU or HDU
From week 36 (ending 7 September) 2025 to week 14 (ending 5 April) 2026, a total of 3,954 test confirmed RSV hospital admissions (excluding ICU or HDU) were reported by 20 participating trusts in the 31 week period. Of 20 trusts, 19 participated for a minimum of 21 weeks this season.
There were 2,030 hospitalisations (excluding ICU or HDU) in children aged under 5 years reported by SARI Watch sentinel trusts in the same period. Of these, 48.7% (n=988) were in children aged under one year, including 648 cases aged 6 months or younger.
Cumulative rates from week 36 to week 14 in the following year are presented for the 2025 to 2026 and 2024 to 2025 seasons. Cumulative rates are based on the sum of weekly rates which take into account only trusts participating in that week. The cumulative rate for hospital admissions (excluding ICU or HDU) in 2025 to 2026 was 44.44 per 100,000 trust catchment population. This was slightly lower than the cumulative rate in the 2024 to 2025 season at 46.24 per 100,000.
Summary of epidemic activity
The overall weekly hospital admission rate (excluding ICU or HDU) peaked at 4.23 per 100,000 trust catchment population in week 51 (ending 21 December) 2025 (figure 17). In the 2024 to 2025 season the rate peaked at 4.73 per 100,000 in week 48 (ending 1 December) 2024 (Figure 17).
The weekly hospital admission rate (excluding ICU or HDU) was highest among those aged 5 years or under. In this age group, 2 peaks in the 2025 to 2026 season were observed. The rate first peaked at 42.72 per 100,000 in week 48 (ending 30 November) 2025 (Figures 18 and 19). The second peak was in week 51 (ending 21 December) 2025 although the rate was similar at 41.61 per 100,000. Those aged 85 years or more had the next highest rate, peaking at 31.6 per 100,000 in week 2 (ending 11 January) 2026 (Figures 18 and 19).
Figure 20 shows the number of hospitalised cases (excluding ICU or HDU) among children aged under 5 years stratified by 4 infant groups: under 6 months, 6 to 11 months, one year and 2 to 4 years. The total number of cases aged under 5 years peaked in week 48 (ending 30 November) 2025 (n=235). Within this cohort, the proportion of infants aged under 6 months peaked at 65.4% in week 2 (ending 11 January) 2026 (51 of total 78 cases). The proportions peaked at lower levels for the other infant groups. Note that case numbers by each of these age groups are very small at the start and at the end of the season thus data in these periods should be interpreted with caution.
Figure 17. Weekly hospital admission (excluding ICU or HDU) rate for new RSV positive cases per 100,000 trust catchment population, England, reported through SARI-Watch sentinel surveillance
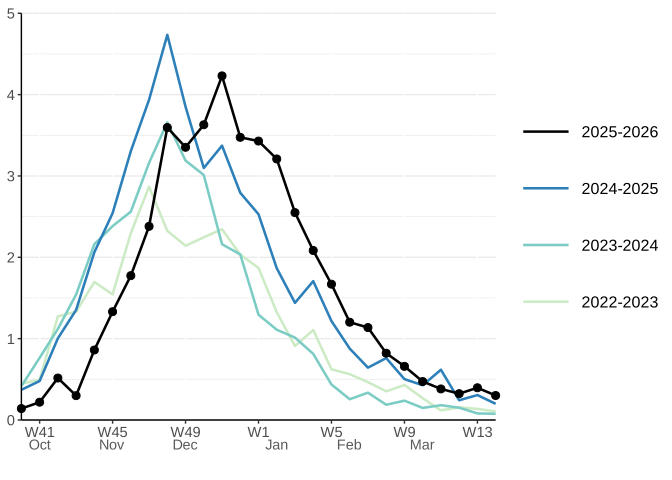
Figure 18. Weekly hospital admission (excluding ICU or HDU) rate for new RSV positive cases per 100,000 trust catchment population in those aged under 5 years, 75 to 84 years and 85 years and over, England, reported through SARI-Watch sentinel surveillance [note 3]
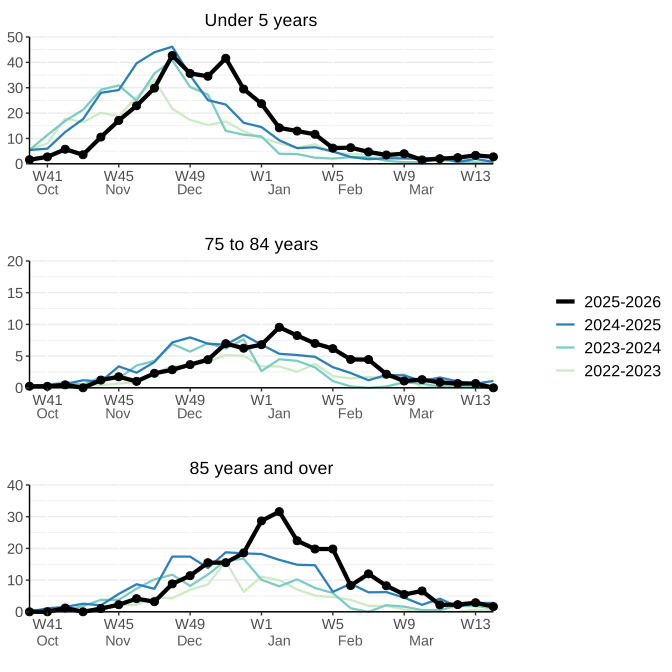
Note 3: the y-scale range is adjusted according to age group to allow seasonal trends to be visualised more clearly.
Figure 19. Weekly hospital admission (excluding ICU or HDU) rate for new RSV positive cases per 100,000 catchment population by age group, England, 2025 to 2026 season, reported through SARI Watch sentinel surveillance [note 4]
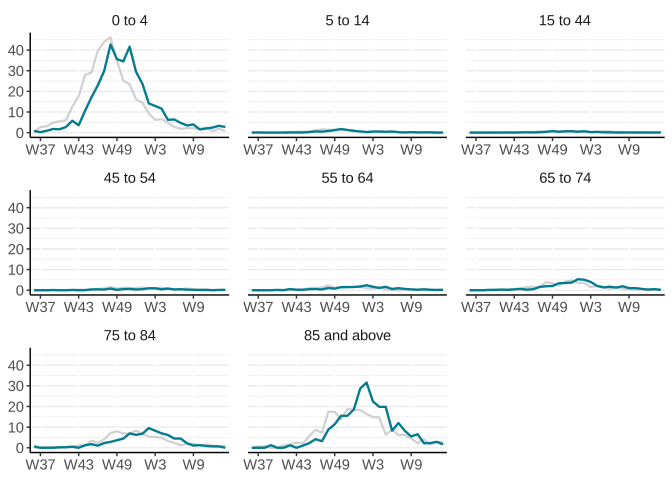
Note 4: the highlighted line corresponds to the 2025 to 2026 season and the grey line corresponds to the previous 2024 to 2025 season.
Figure 20. Weekly count of hospital admissions (excluding ICU or HDU) of new RSV positive cases, in infants aged under 6 months, 6 to 11 months, one year, and 2 to 4 years, England, 2025 to 2026 season, reported through SARI Watch sentinel surveillance [note 5]
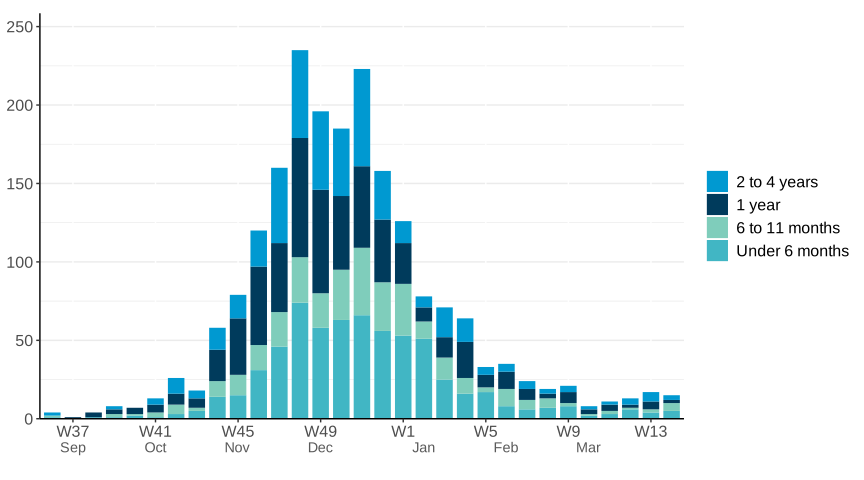
Note 5: the number of admissions are based on data submitted by a small network of acute NHS trusts participating in SARI-Watch’s sentinel surveillance, hence do not represent the totality of RSV admissions in those aged under 5 years in all NHS trusts in England.
RSV admissions by level of care
Figure 21 shows the weekly number of RSV admission by level of care for all ages combined. The case numbers for admissions excluding ICU or HDU peaked in week 51 (ending 21 December) 2025 (n=373). The case numbers for admissions to ICU or HDU peaked in week 49 (ending 7 December) 2025 (n=20).
Figure 21. Weekly count of hospital admissions of new RSV positive cases, England, 2025 to 2026 season, reported through SARI Watch sentinel surveillance by level of care [note 6]
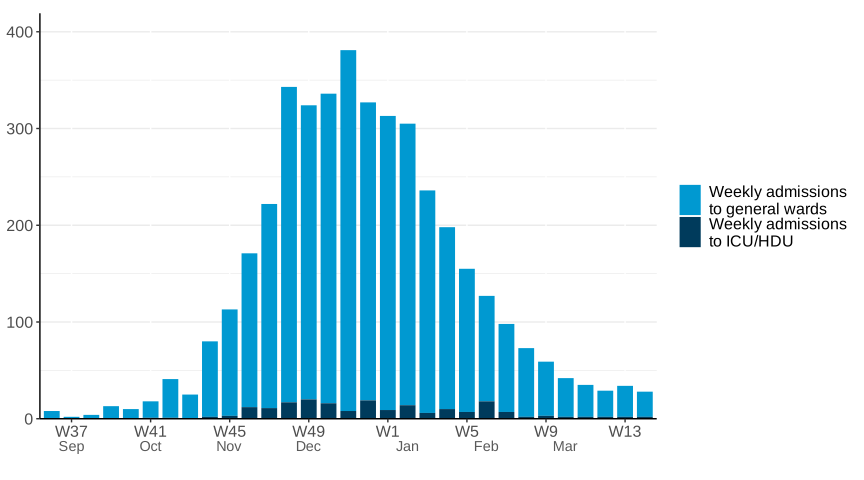
Note 6: the number of admissions are based on data submitted by a small network of acute NHS trusts participating in SARI-Watch’s sentinel surveillance, hence do not represent the totality of RSV admissions in all NHS trusts in England.
Scotland
Patients admitted as an emergency to a hospital in Scotland with a recently confirmed positive RSV test are identified from Rapid Preliminary Inpatient Data (RAPID). RAPID is a daily submission of people who have been admitted to hospital in Scotland. The case definition includes patients admitted as an emergency to a medical speciality (excluding surgical and mental health specialities, and emergency admissions with patient injury codes) who have a positive RSV test result, taken within a period of between 14 days before the admission date and 2 days after the admission date.
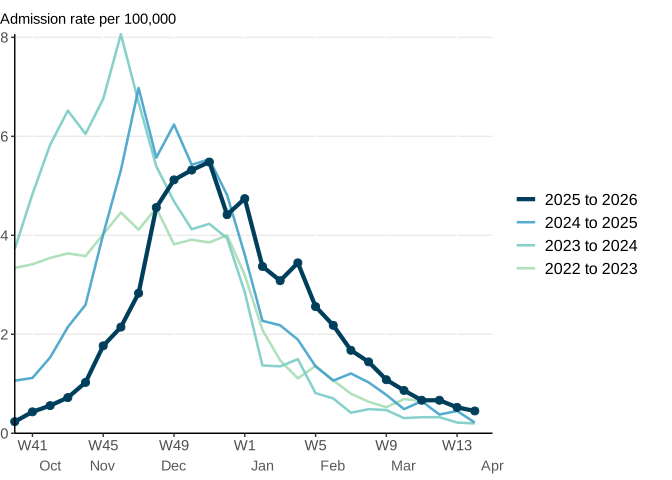
The overall rate of hospitalisation increased from October 2025 and peaked in week 51 (ending 21 December) 2025 at 5.48 per 100,000 and then gradually declined. The start of the season appeared to be later than in previous seasons. Overall rates appeared similar to the 2024 to 2025 season but lower than the 2023 to 2024 season.
Figure 22. Weekly RSV hospital admission rate per 100,000 by season, Scotland, 2022 to 2026
By age, hospital admissions were highest among those aged 5 years or under, peaking between week 48 (ending 30 November) and week 51 (ending 21 December) 2025 at rates of 85 to 95 per 100,000 and declined thereafter. In those above 75 years of age, hospitalisations increased gradually from week 48 (ending 30 November) 2025 and peaked in week 2 (ending 11 January) 2026 and declined thereafter.
Figure 23. Weekly RSV hospital admissions by age group and season, Scotland, 2022 to 2026 [note 7]
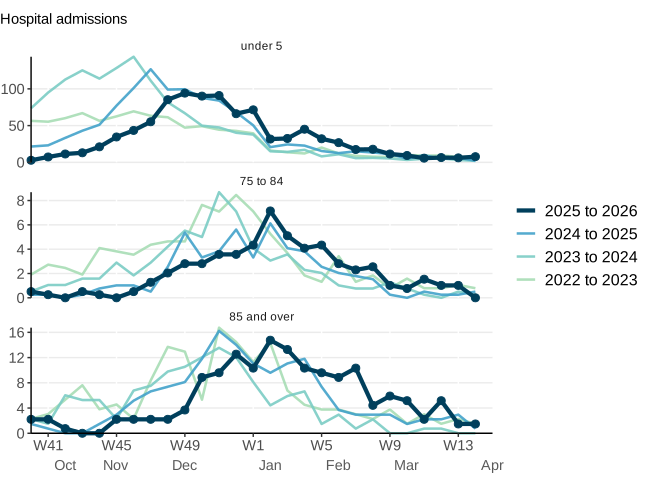
Note 7: scales vary in each graph to enable trend comparisons
Wales
Hospitalised RSV cases in Wales are identified by linking hospital admissions recorded in the Wales Patient Administration Systems (PAS) to laboratory test results using patient NHS number. Cases are defined as those admitted to hospital who tested positive for RSV within 28 days prior to admission or up to day 2 of an inpatient stay (where admission date is day 1).
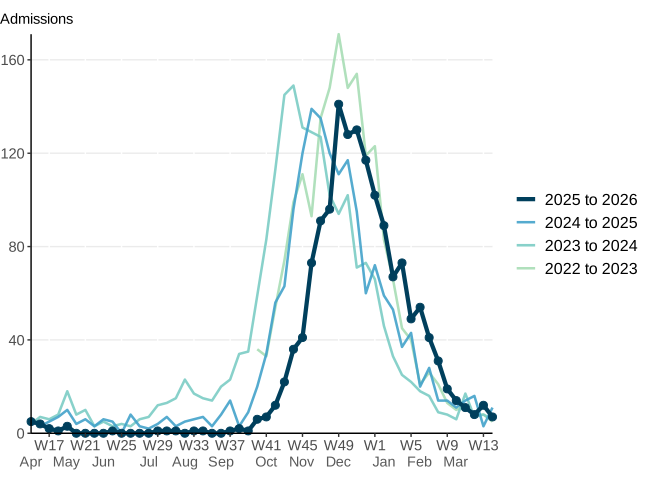
A total of 1,477 hospitalised RSV cases were reported in Wales from week 40 (ending 5 October) 2025 to week 14 (ending 5 April) 2026. Hospital admissions started to increase in week 43 (ending 26 October) 2025 and peaked in week 49 (ending 7 December) 2025 at 141 admissions and gradually declined thereafter.
Figure 24. Weekly RSV hospital admissions by season, Wales, 2022 to 2026
Northern Ireland
Community-acquired RSV emergency admissions to acute hospitals are estimated by combining data from the Patient Administration System (PAS), EPIC and virological reports in The Northern Ireland Health Analytics platform (NIHAP). Admissions are counted where there was a positive test up to 7 days before admission or up to one day after admission, and the method of admission was ‘Emergency’. Admissions refer to the first admission per infection episode. All trusts in Northern Ireland contribute to this data collection.
RSV admission activity increased from week 43, 2025 (week commencing 20 October) showing a single peak in week 51, 2025 (week commencing 15 December) at 3.4 per 100,000 population. RSV admission rates fluctuated throughout the season before declining to low levels, reaching 0.3 per 100,000 population in week 16, 2026 (week commencing 13 April). There was a total of 822 emergency admissions, with a cumulative admission rate of 42.6 per 100,000 population. The majority of RSV emergency admissions were reported in those aged less than 5 years old (86.5%; 711 out of 822).
Figure 25. Weekly RSV hospital admission rate per 100,000 by season, Northern Ireland, 2023 to 2026
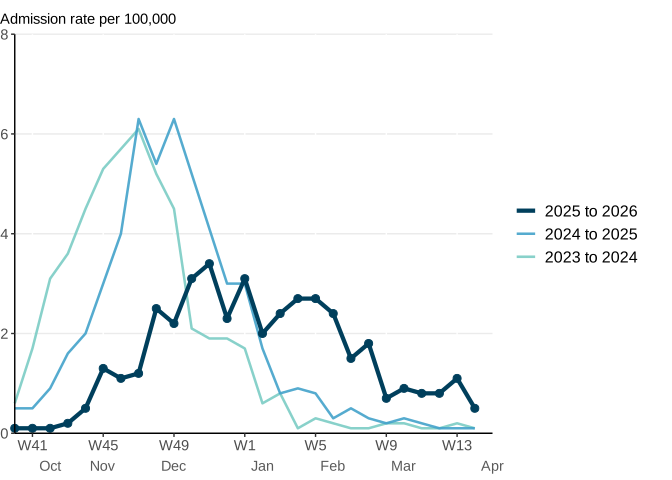
Figure 26. Weekly RSV hospital admission rate per 100,000 by season in those aged under one year, 1 to 4 years and 75 years and over, Northern Ireland, 2021 to 2025 [note 2]
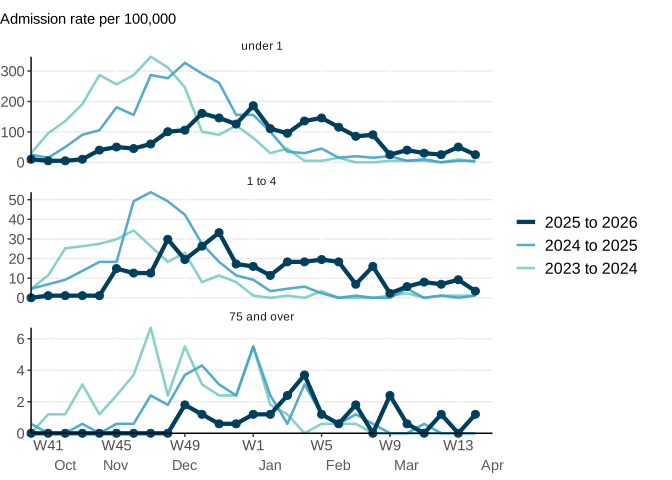
Note 2: scales vary in each graph to enable trend comparisons.
RSV ICU or HDU admissions
England
From week 36 2025 to week 14 2026 inclusive, there was a total of 196 admissions to ICU or HDU reported by 20 sentinel trusts based on all ages. Of these admissions, 132 were among those aged under 5 years, accounting for 67.4% (132 out of 196) of total admissions. This compares with 77.3% (214 out of 277) in the 2024 to 2025 season for the same period where the same trusts participated in RSV surveillance
Among admissions in those aged under 5 years, 59.1% (n=78) were in children aged under one year, including 63 cases aged under 6 months, the latter accounting for 47.7% of those aged under 5 years in the 2025 to 2026 season. In the 2024 to 2025 season, there was a total 214 ICU or HDU admissions in children aged under 5 years, of which 76.6% (164 out of 214) were in children aged under one year, including 132 cases aged under 6 months (the latter accounting for 61.7% of those aged under 5 years in that season).
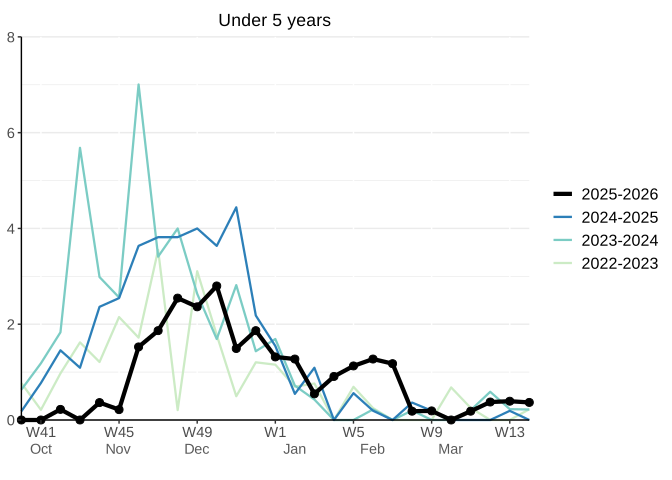
Admission rates to ICU or HDU among children aged under 5 years in 2025 to 2026 and in previous seasons are presented in Figure 27. It is important to note that the weekly ICU or HDU admission rates for RSV fluctuate due to smaller underlying numbers. The rate peaked at 2.80 per 100,000 in week 50 2025 (ending 14 December). In the 2024 to 2025 season, the rate in this age group peaked at 4.44 per 100,000 in week 51 (ending 22 December) 2024.
Figure 27. Weekly admission rate to ICU or HDU for new RSV positive cases in under 5 years, per 100,000 trust catchment population, England, reported through SARI-Watch sentinel surveillance
Scotland
Patients admitted to ICU/HDU with recently confirmed RSV are identified from the Scottish Intensive Care Society Audit Group (SICSAG) that collects detailed patient level data on all patients in ICU/HDU across Scotland. All patients that are admitted to hospital as an emergency with a positive RSV test result within a period of 14 days before or 2 days after the hospital admission, and who are subsequently admitted to ICU or HDU, are included.
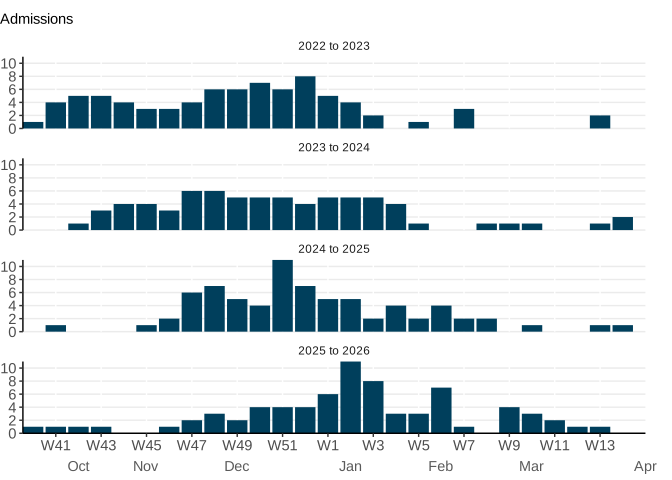
From week 40 (ending 5 October) 2025 to week 14 (ending 5 April) 2026 inclusive, there was a total of 75 admissions to ICU or HDU with an associated positive RSV test. This is similar to the same period in the previous seasons (Figure 28).
Figure 28. Weekly RSV admissions to ICU or HDU for RSV positive cases by season, Scotland, 2022 to 2026
ECMO
Extra-corporeal Membrane Oxygenation (ECMO)
Data is based on reporting by the 8 adult severe respiratory failure (SRF) centres in the UK (7 in England and 1 in Scotland) to the UKHSA ECMO surveillance module. Data from week 40 2025 to week 14 2026 show that there were no admissions for test confirmed RSV acute respiratory infection. Please refer to the Influenza in the UK, annual epidemiological report: winter 2025 to 26 for more details.
Laboratory surveillance
Respiratory Datamart, England
The Respiratory Datamart system began during the 2009 influenza pandemic to collate all laboratory testing information in England. It is now used as a sentinel laboratory surveillance tool, monitoring all major respiratory viruses in England. In this season, data was reported by 14 laboratories in England, including 5 public health laboratories, 8 NHS hospital laboratories and a UKHSA national laboratory. The majority of samples were received from hospitals.
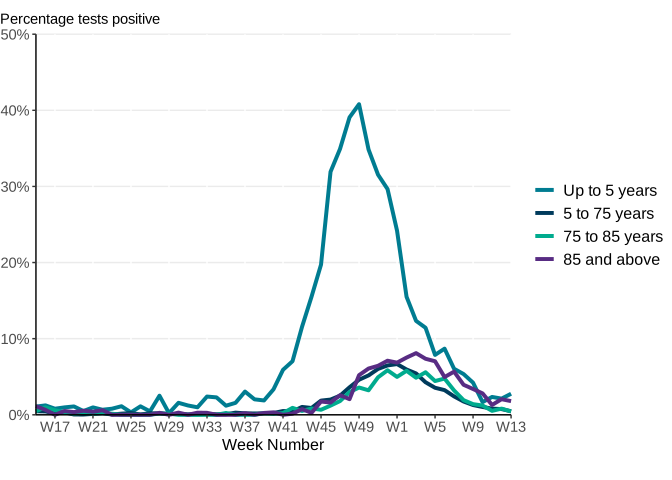
RSV positivity started to increase from week 42 (ending 19 October) 2025 and peaked between week 48 (ending 30 November) 2025 and week 52 (ending 28 December) 2025 at 10 to 11% with a gradual decline thereafter. Positivity by age group for the 2025 to 2026 season is shown in Figure 30, with highest positivity in those aged under 5 years old.
Figure 29. Weekly overall RSV swab percentage positivity through Respiratory DataMart by season, England
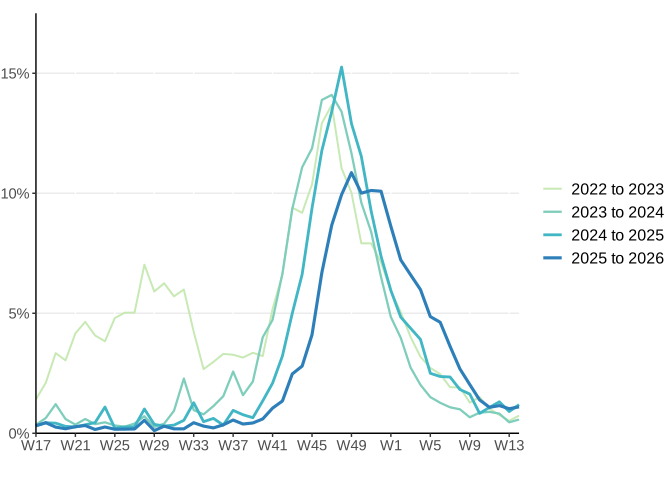
Figure 30. Respiratory DataMart weekly positivity (%) for RSV by age, England, 2025 to 2026
Scotland
All NHS laboratories in Scotland submit data for positive RSV tests via the Electronic Communication of Surveillance Scotland (ECOSS) database. As of the 2024 to 2025 season data submitted by all NHS laboratories include negative results for RSV. Tests which have been taken as part of the CARI programme, are systematically excluded from all of the following ECOSS-derived figures.
Episodes are defined as positive laboratory confirmed RSV test, not occurring within 56 days of a previous positive result for the same pathogen. Test positivity is calculated as the number of samples associated with a positive test divided by the total number of samples for a given pathogen.
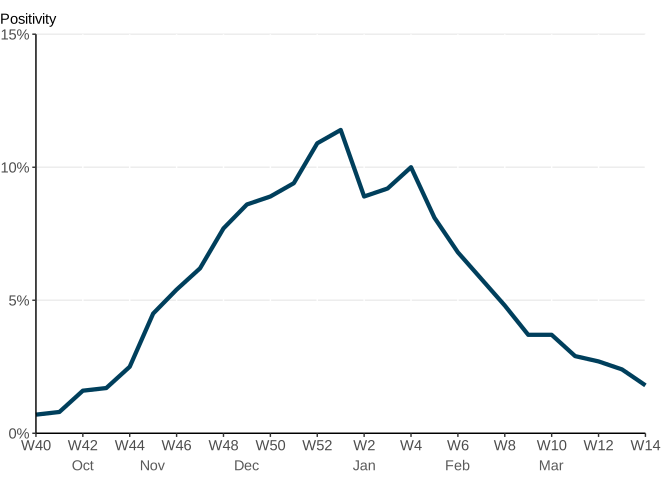
RSV cases increased from week 42 (ending 19 October) 2025 and peaked in week 50 (week ending 14 December) 2025 (Figure 31). RSV positivity peaked in week 1 (week ending 11 January) 2026 at 11.4% before declining thereafter (Figure 32).
Figure 31. Weekly ECOSS RSV counts by season, Scotland, 2022 to 2026
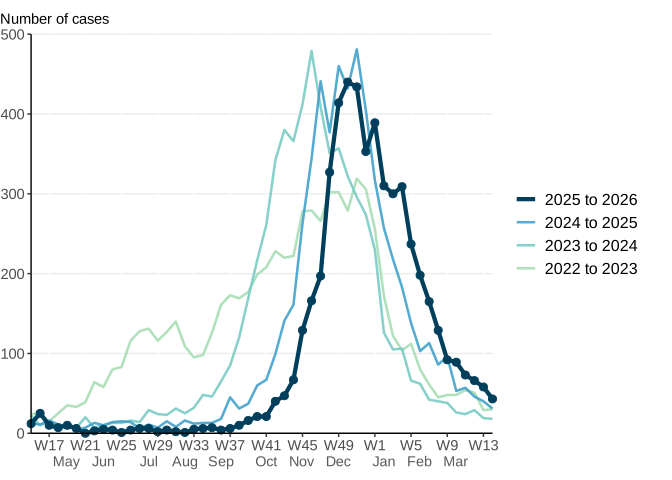
Figure 32. Weekly ECOSS RSV positivity, Scotland, 2025 to 2026 season
Wales
Diagnostic virology results from Wales concern all test results recorded in the national laboratory test results database, Datastore. These are from patients tested from non-sentinel settings. The vast majority of these patients are in hospital, with a small proportion from non-sentinel community sources.
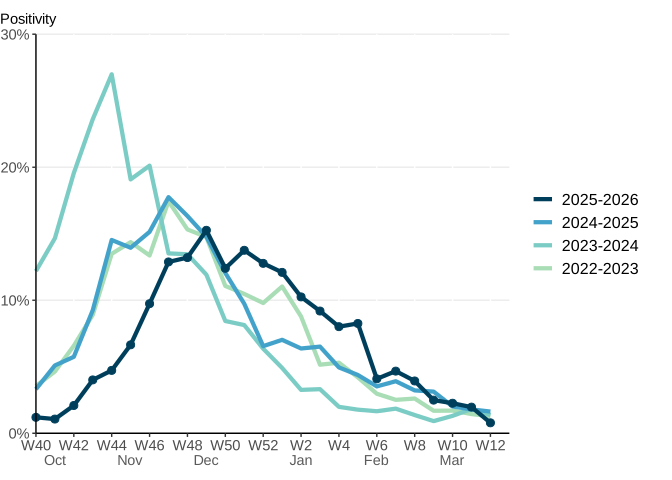
Out of 28,651 samples tested between week 40 (ending 5 October 2025) 2025 and week 12 (ending 22 March) 2026, 2,198 tested positive for RSV. Overall positivity started to increase in week 42 (ending 19 October) 2025 and peaked in week 49 (ending 7 December) 2025 at 15.3%, gradually declining thereafter (Figure 33).
Figure 33. Weekly percentage tests positive for RSV, Wales, 2022 to 2026
Northern Ireland
Results of all positive and negative testing from the RVL and all local laboratories are collated into NIHAP. This RSV surveillance uses data collected from settings such as hospitals and GP surgeries, excluding the sentinel GP practices. The majority of samples were received from hospitals.
Overall RSV positivity showed an increased level of activity (above 5% positivity) from week 48, 2025 (ending 30 November) and remained above this for 13 consecutive weeks, returning to 4.0% positivity in week 9, 2026 (week ending 1 March). Peak positivity was seen in week 4, 2026 (week ending 25 January) at 9.3% which was later and lower than what was reported in the 2024 to 2025 season (17.1% positivity in week 47, 2024; ending 24 November).
Figure 34. Weekly percentage tests positive for RSV by season from NIHAP, Northern Ireland, 2023 to 2026
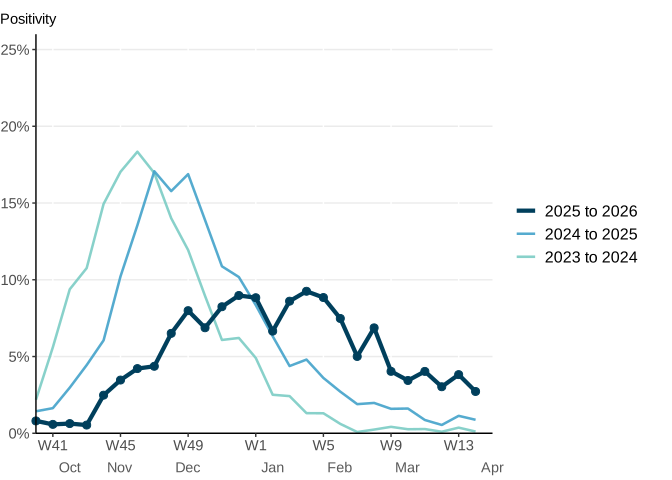
Figure 35. Weekly percentage tests positive for RSV by season and age group from NIHAP, Northern Ireland, 2023 to 2026 [note 2]
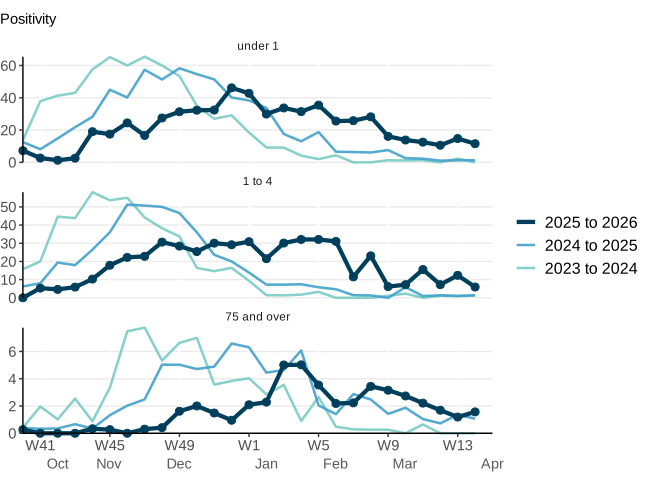
Note 2: scales vary in each graph to enable trend comparisons.
Mortality
Paediatric mortality
Paediatric mortality offers insight into the severity of an RSV season. Children, particularly those under 5 or with underlying health conditions, are more vulnerable to severe outcomes.
RSV-related deaths in children within each season were identified using positive RSV cases from SGSS, ONS all-cause mortality data and death records from the NHS spine. Laboratory confirmed RSV case records were linked to deaths recorded in the NHS spine using demographic batch service tracing and to ONS all-cause mortality records to indicate where a case had died within 28 days of a positive specimen within that season. ONS all-cause mortality data was also used to identify deaths where RSV was mentioned as a cause of death on an individual’s death certificate.
Between 5 October 2025 and 4 April 2026 (week 40 to week 14), an estimated 36 RSV-related deaths occurred in children under 18 years. For comparison, an estimated 78 paediatric RSV-related deaths were reported in the 2024 to 2025 season (6 October 2024 to 17 May 2025), 52 deaths in the 2023 to 2024 season (1 October 2023 to 18 May 2024) and 55 deaths in the 2022 to 2023 season (2 October 2022 to 20 May 2023).
There are significant reporting lags in mortality data. At the time of publication, data is available only up to week 14 for the 2025 to 2026 season, while for previous seasons data is available up to week 20. The date range refers to the date of death and includes individuals who tested positive for RSV up to 28 days prior. Deaths with RSV listed as a cause of death were identified using ICD-10 codes J121, J205, J210 and B974. Some overlap between deaths where RSV was mentioned on the death certificate and deaths within 28 days of a positive test is expected. Note that RSV-related deaths estimates may include deaths that are not attributable to RSV infection.
Please note that the 2024 to 2025 report included an undercount of deaths within 28 days of a positive RSV test, likely due to an error in extraction of testing data. The estimates below reflect a new extract of testing data, including those for previous seasons.
Table 4. Estimated number of deaths associated with RSV in those aged under 18 years, England, 2022 to 2026
| Cause | 2022 to 2023 season | 2023 to 2024 season | 2024 to 2025 season | 2025 to 2026 season |
|---|---|---|---|---|
| Deaths where RSV was mentioned on death certificate | 18 | 15 | 25 | 6 |
| Deaths within 28 days of a positive RSV test | 49 | 46 | 71 | 35 |
| Total RSV related deaths | 55 | 52 | 78 | 36 |
Vaccination
Maternal vaccine uptake
England
An RSV vaccination programme for pregnant women was introduced in England on 1 September 2024, to protect infants against severe RSV disease. Pregnant women become eligible as they reach 28 weeks gestation, remaining eligible until the end of the pregnancy. All women who were at least 28 weeks pregnant at the start of the programme on 1 September 2024 were eligible for a single dose of RSV vaccine.
In this report, the eligible population (denominator) for the maternal vaccination programme is defined as all identified women giving birth in a calendar month. The denominator is collected using the Maternity Services Data Set (MSDS), a patient-level data set from NHS England (NHSE) that captures activities carried out by maternity services. MSDS has a 3-month lag in reporting. RSV vaccination events are collected from the UKHSA’s Immunisation Information System (IIS), which captures denominator data and vaccination events across England, via the Data Provisioning Service (DPS) at NHS England (NHSE). IIS includes a patient-level data set of individuals eligible for primary care in England.
Vaccine uptake for each month is calculated as the number of women giving birth in that month who have received an RSV vaccine (numerator) divided by the denominator for that month. The maternal denominator was extracted from MSDS on 19 June 2026, which included February 2026 births, and linked to RSV vaccine records from IIS. Gestational age at vaccination was calculated using the gestational age at birth from MSDS records and the date of vaccine administration from IIS.
Please note that in this report, the estimates for vaccine coverage differ from those in the monthly RSV maternal vaccination coverage reports published by UKHSA. The monthly coverage report official statistic uses an aggregated data extract of both vaccination status and delivery information from GP systems and is uploaded into the ImmForm platform. The methodology in this report here instead uses individual-level linkage between birth records held in a national dataset of maternity services (MSDS) and IIS. The linkage to MSDS enables further insights into vaccine coverage, particularly calculation of vaccination by gestational age at vaccination. Estimates of vaccine coverage in this report are slightly higher than those in the monthly maternal RSV vaccination coverage report. Further details will be discussed in the accompanying Quality and methodology information in due course.
Between 1 September 2024 and 28 February 2026, 55.6% of all women giving birth had received an RSV vaccine prior to delivery. In the last 12 months with complete data (between March 2025 and February 2026) 61.7% of women giving birth had received an RSV vaccine.
In women who gave birth in February 2026, 66.1% had received an RSV vaccine. The average gestational age at vaccination has decreased as the programme has progressed. By December 2024, the majority of vaccinated women giving birth received their vaccine between 28 and 31 weeks gestation.
Figure 36. RSV vaccine uptake for women giving birth in a given month by gestational age at vaccination, England
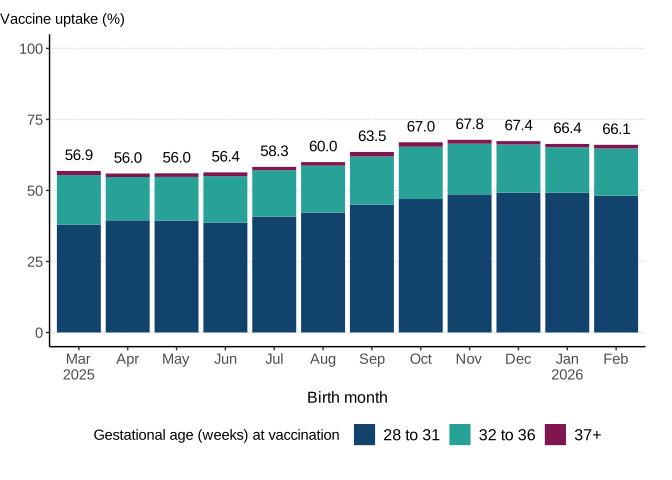
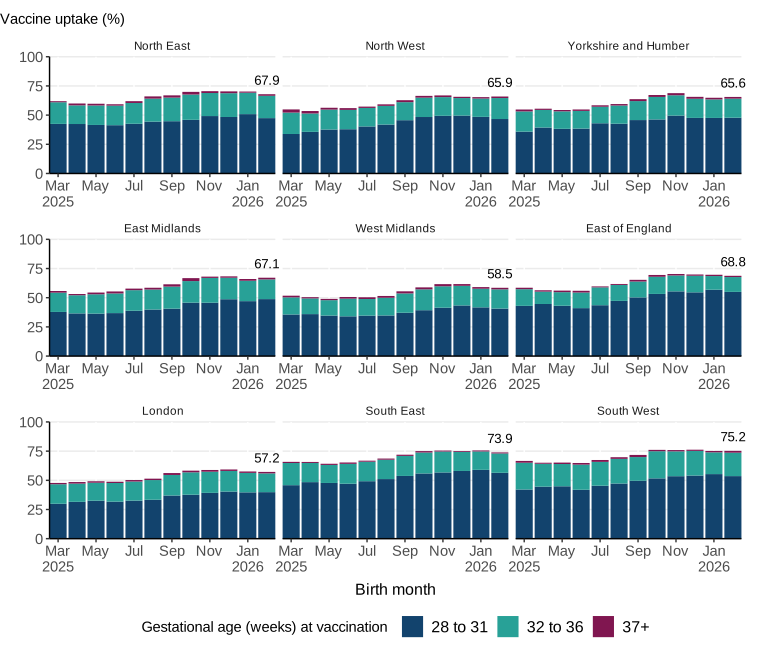
Overall, most regions shared a similar pattern of increasing monthly RSV vaccine uptake as the programme has progressed, although there is some month-on-month variation (Figure 37). There was also a similar increase in women giving birth receiving their vaccine earlier in pregnancy across all regions. There was appreciable variation in uptake between regions in women giving birth in February 2026, with the lowest uptake in London (57.2%) and the highest in the South West (75.2%).
Figure 37. RSV vaccine uptake for women giving birth in a given month by gestational age at vaccination and region, England
Scotland
On 1 August 2024 pregnant women in Scotland became eligible for RSV vaccination from 28 weeks of their pregnancy until the end of pregnancy.
The eligible population (denominator) is sourced from Scottish Linked Pregnancy and Baby Dataset (SLiPBD), and includes both ongoing pregnancies and live births. Vaccination events are recorded using the TURAS Vaccination Management Tool a web-based tool for healthcare staff in Scotland to record real-time patient vaccination data at the point of care. Vaccination events are then stored in the National Clinical Data Store (NCDS) developed by NHS Education Scotland. Information on vaccine uptake for the RSV vaccine programme is available from the PHS Vaccination Surveillance Dashboard.
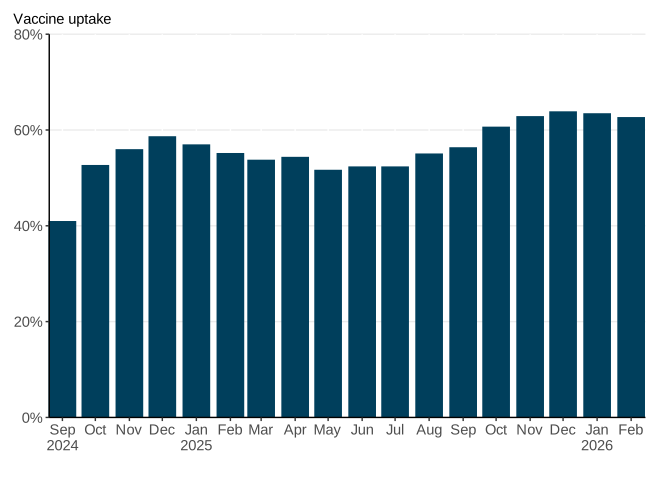
By 28 February 2026, RSV vaccine uptake in pregnancy over the entirety of the programme was 53.7%. In the most recent month with available data, uptake among women giving birth in February 2026 was 62.7% (figure 38).
Figure 38. RSV maternal vaccine uptake in women giving birth by month, Scotland
Wales
RSV vaccine uptake in women who have given birth is calculated using data in the Wales Maternity Indicators Delivery Dataset. The Wales Maternity Indicators Delivery Dataset contains data for women residing in all health board areas and uptake is calculated for women by month of delivery. RSV vaccination events are extracted from the Wales Immunisation System (WIS) and linked to the Maternity Indicators Delivery Dataset using NHS Number. More information on the methodology, as well as the latest uptake figures, can be found in the Immunisation surveillance reports published by Public Health Wales.
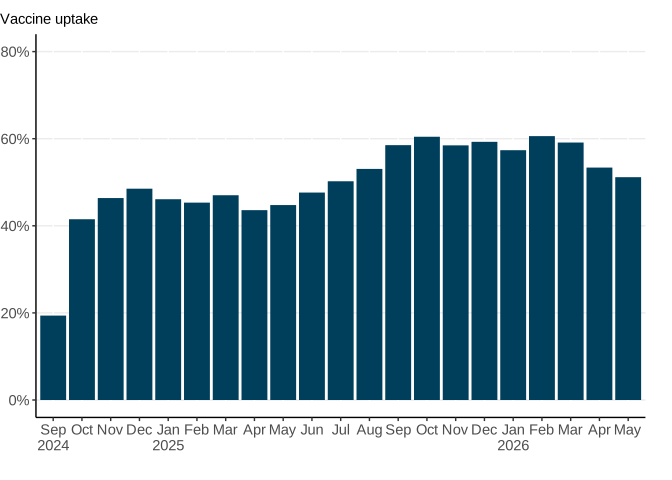
Overall, since the start of the programme on 1 September 2024, 50.0% of women who had given birth had received an RSV vaccine. Monthly RSV vaccine uptake has generally increased since the start of the programme, although there is some month-on-month variation (Figure 39). In the last 12 months with complete data available (June 2025 to May 2026), 56.2% of women giving birth had received an RSV vaccine.
Figure 39. RSV vaccine uptake in women giving birth by month, Wales
Northern Ireland
Data on RSV vaccine uptake in pregnant women in Northern Ireland is not currently available but will be published on the Public Health Agency website following the first full year of the programme.
Older adults vaccine uptake
England
Vaccination against respiratory syncytial virus (RSV) was introduced in England on 1 September 2024, with programmes targeting older adults and pregnant women. All adults turning 75 years of age on or after 1 September 2024 are eligible for vaccination through the routine programme. In addition, a one-off catch-up offer is available for adults aged 75 to 79 years at the start of the programme.
An expansion of the programme eligibility criteria to include older adult care home residents and individuals aged 80 years and over was introduced from 1 April 2026. As this expansion has only recently been implemented, this report focuses on vaccine uptake among individuals in the routine and catch-up cohorts.
The eligible population for the older adult vaccination programme was extracted from the Immunisation Information System (IIS) and linked to RSV vaccination events on 31 May 2026. Vaccine uptake is calculated as the number of eligible older adults who had received an RSV vaccine (numerator) divided by the total number eligible to receive the vaccine (denominator), for both counts a person needs to be alive at the time of data extraction.
Cohort definitions
This report contains 2 cohort definitions:
- a catch-up cohort which has individuals who were already between 75 and 79 years of age at the start of the programme on 1 September 2024
- a routine cohort which contains individuals who became eligible after the programme introduction because they reached the age of 75 years after 1 September 2024.
As of 31 May 2026, the routine cohort in England therefore includes individuals born between 1 September 1949 and 31 May 1951. As the routine programme is dynamic, with new individuals becoming eligible as they turn 75 years of age, the population at each time point reflects all individuals currently eligible for vaccination, including those who have become eligible since programme launch.
In contrast, the catch-up measure quantifies cumulative uptake among individuals eligible when the programme was introduced. This complementary measure is included to support interpretation of long-term programme reach and trends over time.
Vaccine uptake nationally
By 31 May 2026, 65% of all eligible older adults in England had received an RSV vaccination.
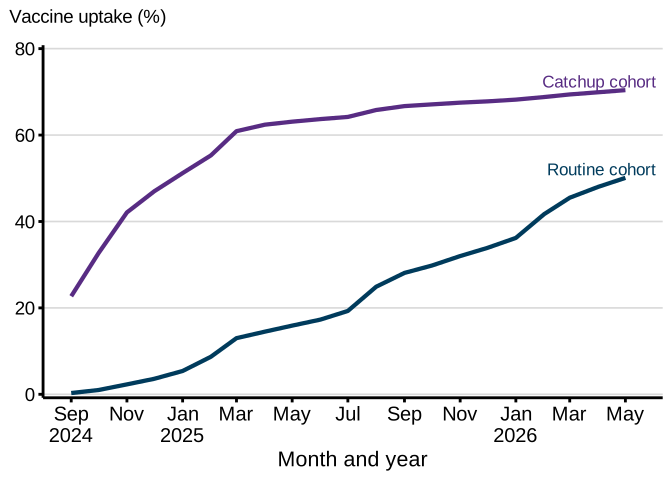
In the catch-up cohort, vaccination uptake was 70.4%, compared to 50.1% in the routine cohort. The lower uptake in the routine cohort should be interpreted in the context of incremental addition of people who have only recently become eligible and therefore have had less opportunity to receive vaccination.
Table 5 gives vaccination coverage overall, further breaking down the catch-up cohort by age in years at the start of the programme
Table 5. Cumulative RSV vaccine uptake in older adults cohorts (routine and catch-up cohorts), measured at 31 May 2026, England
| Cohort group | Birth range of cohort | Age turned in September 2024 | Uptake (%) |
|---|---|---|---|
| Routine cohort | Adults turning 75 years old on or after 1 September 2024 | 75 | 50.2 |
| Catch-up cohort 1 | 1 September 1948 to 31 August 1949 | 75 | 69.4 |
| Catch-up cohort 2 | 1 September 1947 to 31 August 1948 | 76 | 70.2 |
| Catch-up cohort 3 | 1 September 1946 to 31 August 1947 | 77 | 71.3 |
| Catch-up cohort 4 | 1 September 1945 to 31 August 1946 | 78 | 71.2 |
| Catch-up cohort 5 | 1 September 1944 to 31 August 1945 | 79 | 70.1 |
| Total | 65.0 |
RSV vaccine uptake in the routine cohort, who continue to gain eligibility through the programme, remains lower compared to the catch-up cohorts, who were all eligible from the start of the programme (Figure 40).
Figure 40. Cumulative RSV vaccine uptake in older adult cohorts (routine and catch-up cohorts) in England, by month, using the population alive at the reporting date as the denominator, 31 May 2026
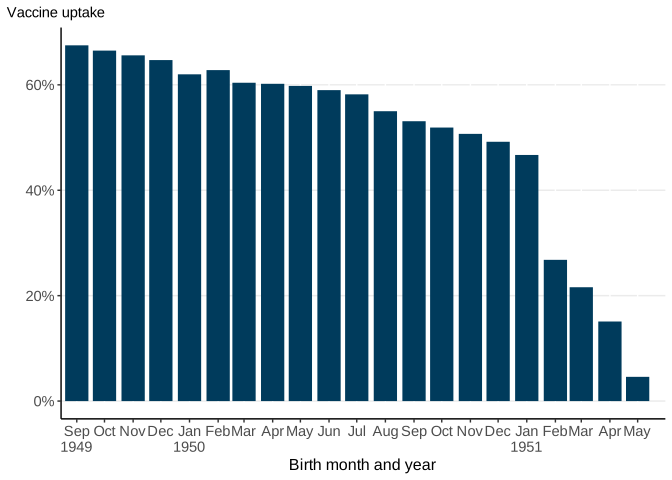
To illustrate the impact of additions of new people to the routine cohort on the routine cohort coverage estimates, figure 41 presents vaccine uptake by month of birth, demonstrating how uptake accumulates as individuals reach 75 years of age and become eligible for vaccination. Individuals born in September 1949, who became eligible at programme introduction in September 2024, have had the longest opportunity to receive an invitation and attend a vaccination appointment. Consequently, vaccine uptake is highest among these earlier eligible birth cohorts. In contrast, individuals who reached 75 years of age more recently, and therefore became eligible closer to the end of the reporting period (31 May 2026), have had less time to be invited and vaccinated, resulting in lower observed uptake.
Figure 41. RSV vaccine uptake among adults in the routine cohorts (individuals turning 75 years on or after 1 September 2024) by month of birth, measured on 31 May 2026, England
Vaccine uptake by region
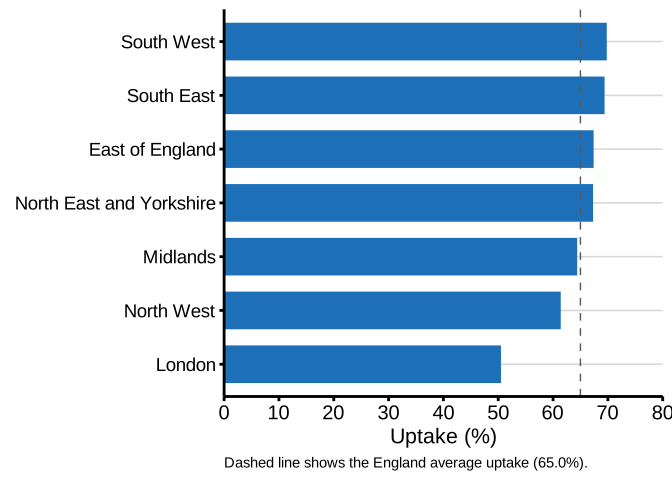
RSV vaccine uptake in the older adults showed a broadly similar trend across most regions in England, with London having a noticeably lower uptake than the rest of the country (Figure 42). By 31 May 2026, the region with the lowest RSV vaccine uptake was London (50.5%), while the region with the highest uptake was the South West (69.8%), representing a 19.3 percentage point difference across the regions. Uptake was below the England average in the London, North West and Midlands regions, with London recording the lowest uptake nationally.
Figure 42. Cumulative RSV vaccine uptake amongst all eligible older adults on 31 May 2026, by region, England
More information on the England uptake estimate is available in our quality and methodology information (QMI) report.
Scotland
From 1 August 2024, those who are turning 75 years old (by 31 July 2025) and those already aged 75 to 79 residing in Scotland were eligible for a free vaccine to protect them from RSV. Vaccination cohort sources are documented on each tab in the PHS Vaccination Surveillance Dashboard.
Amongst older adults (includes those turning 75 years of age and those who were aged 75 to 79 years between 1 August 2024 and 31 July 2025) 70.7% received an RSV vaccination during the 2024 to 2025 season.
In the 2024 to 2025 season (between 1 August 2024 and 31 July 2025), 70.0% of those turning 75 years of age received an RSV vaccination. In the 2025 to 2026 season (between 1 August 2025 and 31 July 2026), of those turning 75 years of age, 68.8% received an RSV vaccination.
Wales
Vaccination data for older adults is sourced from WIS. RSV vaccine uptake is calculated for adults living in Wales and resident there at the end of May 2026. More information on the methodology, as well as the latest uptake figures, can be found in the Immunisation surveillance reports published by Public Health Wales.
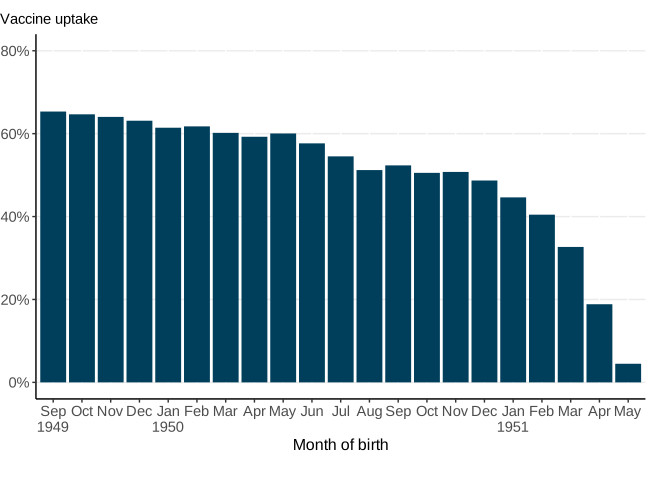
By the end of May 2026, 64.9% of all eligible older adults in Wales had received an RSV vaccination. Split by cohort, 50.4% of adults turning 75 since the start of the programme in September 2024 (the routine cohort) and 71.4% of adults already aged 75 to 79 years at the start of the programme (the catch-up cohort) in Wales had received an RSV vaccine. RSV vaccine uptake in the routine cohort, who continue to gain eligibility through the programme, was greatest in those who have been eligible for longer (Figure 44).
Figure 43. Cumulative RSV vaccine uptake in older adults catch-up cohorts, Wales
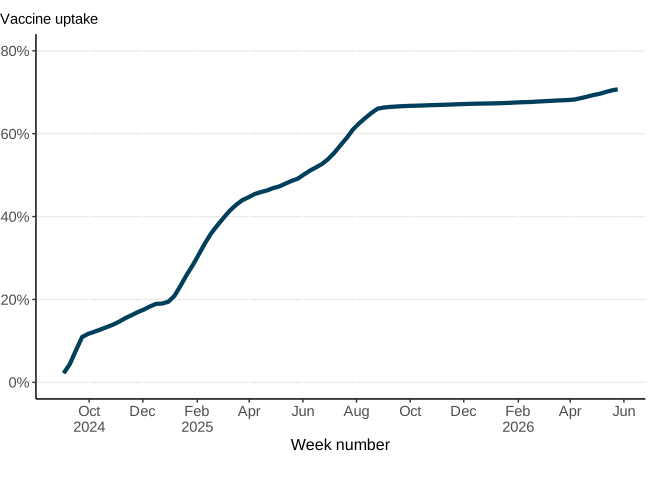
Figure 44. RSV vaccine uptake in older adults routine cohort by month of birth, Wales
Northern Ireland
Data on RSV vaccine uptake in older adults in Northern Ireland is not currently available but will be published on the Public Health Agency website.
Vaccine impact
England
The first analysis on the impact of the RSV vaccination programme in older adults in England was published in March 2025, using a Regression Discontinuity Design (RDD). A 30% reduction in RSV-associated hospitalisation in older adults eligible for the vaccine was found in comparison with those non-eligible, at a time when vaccine uptake was around 40%. An updated version of this analysis following the second RSV season following introduction of the RSV vaccination programme, with data collected up to 31 March 2026.
There was a discontinuity in hospitalisation rates, corresponding to a 43% reduction (95% CI 37% to 48%, p-value <0.001) in those aged 75 to 80 at the start of the programme (the catch-up cohort), and a 28% reduction (95% CI 13% to 41%, p-value <0.001) in those aged 74 at the start of the programme (the routine cohort) (Figure 45).
Figure 45. Observed, modelled, and predicted RSV-associated hospital admission rates by age, England
Vaccine effectiveness
Vaccine effectiveness analyses from the 2024 to 2025 RSV season have been published separately and provide additional context for interpretation of the findings presented in this report.
In older adults aged 75 to 79 years, a UK-wide meta-analysis of 4 national test-negative case-control studies estimated vaccine effectiveness against RSV-related hospitalisation to be:
- 74% (95% confidence interval [CI]: 68% to 80%) in England
- 77% (95% CI: 30% to 95%) in Northern Ireland
- 81% (95% CI: 60% to 91%) in Scotland
- 82% (95% CI: 42% to 94%) in Wales
The pooled vaccine effectiveness estimate across the 4 UK nations was 75% (95% CI: 69% to 80%).
A population-based study in Scotland estimated maternal RSVpreF vaccine effectiveness against RSV-associated lower respiratory tract infection (LRTI) hospitalisation in infants aged 90 days or younger to be 82% (95% CI: 75% to 87%) during the first season of programme implementation.
Data sources and methodology
For additional information regarding data sources please refer to the data quality report for national respiratory virus surveillance.
More details on the data and methods used for Scotland can be found in the Viral respiratory diseases (including influenza and COVID-19) in Scotland surveillance report.
More details on the data from Wales informing this report are available in the weekly report.
More information on the methods and caveats used for Northern Ireland can be found in the Respiratory surveillance report.
More information and contact details
Feedback and contact information
To provide feedback and for all queries relating to this document, please contact respdsr.enquiries@ukhsa.gov.uk
Acknowledgements
Compiled by the RSV surveillance team, Immunisation and Vaccine-Preventable Diseases division, UKHSA, with contributions from:
-
Public Health Scotland
-
Public Health Wales
-
Public Health Agency, Northern Ireland
-
Royal College of General Practitioners
-
Real-time Syndromic Surveillance team, UK Health Security Agency